Column Concept | Judet-Letournel Classification | Approach Selection
- Two-column concept - anterior and posterior columns converge at the sciatic buttress (the dense supra-acetabular bone joining the acetabulum to the sacroiliac joint) in an inverted Y
- 3 Judet views - AP, obturator oblique, iliac oblique
- Dome concept - the weight-bearing dome must be reduced: assessed by Matta roof arcs (45° or more on AP, obturator and iliac obliques) or the intact superior 10mm on CT
- Approach dictated by column - KL for posterior, IL/Stoppa for anterior
- Anatomic reduction (under 2mm step) = ~80-85% good/excellent outcomes (Matta)
- “Both-column = 'spur sign' on obturator oblique
- “Posterior wall = most common pattern
- “Sciatic nerve at risk in posterior approaches
- “Delay surgery 3-5 days to reduce blood loss
Overview and Epidemiology
Acetabular fractures account for 2-3% of all fractures, with an incidence of 3 per 100,000 per year (Laird and Keating); 70% follow motor vehicle accidents. They are complex injuries that demand a detailed anatomical understanding, and approach selection is tied directly to the fracture pattern.
Who. Young adults are injured by high energy, in motor vehicle accidents and falls from height. The elderly are injured by low-energy falls onto osteoporotic bone. Males predominate 3:1.
Mechanism. The classic injury is the dashboard: the knee strikes the dashboard and the force passes up the femur into the acetabulum. The position of the hip at impact determines the pattern, a flexed hip producing a posterior wall fracture, and the magnitude of the force determines the comminution. A direct blow to the trochanter produces a lateral compression injury.
Hip dislocation accompanies the fracture in a pattern-dependent way: near-universal in posterior wall fracture-dislocations, uncommon in isolated anterior patterns.
History. Judet and Letournel revolutionised acetabular surgery between the 1960s and 1980s. Before their work most acetabular fractures were treated non-operatively with poor results; their classification and surgical approaches remain the foundation today.
Anatomy and Biomechanics
The two columns. The acetabulum is supported by two columns of bone that converge above it at the sciatic buttress, the thick supra-acetabular bone that transmits load to the sacroiliac joint. The arrangement is an inverted Y whose stem is the buttress.
- Anterior column (the iliopubic segment): runs from the pubis to the anterior iliac crest via the pelvic brim, and comprises the anterior iliac crest and wing, the pelvic brim, the anterior wall and the superior pubic ramus
- Posterior column (the ischiopubic segment): dense bone running from the greater sciatic notch, through the posterior wall and quadrilateral surface, to the ischial tuberosity and inferior ramus, so from the ischium up through the greater and lesser sciatic notches
The weight-bearing dome. The superior articular surface carries the load and must be reduced. It is assessed by Matta's roof arcs, which should measure 45° or more on the AP, obturator oblique and iliac oblique views, or by the intact superior 10mm of subchondral bone on CT. Fractures that spare this zone may be treated conservatively.
Posterior neurovascular anatomy. The piriformis is the key landmark of the posterior approach. The sciatic nerve courses 1cm inferior to it, the superior gluteal artery emerges above it and the inferior gluteal artery below it.
Anterior neurovascular anatomy. The lateral femoral cutaneous nerve lies medial to the ASIS, and the femoral nerve and vessels lie in the iliac fossa. The external iliac vessels are at risk from medial retraction.
The corona mortis ("crown of death") is an aberrant obturator vessel, an anastomosis crossing the superior pubic ramus, present in 30-70% of patients. It must be identified and ligated during the Stoppa or ilioinguinal approach; uncontrolled bleeding from it can be catastrophic.
Classification Systems
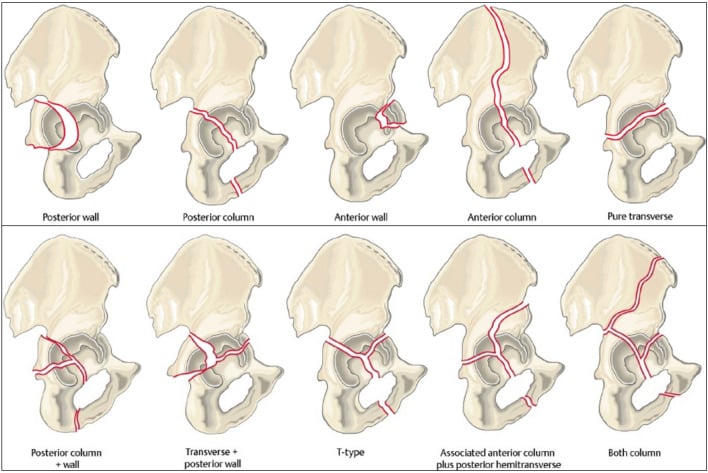
The Judet-Letournel classification is the gold standard. It has 10 patterns: five elementary, in which a single structure is broken, and five associated, in which the elementary patterns combine. The pattern names the fractured column, and the column dictates the approach.
- Frequency
- 25% (most common)
- Key Feature
- Fragment from posterior rim
- Approach
- Kocher-Langenbeck
- Frequency
- 4%
- Key Feature
- Through greater sciatic notch to obturator foramen
- Approach
- Kocher-Langenbeck
- Frequency
- 2% (rare)
- Key Feature
- Anterior rim fragment
- Approach
- Ilioinguinal/Stoppa
- Frequency
- 4%
- Key Feature
- Through pelvic brim
- Approach
- Ilioinguinal/Stoppa
- Frequency
- 8%
- Key Feature
- Divides acetabulum horizontally
- Approach
- Based on displacement
The posterior wall is the most common elementary pattern. The anterior wall fracture is rare and involves the pubic rami. The transverse fracture divides the acetabulum in half, and its approach is chosen by the displacement rather than by a column.
Clinical Assessment
History. Establish the mechanism (dashboard injury, fall from height, lateral blow) and the position of the hip at impact. Ask about head, chest, abdominal and pelvic injuries. Pre-injury function is critical for decision-making.
Examination. Look at the position of the limb: a posteriorly dislocated hip lies flexed, adducted and internally rotated. Palpate for tenderness over the greater trochanter. Movement is limited and painful. Then examine the sciatic nerve.
30% of posterior wall and posterior column fractures have a sciatic nerve injury. Examine and document both divisions before and after every reduction and every operation:
- Peroneal division (more commonly injured): ankle and toe dorsiflexion, foot eversion, sensation over the dorsum of the foot
- Tibial division: ankle and toe plantarflexion, sensation over the sole
Associated injuries. The dashboard mechanism puts the knee ligaments at risk as well, and the CT that classifies the fracture is also read for a femoral head fracture.
- Incidence
- Pattern-dependent (near-universal with posterior wall)
- Assessment
- Hip position, urgent reduction
- Incidence
- 30% (posterior)
- Assessment
- Motor/sensory exam
- Incidence
- 10%
- Assessment
- CT scan
- Incidence
- Dashboard mechanism
- Assessment
- Examine knee
- Incidence
- 10%
- Assessment
- Full femur X-ray
Differential diagnosis. The painful, loaded hip after trauma has several mimics.
- Discriminating Feature
- Disruption of iliopectineal/ilioischial line; dome involvement
- Confirming Test
- AP + Judet views, CT
- Discriminating Feature
- Concentric on post-reduction films, intact lines
- Confirming Test
- Post-reduction CT excludes fragment/wall fracture
- Discriminating Feature
- Fragment infero-medial to head, head incongruity
- Confirming Test
- CT - assess Pipkin type
- Discriminating Feature
- Disruption of Shenton line, shortening/ER of limb
- Confirming Test
- AP pelvis, CT if occult
- Discriminating Feature
- Pubic rami/SI joint disruption, not the dome
- Confirming Test
- Inlet/outlet views, CT
- Discriminating Feature
- Central protrusion of head, teardrop displaced
- Confirming Test
- Obturator oblique, CT
A concentric post-reduction radiograph does not exclude an acetabular fracture. An incarcerated osteochondral or wall fragment can sit in the joint despite an apparently reduced hip, so post-reduction CT is mandatory after every traumatic hip dislocation.
Investigations
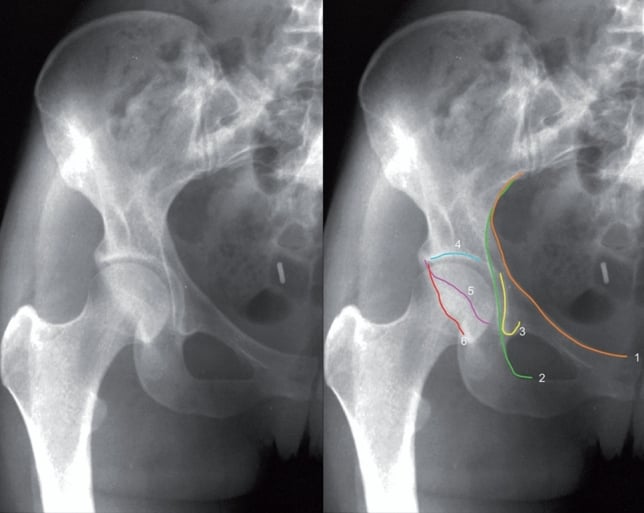
Radiographs. The first-line series is an AP pelvis and the two 45° Judet obliques. The AP shows both columns, the dome and the teardrop. The obturator oblique (45° toward the injured hip) profiles the anterior column and the posterior wall; the iliac oblique (45° away) profiles the posterior column and the anterior wall. All three are needed to classify the fracture.
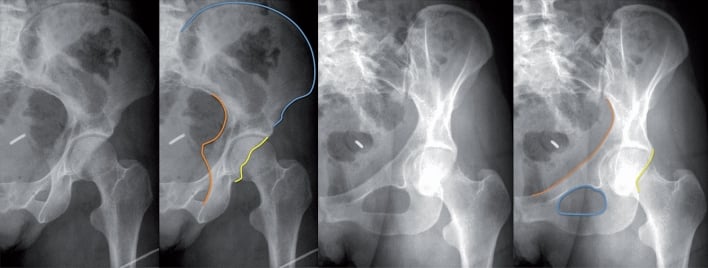
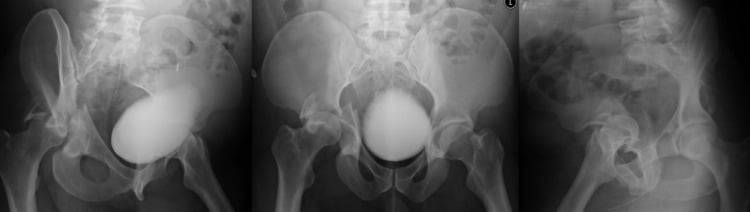
Trace all six on every AP pelvis.
- Iliopectineal line = anterior column; disruption means an anterior column fracture
- Ilioischial line = posterior column; disruption means a posterior column fracture
- Acetabular roof = the weight-bearing dome
- Anterior wall = the medial curve
- Posterior wall = the lateral curve
- Teardrop = the floor of the acetabular fossa: the medial wall and quadrilateral plate
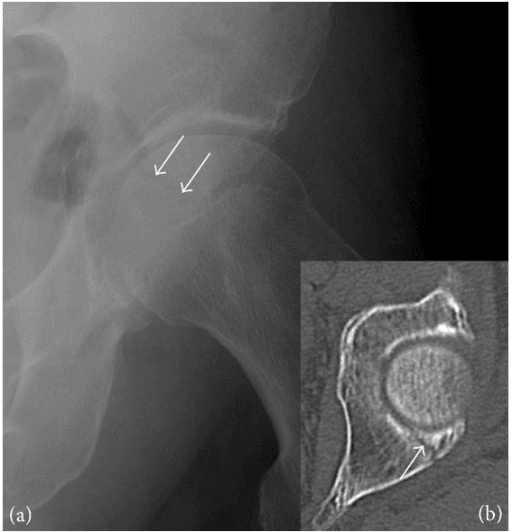
CT is mandatory for every acetabular fracture. It defines the fracture pattern, comminution, impaction and loose bodies, and is the basis of accurate classification and surgical planning. 3D reconstructions show the pattern clearly and are invaluable for planning; subtracting the femoral head gives a better view of the acetabulum.
MRI and CT angiography are for specific concerns. MRI shows labral injury and femoral head cartilage. CT angiography is for suspected vascular injury, which is rare.
Management Algorithm
The decision turns on the weight-bearing dome and the stability of the hip. Displacement at the dome, the roof arcs, congruence of the head within the acetabulum, and any incarcerated fragment or irreducible dislocation decide between traction and the operating theatre; the fractured column then decides the approach.
- Threshold
- Less than 2mm
- Rationale
- Acceptable articular congruity
- Threshold
- 45° or more
- Rationale
- Dome not involved in fracture
- Threshold
- Secondary congruence
- Rationale
- Head moves with medial fragment
- Threshold
- Below sourcil
- Rationale
- Non-weight bearing area
A low anterior column fracture that exits below the weight-bearing dome may be treated non-operatively if it is stable.
Protocol. Traction for 4-8 weeks, or touch-down weight bearing, with close radiographic follow-up.
Surgical Technique
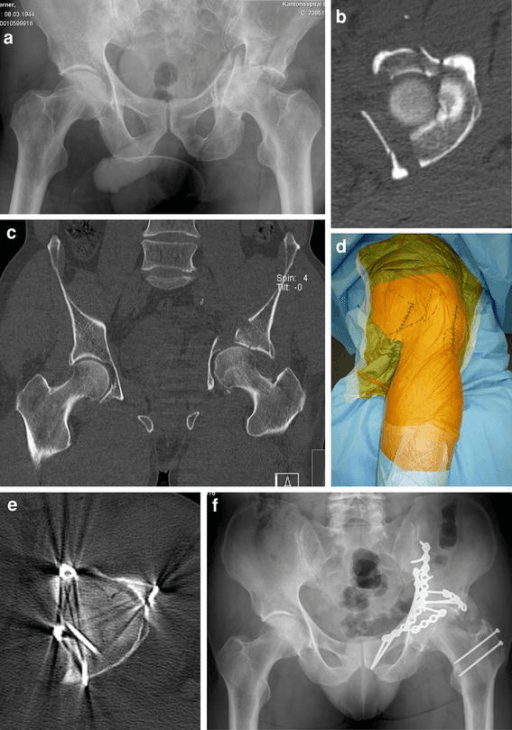
The posterior approach, for the posterior wall, the posterior column and the transverse fracture with posterior displacement. The sciatic nerve and the superior gluteal artery are the structures at risk.
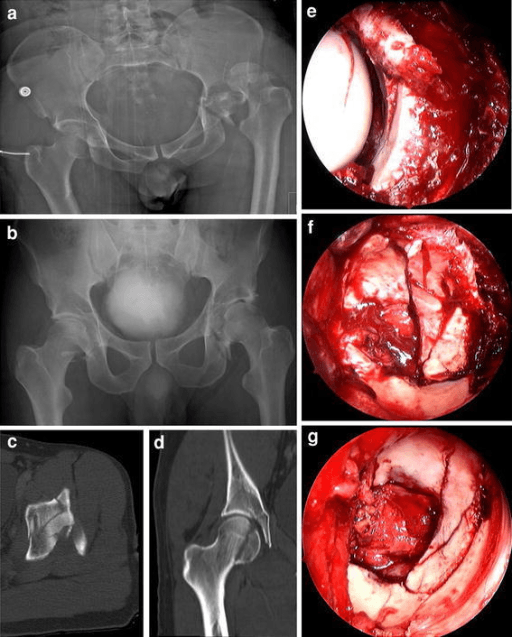
Surgical Steps
Lateral decubitus with the hip flexed 20-30°, or prone with bolsters. The knee is flexed to relax the sciatic nerve.
From the PSIS, curving over the greater trochanter and extending distally along the femoral shaft. The Gibson approach uses a straight incision.
Split gluteus maximus in line with its fibres. Identify and protect the sciatic nerve inferior to piriformis.
Detach piriformis, obturator internus and the gemelli from the greater trochanter, leaving quadratus femoris to protect the MFCA. A capsulotomy gives access to the joint.
Reduce the fragments under direct vision. A buttress (spring) plate holds the posterior wall; a reconstruction plate holds the column.
Knee flexion of at least 60° with the hip extended is the position that takes tension off the sciatic nerve; avoid hip flexion with the knee straight at any point in the case. The short external rotators, once divided, lie between the retractors and the nerve as a protective layer. Place retractors in the lesser notch carefully, never leave persistent traction on the nerve, and consider somatosensory monitoring for prolonged cases.
Marginal impaction. Anatomic reduction of the fracture lines does not guarantee a congruent joint if marginal impaction is missed. Osteochondral fragments at the articular margin, classically the posterior wall and the superior dome, are driven into the cancellous bone and rotated by the femoral head at the moment of injury, so they no longer line up with the joint surface even after the main wall or column fragment is reduced.
Why it matters. If the wall is simply reduced over an impacted segment, the head articulates against a step in the cartilage: residual incongruity, early cartilage wear and post-traumatic arthritis despite a "reduced" fracture. It is a major reason a radiographically anatomic reduction still fails.
Finding and fixing it. CT is essential, on the axial images and the reformats: look for impacted, malrotated subchondral fragments and a gap between the impacted piece and the subchondral bone. It is routinely under-appreciated on plain films. At operation, elevate the impacted osteochondral fragment back to the level of the head, bone-graft the subchondral defect left behind with cancellous autograft or allograft, and only then reduce and buttress the wall or column over it with a spring or buttress plate. The reconstructed wall holds the elevated articular surface out to length.
Complications
- Incidence
- 20-30%
- Risk Factors
- Malreduction, cartilage damage
- Management
- THA when mature
- Incidence
- 5-10%
- Risk Factors
- Dislocation duration, posterior injury
- Management
- Core decompression, THA
- Incidence
- 20-50%
- Risk Factors
- Posterior approach, head injury
- Management
- Prophylaxis (indomethacin or XRT)
- Incidence
- 10-15%
- Risk Factors
- Posterior approach, retraction
- Management
- Observation, most recover
- Incidence
- Variable
- Risk Factors
- Pelvic surgery, immobility
- Management
- Thromboprophylaxis
- Incidence
- 3-5%
- Risk Factors
- Open fracture, prolonged surgery
- Management
- Debridement, antibiotics
Heterotopic ossification. Brooker grade III-IV HO occurs in 20-50% of posterior approaches; head injury is the other risk factor. Prophylaxis is indomethacin 25mg three times daily for 6 weeks, started within 48 hours (the most common choice), or a single 800 cGy fraction of radiotherapy within 72 hours of surgery.
Quote the trial figures rather than a round "under 5%", because the two agents are not equal on point estimate even though the trial could not separate them. In 166 patients randomised after posterior or extensile approaches, Brooker grade III-IV HO occurred in 11% with indomethacin versus 4% with radiation, a difference that did not reach significance, so neither is proven superior and the choice rests on contraindications, tolerability and access rather than on efficacy. What the same trial settles beyond doubt is that prophylaxis is worth giving at all: all 16 untreated patients developed HO, 38% of them grade III-IV (Level I RCT).
Post-traumatic arthritis is the most significant long-term complication. Its risk factors:
- Articular step greater than 2mm
- Femoral head cartilage damage
- Delayed reduction of the dislocation
- Age at injury
Total hip arthroplasty after acetabular fracture is technically challenging, with higher complication rates, and is delayed at least 3-6 months for fracture healing. Joint registries record higher dislocation and revision rates than for primary osteoarthritis THA, and that signal reflects a genuinely more difficult operation.
Why it is hard. Malunion, non-union of a column, residual segmental or cavitary acetabular bone defects and an incongruent bed mean the cup often will not seat or achieve press-fit, requiring bone graft, augments, reinforcement rings or cages or a cup-cage construct, and sometimes a jumbo or multi-hole revision shell. Retained plates and screws obstruct reaming and may need partial removal, and intra-articular screws must be excluded. Heterotopic ossification from the index surgery limits exposure and motion and may need excision. Scarred planes and a previously injured or scarred sciatic nerve raise the risk of nerve injury and infection, and prior incisions constrain the approach.
Counselling and strategy. Dislocation, infection, aseptic loosening and revision are all more frequent than after primary THA, so counsel accordingly, consider a dual-mobility or constrained liner for the instability risk, and plan it as a revision-grade case. In the older, poor-prognosis hip this difficulty is the argument for acute fix-and-replace, which avoids operating through a malunited, hardware-laden, scarred bed.
Postoperative Care
Postoperative Protocol
DVT prophylaxis, mechanical and LMWH. Monitor sciatic nerve function, manage the drains and control pain.
Touch-down weight bearing (TDWB) with a frame or crutches. Physiotherapy for range of motion and strengthening.
Radiographs to assess healing. Continue TDWB. Remove sutures or staples.
Partial weight bearing if healing. Repeat radiographs and continue physiotherapy.
Full weight bearing once there is radiographic union. Return to activities. Monitor for HO and arthritis.
DVT prophylaxis continues for 4-6 weeks. HO prophylaxis is set out under Complications.
Outcomes and Prognosis
Reduction quality drives outcome. Matta tied the clinical result to the accuracy of reduction, and the proportion of good or excellent results falls as the residual step grows.
- Grade
- Excellent
- Good/Excellent Outcome
- 80-85%
- Grade
- Satisfactory
- Good/Excellent Outcome
- 65-75%
- Grade
- Poor
- Good/Excellent Outcome
- 40-50%
The 2mm rule has a measurement problem, and it changes how you verify your own result. In 67 surgically treated posterior wall fractures, plain radiographs graded 65 of 67 reductions as anatomic, yet postoperative 2D CT showed greater than 2mm offset in 11 hips and gaps of 2mm or more in 52. Plain films systematically underestimate residual displacement, so a postoperative radiograph that looks anatomic is weak evidence that it is. In the same series a residual gap of 10mm or more, or a total gap area of 35 square mm or more, predicted a worse result.
Two consequences follow. Auditing your own reductions on plain films alone will flatter them, and postoperative CT gives a more honest picture of both reduction and prognosis after posterior wall fixation. It also reframes the headline outcome figure: anatomic reduction achieved in a landmark series of 262 displaced fractures operated within 21 days was 71% of hips, falling with increasing fracture complexity, older age and delayed surgery, so "aim for under 2mm" is a target met in roughly seven of ten hips by an expert, not a routine expectation.
Long-term joint survival is worth quoting for counselling. With anatomic fixation, ten-year cumulative survivorship of the native hip was 82% in 61 hips followed a mean 12.4 years. The independent predictors of an unfavourable outcome were femoral chondral lesions, marginal impaction and longer operative duration; the first two are injury characteristics to look for deliberately at the time of surgery rather than surprises at follow-up.
Prognostic factors. The good prognostic factors are an anatomic reduction (under 2mm), a simple fracture pattern, a short dislocation time (under 6 hours), young age and an undamaged femoral head. The poor prognostic factors are articular comminution, femoral head impaction (the Gull sign), a posterior dislocation over 12 hours, age over 60 and the complex both-column pattern.
Matta's criteria for outcome assessment:
- Excellent: no pain, normal range of motion, no limp
- Good: mild pain with activity, slight limp
- Fair: moderate pain, limp, uses a cane
- Poor: severe pain, marked limp, disability
Controversies and Areas of Uncertainty
The geriatric fracture. There is no consensus on the best strategy for osteoporotic, dome-involving fractures in older patients. The options span non-operative care, ORIF (often with quadrilateral-plate buttressing) and acute fix-and-replace, ORIF plus same-sitting total hip arthroplasty. Registry and systematic-review data favour acute arthroplasty for poor-prognosis hips, but randomised evidence is still lacking.
HO prophylaxis, whether and which. The trial could not separate indomethacin from single-fraction radiotherapy on efficacy, and the absolute benefit of routine prophylaxis is debated given the NSAID risks (gastrointestinal, renal, a possible effect on bone healing) and the logistics and cost of radiotherapy. Many units now reserve prophylaxis for extensile or posterior approaches in high-risk patients.
Approach selection. The modified Stoppa, or anterior intrapelvic, approach has largely displaced the classical ilioinguinal in many centres for anterior and quadrilateral-plate access, but the extent of its advantage and the role of combined approaches for complex transverse and T-type patterns remain debated.
Posterior wall stability. The classic 40-50% fragment-size threshold for instability is imperfect. Examination under anaesthesia and CT-based fragment mapping are increasingly used because intermediate-size fragments (20-50%) have unpredictable stability and may still require fixation.
Guidelines, Registries & Global Practice
Global Epidemiology
- Bimodal incidence: high-energy injuries in young men (road traffic, falls from height) and a rising low-energy group in osteoporotic elderly
- Ageing shift: the fastest-growing cohort worldwide is patients over 60 with anterior-column and quadrilateral-plate involvement
- Male predominance overall (~3:1) but narrows with age
- Hip dislocation accompanies the posterior fracture-dislocation patterns almost by definition; isolated anterior-column patterns rarely dislocate
- High-resource: CT-based planning, dedicated pelvic-acetabular surgeons, fix-and-replace pathways
- Limited-resource: plain-film classification, traction-based non-operative care, delayed or no fixation
- Transfer to a specialist centre improves reduction quality and is recommended for displaced/complex patterns everywhere
Guidelines & Society Positions (Side by Side)
- Region
- Global / US
- Emphasis
- Two-column concept and Judet-Letournel as the operative framework; anatomic reduction of the weight-bearing dome; approach dictated by column
- Region
- UK
- Emphasis
- Network model - timely transfer of complex fractures to a specialist pelvic-acetabular unit; definitive surgery by a named specialist team
- Region
- Europe
- Emphasis
- Early CT, dedicated theatre lists, growing role of acute total hip arthroplasty in the elderly
- Region
- US
- Emphasis
- Reduction accuracy and articular congruity as the dominant outcome determinants; HO prophylaxis for extensile approaches
There is broad global consensus on the essentials: CT is mandatory for classification and planning; displaced fractures of the weight-bearing dome warrant anatomic operative reduction (under 2mm); approach is dictated by the fractured column; and complex patterns are best managed in specialist pelvic-acetabular units. The main area of practice variation is the management of the geriatric fracture - non-operative care, ORIF, or acute fix-and-replace.
Registry & Outcome Notes
- Joint registries (NJR UK, AJRR US, AOANJRR Australia, Swedish/Norwegian) track total hip arthroplasty performed after acetabular fracture as a distinct, higher-risk indication, with elevated dislocation and revision rates compared with primary osteoarthritis THA.
- This registry signal underpins the interest in acute fix-and-replace for poor-prognosis fractures in older patients, where revision rates appear lower than for delayed conversion.
High- vs Limited-Resource Practice Variation
- High-resource: routine 3D CT planning, intra-operative fluoroscopy/navigation, dedicated pelvic-acetabular surgeons, and ready access to acute arthroplasty.
- Limited-resource: greater reliance on skeletal traction and accepted non-operative management of borderline patterns, with fixation reserved for clearly unstable or dome-involving fractures; outcomes remain acceptable when secondary congruence is preserved.
MCQ Practice Points
Q: What is the most common elementary acetabular fracture pattern?
A: Posterior wall - accounts for approximately 25% of all acetabular fractures. Typically caused by dashboard injury with hip in flexed position.
Q: Which radiographic line represents the anterior column on AP pelvis?
A: Iliopectineal line - the ilioischial line represents the posterior column. Remember: "Pectineal = Anterior, Ischial = Posterior"
Q: What approach is used for posterior column fractures?
A: Kocher-Langenbeck - this posterior approach gives direct access to posterior column and wall. The ilioinguinal/Stoppa is used for anterior column.
Q: What is pathognomonic for a both-column acetabular fracture?
A: Spur sign - a fragment of intact ilium "floating" above the acetabulum visible on obturator oblique view. Indicates both columns separated from axial skeleton.
Q: What is the most important factor for good outcome in acetabular fractures?
A: Anatomic reduction (under 2mm) - Matta's studies showed 83% excellent/good outcomes with anatomic reduction vs 50% with poor reduction greater than 3mm.
Q: What is the corona mortis?
A: Aberrant obturator vessel crossing the superior pubic ramus. Present in 30-70% of patients. Must be ligated during ilioinguinal/Stoppa approaches to prevent catastrophic hemorrhage.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“28-year-old driver in MVA. X-ray shows posterior hip dislocation with posterior wall fracture. Sciatic nerve intact. How do you manage this?”
“45-year-old fell from roof. CT shows both-column acetabular fracture with spur sign visible. No dislocation. How do you approach this?”
“32-year-old motorcyclist with acetabular fracture. CT shows transverse pattern with associated posterior wall fragment. Which approach?”
“78-year-old woman, low-energy fall onto the side. CT shows a displaced anterior-column fracture with quadrilateral-plate comminution, marginal impaction and pre-existing hip osteoarthritis. How do you manage her?”
Classification
- 5 Elementary: PW, PC, AW, AC, Transverse
- 5 Associated: Both-column, T-type, Trans+PW, PC+PW, AC+PHT
- Posterior wall = most common (25%)
- Both column = spur sign pathognomonic
Radiographic Lines
- Iliopectineal = anterior column
- Ilioischial = posterior column
- Obturator oblique: anterior column + posterior wall
- Iliac oblique: posterior column + anterior wall
Approach Selection
- Kocher-Langenbeck: Posterior wall/column
- Ilioinguinal/Stoppa: Anterior wall/column
- Extended iliofemoral: Both column (rare)
- Sciatic nerve at risk in KL approach
Key Numbers
- Under 2mm step = acceptable reduction
- Greater than 40% wall = needs fixation
- 3-5 days delay = less blood loss
- ~80-85% good outcome with anatomic reduction (Matta)
Complications
- HO: 20-50% (indomethacin prophylaxis)
- Sciatic nerve: 10-15%
- Post-traumatic arthritis: 20-30%
- Corona mortis: ligate in anterior approaches
Evidence Base
Accuracy of Reduction Drives Outcome (Landmark Series)
- 262 displaced acetabular fractures (255 hips, mean 6-year follow-up) treated by open reduction and internal fixation within 21 days. Anatomic reduction was achieved in 71% of hips and the rate fell with increasing fracture complexity, older age and delayed surgery. Overall clinical result was excellent in 40%, good in 36%, fair in 8% and poor in 16% - clinical outcome tracked closely with radiographic reduction. Both-column fractures were the most common pattern (35%).
Postoperative CT Predicts Posterior Wall Outcome
- 67 surgically treated posterior wall fractures assessed with postoperative 2D CT. Plain films graded 65 of 67 reductions as anatomic, yet CT revealed greater than 2mm offset in 11 hips and gaps of 2mm or more in 52. A residual gap of 10mm or more, or total gap area of 35mm2 or more, was associated with a poor result. CT-assessed reduction was highly predictive of clinical outcome.
HO Prophylaxis: Indomethacin vs Radiation (RCT)
- Prospective randomised trial of 166 patients operated through posterior or extensile approaches. Brooker grade III-IV heterotopic ossification occurred in 11% of the indomethacin group (25mg three times daily for 6 weeks) versus 4% of the radiation group (800 cGy within 72h) - no significant difference. All 16 untreated patients developed HO (38% grade III-IV).
Long-Term Joint Survival After Fixation
- 61 hips treated with open reduction and internal fixation via surgical hip dislocation (mean follow-up 12.4 years). Ten-year cumulative survivorship was 82%. Independent predictors of an unfavourable outcome were femoral chondral lesions, marginal impaction, longer operative duration and older patient age.
Acute vs Delayed THA (Systematic Review)
- Systematic review and meta-analysis of 5 studies (255 patients) comparing acute 'fix-and-replace' total hip arthroplasty with delayed THA after initial fixation. Functional outcomes, complications and mortality were comparable, but delayed THA had a significantly higher revision rate (17.1% vs 4.3%, p=0.002).
Geriatric Fix-and-Replace vs ORIF
- Retrospective comparison of 17 fix-and-replace versus 11 ORIF-alone patients aged 55 and over. Acute outcomes (length of stay, disposition, 90-day readmission, time to mobilisation and HOOS Jr. scores) did not differ, but more fix-and-replace patients were permitted earlier weight-bearing (70% vs 9%).
Judet-Letournel Classification & Surgical Approaches
- Foundational text defining the two-column concept, the 10-pattern classification (5 elementary, 5 associated) and the standard surgical approaches (Kocher-Langenbeck, ilioinguinal, extended iliofemoral). Established that operative reduction of displaced fractures yields markedly better results than non-operative treatment.