Surgical Emergency | Clinical Diagnosis | Fasciotomy Within 6 Hours | Irreversible After 8 Hours
- Clinical diagnosis - do not wait for pressure measurement if clinical suspicion high
- Pain out of proportion and pain on passive stretch are the earliest signs - out of proportion the most sensitive, passive stretch the most specific
- Delta P (diastolic BP minus compartment pressure) under 30mmHg SUSTAINED FOR MORE THAN 2 HOURS is the threshold for fasciotomy - an absolute pressure over 30mmHg alone is NOT, and neither is a single transient dip in delta P
- Fasciotomy within 6 hours gives best outcomes - after 8 hours damage is irreversible
- All compartments must be released - leg has 4, forearm has 3, thigh has 3
- “Tibial fractures are the most common cause (36% of all ACS)
- “Absence of pulse does NOT rule out ACS - ACS occurs at pressures below arterial occlusion
- “Deep posterior compartment (leg) is most commonly missed
- “Volkmann's contracture is the end result of untreated forearm ACS
Overview and Epidemiology
What it is. Acute compartment syndrome (ACS) is a surgical emergency in which raised pressure within a closed osseofascial compartment compromises local blood flow (capillary perfusion pressure approximately 25mmHg) and the muscle and nerve inside become ischaemic. Without timely fasciotomy the damage becomes irreversible after 6-8 hours of ischaemia.
Causes. Anything that adds volume to a compartment or shrinks the space around it:
- Fractures (75% of cases) - the tibial shaft is the most common, 36% of all ACS
- Soft-tissue injury without fracture
- Arterial injury with ischaemia-reperfusion
- Burns, especially circumferential
- Crush injury - direct trauma to muscle
- Tight casts and dressings - external compression
- Extravasation of intravenous fluids
- Prolonged limb compression, as in the drug-overdose position
Who to watch. The scenarios in which the syndrome is most likely, and most likely to be missed:
- Tibial shaft fractures, especially high-energy
- Forearm fractures in children (supracondylar)
- Vascular injury with delayed reperfusion
- Polytrauma, especially the obtunded patient
- The anticoagulated patient, in whom a compartment haematoma is enough
Anatomy - Compartments by Region
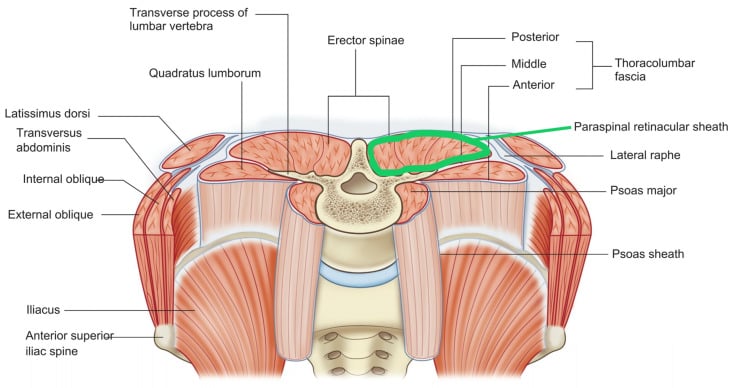
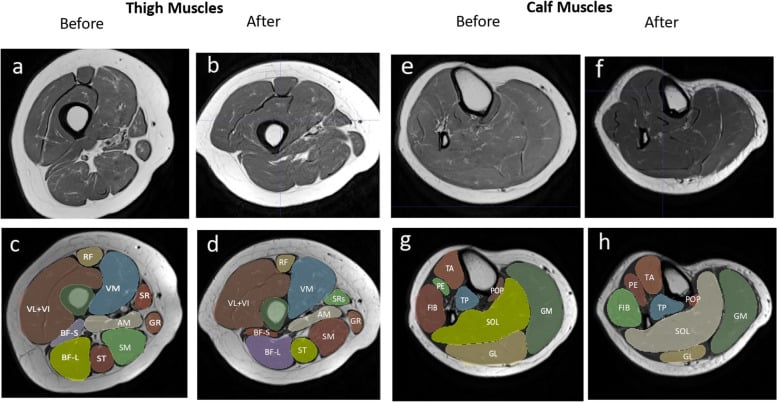
A missed compartment means an incomplete decompression and a persistent compartment syndrome, so the compartments of each region have to be known cold. The leg has 4, the forearm 3 and the thigh 3, and the one most commonly missed is the deep posterior compartment of the leg.
- Contents
- Tibialis anterior, EHL, EDL, peroneus tertius
- At-Risk Nerve
- Deep peroneal nerve
- Fasciotomy Access
- Anterolateral incision
- Contents
- Peroneus longus, peroneus brevis
- At-Risk Nerve
- Superficial peroneal nerve
- Fasciotomy Access
- Anterolateral incision
- Contents
- Gastrocnemius, soleus, plantaris
- At-Risk Nerve
- Sural nerve
- Fasciotomy Access
- Posteromedial incision
- Contents
- Tibialis posterior, FHL, FDL, popliteus
- At-Risk Nerve
- Tibial nerve, posterior tibial vessels
- Fasciotomy Access
- Posteromedial incision - MOST MISSED
Why the deep posterior compartment is missed. It lies beneath the deep transverse intermuscular septum, which separates it from the superficial posterior compartment. It must be identified and released specifically; failing to do so is the most common cause of an incomplete fasciotomy.
Pathophysiology
The cycle. Whatever starts it, the sequence is the same: volume rises inside a space that cannot stretch, pressure follows, and the smallest vessels are the first to close.
Fracture, crush, vascular injury or reperfusion leads to bleeding and oedema within the closed compartment.
Increased compartment volume within non-compliant fascia raises the pressure. Capillary perfusion pressure is approximately 25-30mmHg.
Capillaries and venules collapse. Arterial inflow continues briefly, worsening the oedema. Ischaemia begins.
Muscle and nerve ischaemia, reversible if decompressed. Pain on passive stretch occurs.
Muscle necrosis begins. Nerve injury (neuropraxia initially, axonotmesis later). Myoglobin release.
Significant muscle death. Volkmann's contracture develops. Renal failure risk from myoglobinuria.
Why the pulses stay. ACS is a microvascular problem, not an arterial occlusion. Compartment pressure exceeds capillary perfusion pressure but stays below systolic arterial pressure, typically over 90mmHg, so the arteries remain patent and the pulses are present until very late. Never rule out ACS because a pulse is palpable.
Why delta P, not absolute pressure. The compartment does not care what its pressure is in absolute terms; it cares whether blood can still be driven into it. Perfusion depends on the difference between the diastolic blood pressure and the compartment pressure, which is why the same 35mmHg reading is harmless in a normotensive patient and limb-threatening in a shocked one. The reference values:
- Normal compartment pressure: under 10mmHg
- Delta P (diastolic BP minus compartment pressure) under 30mmHg sustained for more than 2 hours indicates ischaemia and is the threshold for decompression
- An absolute pressure over 30mmHg is common after a tibial fracture and is not by itself an indication for fasciotomy
The duration is part of the threshold, not an optional refinement. A single transient dip below 30 is common after a tibial fracture and frequently self-corrects, and treating it as the diagnosis is what over-operates.
Classification Systems
Compartment syndrome is classified by the timing of its onset, by the mechanism that raised the pressure (Matsen), and by the severity it has reached. Classification by location is the anatomy above.
- Onset
- Minutes to hours
- Features
- Surgical emergency, follows trauma or ischaemia-reperfusion
- Management
- Emergent fasciotomy
- Onset
- During exercise
- Features
- Reversible with rest, typically in athletes
- Management
- Conservative or elective fasciotomy
- Onset
- Hours post-release
- Features
- Systemic effects dominant, reperfusion injury
- Management
- Fasciotomy plus resuscitation
By mechanism (Matsen). Matsen divides the causes into increased content (bleeding, oedema, intravenous extravasation) and decreased compartment size (tight casts, closure of fascial defects, MAST trousers). Both roads lead to the same raised compartment pressure.
A distinct entity examiners use to test that you will not confuse it with the acute emergency. Chronic exertional compartment syndrome (CECS) is a reversible, exercise-induced rise in compartment pressure causing pain - it is not a surgical emergency and is managed completely differently from acute ACS.
- Who: young athletes (especially runners) and military recruits; usually bilateral; the anterior compartment of the leg is most common (then deep posterior).
- Presentation: cramping, aching or tightness (sometimes paraesthesia or foot-drop sensation) that begins at a reproducible point during exertion, worsens if exercise continues, and resolves within minutes of stopping - the opposite of the unrelenting pain of acute ACS.
- Diagnosis: clinical history plus dynamic intracompartmental pressure measurement before and after provocative exercise. The modified Pedowitz criteria support the diagnosis: resting pressure at least 15 mmHg, 1-minute post-exercise at least 30 mmHg, or 5-minute post-exercise at least 20 mmHg. MRI and near-infrared spectroscopy are adjuncts.
- Differential: medial tibial stress syndrome, tibial stress fracture, popliteal artery entrapment syndrome (exclude with dynamic vascular studies), and nerve entrapment.
- Treatment: first activity modification/relative rest (gait retraining to a forefoot strike helps anterior CECS); refractory cases have an elective fasciotomy or fasciectomy (planned, not emergent) - anterior-compartment release has the best return-to-sport results.
Clinical Presentation and Assessment
A clinical diagnosis. ACS is diagnosed at the bedside, and when clinical suspicion is high fasciotomy is not delayed for a pressure measurement. A single normal pressure does not exclude it, and at-risk patients need serial reassessment rather than one examination.
History. The mechanism of injury and the time since it, which is critical for prognosis. Then the pain: is it out of proportion to the injury, and are the analgesia requirements rising? Ask about numbness or weakness developing.
The 6 P's, in order of appearance. Pain out of proportion is the most sensitive early sign and pain on passive stretch the most specific; a tense compartment is early but subjective. Everything after that is a sign of progression or of damage already done.
- Timing
- EARLY
- Mechanism
- Muscle ischaemia
- Reliability
- Most sensitive early sign
- Timing
- EARLY
- Mechanism
- Muscle ischaemia
- Reliability
- Most specific early sign
- Timing
- EARLY
- Mechanism
- Increased volume
- Reliability
- Variable - subjective
- Timing
- INTERMEDIATE
- Mechanism
- Nerve ischaemia
- Reliability
- Indicates progression
- Timing
- LATE
- Mechanism
- Muscle necrosis
- Reliability
- Poor prognosis if present
- Timing
- VERY LATE
- Mechanism
- Complete vascular compromise
- Reliability
- Do not wait for these
Passive stretch, compartment by compartment. Stretch the muscles that live in the compartment you suspect:
- Anterior leg - pain on passive plantar flexion of the toes or ankle
- Deep posterior leg - pain on passive dorsiflexion of the toes
- Volar forearm - pain on passive extension of the fingers
- Dorsal forearm - pain on passive flexion of the fingers
The patient who cannot tell you. In the unconscious, intubated or heavily sedated patient the pain assessment is gone, and these patients are at the highest risk of a missed ACS. Keep a very low threshold for pressure measurement and for fasciotomy. The same applies wherever the examination is unreliable:
- Polytrauma patients, often sedated and ventilated
- Regional anaesthesia, which masks the pain
- Paediatric patients, who cannot articulate it
- Drug intoxication
- Neurological injury
- Distinguishing Features
- Pain out of proportion, pain on passive stretch, tense compartment, pulses usually present
- Key Test
- Delta P under 30mmHg / clinical
- Pitfall
- Waiting for pulselessness or pallor
- Distinguishing Features
- Cold, pulseless, pale limb; pain at rest; classic 6 P's of ischaemia
- Key Test
- Doppler / CT angiography; ABPI
- Pitfall
- ACS can co-exist after reperfusion - both may be present
- Distinguishing Features
- Diffuse swelling, warmth, less pain on passive stretch, no tense fascial compartment
- Key Test
- Duplex ultrasound
- Pitfall
- Calf swelling attributed to DVT delays ACS diagnosis
- Distinguishing Features
- Erythema, fever, systemic sepsis; crepitus and disproportionate pain in necrotising infection
- Key Test
- Bloods, LRINEC, surgical exploration
- Pitfall
- Necrotising fasciitis also a surgical emergency - do not miss
- Distinguishing Features
- Pain proportionate to injury, settles with analgesia and splintage, compartments soft
- Key Test
- Serial clinical review
- Pitfall
- Rising analgesia requirement should prompt ACS reassessment
- Distinguishing Features
- Sensory/motor deficit in a single nerve territory, no compartment tension
- Key Test
- Clinical mapping; nerve studies (late)
- Pitfall
- Isolated paraesthesia attributed to nerve injury masks early ACS
A frequently-examined paediatric pearl: the classic 6 P's are unreliable in children, so a different set of warning signs is used. A young or frightened child cannot describe "pain out of proportion" or cooperate with passive-stretch testing, and pain becomes a late, insensitive sign - so waiting for the adult signs causes dangerous delay.
The earliest and most reliable indicators of compartment syndrome in a child are the three A's:
- increasing Analgesia requirement (escalating or unusually high analgesic demand after a fracture),
- Anxiety, and
- Agitation.
A child needing escalating opioid analgesia after an injury has compartment syndrome until proven otherwise.
- Highest-risk paediatric injuries: supracondylar humerus fractures (forearm volar compartment, the classic route to Volkmann's contracture), both-bone forearm fractures, the floating elbow, and tibial fractures. A pink, pulseless hand after a supracondylar fracture demands urgent assessment.
- Management principle: maintain a very low threshold, measure compartment pressures (delta P) when the examination is unreliable, and decompress. Children have greater regenerative capacity, so even a relatively late fasciotomy is often worthwhile - but the priority is early recognition through the three A's.
Investigations and Pressure Measurement
When to measure. In an awake, examinable patient a convincing clinical diagnosis overrides any number. Measurement earns its place where the examination cannot be trusted: McQueen and Duckworth's review (PMID 26814506) puts the sensitivity of clinical findings at only 13 to 64 per cent, against 94 per cent for continuous pressure monitoring at the sustained threshold, with a specificity of 98 per cent for monitoring against 63 to 98 per cent for clinical signs. That is the argument for monitoring the obtunded, intubated, regionally blocked or paediatric patient, not for replacing clinical judgement in the awake one.
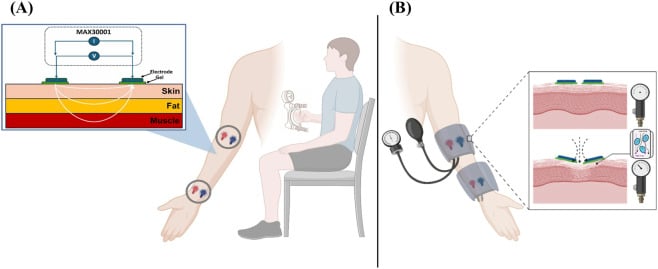
The Stryker STIC device is the one most commonly used in practice. The highest pressure is usually within 5cm of the fracture, so that is where to measure; measure all the compartments, and repeat the readings in borderline cases.
- Sterilise the skin
- Insert the needle into the compartment at 90 degrees
- Inject a small amount of saline
- Read the pressure on the digital display
- Measure at multiple points, within 5cm of the fracture site
An arterial line transducer is more accurate but less practical: a standard arterial line configuration zeroed at the level of the compartment, an 18G needle into the compartment, flushed with saline and read. Whitesides' technique, the original method, used a mercury manometer with intravenous tubing and saline; it is more cumbersome and less accurate than modern methods and is now mainly of historical interest.
- Threshold
- Over 30mmHg
- Notes
- Traditional threshold - SUPERSEDED, not an indication alone
- Threshold
- Under 30mmHg SUSTAINED over 2 hours
- Notes
- More reliable in hypotension
- Threshold
- Under 40mmHg
- Notes
- Alternative measure
Where the threshold comes from. McQueen and Court-Brown monitored the anterior compartment continuously for 24 hours in 116 tibial diaphyseal fractures (PMID 8898137). In the first 12 hours alone 53 patients exceeded an absolute 30mmHg and 30 exceeded 40mmHg, yet only 3 patients (2.6%) developed true acute compartment syndrome, and none of the 116 had any sequelae at six-month review. Decompressing on an absolute threshold of 30mmHg would have sent 50 patients (43%) to an unnecessary fasciotomy, and even a 40mmHg threshold would have sent 23%; a delta P of 30mmHg missed no cases.
The error runs in both directions. Treating a high absolute pressure as an automatic indication over-operates on a scale of roughly 4 in 10 monitored tibial fractures, and a fasciotomy is not a benign investigation but a wound that needs closure or grafting. Waiting for an absolute number to look alarming in a hypotensive trauma patient under-calls the genuine emergency: a patient with a diastolic pressure of 50mmHg and a compartment pressure of 25mmHg has a delta P of 25, and this indicates ACS even though the absolute reading is under 30. Quote delta P as the threshold and the absolute reading only as a component of it. The study's own limits apply: single centre, anterior compartment only, and continuous monitoring equipment that is not universally available.
McQueen and Duckworth recommend, in their own words, that "decompression is carried out primarily on the basis of the differential pressure being less than 30 mmHg for more than 2 h". Quoting "delta P under 30" alone converts a sustained trend into a single reading, and a single reading is exactly what over-operates: the monitoring study above recorded transient excursions above 30mmHg in 53 of its 116 fractures while only 3 developed the syndrome.
Other investigations.
- Bloods - CK (elevated with muscle damage), renal function, coagulation
- Urine - myoglobinuria (dark urine)
- No role for imaging in the acute diagnosis; do not delay for CT or MRI
Management
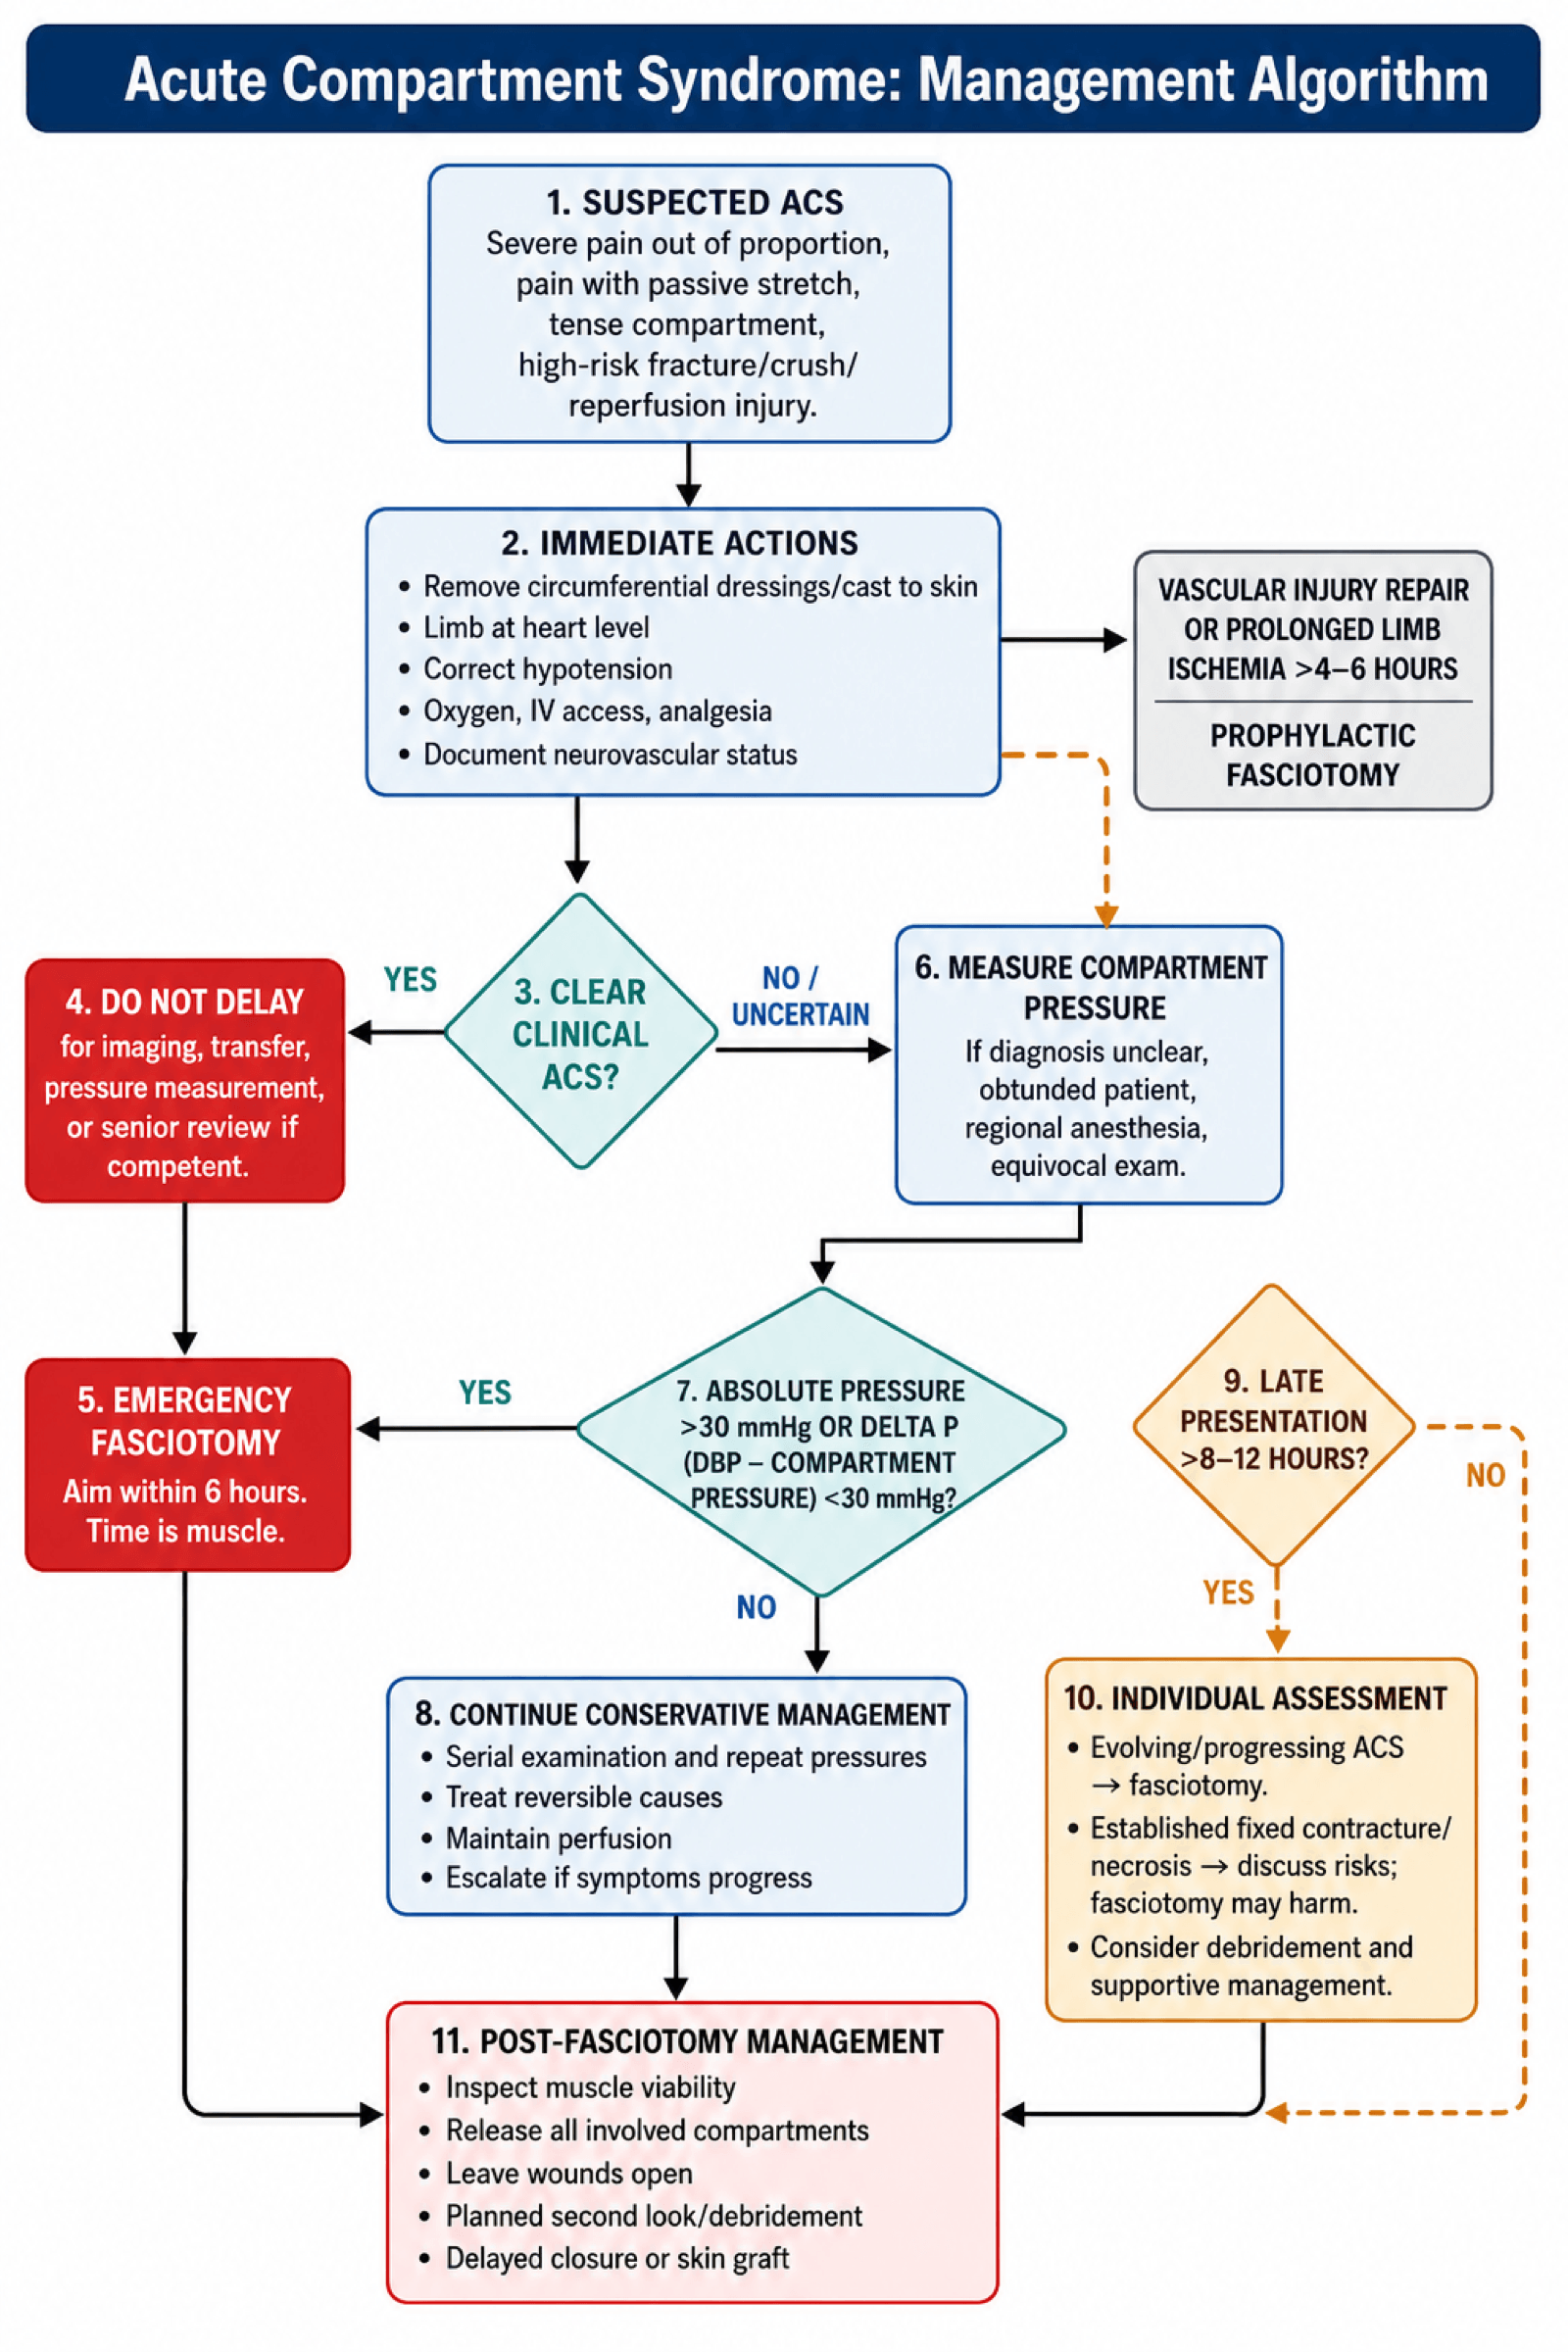
- Pressure Reading
- Not measured / unavailable
- Action
- Immediate fasciotomy
- Timing
- Do not delay for measurement
- Pressure Reading
- ΔP under 30 sustained over 2h (not absolute pressure, not a single reading)
- Action
- Fasciotomy
- Timing
- Within 1 hour
- Pressure Reading
- Borderline (25-30mmHg)
- Action
- Serial monitoring
- Timing
- Repeat every 1-2 hours
- Pressure Reading
- Any elevation
- Action
- Low threshold for fasciotomy
- Timing
- Cannot rely on clinical exam
- Pressure Reading
- Elevated
- Action
- Consider risks of late fasciotomy
- Timing
- Discuss with patient/family
While theatre is being arranged. In preparation for fasciotomy:
- Remove all circumferential dressings - split casts to skin
- Position the limb at heart level - elevation reduces arterial inflow
- Correct hypotension - it improves perfusion pressure
- Supplemental oxygen
- IV access, in preparation for surgery
- Analgesia, without masking the evolving symptoms
- Document neurovascular status before and after every intervention
Splitting the cast. Split it completely to skin, including the padding: studies show that splitting cast and padding together decreases compartment pressure by 30-65%, and bivalving alone is insufficient.
Surgical Technique - Fasciotomy
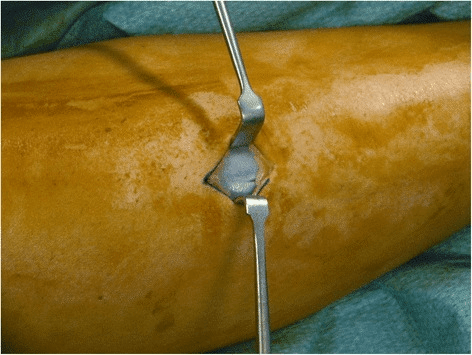
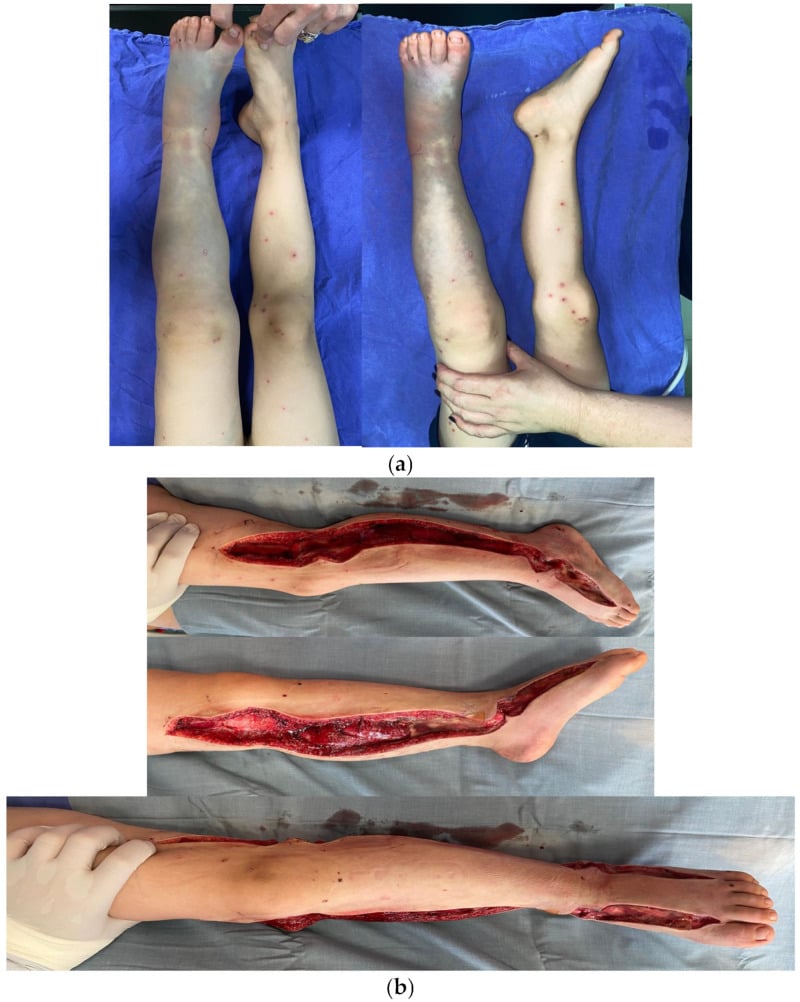
The two-incision technique is the gold standard for the leg: an anterolateral incision for the anterior and lateral compartments, a posteromedial incision for the superficial and deep posterior compartments. The patient is supine with the leg slightly externally rotated.
Anterolateral incision. Longitudinal, from the fibular head to the lateral malleolus, 2cm anterior to the fibula, and essentially the whole length of the leg, 15-20cm at a minimum:
- Incise skin and subcutaneous tissue
- Identify the fascia of the anterior compartment
- Release the anterior compartment along its full length
- Identify the intermuscular septum
- Release the lateral compartment posterior to the septum
The superficial peroneal nerve pierces the fascia approximately 10-12cm proximal to the lateral malleolus. Identify and protect it during the lateral compartment release.
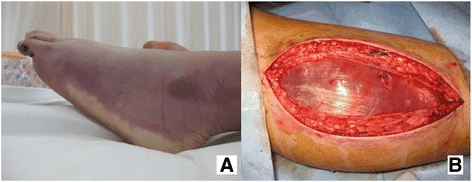
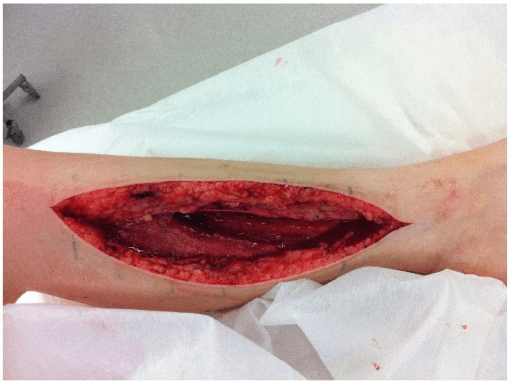
Posteromedial incision. Longitudinal, 2cm posterior to the medial tibial border, matching the anterolateral incision in length, keeping the saphenous vein and nerve safe anteriorly:
- Incise skin and subcutaneous tissue
- Release the fascia of the superficial posterior compartment
- Identify and divide the deep transverse intermuscular septum
- Release the deep posterior compartment - the step that is missed
- Detach soleus from the tibia if needed for access
Complications
- Cause
- Delayed diagnosis, missed compartment
- Prevention/Management
- High index of suspicion, release all compartments
- Cause
- Untreated forearm ACS
- Prevention/Management
- Timely fasciotomy; reconstruction if established
- Cause
- Rhabdomyolysis
- Prevention/Management
- Aggressive IV fluids, monitor CK/urine
- Cause
- Direct injury or ischaemic
- Prevention/Management
- Careful technique; neuropraxia may recover
- Cause
- Muscle necrosis, scarring
- Prevention/Management
- Physiotherapy, pain management
- Cause
- Large open wound
- Prevention/Management
- VAC therapy, staged closure, skin graft
- Cause
- Muscle necrosis
- Prevention/Management
- Physiotherapy; tendon transfers if needed
- Cause
- Established necrosis, sepsis
- Prevention/Management
- Rare - occurs with massive tissue loss
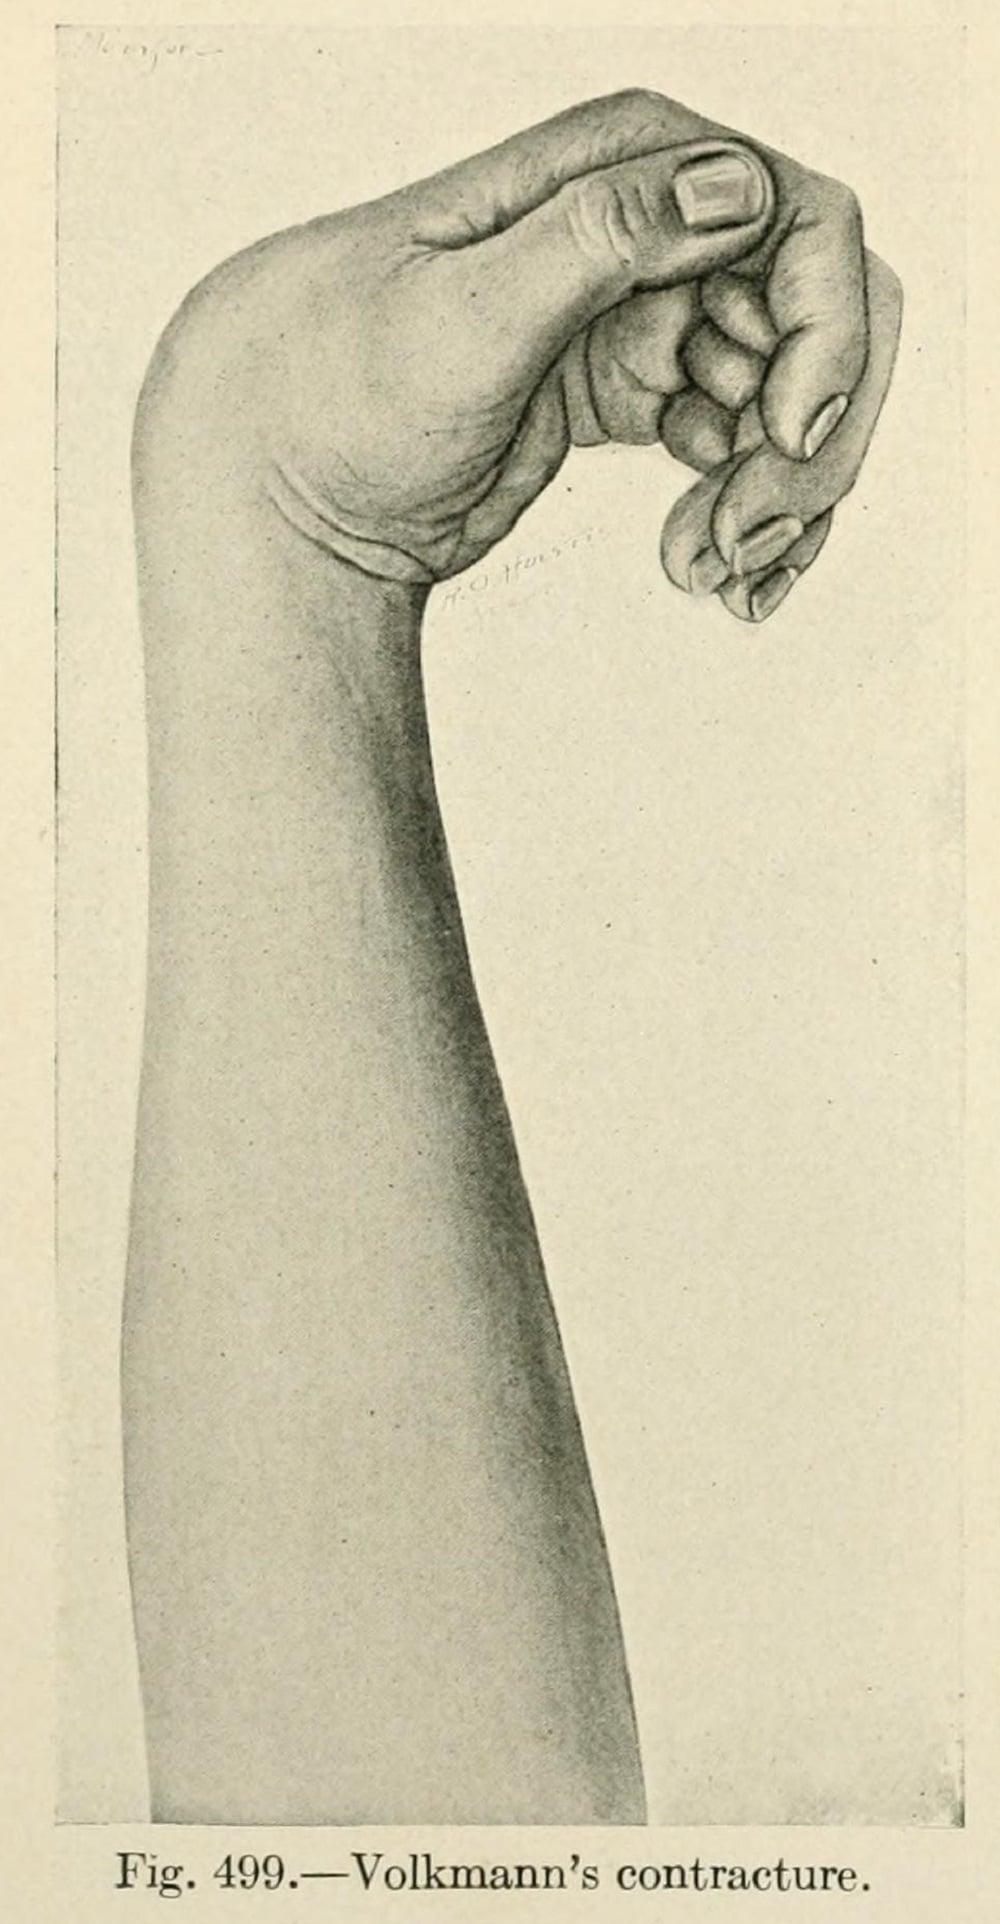
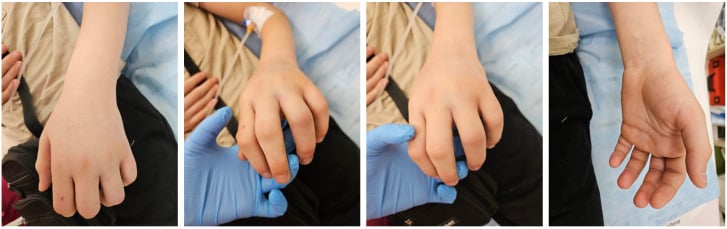
Volkmann's ischaemic contracture is the end result of untreated volar forearm ACS: the ischaemic muscle necroses, fibroses and contracts, and the hand is left in the classic claw-hand posture of flexed wrist, extended MCP joints and flexed IP joints. The fingers extend as the wrist is flexed, the cascade sign. Treatment is reconstruction: muscle slide, tendon lengthening or free muscle transfer.
Rhabdomyolysis releases myoglobin, turns the urine dark, and can lead to acute kidney injury. Manage it with aggressive intravenous fluids to a urine output over 1ml/kg/hr, alkalinise the urine with sodium bicarbonate, and monitor renal function and electrolytes for the risk of hyperkalaemia.
Postoperative Care
- Moist dressings to the fasciotomy wounds
- Splint the limb in a functional position
- Elevate, but not above the heart, to balance perfusion
- Monitor neurovascular status
- IV fluids for renal protection
- Monitor CK, renal function and urine output
- Return to theatre for wound inspection and debridement of any necrotic tissue
- Close, apply VAC/NPWT, or plan a skin graft, as described under Wound Management
- Serial debridements if necrosis is ongoing
- Staged closure or skin grafting
- Physiotherapy begins once the wound is stable
- Active and passive range of motion
- Strengthening as tolerated
- Tendon surgery may be needed for contractures
- Assess for permanent deficits
What to monitor. CK, which peaks at 24-72 hours; urine output and colour; renal function (creatinine); potassium, because cell lysis causes hyperkalaemia; and the wound.
Outcomes and Prognosis
What decides the outcome. Time to fasciotomy is the most important factor, then the completeness of the fasciotomy, the severity of the underlying injury, and the patient's age and comorbidities.
- Expected Outcome
- Good recovery expected
- Expected Outcome
- Variable - some permanent deficits
- Expected Outcome
- Likely permanent deficits
- Expected Outcome
- 90% have permanent deficits
Medicolegal. Missed or delayed compartment syndrome is a common cause of medical litigation in orthopaedics, and delay is the most common cause of it. Documentation of serial clinical assessments, pressure measurements and the timing of intervention is essential, and early involvement of senior colleagues is prudent.
Guidelines, Registries & Global Practice
Global epidemiology:
- Figure
- ~11.5% (160 of 1,388)
- Source
- McQueen et al 2015, J Orthop Trauma (PMID 25882967)
- Figure
- 69%; ~half tibial shaft (≈36% of all ACS)
- Source
- McQueen, Gaston, Court-Brown 2000, JBJS Br (PMID 10755426)
- Figure
- Youth (peak ages 12-29); male predominance
- Source
- McQueen et al 2015 (PMID 25882967)
- Figure
- 2.6% of monitored tibial fractures
- Source
- McQueen, Court-Brown 1996, JBJS Br (PMID 8898137)
- Figure
- Soft-tissue injury without fracture
- Source
- McQueen, Gaston, Court-Brown 2000 (PMID 10755426)
ACS is a worldwide trauma problem driven by high-energy mechanisms (road traffic, falls, sport, crush and industrial injury). Distribution shifts with regional injury patterns and the time-to-presentation differs sharply between well-resourced trauma systems and rural or limited-resource settings, where delayed transfer worsens outcomes.
Major guidance, side by side:
- Key recommendation
- Emergency fasciotomy with documented time targets; hourly observation of at-risk limbs; escalate without delay
- Diagnostic emphasis
- Primarily clinical (escalating analgesia, pain on passive stretch); pressure monitoring adjunctive
- Evidence level
- Consensus / expert (Grade D-equiv.)
- Key recommendation
- Clinical diagnosis paramount; delta P under 30mmHg triggers fasciotomy; continuous monitoring for obtunded/unreliable patients
- Diagnostic emphasis
- Clinical + delta P; serial or continuous measurement when exam unreliable
- Evidence level
- Level II-III evidence-informed
- Key recommendation
- Two-incision four-compartment leg release as standard; carpal tunnel release mandatory with forearm fasciotomy
- Diagnostic emphasis
- Combined clinical and pressure; emphasis on completeness of release
- Evidence level
- Consensus
- Key recommendation
- Liberal prophylactic fasciotomy at revascularisation after prolonged warm ischaemia (over ~4-6h)
- Diagnostic emphasis
- Anticipatory, not reactive
- Evidence level
- Level III (PMID 31034949)
All major bodies agree on the core principles: ACS is a clinical diagnosis, fasciotomy must not be delayed, delta P under 30mmHg is the most defensible pressure threshold, continuous monitoring is reserved for patients who cannot be examined, and all compartments must be released. Differences are largely of emphasis (how heavily to rely on pressure measurement) rather than substance.
Registry & population evidence:
There is no dedicated compartment-syndrome registry; the evidence base is built on prospective and cohort series (chiefly the Edinburgh series - PMIDs 8898137, 8898136, 10755426). National trauma registries (e.g. the UK TARN and equivalents) capture ACS as a complication of long-bone trauma and consistently identify young men with tibial shaft fractures as the highest-risk cohort, mirroring the published series.
Global practice variation:
- Continuous pressure monitoring (Stryker/arterial transducer) is widely available in high-resource trauma centres but scarce elsewhere
- In limited-resource settings, diagnosis is necessarily clinical and the threshold to operate is even lower
- Delayed transfer is a key driver of poor outcomes in rural/remote systems worldwide
- Do NOT delay fasciotomy for transfer - decompress where ACS is diagnosed, then transfer
- Release all compartments completely (deep posterior most missed in the leg)
- Document serial neurovascular assessments with times - the single most protective medicolegal step
Missed or delayed compartment syndrome is among the most frequent and costly sources of orthopaedic litigation in every jurisdiction studied. Protective practice is identical everywhere: a low diagnostic threshold, timed serial assessments, prompt decompression and early senior involvement.
MCQ Practice Points
Q: Why are peripheral pulses typically present in acute compartment syndrome? A: ACS is a microvascular problem. Compartment pressures (over 30mmHg) exceed capillary perfusion pressure (approximately 25mmHg) but remain below systolic arterial pressure (typically over 90mmHg). Arterial inflow continues, actually worsening edema. Pulselessness is a very late sign.
Q: Which compartment is most commonly missed during leg fasciotomy? A: The deep posterior compartment, which contains tibialis posterior, FHL, and FDL. It is separated from the superficial posterior by the deep transverse intermuscular septum, which must be specifically divided. Accessed via posteromedial incision.
Q: A trauma patient has BP 80/50 and compartment pressure of 28mmHg. Does this require fasciotomy? A: Yes. The delta P (DBP minus compartment pressure) = 50 - 28 = 22mmHg, which is under the 30mmHg threshold. Delta P is more reliable than absolute pressure in hypotensive patients. Absolute pressure may look acceptable but perfusion is inadequate.
Q: What is the expected outcome if fasciotomy is performed at 12 hours? A: Poor outcome expected. Studies show fasciotomy under 6 hours gives normal muscle function. At 6-12 hours outcomes are variable. Beyond 12 hours, 90% have permanent neurological deficits. Time is muscle.
Q: What additional release must always be performed with forearm fasciotomy? A: The carpal tunnel must always be released. The median nerve passes through this confined space and will be compressed if not released. Failure to release carpal tunnel is a cause of ongoing median nerve symptoms.
Q: What is the earliest and most reliable clinical sign of compartment syndrome? A: Pain on passive stretch of the muscles in the affected compartment. For anterior leg compartment: pain on passive plantar flexion. For deep posterior: pain on passive toe dorsiflexion. For volar forearm: pain on passive finger extension.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old man presents 6 hours after a motorcycle accident with a closed tibial shaft fracture. His leg is in a plaster backslab. He is requiring increasing analgesia and describes severe pain in his leg. On examination, his toes are pink with sensation present, but he has pain on passive dorsiflexion of his great toe. What is your assessment and management?”
“You are called to ICU about a 45-year-old intubated patient 18 hours post-polytrauma with bilateral femur fractures, now fixed with IM nails. The ICU nurse is concerned the left leg looks swollen and tense. The patient cannot be assessed clinically. How do you approach this?”
“A 7-year-old boy presents 24 hours after a supracondylar humerus fracture was pinned at another hospital. He has severe pain, a tense forearm, cannot extend his fingers actively, and has decreased sensation in the median nerve distribution. The referring hospital did not perform fasciotomy. How do you manage this?”
“You are asked to see a patient in recovery who just had a popliteal artery repair after 5 hours of warm ischemia from a knee dislocation. The vascular surgeon asks if you want to do a prophylactic fasciotomy. What is your response?”
PRESSURE THRESHOLDS
- Delta P (DBP minus compartment) under 30mmHg = fasciotomy - this is THE threshold
- Absolute pressure over 30mmHg alone is NOT an indication - it occurred in 53 of 116 monitored tibial fractures
- Delta P matters most in hypotensive patients, where a normal-looking absolute pressure still starves the compartment
- Do NOT wait for pressure if clinical diagnosis clear
TIMING
- Under 6 hours: best outcomes (normal function)
- 6-8 hours: variable outcomes
- Over 8 hours: irreversible damage beginning
- Over 12 hours: 90% permanent deficits
CLINICAL SIGNS
- EARLY: Pain out of proportion, pain on passive stretch
- EARLY: Tense compartment on palpation
- INTERMEDIATE: Paresthesia (nerve ischemia)
- LATE: Paralysis, pallor, pulselessness - TOO LATE
LEG COMPARTMENTS (4)
- Anterior: TA, EHL, EDL, deep peroneal nerve
- Lateral: peroneus longus/brevis, superficial peroneal
- Superficial posterior: gastroc, soleus
- Deep posterior: TP, FHL, FDL - MOST MISSED
FASCIOTOMY TECHNIQUE (LEG)
- Two-incision technique for complete release
- Anterolateral: anterior + lateral compartments
- Posteromedial: superficial + deep posterior
- MUST divide deep transverse septum for deep posterior
MEDICOLEGAL
- Common cause of orthopaedic litigation
- Document serial assessments with times
- Document decision-making rationale
- Early senior involvement is protective
Evidence Base
McQueen & Duckworth - The Diagnosis of ACS: where the 2-hour duration comes from
- THE THRESHOLD IS A DIFFERENTIAL PRESSURE UNDER 30 mmHg FOR MORE THAN 2 HOURS - the duration is stated as part of the recommendation, not as a refinement of it, and it is the half most often dropped when the threshold is quoted
- Clinical findings have sensitivities of only 13 to 64 per cent for acute compartment syndrome, against 94 per cent for continuous intracompartmental pressure monitoring at that sustained threshold
- Specificity is 98 per cent for monitoring, against a range of 63 to 98 per cent for clinical findings
- The authors recommend decompression primarily on the sustained differential pressure rather than waiting for clinical signs to declare, because doing so shortens time to definitive treatment
McQueen & Court-Brown - Delta P Threshold for Decompression
- Prospective study of 116 tibial diaphyseal fractures with 24-hour continuous anterior compartment monitoring
- Using a differential (delta) pressure threshold of under 30mmHg led to NO missed cases of acute compartment syndrome
- An absolute threshold of 30mmHg would have led to fasciotomy in 43% of patients; 40mmHg in 23% - most unnecessary
- Only 3 patients (2.6%) developed true acute compartment syndrome
McQueen, Christie & Court-Brown - Continuous Monitoring & Outcomes
- 25 tibial diaphyseal fractures complicated by acute compartment syndrome (13 monitored, 12 not)
- Mean delay to fasciotomy 16 hours (monitored) versus 32 hours (non-monitored), p under 0.05
- No sequelae in the monitored group versus definite weakness/contractures in 10 of 11 survivors not monitored, p under 0.01
- Significantly delayed tibial union in the non-monitored group
McQueen, Gaston & Court-Brown - Who Is at Risk?
- 164 patients with acute compartment syndrome over 8 years - the defining epidemiological series
- An associated fracture was present in 69%; about half of these were tibial shaft fractures (≈36% of all ACS)
- Most patients were young men, typically under 35 years; forearm ACS most often accompanied distal radius fractures
- Soft-tissue injury without fracture was the second commonest cause; ~10% had a bleeding disorder or were anticoagulated
McQueen et al - Predictors of ACS After Tibial Fracture
- Retrospective cohort of 1,388 tibial diaphyseal fractures; 160 (11.5%) developed acute compartment syndrome
- Youth was the strongest independent predictor (highest prevalence ages 12-29)
- Blue-collar occupation and implant type also predictive on adjusted analysis
- Male gender and sporting injury associated on univariate analysis
Whitesides et al - Tissue Pressure as Determinant for Fasciotomy
- Foundational description linking compartment pressure to diastolic blood pressure rather than an absolute number
- Inadequate perfusion when tissue pressure rises to within 10-30mmHg of diastolic BP
- No effective perfusion once tissue pressure equals or exceeds diastolic BP - even with palpable distal pulses
- Introduced the perfusion-pressure concept underpinning modern delta P thresholds
Mubarak, Owen et al - Wick Catheter Diagnosis & 30mmHg Threshold
- 65 compartments in 27 patients clinically suspected of ACS, measured by wick catheter
- Normal compartment pressure 0-8mmHg; 30mmHg used as the indication for decompressive fasciotomy
- No sequelae in 16 patients whose pressures stayed under 30mmHg and in whom fasciotomy was withheld
- Established the historical absolute 30mmHg threshold and the role of intra-operative monitoring of decompression
Shaikh et al - Acute Compartment Syndrome of the Upper Extremity
- Contemporary review of upper-limb ACS - forearm most common site, but arm and hand also affected
- Most cases follow trauma; non-traumatic causes include prolonged decubitus positioning, bleeding disorders and reperfusion injury
- Emergent fasciotomy is the cornerstone; delay risks myonecrosis, Volkmann's contracture and limb dysfunction
- Reviews controversies in delayed/missed presentation and advances in diagnosis
Lin et al - Risk Factors for Poor Outcome in Lower-Leg ACS
- Retrospective case-control study of 103 lower-leg ACS cases (44 poor, 59 good outcome)
- Associated arterial injury was an independent risk factor for poor outcome (OR 66.2)
- Lower haemoglobin associated with worse outcomes; open injury and high CK also significant on bivariate analysis
- Timing of fasciotomy was NOT independently associated with outcome in this cohort
Rothenberg et al - Delayed Fasciotomy & Amputation in Acute Limb Ischaemia
- 138 lower-extremity revascularisations for acute limb ischaemia; 42 (30.4%) underwent fasciotomy
- Delayed (rather than prophylactic) fasciotomy was associated with major amputation in 50% versus 5.9% at 30 days, p=0.002
- Higher Rutherford ischaemia class predicted need for fasciotomy
- Supports a liberal approach to prophylactic 4-compartment fasciotomy at revascularisation