FOOSH Mechanism | Lateral X-ray Essential | Headless Screws Anterior-to-Posterior
- Coronal shear mechanism - FOOSH with elbow extended, radial head drives into capitellum
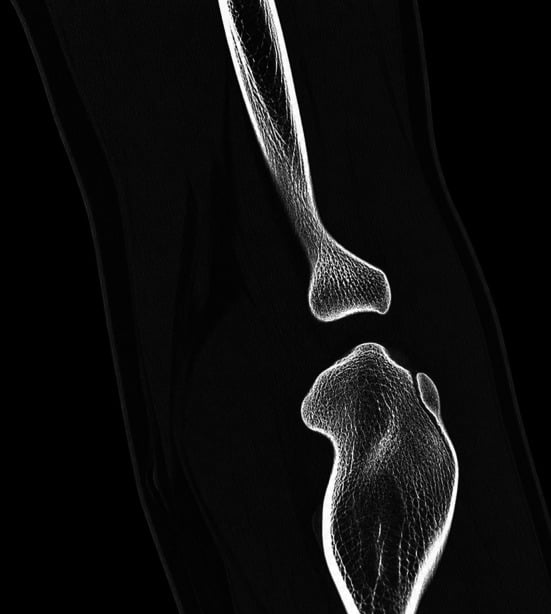
- Lateral X-ray is KEY - 'double arc' sign (capitellum + LATERAL TROCHLEAR RIDGE, signalling medial extension into the trochlea)
- Headless compression screws anterior to posterior - bury beneath cartilage
- Kocher (lateral) approach for ORIF - preserve lateral collateral ligament complex
- Type IV includes trochlea - involves ulnohumeral joint, worst prognosis
- “Often missed on AP view - ALWAYS check lateral radiograph
- “Associated radial head fracture in 30% - examine carefully
- “Early ROM critical to prevent stiffness - start at 48-72 hours
- “No soft tissue attachments anteriorly - AVN risk
Overview and Epidemiology
A coronal shear fracture is a distal humerus fracture that behaves like nothing else in that family. It belongs to distal humerus fractures, but the rest of that family fails in the sagittal or transverse plane and is fixed with columns and plates; this one shears in the CORONAL plane, which is why the fixation runs anterior-to-posterior with buried headless screws and why the lateral radiograph carries the diagnosis while the AP can look normal.
Its company is the reason to look further. The same lateral-side FOOSH load that shears the capitellum also drives the radial head into it, so radial head fracture is the classic associate; and if the elbow also dislocated, the pattern to exclude is the terrible triad with its coronoid component, since a missed coronoid turns a fixable elbow into an unstable one. The paediatric equivalent of the same lateral-column injury is the lateral condyle fracture, which behaves entirely differently because the physis is involved. The complication that decides the functional result here is elbow stiffness - which is why these are fixed rigidly enough to move early rather than splinted.
How common. Capitellar fractures are only 1% of elbow fractures, and they are tested frequently because the mechanism, the diagnostic difficulty and the fixation principles are all particular to them.
Who. There is a 4:1 female predominance, and the injury is commoner in osteoporotic bone. The distribution is bimodal - young men injured at high energy, older women injured at low energy - with a mean age of 45-50 years.
Mechanism. A fall on the outstretched hand with the elbow extended is the most common mechanism. The radial head is driven into the capitellum and shears it off in the coronal plane; a direct blow to the lateral elbow does the same. 20% are associated with an elbow dislocation.
The capitellum is protected by the radial head, which typically fails first. A capitellar fracture therefore needs one of three things:
- A radial head that has already fractured - 30% have a concurrent radial head fracture
- An intact radial head with a force vector that produces shear rather than axial load
- Poor bone quality
Anatomy and Pathophysiology
The bare hemisphere. The capitellum has no soft-tissue attachments anteriorly and an anterior surface covered entirely by articular cartilage, so a fracture fragment holds on to its blood supply only through whatever posterior bone attachment remains. That is why AVN is a risk here, and why the screws are placed anterior to posterior: the vessels enter from the posterior humerus, so a screw driven backwards compresses the fragment against the humerus without disturbing them.
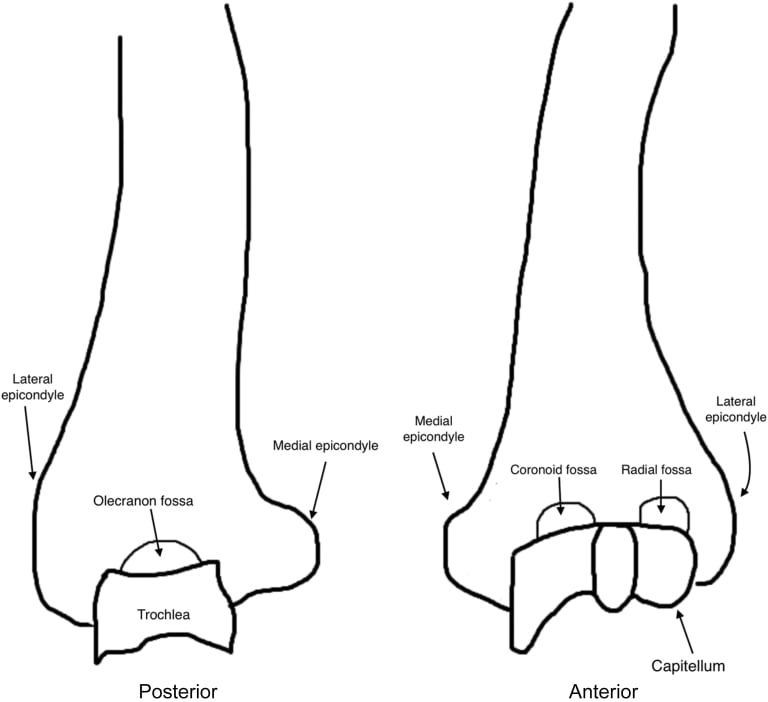
- Location
- Lateral 1/3 of distal humeral articular surface
- Clinical Relevance
- Articulates with radial head - forms radiocapitellar joint
- Location
- Medial 2/3 of distal humeral articular surface
- Clinical Relevance
- Type IV fractures involve trochlea - affects ulnohumeral joint
- Location
- Non-articular prominence lateral to capitellum
- Clinical Relevance
- Origin of common extensor tendons and LCL
- Location
- Lateral ulnar collateral ligament
- Clinical Relevance
- Must preserve during approach - posterolateral rotatory stability
What it does mechanically. The capitellum transmits 60% of the axial load across the elbow and works with the radial head as a secondary valgus stabiliser. Lose the capitellum and the radiocapitellar joint becomes unstable; take the trochlea with it, as a Type IV does, and the ulnohumeral joint is unstable as well.
The ligaments sit immediately above it. The lateral collateral complex arises from the lateral epicondyle just proximal to the capitellum, so a lateral approach or a comminuted lateral column threatens it. The lateral ulnar collateral ligament is the component that resists posterolateral rotatory instability, and it must be repaired if it is detached.
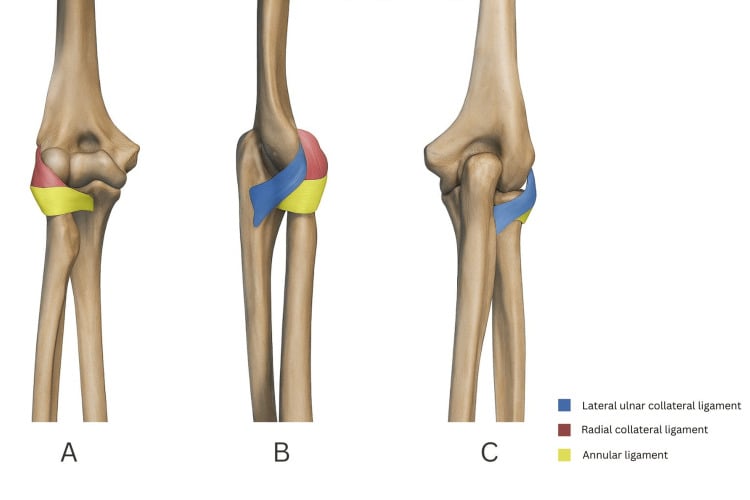
The lateral epicondyle is non-articular and gives origin to the extensors; the capitellum is articular and lies anterior and distal to it. On the lateral radiograph the capitellum casts the characteristic hemispherical shadow that, once fractured and displaced, produces the 'double arc' sign.
Classification Systems
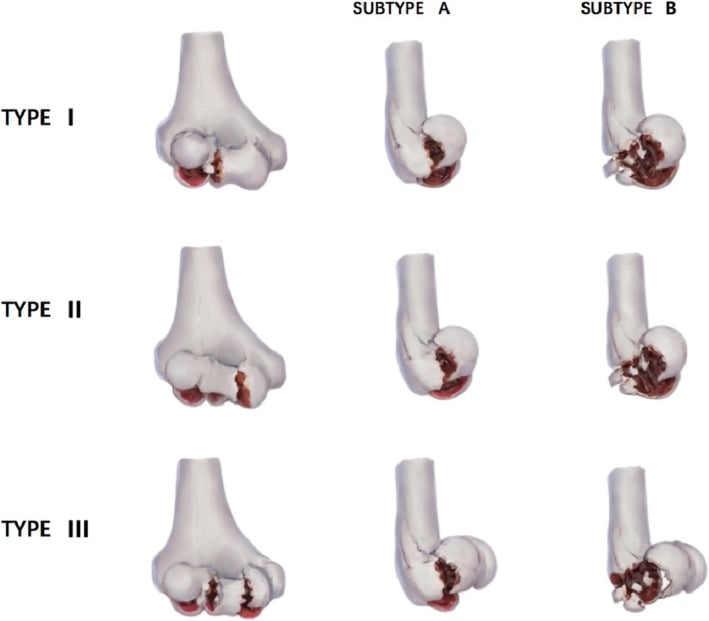
Two systems are in use and they answer different questions. Bryan-Morrey is the one most commonly used: it names the fracture and carries the eponyms an examiner will ask for. Dubberley describes what changes the operation - how far the shear runs medially, and whether the posterior condyle is comminuted.
The grades run from a large bony fragment that takes a screw well to an articular surface that may not be reconstructable at all.
- Eponym
- Hahn-Steinthal
- Fragment Characteristics
- Large fragment with substantial bone stock
- Prognosis
- Best - most fixable
- Eponym
- Kocher-Lorenz
- Fragment Characteristics
- Thin osteochondral shell, minimal bone
- Prognosis
- Variable - size dependent
- Eponym
- -
- Fragment Characteristics
- Comminuted multiple fragments
- Prognosis
- Challenging - may need excision
- Eponym
- -
- Fragment Characteristics
- Capitellum + trochlea involved
- Prognosis
- Worst - involves both joints
Type IV is the one to recognise. Because the fracture crosses into the trochlea it takes in the ulnohumeral joint as well as the radiocapitellar, and it carries the highest stiffness rate and the worst functional outcomes.
Clinical Assessment
History. A fall on the outstretched hand with the elbow extended, or a direct blow to the lateral side. The pain is lateral and worse with pronation and supination, the swelling comes on rapidly because the joint fills with blood, and the elbow is painful and will not move through its range.
Examination. Look for swelling, ecchymosis and deformity, all of which may be subtle. Feel for tenderness over the anterolateral elbow and for an effusion at the posterolateral soft spot. Move the elbow to find a limited, crepitant arc, and test stability after any reduction.
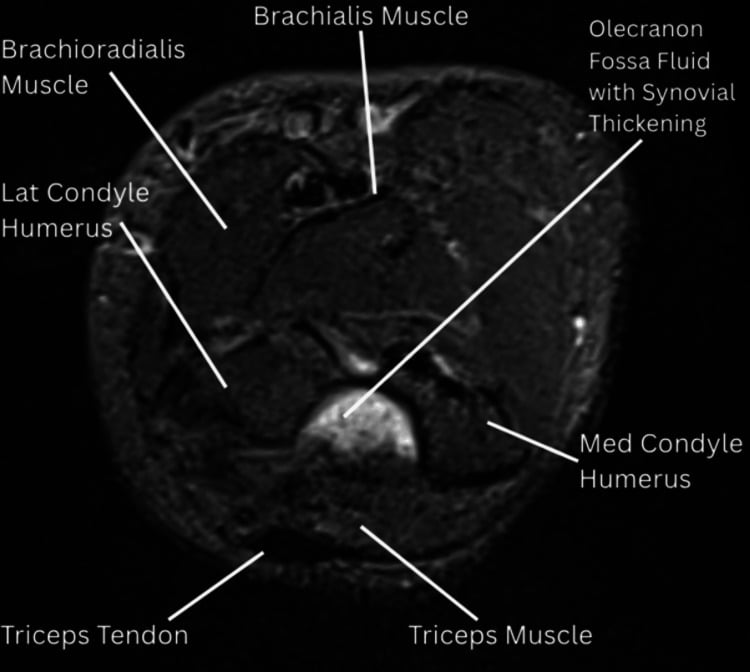
- Location
- Over capitellum (anterolateral)
- Significance
- Direct sign of injury
- Location
- Posterolateral soft spot
- Significance
- Haemarthrosis - suggests intra-articular fracture
- Location
- Radiocapitellar joint
- Significance
- Fragment blocking motion or radial head injury
- Location
- With pivot shift test
- Significance
- Associated LCL injury - may need repair
- Location
- Proximal radius
- Significance
- 30% have concurrent radial head fracture
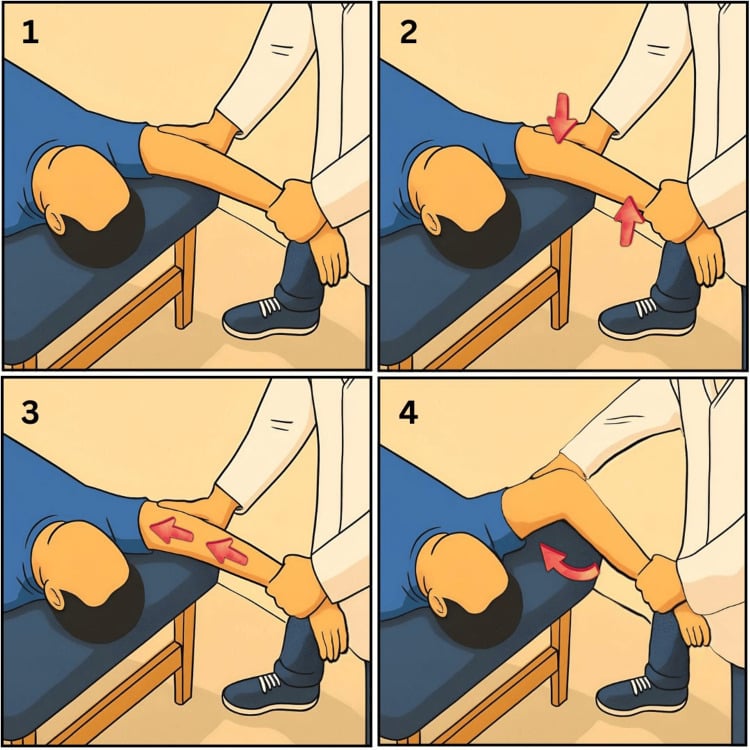
Look for the associated injuries. Examine the radial head specifically, and if the elbow dislocated look for the coronoid fracture that completes the terrible triad. The anterior capsule is injured as part of the coronal shear pattern, and a lateral collateral complex that is unstable on testing may need repair at the same operation.
Document radial, median and ulnar nerve function and the radial and ulnar pulses. Neurovascular injury is rare with an isolated capitellar fracture, but the associated injuries - dislocation, radial head fracture - raise the risk. Record PIN function (finger extension) before surgery, because the nerve is at risk during the approach.
- Discriminating features
- Double arc sign on lateral X-ray; AP often normal; block to flexion
- Key investigation
- Lateral radiograph then CT for planning
- Discriminating features
- Tenderness over radial head, painful supination/pronation; coexists in up to 30%
- Key investigation
- AP, lateral and radiocapitellar (Greenspan) view
- Discriminating features
- Child, lateral swelling, fat pad sign; involves physis and trochlear groove
- Key investigation
- Internal oblique radiograph; arthrogram/MRI if cartilaginous
- Discriminating features
- Gross instability, coronoid and radial head fractures with dislocation
- Key investigation
- Post-reduction CT for coronoid, radial head and capitellum
- Discriminating features
- Adolescent throwing athlete, insidious lateral pain, no acute high-energy mechanism
- Key investigation
- MRI for subchondral changes and fragment stability
- Discriminating features
- Non-articular point tenderness, no intra-articular effusion, normal joint line
- Key investigation
- Radiograph (usually normal); clinical diagnosis
Investigations
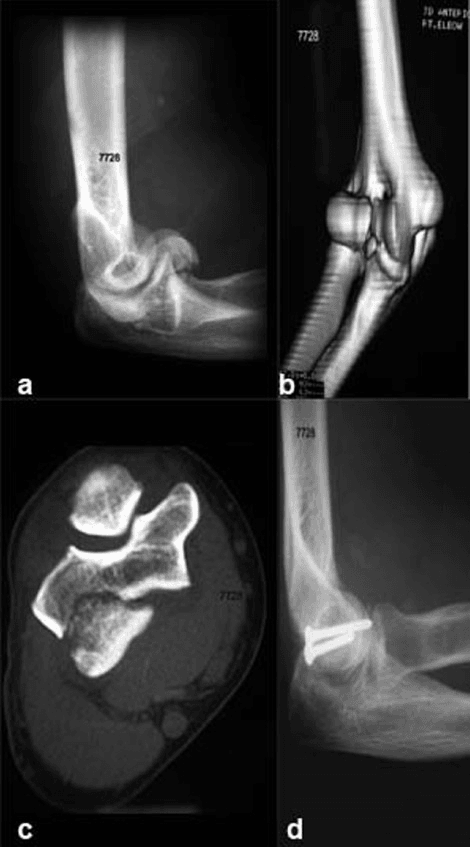
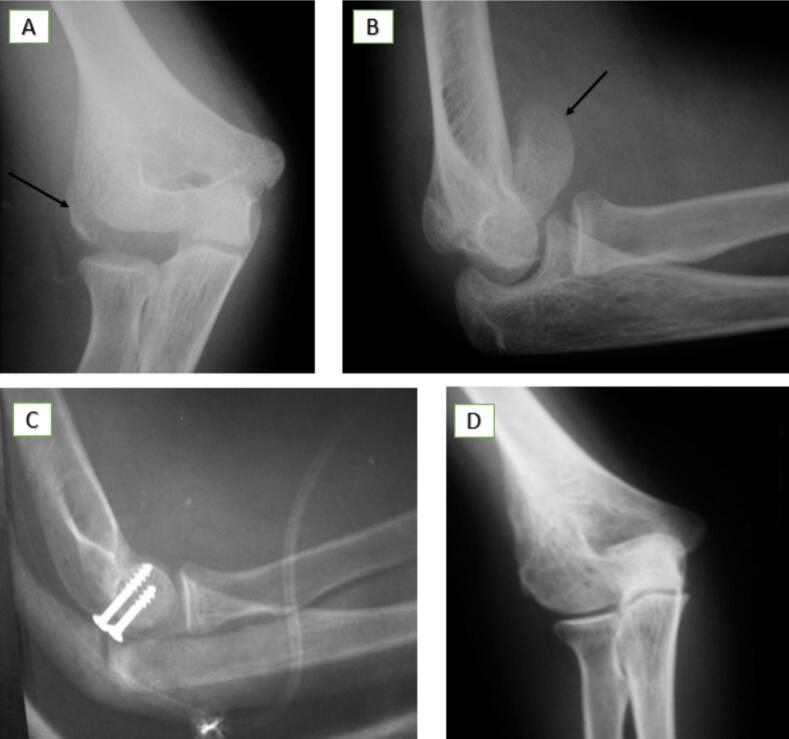
Radiographs, and the lateral is the one that makes the diagnosis. Request AP, lateral and oblique views. The fracture line lies in the coronal plane, front to back, so on the AP film you are looking along it, edge-on, and it can appear nearly normal; on the lateral you are looking across it and it becomes obvious. An elevated posterior fat pad says there is blood in the joint even when no line is visible.
The double arc sign. Two concentric semicircular arcs on the lateral view: the displaced capitellar fragment and the lateral trochlear ridge. Described by McKee, it means something more specific than "capitellar fracture" - it says the shear has extended medially into the trochlea, which flags the more complex patterns (Bryan-Morrey IV, the higher-grade Dubberley fractures) that need a wider exposure and often column support.
Read it as a rule-in sign only. Its presence is highly suggestive; its absence does not exclude trochlear or posterior-column involvement, and plain films underestimate the true extent in roughly a third of cases, with reported sensitivity for the full extent only around two-thirds. Proceed to CT regardless.
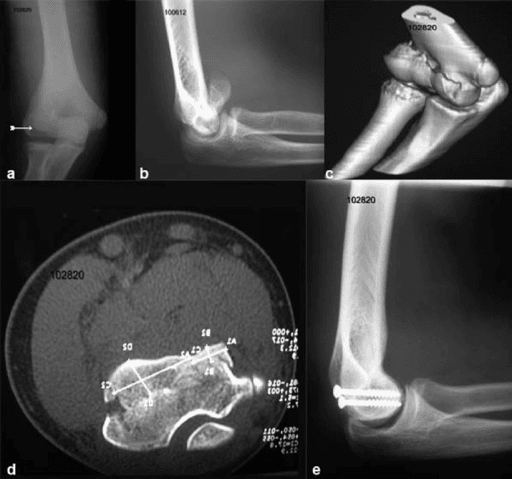
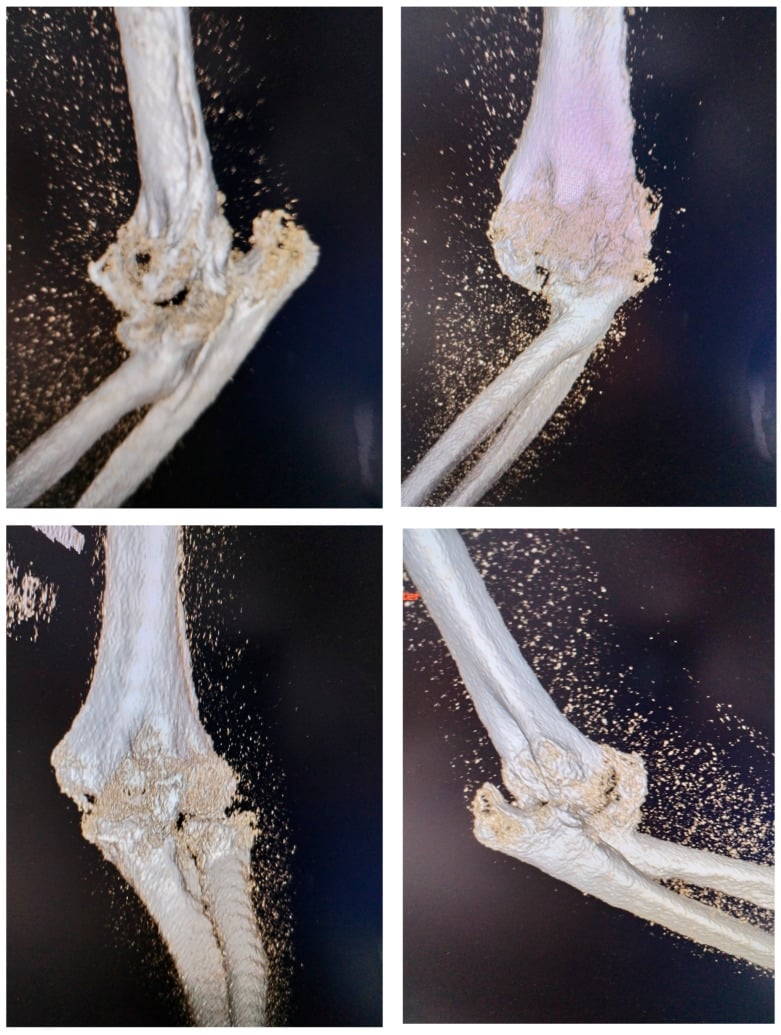
CT is the gold standard for preoperative planning. The sagittal reconstruction profiles the coronal shear line and 3D reconstruction helps with the complex patterns; together they give fragment size and position, comminution, trochlear involvement and the associated injuries.
Always obtain CT for surgical planning. Plain films cannot reliably assess:
- Fragment size, which decides fixation versus excision
- Trochlear involvement (Type IV), which changes the prognosis
- Posterior column comminution (the Dubberley B subtypes)
- Associated radial head or coronoid fractures
MRI is rarely needed. Consider it when an occult fracture is suspected with negative radiographs and high clinical suspicion, or to assess a ligamentous injury.
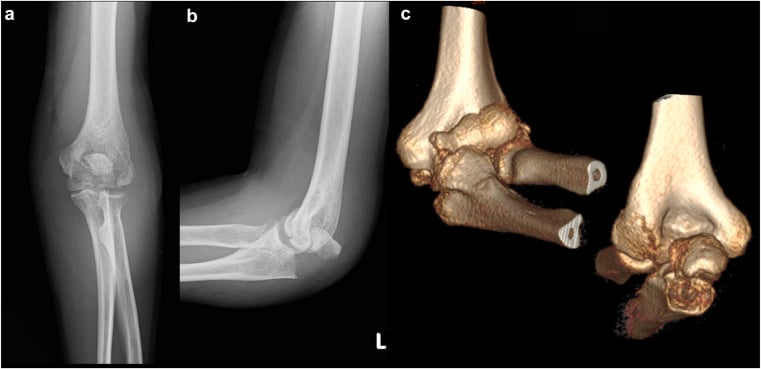
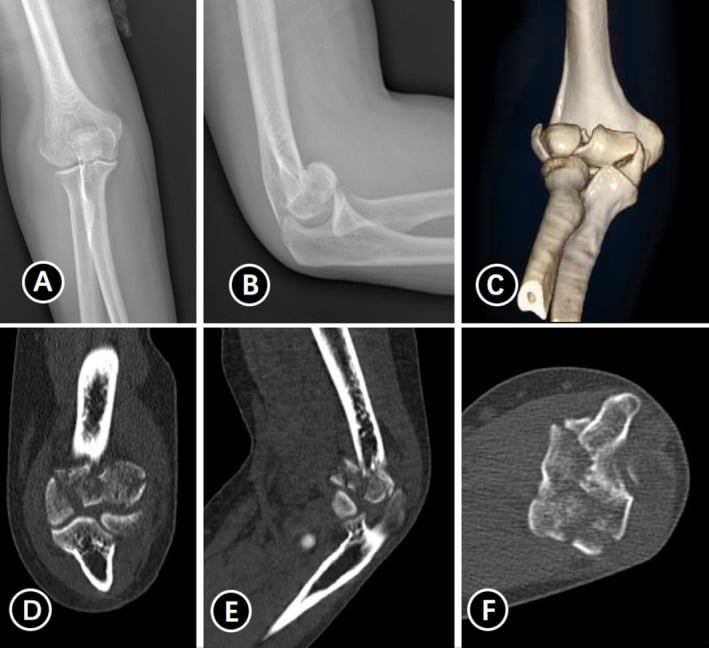
Management Algorithm
The decision is short. Virtually every displaced capitellar fracture is fixed, and what remains to be decided is whether the fragment can be reconstructed or has to come out, and how soon the patient goes to theatre.
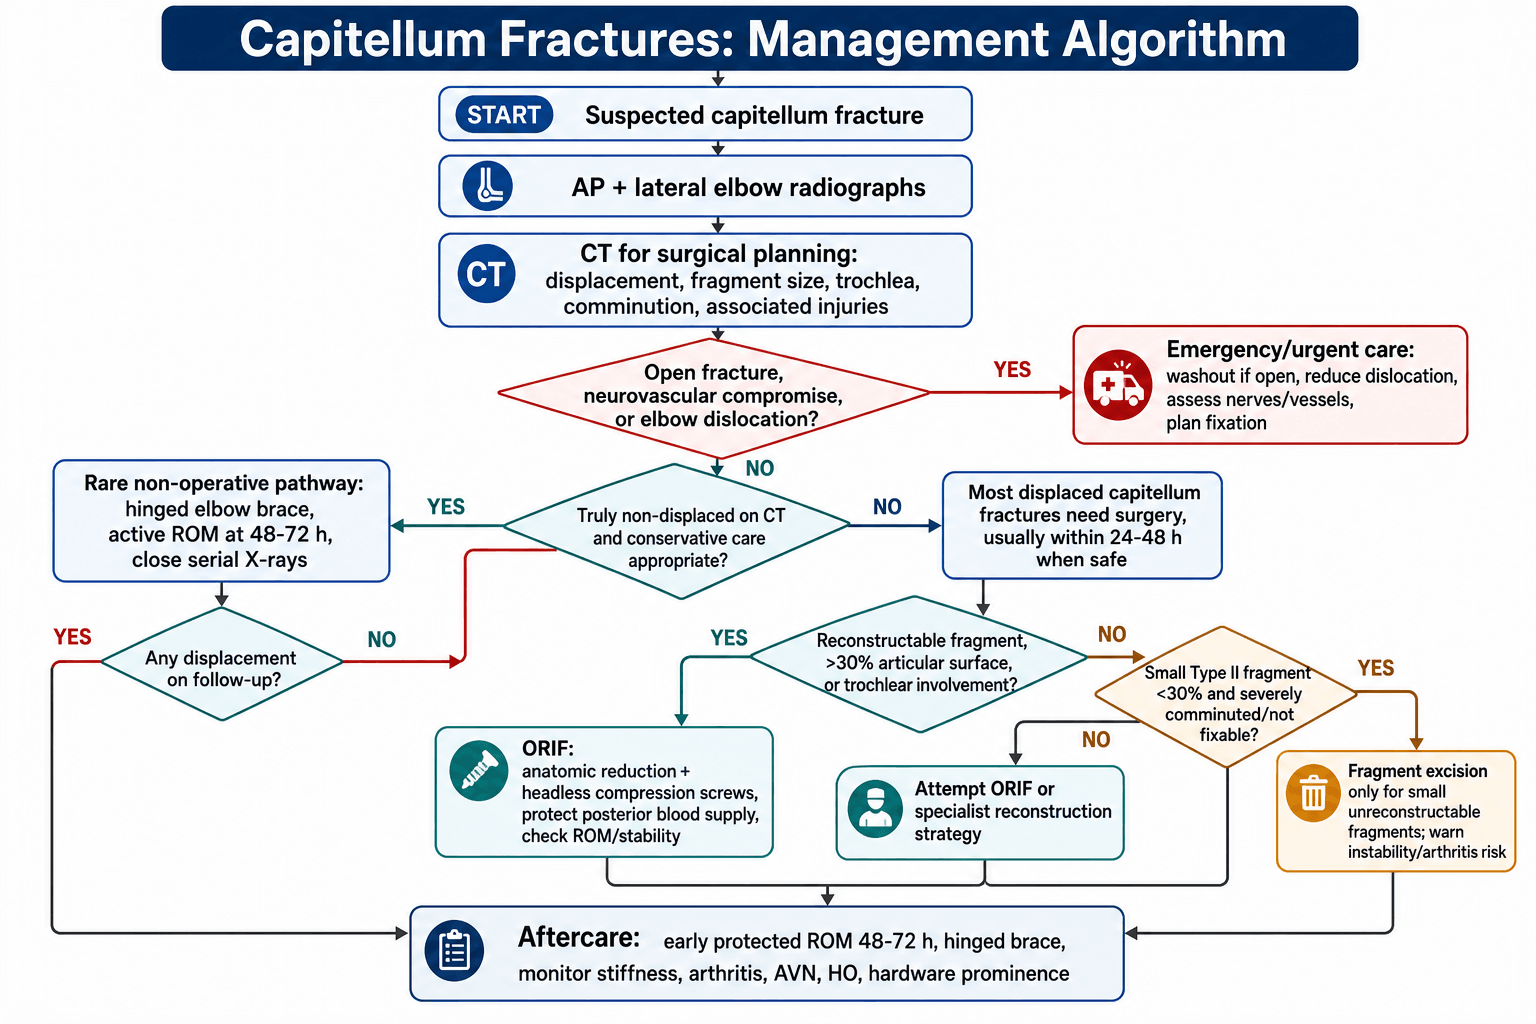
A displaced capitellar fracture treated non-operatively goes on to malunion, stiffness and post-traumatic arthritis. Non-operative treatment of a displaced fracture belongs only to the patient in whom surgery is absolutely contraindicated.
- Fragment Quality
- Large fragment, good bone stock
- Key Decision
- Always fixable
- Treatment
- ORIF headless screws - excellent prognosis
- Fragment Quality
- Thin osteochondral shell
- Key Decision
- Size dependent
- Treatment
- ORIF if larger than 30%, excise if small
- Fragment Quality
- Multiple fragments
- Key Decision
- Assess reducibility
- Treatment
- ORIF if reconstructable, excise if severely comminuted
- Fragment Quality
- Capitellum + trochlea
- Key Decision
- Critical to fix
- Treatment
- ORIF essential - involves ulnohumeral joint
Non-operative treatment and its short list. Reserve it for a fracture that is truly non-displaced on CT, which is very rare, for the non-ambulatory patient, and for comorbidities that preclude surgery. Manage in a hinged elbow brace with early active motion at 48-72 hours and close follow-up radiographs, and convert to fixation if any displacement appears.
Timing. Most isolated capitellar fractures are semi-urgent and go to theatre within 24-48 hours, since early surgery is what allows the early mobilisation elbow outcomes depend on. An associated elbow dislocation or neurovascular compromise makes the case urgent - the instability itself is the indication - and an open fracture is an emergency needing washout and fixation. Displaced Type I and large Type II fragments earn their operation by restoring the articular surface; a Type IV earns it because both joints have to be restored.
Surgical Technique
ORIF Steps
Lateral decubitus is preferred, or supine with the arm across the chest. Tourniquet on the upper arm, image intensifier from the opposite side.
Kocher (lateral) approach between anconeus and ECU. Develop the interval and protect the lateral collateral complex; extend proximally if more exposure is needed.
Flex the elbow to 90 degrees, add a capsulotomy if the view demands it, then irrigate the joint and clear loose bodies and haematoma.
Anatomic reduction is critical. Pointed reduction clamps damage cartilage, so use them carefully, and hold the reduction with K-wires.
Headless compression screws (Herbert, Acutrak) from anterior to posterior, perpendicular to the fracture plane, two or three depending on fragment size, countersunk below the cartilage.
Take the elbow through a full arc, confirm on fluoroscopy that the reduction has held, and assess the stability of the radiocapitellar joint.
Why the screws run forwards. The blood supply enters from the posterior humerus, so a screw driven from anterior to posterior compresses the fragment onto the humerus without disturbing the vessels that keep it alive. The heads are what make that tolerable: headless compression screws countersunk beneath the cartilage leave nothing prominent to impinge, which is what allows motion to start within days. A Type I usually takes two or three; a Type IV may need more.
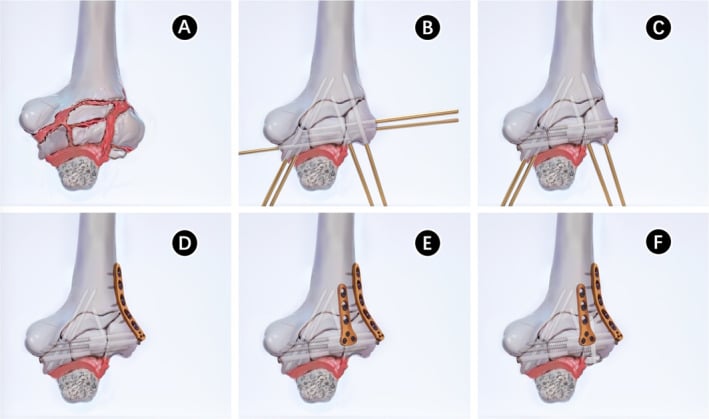
"ORIF if large, excise if small" does not answer the harder question of how to fix a fragment that is mostly cartilage over a sliver of subchondral bone. A standard headless compression screw needs bone to purchase and can shatter a thin shell, so what is used depends on how much bone is left to grip.
- Countersunk mini headless screws (for example small-diameter Acutrak or Herbert) engaging whatever subchondral bone exists, heads buried beneath the cartilage - feasible only if there is a rim of bone to grip
- Bioabsorbable pins or darts (e.g. PLLA) passed through the cartilage and into the recipient bed - they leave no prominent hardware, avoid a second removal operation, and are useful when the shell is too thin for metal
- Threaded or smooth K-wires countersunk beneath the surface, as provisional or definitive fixation for a very thin fragment
The osteochondral principles apply throughout: freshen the bed, avoid fragmenting the shell with reduction clamps, and finish with a flush congruent surface. The thin Kocher-Lorenz shell is the pattern where fixation is technically hardest, and if it is truly small and non-fixable, excise it rather than leave an incongruent or loose fragment.
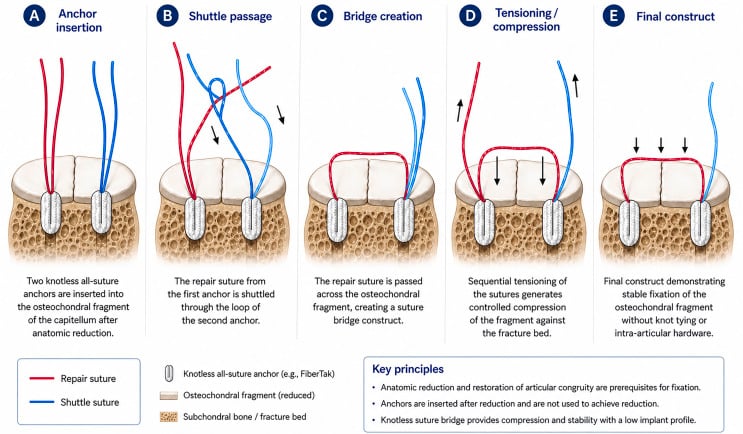
Fragment excision. Excision is for the fragment that cannot be fixed: a small Type II shell, a Type III too comminuted to reconstruct, a failed primary ORIF with a non-viable fragment, or salvage. The threshold is the rule of 30% - a fragment under 30% of the capitellar articular surface that is also severely comminuted or unfixable may be excised, while anything over 30%, or any trochlear involvement, means ORIF must be attempted.
Excising a large fragment produces radiocapitellar instability, valgus instability through the loss of the secondary stabiliser, and early post-traumatic arthritis. Only small Type II fragments should be excised.
Anterior-to-posterior headless screws are the right answer for a simple anterior fragment (Dubberley A). They are inadequate when the posterior condyle is comminuted - Dubberley B, the Ring posterior-column component - because pure lag screws have nothing solid to compress against and the construct collapses into extension and posterior translation.
- Add posterior or posterolateral column support: a small buttress or contoured plate on the posterolateral column, with or without supplementary screws, to reconstruct the column and neutralise the shear
- This is the technical reason these patterns are approached posteriorly (transolecranon) rather than through a simple lateral window - the exposure has to reach the comminuted posterior column to apply the plate
- It is also why Dubberley B types carry the worst prognosis, with higher reoperation, stiffness and nonunion: they are a column reconstruction, not a single-fragment lag-screw job
Match the construct to the pattern - lag screws for an anterior shell, column plating for posterior comminution. Calling anterior-to-posterior screws sufficient for a Dubberley B fracture is a recognised error.
Type IV needs more exposure than a Kocher window gives. Plan for a combined lateral and medial approach if the trochlear fragment cannot be reached, or an olecranon osteotomy if the exposure is still inadequate, and fix the trochlea with buried screws or K-wires. Even with good technique, 30-50% of these end with a fair or poor result.
With a radial head fracture, fix the capitellum first to restore the articular surface, then address the radial head by fixation or replacement; the Kocher approach serves both. With a dislocation, address every component of the instability, repair the lateral collateral ligament if it is torn, and check the coronoid for the terrible triad pattern. Complex patterns are worth additional imaging before committing to a plan.
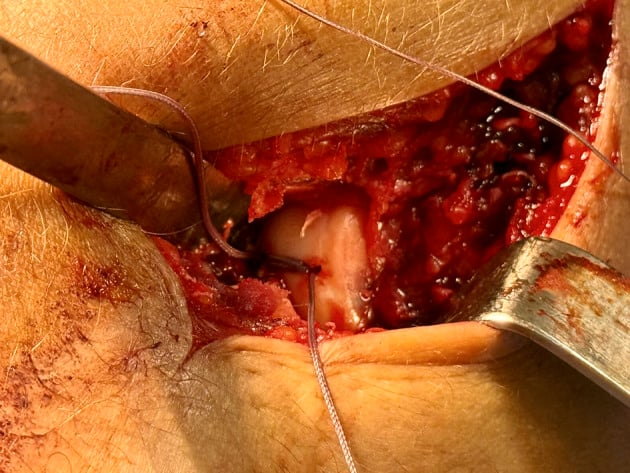
Complications
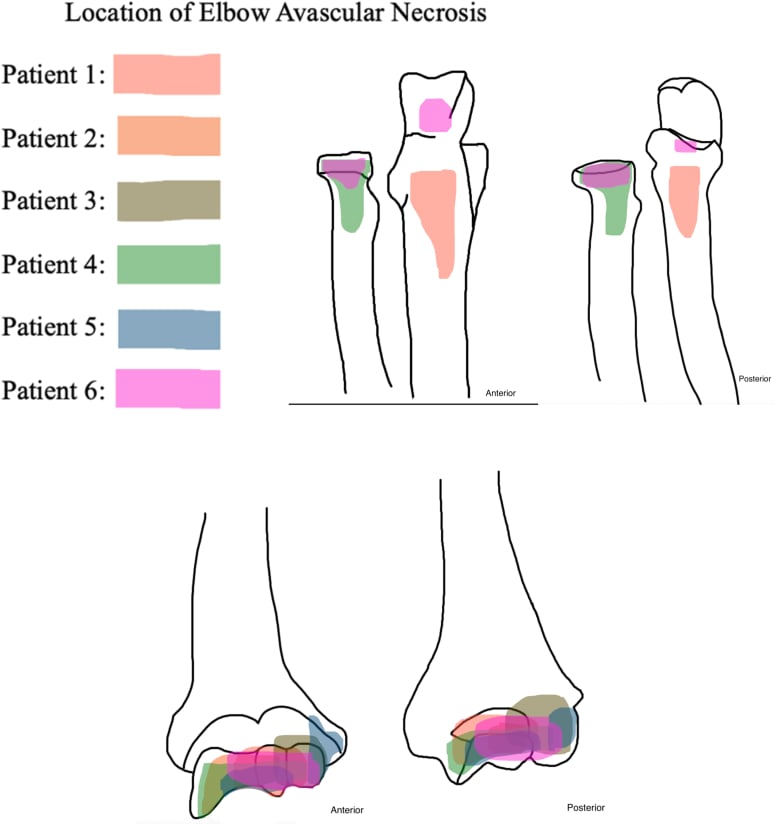
Stiffness is the most common problem, and delayed surgery and a Type IV pattern recur down the risk-factor column.
- Incidence
- 20-40%
- Risk Factors
- Delayed surgery, Type IV, prolonged immobilisation
- Management
- Early ROM, hinged brace, may need arthrolysis
- Incidence
- 15-30%
- Risk Factors
- Malreduction, Type IV, comminution
- Management
- Activity modification, ultimately arthroplasty
- Incidence
- 5-10%
- Risk Factors
- Posterior dissection, comminution
- Management
- Fix A-to-P, minimise soft tissue stripping
- Incidence
- 5-15%
- Risk Factors
- Delayed surgery, forced passive ROM, head injury
- Management
- Prophylaxis: NSAIDs or radiation, excision if symptomatic
- Incidence
- Under 5%
- Risk Factors
- Technical error, AVN
- Management
- Revision surgery if symptomatic
- Incidence
- 5-10%
- Risk Factors
- Screws not countersunk
- Management
- Use headless screws, countersink properly
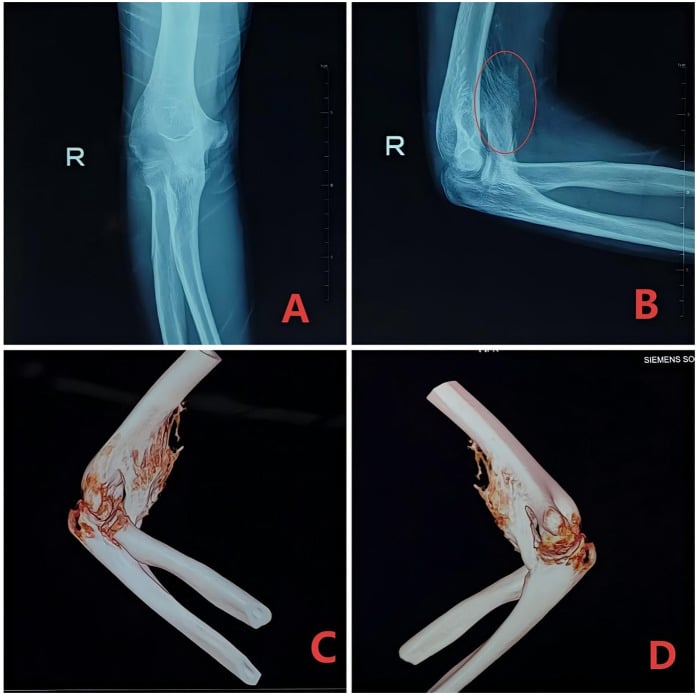
Prevention is built into the operation rather than added afterwards: reduce anatomically so the joint can be moved, use headless screws so nothing impinges, start motion early, and never force passive motion - that is what drives heterotopic ossification.
Postoperative Care
The first days are protection with a plan, not immobilisation. The elbow is splinted only long enough for the swelling and pain to settle, because the timing of the first movement is what the functional result turns on.
Rehabilitation Timeline
Backslab in 90 degrees flexion. Elevation and ice. Plan the start of motion - the timing is what matters.
Remove the backslab and start active ROM, gravity-assisted flexion and extension. No passive motion (HO risk).
Full active ROM encouraged. Hinged brace if unstable. No resistance exercises. Serial X-rays at 2 and 6 weeks.
Progressive strengthening, light resistance, return to activities as tolerated.
Return to full activities. Maximum recovery may take 6-12 months.
The elbow stiffens rapidly after injury, and delayed mobilisation produces flexion contracture, heterotopic ossification and a poor functional result. Active motion only: forced passive motion increases the risk of HO.
Heterotopic ossification. The risk rises with high-energy trauma, delayed surgery (more than 2 weeks), an associated elbow dislocation, extensive soft-tissue stripping and repeated attempts at reduction, and again with head injury, burns, prolonged intubation and previous HO. Active motion begun at 48-72 hours is the most important preventive measure; drugs and radiation are for the patient who is already high risk.
- Indomethacin 25mg three times daily (75mg daily) for 3-6 weeks
- A single 7Gy (700cGy) dose of radiation within 72 hours - rarely needed
Outcomes and Prognosis
The pattern arrives with the patient; the accuracy of the reduction, the delay before theatre and the rehabilitation are what the surgeon contributes.
- Impact on Outcome
- Most important
- Notes
- Type I best, Type IV worst
- Impact on Outcome
- Critical
- Notes
- Anatomic reduction = better outcomes
- Impact on Outcome
- Significant
- Notes
- Early surgery (under 2 weeks) preferred
- Impact on Outcome
- Negative
- Notes
- Radial head, dislocation worsen prognosis
- Impact on Outcome
- Moderate
- Notes
- Younger patients have better outcomes
- Impact on Outcome
- Important
- Notes
- Early ROM essential for good outcome
After ORIF of a Type I fracture, expect a flexion-extension arc of 100-130 degrees, with a 10-20 degree loss of terminal extension that is common and well tolerated, and full pronation and supination. The Mayo Elbow Performance Score is 85-90 (good or excellent) in the majority.
Guidelines, Registries & Global Practice
Capitellar (coronal shear) fractures are uncommon, so no joint registry tracks them and no single national society publishes a dedicated guideline. Practice is therefore driven by case series, by the two defining classifications (Bryan-Morrey, Dubberley) and by a systematic review of surgical approaches. Care is remarkably consistent worldwide: CT for planning, anatomic ORIF with buried headless compression screws and early motion, with fragment excision or arthroplasty reserved for unreconstructable injuries.
- Value
- 44.9 years (95% CI 39.7-50.2)
- Source
- Fisher 2022 systematic review (PMID 36353417)
- Value
- Type A 38%, Type B 33%
- Source
- Fisher 2022 (PMID 36353417)
- Value
- 13.8% (95% CI 9.6-19.5)
- Source
- Fisher 2022 (PMID 36353417)
- Value
- 21.2% (95% CI 18.0-24.9)
- Source
- Fisher 2022 (PMID 36353417)
- Value
- 12.0% (95% CI 9.2-15.6)
- Source
- Fisher 2022 (PMID 36353417)
- Value
- 7.8% / 7.4%
- Source
- Fisher 2022 (PMID 36353417)
- Position on capitellar fractures
- Coronal shear = partial articular (B3); anatomic ORIF with headless compression / countersunk screws, early mobilisation
- Evidence level
- Expert consensus / Level IV-V
- Position on capitellar fractures
- No dedicated guideline; teaching mirrors series - CT planning, ORIF for displaced fractures, headless screws, early ROM
- Evidence level
- Level IV
- Position on capitellar fractures
- Covered under general open-fracture and intra-articular fracture principles (timely senior review, CT, anatomic reduction); no fracture-specific BOAST
- Evidence level
- Level IV-V
- Position on capitellar fractures
- Approach tailored to pathoanatomy - lateral for simple, anterolateral for anterior Dubberley A, transolecranon for posterior B
- Evidence level
- Level IV (Ravishankar PMID 27844160)
- Position on capitellar fractures
- Anterolateral approach had lower complication rate than extended lateral for Dubberley A; evidence insufficient to mandate either
- Evidence level
- Level II (Fisher PMID 36353417)
Unlike arthroplasty topics, capitellar fractures are not captured by joint registries (NJR, AJRR, AOANJRR, SHAR). The evidence base is case series plus one systematic review, which is why the Bryan-Morrey and Dubberley classifications and the Fisher meta-analysis carry disproportionate weight in any viva.
- High-resource settings: routine CT, headless compression screws, fellowship/elbow-unit referral for Dubberley B and Type IV patterns
- Limited-resource settings: conventional AO/buried Kirschner-wire or cannulated-screw fixation where headless implants are unavailable; CT may be limited
- Approach choice (lateral vs anterolateral vs transolecranon) varies by surgeon and fracture pattern, not by country
- Diagnosis on the lateral radiograph (double arc sign); AP often normal
- Bryan-Morrey and Dubberley classifications and what each grade changes
- Anatomic ORIF with anterior-to-posterior headless screws
- Early active motion to prevent stiffness; guarded prognosis for Type IV / Dubberley B
- Document that lateral X-ray was reviewed (not just AP)
- Document neurovascular status pre- and post-operatively
- Document PIN function (at risk during lateral / anterolateral approach)
- Consent must include: stiffness (most common), AVN, post-traumatic arthritis, need for further surgery, guarded prognosis for Type IV
- Missing fracture on AP view alone
- Delayed diagnosis leading to worse outcomes
- Inadequate rehabilitation instructions
Specific risks to discuss for capitellar ORIF:
- Stiffness (20-40%) - most common complication
- Post-traumatic arthritis (15-30%)
- AVN (5-10%)
- Heterotopic ossification (5-15%)
- PIN palsy - transient, usually recovers
- Need for further surgery - arthrolysis, hardware removal
- Guarded prognosis if Type IV - counsel specifically
MCQ Practice Points
Q: What does the 'double arc' sign on the lateral radiograph actually tell you? A: Two concentric semicircular arcs on the lateral view - the displaced capitellar fragment and the lateral trochlear ridge. Described by McKee, it does not merely say "capitellar fracture"; it says the coronal shear has extended medially into the trochlea, flagging the more complex patterns (Bryan-Morrey IV / higher-grade Dubberley) that need a wider exposure and often column support. Treat it as a rule-in sign only: plain radiographs underestimate the extent of these injuries in roughly a third of cases, so a lateral without a double arc does NOT exclude trochlear or posterior-column involvement - get the CT.
Q: In the Bryan-Morrey classification, which type has the worst prognosis and why? A: Type IV has the worst prognosis because it involves both the capitellum and trochlea, affecting both the radiocapitellar and ulnohumeral joints. This leads to higher rates of stiffness, arthritis, and poor functional outcomes.
Q: Why are headless screws placed from anterior to posterior in capitellar fixation? A: To preserve the blood supply. The capitellum has no soft tissue attachments anteriorly and receives blood supply only from posterior vessels. A-to-P screw placement avoids penetrating the articular surface posteriorly and preserves the posterior blood supply, reducing AVN risk.
Q: What is the most common complication after capitellar fracture fixation? A: Stiffness/loss of motion occurs in 20-40% of cases. The elbow is highly prone to contracture after trauma. Prevention requires anatomic reduction allowing early active ROM (start 48-72 hours), use of headless screws, and avoiding forced passive motion.
Q: What eponyms are associated with Bryan-Morrey Type I and Type II fractures? A: Type I = Hahn-Steinthal (large fragment with significant bone), Type II = Kocher-Lorenz (thin osteochondral shell with minimal bone). Memory aid: "H" for Huge fragment (Hahn-Steinthal), "K" for thin Kartilage (Kocher-Lorenz).
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 48-year-old woman presents after falling onto her outstretched hand with her elbow extended. She has lateral elbow pain and limited motion. AP X-ray shows only soft tissue swelling. How would you proceed?”
“A 35-year-old man involved in a motorcycle accident has a complex elbow injury. CT shows a capitellar fracture extending to involve the trochlea with moderate comminution. The radial head appears intact. Describe your classification and management.”
“You review a 45-year-old woman 3 months after ORIF of a Type I capitellar fracture. She has an arc of motion of only 45-100 degrees (55 degrees total) and is very frustrated. X-rays show united fracture with good reduction. How do you manage this?”
Key Facts
- 1% of elbow fractures, 6% of distal humerus fractures
- 4:1 female predominance, mean age 45 years
- FOOSH with extended elbow = coronal shear mechanism
- 30% have concurrent radial head fracture
Imaging
- LATERAL X-RAY IS KEY - AP often normal; plain films still underestimate extent, so CT always
- Double arc sign = displaced capitellum + LATERAL TROCHLEAR RIDGE (= medial extension, not just a capitellar fracture)
- AP view often NORMAL - don't be fooled
- CT for surgical planning - assess trochlea, comminution
Bryan-Morrey Classification
- Type I (Hahn-Steinthal): Large bony fragment - BEST prognosis
- Type II (Kocher-Lorenz): Thin osteochondral shell
- Type III: Comminuted - may need excision
- Type IV: Includes trochlea - WORST prognosis
Surgical Technique
- Kocher approach (lateral): between anconeus and ECU
- Headless compression screws (Herbert, Acutrak)
- ANTERIOR to POSTERIOR direction - preserves blood supply
- Countersink below cartilage for early ROM
Postoperative
- Early ROM is CRITICAL - start 48-72 hours
- Active motion only - avoid forced passive (HO risk)
- Hinged brace if stability concern
- Expect 10-20 degree loss of terminal extension
Complications
- Stiffness: 20-40% (MOST COMMON)
- Post-traumatic arthritis: 15-30%
- AVN: 5-10% (fix A-to-P to prevent)
- HO: 5-15% (prophylax high-risk patients)
Evidence Base
Dubberley Classification and Outcomes (Landmark)
- ORIF of 28 capitellar and trochlear fractures (mean age 43 years, mean follow-up 56 months). The classification that bears the authors' name was derived here: types defined by capitellar/trochlear pattern and presence or absence of posterior comminution. More complex fractures (separate fragments, posterior comminution) needed more extensive surgery, had more secondary procedures and poorer outcomes; mean Mayo Elbow Performance Index 91, mean arc 19 to 138 degrees, with two comminuted nonunions converted to total elbow arthroplasty.
Apparent Capitellum Fractures Are Often More Complex (Landmark)
- Retrospective series of 21 articular distal humeral fractures fixed with implants buried beneath the articular surface. Five recurring components were identified, including the lateral trochlear ridge and posterior column - so an apparently isolated capitellar fracture is frequently a more extensive coronal articular injury. All fractures healed; mean ulnohumeral arc 96 degrees; MEPI excellent or good in 16 of 21; ten required a second operation (six for contracture release).
Headless Compression Screw Fixation via Anterolateral Approach
- Prospective series of 16 capitellar fractures fixed with headless double-threaded compression screws through an anterolateral approach. Mean time to union 3.5 months with no malunion or nonunion; mean flexion 132 degrees, mean extensor lag 10 degrees; no osteonecrosis, post-traumatic arthritis or heterotopic ossification; 10 excellent and 6 good results.
Tailoring the Surgical Approach to Fracture Pathoanatomy
- Thirty-three capitellar fractures: Bryan-Morrey I to III approached by extended lateral; Dubberley 2A/3A by anterolateral; Dubberley 2B/3B by posterior transolecranon. All united (two with AVN). Mean flexion/extension arc 133 degrees, mean MEPI 80.9; poor results occurred only in Dubberley 3B fractures.
Surgical Approach and Pooled Complications (Systematic Review)
- Systematic review and meta-analysis of 45 studies (899 patients, mean age 44.9 years). Pooled reoperation rate 13.8%; post-traumatic arthritis 21.2%; heterotopic ossification 12.0%; nerve injury 7.8%; avascular necrosis 7.4%. Complication rate in non-comparative studies was 25.8% after the extended lateral approach versus 16.7% after the anterolateral approach for Dubberley A fractures, though evidence is insufficient to mandate one approach.