Proximal Tibiofibular Joint | Peroneal Nerve Risk | Often Missed
- Anterolateral (Type II) is MOST COMMON - fibula displaced forward and lateral
- Common peroneal nerve wraps around fibular neck - AT RISK in all types
- Closed reduction: knee flexed 90 degrees, direct pressure on fibular head
- Recurrent instability: may need PTFJ fusion or ligament reconstruction
- “Often missed - requires specific examination for lateral knee pain
- “Check peroneal nerve function BEFORE any reduction attempt
- “If irreducible: may have soft tissue interposition
- “Chronic instability more problematic than acute injury
Proximal Tibiofibular Joint Dislocations
Overview
Proximal tibiofibular joint (PTFJ) dislocations are rare and frequently missed at first presentation, so lateral knee pain needs a high index of suspicion. The joint lies just below the lateral knee and is held by the anterior and posterior tibiofibular ligaments; dislocation follows their disruption, and the fibular head most commonly goes anterolaterally.
The nerve. The common peroneal nerve wraps around the fibular neck just distal to the joint. Its function is documented before and after every reduction attempt.
The course. Most acute Type II and III dislocations reduce with closed manipulation. Irreducibility or persistent instability may need surgery, and some patients go on to recurrent instability that may require surgical stabilisation. Ogden's classification sorts the injuries by direction of displacement and mechanism.
Anatomy
The joint. A plane synovial joint in which the fibular head articulates with the posterolateral tibia. The articular surface is inclined at a variable angle, and its oblique orientation allows rotation.
The restraints, direct and indirect:
- Location
- Anterior joint
- Function
- Primary restraint to anterior translation
- Location
- Posterior joint
- Function
- Primary restraint to posterior translation
- Location
- Circumferential
- Function
- Secondary stabiliser
- Location
- Lateral
- Function
- Attaches to fibular head
- Location
- Posterolateral
- Function
- Attaches to fibular head
Joint variants. The horizontal type, with a more horizontal articular surface, is inherently more stable and the more common (70%). The oblique type is less stable and predisposes to instability.
The common peroneal nerve. It branches from the sciatic nerve in the popliteal fossa, winds around the fibular neck only 1-2cm from the joint, and divides into superficial and deep branches. It is at risk because it is superficial, tethered around bone and covered by little soft tissue. Traction during the dislocation can injure it, and so can the reduction manoeuvre.
Biomechanical Role of the PTFJ
Why fusion is tolerated but can cause ankle symptoms. The load-bearing role of the joint underpins the whole treatment logic. Classically (Ogden) the PTFJ has three biomechanical functions:
- Dissipation of torsional stress from the ankle - rotational forces generated at the ankle are transmitted up the fibula and absorbed at the PTFJ rather than concentrated at a single point
- Dissipation of lateral tibial bending moments - the fibula and PTFJ share the lateral bending load of the leg
- Transmission of a share of the axial (weight-bearing) load - the fibula bears part of the vertical load, greatest in ankle dorsiflexion when the mortise widens and the fibula is loaded
The trade-off. Normal PTFJ excursion is small, but it contributes to torsional accommodation between knee and ankle. Arthrodesis eliminates painful motion at this low-excursion joint and can relieve a painful unstable or arthritic joint, yet it removes that accommodation and may transfer stress distally, toward the fibula and ankle. It is therefore a salvage option rather than the default for every chronic instability, and motion-preserving ligament reconstruction is preferred when symptoms arise from instability in an active patient with a salvageable articular surface.
Classification Systems
Ogden described one subluxation pattern and three directions of dislocation. The numbering matters.
Type I, subluxation. Habitual or atraumatic instability with no fixed acute displacement. It usually occurs in younger patients with ligamentous laxity, and it may be bilateral or voluntarily reproducible.
Type II, anterolateral. The commonest true dislocation. The fibular head lies anterior and lateral to the tibial facet, often after a twisting injury with the knee flexed and the foot inverted and plantarflexed.
Type III, posteromedial. Uncommon and more difficult to reduce. A direct anterior blow or a violent rotational injury drives the fibular head posteriorly and medially, and the common peroneal nerve is especially vulnerable to traction or compression.
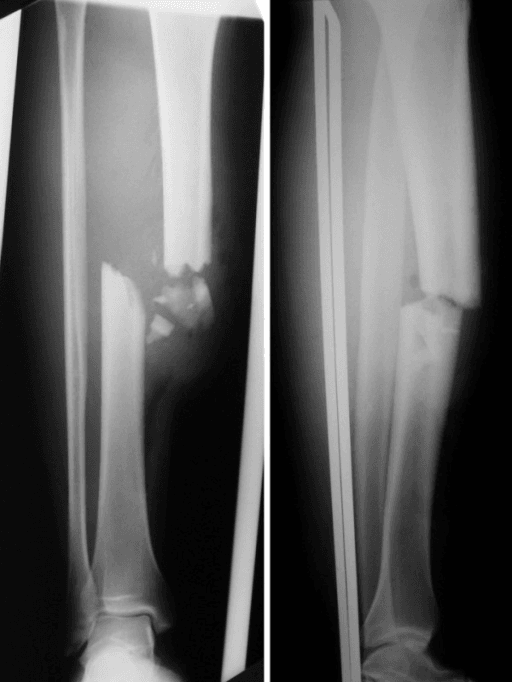
Type IV, superior. Proximal migration of the fibula accompanying major disruption of the tibial shaft, interosseous membrane or ankle syndesmosis. Do not call a routine proximal-fibular-shaft Maisonneuve fracture a PTFJ dislocation unless the joint itself is displaced.
Clinical Presentation
History. The patient reports lateral knee pain, a feeling of instability or of "something out of place", and pain on weight-bearing. The mechanisms:
- Twisting knee injury
- Direct blow to the fibular head
- Fall onto the flexed knee
- Sport, such as parachuting and football
Examination. The fibular head may be prominent anterolaterally, with lateral knee swelling, asymmetry against the other side and sometimes an obvious deformity. It is tender and mobile to palpation, always compared with the contralateral fibular head.
The nerve examination comes first. Document common peroneal function before any manipulation and compare it with the other side:
- Foot dorsiflexion (deep peroneal)
- Toe extension, EHL and EDL (deep peroneal)
- Foot eversion (superficial peroneal)
- First web space sensation
- Lateral leg sensation
- Heel-toe walking
Provocative tests. There is no validated radiographic threshold for subluxation, so the diagnosis of subtle or chronic instability rests on reproducible bedside signs compared with the uninjured side. How the tests are performed and interpreted matters.
Fibular-head translation (glide or ballottement). With the knee flexed to about 90 degrees to relax the LCL and biceps femoris, grasp the fibular head between thumb and index finger and translate it anteriorly and posteriorly. Excessive anteroposterior glide indicates instability, especially when it reproduces the patient's lateral knee pain or apprehension. Grade it against the contralateral fibular head, because normal laxity varies between individuals.
Cross-leg sign. With the patient seated and the affected leg crossed over the opposite knee (figure-of-four), the fibular head is thrown into prominence and lateral knee pain, or a sense of the head subluxing, is reproduced. Symptoms typically resolve when the leg is uncrossed. It is a useful bedside test for chronic anterolateral instability, where standard radiographs are frequently normal.
Provocative dorsiflexion-eversion. Active ankle dorsiflexion and eversion tension the biceps femoris and peroneal musculature and can provoke anterolateral subluxation of the fibular head in an unstable joint.
Reproducible fibular-head hypermobility plus a positive cross-leg sign, correlated with comparison radiographs, is more informative than any single static image in this diagnosis.
Investigations
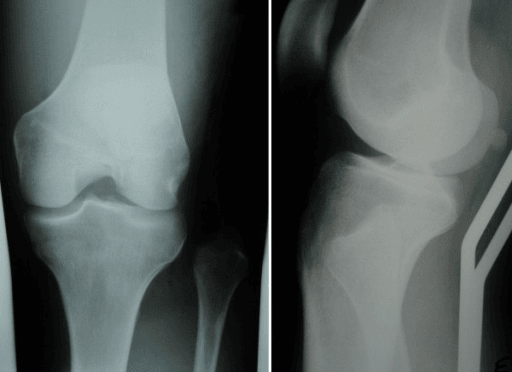
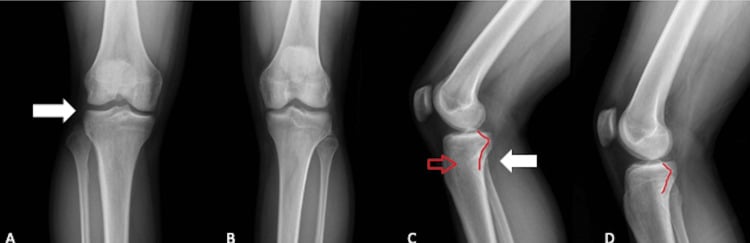
Radiographs. AP and lateral views of the knee, compared with the contralateral knee. Look at the position of the fibular head, its overlap with the tibia on the AP and its position on the lateral, and for associated fractures. In a Type II anterolateral dislocation the AP overlap decreases and the head sits anterior to the posterior tibial line on the lateral. The findings are subtle and the films may appear normal, which is why comparison views help.
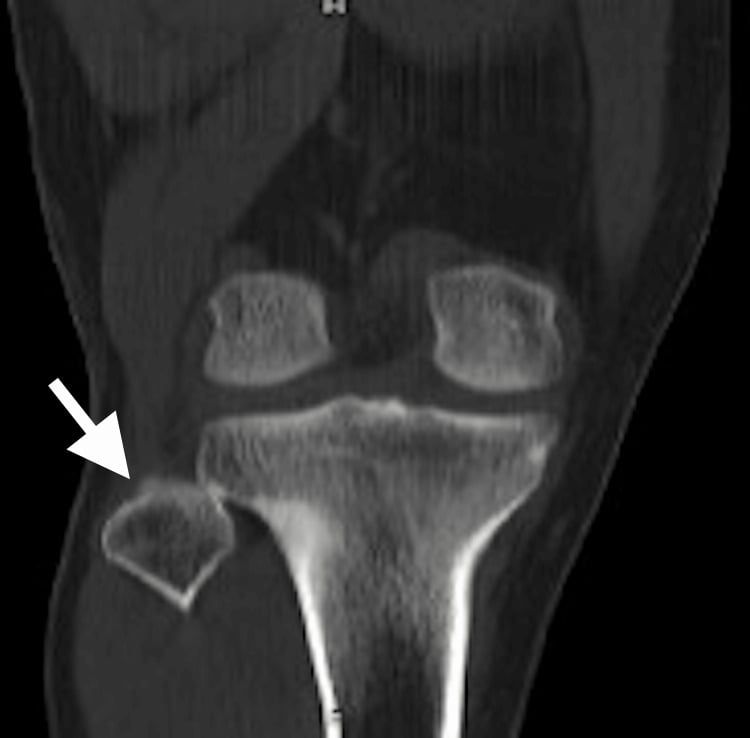
CT. For an uncertain diagnosis, associated fractures, surgical planning and the assessment of chronic instability. It earns its place when plain-film alignment remains equivocal or operative planning needs the displacement defined in two planes.
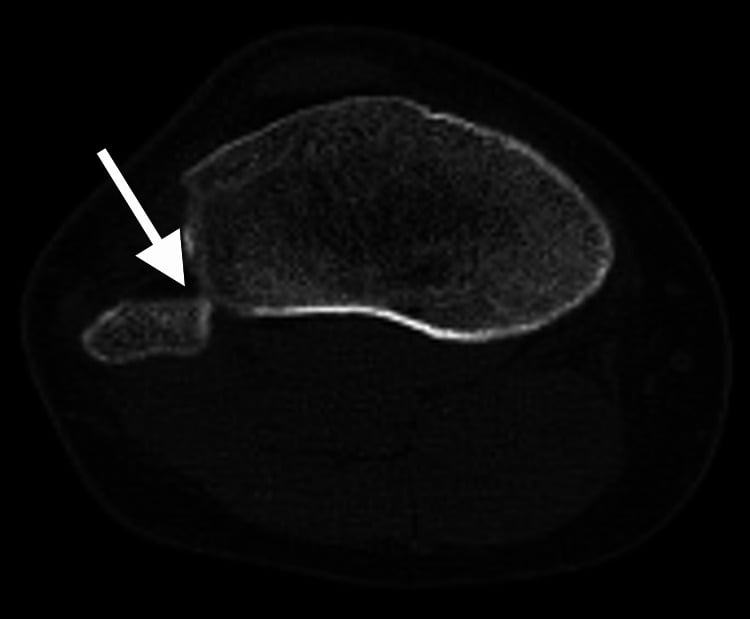
MRI. For ligament assessment, chronic instability and associated soft-tissue injury. It is not routine in the acute injury.
Differential diagnosis. Lateral knee pain with a prominent or mobile fibular head has several mimics. The key discriminators are the position of the fibular head on comparison radiographs and reproducible fibular-head hypermobility.
- Key Distinguishing Features
- Displaced or hypermobile fibular head; lateral knee pain; cross-leg test positive
- Confirmatory Test
- Comparison AP/lateral radiographs; CT if uncertain
- Key Distinguishing Features
- Varus laxity; pain over LCL, not the joint line of PTFJ; fibular head reduced
- Confirmatory Test
- Varus stress test; MRI
- Key Distinguishing Features
- Combined varus and external-rotation laxity; dial test positive at 30 degrees
- Confirmatory Test
- Dial test; MRI of PLC structures
- Key Distinguishing Features
- Foot drop/sensory loss without joint displacement; Tinel at fibular neck
- Confirmatory Test
- Nerve conduction studies; normal PTFJ radiographs
- Key Distinguishing Features
- Cortical break on radiograph; consider Maisonneuve if ankle tender
- Confirmatory Test
- Radiograph; full-length tibia-fibula views
- Key Distinguishing Features
- Joint-line tenderness; mechanical symptoms; fibular head normal
- Confirmatory Test
- MRI; McMurray test
- Key Distinguishing Features
- Posterolateral pain with resisted knee flexion; fibular head reduced
- Confirmatory Test
- MRI; clinical exam
Management Algorithm
Acute Type II or III: closed reduction first. Closed reduction usually succeeds when attempted early and becomes progressively harder with delay.
- Document dorsiflexion, great-toe extension, eversion and first-web-space sensation.
- Obtain AP and lateral knee radiographs; compare the opposite knee when alignment is subtle.
- Provide adequate analgesia or sedation, flex the knee to 90 degrees to relax the biceps femoris and lateral collateral ligament, and externally rotate the foot.
- Locate the fibular head precisely. For Type II anterolateral, with the ankle relaxed, push it posteriorly; for Type III posteromedial, push it gently anteriorly.
- Confirm reduction radiographically and repeat the nerve examination.
After a stable reduction. The patient enters protected weight bearing and rehabilitation. Most maintain reduction with 2-3 weeks of immobilisation, and less than 2 weeks is among the risk factors for recurrence; beyond that the duration is individualised, and prolonged rigid casting is not required routinely.
A nerve deficit. Reduce urgently and observe for recovery; the nerve pathway is under Complications.
Irreducible or unstable. A minority are irreducible closed, and the risk rises steeply with delay. The blocks to reduction:
- Soft-tissue interposition (biceps, capsule)
- Delayed presentation (more than 2 weeks)
- Associated fracture
- Fibular head button-holed through the fascia
Stop repeated forceful manipulation when the joint will not reduce or immediately redislocates. Through a lateral approach, identify and protect the common peroneal nerve before removing capsular, biceps-femoris or other interposed tissue, reduce under direct vision and repair the disrupted restraints when feasible. Temporary screw or flexible cortical-button fixation is reserved for persistent instability; implant choice and removal depend on the construct, the associated injury and the surgeon's strategy.
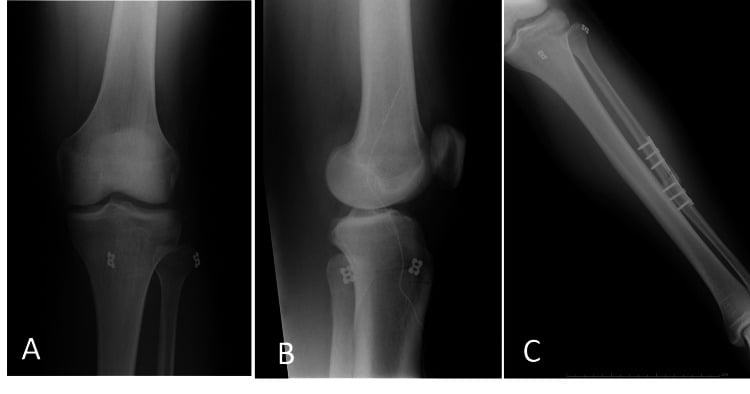
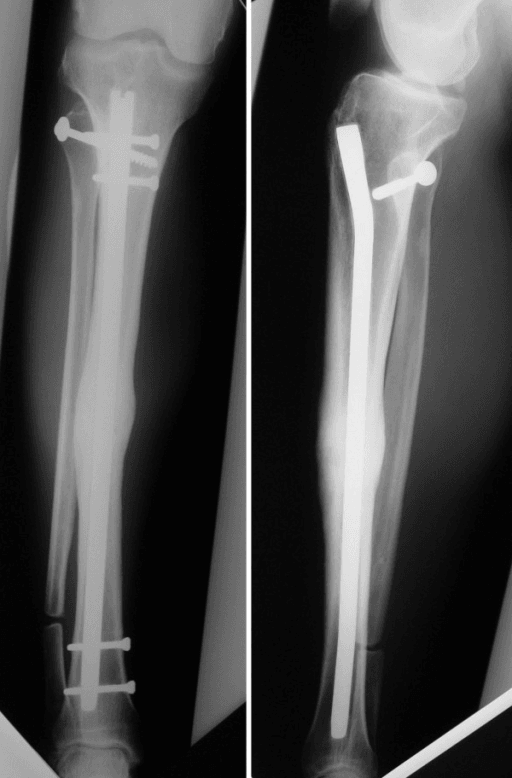
Type IV superior: treat the associated injury. Image the tibial shaft, the entire fibula and the ankle syndesmosis, then reduce and fix the tibial-shaft, ankle or syndesmotic injury as indicated. Reassess the PTFJ once the associated injury is restored, and add PTFJ stabilisation only if reduction is not maintained.
Chronic instability and Type I subluxation: rehabilitation before reconstruction. Confirm that the symptoms localise to the PTFJ, and exclude biceps-femoris snapping, peroneal neuropathy and posterolateral-corner pathology. Start with education, activity modification, strengthening and targeted rehabilitation, a trial of 3-6 months, with a brace when helpful and during sport. Operate only for disabling instability that persists despite structured non-operative care:
- Anatomic ligament reconstruction for patients who benefit from preserving motion
- Arthrodesis for painful arthrosis, failed reconstruction or low-demand salvage, because fusion transfers torsional stress distally
Fusion is described as the more durable of the two, though they have never been compared.
- Direction
- Habitual/atraumatic instability
- Management
- Rehabilitation; surgery only for disabling refractory symptoms
- Direction
- Fibula forward/lateral
- Management
- Closed reduction with posterior pressure
- Direction
- Fibula backward/medial
- Management
- Closed reduction with anterior pressure; higher nerve concern
- Direction
- Fibula migrates proximally
- Management
- Treat associated tibial-shaft or ankle/syndesmotic injury
- Direction
- Any type
- Management
- Open reduction, remove interposed tissue
- Direction
- Any type
- Management
- Urgent reduction, observe nerve recovery
- Direction
- Usually Type I subluxation or chronic post-traumatic instability
- Management
- Ligament reconstruction; arthrodesis is salvage
- Direction
- Type IV pattern
- Management
- Treat associated injury and confirm PTFJ reduction/stability
Surgical Technique
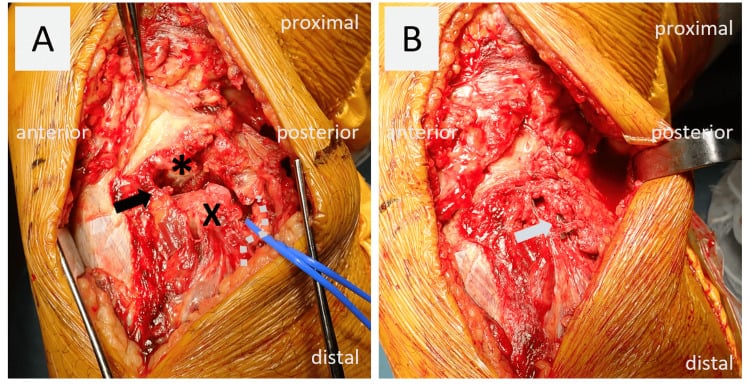
For the acute irreducible dislocation. The patient lies supine with a bump under the ipsilateral hip and the knee flexed over a bolster. A 6-8 cm longitudinal lateral incision is centred over the fibular head.
Approach.
- Incise skin and subcutaneous tissue.
- Identify and protect the common peroneal nerve.
- Incise the fascia anterior to the nerve.
- Reflect biceps femoris posteriorly.
- Expose the PTFJ capsule.
Reduction.
- Incise the capsule longitudinally.
- Remove any interposed soft tissue (biceps, capsule).
- Reduce the fibular head under direct vision.
- Repair the anterior and posterior tibiofibular ligaments.
- Consider a temporary 3.5mm screw if unstable.
Closure. Repair the capsule with absorbable sutures, then the fascia and skin, and apply a long leg splint in slight flexion.
Complications
Common peroneal nerve injury. Commonly quoted at around one in ten, but the figure comes from collected case reports and has no true denominator; the risk is highest in the posteromedial (Type III) injury.
- Neurapraxia - the usual pattern, and the reason most recover; most recover within 6-12 weeks
- Axonotmesis - slower, and recovery may take 3-6 months
- Neurotmesis - rare, and generally implies a more violent injury
Most reported nerve injuries are neurapraxias and recover; the proportion that does not is unknown. Observe a neurapraxia initially, with an ankle-foot orthosis for foot drop during recovery. Request EMG/NCS at 3-4 weeks if there is no clinical recovery, and explore if there is no improvement by 3 months, repairing or grafting the nerve if needed. A minority are left with mild residual weakness that usually does not limit function significantly. Permanent significant deficit is uncommon but described and may need tendon transfers or ankle fusion.
Recurrent instability. Recurrence after reduction is well described, particularly in atraumatic and hypermobile patients; no rate is established. A minority are affected, most within the first 6 months. The risk factors:
- Oblique joint variant
- Inadequate immobilisation (less than 2 weeks)
- Generalised ligamentous laxity
- Return to activity too early
- Inadequate rehabilitation
It is managed as chronic instability (see Management).
Chronic pain. Ongoing lateral knee pain is the commonest late complaint; no rate is established. It comes from articular cartilage damage at injury, residual microinstability, peroneal nerve irritation or post-traumatic arthritis. Treat with activity modification, physiotherapy and strengthening, a corticosteroid injection if there is localised synovitis, and fusion for severe refractory cases.
Other complications.
- Early: vascular injury (rare), compartment syndrome (rare), wound complications after surgery
- Late: post-traumatic arthritis (uncommon, and described as rare after closed reduction), hardware complications if a screw is used, non-union after fusion (reported but uncommon; no rate established)
Postoperative Care
After open reduction. Immobilisation runs 3-4 weeks, longer than after closed reduction.
- Protocol
- Long leg splint, knee in 15-20 degrees of flexion; non-weight bearing; ice, elevation and analgesia; check peroneal nerve function daily
- Protocol
- Hinged knee brace; gentle ROM; non- or touch weight bearing; physiotherapy begins
- Protocol
- Partial weight bearing; increase ROM; strengthening begins
- Protocol
- Remove temporary screw if placed; full weight bearing; continue strengthening
- Protocol
- Return to normal activities; sport-specific rehabilitation
After fusion.
- Protocol
- Long leg cast, knee in slight flexion; non-weight bearing; wound care; monitor for complications
- Protocol
- Remove cast; hinged brace; start ROM (fusion site stable); progressive weight bearing
- Protocol
- Continue strengthening; gradual return to activities; monitor fusion on radiographs
- Protocol
- Return to sport if fusion solid; resume full activities; minimal functional deficit expected
After ligament reconstruction.
- Protocol
- Long leg cast or locked brace; non-weight bearing; protect the reconstruction
- Protocol
- Unlock brace; gentle ROM; partial weight bearing; avoid stress on the reconstruction
- Protocol
- Full ROM goal; strengthening programme; full weight bearing
- Protocol
- Return to sport after functional testing
Red flags. Early: new foot drop (peroneal nerve injury), loss of reduction on the radiograph, wound infection, symptoms of compartment syndrome. Late: recurrent instability, persistent pain, hardware failure and, after fusion, non-union.
Outcomes/Prognosis
After closed reduction. Good to excellent results are what the case literature reports, but there is no cohort to give a percentage. Return to sport takes 8-12 weeks, and most patients return to their pre-injury level with minimal long-term deficit, occasionally with mild discomfort in extreme flexion.
After open reduction. Reduction is generally maintained and functional outcomes are good in most cases, though recurrence is described as somewhat more likely than after closed reduction. There may be mild stiffness initially, and return to sport takes 3-4 months.
After fusion. Union is generally achieved and is the expected outcome, most series reporting union by around three months; non-union is uncommon. A solid fusion gives permanent stability with minimal functional deficit, no significant gait abnormality and minimal restriction, and patients can return to high-level sport. Satisfaction is consistently reported as high, and fusion patients report excellent stability. Activities resume at 3-4 months; reported return to sport is 4-6 months, later than the 3-4 month protocol target.
After ligament reconstruction. Motion is preserved, which reconstruction patients value, and the joint may feel more "normal" than after fusion. It is described as less stable than fusion, with no comparative data. Outcomes are reported as good in the published cases, but no series is large enough to give a rate. Rehabilitation is longer (4-6 months) and needs compliance, and reported return to sport is 6-9 months, later than the 4-6 month protocol target.
Prognostic factors.
- Poor prognosis
- Delayed presentation
- Poor prognosis
- Posteromedial Type III injury with nerve deficit
- Poor prognosis
- Irreducible or recurrent instability
- Poor prognosis
- Oblique joint variant
- Poor prognosis
- Generalised ligamentous laxity
- Poor prognosis
- Multiple recurrences
The long view. No cohort has been followed to ten years; the longest published follow-up is a single bilateral case at nine and five years, in which both knees did well. Return to pre-injury sport is the usual reported outcome, though high-level athletes may take 6-12 months and contact sports may require longer, and satisfaction is reported as high in the published cases. Expect a good result after early recognition and reduction, and counsel that the evidence for that expectation is a body of case reports rather than a series.
Guidelines, Registries & Global Practice
Guidelines, Registries & Global Practice
Global Epidemiology
PTFJ dislocation is a rare injury - Ogden's original 1974 literature review identified only 108 reported cases, and few large series exist anywhere in the world. It is consistently under-recognised: lateral knee pain is frequently attributed to soft-tissue injury and the diagnosis missed at first presentation. Reported demographics across case series are similar internationally: young, active adults, with sport (skiing/snowboarding, parachuting, football codes, soccer) and high-energy trauma (with the superior/Maisonneuve pattern) the dominant mechanisms.
Guidelines - No Dedicated Society Guideline
Because the injury is rare, no orthopaedic society (AAOS, BOA/NICE, AO Foundation, EFORT) publishes a dedicated PTFJ-dislocation guideline. Practice is therefore derived from general acute joint-injury and trauma principles, which are consistent worldwide:
- Position on PTFJ Dislocation
- Document neurovascular status, closed reduction first, confirm with imaging, temporary trans-fixation/ORIF for irreducible or unstable joints
- Position on PTFJ Dislocation
- Early neurovascular assessment and documentation; timely reduction; orthoplastic input only if open/associated injury
- Position on PTFJ Dislocation
- No specific recommendation; supports reduction and immobilisation, surgery for recurrent instability
- Position on PTFJ Dislocation
- No dedicated statement; same principle-based approach
There is no implant registry data for this joint (no arthroplasty/standard implant is used), so registry evidence does not apply.
Areas of Consensus (Global)
- Peroneal nerve documentation before and after any manipulation is universal.
- Closed reduction is first-line for acute Type II and III dislocations.
- Temporary screw or flexible fixation is reserved for irreducible or persistently unstable injuries; implant strategy is case-specific.
- Reconstruction is motion-preserving; arthrodesis is salvage for arthrosis, failed reconstruction or selected low-demand patients.
High- vs Limited-Resource Practice Variation
- Well-resourced settings: CT/MRI available for diagnostic uncertainty and chronic instability work-up; arthroscopic-assisted or anatomic reconstruction techniques offered to preserve motion.
- Limited-resource settings: Diagnosis rests on comparison radiographs of both knees; closed reduction under sedation and, if needed, open reduction with screw transfixation are reliable, low-cost solutions with good reported outcomes (e.g. Fang et al. series).
Sport-Specific Considerations
- Skiing/snowboarding: classic mechanism - knee flexed, foot inverted, twisting fall.
- Parachuting/landing injuries: a classic mechanism for Type II anterolateral dislocation.
- Football codes / soccer: twisting tackles with a planted foot.
- Return to contact sport is typically 8-12 weeks after successful closed reduction, often with a hinged knee brace initially.
Related pages: Common Peroneal Nerve Anatomy explains why this joint is dangerous: the nerve winds round the fibular neck close to the displacing fibular head and must be documented before and after reduction; Superficial Peroneal Nerve Anatomy and Deep Peroneal Nerve Anatomy describe the branches that determine the deficit; Syndesmotic Instability covers associated ankle disruption; Knee Dislocation Management covers the different high-energy injury in which vascular assessment dominates.
Controversies & Areas of Uncertainty
Controversies & Areas of Uncertainty
The rarity of PTFJ dislocation means the evidence base is limited to case reports and small series (Level IV), with no randomised or comparative trials. Several practical questions remain unresolved.
Reconstruction preserves motion and is generally favoured for symptomatic instability in active patients with a salvageable joint. Arthrodesis can be reliable for painful arthrosis, failed reconstruction or low-demand salvage but transfers torsional load distally. No comparative trial defines superiority.
Whether a trans-fixation screw is needed after open reduction (vs ligament repair alone), and the optimal timing of removal (commonly 6-8 weeks), is based on case-series opinion, not trial data. Retained or broken hardware is a recognised concern.
Reported immobilisation after closed reduction ranges from a few days to 3 weeks. The trade-off between recurrence (too little) and stiffness (too much) is not defined by evidence.
Many habitual Type I subluxations are asymptomatic and best left alone. Surgery in hypermobile patients carries recurrence risk and is reserved for genuinely disabling symptoms that persist despite structured rehabilitation.
Diagnostic uncertainty: there is no validated radiographic measurement defining PTFJ subluxation, so subtle or chronic cases rely on comparison views and clinical hypermobility rather than an objective threshold.
Viva Scenarios
Viva Scenarios
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old parachutist lands awkwardly and presents with lateral knee pain. Examination shows a prominent fibular head anterolaterally. What is your diagnosis and management?”
“Describe the Ogden classification of proximal tibiofibular joint dislocations and the significance of the common peroneal nerve.”
“A patient has recurrent PTFJ instability despite conservative treatment. The joint subluxes with activity. What are your surgical options?”
MCQ Practice Points
Q: What is the most common true proximal tibiofibular joint dislocation? A: Ogden Type II, anterolateral. Type I is habitual/atraumatic subluxation, not the commonest acute dislocation. The fibular head displaces anteriorly and laterally, typically after a twisting injury with the knee flexed and the foot inverted and plantarflexed.
Q: Which Ogden pattern raises the greatest common-peroneal-nerve concern? A: Type III posteromedial dislocation. The nerve is vulnerable around the fibular neck in every traumatic pattern, so document motor and sensory function before and after reduction rather than relying on the classification alone.
Q: Which Ogden type describes superior PTFJ dislocation? A: Type IV. It accompanies major tibial-shaft or ankle/syndesmotic disruption. Image the entire leg and ankle, treat the associated injury and confirm that the PTFJ itself is reduced and stable.
Q: What must be documented BEFORE reducing a PTFJ dislocation? A: Common peroneal nerve function. Test foot dorsiflexion (tibialis anterior), great toe extension (EHL), and first web space sensation. The nerve is only 1-2cm from the PTFJ and at risk in ALL dislocation types.
Q: How do you reduce an anterolateral Type II PTFJ dislocation? A: Provide adequate analgesia or sedation, flex the knee to relax the lateral restraints, then apply direct posterior pressure to the fibular head. Confirm reduction radiographically and repeat the common-peroneal-nerve examination. A posteromedial Type III injury requires the opposite, anteriorly directed pressure.
Q: What is the operative strategy for recurrent PTFJ instability? A: In an active patient with a salvageable joint, anatomic ligament reconstruction preserves motion and is generally preferred after failed rehabilitation. Arthrodesis is salvage for painful arthrosis, failed reconstruction or selected low-demand patients; no comparative trial establishes a universally superior operation.
- Anatomic ligament reconstruction: motion-preserving option for symptomatic instability
- Arthrodesis: salvage for arthrosis, failed reconstruction or selected low-demand patients
- Temporary screw or cortical-button stabilisation: selected acute instability, not a universal chronic solution
- Reconstruction, arthrodesis and other salvage procedures are supported mainly by case reports and small series
- No comparative study establishes superiority or a reliable success percentage
- The practical trade-off is preserved motion versus the distal stress transfer of fusion
Common Exam Scenarios
"28-year-old parachutist with lateral knee pain after landing"
- Answer: Ogden Type II anterolateral PTFJ dislocation
"Patient with PTFJ dislocation that remains irreducible or immediately unstable"
- Answer: Stop forceful repeated manipulation; open reduction, nerve protection and selective stabilisation
"Recurrent symptomatic PTFJ instability despite structured rehabilitation"
- Answer: Consider motion-preserving ligament reconstruction; reserve arthrodesis for salvage
"Tibial-shaft or ankle/syndesmotic injury with proximal migration of the fibular head"
- Answer: Ogden Type IV superior PTFJ dislocation; treat the associated injury and reassess joint stability
"New foot drop after PTFJ reduction"
- Answer: Peroneal nerve injury from reduction maneuver
Key Numbers to Remember
- 8 of 12 - anterolateral share in the only series that counted directions (Fang 2012); the "70%" quoted in revision sources is this, rounded
- 90 degrees - Knee flexion for reduction
- 2-3 weeks - Immobilization duration
- 6-8 weeks - Screw removal timing
- No reliable percentage exists for reduction success, nerve injury, recurrence, fusion success or nerve recovery. The published evidence is 108 literature-collected cases from 1974, one 12-patient series, and a handful of single case reports - none of it capable of producing a rate. Say so in a viva; quoting a fabricated denominator is the error the examiner is listening for.
Examiner Favorites
"Why does knee flexion help with reduction?"
- Relaxes LCL and biceps femoris attachments to fibular head
"What structure is interposed in irreducible dislocations?"
- Biceps femoris tendon or joint capsule most common
"Why is PTFJ fusion well-tolerated?"
- Joint has minimal motion normally (less than 5 degrees)
- No significant functional deficit from fusion
"What predisposes to recurrent instability?"
- Oblique joint variant (more vertical articular surface)
- Inadequate immobilization duration
- Generalized ligamentous laxity
Exam Cheat Sheet
Exam Day Cheat Sheet
Classification (Ogden)
- Type I: Subluxation (habitual/atraumatic)
- Type II: Anterolateral (COMMONEST true dislocation)
- Type III: Posteromedial (greatest nerve concern)
- Type IV: Superior (associated tibial-shaft/ankle injury)
Peroneal Nerve
- Wraps around fibular neck
- At risk in ALL types
- Document function BEFORE reduction
- Test: dorsiflexion, toe extension, sensation
Reduction Technique
- Flex knee to 90 degrees
- Externally rotate foot
- Direct pressure on fibular head
- Type II: push posteriorly; Type III: push anteriorly
Post-Reduction
- Confirm reduction on XR
- Long leg cast 2-3 weeks
- Protected weight-bearing
- Monitor for recurrence
Surgical Indications
- Irreducible dislocation
- Recurrent instability
- Associated nerve injury requiring exploration
- Type IV instability after associated-injury fixation
Surgical Options
- Open reduction (acute irreducible)
- Ligament reconstruction (motion-preserving)
- PTFJ arthrodesis (salvage)
- Temporary screw or cortical-button fixation (selected acute instability)
Quick Reference: Key Points
- Details
- Type II (Anterolateral)
- Details
- Common peroneal
- Details
- Knee flexed 90 degrees
- Details
- 2-3 weeks
- Details
- Not established - reported in case series, no denominator
- Details
- Usually successful if attempted early; no cohort figure exists
- Details
- Case-report level only; arthrodesis loads the ankle and is a last resort
Ogden Classification Summary
- Pattern
- Subluxation
- Typical context
- Habitual/atraumatic laxity
- Nerve concern
- Low unless symptomatic instability
- Pattern
- Anterolateral
- Typical context
- Flexed-knee twisting injury
- Nerve concern
- Present; document before/after reduction
- Pattern
- Posteromedial
- Typical context
- Direct anterior blow/rotation
- Nerve concern
- Greatest concern
- Pattern
- Superior
- Typical context
- Tibial-shaft or ankle/syndesmotic injury
- Nerve concern
- Depends on associated trauma
Evidence
Evidence Base
Ogden Classification (Original Description)
- Cadaveric and clinical study describing PTFJ anatomy, biomechanics and a four-type classification (anterolateral, posteromedial, superior, atraumatic) from a literature review of 108 cases
Ogden - Subluxation and Surgical Management
- Companion paper detailing chronic subluxation, association with hypermobility/Ehlers-Danlos, and surgical options including arthrodesis and screw fixation for symptomatic recurrent instability
Early Diagnosis is Critical
- Bilateral fibular head dislocation case with 9- and 5-year follow-up; prompt recognition and early reduction were associated with good recovery, whereas delay complicates management