Age-Dependent Management | AVN Prevention Critical | Early Diagnosis Essential | 83.4% Pavlik Success (Abdulla)
- Age determines treatment: 0-6mo = Pavlik, 6-18mo = closed reduction, 18mo-3yr = open reduction, over 3yr = open reduction + osteotomy
- AVN is most devastating complication - always results from treatment, not disease. Prevention: avoid forced abduction (immobilisation at 60° or more raises AVN risk - Gardner), human position in spica
- Pavlik harness positioning: Flexion 100-110°, abduction 50-70°, wear 23 hours/day, monitor with ultrasound every 3-4 weeks
- Safe zone concept: Range between redislocation and AVN risk positions. Must be at least 25° for closed reduction to succeed
- Graf ultrasound classification: Type I (normal), II (immature/dysplastic), III (subluxed), IV (dislocated)
- “Know age-based treatment algorithm - examiners frequently test this
- “AVN prevention is key - describe human position (100° flexion, 40-50° abduction, neutral rotation)
- “Pavlik harness failure: discontinue if not reduced by 3-4 weeks to prevent AVN
- “Obstacles to reduction: psoas, ligamentum teres, pulvinar, limbus, transverse acetabular ligament, capsule, adductors
Overview and Epidemiology
Developmental dysplasia of the hip is the most common hip disorder in infants. Early diagnosis and age-appropriate treatment are essential to prevent long-term disability, AVN and early osteoarthritis.
Who. The incidence is 1 in 1000 live births, with a female predominance of 7:1 (relaxin sensitivity). The left hip is affected in 60% (fetal position) and both hips in 20%. DDH is commoner in Caucasian, Lapland and Native American populations.
Risk factors. Beyond female sex and ethnicity:
- Breech presentation - 20% of children with DDH were breech, against 2% of the population
- Family history - 12% if parents had DDH
- Firstborn
- Packaging disorders - torticollis, CTEV, metatarsus adductus
- Calcaneovalgus - 5% risk of associated DDH
Natural history. 1 in 60 is abnormal at birth, but 60% stabilise by one week and 88% by two months. Untreated DDH leads to abnormal gait, limb shortening and early osteoarthritis. The earlier treatment starts, the better the harness works; late treatment brings worse outcomes and a higher AVN risk, and may require multiple surgeries.
The epidemiology figures above (1:1000 incidence, 7:1 female ratio, left 60%/bilateral 20%, breech 20% vs 2%, family history 12%, calcaneovalgus 5%) are conventional teaching figures - none of the cited series measured them. The measured anchors on this page are Abdulla 2023 (83.4% normalisation), Pollet 2010 (Graf-dependent late reduction), Gardner 2014 (AVN 20-24%) and Bohm 2002 (90% revision-free at 35 yr); the natural-history figure (~90% of mild instability resolving by 8 weeks) follows Vaquero-Picado 2019.
Pathophysiology and Mechanisms
The spectrum. DDH runs from mild acetabular dysplasia to complete dislocation. The acetabulum is shallow, the labrum hypertrophies and inverts, the capsule is lax, the ligamentum teres elongates, fibrofatty pulvinar develops in the acetabulum, and the femoral head changes secondarily. Understanding these changes guides the treatment approach: the labrum, capsule, ligamentum teres and pulvinar each block reduction.
- Normal
- Deep, covers 50%+ of head
- DDH Changes
- Shallow, covers less than 50%
- Clinical Significance
- Reduced coverage, instability
- Normal
- Normal size, everted
- DDH Changes
- Hypertrophied, inverted
- Clinical Significance
- Blocks reduction, requires release
- Normal
- Normal tension
- DDH Changes
- Lax, hourglass constriction
- Clinical Significance
- Prevents reduction, requires release
- Normal
- Normal size
- DDH Changes
- Elongated, hypertrophied
- Clinical Significance
- Obstacle to reduction, excise
- Normal
- Minimal
- DDH Changes
- Fibrofatty tissue in acetabulum
- Clinical Significance
- Obstacle to reduction, excise
- Normal
- Spherical, centred
- DDH Changes
- May be flattened, displaced
- Clinical Significance
- Secondary changes from dislocation
The acetabulum. The acetabular index is 30° at birth and falls to 20° by 24 months; in DDH it is elevated and the acetabulum is shallow. The acetabulum can remodel up to 5 years of age. After that remodelling is limited, and an osteotomy may be needed.
The femoral head. A recently dislocated head may be normal. A chronically dislocated one flattens and loses sphericity. Ossification is delayed in the dislocated hip. Reduced early, it may remodel.
Classification Systems
Graf ultrasound. Graf grades the infant hip on two angles: the alpha angle, bony acetabular coverage, normal over 60°, and the beta angle, cartilaginous coverage, normal under 60°. Ultrasound is the imaging modality of choice under 4-6 months, because the cartilaginous head is not visible on X-ray.
- Alpha Angle
- Over 60°
- Beta Angle
- Under 60°
- Description
- Normal hip
- Treatment
- Observation
- Alpha Angle
- 43-60°
- Beta Angle
- 55-77°
- Description
- Immature or dysplastic
- Treatment
- Monitor or Pavlik
- Alpha Angle
- Under 43°
- Beta Angle
- Over 77°
- Description
- Subluxed
- Treatment
- Pavlik harness
- Alpha Angle
- Under 43°
- Beta Angle
- Over 77°
- Description
- Dislocated
- Treatment
- Pavlik harness
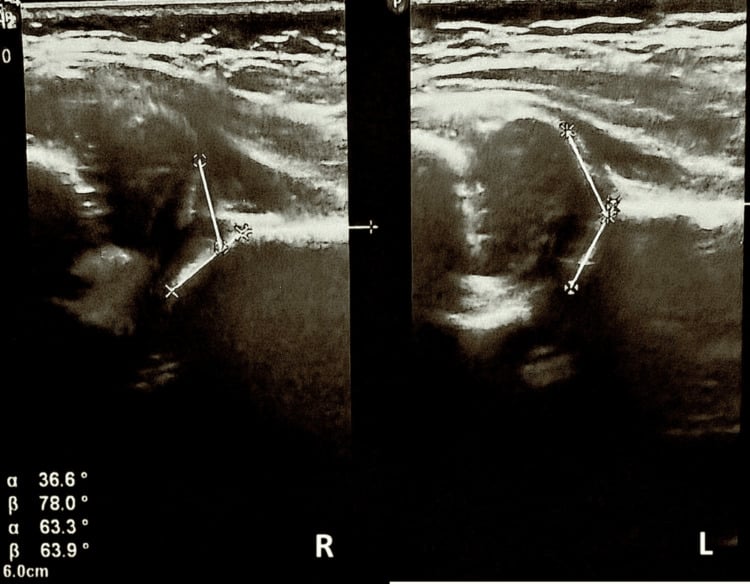
Radiographs. Once the femoral head ossifies, after 4-6 months, radiographs take over. Hilgenreiner's line runs horizontally through the triradiate cartilage and Perkin's line vertically through the lateral edge of the acetabulum.
- Normal
- 30° at birth, 20° at 24mo
- DDH
- Elevated, over 30°
- Clinical Significance
- Indicates dysplasia
- Normal
- Continuous arc
- DDH
- Broken
- Clinical Significance
- Indicates subluxation/dislocation
- Normal
- Over 20° (after age 5)
- DDH
- Under 20°
- Clinical Significance
- Indicates dysplasia
- Normal
- Under 25%
- DDH
- Over 25%
- Clinical Significance
- Head not covered by acetabulum
Clinical Assessment
The neonate. Two tests, both read by a clunk:
- Ortolani - abduction with gentle pressure over the greater trochanter; a clunk indicates reduction
- Barlow - adduction with posterior pressure; a clunk indicates subluxation
Both are reliable in the first three months and become unreliable after 2-3 months as the soft tissues tighten. The other signs are asymmetric creases, limited abduction (under 60°) and the Galeazzi sign, which works in unilateral cases only.
The older infant. After 3 months, limited abduction is the primary sign, and between 3 and 12 months abduction range and the Galeazzi sign are moderately reliable. A unilateral dislocation produces a limb length discrepancy. Asymmetric skin creases may be present but are not diagnostic.
The walking child. Over 12 months the child presents with a limp, limb length discrepancy and limited motion: a waddling gait when both hips are affected, a Trendelenburg gait when one is. Examination is less reliable at this age, and imaging is key.
Investigations
Ultrasound. Most useful from 4-6 weeks until the femoral head ossifies. Beyond the static Graf angles, a dynamic assessment evaluates stability during movement.
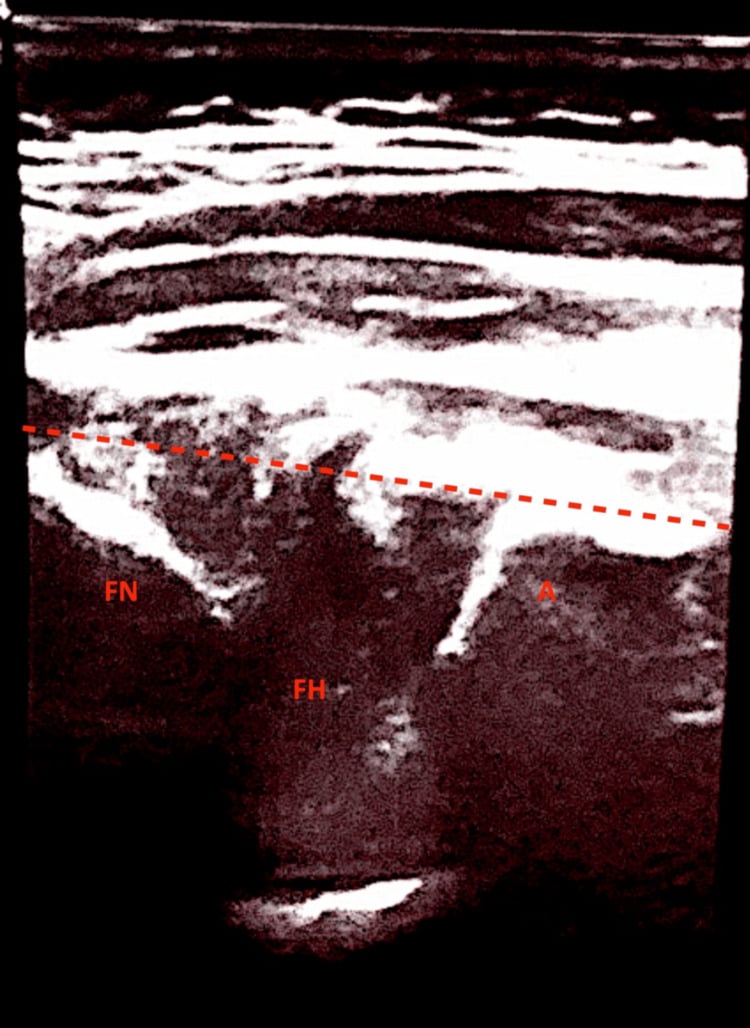
Radiographs. After 4-6 months:
- AP pelvis - acetabular index, Shenton's line, head position
- Frog-leg lateral - femoral head coverage, version
The acetabular index is normally under 30° at 1 year; the centre-edge angle is measured after age 5.
Arthrogram. Performed during the examination under anaesthesia for closed reduction, it shows the quality of the reduction and determines the safe zone, the abduction range that maintains reduction without AVN risk. A normal study shows a sharp labrum (the rose thorn sign) and minimal medial pooling. An abnormal one shows a widened medial joint space (pooling over 5mm), a blunted labrum and an hourglass constriction.
Differential Diagnosis
DDH itself is reducible or dislocatable, with a shallow acetabulum and no fixed deformity.
- Key Distinguishing Feature
- Reducible/dislocatable, shallow acetabulum, no fixed deformity
- Investigation
- Ultrasound (Graf), AP pelvis
- Why It Matters
- Index diagnosis - reversible if treated early
- Key Distinguishing Feature
- Fixed, irreducible at birth; syndromic (arthrogryposis, myelomeningocele)
- Investigation
- Exam, screen for neuromuscular cause
- Why It Matters
- Will NOT respond to Pavlik; needs surgery and a different prognosis
- Key Distinguishing Feature
- Short femur, abnormal proximal femur, not simply dislocated
- Investigation
- Radiograph of whole femur
- Why It Matters
- Limb reconstruction problem, not a reduction problem
- Key Distinguishing Feature
- Pain, fever, raised inflammatory markers, pseudoparalysis
- Investigation
- Aspiration, bloods, ultrasound effusion
- Why It Matters
- Surgical emergency; late sequela can mimic dysplasia
- Key Distinguishing Feature
- Decreased neck-shaft angle, vertical physis, Trendelenburg
- Investigation
- AP pelvis (Hilgenreiner-epiphyseal angle)
- Why It Matters
- Femoral-side problem, different osteotomy
- Key Distinguishing Feature
- Spasticity, progressive subluxation, GMFCS-related
- Investigation
- Hip surveillance radiographs (migration %)
- Why It Matters
- Salter contraindicated; needs Dega-type and soft-tissue surgery
A teratologic dislocation is irreducible from birth and is associated with arthrogryposis, myelomeningocele and other syndromes. Attempting Pavlik or forced closed reduction wastes time and risks AVN. Always examine for fixed deformity, contractures and neurological signs before committing to conservative reduction.
Management Algorithm
Age decides the treatment. The first-line treatment by age band:
- 0-6 months: Pavlik harness - first-line for dislocatable and dislocated hips
- 6-18 months: closed reduction - examination under anaesthesia, arthrogram and spica
- 18 months-3 years: open reduction - when closed reduction fails, with femoral shortening if the hip is tight
- Over 3 years: open reduction with osteotomy - open reduction is always required, with a femoral varus and shortening osteotomy and a pelvic osteotomy for residual dysplasia; more complex, with a higher complication risk
The Graf type decides the harness's odds. Abdulla's 83.4% sonographic normalisation spans all Graf types; the rate is far higher in Graf II and far lower in Graf III/IV. An earlier start favours success, mean age 6.7 weeks in successes against 8.8 weeks in failures. The conventional age ceiling for the harness is 6-7 months, but Pollet trialled a progressively applied harness in late-diagnosed dislocated hips aged 6-24 months, and the results again split by Graf type (table).
What the evidence does not give you. No series reports a success rate for closed or open reduction. For closed reduction the endpoints are intraoperative, an adequate safe zone and a concentric arthrographic reduction; for open reduction the reported harm is AVN. Over 3 years there is no comparative series; Bohm's Salter osteotomies supply the long-term figures.
- Age
- 0-6 months
- Technique
- Flexion 100-110°, abduction 50-70°, monitor with USS
- What the cited evidence reports
- 83.4% sonographic normalisation across all Graf types (Abdulla, n=265)
- Age
- 6-24 months (closed reduction conventionally 6-18 months)
- Technique
- EUA with arthrogram, safe zone over 25 degrees, human position
- What the cited evidence reports
- Harness reduced 60% of Graf III (6/10) and 0% of Graf IV (0/7) (Pollet, n=26 hips); no published closed-reduction success rate
- Age
- Under 12 months (9-12 months)
- Technique
- Ludloff/Ferguson approach
- What the cited evidence reports
- No success-rate series; AVN after MEDIAL open reduction 20%, rising to 24% at maturity (Gardner, 734 hips)
- Age
- Over 12 months
- Technique
- Smith-Petersen approach
- What the cited evidence reports
- No published rate
- Age
- Over 3 years
- Technique
- Femoral shortening/varus + pelvic osteotomy
- What the cited evidence reports
- Salter at mean age 4.1 yr: 90% revision-free at 35 yr, but 21% failed on the wider endpoint (Bohm, n=73)
Surgical Technique
Indications. The harness is used for:
- Graf type III or IV (subluxed or dislocated)
- Age 0-6 months (maximum 6-7 months)
- Dislocatable hip on examination
Application. The chest strap sits at the nipple line, snug but not tight. The anterior strap controls flexion at 100-110° and the posterior strap abduction at 50-70°, so the hip is held flexed and abducted while active motion is allowed. The harness is worn 23 hours a day initially, and the parents are taught application and care.
Monitoring. Ultrasound every 3-4 weeks checks for reduction and for improvement in the Graf type, and the straps are adjusted as needed.
Stopping. A hip that reduces is weaned gradually over 2-4 months as it stabilises. A hip not reduced by 3-4 weeks comes out of the harness to prevent AVN and goes on to closed reduction; Pollet tolerated up to 6 weeks with a gentle progressive protocol (see Controversies).
Complications.
- AVN - from forced abduction; discontinue if not reduced
- Pavlik disease - posterolateral acetabular wear from treatment in the unreduced position
- Recurrence - ~10% conventional figure after successful treatment (no measured rate in the cited series)
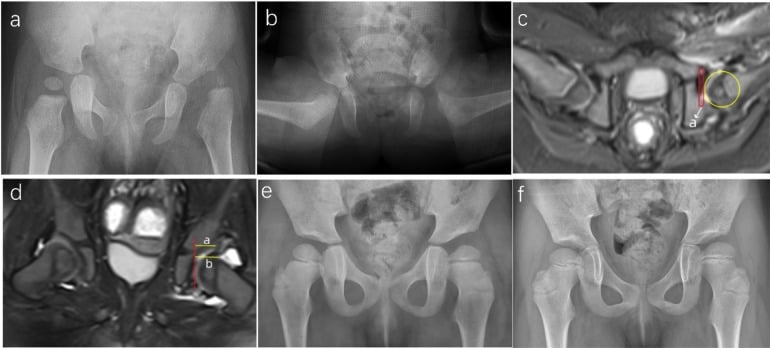
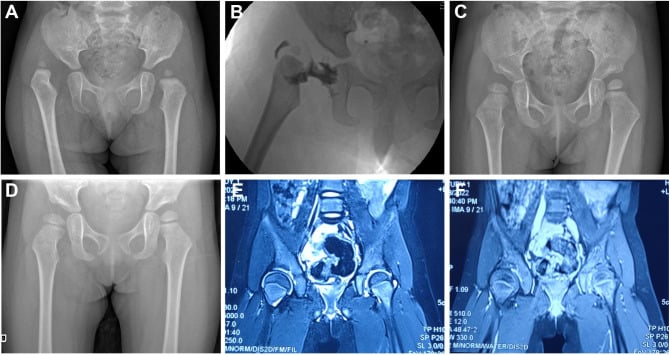
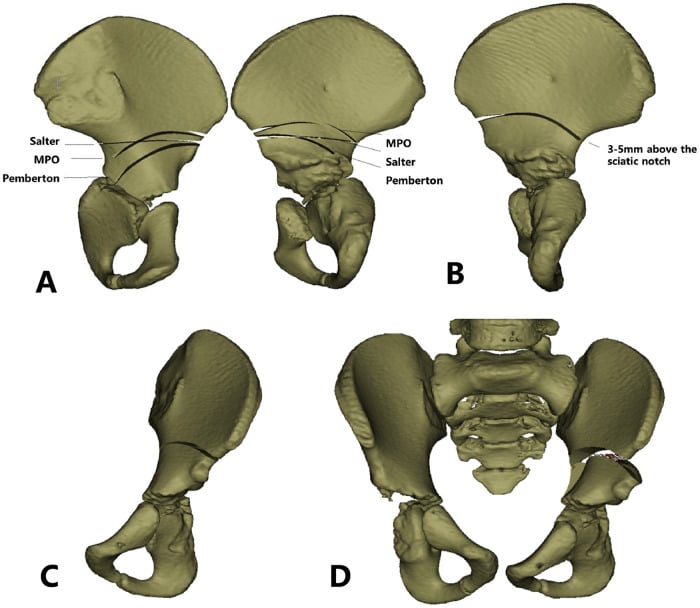
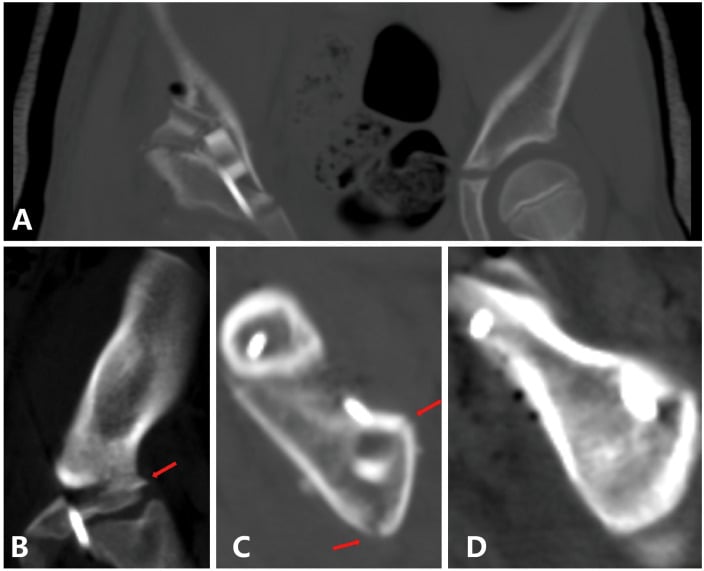
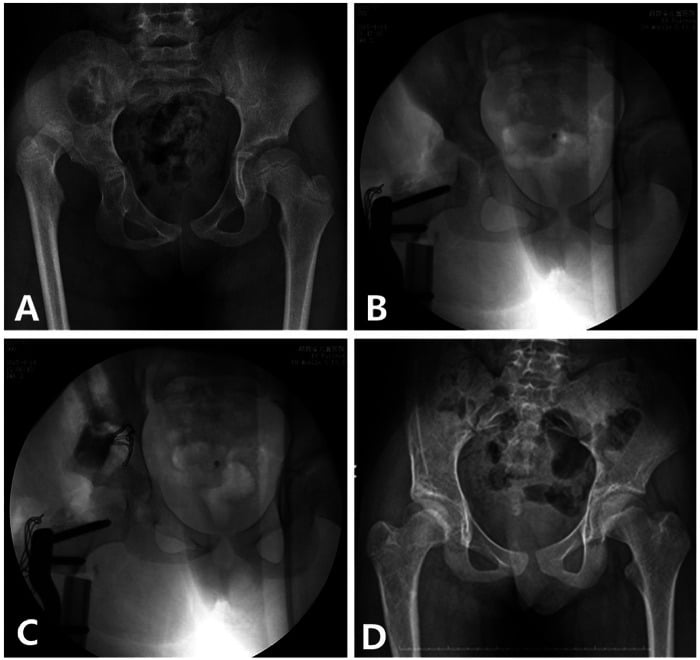
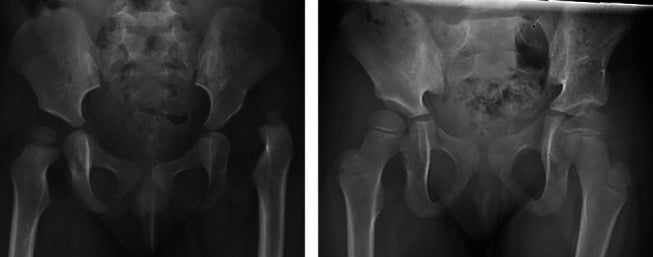
Complications
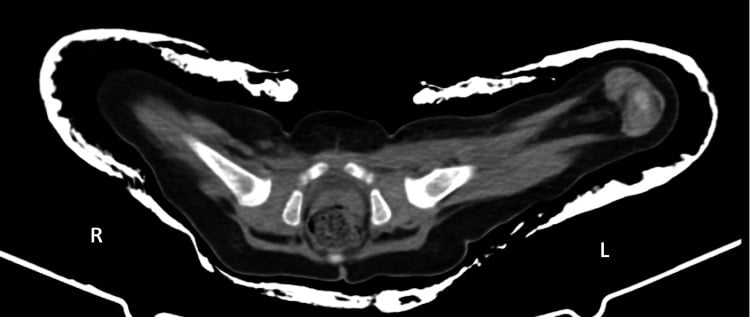
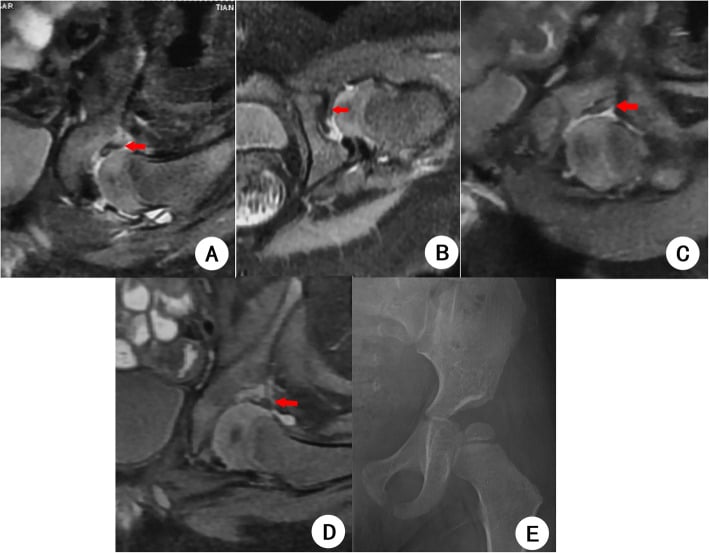
Avascular necrosis. The most devastating complication, and it always results from treatment, not the disease. Preventing it is the most important principle in DDH treatment.
- Pavlik harness - 0% of reduced hips (Pollet 2010); 5-10% conventional range
- Closed reduction - ~20% conventional (Salter type 1)
- Open reduction - medial approach 20% measured, rising to 24% at skeletal maturity (Gardner 2014, 734 hips); anterior approach 10-20% conventional
- Open reduction with osteotomy - 15-25% conventional
What causes it. Forced or extreme abduction: immobilisation at 60° or more measurably raised AVN in Gardner's review. Extreme abduction combined with internal rotation and extension, multiple reduction attempts and early rigid casting add to the risk. Prevention follows: a gentle reduction technique, avoiding multiple reduction attempts, the human position in the spica, and a harness discontinued when the hip has not reduced.
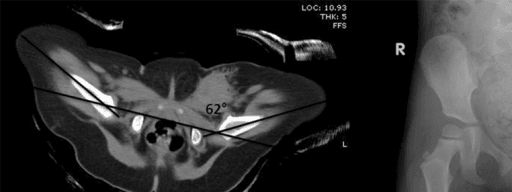
Grading. Kalamchi-MacEwen grades the damage by the part of the head and physis involved:
- Class I - nucleus only; will be normal
- Class II - lateral physis; coxa valga from lateral physeal fusion
- Class III - central; moderate deformity
- Class IV - whole physis; severe deformity, poor outcomes
Established AVN. Managed with containment procedures, and may need later salvage. Monitor for growth disturbance, coxa magna, coxa breva and coxa vara.
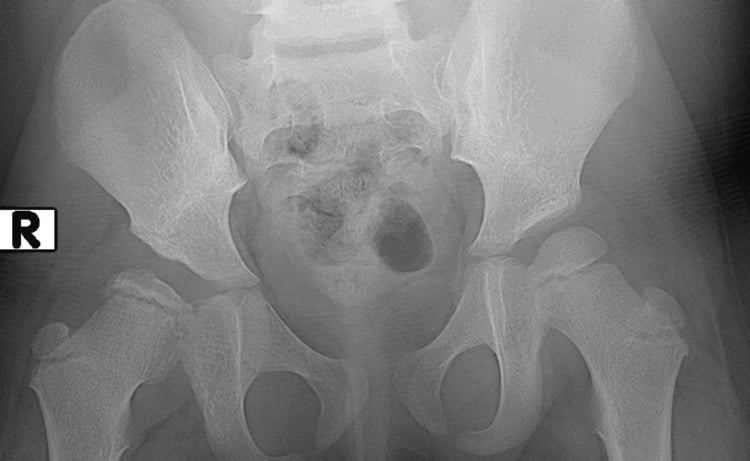
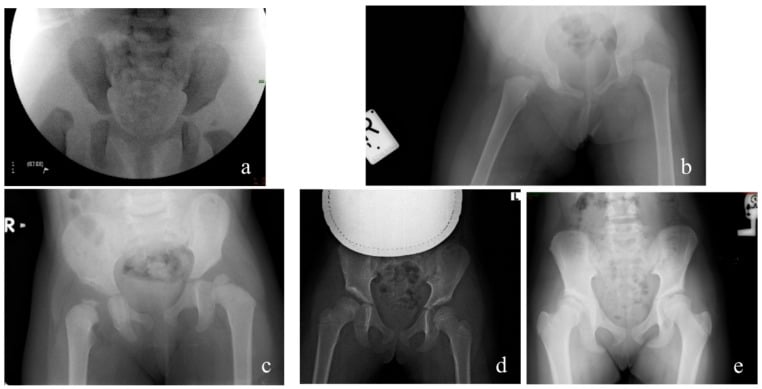
Redislocation. Conventionally quoted at 5-10% of closed reductions (no measured rate in the cited series). An inadequate safe zone, poor positioning and cast problems are the risk factors, and it is managed by repeat closed reduction or open reduction.
Stiffness. May occur after open reduction. It usually improves with time and physiotherapy, and may require manipulation or arthrolysis if severe.
Limb length discrepancy. May occur with unilateral DDH. It is usually mild (under 2cm) and may require later equalisation if significant.
Early osteoarthritis. Even successfully treated DDH carries an increased risk, and it may require total hip arthroplasty in adulthood.
Residual Acetabular Dysplasia After Reduction: the Remodelling Window and When to Add an Osteotomy
A concentric reduction is itself the main treatment for the acetabulum. Residual dysplasia may occur despite a successful reduction and requires monitoring with serial radiographs. Acetabular development depends on a concentrically reduced femoral head providing the growth stimulus, so achieving and holding a concentric reduction lets the majority of acetabular dysplasia remodel spontaneously. The trajectory of the acetabular index over serial radiographs is the best predictor of persistent dysplasia: an index steadily falling toward normal can be observed, whereas one that plateaus or stays high will not correct on its own.
How long to wait. Most acetabular improvement occurs in the first 18-24 months after reduction, with useful remodelling potential continuing to about 4-5 years. A reasonable rule is to observe with serial films while the index is improving. Consider a pelvic (acetabular) procedure once it is clear that spontaneous correction has stalled, with an acetabular index over 30° or a centre-edge angle under 20° persisting beyond the expected window (typically after about age 3-5), rather than operating on every high index early.
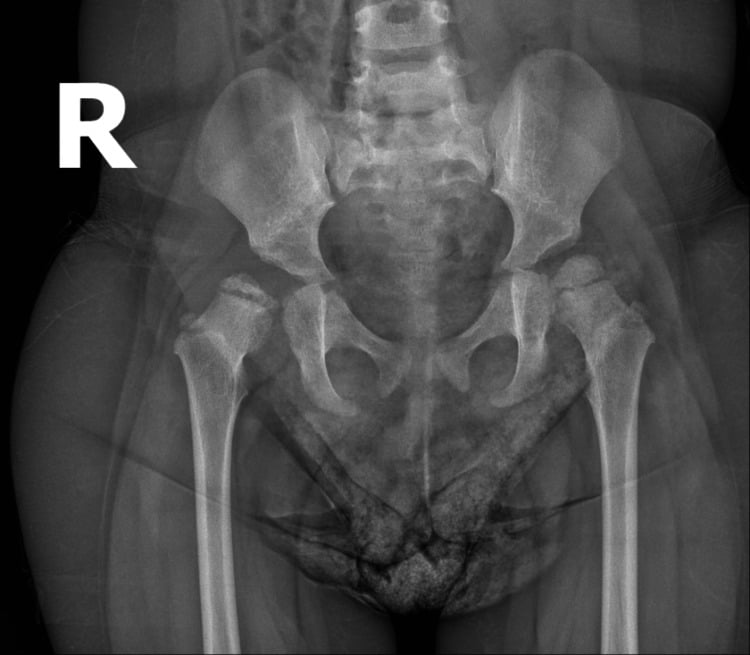
Which osteotomy. The triradiate cartilage and the deformity decide. With it open, in a young child, a reshaping acetabuloplasty (Pemberton, or Dega for posterior deficiency) or a redirectional Salter innominate osteotomy is used; once it closes, a redirectional periacetabular (Ganz) osteotomy is required. A coexisting femoral deformity (excess anteversion or valgus) may need a varus derotation femoral osteotomy alongside.
Concentric and AVN-free first. As the long-term Salter data show, durability depends on a concentric, AVN-free reduction. A pelvic osteotomy corrects persistent structural dysplasia; it cannot rescue a non-concentric or AVN-damaged hip, so fix the reduction before the osteotomy, or reserve or stage it.
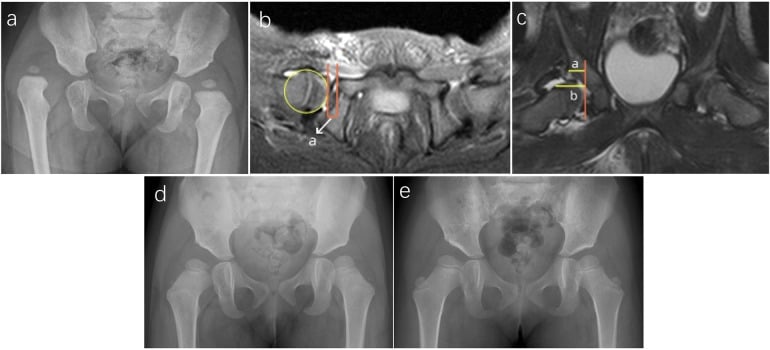
Postoperative Care
After open reduction. A spica for 3 months, changed at 6 weeks, then physiotherapy once the cast is off. Serial radiographs watch for AVN, which may present late.
To skeletal maturity. Follow-up continues until the skeleton is mature, looking for AVN, residual dysplasia and redislocation, and following acetabular development and femoral head shape. The acetabular index should normalise by age 2-3 years, and the centre-edge angle is assessed after age 5.
- Radiographs at 6 months, 1 year and 2 years
- Then annually until skeletal maturity
Outcomes and Prognosis
What predicts a good hip. Early diagnosis, and a concentric reduction achieved without force or extreme abduction. Late diagnosis correlates with worse outcomes.
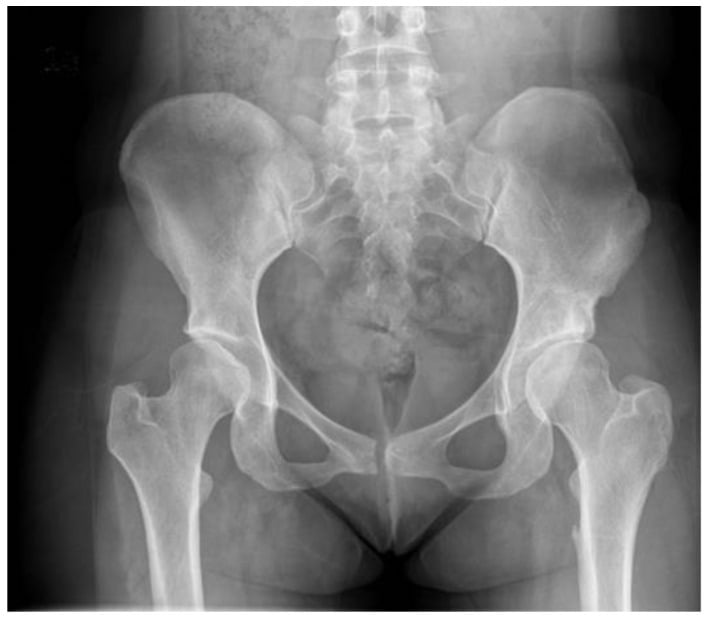
Guidelines, Registries & Global Practice
- Incidence: Wide range (0.06 to 76 per 1000) depending on definition and screening intensity; clinically significant DDH ~1 per 1000
- Highest prevalence: Native American, Lapland/Sami, and other swaddling cultures (tight hip extension)
- Lowest prevalence: Populations carrying infants in abduction (parts of Africa and Asia)
- Consistent risk factors worldwide: Female sex, breech, family history, firstborn, oligohydramnios
- Clinical screening: Universal newborn Ortolani/Barlow is endorsed across all major societies
- Selective ultrasound: Risk-factor plus abnormal-exam based - UK NIPE, BOA, and most European programmes
- Universal ultrasound: Standard in Austria and parts of Germany/Switzerland (Graf); reduces late surgery but increases harness treatment
- AAOS (US): Conditional recommendation for imaging surveillance of at-risk infants rather than universal ultrasound
- Imaging Approach
- Selective imaging of at-risk infants; no universal ultrasound
- Treatment Emphasis
- Pavlik or rigid abduction brace first-line under 6 months
- Imaging Approach
- Universal clinical exam + selective ultrasound (risk factors, abnormal exam)
- Treatment Emphasis
- Brace under 6 months; closed/open reduction thereafter
- Imaging Approach
- Universal ultrasound screening of all newborns
- Treatment Emphasis
- Early ultrasound-guided abduction treatment, low late-surgery rate
- Imaging Approach
- Selective ultrasound with mandatory clinical screening
- Treatment Emphasis
- Avoid forced abduction; staged reduction by age and severity
DDH is the single largest cause of hip osteoarthritis requiring total hip arthroplasty in young adults, accounting for 21-29% of total hip replacements in young people (Vaquero-Picado 2019, citing arthroplasty registry data). This long-term burden - not short-term reduction success - is the real justification for early diagnosis and AVN-avoiding treatment.
- High-resource settings: Newborn ultrasound capacity, early Pavlik, arthrogram-guided reduction, MRI-confirmed spica position, multidisciplinary follow-up to maturity
- Limited-resource settings: Reliance on clinical exam and late radiographs, higher rate of neglected/late-presenting dislocation, greater use of traction and open reduction with osteotomy
- Universal principle everywhere: Gentle concentric reduction in the human position, avoiding immobilisation at 60° or more of abduction (Gardner), remains the AVN-avoidance standard regardless of resources
Controversies and Areas of Uncertainty
Universal or selective ultrasound. Universal newborn ultrasound treats infants earlier and makes surgery less likely, but it markedly increases harness treatment (overtreatment of physiologically immature hips), and in the cited cohort it did not reduce delayed presentation. Selective screening avoids overtreatment but depends on reliable clinical examination. No global consensus exists; practice tracks resources and historical programmes.
Static or dynamic devices. The Pavlik harness allows active motion within a safe range, whereas rigid abduction braces (von Rosen, Tübingen, Plastazote) provide more fixed control. Evidence does not clearly favour one device, and rigid braces are often used as second-line after Pavlik failure or for non-compliant families rather than as proven superiors.
When to abandon the harness. The classic teaching is to abandon it if the hip is not reduced within 3-4 weeks, to limit AVN and Pavlik disease. Some series tolerate up to 6 weeks with a gentle progressive protocol. The unifying principle is that a persistently dislocated hip inside a harness causes posterior acetabular wear and must not be left.
Concurrent or staged osteotomy. In older children, whether to perform the pelvic or femoral osteotomy at the same sitting as the open reduction or in a staged fashion is debated. Long-term Salter data suggest that performing open reduction first and reserving or staging the osteotomy improves durability, but single-stage surgery is widely practised to limit anaesthetics.
The painless bilateral dislocation in the older child. In a walking child with bilateral, painless, completely dislocated hips presenting late (e.g. over 4-6 years), the morbidity of bilateral open reduction and osteotomy (stiffness, AVN, redislocation) may exceed the natural history of well-tolerated bilateral dislocation for many years. Whether to operate, operate on one side, or observe remains genuinely controversial and is individualised to symptoms, function and family expectations.
MCQ Practice Points
Q: What success rate should you quote for the Pavlik harness, and why does the question have to specify the Graf type? A: 83.4% overall, but the number is meaningless without the type. In the largest cited cohort (265 infants, all Graf types) 83.4% normalised sonographically, and Graf III and IV independently predicted failure. In late-diagnosed dislocated hips the harness reduced 60% of Graf III (6 of 10) and none of 7 Graf IV. So the harness is highly effective for the dysplastic-but-located hip, moderately effective for Graf III, and close to futile for Graf IV. Earlier is better - mean age at start was 6.7 weeks in successes against 8.8 weeks in failures. Beware the commonly quoted "95%": it describes mild early-detected dysplasia and is not a figure any cited series reports for Graf III/IV.
Q: The most devastating complication of DDH treatment is: A: Avascular necrosis (AVN) - AVN is the most devastating complication, causing femoral head deformity and growth disturbance. It always results from treatment, not disease.
Q: What is the maximum abduction angle in spica cast to minimize AVN risk? A: Keep abduction in the 40-50° human position - Gardner's systematic review (734 hips) measured increased AVN with post-operative immobilisation at 60° or more of abduction. There is no separately validated 55° threshold; the sourced danger line is 60°.
Q: At what age does acetabular remodeling potential significantly decrease? A: 5 years - Acetabular remodeling potential exists up to 5 years. After this, limited remodeling occurs and osteotomy may be required.
Q: Which approach is preferred for open reduction of DDH in a 10-month-old child? A: Medial approach (Ludloff/Ferguson) - Conventional choice under 12 months (bilateral access easy, adductor release included, no abductor damage) - but do not claim it is safer: Gardner's systematic review measured 20% AVN after medial open reduction (24% at skeletal maturity), and surgery under 12 months independently increased the risk.
Q: What is the minimum safe zone required for successful closed reduction? A: 25° - Safe zone under 25° is associated with high failure and AVN risk. Adductor tenotomy may widen safe zone.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 3-month-old infant presents with Graf Type IV DDH (dislocated hip). You decide to use Pavlik harness. Describe your management approach including positioning, monitoring, and when you would discontinue treatment.”
“An 8-month-old infant with DDH failed Pavlik harness treatment. You perform examination under anaesthesia with arthrogram. The arthrogram shows medial pooling of 8mm and a safe zone of only 15°. Discuss your management.”
“A 2.5-year-old child presents with untreated unilateral DDH. The hip is dislocated and irreducible. Discuss your management approach including surgical technique and expected outcomes.”
Age-Based Treatment Algorithm
- 0-6 months: Pavlik harness (83.4% normalise; far less in Graf III/IV)
- 6-18 months: Closed reduction + spica (no published success rate)
- 18 months-3 years: Open reduction (AVN 20% after the medial approach)
- Over 3 years: Open reduction + osteotomy (Salter 90% revision-free at 35 yr, 21% failed on the wider endpoint)
Pavlik Harness Management
- Positioning: Flexion 100-110°, abduction 50-70°
- Wear: 23 hours/day initially
- Monitoring: Ultrasound every 3-4 weeks
- Discontinue if not reduced by 3-4 weeks (prevents AVN)
- Success depends on Graf type: 83.4% overall, 0 of 7 Graf IV in the cited series
AVN Prevention - Critical Principles
- Human position: 100° flexion, 40-50° abduction, neutral rotation
- Immobilisation at 60° or more abduction measured to increase AVN (Gardner); use the 40-50° human position
- Gentle reduction - forced reduction causes AVN
- Discontinue Pavlik promptly if reduction fails
- AVN always results from treatment, not disease
Safe Zone and Closed Reduction
- Safe zone: Range between redislocation and AVN risk
- Minimum 25° required for closed reduction success
- Medial pooling over 7mm = poor outcome predictor
- Adductor tenotomy may widen safe zone
- If safe zone inadequate after tenotomy → open reduction
Obstacles to Reduction
- Psoas tendon (release)
- Ligamentum teres (excise)
- Pulvinar (excise)
- Inverted limbus (may need release)
- Transverse acetabular ligament (release)
- Capsule hourglass constriction (incise)
- Adductors (tenotomy)
Graf Classification
- Type I: Normal (alpha over 60°, beta under 60°)
- Type II: Immature (may resolve)
- Type III: Subluxed (needs treatment)
- Type IV: Dislocated (needs treatment)
- Ultrasound under 4-6 months (cartilaginous head)
Open Reduction Approaches
- Medial approach (Ludloff/Ferguson): under 12 months; measured AVN 20%, 24% at maturity (Gardner) - not the oft-quoted 10%
- Anterior approach (Smith-Petersen): Over 12 months, 10-20% AVN risk
- Medial preserves blood supply better in infants
- Anterior allows pelvic osteotomy if needed
Pelvic Osteotomies
- Salter: Redirectional, young children
- Pemberton: Reshaping, under 8 years
- PAO (Periacetabular Osteotomy): Adolescent/adult
- Indicated if acetabular index over 30° or center-edge angle under 20°
AVN Rates by Treatment
- Pavlik harness: 0% if reduced (Pollet); 5-10% conventional
- Closed reduction: ~20% conventional (Salter type 1)
- Open reduction: medial 20% measured, 24% at maturity (Gardner); anterior 10-20% conventional
- Late presentation: Higher complication rates
- AVN is most devastating complication
Key Principles
- Early diagnosis and treatment essential
- Pavlik normalises 83.4% overall - but Graf III/IV predict failure
- Age-based treatment algorithm critical
- AVN prevention is paramount
- Address all obstacles to reduction
Evidence Base
Pavlik Harness Success and Failure Predictors
- Overall Pavlik success 83.4% across all Graf types
- Earlier start (mean 6.7 vs 8.8 weeks) favours success
- Frank dislocation and Graf III/IV independently predict failure
- Femoral nerve palsy is a marker of excessive flexion and impending failure
Pavlik Harness in the Late-Diagnosed Dislocated Hip (6-24 Months)
- Graf III hips can still reduce in older infants (60%)
- Graf IV (frankly dislocated) success was 0% - do not persist
- No AVN in successfully reduced hips with gentle progressive technique
- Abandon the harness if not reduced by ~6 weeks
Risk Factors for Failed Pavlik Reduction
- Higher initial dislocation (small distance A) predicts failure
- Acetabular angle over 36° predicts failure
- Age over 4 months at application predicts failure
- Quantifies the case selection that favours Pavlik success
AVN After Medial Open Reduction - Systematic Review
- Medial open reduction AVN rate ~20% (24% at maturity)
- AVN nearly triples the unsatisfactory outcome rate
- Immobilisation at 60° abduction or more increases AVN
- Surgery under 12 months independently increases AVN risk
Salter Innominate Osteotomy - 26-35 Year Follow-up
- 90% survival of the Salter osteotomy at 35 years
- AVN and residual dysplasia drive long-term failure
- Higher dislocation grade predicts worse outcome
- Stage open reduction before pelvic osteotomy when both needed
Universal vs Selective Ultrasound Screening
- Selective screening did not increase true late diagnoses
- Universal screening increases treatment rate (overtreatment)
- Universal screening shifts treatment earlier and less invasive
- Trade-off between overtreatment and avoiding late surgery
DDH Management - Contemporary Review (AVN Mechanisms)
- ~90% of mild neonatal instability resolves by 8 weeks
- Ortolani-positive hip requires immediate treatment
- AVN linked to excessive abduction and forced reduction
- Acetabular index evolution best predicts residual dysplasia