Not Just a 'Small Adult Bunion'
- Don't operate for cosmetic reasons: operate for pain, never for appearance.
- High Recurrence: Warn parents explicitly.
- DMAA: The articular surface is often tilted (Dysplasia). Correcting the shaft without correcting the DMAA leads to recurrence or stiffness.
- Congruency: Most juvenile deformities are congruent (joint lines parallel).
- Physes: Must respect open growth plates.
- “Assess Hypermobility (Beighton Score)
- “Check for Flatfoot (Pes Planus exacerbates valgus)
- “Assess Congruency (Can you correct it passively?)
- “Look for Metatarsus Adductus (increases deformity perception)
Overview and Epidemiology
Juvenile hallux valgus is hallux valgus that begins before skeletal maturity, usually under 14-16 years. It is distinct from congenital hallux valgus, which is present at birth, and from adult acquired hallux valgus.
Who. Girls, overwhelmingly: around 88% of Coughlin's series were female, and 40% presented at age 10 or younger.
Inheritance. Familial penetrance is high, with an autosomal dominant pattern of incomplete penetrance. Maternal transmission was recorded in 72% of patients in Coughlin's landmark cohort.
- Juvenile HV
- Genetic / Dysplasia (DMAA)
- Adult HV
- Degenerative / Shoes
- Juvenile HV
- Usually Congruent
- Adult HV
- Usually Incongruent (Subluxated)
- Juvenile HV
- Common
- Adult HV
- Less Common
- Juvenile HV
- Common, and rises with length of follow-up
- Adult HV
- Low (less than 10%)
Pathophysiology and Mechanisms
The primary deformity. Juvenile hallux valgus is often related to metatarsus primus varus, medial deviation of the first metatarsal, and the varus of the first metatarsal is the primary deformity. Ligamentous laxity allows the first ray to drift medially while the toe stays laterally.
The articular tilt. The distal metatarsal articular angle (DMAA) defines the orientation of the cartilage of the metatarsal head relative to the shaft. In juveniles the surface is often dysplastic, tilted laterally, and because the cartilage itself is tilted the joint surfaces remain parallel, or congruent, despite the valgus appearance. An elevated DMAA was present in roughly half of juvenile cases, and it is higher in early-onset and congruent-joint deformities.
Why the DMAA decides the operation. In adults the hallux valgus angle comes from subluxation of the joint; in children it often comes from the shape of the bone. Straighten the shaft by moving the head laterally without changing the tilt, and the toe points medially on a joint that is now incongruent. The toe then drifts back into valgus to make the joint congruent again, so a simple chevron that ignores the DMAA looks straight at first but leaves a joint that is incongruent and stiff, or a deformity that rapidly recurs.
What drives progression. Five risk factors are recognised:
- Female sex
- Generalised ligamentous laxity
- Anatomy: a high DMAA and metatarsus primus varus
- A tight or contracted tendo-Achilles (gastrocnemius)
- Constrictive footwear, the extrinsic factor
The physes. The first metatarsal physis is proximal, at the base, unlike the lesser metatarsals, whose physes are distal; the proximal phalanx physis is also proximal. A distal chevron or Mitchell osteotomy is therefore performed distal to the physis, though care must still be taken not to violate it while it is open. A proximal osteotomy (base wedge) or a scarf puts the physis at risk.
Pes Planus and the Pronated Foot: Driver or Innocent Bystander?
The case for a driver. A planovalgus, pronated foot carries the hindfoot into valgus and the forefoot into abduction, which unlocks the midtarsal joint and destabilises the medial column. The first ray becomes hypermobile, the windlass mechanism is blunted, the IMA is effectively increased, and the ground reaction force drives the first metatarsal into varus while the hallux drifts laterally. That makes a flat, pronated foot a plausible driver of the bunion and, if left uncontrolled, a plausible cause of recurrence after correction.
The counter-evidence. In Coughlin's juvenile series, moderate-to-severe pes planus occurred in only 17%, no different from the normal population, and there were no recurrences in the feet with pes planus. He concluded that pes planus did not affect the occurrence or recurrence of juvenile hallux valgus, so its causal role is debated, not established.
The practical position. Correct the heel valgus on examination and see whether the bunion improves; if it does, there is a dynamic, pronation-driven component. Orthoses that control pronation offload the medial column and may reduce that component, but they relieve symptoms rather than cure the bunion. Do not over-attribute the bunion to the flatfoot, promise that an orthosis will cure it, or let a flatfoot by itself dictate surgery.
Classification Systems
- HVA
- less than 20
- IMA
- less than 11
- Treatment
- Observation
- HVA
- 20-40
- IMA
- 11-16
- Treatment
- Distal osteotomy (chevron)
- HVA
- greater than 40
- IMA
- greater than 16
- Treatment
- Proximal osteotomy or Lapidus
Clinical Assessment
History. Establish where the pain is: over the medial eminence, or inside the joint. Cosmesis is often the driving factor for the parents or the teenager, and expectations need to be managed firmly. Ask whether the mother has bunions, and how her surgery went.
Examination. Each step answers a question that shapes the plan:
- Standing: assess hindfoot valgus and arch height, and perform the heel-correction test described above
- First ray mobility: check for sagittal-plane hypermobility, and score generalised laxity with the Beighton score
- Congruency test: reduce the hallux valgus angle to neutral and watch whether the toe rotates or the range of motion decreases. If motion is blocked when the toe is straight, the joint is congruent and the DMAA high
- Grind: crepitus suggests arthritis, which is rare
- Forefoot: look for metatarsus adductus, which increases the perceived deformity
Investigations
Weightbearing radiographs are mandatory. They give the angles that grade the deformity and choose the osteotomy, and they show whether the physes are open:
- Hallux valgus angle (HVA): between the first metatarsal and the proximal phalanx; abnormal over 15°
- Intermetatarsal angle (IMA): between the first and second metatarsal shafts; abnormal over 9°
- DMAA: the tilt of the articular surface on the shaft, measured as below
- Physeal status: open or closed
Measuring the DMAA. Draw the axis of the first metatarsal, then a line joining the medial and lateral margins of the articular surface; the angle between them is the DMAA. Normal is under 10°, with the cartilage facing straight. An angle over 15-20° is abnormal, the cartilage facing laterally, and in juvenile hallux valgus it is often 20-30°, which is dysplastic.
Sesamoid view. Shows subluxation of the sesamoids and rotation of the metatarsal head. Crista erosion is rare in children.
Management
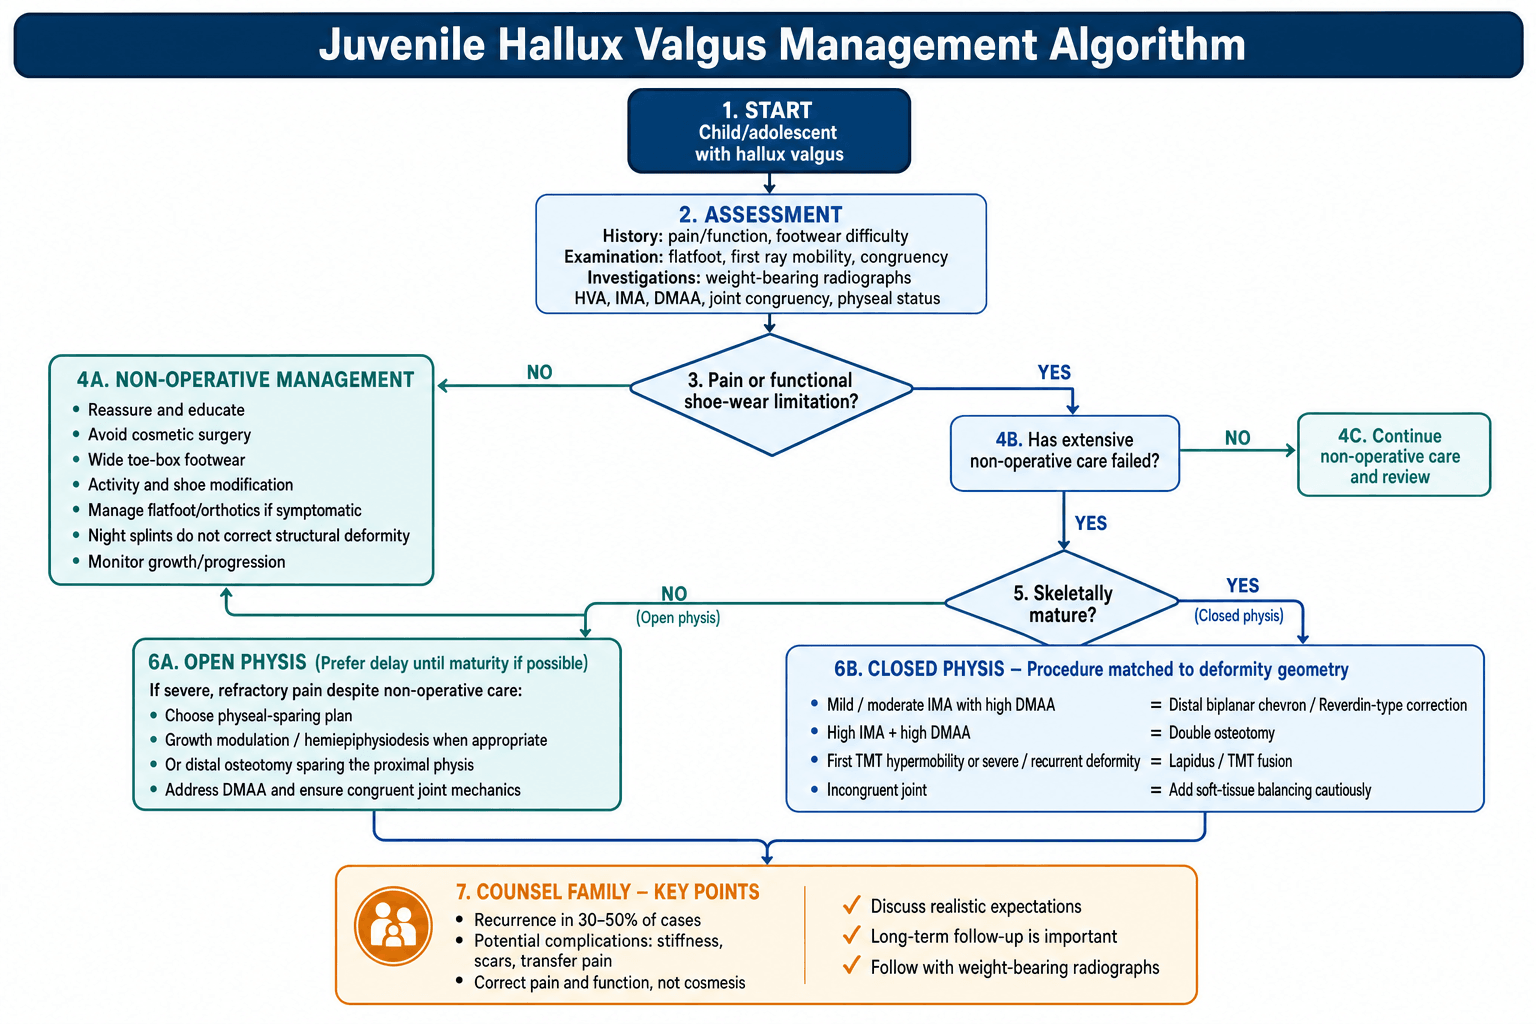
Non-operative care is the gold standard. Surgery should only be considered once it has failed extensively, and before maturity it is the default:
- Education: explain the high recurrence rate after surgery
- Shoes: a wide toe box; avoid heels
- Orthotics: correct a dynamic valgus or flatfoot; they offload the medial column but do not cure the bunion
- Night splints: do not correct the structural deformity
Indications for surgery. Pain is the indication, never appearance, and correction after skeletal maturity is best:
- Severe pain interfering with daily activities and refractory to shoe modification
- Inability to wear any reasonable shoes
- Ulceration over the medial eminence, which is rare
The physis sets the options. With an open physis, the choices are growth modulation by hemiepiphysiodesis or a distal osteotomy that spares the physis. With a closed physis, adult-type osteotomies are tailored to the IMA and the DMAA.
Surgical Techniques
Indication. A high HVA, a high IMA and a high DMAA together: the multi-planar deformity.
- Proximal osteotomy corrects the IMA, bringing the first metatarsal closer to the second. An opening wedge adds length; a closing wedge shortens.
- Distal osteotomy, a biplanar chevron, corrects the DMAA and the pronation.
Together they correct both the strut angle and the articular tilt.
Hallux valgus interphalangeus. A distinct deformity: valgus angulation within the hallux itself, distal to the metatarsophalangeal joint at the level of the proximal phalanx and interphalangeal joint. It is measured by the hallux valgus interphalangeus angle, between the long axes of the proximal and distal phalanges, and usually arises from a trapezoidal, asymmetric proximal phalanx whose distal articular surface is tilted into valgus. It is common in juveniles and adds to the apparent lateral deviation of the toe, but a metatarsal osteotomy does nothing to it, and missing it is a common reason a great toe still looks bent after the metatarsal has been corrected.
The Akin osteotomy corrects it with a medial closing wedge of the proximal phalanx. It is an adjunct, never a stand-alone bunion operation: used alone it straightens the toe cosmetically while leaving the metatarsus primus varus, the high DMAA and any MTP subluxation uncorrected, so the bunion persists and recurs. It is added to a metatarsal procedure to fine-tune the final alignment once the IMA and DMAA have been addressed.
- Corrected by Akin?
- Yes
- Note
- Medial closing wedge of the proximal phalanx realigns the toe
- Corrected by Akin?
- No (only the appearance)
- Note
- An extra-articular phalangeal cut does not address MTP subluxation
- Corrected by Akin?
- No
- Note
- Needs a metatarsal osteotomy
- Corrected by Akin?
- No
- Note
- Needs a head-reorienting osteotomy (biplanar chevron/Reverdin)
Complications
In Coughlin's series overcorrection into hallux varus was as common as recurrence, so quote both when consenting.
- Rate
- Common, and higher with longer follow-up (6 of 60 feet in Coughlin; 23% at median 6.5 years in Bard)
- Prevention/Management
- Don't operate early. Correct the DMAA. Address pes planus, though its role in recurrence is debated.
- Rate
- 6 cases in Coughlin's 60 feet, as many as recurred
- Prevention/Management
- Excessive lateral release.
- Rate
- Common
- Prevention/Management
- Intra-articular dissection or uncorrected incongruency.
- Rate
- Rare
- Prevention/Management
- Damage to the blood supply (lateral/dorsal) during distal stripping.
- Rate
- Common
- Prevention/Management
- Thin soft tissues in children.
Postoperative Care
- Immobilisation: heel-wedge shoe or cast for 6 weeks
- Weightbearing: heel weightbearing is usually allowed if the osteotomy is stable
- Radiographs: at 2 weeks for position and 6 weeks for union
- Return to sport: 3-4 months
Outcomes and Prognosis
Satisfaction is generally lower than in adults, because of unrealistic cosmetic expectations and stiffness. Most return to sport, but range of motion is often permanently reduced compared with normal. Recurrence is the major long-term issue, and many require revision in adulthood.
Guidelines, Registries & Global Practice
Global epidemiology
- Strong female preponderance (around 80-90% across series) and frequent positive family history with maternal transmission. There is no implant registry for juvenile hallux valgus, so evidence rests on retrospective cohorts and small comparative series.
Society guidance, side by side There is no dedicated international guideline for juvenile hallux valgus; recommendations are extrapolated from paediatric forefoot and adult bunion consensus. Common threads across bodies:
- Position emphasised
- Surgery for pain and functional impairment, not cosmesis; match procedure to deformity geometry (IMA, DMAA, congruency).
- Position emphasised
- Conservative management until skeletal maturity where possible; explicit recurrence counselling.
- Position emphasised
- Respect the proximal first-metatarsal physis; stable internal fixation of osteotomies.
- Position emphasised
- No single osteotomy proven superior; individualised, deformity-specific correction.
Practice variation by resource setting
- High-resource: Weightbearing radiographs, biplanar/double osteotomies with screw fixation, and growth-modulation (hemiepiphysiodesis) for selected young patients.
- Limited-resource: Greater reliance on simple distal osteotomies with Kirschner-wire fixation and percutaneous/minimally invasive (e.g. SERI) techniques where fluoroscopy is available; emphasis on conservative management and footwear given cost and follow-up constraints.
Controversies and Areas of Uncertainty
Timing of surgery. Whether to operate before skeletal maturity for severe symptomatic deformity, or to wait and reduce recurrence, remains debated. Comparative data (Bard et al, 2024) show recurrence and complications are common regardless of physeal status, which supports a cautious, pain-driven threshold.
The optimal osteotomy. No single osteotomy is proven superior. Edmonds et al (2015) found that double osteotomy corrects all three angles best but overcorrects the DMAA most often, while a single distal osteotomy is the most consistent, with the fewest complications.
Hemiepiphysiodesis. Growth modulation carries little morbidity, but the radiographic correction is modest. Patient selection is critical, favouring young age, adequate remaining growth and a predominantly IMA deformity, and outcomes are variable.
Hypermobility and the Lapidus. Whether a hypermobile first ray mandates a first tarsometatarsal fusion in adolescents is unsettled. The procedure risks the physis and is generally deferred to maturity or to recurrence.
Minimally invasive techniques. Percutaneous, SERI and other MIS osteotomies report good short-term results, but long-term comparative evidence in skeletally immature patients is limited.
DMAA reliability. The angle has substantial inter-observer variability and is sensitive to rotation on radiographs, which complicates both classification and surgical planning.
MCQ Practice Points
Q: Where is the growth plate (physis) of the first metatarsal located? A: Proximal. (Lesser metatarsals have distal physes).
Q: What is the most common cause of early recurrence in juvenile hallux valgus surgery? A: Failure to correct the DMAA (Distal Metatarsal Articular Angle).
Q: What is the inheritance pattern of juvenile hallux valgus? A: Autosomal Dominant with incomplete penetrance (strong maternal transmission).
Q: Which procedure allows for correction of the IMA without osteotomy in a growing child? A: Lateral Hemiepiphysiodesis of the first metatarsal base.
Q: What defines a Congruent joint in Piggott's classification? A: Parallel articular surfaces, despite the valgus angulation.
Self-Assessment Quiz
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“14-year-old girl. Bilateral bunions. No pain, but hates how they look. Mum wants surgery.”
“12-year-old female. Severe pain. HVA 50, IMA 18, DMAA 25. Open physis.”
“16-year-old. Had Chevron osteotomy at age 12. Deformity has recurred fully. Painful.”
KEY FEATURES
- Congruent Joint
- High DMAA
- Open Physis
- Ligament Laxity
RULE OUT
- Metatarsus Adductus
- Cerebral Palsy
- Marfan/Ehlers-Danlos
- Rheumatoid
ANGLES
- HVA greater than 15
- IMA greater than 9
- DMAA greater than 10 (Dysplastic)
- Sesamoid Station (Subluxation)
MANAGEMENT
- Non-op (Mainstay)
- Hemiepiphysiodesis (Growth)
- Distal Osteotomy (Mild)
- Double Osteotomy (Severe/DMAA)
Evidence Base
Coughlin (Roger A. Mann Award)
- 45 patients (60 feet); 88% female, 40% onset at age 10 or younger
- Maternal transmission in 72%; elevated DMAA in 48% of feet
- Congruent joints had a high mean DMAA (15.3 deg) versus 7.9 deg with MTP subluxation
- Multiprocedural approach (double osteotomy for high DMAA) gave 92% good/excellent results
Edmonds et al
- 106 feet comparing single distal, single proximal and double osteotomy
- Double osteotomy best corrected all three angles (IMA, HVA, DMAA) simultaneously
- Double osteotomy carried the highest rate of DMAA overcorrection
- Single distal osteotomy gave the most consistent results with lowest complication risk
Al-Mohrej et al (Systematic Review)
- 6 studies, 147 feet in 85 patients undergoing first-metatarsal hemiepiphysiodesis
- AOFAS improved from 62.2 to 88.6; HVA 29.2 to 23.8 deg; IMA 13.9 to 11.4 deg
- Modest radiographic correction; overall complication rate 14.2% (recurrence/revision)
Bard et al
- Multicentre series of 18 patients (26 feet), median 6.5-year follow-up
- Complication rate 31% and recurrence rate 23%
- No significant difference between basimetatarsal, scarf or distal osteotomy
- Outcomes were independent of physeal status at the time of surgery
Groiso
- 56 children/teenagers treated with a night thermoplastic splint plus exercises
- MTP and/or intermetatarsal angle improved in roughly half of feet at 2-6 years
- No recurrences among feet that improved
Piggott
- Original description of congruent, deviated and subluxated metatarsophalangeal joints
- The 'Piggott' congruency classification
- Foundation for choosing extra-articular vs soft-tissue procedures