Marble Bone Disease | Osteoclast Dysfunction | Dense But Brittle Bones
- Osteoclast Dysfunction: Failure of bone resorption, NOT increased bone formation
- Malignant Infantile (ARO): Life-threatening, pancytopenia, cranial nerve compression, death by age 10 without BMT
- Benign Adult (ADO): Often incidental, may present with fractures, Type II more common than Type I
- Radiographic Triad: Sandwich vertebrae, Erlenmeyer flask deformity, bone-in-bone appearance
- Surgical Challenge: Dense but brittle bone, difficult drilling, high implant failure, delayed/nonunion
- “Osteoclasts present but dysfunctional (carbonic anhydrase II or chloride channel defects)
- “Dense on X-ray but WEAK in reality - paradoxically fragile
- “Bone marrow failure from obliterated medullary canal causes pancytopenia
- “Foraminal narrowing causes optic nerve and facial nerve palsies
Overview and Epidemiology
Osteopetrosis (marble bone disease, Albers-Schonberg disease) is a group of rare inherited skeletal disorders characterised by defective osteoclast-mediated bone resorption, which leaves the skeleton generally sclerotic. Despite its radiographic density the bone is structurally abnormal and paradoxically brittle.
Three forms. Inheritance, age at onset and severity separate them:
- Autosomal recessive osteopetrosis (ARO): 1 in 250,000 births, severe, infantile onset
- Autosomal dominant osteopetrosis (ADO): 1 in 20,000, mild, adult onset. ADO Type II is the most common form overall
- Intermediate autosomal recessive: variable, childhood onset
Males and females are affected equally, and ARO has a higher incidence in consanguineous populations.
Genetics. Recessive disease is caused by mutations in TCIRG1 (50%), CLCN7 (15%) or OSTM1, or in TNFSF11 (RANKL) or TNFRSF11A (RANK), which produce an osteoclast-poor form. In dominant disease CLCN7 accounts for 70% and is the most common cause of ADO Type II, while LRP5 is associated with ADO Type I. What each gene does is set out under Pathophysiology.
CLCN7 mutations can cause both ARO and ADO - the severity depends on whether mutations are biallelic (recessive, severe) or monoallelic (dominant, mild). This explains phenotypic variability.
Pathophysiology
The core defect. Osteopetrosis is a disease of osteoclast dysfunction. In most forms the osteoclasts are present but cannot resorb bone effectively, while osteoblast function is normal.
How an osteoclast resorbs bone. The normal sequence:
- The osteoclast attaches to the bone surface (sealing zone)
- The proton pump (H+-ATPase) acidifies the resorption lacuna
- The chloride channel (CLCN7) provides charge balance
- Acid dissolves the hydroxyapatite mineral
- Cathepsin K digests the collagen matrix
- The resorption products are endocytosed
Where it fails. The genes, and what their mutations break:
- Protein
- Proton pump a3 subunit
- Function
- Acid secretion
- Result of Mutation
- Cannot acidify lacuna
- Protein
- Chloride channel 7
- Function
- Charge balance
- Result of Mutation
- Cannot maintain acid pH
- Protein
- Carbonic anhydrase II
- Function
- H+ generation
- Result of Mutation
- No protons for pump
- Protein
- CLCN7 partner
- Function
- Channel stability
- Result of Mutation
- CLCN7 degraded
- Protein
- Osteoclast formation
- Function
- Differentiation
- Result of Mutation
- Osteoclast-poor form
TCIRG1 encodes the a3 subunit of the vacuolar H+-ATPase, and OSTM1 is the osteopetrosis-associated transmembrane protein. With no resorption, calcified cartilage cores accumulate and primary spongiosa is never converted to mature bone, so the sclerotic skeleton has an abnormal architecture.
Why dense bone is weak. The bone lacks normal architecture. Calcified cartilage is retained within it, the trabecular microstructure is disorganised, woven rather than mature lamellar bone predominates, and without remodelling microdamage is never repaired. Its mineral content is increased, which is why it looks dense, but its elastic modulus is decreased and its ultimate strength reduced, so it breaks at lower loads, like chalk, with a transverse, shattering fracture pattern.
Failed modelling. Tubulation of the metaphysis requires resorption. Without it the metaphyses stay flared, the Erlenmeyer flask deformity, and the diaphysis remains wider than normal.
Marrow obliteration. The medullary canal fills with abnormal bone and replaces the haematopoietic tissue. The result is pancytopenia: anaemia from reduced erythropoiesis and haemolysis, thrombocytopenia with bleeding and bruising, and leucopenia with recurrent infections. Extramedullary haematopoiesis enlarges the liver and spleen.
The cranial foramina. The foramina of the skull base cannot enlarge normally because resorption fails, and the structures passing through them are compressed:
- Nerve
- Optic nerve (II)
- Consequence
- Blindness (progressive)
- Nerve
- Vestibulocochlear (VIII)
- Consequence
- Deafness
- Nerve
- Facial nerve (VII)
- Consequence
- Facial palsy
- Nerve
- Brainstem
- Consequence
- Hydrocephalus, death
Teeth and jaw. Teeth erupt late because the overlying bone is not resorbed. Dental abscesses and osteomyelitis of the jaw follow from its poor blood supply, and mandibular osteomyelitis is a major complication.
Calcium. In some forms the bone cannot release calcium, causing hypocalcaemia with secondary hyperparathyroidism, and rickets-like features are paradoxically possible. The mechanism has its own section, Osteopetrorickets, below.
Clinical Presentation
Onset. Autosomal recessive osteopetrosis presents in the first year of life, often within months of birth.
Marrow failure. Severe pancytopenia shows as pallor, fatigue and failure to thrive. Recurrent infections (pneumonia, sepsis) and bleeding or bruising follow, and extramedullary haematopoiesis makes the hepatosplenomegaly massive.
Nerve compression. Progressive blindness from optic nerve compression affects 50-80%. Auditory and facial nerve compression cause deafness and facial palsy, foramen magnum stenosis causes hydrocephalus, and development is delayed.
Skeleton and teeth. Skull thickening causes macrocephaly, with frontal bossing, growth is retarded, and fractures occur even with birth trauma. Dental disease runs from delayed eruption and abscesses to osteomyelitis of the mandible, a major source of morbidity.
Natural history. Without bone marrow transplant the disease is fatal by age 10, from infection, bleeding or anaemia, with progressive blindness and neurological deterioration.
Early diagnosis is critical. Bone marrow transplant in infancy offers the best chance of cure. Delayed transplant has worse outcomes because of established, often irreversible, neurological damage.
The two main forms side by side:
- ARO (Malignant Infantile)
- Autosomal recessive
- ADO Type II (Benign Adult)
- Autosomal dominant
- ARO (Malignant Infantile)
- 1:250,000
- ADO Type II (Benign Adult)
- 1:20,000 (most common form)
- ARO (Malignant Infantile)
- TCIRG1 (50%), CLCN7, OSTM1
- ADO Type II (Benign Adult)
- CLCN7 (70%)
- ARO (Malignant Infantile)
- Infancy (first year)
- ADO Type II (Benign Adult)
- Adolescence/adulthood
- ARO (Malignant Infantile)
- Fatal by age 10 without BMT
- ADO Type II (Benign Adult)
- Normal
- ARO (Malignant Infantile)
- Obliterated - pancytopenia
- ADO Type II (Benign Adult)
- Preserved - normal counts
- ARO (Malignant Infantile)
- Blindness, deafness, facial palsy common
- ADO Type II (Benign Adult)
- Rare cranial nerve issues
- ARO (Malignant Infantile)
- Marked (extramedullary haematopoiesis)
- ADO Type II (Benign Adult)
- None
- ARO (Malignant Infantile)
- Very high
- ADO Type II (Benign Adult)
- Moderate (lower limbs)
- ARO (Malignant Infantile)
- Bone marrow transplant (curative)
- ADO Type II (Benign Adult)
- Supportive, fracture management
MARBLEOsteopetrosis Features
Hook:MARBLE bone disease - dense like marble but breaks like chalk!
Investigations
Blood. The full blood count shows pancytopenia in ARO and is usually normal in ADO. The film shows nucleated red cells and immature white cells from extramedullary haematopoiesis, and the reticulocyte count may be raised by haemolysis. The biochemistry:
- Calcium: variable - normal, low or high
- Phosphate: usually normal
- Alkaline phosphatase: may be elevated (osteoblast activity)
- Acid phosphatase (TRAP): elevated (osteoclast marker)
- Creatine kinase BB isoenzyme: elevated (osteoclast marker in ARO)
- PTH: may be elevated (secondary hyperparathyroidism)
Genetic testing. The panel covers TCIRG1, CLCN7, OSTM1, TNFSF11 and TNFRSF11A. The result matters for prognosis and family counselling, and it determines eligibility for BMT.
Bone marrow. Aspiration is difficult through sclerotic bone. A trephine biopsy may show abnormal architecture, with reduced or absent haematopoietic tissue.
Radiographs. The plain film findings are pathognomonic:
- Sandwich vertebrae (rugger jersey spine): sclerotic endplates with a relatively lucent centre, alternating bands of sclerosis and lucency. Diagnostic for osteopetrosis
- Erlenmeyer flask deformity: flask-shaped widening of the metaphysis from failed tubulation, most visible at the distal femur
- Bone-in-bone appearance (endobone phenomenon): a ghost outline of the previous bone within the current one, representing retained growth lines, seen in the vertebrae, phalanges and iliac wings
- Diffuse osteosclerosis: generalised increased density through the entire skeleton, with loss of medullary cavity distinction
Elsewhere, the skull base is thickened with frontal bossing, the iliac wings are dense, the long bones show transverse fractures with variable callus formation, and the spine shows vertebral compression fractures.
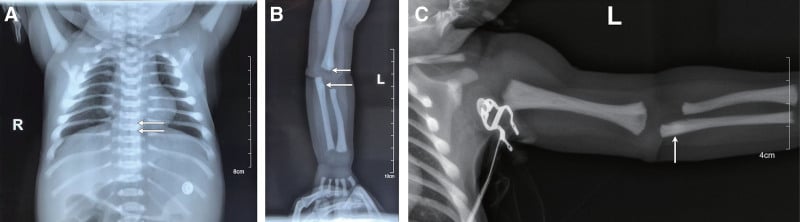
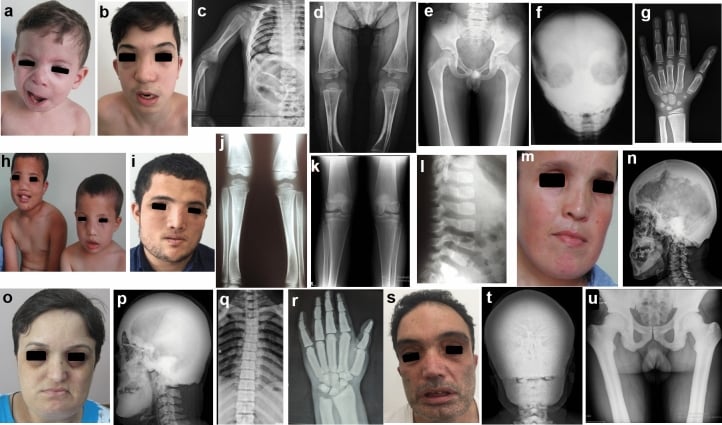
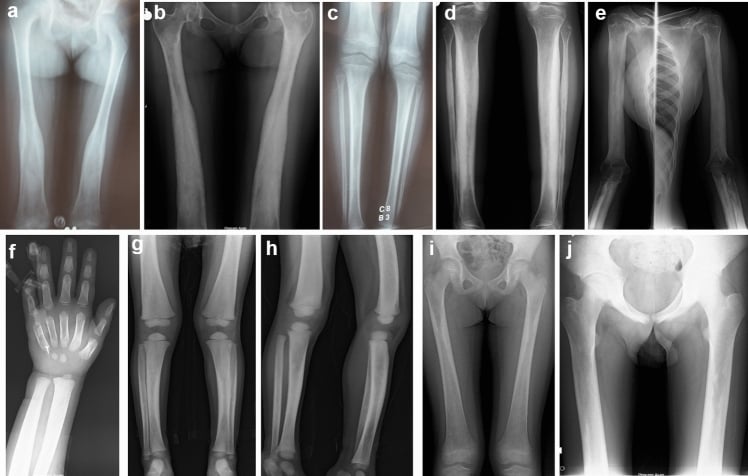
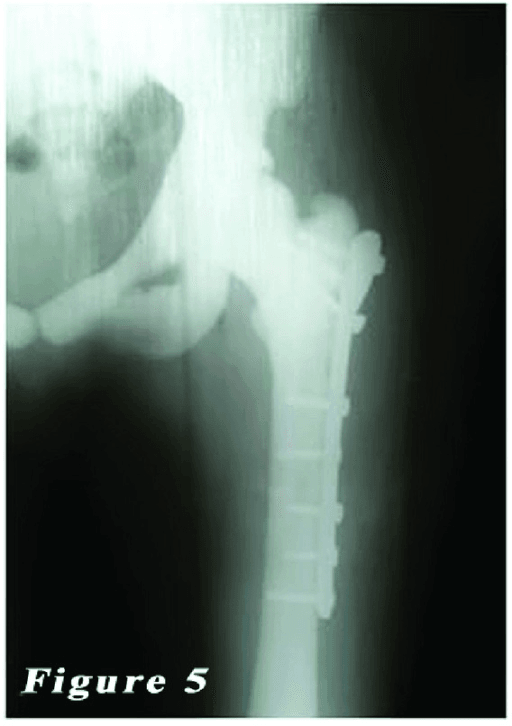
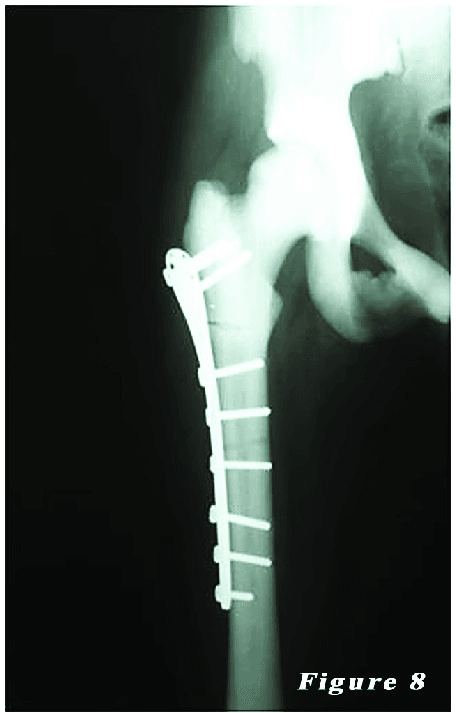
Look-alikes. Other sclerosing bone disorders are the trap on a film of dense bone, and the differential is tabulated under Differential Diagnosis below. The three figures that follow come from a cohort of osteosclerotic disorders that excluded osteopetrosis, and are shown for comparison only.
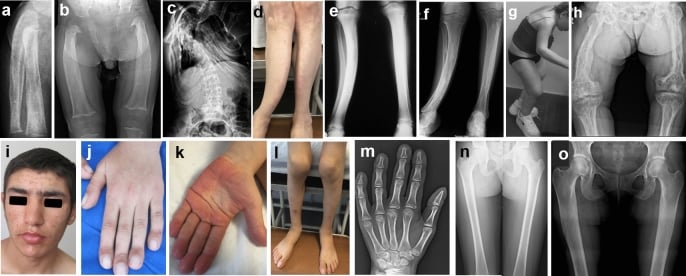
CT and MRI. CT gives better visualisation of foraminal stenosis and cranial nerve canal narrowing, and helps surgical planning. MRI assesses marrow replacement and cranial nerve compression, and identifies extramedullary haematopoiesis.
Eyes and ears. Ophthalmology uses visual evoked potentials (VEP) and fundoscopy for optic atrophy, with regular monitoring for optic nerve compression. Audiology uses brainstem auditory evoked responses (BAER) and pure tone audiometry to monitor progression of hearing loss.
Bone density. DEXA shows a paradoxically high BMD despite weak bone. Do not use BMD to guide treatment in osteopetrosis: the quality of the bone matters more than its quantity.
Bone biopsy. Rarely needed for diagnosis. It shows retained calcified cartilage cores and, in most forms, osteoclasts that are present but ineffective, with no resorption lacunae.
HLA typing. Needed for transplant donor matching. Sibling donors are preferred, with a search of the unrelated donor registry otherwise.
Differential Diagnosis
Sclerosing Bone Disorders
- Key Differentiator
- Osteoclast dysfunction, Erlenmeyer flask, sandwich vertebrae
- Genetics
- TCIRG1, CLCN7
- Key Differentiator
- Short stature, open fontanelles, acro-osteolysis, mandible hypoplasia
- Genetics
- CTSK (cathepsin K)
- Key Differentiator
- Diaphyseal involvement, limb pain, symmetric long bone sclerosis
- Genetics
- TGFB1
- Key Differentiator
- Dripping candle wax appearance, dermatomal distribution
- Genetics
- LEMD3 (mosaic)
- Key Differentiator
- Spotted bones, asymptomatic, bone islands
- Genetics
- LEMD3
- Key Differentiator
- Prostate/breast cancer history, focal lesions
- Genetics
- Acquired
Key Distinguishing Points:
- Pyknodysostosis: Toulouse-Lautrec had this; characterized by short stature, fragile bones, but with ACRO-OSTEOLYSIS (absent in osteopetrosis) and open fontanelles
- Engelmann Disease: Affects diaphyses primarily, causes pain and weakness, autosomal dominant
- Melorheostosis: Unilateral, follows sclerotome/dermatomal pattern, looks like dripping candle wax
Management
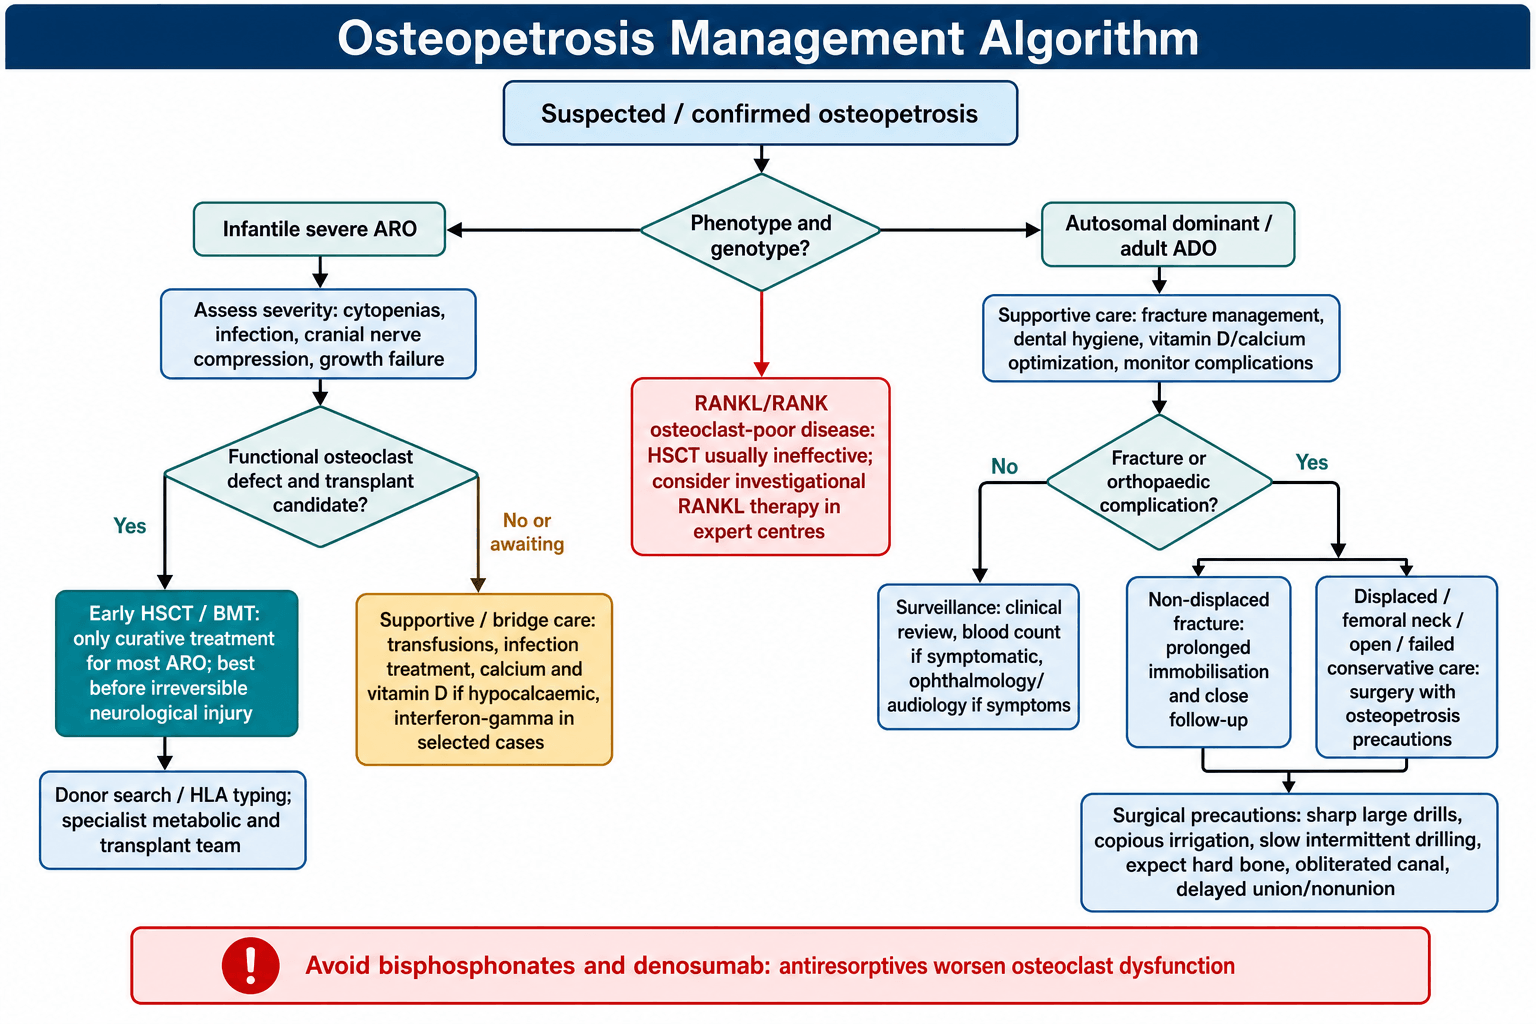
Transplant for ARO. Bone marrow or haematopoietic stem cell transplant is the only curative treatment for most forms of ARO, because donor osteoclast precursors can form functional osteoclasts. Outcomes are best if it is performed early in infancy, before irreversible neurological damage. In the international registry, 5-year survival was approximately 62% with an HLA-matched sibling donor and approximately 42% with alternative (mismatched related or unrelated) donors, and graft failure is the leading cause of post-transplant death.
Transplant is indicated for:
- Confirmed ARO with functional osteoclast defects
- Severe haematological involvement
- Progressive disease
It is contraindicated by:
- RANKL/RANK mutations (osteoclast-poor form - donor cells cannot form osteoclasts)
- Established severe neurological damage (may proceed if other organs are threatened)
Supporting the child with ARO. Transfusions for anaemia and thrombocytopenia, antibiotics for infections, and vitamin D and calcium if hypocalcaemic. Corticosteroids have a limited role, short-term, for pancytopenia.
Interferon-gamma-1b is FDA-approved for severe osteopetrosis and may enhance osteoclast function. The benefit is modest and seen in some patients, and it is used as a bridge to BMT or in patients who are not transplant candidates.
ADO. There is no specific medical treatment, only supportive care: manage fractures and complications, optimise bone health with vitamin D and calcium, and keep up dental hygiene to prevent osteomyelitis.
Do NOT give bisphosphonates in osteopetrosis. These drugs inhibit osteoclast function - the exact problem in osteopetrosis - and further impair resorption. They will worsen the disease.
Denosumab. An anti-RANKL antibody that inhibits osteoclast formation. As a treatment for osteopetrosis it is contraindicated and would worsen the disease; its only studied use in these patients is for hypercalcaemia after transplant (see Controversies).
Surgical Management
Drilling and fixation. The cortex is extremely hard. Drill bits break frequently, prolonged drilling generates heat, saw blades dull rapidly, bone cuts are difficult and tourniquet time is prolonged. Fixation is no easier: screws strip easily and plates loosen, plates may not seat properly on the irregular surface, and intramedullary nails are difficult to insert through an obliterated canal, which may need reaming if nailing is attempted.
Healing. Delayed union is very common, and should be expected as the norm, because there is no bone remodelling. Nonunion and implant failure are markedly more frequent than in normal bone. Callus forms but may not mature, yet a fracture may heal to some degree if aligned and immobilised.
Conservative or operative. Strongly consider conservative treatment for non-displaced fractures: cast immobilisation for extended periods, 3-6 months, may achieve union with patience and avoids surgical complications. Surgical indications:
- Displaced fractures
- Failure of conservative treatment
- Femoral neck fractures (high nonunion risk)
- Open fractures
Technique. Large drill bits, sharp instruments and patience:
- New, sharp instruments throughout, changing drill bits frequently (after every few holes)
- The largest diameter drill bits available, 3.2mm or larger if possible, being less likely to break
- Intermittent drilling with constant saline irrigation to prevent thermal necrosis
- Longer screws with larger diameter if the bone allows
- Locked plating preferred: angle-stable, less torque on screws and less reliance on bone quality
- External fixation avoids screw placement in dense bone, as primary treatment or as backup if internal fixation proves impossible
- Bone grafting may help (autograft preferred)
- Prolonged immobilisation postoperatively
Complications
The disease-related complications of each form are described under Clinical Presentation. The operative and transplant complications:
Early. The complications of the operation itself:
- Intraoperative fracture of the brittle bone during manipulation
- Drill bit breakage, the broken bits usually left in situ
- Prolonged operative time, increasing the infection risk
- Bleeding, which may be significant from the abnormal bone
- Thermal necrosis from prolonged drilling
Late. Those that emerge after the operation:
- Delayed union and nonunion (see Healing, above)
- Implant failure: screw loosening, plate breakage
- Refracture after implant removal or adjacent to hardware
- Infection, with increased susceptibility and difficult to eradicate
After BMT. The transplant carries its own risks:
- Graft-versus-host disease (GVHD)
- Graft failure
- Infection during the immunocompromised period
- Veno-occlusive disease
- Late effects of conditioning chemotherapy
Guidelines, Registries & Global Practice
Global Epidemiology
- Figure
- approximately 1 in 250,000 births
- Source population
- Worldwide; higher in consanguineous populations
- Figure
- approximately 1 in 20,000 births
- Source population
- Most common form overall
- Figure
- approximately 70% of cases explained by 10+ genes
- Source population
- International cohorts
- Figure
- Costa Rica, Middle East, parts of Northern Europe
- Source population
- Founder and consanguinity effects
There is no high-level (RCT) guidance for this rare disease; practice rests on registry data and expert consensus.
Consensus Positions Across Societies
- Working consensus
- Allogeneic HSCT
- Comment
- Best survival with HLA-matched sibling; refer in infancy
- Working consensus
- Mandatory
- Comment
- RANKL/TNFSF11 (osteoclast-poor) forms are NOT cured by HSCT
- Working consensus
- Contraindicated as disease treatment
- Comment
- They further suppress osteoclasts; denosumab studied only for post-HSCT hypercalcaemia
- Working consensus
- Anticipate hard, brittle bone
- Comment
- Locked plating favoured; external fixation as backup
- Working consensus
- Vision, hearing, FBC, dental
- Comment
- Optic-canal decompression considered before established atrophy
Registries and Networks
HSCT outcomes are pooled through international transplant registries (CIBMTR in North America, EBMT in Europe), which together generated the largest osteopetrosis transplant cohort to date. Unrelated-donor matching relies on national and international marrow donor registries. Rare-bone-disease reference networks (for example ERN-BOND in Europe) coordinate diagnosis, genetic confirmation and multidisciplinary care.
High- vs Limited-Resource Practice Variation
- Well-resourced settings: next-generation sequencing gene panels, early HSCT in infancy, skull-base and ophthalmology services, and locked-plate plus external-fixation inventories for fracture surgery.
- Limited-resource settings: diagnosis is often clinical and radiographic; transplant access may be delayed or unavailable, shifting care toward transfusion support, infection control and conservative fracture management. Consanguinity raises ARO incidence, so genetic counselling and antenatal diagnosis carry high value where available.
Carbonic Anhydrase II Deficiency (Guibaud-Vainsel Syndrome)
Carbonic anhydrase II deficiency is the one osteopetrosis variant with a signature systemic triad, which makes it highly examinable: the diagnosis can be reached from the combination rather than from the bone alone.
- A distinct autosomal-recessive triad. Carbonic anhydrase II (CA2) deficiency causes a recognisable syndrome of (1) osteopetrosis + (2) renal tubular acidosis (RTA) + (3) cerebral (basal ganglia) calcification - often remembered together, with developmental delay/intellectual disability and short stature completing the picture. It is also called Guibaud-Vainsel syndrome or "marble brain disease".
- Why one enzyme does all three. Carbonic anhydrase II generates the protons (H⁺) that the osteoclast's proton pump secretes to acidify the resorption lacuna - so its loss impairs bone resorption (osteopetrosis). The same enzyme is needed for renal tubular acid handling (both proximal and distal), producing a mixed proximal + distal RTA; and it is expressed in the brain, where its deficiency is associated with the characteristic basal-ganglia calcification. One shared biochemical step, three organ systems.
- How it differs from "classic" osteopetrosis - and why it matters. Unlike TCIRG1/CLCN7 disease, CA2 deficiency is milder in its skeletal severity (marrow failure is usually NOT life-threatening), the sclerosis may even diminish with age, and crucially it is NOT curable by haematopoietic stem-cell transplant - because the defect is a systemic enzyme deficiency, HSCT corrects the marrow-derived osteoclast but not the renal or cerebral disease. Management is therefore supportive: treat the RTA (alkali therapy), manage fractures, and monitor growth/development.
Q: A child has osteopetrosis, a metabolic (renal tubular) acidosis and basal-ganglia calcification - what is the diagnosis and does BMT cure it? A: Carbonic anhydrase II (CA2) deficiency (Guibaud-Vainsel / "marble brain" syndrome) - the autosomal-recessive triad of osteopetrosis + renal tubular acidosis + cerebral calcification, often with intellectual disability and short stature. CA2 makes the protons for both the osteoclast and the renal tubule, hence one enzyme, three organs. It is milder skeletally and NOT cured by HSCT (the renal/cerebral disease persists); manage with alkali for the RTA and supportive fracture/growth care.
Osteopetrorickets: the Paradox of Rickets in Dense Bone
How a disease of too much bone can coexist with rickets is a classic exam curveball, and thickened growth plates with rickets-like features are genuinely described in osteopetrosis.
- It is real, and it makes mechanistic sense. "Osteopetrorickets" is the coexistence of rachitic (unmineralised) growth-plate changes on a background of dense osteopetrotic bone - seen particularly in severe infantile ARO. The key is that osteopetrosis is a defect of resorption, not of mineral supply, and the two problems attack different compartments.
- Why the osteoclast defect causes a mineralisation failure. Normal osteoclasts liberate calcium (and phosphate) from bone into the blood; when they cannot resorb, the skeleton behaves as a calcium "sink" that traps mineral and cannot release it, so despite radiodense bones the child can become hypocalcaemic. The hypocalcaemia drives secondary hyperparathyroidism, and the low available mineral at the growth plate produces genuine rickets (widened, frayed, cupped physes) - hence dense metaphyses with rachitic growth plates side by side.
- Clinical consequences to recognise. The hypocalcaemia can be symptomatic - tetany and seizures in infancy (a feature specifically noted in ARO) - and the picture can be worsened by coexisting nutritional vitamin-D deficiency. Treatment is calcium and vitamin D/calcitriol to correct the mineral deficit (calcitriol may additionally stimulate residual osteoclasts); this is one reason mineral status is monitored closely, and it does not contradict the "no antiresorptives" rule.
Q: How can a child with osteopetrosis (dense bone) also have rickets and hypocalcaemia? A: Osteopetrosis is a defect of resorption, not mineralisation. Because osteoclasts normally release calcium from bone into the blood, a failed osteoclast makes the skeleton a calcium sink - the child becomes hypocalcaemic (with secondary hyperparathyroidism and even tetany/seizures in infancy), and the low mineral at the physis produces genuine rachitic growth plates on a dense-bone background ("osteopetrorickets"). Treat with calcium and vitamin D/calcitriol, not antiresorptives.
Controversies & Areas of Uncertainty
The rarity of osteopetrosis means most management rests on registries and expert opinion rather than randomised trials. Several genuine areas of debate persist:
-
Optimal timing and conditioning for HSCT. Earlier transplantation in infancy is associated with better outcomes, but the ideal age threshold, conditioning regimen, and donor hierarchy beyond matched siblings remain unsettled. Graft failure and hepatic/pulmonary toxicity are the dominant limitations rather than the transplant decision itself.
-
Reversibility of neurosensory deficits. Whether established optic atrophy or hearing loss can be salvaged by transplant or surgical decompression is uncertain; most evidence suggests vision rarely improves once atrophy is fixed, which is why decompression is considered only before established damage.
-
Role of optic-canal decompression. Indications and benefit are inconsistent across centres, and it is reserved for selected, progressive cases rather than offered routinely.
-
Pharmacological alternatives to transplant. Interferon-gamma-1b offers only modest, mainly supportive benefit; recombinant RANKL for osteoclast-poor (TNFSF11) disease and gene therapy for TCIRG1/CLCN7 remain investigational, with limited human data.
-
Denosumab in osteopetrosis. As a disease therapy it is contraindicated (it suppresses osteoclasts), yet it has been explored narrowly for transplant-related hypercalcaemia - a nuance that is easy to misstate.
-
Fracture fixation strategy. There is no consensus trial comparing plating, intramedullary fixation, and external fixation; choice is individualised, and the often-quoted precise nonunion percentages are extrapolated from small series rather than robust cohort data.
Self-Assessment Questions
What is the fundamental defect in osteopetrosis?
A: Osteoclast dysfunction leading to failure of bone resorption. The osteoclasts are present (in most forms) but cannot resorb bone effectively due to defects in proton pump (TCIRG1), chloride channel (CLCN7), or carbonic anhydrase (CA2). This leads to accumulation of calcified cartilage and primary spongiosa.
Which gene is most commonly mutated in autosomal recessive osteopetrosis?
A: TCIRG1 (50% of ARO cases). This gene encodes the a3 subunit of the vacuolar H+-ATPase (proton pump) essential for acidification of the resorption lacuna.
Name three classic radiographic features of osteopetrosis.
A: Sandwich vertebrae (rugger jersey spine - sclerotic endplates with lucent center), Erlenmeyer flask deformity (flared metaphyses from failed tubulation), and bone-in-bone appearance (endobone phenomenon).
Why is bone marrow transplant curative for most forms of ARO?
A: Osteoclasts are derived from hematopoietic stem cells. Donor HSCs can differentiate into functional osteoclasts that restore bone resorption. However, RANKL-deficient forms do NOT respond because osteoclast precursors cannot differentiate without RANKL signal.
Why are delayed union and nonunion common after fractures in osteopetrosis?
A: Fracture healing depends on coordinated bone remodelling, which requires functional osteoclasts. In osteopetrosis the osteoclast defect abolishes normal remodelling, so callus forms but cannot be reorganised into mature lamellar bone. The result is a markedly elevated rate of delayed union and nonunion compared with normal bone, alongside the technical difficulty of fixation in dense, brittle bone.
Why are bisphosphonates absolutely contraindicated in osteopetrosis?
A: Bisphosphonates inhibit osteoclast function - the exact problem in osteopetrosis. Administration would further impair bone resorption and worsen the disease.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are asked to see a 6-month-old infant diagnosed with autosomal recessive osteopetrosis. The child has pancytopenia, hepatosplenomegaly, and progressive vision loss. How would you manage this patient?”
“A 35-year-old man with known benign adult osteopetrosis (ADO Type II) presents with a displaced mid-shaft femoral fracture after a fall. How would you manage this fracture?”
“You are shown X-rays of the lumbar spine and distal femur showing diffuse sclerosis, 'sandwich vertebrae', and flaring of the distal femoral metaphysis. What is the diagnosis and what are the key radiographic features of this condition?”
PATHOPHYSIOLOGY
- Osteoclast DYSFUNCTION (not absent)
- Failed bone RESORPTION
- Dense but BRITTLE bone
- Medullary canal OBLITERATED
TYPES
- ARO: Autosomal recessive, infantile, FATAL without BMT
- ADO Type II: Most common, benign, adult, CLCN7
- ADO Type I: Rare, cranial vault involvement
- Intermediate: Variable, childhood onset
RADIOGRAPHIC FEATURES
- Sandwich vertebrae (rugger jersey)
- Erlenmeyer flask (flared metaphyses)
- Bone-in-bone (endobone)
- Diffuse osteosclerosis
ARO COMPLICATIONS
- Pancytopenia (marrow obliteration)
- Blindness (optic canal stenosis)
- Hepatosplenomegaly (extramedullary hematopoiesis)
- Death by age 10 without BMT
GENES
- TCIRG1: 50% of ARO (proton pump)
- CLCN7: ARO and ADO (chloride channel)
- RANKL: Osteoclast-poor (no BMT benefit)
- CA2: With renal tubular acidosis
SURGICAL CHALLENGES
- Drill bits BREAK - use large diameter, change often
- Screws STRIP - use locked plates
- Healing DELAYED - high delayed-union and nonunion risk
- Consider EXTERNAL FIXATION as alternative
TREATMENT
- ARO: BMT curative (early, before age 2)
- ADO: Supportive, fracture management
- NO bisphosphonates (worsen disease)
- Interferon-gamma (bridge therapy)
Evidence Base
Tolar, Teitelbaum & Orchard
- Authoritative review of osteopetrosis pathophysiology and classification
- Osteoclast development vs function defects distinguished as the unifying mechanism
- Proton pump (TCIRG1), chloride channel (CLCN7) and RANK/RANKL pathways mapped to phenotypes
- Haematopoietic stem cell transplantation framed as the only cure for osteoclast-rich infantile disease
Stark & Savarirayan
- ARO incidence 1 in 250,000 births; ADO incidence 1 in 20,000 births
- At least 10 causative genes account for roughly 70% of all cases
- Severe infantile forms cause death in the first decade if untreated; adult-onset forms have normal life expectancy
- Diagnosis is clinical and radiographic, confirmed by gene testing where applicable