Extraarticular Metaphyseal Fracture | Extension vs Flexion Type | High Stiffness Rate
- Extraarticular by definition - articular involvement = intercondylar fracture
- Extension type (95%) - distal fragment displaces posteriorly
- Flexion type (5%) - distal fragment displaces anteriorly
- Adults differ from children - osteoporotic bone, stiffness is major issue
- Dual column fixation preferred even for extraarticular fractures
- “Draw the distinction from paediatric supracondylar fractures clearly
- “Examiners expect discussion of extension vs flexion type
- “Know the surgical approaches - posterior vs lateral vs medial
- “Discuss stiffness prophylaxis and early ROM protocols
Overview and Epidemiology
An adult supracondylar humerus fracture is an extra-articular fracture of the distal humeral metaphysis, proximal to the condyles, lying between the supracondylar ridges and the olecranon fossa. It accounts for approximately 10% of adult distal humerus fractures.
The definition is the exam point. Any articular involvement makes the fracture intercondylar (AO/OTA 13-C), and examiners test the distinction because it changes the classification, the approach and the prognosis.
Who. The peak is at 50-60 years, in osteoporotic bone, but the distribution is bimodal:
- Young adults (20-40) - high-energy trauma: motor vehicle accidents, falls from height, sports injuries and industrial accidents
- Elderly (50+) - low-energy falls from standing on osteoporotic bone, sometimes with minimal trauma
Not a big child's fracture. In children the injury follows a fall on the outstretched hand at 5-7 years, and the long-term cost is cubitus varus. In adults the mechanism is an axial load or a direct blow, the bone is often osteoporotic, and the long-term cost is stiffness rather than deformity. The aim of treatment is therefore fixation stable enough to move the elbow early, which in adults means dual-column plating.
- Adult
- Axial load/direct blow
- Paediatric
- FOOSH with hyperextension
- Adult
- Often osteoporotic
- Paediatric
- Strong cortical bone
- Adult
- Low transverse or oblique
- Paediatric
- High transverse
- Adult
- Stiffness (up to 50% functional loss)
- Paediatric
- Cubitus varus
- Adult
- Less common
- Paediatric
- Brachial artery concern
- Adult
- Stable fixation for early ROM
- Paediatric
- Anatomic reduction, avoid growth arrest
- Adult
- Dual column plating
- Paediatric
- Crossed K-wires
- Adult
- Stiffness predominates over deformity
- Paediatric
- Cubitus varus deformity
- Adult
- Wrist fractures, other fragility fractures
- Paediatric
- Isolated injury typical
- Adult
- Female predominant (2:1)
- Paediatric
- Male predominant
Differential diagnosis. The key task is to distinguish a true extra-articular supracondylar fracture from the intra-articular and adjacent injuries around it.
- Distinguishing Feature
- Extra-articular metaphyseal line; intact articular surface; Triangle of Hueter preserved
- Key Investigation
- AP/lateral radiograph; CT confirms no articular extension
- Distinguishing Feature
- Articular split between trochlea and capitellum; commonest pattern in elderly
- Key Investigation
- CT with 3D reconstruction
- Distinguishing Feature
- Partial articular, one column with articular involvement
- Key Investigation
- Oblique radiographs / CT
- Distinguishing Feature
- Anterior articular fragment, double-arc sign on lateral
- Key Investigation
- Lateral radiograph; CT
- Distinguishing Feature
- Lateral tenderness, painful pronation/supination, positive fat-pad sign
- Key Investigation
- AP/lateral and radiocapitellar (Greenspan) view
- Distinguishing Feature
- Gross deformity, loss of bony triangle, ulnohumeral incongruity
- Key Investigation
- Pre- and post-reduction radiographs; CT
- Distinguishing Feature
- Prior implant or lytic lesion; low-energy mechanism
- Key Investigation
- Full-length humerus radiograph; cross-sectional imaging
Anatomy and Biomechanics
Two columns. The distal humerus has a triangular architecture: a medial and a lateral column, joined distally by the trochlear-capitellar articular arch. Forces across the elbow are transmitted through both columns.
- Medial column
- Supracondylar ridge to medial epicondyle
- Lateral column
- Supracondylar ridge to lateral epicondyle
- Medial column
- Trochlea, articulating with the ulna
- Lateral column
- Capitellum, articulating with the radius
- Medial column
- Common flexor origin
- Lateral column
- Common extensor origin
- Medial column
- 40% through the ulnotrochlear joint
- Lateral column
- 60% through the radiocapitellar joint
- Medial column
- Ulnar nerve courses posteriorly
- Lateral column
- More robust than the medial column
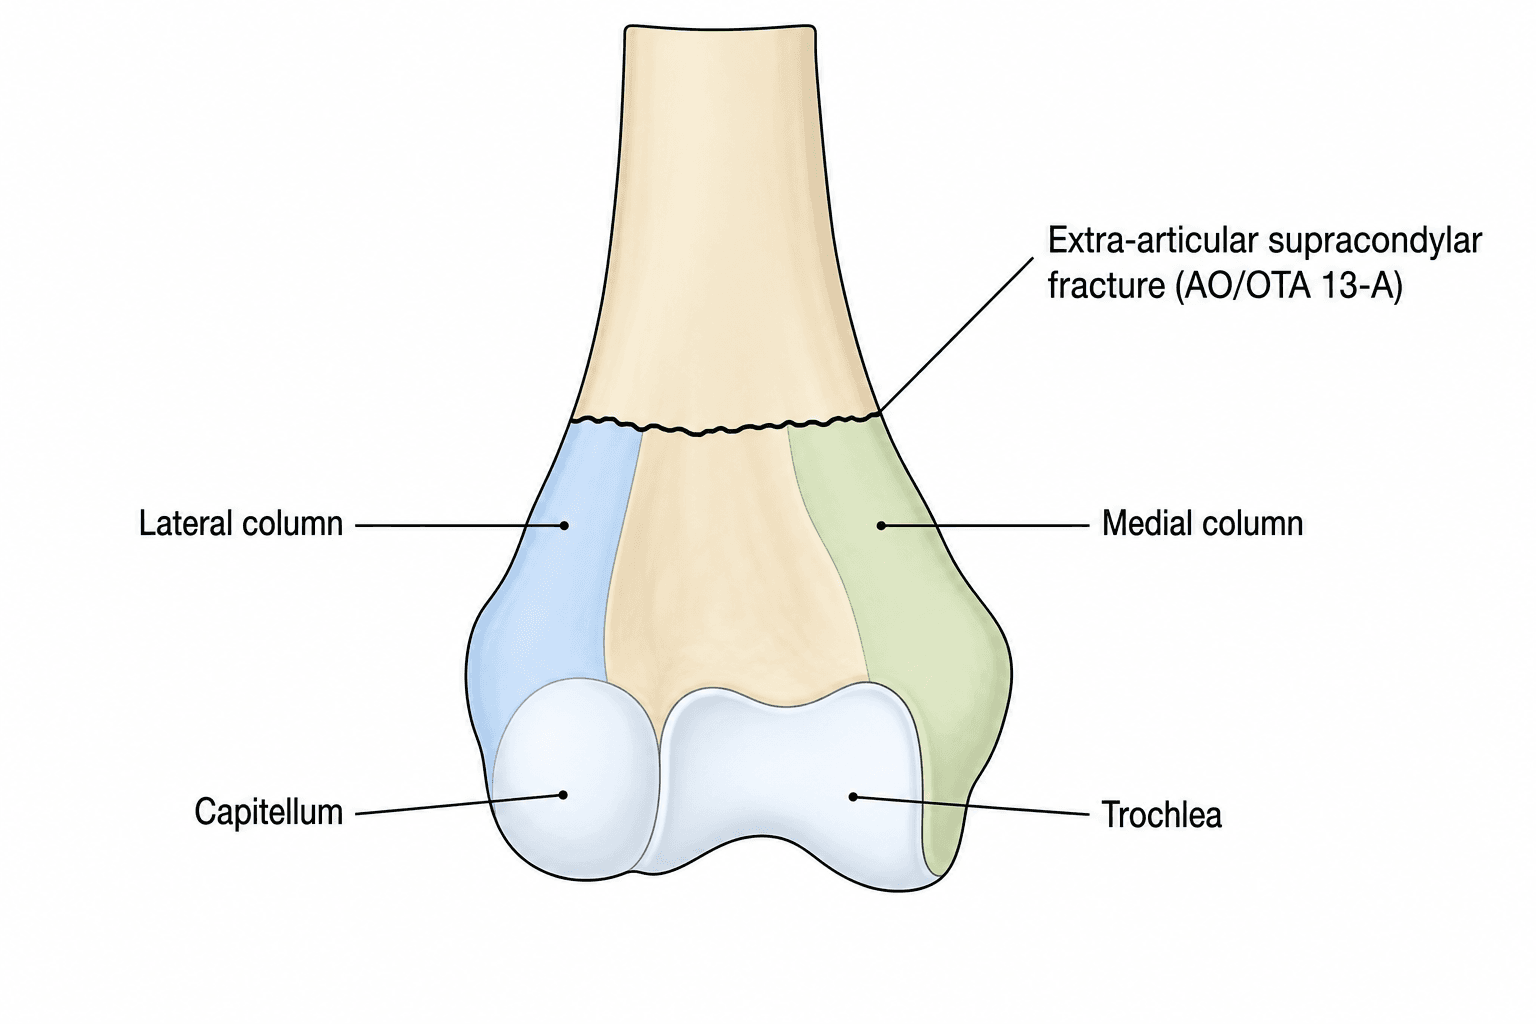
Why the supracondylar region breaks. It is the weakest point of the distal humerus. The cylindrical diaphysis changes to a flat metaphysis, thin cortical bone bridges the columns, and the olecranon and coronoid fossae act as stress risers; the supracondylar ridges mark the proximal extent of the region.
What stability needs. Stability requires restoration of both columns, and single-column fixation is insufficient. Fixation also has to be rigid enough for early range of motion.
Nerves and vessels. Management of the ulnar nerve at surgery is discussed under Complications.
- Course
- Cubital tunnel, behind the medial epicondyle
- At risk from
- Medial column displacement, the medial approach, plate placement
- Course
- Pierces the lateral intermuscular septum 10 cm above the lateral epicondyle
- At risk from
- Proximal fracture extension, the anterolateral approach
- Course
- Anteriorly, in the antecubital fossa
- At risk from
- An anterior spike of the proximal fragment
The median nerve and brachial artery are less commonly injured than in paediatric fractures. Collateral circulation is usually adequate, and a pulseless but perfused limb may be observed.
Classification Systems
AO/OTA 13-A. Adult supracondylar fractures sit in the extra-articular distal humerus group. A2 is the true adult supracondylar pattern.
- Pattern
- Epicondylar (apophyseal) avulsion of the medial or lateral epicondyle
- Subtypes
- A1.1 medial epicondyle; A1.2 lateral epicondyle
- Pattern
- Metaphyseal simple: a single fracture line above the condyles
- Subtypes
- A2.1 oblique downward and inward; A2.2 oblique downward and outward; A2.3 transverse
- Pattern
- Metaphyseal multifragmentary: a comminuted metaphyseal pattern
- Subtypes
- A3.1 intact wedge; A3.2 fragmented wedge; A3.3 multifragmentary, including bone loss
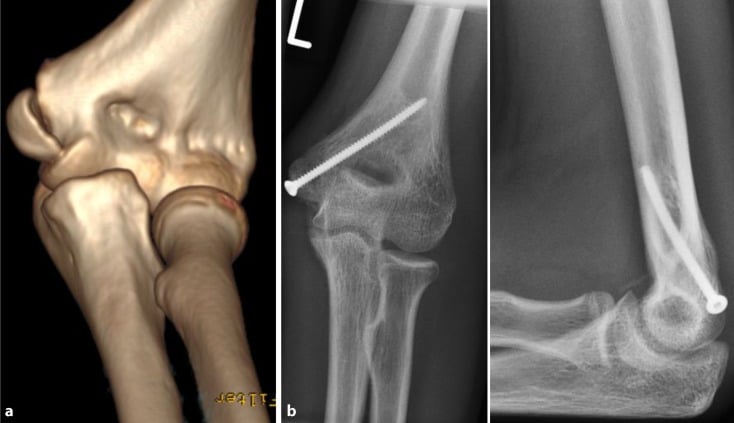
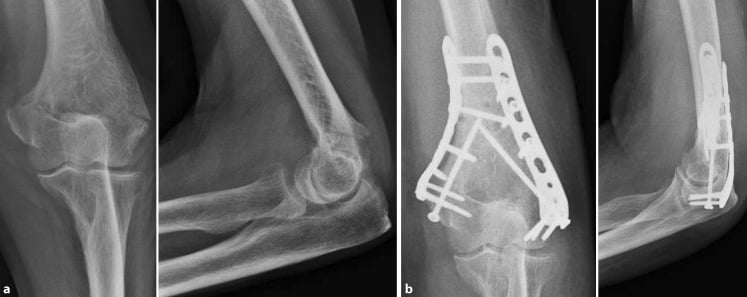
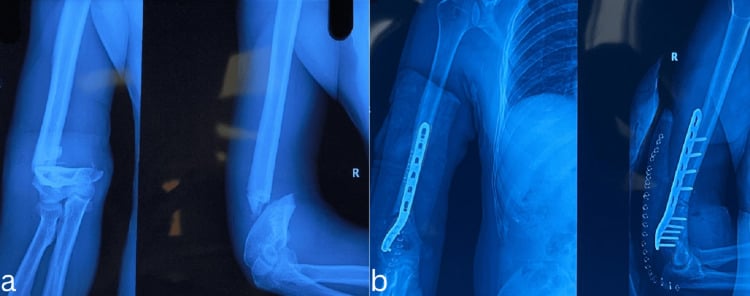
Extension and flexion types. The type is named by the direction in which the distal fragment displaces.
- Share
- 95%
- Distal fragment
- Posterior
- Mechanism
- Axial load with the elbow in extension, or a direct blow
- Force vector
- Anterior to posterior
- Tension side
- Anterior cortex (posterior in compression)
- Lateral radiograph
- S-shaped deformity
- Share
- 5%
- Distal fragment
- Anterior
- Mechanism
- Direct blow to the posterior elbow, or a fall on the flexed elbow
- Force vector
- Posterior to anterior
- Tension side
- Posterior cortex
- Lateral radiograph
- Reverse deformity
Fracture pattern. The shape of the line decides what the fixation has to do.
- Description
- Perpendicular to shaft
- Stability
- Relatively stable
- Fixation Challenge
- Standard dual plating
- Description
- Angled fracture line
- Stability
- Less stable
- Fixation Challenge
- May need lag screws
- Description
- Rotational component
- Stability
- Variable
- Fixation Challenge
- Longer plates needed
- Description
- Multiple fragments
- Stability
- Unstable
- Fixation Challenge
- Bridge plating, bone graft
A classic examiner distinction: where exactly is the fracture line? Three levels, three entities:
- Supracondylar (this topic) - the line is above the condyles, through the supracondylar metaphysis - extra-articular (AO/OTA 13-A).
- Transcondylar / diacondylar - the line runs through both condyles at the level of the joint, within the capsule but without splitting the articular surface into separate trochlear and capitellar fragments. It is a low, intracapsular fracture typically seen in the very elderly, osteoporotic patient.
- Intercondylar (bicolumnar) - an articular split between the trochlea and capitellum (AO/OTA 13-C).
Why the transcondylar pattern matters: the distal fragment is tiny and entirely intracapsular, so there is almost no metaphyseal bone for distal screws, fixation is precarious in osteoporotic bone, and intracapsular position predisposes to non-union and stiffness. It is one of the strongest indications to consider primary total elbow arthroplasty in a low-demand elderly patient when stable internal fixation cannot be achieved. (The paediatric counterpart - a transcondylar fracture through the physis in a young child - is the rare, easily-missed "low" supracondylar variant.)
Clinical Presentation and Assessment
History. Establish the mechanism and the energy behind it, then the answers that shape the plan:
- Hand dominance - functional importance
- Occupation - manual labour or sedentary
- Pre-injury function - baseline ROM, arthritis
- Previous elbow surgery - may affect the approach
- Medical comorbidities - surgical fitness, bone quality
- Anticoagulation - bleeding risk, haematoma
- Smoking - wound healing, union
Inspection. Expect significant periarticular swelling. An extension-type fracture gives an S-shaped deformity with anterior ecchymosis; a flexion-type fracture gives a reverse S-shaped deformity with posterior ecchymosis. Check the skin for open wounds, tenting and blisters.
Palpation and movement. Assess column integrity, point tenderness over the fracture and crepitus with gentle movement. The Triangle of Hueter stays a normal equilateral triangle, because the fracture is extra-articular. Do not force the examination acutely: document pre-injury ROM if possible, and assess elbow movement and forearm rotation, which tests the DRUJ and PRUJ and is normally full. Ligamentous stability is not testable acutely.
Neurovascular examination. Examine each nerve in turn:
- Motor
- First dorsal interosseous, finger abduction
- Sensory
- Small finger and ulnar half of the ring finger
- Test
- Crossed fingers, card test
- Motor
- Wrist and finger extension
- Sensory
- First dorsal web space
- Test
- Wrist extension against resistance
- Motor
- Thumb opposition, index finger flexion
- Sensory
- Palmar thumb, index and middle fingers
- Test
- OK sign, FPL function
- Motor
- FPL, FDP to index, pronator quadratus
- Sensory
- Test
- OK sign (cannot make a circle)
For the circulation, feel the radial and ulnar pulses, check capillary refill and compare with the other side; use a Doppler if the pulses are not palpable.
Document neurovascular status, the ulnar nerve above all, before any intervention. Ulnar nerve injury is common with medial column involvement, and a pre-operative deficit changes surgical planning and is critical medicolegally.
Investigations
Radiographs. AP and lateral views of the elbow, and a full-length humerus.
- AP - column integrity, the fracture angle, medial or lateral displacement, and any articular involvement, which would make the fracture intercondylar
- Lateral - confirms the fracture is extra-articular, shows the direction of displacement that defines the type, and shows whether the coronoid and olecranon fossae are involved
- Full-length humerus - required to plan plate length, exclude proximal extension and look for a pathological fracture
A fat pad sign indicates haemarthrosis, though there may be less effusion if the capsule is torn. Intact columns carry a good prognosis; column comminution makes fixation more challenging.
CT. The 3D reconstruction is the gold standard for surgical planning, and it helps confirm that the fracture is truly extra-articular and not an intercondylar pattern requiring intra-articular reconstruction. Obtain thin-cut axial images (1-2 mm) through the full distal humerus, with coronal and sagittal reformats. The indications:
- A fracture pattern that is unclear on plain films
- Assessing the degree of comminution
- Confirming extra-articular versus intercondylar
- Preoperative planning for complex patterns
- Clinical Relevance
- Confirm extraarticular (supracondylar)
- Clinical Relevance
- Plate length, grafting needs
- Clinical Relevance
- Approach planning
- Clinical Relevance
- Fixation strategy
- Clinical Relevance
- Plate positioning
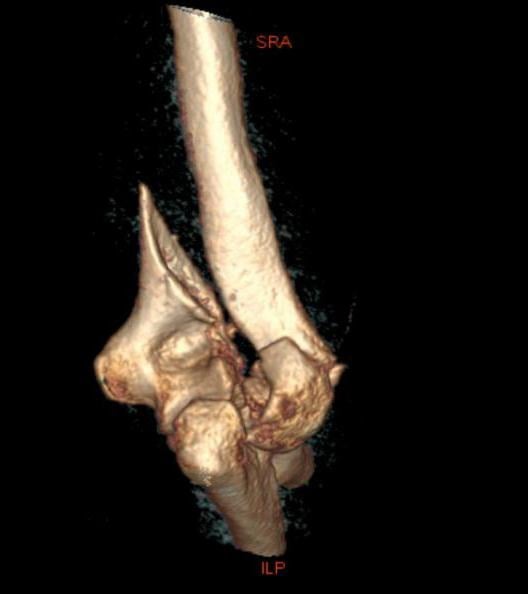
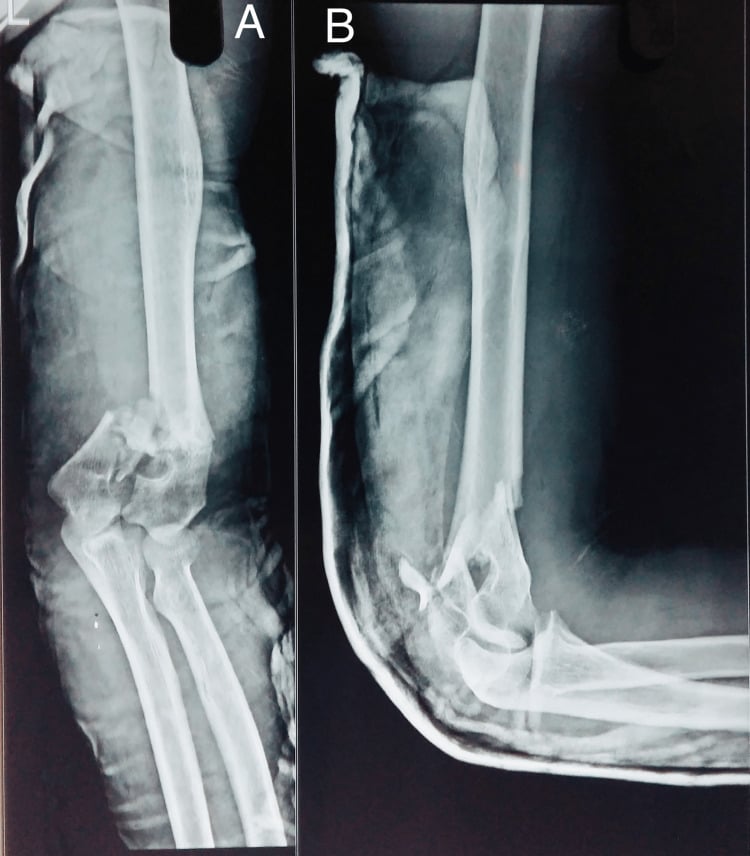
Other studies. MRI has a limited role in acute fracture management but may assess ligament integrity, soft tissue interposition and occult pathology. Consider DEXA after a low-energy fracture in the elderly, for fragility fracture pathway planning and to inform the fixation strategy (locking plates, cement). Nerve conduction studies are not typically performed acutely, but may document a pre-existing neuropathy, evaluate post-operative nerve dysfunction, and serve medicolegal documentation.
Angiography is indicated for:
- Hard signs of vascular injury (a pulseless, cold limb)
- An expanding haematoma
- A bruit or thrill
- Active haemorrhage
Management
Most need surgery. Operate for:
- Displacement over 5 mm
- Any angulation
- Unstable patterns
- Polytrauma requiring mobilisation
- Open fractures
- Vascular injury requiring repair
Non-operative treatment. Appropriate for minimally displaced fractures (under 5 mm), patterns stable on stress views, non-ambulatory patients with minimal functional demands, and patients whose comorbidities preclude surgery or who prefer it after informed consent. It often results in poor ROM recovery with high rates of stiffness, so it is reserved for truly stable patterns or poor surgical candidates.
- Weeks 0-2 - long arm splint at 90° flexion, ice and elevation; begin hand and shoulder exercises
- Weeks 2-4 - convert to a hinged brace; gentle ROM within it, targeting full extension to 90° flexion
- Weeks 4-6 - increase ROM progressively, begin strengthening, wean from the brace
- Week 6 onwards - full ROM exercises, progressive strengthening and return to activities
Bone quality decides the construct. Good bone allows standard plate fixation. Osteoporotic bone brings poor screw purchase, comminution and a risk of implant cutout: locking plates are mandatory, longer plates distribute the load, selected screws can be cement-augmented, and in severe osteoporosis with low demand primary TEA is considered.
High-energy injuries. Consider associated injuries and the soft tissue status, and apply damage-control principles. The staged approach is a temporary spanning external fixator, soft tissue recovery over 7-14 days, then definitive ORIF.
Open fractures. Management follows the Gustilo grade.
- Management
- Debridement, primary ORIF
- Management
- Debridement, ORIF if soft tissue allows
- Management
- Staged, external fixation first
- Management
- Complex reconstruction, may need TEA
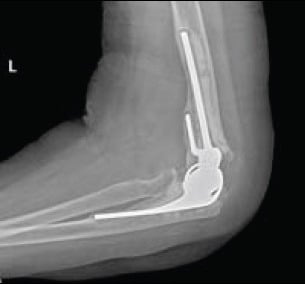
Primary total elbow arthroplasty. In the elderly, low-demand patient, consider primary TEA with:
- Age over 65-70 with a comminuted fracture
- Severe osteoporosis
- Low functional demands
- Rheumatoid arthritis
- Pre-existing arthritis
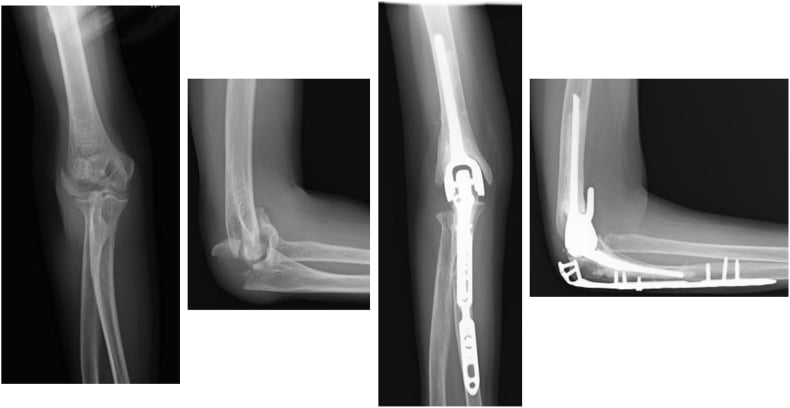
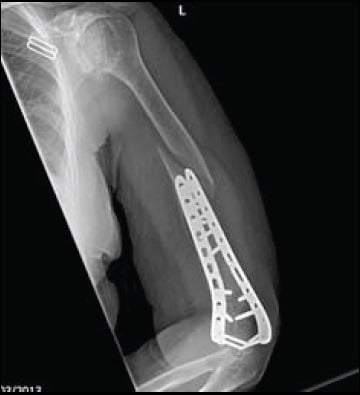
TEA for acute distal humerus fractures has good short-term outcomes but a lifelong 5 kg lifting restriction. Discuss this trade-off with examiners: ORIF is preferred in younger, active patients.
Surgical Technique
Posterior approach. The most common approach, used for complex fracture patterns, when both columns need access, or when an olecranon osteotomy is planned. It gives excellent exposure, allows dual plating and can be extended proximally and distally; the price is an extensile dissection, a risk of triceps dysfunction and higher stiffness rates.
- Lateral decubitus or prone
- Midline posterior incision
- Full-thickness flaps
- Identify and protect the ulnar nerve
- Reach the columns by triceps-splitting, triceps-reflecting (Bryan-Morrey) or olecranon osteotomy
Lateral (Kocher) approach. For simple lateral column fractures and less comminuted patterns. A lateral skin incision is carried through the interval between anconeus and ECU to the lateral column, protecting the radial nerve.
Medial approach. For isolated medial column fractures, or when the ulnar nerve needs exploring. Through a medial skin incision the ulnar nerve is identified first and protected or transposed, and only then is the medial column exposed.
Olecranon osteotomy. Used for complex fracture patterns, when the articular surface needs to be seen (if there is concern for articular extension), and as the approach for TEA. A chevron cut, V-shaped with the apex proximal, gives rotational stability; a transverse cut is simpler and faster. The osteotomy is marked at the non-articular bare area, scored with a saw and completed with an osteotome, and the olecranon is elevated with the triceps attached, giving excellent articular and column exposure.
Pre-drill the osteotomy fixation holes BEFORE making the osteotomy. This ensures accurate reduction and avoids technical difficulties later.
- Advantage
- Simple, reliable
- Disadvantage
- Hardware prominence
- Advantage
- Low profile
- Disadvantage
- More expensive
- Advantage
- Low profile
- Disadvantage
- Less compression
Osteotomy non-union is quoted at 5-10%, and hardware prominence and the need for removal are the other complications. In the Coles series (see Evidence Base) every chevron osteotomy with adequate follow-up united, and the main downside was hardware prominence requiring removal.
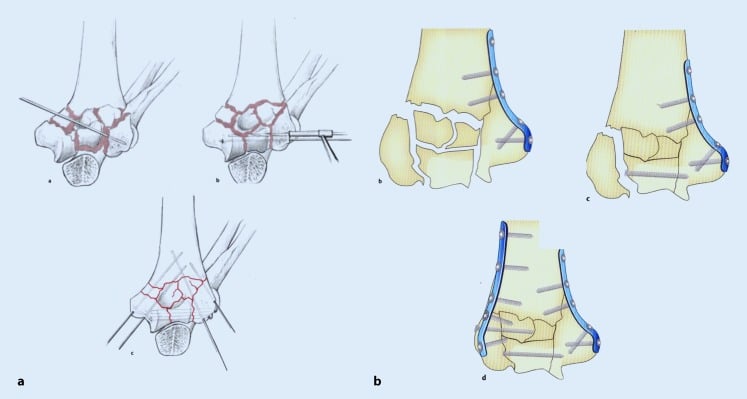
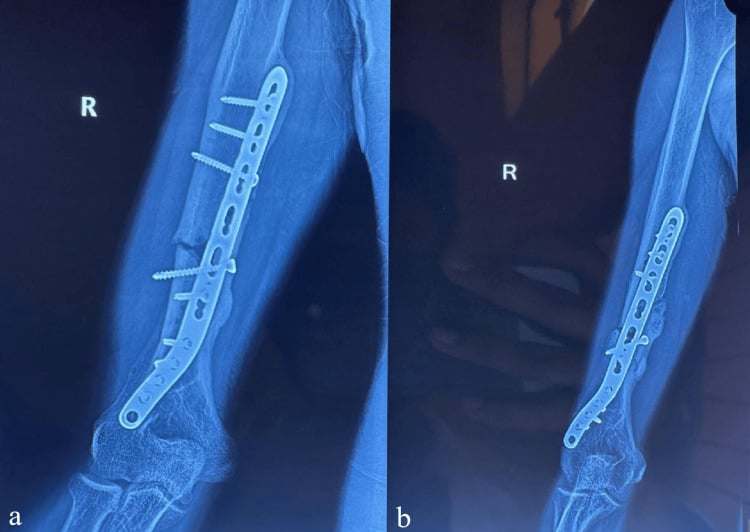
Dual plating, the gold standard. Even for an extra-articular fracture, both columns are plated, each stabilised independently. AO accepts either configuration.
- Placement
- Medial + posterolateral
- Advantages
- Familiar; the posterolateral plate sits on a broad flat surface and the two plates are less likely to collide distally. But in paired osteoporotic cadaveric testing its stability was more sensitive to bone mineral density
- Placement
- Medial + lateral directly
- Advantages
- The stiffer construct in the biomechanical study (Stoffel): significantly greater compressive and external-rotation stiffness, with better resistance to axial plastic deformation. Long distal screws interdigitate and lag the columns together
Say this carefully in a viva. The biomechanical edge belongs to parallel plating, but it is cadaveric, paired-specimen, osteoporotic AO C2 bone, and both constructs allowed early mobilisation, which is the outcome that matters. No clinical trial has shown one configuration to be superior in patients. The defensible position is that the configuration matters less than the principles below, and that the surgeon should use whichever lets them get maximum screw purchase in the distal fragments.
The principles. Whatever the configuration:
- Minimum 6 cortices proximal to the fracture in each column; long plates are preferred
- Maximum screw density in the distal fragments
- Locking screws in osteoporotic bone
- Anatomic plates that match the distal humerus contour
- Screw Type
- Non-locking or locking
- Consideration
- 6+ cortices
- Screw Type
- Locking
- Consideration
- Bridge comminution
- Screw Type
- Locking
- Consideration
- Maximum purchase
- Screw Type
- Lag screws
- Consideration
- For simple patterns only
The sequence. Reduce and fix in this order:
- Reduce the articular surface first, if there is any involvement
- Provisional K-wire fixation
- Plate one column, reduce the other, plate the second
- Check for impingement through a range of motion
- Confirm position with intraoperative imaging
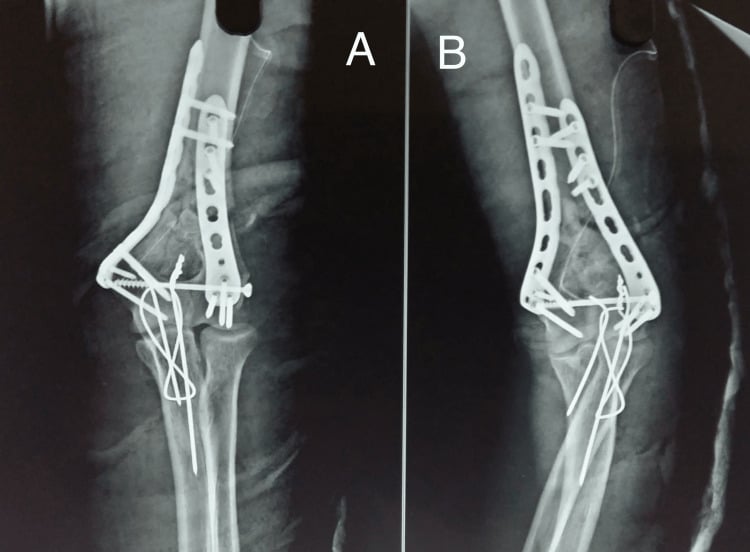
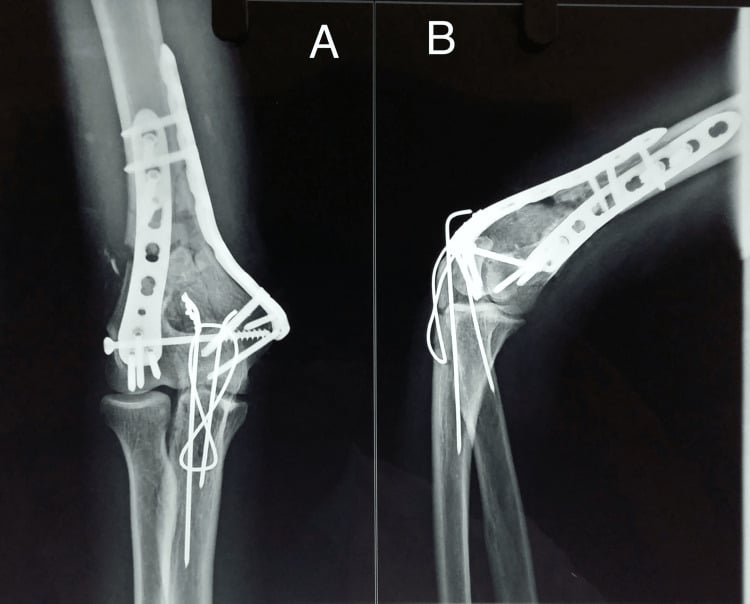
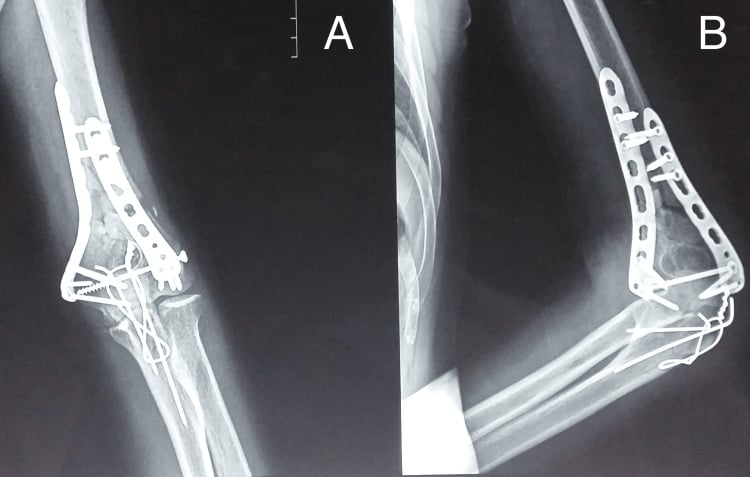
Complications
Stiffness. The number one complication: up to 50% of patients lose functional ROM, which is why stable fixation enabling early ROM is paramount. Risk factors are prolonged immobilisation, heterotopic ossification, intra-articular adhesions, a complex fracture pattern and poor compliance with rehabilitation. Prevention is stable fixation (dual plating), early ROM within 2 weeks, indomethacin prophylaxis against HO and aggressive physiotherapy.
- Approach
- Physiotherapy, static progressive splinting
- Approach
- Consider manipulation under anaesthesia
- Approach
- Surgical release (arthroscopic or open)
Heterotopic ossification. Occurs in 5-25%, with head injury, burns and delayed surgery as risk factors. Prevent it with indomethacin 75 mg daily for 6 weeks or single-dose radiation. Excise it when mature (12-18 months) and symptomatic.
Nerve injury. The ulnar nerve is the most commonly injured, with neurapraxia in 15-20% from the initial injury, surgical manipulation or hardware. The radial nerve is injured in 5-10%, from proximal fracture extension or the lateral approach. Both are observed for 3 months, then explored if there is no recovery.
Transposing the ulnar nerve. Routine transposition is debated, and the evidence does not support it as protective. In 69 bicolumnar fractures (OTA 13A and 13C) with no pre-operative deficit, ulnar nerve dysfunction was present in 10.1% immediately after surgery and 16% at final follow-up, and no treatment factor, transposition included, was associated with the risk (Vazquez); the authors state plainly that transposition was not protective, and that a retrospective design probably underestimates the true rate. A later review reported late ulnar neuropathy in 38% after this operation, again with no significant difference between in-situ release and anterior transposition.
What follows for practice and for consent. Identify and protect the nerve in every case. Decide on transposition by what the plate actually does to the cubital tunnel rather than by routine; that applies at the index operation, and irritation from a medial plate or screws later may also require it. Warn the patient before surgery that some ulnar symptoms are common: this is one of the few complications where the honest quoted figure is well into double digits, and a patient told nothing will reasonably attribute it to a technical error.
Infection and the wound. Infection is higher with extensile approaches. Wound problems are skin necrosis (especially after the posterior approach), dehiscence and haematoma, and the risk is higher with diabetes, smoking and anticoagulation. Triceps weakness follows the approach or scarring.
- Incidence
- 2-5%
- Management
- Antibiotics, wound care
- Incidence
- 1-3%
- Management
- Debridement, IV antibiotics
- Incidence
- Rare
- Management
- Staged reconstruction
Malunion. The direction of the malunion decides its consequence.
- Consequence
- Cubitus varus, instability
- Management
- Corrective osteotomy
- Consequence
- Tardy ulnar nerve palsy
- Management
- Osteotomy ± nerve transposition
- Consequence
- Loss of flexion
- Management
- Usually tolerated
- Consequence
- Loss of extension
- Management
- Usually tolerated
Nonunion. Occurs in 2-5%, more commonly than in children. Smoking, diabetes, infection and inadequate fixation are the risk factors, and management is revision ORIF with bone graft, or TEA.
Hardware. Fixation failure is a particular risk in osteoporotic bone.
- Cause
- Osteoporosis
- Prevention
- Locking screws, cement
- Cause
- Inadequate fixation
- Prevention
- Longer plates, dual plating
- Cause
- Nonunion
- Prevention
- Ensure union before loading
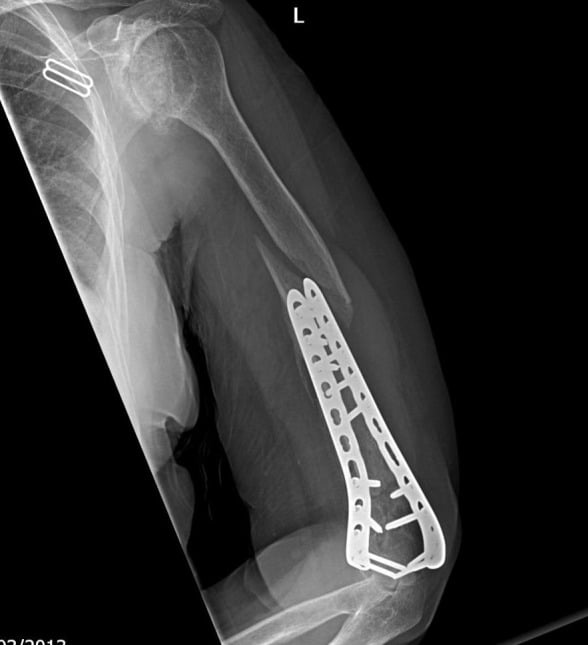
Prominent hardware is common posteriorly and may need removal after union; use low-profile plates when possible. Implants are removed for prominence, nerve irritation, infection, or at the patient's request after union, at a minimum of 12-18 months after fixation and with confirmed radiographic union.
Postoperative Care
Rehabilitation. Four phases, from protection to return to activity.
- Timing
- Weeks 0-2
- Content
- Multimodal analgesia; dressings and monitoring for infection; elevation and compression for oedema; passive and active-assisted ROM as pain allows
- Avoid or target
- Avoid valgus stress and loaded extension
- Timing
- Weeks 2-6
- Content
- Active ROM through the full arc; full pronation and supination; gentle strengthening, isometrics only; night extension splint if stiff
- Avoid or target
- Target 0-130° flexion-extension arc
- Timing
- Weeks 6-12
- Content
- Progressive resistance exercises; ADLs and light work; continue ROM to maintain gains
- Avoid or target
- Target 75% of contralateral strength
- Timing
- 3-6 months
- Content
- Sport-specific or occupational strengthening; gradual return to impact activities
- Avoid or target
- Monitor for regression of stiffness
Follow-up. Radiographs are also taken whenever there is concern for nonunion or hardware failure.
- Assessment
- Wound check, remove sutures, begin ROM
- Assessment
- AP and lateral radiographs for callus formation; ROM assessment
- Assessment
- Radiographs to confirm union progression; functional assessment
- Assessment
- Final union confirmation; final ROM, strength testing
- Assessment
- Discharge if stable
Outcomes and Prognosis
Expected range. After ORIF or TEA:
- ORIF
- 100-130°
- TEA
- 90-130°
- ORIF
- 10-30°
- TEA
- 20-30°
- ORIF
- Near full
- TEA
- Near full
- ORIF
- Near full
- TEA
- Near full
The reason stiffness, not deformity, dominates adult elbow trauma is that the elbow has a narrow functional range, defined by Morrey: most activities of daily living are performed within a 30 to 130 degree flexion-extension arc (a 100-degree arc) and a 50-50 degree pronation-supination arc (50 each way).
A patient can lose terminal extension and terminal flexion and still function, but losing the middle of the arc is disabling. That is why the treatment goal is a stable construct that allows early motion to keep the functional arc, rather than a perfect reduction held rigid in a cast, and why dual-plate fixation morbidity is accepted to permit early ROM.
Warn the patient that some loss of terminal extension is the rule; the realistic target is the functional arc, not a normal one. The same benchmark defines a "successful" outcome on scores such as the Mayo Elbow Performance Score.
Scoring a good result. A good outcome is an MEPS over 80 points, a DASH under 20 points and grip strength over 75% of the other side.
Predictors. Young age, a simple fracture pattern, good bone quality, early ROM and a compliant patient favour a good result. Older age, comminution, osteoporosis, delayed treatment, smoking and diabetes count against it.
- Expected Return
- 2-4 weeks
- Expected Return
- 6-8 weeks
- Expected Return
- 3-4 months
- Expected Return
- 6+ months
- Expected Return
- 6-12 months
In the long term. Stiffness is the most common permanent sequela. Symptomatic post-traumatic arthritis develops in 10-20%, hardware removal may be needed in 10-20%, and secondary TEA is the salvage for failed ORIF or severe stiffness.
Guidelines, Registries & Global Practice
Global Epidemiology
Adult distal humerus fractures show a consistent bimodal distribution worldwide: high-energy injuries in young men and low-energy fragility fractures in older women. Nationwide Finnish registry data (Palvanen et al., Bone 2009) recorded an age-adjusted incidence of low-trauma distal humerus fractures in women aged 60 and over rising from 12 to 34 per 100,000 between 1970 and 1998, then stabilising/declining to roughly 25 per 100,000 by 2007 — a pattern attributed to cohort and fall-prevention effects (DOI). Extra-articular supracondylar (AO/OTA 13-A) patterns make up roughly 10% of distal humerus fractures; the majority are intra-articular (13-C) in elderly cohorts.
Guidance Compared Side by Side
- Position on adult supracondylar / distal humerus fractures
- Bicolumnar (dual-column) fixation of 13-A; restore both columns then absolute/relative stability allowing early motion
- Basis
- Principle-based, supported by biomechanical and clinical series
- Position on adult supracondylar / distal humerus fractures
- Open fractures and fragility upper-limb fractures managed on standard BOAST pathways: senior decision-making, early definitive fixation, bone-health referral
- Basis
- Consensus standards
- Position on adult supracondylar / distal humerus fractures
- Early senior-led fixation and early mobilisation; structured rehabilitation; fragility-fracture/osteoporosis assessment
- Basis
- Guideline (consensus, low-grade evidence)
- Position on adult supracondylar / distal humerus fractures
- No dedicated supracondylar guideline; supports anatomic dual-column ORIF, with primary TEA reserved for non-reconstructable fractures in low-demand elderly
- Basis
- Expert consensus + RCT (McKee)
- Position on adult supracondylar / distal humerus fractures
- Dual-column locking-plate fixation as default; primary TEA an accepted option in selected elderly
- Basis
- Consensus
The single highest-level evidence point shared across bodies: in elderly patients with comminuted, non-reconstructable intra-articular fractures, primary semiconstrained TEA gave better 2-year Mayo Elbow Performance Scores than ORIF (McKee et al., Level I RCT — DOI), with a quarter of ORIF-allocated patients converted intraoperatively because stable fixation could not be achieved.
Registry & Implant Evidence
No joint registry tracks plate-fixation outcomes for supracondylar fractures, but national elbow-arthroplasty data inform the TEA-as-primary-treatment decision. Registries including the NJR (England & Wales), AOANJRR (Australia), AJRR (USA), SHAR/Swedish and NZJR report total elbow replacement as a low-volume procedure with higher revision rates than hip or knee arthroplasty and meaningful early failure when used for acute trauma — reinforcing that primary TEA is reserved for genuinely low-demand patients who can accept a lifelong lifting restriction.
Practice Variation
- High-resource settings: routine CT, precontoured anatomic locking plates, and selective primary TEA; early supervised physiotherapy to combat stiffness.
- Limited-resource settings: conventional reconstruction/one-third tubular plates or non-operative management of stable patterns are more common; TEA and revision capacity are scarce, raising the threshold for arthroplasty.
- Ulnar nerve handling (in-situ decompression vs routine anterior transposition) varies between surgeons and regions without consistent evidence of superiority for routine transposition.
MCQ Practice Points
Q: In an extension-type adult supracondylar fracture, the distal fragment displaces in which direction?
A: Posteriorly (Answer B). Extension type (95% of cases) has posterior displacement of the distal fragment. The mechanism is axial load with elbow extended, causing the distal fragment to angulate posteriorly. Creates classic S-shaped deformity on lateral view.
Q: A supracondylar humerus fracture with involvement of the articular surface should be classified as which AO type?
A: AO 13-C (Answer C). By definition, supracondylar fractures are EXTRAARTICULAR (13-A). Any articular involvement makes it an intercondylar fracture (13-C). This distinction is critical as it changes surgical planning and prognosis.
Q: What is the preferred fixation for adult supracondylar humerus fractures?
A: Dual column plating (Answer C). Dual column plating (perpendicular or parallel) is the gold standard. It provides stability for early ROM, which is critical to prevent stiffness - the most common complication. Single plate fixation has higher failure rates.
Q: What is the most common complication following adult supracondylar humerus fractures?
A: Stiffness (Answer C). Stiffness is the NUMBER ONE complication, with up to 50% of patients losing functional ROM. This is why stable fixation enabling early ROM is the primary treatment goal. Extension loss is most common.
Q: Which nerve is most commonly affected in adult supracondylar fractures and their fixation?
A: Ulnar Nerve (Answer C). The ulnar nerve is most commonly affected (neurapraxia) due to its proximity to the medial column and potential tethering in the cubital tunnel - postoperative dysfunction was 16% at final follow-up in the Vazquez series. Radial nerve injury is also possible with proximal extension or lateral approach. Do not import the paediatric rule here: in a child's extension-type supracondylar fracture the classic answer is the anterior interosseous nerve (median).
Q: Which surgical approach offers the maximal visualization of the articular surface for complex intra-articular fractures?
A: Olecranon Osteotomy (Answer D). While the triceps-splitting/reflecting approaches preserve the extensor mechanism, an olecranon osteotomy provides the most extensile view of the articular surface, essential for restoring congruity in complex comminuted patterns (AO 13-C3).
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old woman presents with a low-energy supracondylar humerus fracture. X-rays show posterior displacement. How would you manage this?”
“Describe your approach to a comminuted supracondylar fracture in an 80-year-old with rheumatoid arthritis and severe osteoporosis.”
“Six months post-ORIF of a supracondylar fracture, your patient has 30-100° of flexion. How do you manage this stiffness?”
“You are planning ORIF for an adult supracondylar fracture. Describe your surgical approach and fixation strategy.”
Definition & Classification
- Extraarticular distal humerus fractures in metaphyseal region
- AO/OTA 13-A (extraarticular): A1 epicondylar avulsion, A2 metaphyseal simple, A3 multifragmentary
- Any articular extension = Intercondylar (AO 13-C)
- Extension type (95%) vs Flexion type (5%)
Key Exam Concepts
- Stiffness is THE major complication (vs deformity in kids)
- Dual column plating is gold standard fixation
- Minimum 6 cortices proximal fixation per column
- Primary TEA valid for elderly, osteoporotic, comminuted
Crucial Management Steps
- CT Scan standard for surgical planning
- Identify Ulnar Nerve early in posterior approach
- Rigid fixation (LOCKING in osteporosis) allows early ROM
- Pre-drill olecranon osteotomy before cutting
Common Pitfalls
- Confusing supracondylar (extraarticular) with intercondylar
- Using single plate fixation (high failure rate)
- Delaying ROM leads to Stiffness (up to 50% incidence)
- Missing ulnar nerve palsy or vascular injury
Evidence Base
Parallel (Bicolumnar) Plating for Distal Humerus Fractures
- 37 AO/OTA type C distal humerus fractures fixed with precontoured parallel (bicolumnar) plates
- All fractures united with no implant failures at mean 27 months
- Mean flexion-extension arc 97 degrees; mean Mayo Elbow Performance Score 82
- 53% complication rate (24 complications in 17 patients), including 16% postoperative nerve injuries