High Arch | Neurological Etiology | Coleman Block Test | Staged Correction
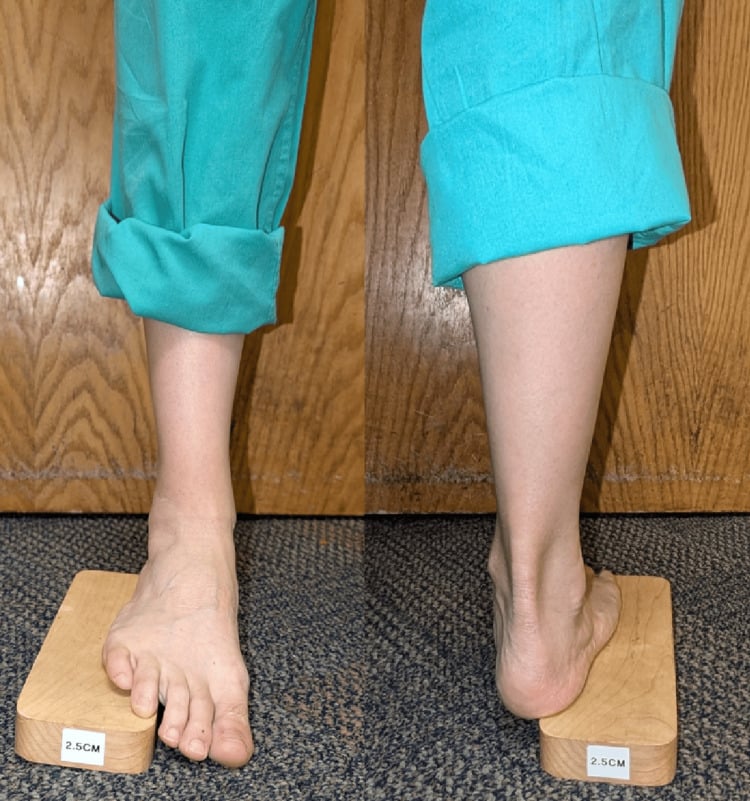
- Coleman block test differentiates flexible vs fixed hindfoot varus - critical for surgical planning
- Neurological workup essential - CMT, spinal dysraphism, tethered cord must be ruled out
- Plantar-flexed 1st ray is the CLASSIC driver (Coleman's tripod model) - but know it is contested: pedobarography shows ~60% of CMT varus feet land in varus BEFORE the first ray contacts, so many are pre-positioned in varus rather than forefoot-driven (Ferguson 2024). Rebalance the deforming forces, do not just correct the first ray
- Conservative management first - orthotics, stretching, observation for mild cases
- Staged surgical correction - soft tissue balancing first, then bony correction if needed
- “Viva question: Walk me through the Coleman block test in a child
- “Always examine for neurological causes - CMT, spinal dysraphism, tethered cord
- “Sequential surgery: plantar fascia release → 1st MT osteotomy → calcaneal osteotomy if needed
- “Complications: overcorrection, growth disturbance, recurrence if underlying cause not addressed
Overview and Epidemiology
The deformity. Paediatric cavus foot is a three-dimensional deformity: a high medial longitudinal arch, often with hindfoot varus and forefoot adduction. It is less common than flatfoot in children, bilateral in 80% and often asymmetric, and it is progressive if left alone.
This page is about the child. If your patient is a skeletally mature adult, the deformity, the workup and the operations differ enough that cavovarus foot is the page you want. In the child the cavus is a symptom you are being shown, and often the first sign of an underlying neurological condition, so the job is to find what is causing it before you correct anything - which is why this page spends more effort on the spine and the nerves than on the osteotomies.
Why the child differs. Adult cavovarus is predominantly CMT-related; the paediatric differential is broader and includes idiopathic cases, spinal dysraphism and other neuromuscular conditions. Neurological causes are commoner in children than in adults, and idiopathic cases may be familial, with an autosomal dominant pattern in some families.
Where the deformity comes from. Cause dictates both the workup and the order of treatment:
- Neurological - 50-60%. CMT is the commonest inherited neuropathy and presents in childhood or adolescence; spinal dysraphism covers spina bifida, tethered cord and diastematomyelia; cerebral palsy gives a spastic cavus from muscle imbalance; residual polio is less common now but still seen; and the wider hereditary motor and sensory neuropathies cover various other types. Progressive, bilateral and accompanied by muscle wasting, and treatment begins with the underlying condition before staged correction.
- Idiopathic - 30-40%. No identifiable cause, and may be familial. Progression is variable and the deformity may stabilise, so conservative treatment comes first and surgery only if it progresses.
- Post-traumatic - 5-10%. Compartment syndrome or malunion. Unilateral, with a history of trauma, and the correction addresses the underlying deformity.
- Arthrogryposis - multiple joint contractures, the foot among them.
- Muscular dystrophy - Duchenne and other types.
Natural history. The muscle imbalance does not stop, so the deformity worsens over the years, and the consequences accumulate:
- Lateral ankle instability - recurrent sprains from a varus heel strike
- Peroneal tendinopathy
- Metatarsalgia - the plantar-flexed first ray and the claw toes concentrate pressure
- Stress fractures - lateral column overload, commonly the fifth metatarsal
- Arthritis - midfoot and ankle degeneration by adulthood if untreated
Why early matters. Recognising the deformity early lets the underlying cause be worked up and treated, and intervening early prevents the severe fixed deformity that ends in triple arthrodesis.
Pathophysiology and Mechanisms
The tripod model. The classic driver, Coleman's tripod model, is a plantar-flexed first metatarsal. In CMT the peroneus longus is relatively spared and overpowers a weak tibialis anterior, so it is the strong longus, not a weak one, that pulls the first ray down. The first ray drops plantarwards, the medial arch rises, and the forefoot has to pronate to bring the heel to the ground, which produces a functional hindfoot varus.
What follows from it. The compensations become the deformity: forefoot pronation to accommodate the plantar-flexed first ray, hindfoot varus that is functional at first and becomes fixed, claw toes from flexor overpull with intrinsic weakness, and a tight plantar fascia that holds the arch elevated.
Do not recite the tripod as settled. Dynamic pedobarography in 118 CMT feet found first-ray contact preceded fifth-ray contact in only 39.7% of varus feet - no different from non-varus feet (34.0%, p=0.526). Around 60% landed already in varus before the first ray touched down, meaning the foot is often pre-positioned in varus by proximal muscle imbalance rather than levered there by the forefoot (Ferguson 2024).
The surgical consequence is real. Rebalance the deforming forces; do not assume a first-ray osteotomy alone addresses the cause.
- Status
- Weak
- Effect
- Cannot evert hindfoot
- Clinical Finding
- Hindfoot varus, lateral ankle instability
- Status
- Overactive
- Effect
- Inverts hindfoot
- Clinical Finding
- Worsens varus, creates adduction
- Status
- Weak
- Effect
- Cannot stabilize metatarsals
- Clinical Finding
- Claw toes, metatarsalgia
- Status
- Weak (CMT)
- Effect
- Cannot dorsiflex
- Clinical Finding
- Foot drop, steppage gait
CAVECavus Foot Deformity Components - CAVE
Hook:CAVE: The child's foot is stuck in a CAVE - deep arch, toes clawed, heel turned in!
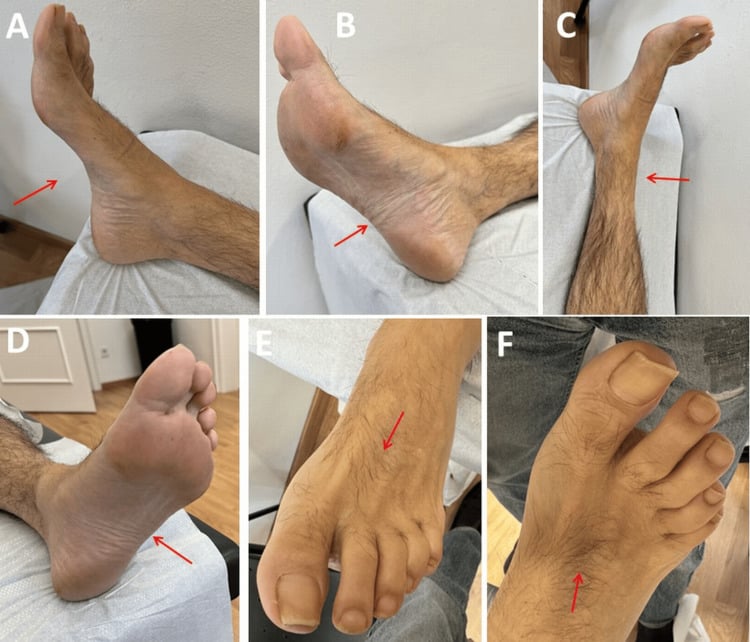
Calcaneocavus breaks the rule. In this pattern the calcaneus is dorsiflexed rather than the forefoot plantarflexed, usually following poliomyelitis or triceps weakness, and plantar release with forefoot osteotomy will not correct it.
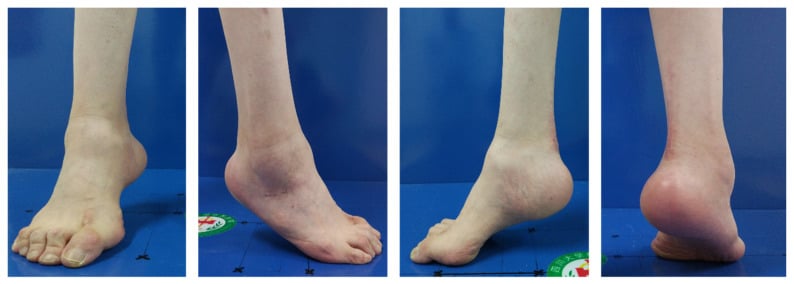
Classification Systems
Severity is graded on how much of the deformity is fixed, how symptomatic the foot is, and the calcaneal pitch. Note that mild is a pitch of 25-30 degrees while the radiographic threshold for calling a foot cavus is over 30 degrees, so a pitch in the high twenties sits inside the mild band and below the cavus threshold at the same time.
- Clinical Features
- High arch only, no varus, asymptomatic
- Radiographic Findings
- Calcaneal pitch 25-30 degrees
- Treatment
- Observation, orthotics
- Clinical Features
- Cavus + flexible hindfoot varus, some symptoms
- Radiographic Findings
- Calcaneal pitch 30-40 degrees, flexible on Coleman block
- Treatment
- Plantar fascia release + 1st MT osteotomy
- Clinical Features
- Cavus + fixed hindfoot varus, clawing, instability
- Radiographic Findings
- Calcaneal pitch over 40 degrees, fixed on Coleman block
- Treatment
- Staged reconstruction
Clinical Assessment
What the assessment is for. Two questions run in parallel: how much of the deformity is fixed, and what is causing it. Missing the underlying diagnosis delays appropriate treatment and may allow progression to a severe fixed deformity.
History. Ask when the high arch was first noticed and whether it is getting worse, then ask the questions that decide how hard you look for a cause:
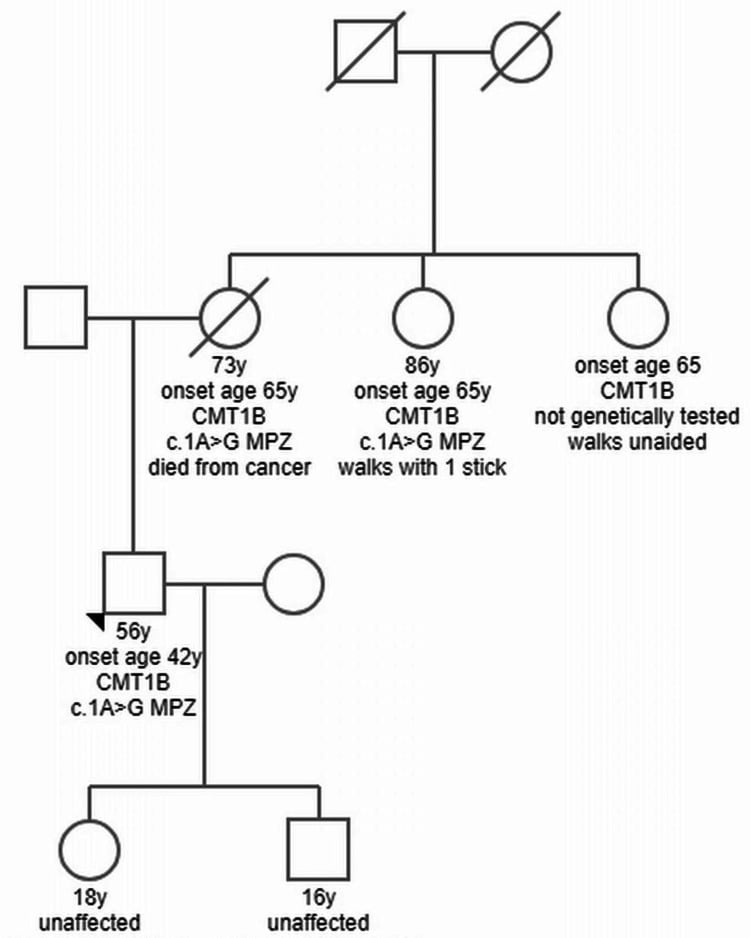
- Family history - CMT, other neuropathies, or a similar foot deformity in a relative
- Neurological symptoms - weakness, numbness, balance problems
- Spinal symptoms - back pain, bladder or bowel problems, which point to a tethered cord
- Functional limitations - ankle sprains, metatarsalgia, difficulty with shoes
- Bilateral involvement - and whether the two feet are affected equally
Red flags. Each of these moves the diagnosis away from idiopathic cavus:
- Progressive weakness - suggests a neurological cause
- Family history of CMT - autosomal dominant inheritance
- Back pain or urinary symptoms - suggest dysraphism
- Unilateral, with a history of trauma - a post-traumatic cause
- Rapid progression - may indicate spinal pathology
Examination. Work through the foot in the same order every time, and finish with the neurological assessment rather than leaving it out.
Systematic Examination
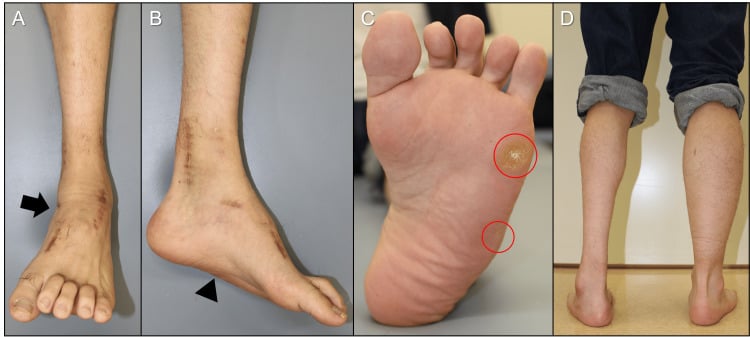
- High medial arch and the peek-a-boo heel sign - the toes visible from behind, medial to the ankle
- Hindfoot varus - heel turned inward, worse on weight-bearing
- Claw toes - hyperextension at the MTP joints with flexion at the PIP and DIP joints
- Muscle wasting - anterior and lateral compartments, the stork leg of CMT
- Calluses under the first metatarsal head and along the lateral border
- Compare both feet and assess symmetry
- Plantar fascia tight and prominent
- First metatarsal head plantar-flexed and prominent
- Lateral border - calluses and stress fracture sites
- Peroneal tendons may be tender, subluxed or torn
- ATFL and CFL may be lax from recurrent sprains
- Ankle dorsiflexion may be limited - the equinus component
- Hindfoot inversion and eversion - assess strength and flexibility
- Forefoot - plantar-flexed first ray, forefoot pronation
- Toes - clawing, with limited extension at the MTP joints
- Coleman block test - the test that decides the operation
- Muscle strength - peroneals, tibialis anterior, tibialis posterior
- Neurological examination - sensation, reflexes, Babinski
- Gait - varus heel strike, lateral foot contact, steppage if tibialis anterior is weak
- Spine - midline defects, hair tufts, dimples
- Reflexes - may be absent in CMT
- Sensation - stocking distribution loss in the neuropathies
- Upper limbs - CMT may affect the hands, with intrinsic wasting
- Family - examine parents and siblings for subtle signs
Read the sole. Callus and footprint tell you how the foot is actually loaded, before any radiograph is taken.
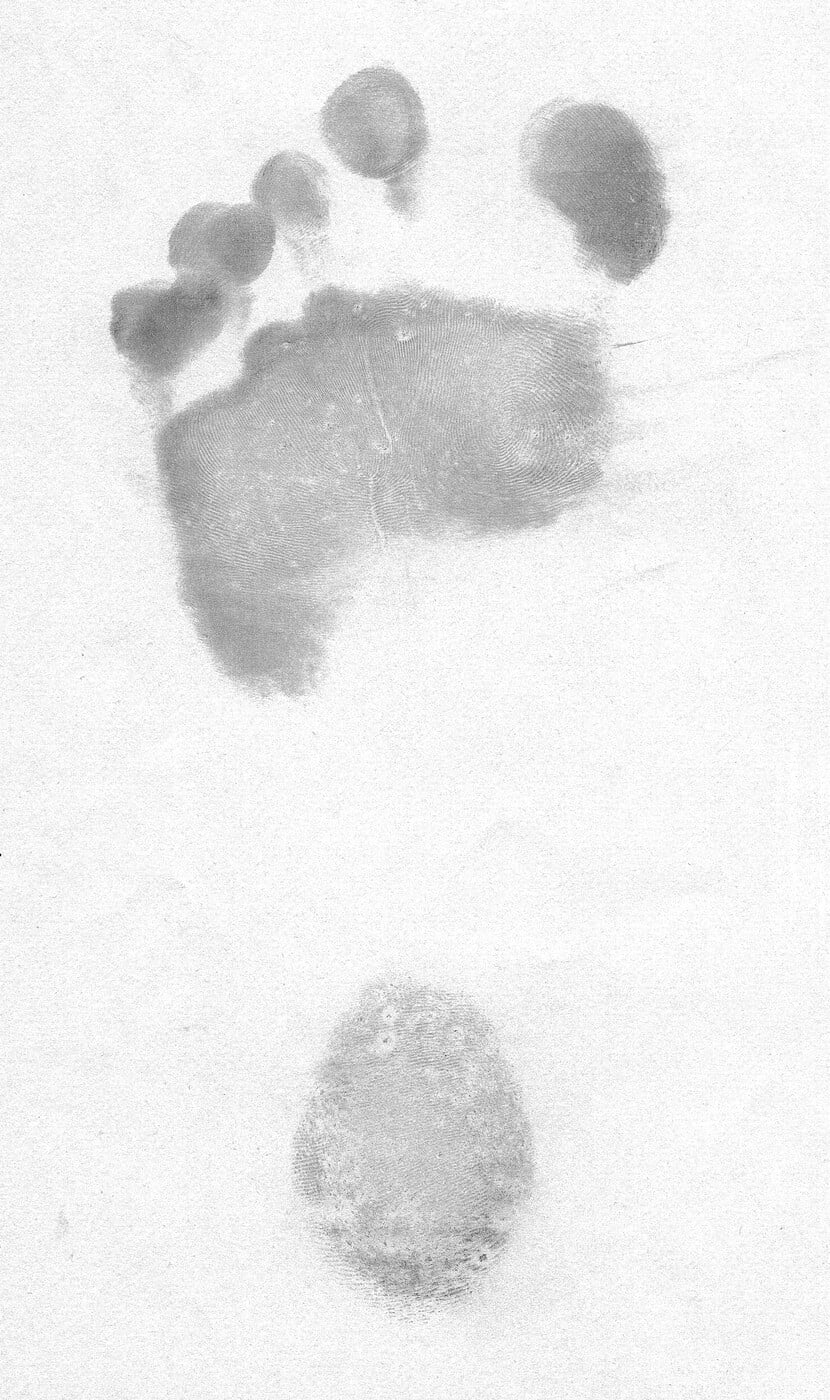
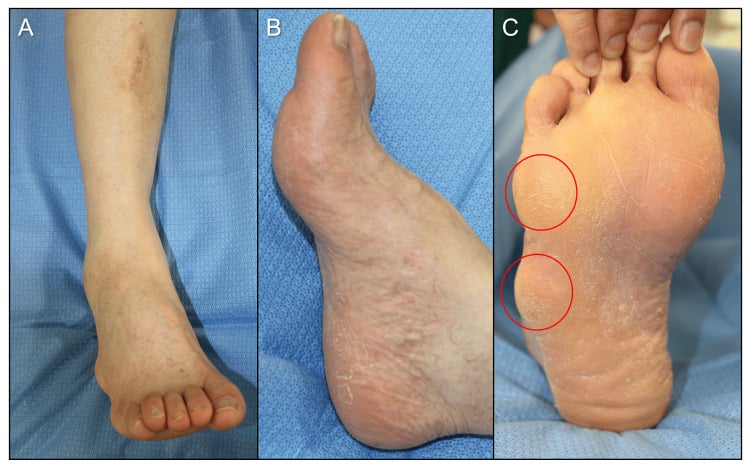
Spinal dysraphism and tethered cord commonly present with cavus foot. In any child with a cavus foot, and especially if it is progressive or accompanied by neurological symptoms, you must examine the spine for midline defects, hair tufts, dimples or other stigmata, and consider a spinal MRI if there is any suspicion. Missing a tethered cord can lead to permanent neurological damage.
Differential Diagnosis of the High-Arched / Cavus Foot in Children
- Distinguishing Features
- Progressive cavovarus, intrinsic and peroneal wasting, hand involvement, family history
- Laterality / Onset
- Usually bilateral, adolescent onset
- Key Discriminator
- Genetic test (PMP22 duplication in CMT1A), nerve conduction studies
- Distinguishing Features
- Asymmetric deformity, back/midline stigmata, bladder/bowel symptoms, upper motor neuron signs
- Laterality / Onset
- Often unilateral or asymmetric, may progress rapidly
- Key Discriminator
- Whole-spine MRI
- Distinguishing Features
- Spasticity, brisk reflexes, equinocavovarus, birth history
- Laterality / Onset
- Hemiplegic equals unilateral; diplegic equals bilateral
- Key Discriminator
- Upper motor neuron signs, developmental history
- Distinguishing Features
- Forefoot adductus, cavus, hindfoot varus, history of clubfoot correction
- Laterality / Onset
- Bilateral or unilateral, congenital
- Key Discriminator
- History of CTEV and prior casting/surgery
- Distinguishing Features
- Mild high arch, neutral or mild varus, normal neurology
- Laterality / Onset
- Bilateral, may be familial
- Key Discriminator
- Normal neurological and spinal examination by exclusion
- Distinguishing Features
- Unilateral, intrinsic contracture, history of crush/fracture
- Laterality / Onset
- Unilateral, acquired
- Key Discriminator
- Clear antecedent trauma or compartment syndrome
Where each of these is worked up. The differential above is really a differential of causes, and each has its own page: Charcot-Marie-Tooth disease and the wider family of hereditary motor and sensory neuropathies (which is where the muscle-balance logic behind every tendon transfer is set out), tethered cord syndrome for the asymmetric foot with spinal stigmata, Friedreich's ataxia where cavus comes with ataxia and cardiomyopathy, spastic equinovarus foot for the cerebral palsy pattern, and clubfoot for the residual or overcorrected foot that looks cavus but has a treatment history behind it. The radiographic measurement the whole assessment turns on is Meary's angle.
A truly unilateral or markedly asymmetric paediatric cavus foot is a red flag for a focal spinal cord lesion (tethered cord, diastematomyelia, intraspinal tumour) rather than CMT, which is typically symmetrical and bilateral. This pattern lowers the threshold for whole-spine MRI substantially.
Investigations
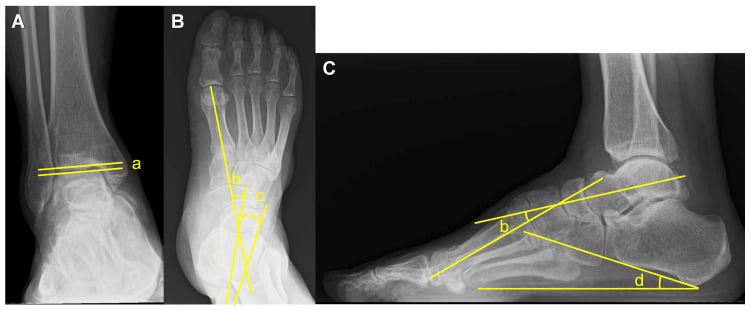
Radiographs. Take them weight-bearing, and know what each view answers:
- AP foot - forefoot adduction, the metatarsal break pattern, degenerative change
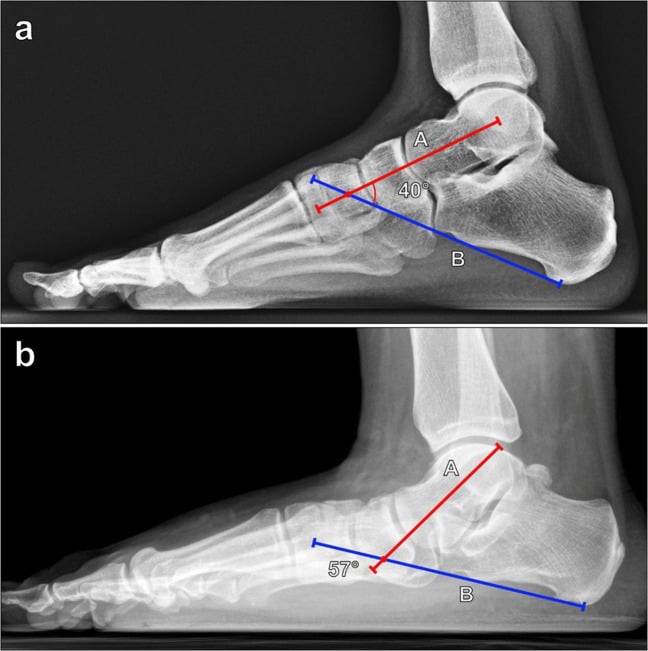
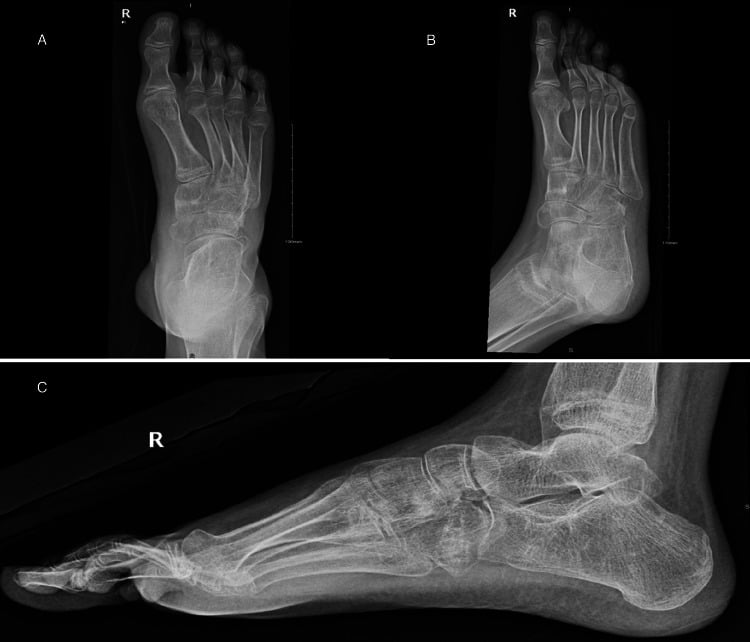
- Lateral foot - the calcaneal pitch (normal 20 degrees), the Meary angle for the lateral arch, and first metatarsal plantar-flexion
- AP ankle - ankle joint arthritis, and talar tilt from chronic instability
- Hindfoot alignment view (Saltzman) - quantifies hindfoot varus; a plumb line falling medial to the heel means varus
The numbers to quote. Calcaneal pitch greater than 30 degrees is cavus, a Meary angle less than 150 degrees means an elevated lateral arch, and a talar-first metatarsal (Meary) line with its apex plantar is cavus. These measurements are what surgical planning and the monitoring of progression are built on.
Neurological work-up. Order it when the history, the examination or an asymmetric deformity raises the question of a cause:
- Nerve conduction studies - reduced motor and sensory conduction velocities in CMT type 1, the demyelinating form
- Electromyography - a denervation pattern in the affected muscles
- Genetic testing - PMP22 duplication for CMT1A, which accounts for 70% of CMT cases
- MRI of the spine - for any suspicion of spinal dysraphism or tethered cord, and critical in the child
MRI of the foot and ankle. This is a surgical planning study rather than a diagnostic one. It shows the peroneal tendons, where split tears and subluxation are common with a varus hindfoot, chronic ATFL and CFL injury from recurrent sprains, degenerative change in the ankle cartilage, and the quality of the plantar fascia and posterior tibial tendon that any soft-tissue balancing will rely on.
Order a spinal MRI in paediatric cavus if any one of these is present: (1) progressive deformity, (2) neurological symptoms - weakness, numbness, bladder or bowel, (3) spinal stigmata on examination - midline defects, hair tufts, (4) no family history of CMT, which points away from CMT without excluding it, or (5) a unilateral or asymmetric deformity.
Management Algorithm
The decision. Most children with mild cavus never need surgery, and many cases stabilise or improve with growth, so conservative treatment is first-line for the mild and the flexible foot. Surgery belongs to the foot that progresses, hurts, or has gone fixed - and because a fixed deformity is harder to correct, it should not be delayed unnecessarily.
- Coleman Block Result
- N/A - observation
- Primary Management
- Custom orthotics, stretching, observation
- Key Pearl
- Many children never need surgery
- Coleman Block Result
- Hindfoot corrects to neutral on block
- Primary Management
- Plantar fascia release + 1st MT osteotomy
- Key Pearl
- Forefoot-driven deformity - fix the 1st ray
- Coleman Block Result
- Hindfoot stays varus on block
- Primary Management
- Add calcaneal lateralizing osteotomy
- Key Pearl
- Fixed deformity needs bone realignment
- Coleman Block Result
- Fixed hindfoot, weak eversion
- Primary Management
- Staged: soft tissue first, then calcaneal osteotomy + tendon transfers
- Key Pearl
- Address underlying neurological condition
Non-Operative Management (First-Line for Mild Cases)
Conservative Treatment Protocol
An asymptomatic mild cavus needs observation only: serial clinical examination and radiographs to detect progression, and reassurance for the family that many cases stabilise or improve with growth. No intervention is needed while there are no functional limitations.
Custom orthotics with a lateral wedge accommodate the varus, and a metatarsal pad relieves forefoot pressure. AFOs (ankle-foot orthoses) support weak dorsiflexors and prevent foot drop, UCBL (University of California Biomechanics Laboratory) inserts control hindfoot varus, and shoe modifications - a lateral heel wedge, a rocker bottom - do the rest.
Plantar fascia stretching may help mild cases, and Achilles stretching is added where there is an equinus component. Strengthen the peroneals and tibialis anterior if they are weak, and add balance training, which is important in the neurological causes.
Casting may help correct a mild cavus in a flexible deformity, but it is not as effective as in clubfoot because cavus is the more rigid deformity. Its other use is pre-operative, to stretch the soft tissues before correction.
What it is. Fusion of the three hindfoot joints - subtalar, talonavicular and calcaneocuboid - correcting a fixed deformity through the fusion mass to produce a plantigrade, stable foot. The staged, joint-preserving plan above exists to avoid it, but you must be able to discuss it as the salvage option.
When it is used. A rigid, fixed, often arthritic cavovarus foot that cannot be balanced by osteotomy and tendon transfer: typically the mature or near-mature, end-stage deformity, or a failed reconstruction.
Why it is a last resort, especially in CMT. It sacrifices hindfoot motion and transfers stress to adjacent joints, accelerating ankle and midfoot arthritis, and in the progressive, often insensate CMT foot the results deteriorate over time. Pseudarthrosis, classically of the talonavicular joint, is common, and the deformity can recur or progress at the ankle because the underlying muscle imbalance persists. That is why the growing foot is offered joint-preserving reconstruction instead.
Even when arthrodesis is needed. The trend is towards limited or selective fusions with concurrent tendon balancing, because an unbalanced fused foot still fails.
Surgical Technique
Staged Surgical Correction
Why stage it. Correcting everything at once removes the chance to see what each step achieved. Staging allows reassessment after each stage, many feet are corrected by Stage 1 alone, and the risk of overcorrection and other complications is lower than with a single-stage correction.
Stage 1: Soft Tissue Balancing
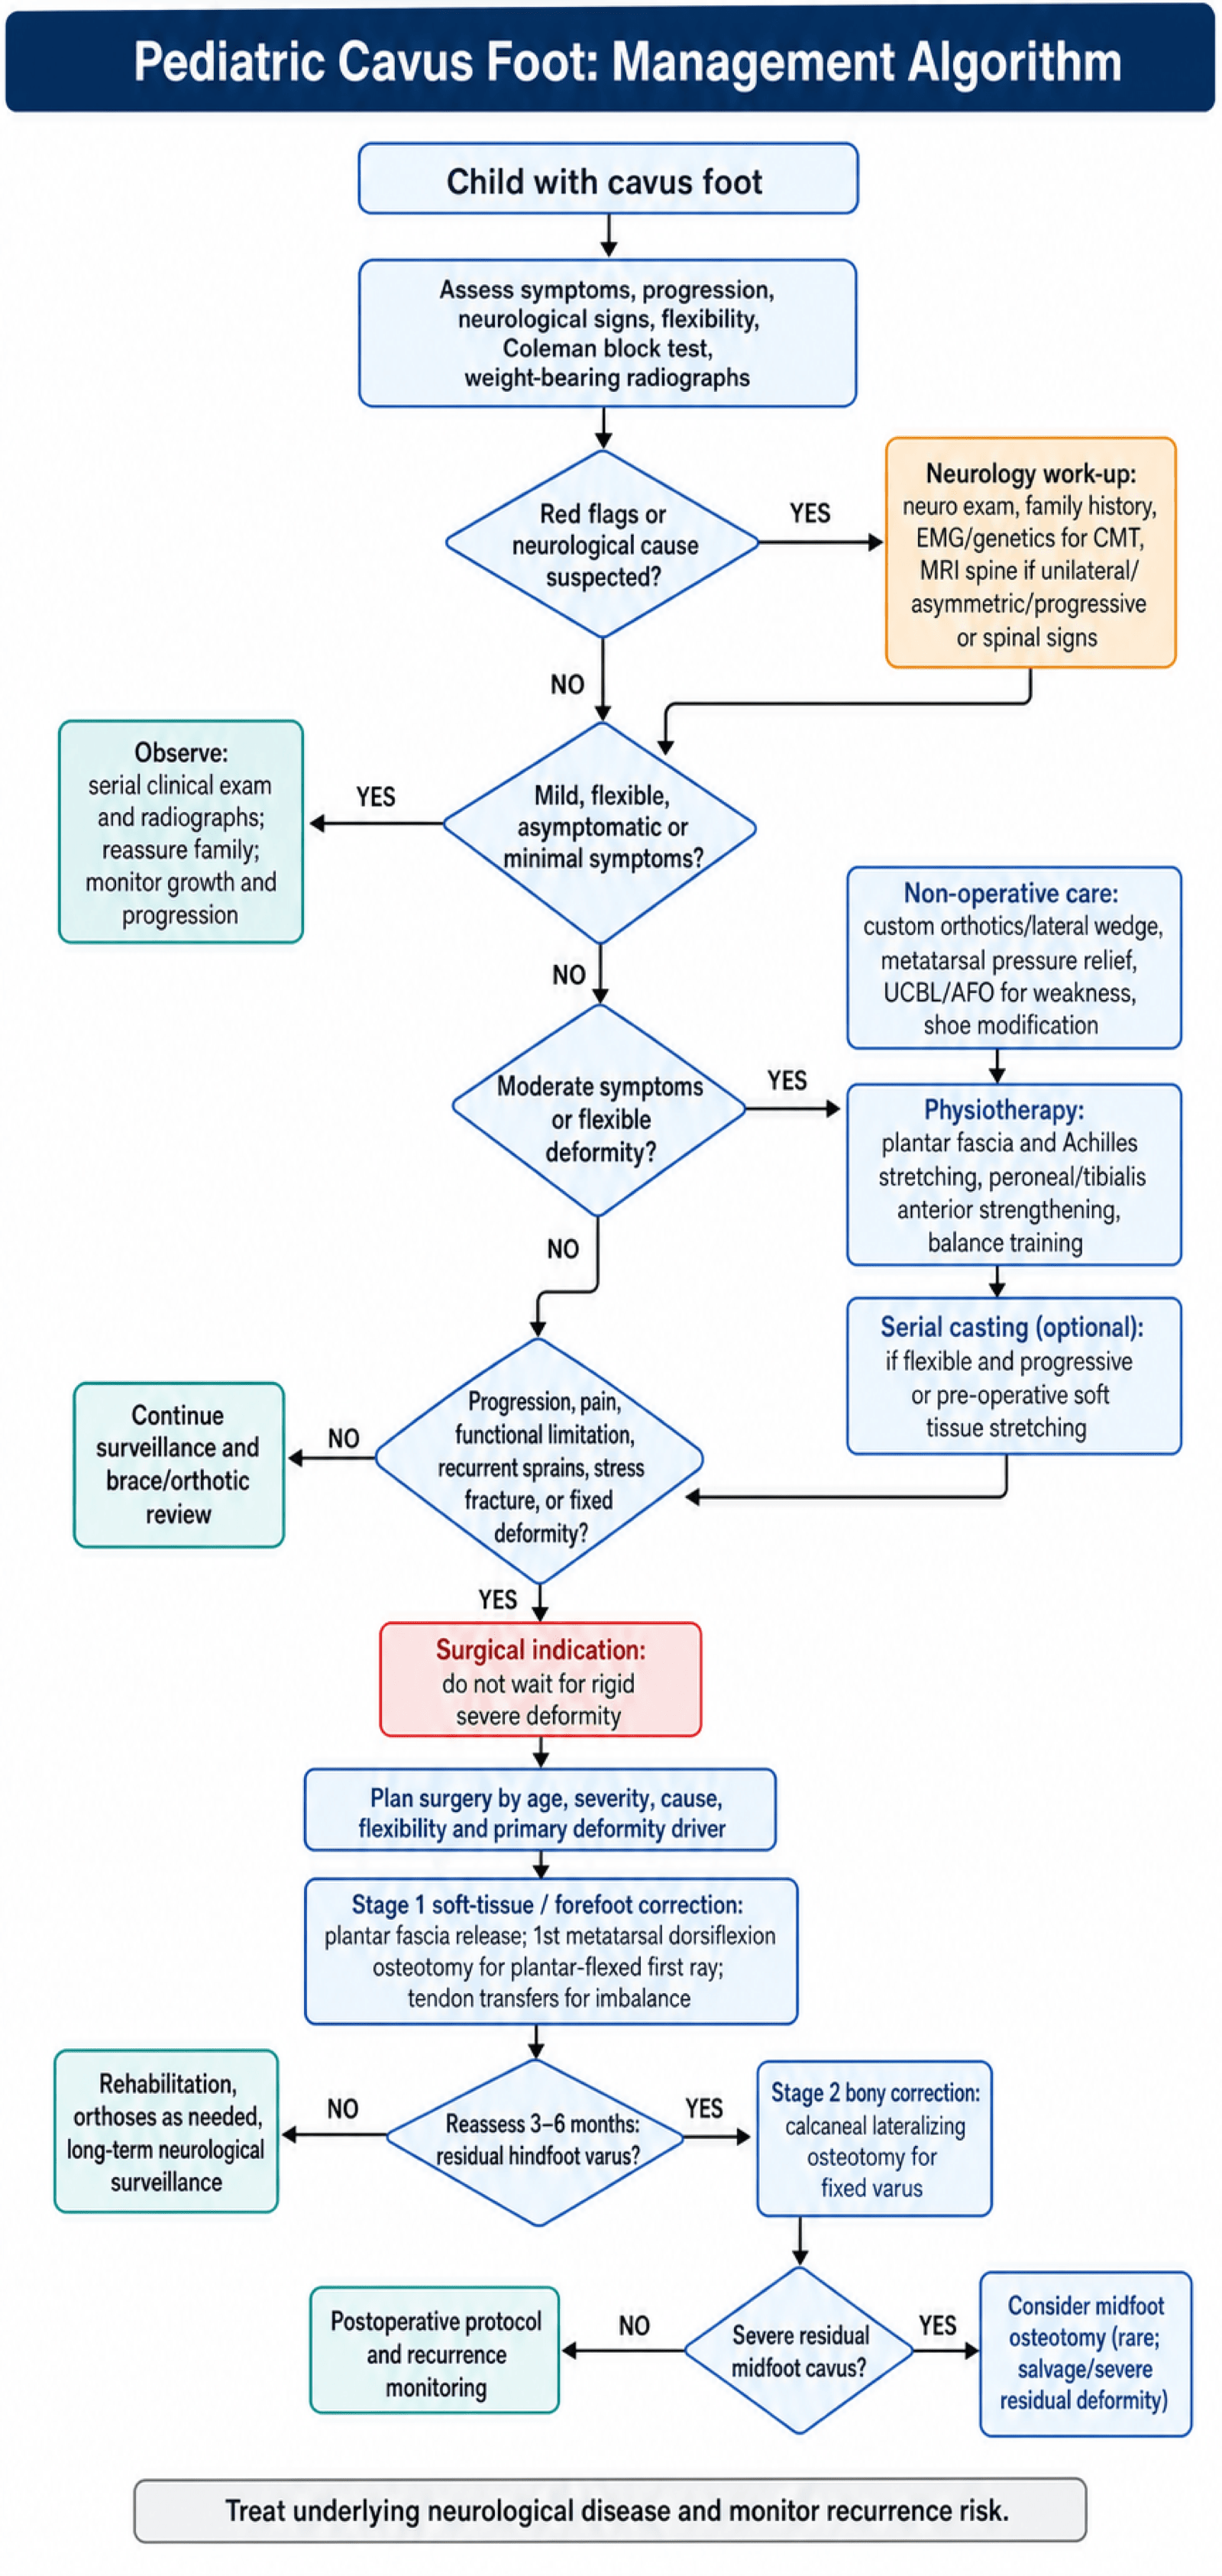
Release the plantar fascia, open or endoscopically, through a medial or plantar incision, taking the central and medial bands. The aim is to drop the arch and reduce the cavus. The child then weight-bears in a cast for 2-3 weeks.
A dorsal closing wedge osteotomy of the first metatarsal, through a dorsal approach, preserving the growth plate if it is still open. Fix with K-wires or screws depending on the age of the child, then non-weight-bearing for 4-6 weeks. This is the step that corrects the plantar-flexed first ray, the classic driver of the deformity.
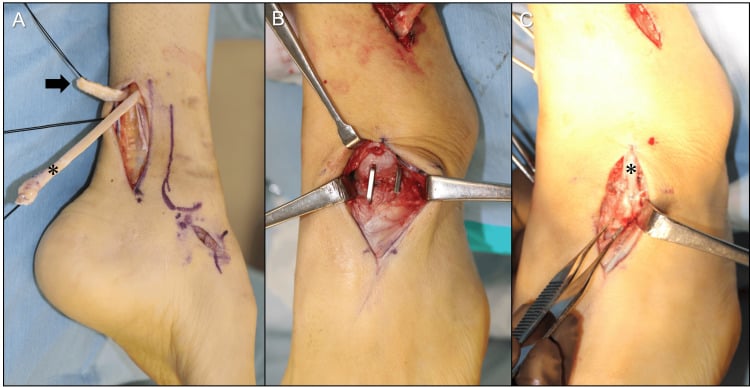
Peroneus longus to peroneus brevis where the brevis is weak, the CMT pattern. Posterior tibial transfer to the dorsum for severe imbalance, and EHL or FHL transfers for severe claw toes. These can be done with Stage 1 or with Stage 2.
Stage 2: Bony Correction (If Needed)
Re-examine the foot, repeat the radiographs and repeat the Coleman block test. If the hindfoot is still varus, proceed to Stage 2; if it has corrected, Stage 2 may not be needed at all.
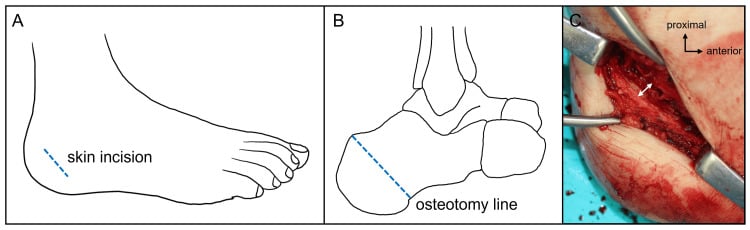
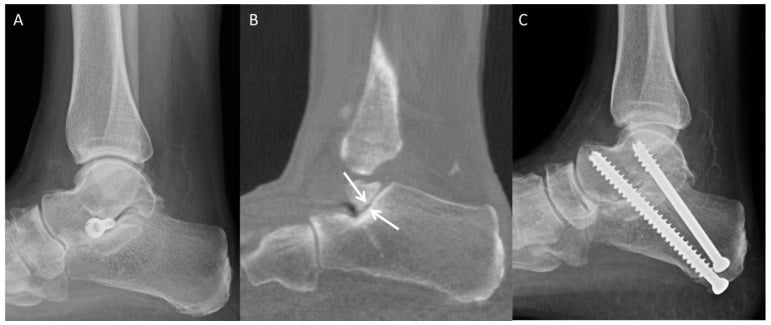
A lateral closing wedge or lateralising slide osteotomy corrects the fixed hindfoot varus. Use a lateral approach, preserving the peroneal tendons, fix with screws while avoiding an open growth plate, and keep the child non-weight-bearing for 6-8 weeks.
A Cole midfoot dorsal closing wedge osteotomy for severe residual midfoot cavus, indicated only if significant cavus remains after Stages 1 and 2. It is rarely needed, because most feet are corrected by then.

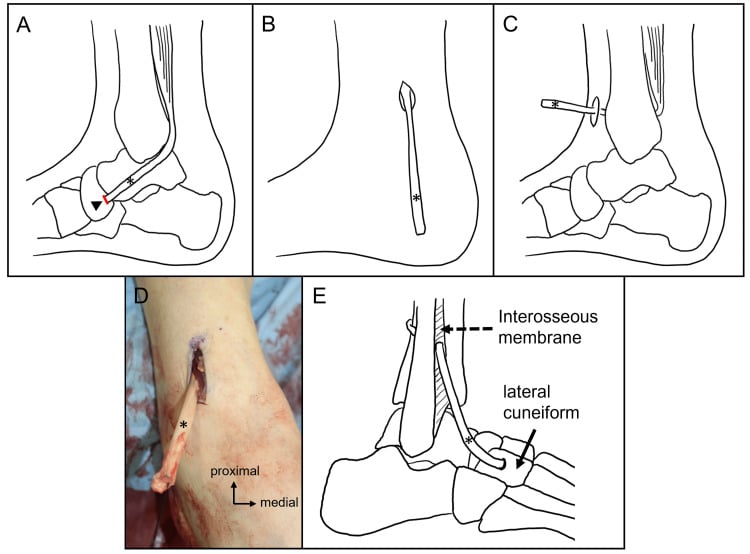
- Peroneus longus to peroneus brevis: the central CMT transfer. The peroneus longus is relatively strong and plantarflexes the first ray (a deforming force); the peroneus brevis (the main everter) is weak. Transferring PL into PB removes the first-ray plantarflexion force and augments eversion in one move.
- Jones transfer: extensor hallucis longus transferred to the first metatarsal neck, combined with interphalangeal joint fusion of the hallux. It removes the EHL's deforming pull on the cock-up great toe, recruits it to help dorsiflex the first ray/forefoot, and corrects the clawed hallux.
- Hibbs transfer: extensor digitorum longus transferred to the lateral cuneiform (with IP fusions of the lesser toes) - removes the recruited long-toe-extensor pull that causes lesser-toe clawing and adds dorsiflexion power to the midfoot.
- Tibialis posterior transfer to the dorsum (through the interosseous membrane): for the weak/foot-drop CMT or dysraphic foot, to restore active dorsiflexion and remove the deforming inversion force.
Complications
- Incidence
- 5-10%
- Risk Factors
- Aggressive calcaneal osteotomy
- Management
- Reverse calcaneal osteotomy if severe
- Incidence
- 10-20%
- Risk Factors
- Underlying cause not addressed, growth
- Management
- Re-operation, address underlying condition
- Incidence
- 5-10%
- Risk Factors
- Calcaneal osteotomy, poor fixation
- Management
- Revision with bone graft
- Incidence
- Rare
- Risk Factors
- Osteotomy through growth plate
- Management
- Monitor growth, may need epiphysiodesis
- Incidence
- Rare
- Risk Factors
- Lateral approach to calcaneus
- Management
- Usually resolves, may need exploration
- Incidence
- 10-15%
- Risk Factors
- Multiple procedures, severe deformity
- Management
- Aggressive rehabilitation
Recurrence is common if the underlying neurological cause is not addressed. CMT, spinal dysraphism and the other progressive conditions carry on causing muscle imbalance: surgery corrects the deformity but does not treat the condition behind it. Ongoing management of the neurological condition is essential to prevent recurrence.
Postoperative Care and Rehabilitation
Whose protocol this is. The timeline below follows the bony procedures. An isolated plantar fascia release is different: that foot weight-bears in its cast.
Postoperative Protocol
Cast immobilisation, non-weight-bearing, with the limb elevated to reduce swelling, adequate analgesia, and wound care with surveillance for infection.
Continue non-weight-bearing until there is radiographic healing, with gentle range of motion at the ankle, subtalar and midfoot joints where they have not been fused. Watch the incisions, and take radiographs at 6 weeks to check healing.
Weight-bear gradually as tolerated and progress to full, with physiotherapy for strengthening, stretching and gait training. Custom orthotics may be needed post-operatively, and high-impact activity is avoided initially.
Full weight-bearing with a normal gait pattern, and sport-specific training where it applies. Clinical and radiographic follow-up watches for recurrence while the underlying neurological condition continues to be managed.
Long-term follow-up. Annual clinical and radiographic assessment, particularly where the underlying cause has not been addressed, with further procedures if the deformity recurs.
Outcomes
Results. Staged correction gives good to excellent results in 80-90%, better outcomes than single-stage correction, and most children return to normal activities.
Predictors of a poor outcome.
- Underlying neurological cause not addressed
- Fixed deformity at presentation
- Overcorrection to valgus
- Nonunion after calcaneal osteotomy
- Growth disturbance
Guidelines, Registries & Global Practice
Global epidemiology. Charcot-Marie-Tooth disease is the most common inherited peripheral neuropathy, with population prevalence generally cited around 1 in 2,500, and CMT1A (PMP22 duplication) accounting for the majority of demyelinating cases. Because over half of children with CMT develop foot and ankle problems, of which cavovarus is by far the commonest pattern, cavovarus foot is a near-universal management consideration in paediatric neuromuscular clinics worldwide (Olney, Foot Ankle Clin 2000, PMID 11232232; Schwend & Drennan, J Am Acad Orthop Surg 2003, PMID 12828450). In a paediatric population, neurological causes (CMT, spinal dysraphism, cerebral palsy, residual polio in low-income settings) predominate over the idiopathic cavus that is relatively more common in adults.
Side-by-side guidance and consensus across regions. There is no single high-level (RCT-based) international guideline that dictates operative thresholds for paediatric cavovarus; practice is built on instructional reviews, expert consensus and observational cohorts. The convergent principles below are drawn from the verified evidence base.
- Region
- North America
- Position
- Neurological assessment directs treatment; preserve a plantigrade mobile motor-balanced foot; favour soft-tissue release and osteotomy over arthrodesis; reserve triple arthrodesis as salvage
- Evidence Level
- Level 5 (expert review)
- Region
- International (foundational)
- Position
- Flexible hindfoot varus = forefoot/soft-tissue surgery; fixed varus = calcaneal osteotomy
- Evidence Level
- Level 5 (foundational technique)
- Region
- Europe
- Position
- Early bracing once progression detected can avoid or delay surgery to a single procedure near maturity
- Evidence Level
- Level 4 (cohort)
- Region
- UK
- Position
- Multidisciplinary paediatric orthopaedic and neurology pathway; whole-spine MRI for asymmetric or atypical cavus; staged joint-preserving correction
- Evidence Level
- Consensus / pathway
- Region
- Europe
- Position
- Joint-preserving, deformity-specific reconstruction preferred over early arthrodesis in the growing foot
- Evidence Level
- Consensus / review
- No dedicated international paediatric cavovarus registry exists; evidence is from single-centre prospective and retrospective cohorts
- Prospective cohort data support joint-preserving subtalar (talocalcaneonavicular) realignment for severe resistant deformity with low complication rates (PMID 39382214)
- Dynamic pedobarography cohorts question the universal "forefoot-driven" model, favouring force-rebalancing strategies (PMID 39132914)
- National CMT patient registries (e.g. INC/RDCRN, European CMT networks) capture natural history but not foot-surgery outcomes specifically
- Bracing-first vs early-surgery thresholds vary markedly between European and North American centres
- Use of single-stage vs staged reconstruction varies with surgeon preference and deformity rigidity
- In low-resource settings residual poliomyelitis remains a relevant cause; access to genetic testing and MRI is uneven globally
- Universal agreement on two points: exclude a neurological cause, and use the Coleman block test to guide hindfoot surgery
Key documentation points:
- Thorough neurological examination performed (including upper limbs and reflexes)
- Coleman block test result documented (flexible vs fixed)
- Discussion of underlying causes (CMT, spinal pathology, cerebral palsy)
- Spinal examination findings (midline defects, hair tufts, dimples)
- Indication for and result of whole-spine MRI if ordered
- Discussion of recurrence risk if the underlying cause is not addressed
Don't Miss Spinal Pathology: Missing tethered cord or spinal dysraphism in a child with cavus foot is a serious clinical error. Always document the spinal examination and the reasoning for or against whole-spine MRI, particularly for any unilateral or asymmetric deformity.
MCQ Practice Points
Q: What does the Coleman block test determine in cavus foot? A: The Coleman block test determines if hindfoot varus is flexible (forefoot-driven) or fixed. Patient stands on 1-inch block under lateral foot with 1st and 2nd rays off. If hindfoot corrects to neutral = flexible, 1st MT osteotomy may suffice. If stays varus = fixed, needs calcaneal osteotomy.
Q: What is the most common neurological cause of pediatric cavus foot? A: Charcot-Marie-Tooth (CMT) disease is the most common neurological cause. CMT is an inherited motor and sensory neuropathy that causes progressive muscle weakness and imbalance, leading to cavovarus foot deformity. Always consider CMT in pediatric cavus, especially if bilateral and progressive.
Q: What is the recommended surgical approach for pediatric cavus foot? A: Staged correction is preferred. Stage 1: Plantar fascia release + 1st metatarsal dorsiflexion osteotomy. Reassess after 3-6 months. Stage 2: Calcaneal lateralizing osteotomy only if hindfoot varus persists. Staged approach has better outcomes and lower complication rates than single-stage correction.
Q: What is the primary driver of cavus foot deformity? A: Plantar-flexed 1st metatarsal is the primary driver. The tripod effect: plantar-flexed 1st ray forces forefoot to pronate to get heel to ground, creating functional hindfoot varus. Correcting the 1st ray often corrects the hindfoot without calcaneal osteotomy if flexible.
Q: When should you order spinal MRI in pediatric cavus foot? A: Order spinal MRI if: progressive deformity, neurological symptoms (weakness, numbness, bladder/bowel), spinal stigmata on exam (midline defects, hair tufts), negative family history (which points away from CMT without excluding it), or unilateral/asymmetric presentation. Missing tethered cord or spinal dysraphism has serious consequences.
Q: What is the recurrence rate after cavus foot correction? A: 10-20% recurrence rate, especially if underlying neurological cause is not addressed. CMT and other progressive conditions continue to cause muscle imbalance. Surgery corrects the deformity but does not treat the underlying condition. Ongoing neurological management is essential.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 10-year-old boy presents with bilateral high arches. His parents noticed the arches getting higher over the past year. He has had several ankle sprains.”
“A 14-year-old girl with CMT has progressive bilateral cavovarus feet. The Coleman block test shows the hindfoot corrects to neutral on the right but stays varus on the left.”
“A 12-year-old boy had a calcaneal lateralizing osteotomy for cavovarus foot 6 months ago. He now presents with a valgus hindfoot and lateral ankle pain.”
Key Pathophysiology
- 50-60% neurological cause - CMT most common
- Plantar-flexed 1st ray = primary deformity driver
- Tripod effect: 1st MT too low → forefoot pronates → hindfoot varus
- Coleman block test = gold standard for flexibility
Clinical Assessment
- Coleman block test: Stand on 1-inch block under lateral foot - does hindfoot correct?
- Neurological exam: Muscle strength, reflexes, sensation, spine examination
- Muscle wasting: Anterior/lateral compartments (stork leg in CMT)
- Calcaneal pitch angle: greater than 30 degrees = cavus (normal 20 degrees)
Etiology Workup
- CMT: Family history, nerve conduction studies, genetic testing
- Spinal dysraphism: Spine exam, spinal MRI if any suspicion
- Tethered cord: Progressive deformity, bladder/bowel symptoms, spinal MRI
- Idiopathic: No underlying cause, may be familial
Surgical Algorithm
- Hindfoot CORRECTS on the block (flexible): Plantar fascia release + 1st MT osteotomy
- Hindfoot STAYS VARUS on the block (fixed): Add calcaneal lateralizing osteotomy
- Say what the hindfoot DID, never 'positive' or 'negative' - the labels are used both ways in print and an examiner cannot tell which you mean
- Staged approach: Stage 1 first, reassess, Stage 2 if needed
- Never do everything at once - high complication rate
Complications
- Overcorrection to valgus: 5-10% incidence
- Recurrence: 10-20% if underlying cause not addressed
- Nonunion: 5-10% after calcaneal osteotomy
- Growth disturbance: Rare, avoid osteotomy through growth plate
Evidence Base
A Simple Test for Hindfoot Flexibility in the Cavovarus Foot (Coleman Block Test)
- Original description of the lateral-block (Coleman) test for the cavovarus foot
- Placing the heel and lateral border on a block while the first ray hangs free unloads the plantar-flexed first ray
- Hindfoot correction on the block indicates a forefoot-driven, flexible varus
- Persistent hindfoot varus on the block indicates a fixed (structural) hindfoot deformity
Cavus Foot Deformity in Children
- Authoritative AAOS review of paediatric cavus foot evaluation and treatment
- Cavovarus is the commonest pattern; CMT is the most frequent progressive cause, with cerebral palsy and poliomyelitis among non-progressive causes
- Deformity begins flexible and becomes a fixed bony deformity if untreated
- Triple arthrodesis has poor long-term results in progressive deformity with sensory impairment
Is a Plantarflexed First Ray the Primary Deformity in Children with CMT Cavovarus Feet? A Pedobarographic Analysis
- 118 feet from 60 children with CMT analysed with dynamic pedobarography
- First-ray contact preceded fifth-ray contact in only 39.7% of varus feet versus 34.0% of non-varus feet (P=0.526)
- About 60% of varus feet landed in varus before first-ray contact, suggesting the foot is pre-positioned in varus
- Challenges the assumption that a plantar-flexed first ray is the sole primary driver in all CMT feet
Is Non-operative Management of Childhood Neurologic Cavovarus Foot Effective?
- 23 children (35 feet) with neurologic cavovarus treated with an untwisting nocturnal splint, with an untwisting walking cast in some
- Good or very good clinical results in 23 of 35 feet (65%) at mean 4.5-year follow-up
- Of feet followed to skeletal maturity, about half (10 of 21) achieved good or very good results without surgery; no triple arthrodeses were required
- Young age at initiation and poor splint compliance predicted worse outcomes
Talocalcaneonavicular Realignment for Severe Resistant Neurologic Cavovarus and Equinocavovarus in Children
- Prospective cohort of 26 patients (36 feet); 54% cerebral palsy, 23% CMT; median age 12.1 years
- Significant improvement in talocalcaneal, talus-first metatarsal and talonavicular coverage angles and in functional scores (P<0.01)
- Median follow-up 32.9 months with only 3 minor complications (hypersensitivity, partial recurrence, undercorrection)
- Subtalar (talocalcaneonavicular) realignment is the foundational step in comprehensive multi-segmental reconstruction
Treatment of the Cavus Foot in the Paediatric Patient with Charcot-Marie-Tooth
- Over half of patients with CMT develop foot and ankle problems, of which cavovarus is by far the commonest
- Deformity arises from imbalance between peroneus longus and tibialis anterior, and between tibialis posterior and peroneus brevis
- Early soft-tissue procedures and osteotomies in the flexible foot can restore posture and delay bony salvage
- Triple arthrodesis is a salvage option for severely rigid feet, and deformity may progress despite surgery
Malalignment and Lateral Ankle Instability in the Cavovarus Foot
- Hindfoot and tibial varus malalignment is an underestimated cause of chronic lateral ankle instability and later ankle arthritis
- A high index of suspicion for varus malalignment is required when assessing recurrent ankle instability
- Management should include a generous indication for accurate hindfoot realignment
- In young, active patients realignment should be combined with formal lateral ligament repair