Wagner Classification | Texas Classification | Infection Control | Amputation Levels
- Wagner classification = depth (0-5); Texas = depth + ischemia + infection
- Probe-to-bone test: positive likelihood ratio 6.4 for osteomyelitis
- IDSA guidelines: antibiotics for infection, NOT colonization
- Transtibial amputation has better healing (80-90%) than transmetatarsal (50-70%)
- Multidisciplinary team approach reduces amputation rate by 50%
- “Texas classification adds ischemia/infection to Wagner depth grading
- “PEDIS system: Perfusion, Extent, Depth, Infection, Sensation
- “Offloading is THE critical treatment - total contact casting is gold standard
- “Major amputation mortality (Aulivola 2004): about 30% at 1 year, about 65% at 5 years
Overview and Epidemiology
Diabetic foot disease is the leading cause of non-traumatic lower limb amputation worldwide. The pooled global prevalence of diabetic foot ulceration is about 6.3%, highest in North America at 13% and lowest in Oceania at 3%, and the lifetime risk of an ulcer in a person with diabetes is estimated at 19-34% (Zhang 2017; Armstrong, NEJM 2017). Five-year mortality after an ulcer rivals that of several common cancers.
Why the ulcer is the target. Neuropathy means trauma without pain awareness, and peripheral arterial disease means impaired healing; together they create the chronic non-healing ulcer. In Pecoraro's dissection of the pathways to amputation, ulceration was a component cause in 84% of cases. The ulcer is the visible, interruptible step on the road to amputation, which is why screening and footwear target it.
The burden is unequal. Indigenous and lower-resource populations carry a disproportionately high amputation burden. Prevention and early intervention are cost-effective everywhere.
Four sibling pages carry the detail behind this overview: diabetic neuropathy for the mechanism and the screening examination, diabetic foot ulcers for wound care and offloading, diabetic foot infections for antibiotic selection and osteomyelitis, and Charcot neuroarthropathy for Eichenholtz staging, Brodsky anatomical patterns and reconstruction.
Pathophysiology and Mechanisms
Three processes combine to produce the chronic non-healing ulcer: neuropathy, ischaemia and infection.
Neuropathy removes the warning. Sensory neuropathy causes loss of protective sensation (LOPS), so injuries go unnoticed; the 10 g monofilament is the diagnostic test. Motor neuropathy wastes the intrinsic muscles, and the imbalanced forces produce claw toes, prominent metatarsal heads and high plantar pressure. Autonomic neuropathy dries the skin (anhidrosis), and the resulting cracks and fissures are entry points for infection. Repetitive microtrauma without pain also destroys bone and joint, which is Charcot neuroarthropathy.
Ischaemia stops the healing. Peripheral arterial disease in diabetes preferentially involves the tibial vessels (anterior tibial, posterior tibial, peroneal) and spares the profunda femoris. Medial calcification (Mönckeberg sclerosis) deposits calcium in the arterial media: it is non-obstructive, but it reduces vessel compliance and makes the ABI falsely elevated. At the microvascular level a thickened capillary basement membrane reduces oxygen diffusion, and diabetic wounds have a reduced VEGF response with poor collateral formation. Ischaemia prevents healing even when infection is controlled.
Infection. Diabetic foot infection is polymicrobial and often involves anaerobes, and biofilm formation prevents healing.
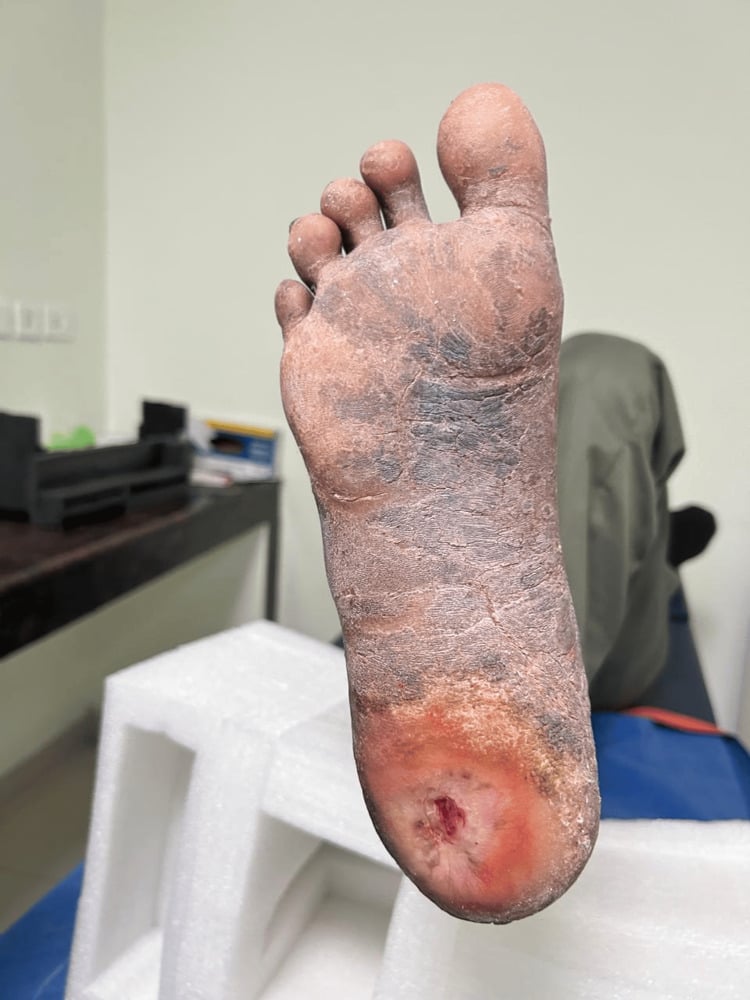
Biomechanics of the plantar ulcer. Normal plantar pressure is 200-300 kPa. With neuropathy and motor imbalance, pressure at the metatarsal heads rises to 700-1000 kPa, seven to ten times higher. Callus forms as a protective response but, being thick and non-compressible, raises local pressure further. Repetitive high pressure plus loss of sensation produces an ulcer at the pressure point, and this is why offloading is critical: a total contact cast reduces plantar pressure by 80-90%, to below the ulceration threshold.
- Mechanism
- Intrinsic muscle atrophy, unopposed long extensors/flexors
- High-Risk Zone
- Plantar metatarsal heads, dorsal PIP joints
- Prevention
- Achilles lengthening, toe straightening, custom orthotics
- Mechanism
- Bone/joint destruction from repetitive trauma without pain
- High-Risk Zone
- Medial midfoot (rocker-bottom deformity)
- Prevention
- Total contact casting during acute phase, custom AFO
- Mechanism
- Bunion formation, first MTP prominence
- High-Risk Zone
- Medial first MTP, plantar first metatarsal head
- Prevention
- Wide toe-box shoes, bunion pads, surgical correction if severe
- Mechanism
- Fixed deformity, concentrated pressure points
- High-Risk Zone
- Plantar heel, metatarsal heads, lateral border
- Prevention
- Custom moulded orthotics redistributing pressure

Classification Systems
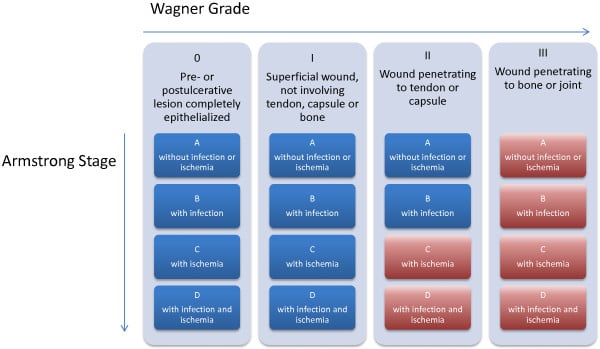
Two systems are expected: Wagner, which grades depth alone, and the University of Texas system, which adds infection and ischaemia to depth and predicts outcome better. PEDIS is the research system, and WIfI and SINBAD are the modern tools for limb-threat stratification and audit. Know both classic systems, and be able to say which one guides treatment.
The original and most widely used system: simple, reproducible, and built on ulcer depth and tissue involvement. It guides treatment urgency and predicts amputation risk.
- Definition
- Intact skin at risk
- Clinical Features
- Callus, deformity, Charcot foot, prior ulcer
- Treatment Approach
- Prevention: custom orthotics, patient education, regular foot checks
- Definition
- Superficial ulcer
- Clinical Features
- Partial or full thickness skin loss, no deeper structures visible
- Treatment Approach
- Offloading (total contact cast), sharp debridement, moist dressing
- Definition
- Deep ulcer to bone/tendon
- Clinical Features
- Ulcer extends to ligament, tendon, joint capsule, or bone
- Treatment Approach
- Surgical debridement, probe-to-bone test, consider antibiotics
- Definition
- Deep with abscess/osteomyelitis
- Clinical Features
- Deep-tissue abscess, osteomyelitis, or septic arthritis
- Treatment Approach
- Urgent surgical debridement, IV antibiotics, prolonged therapy
- Definition
- Localised gangrene
- Clinical Features
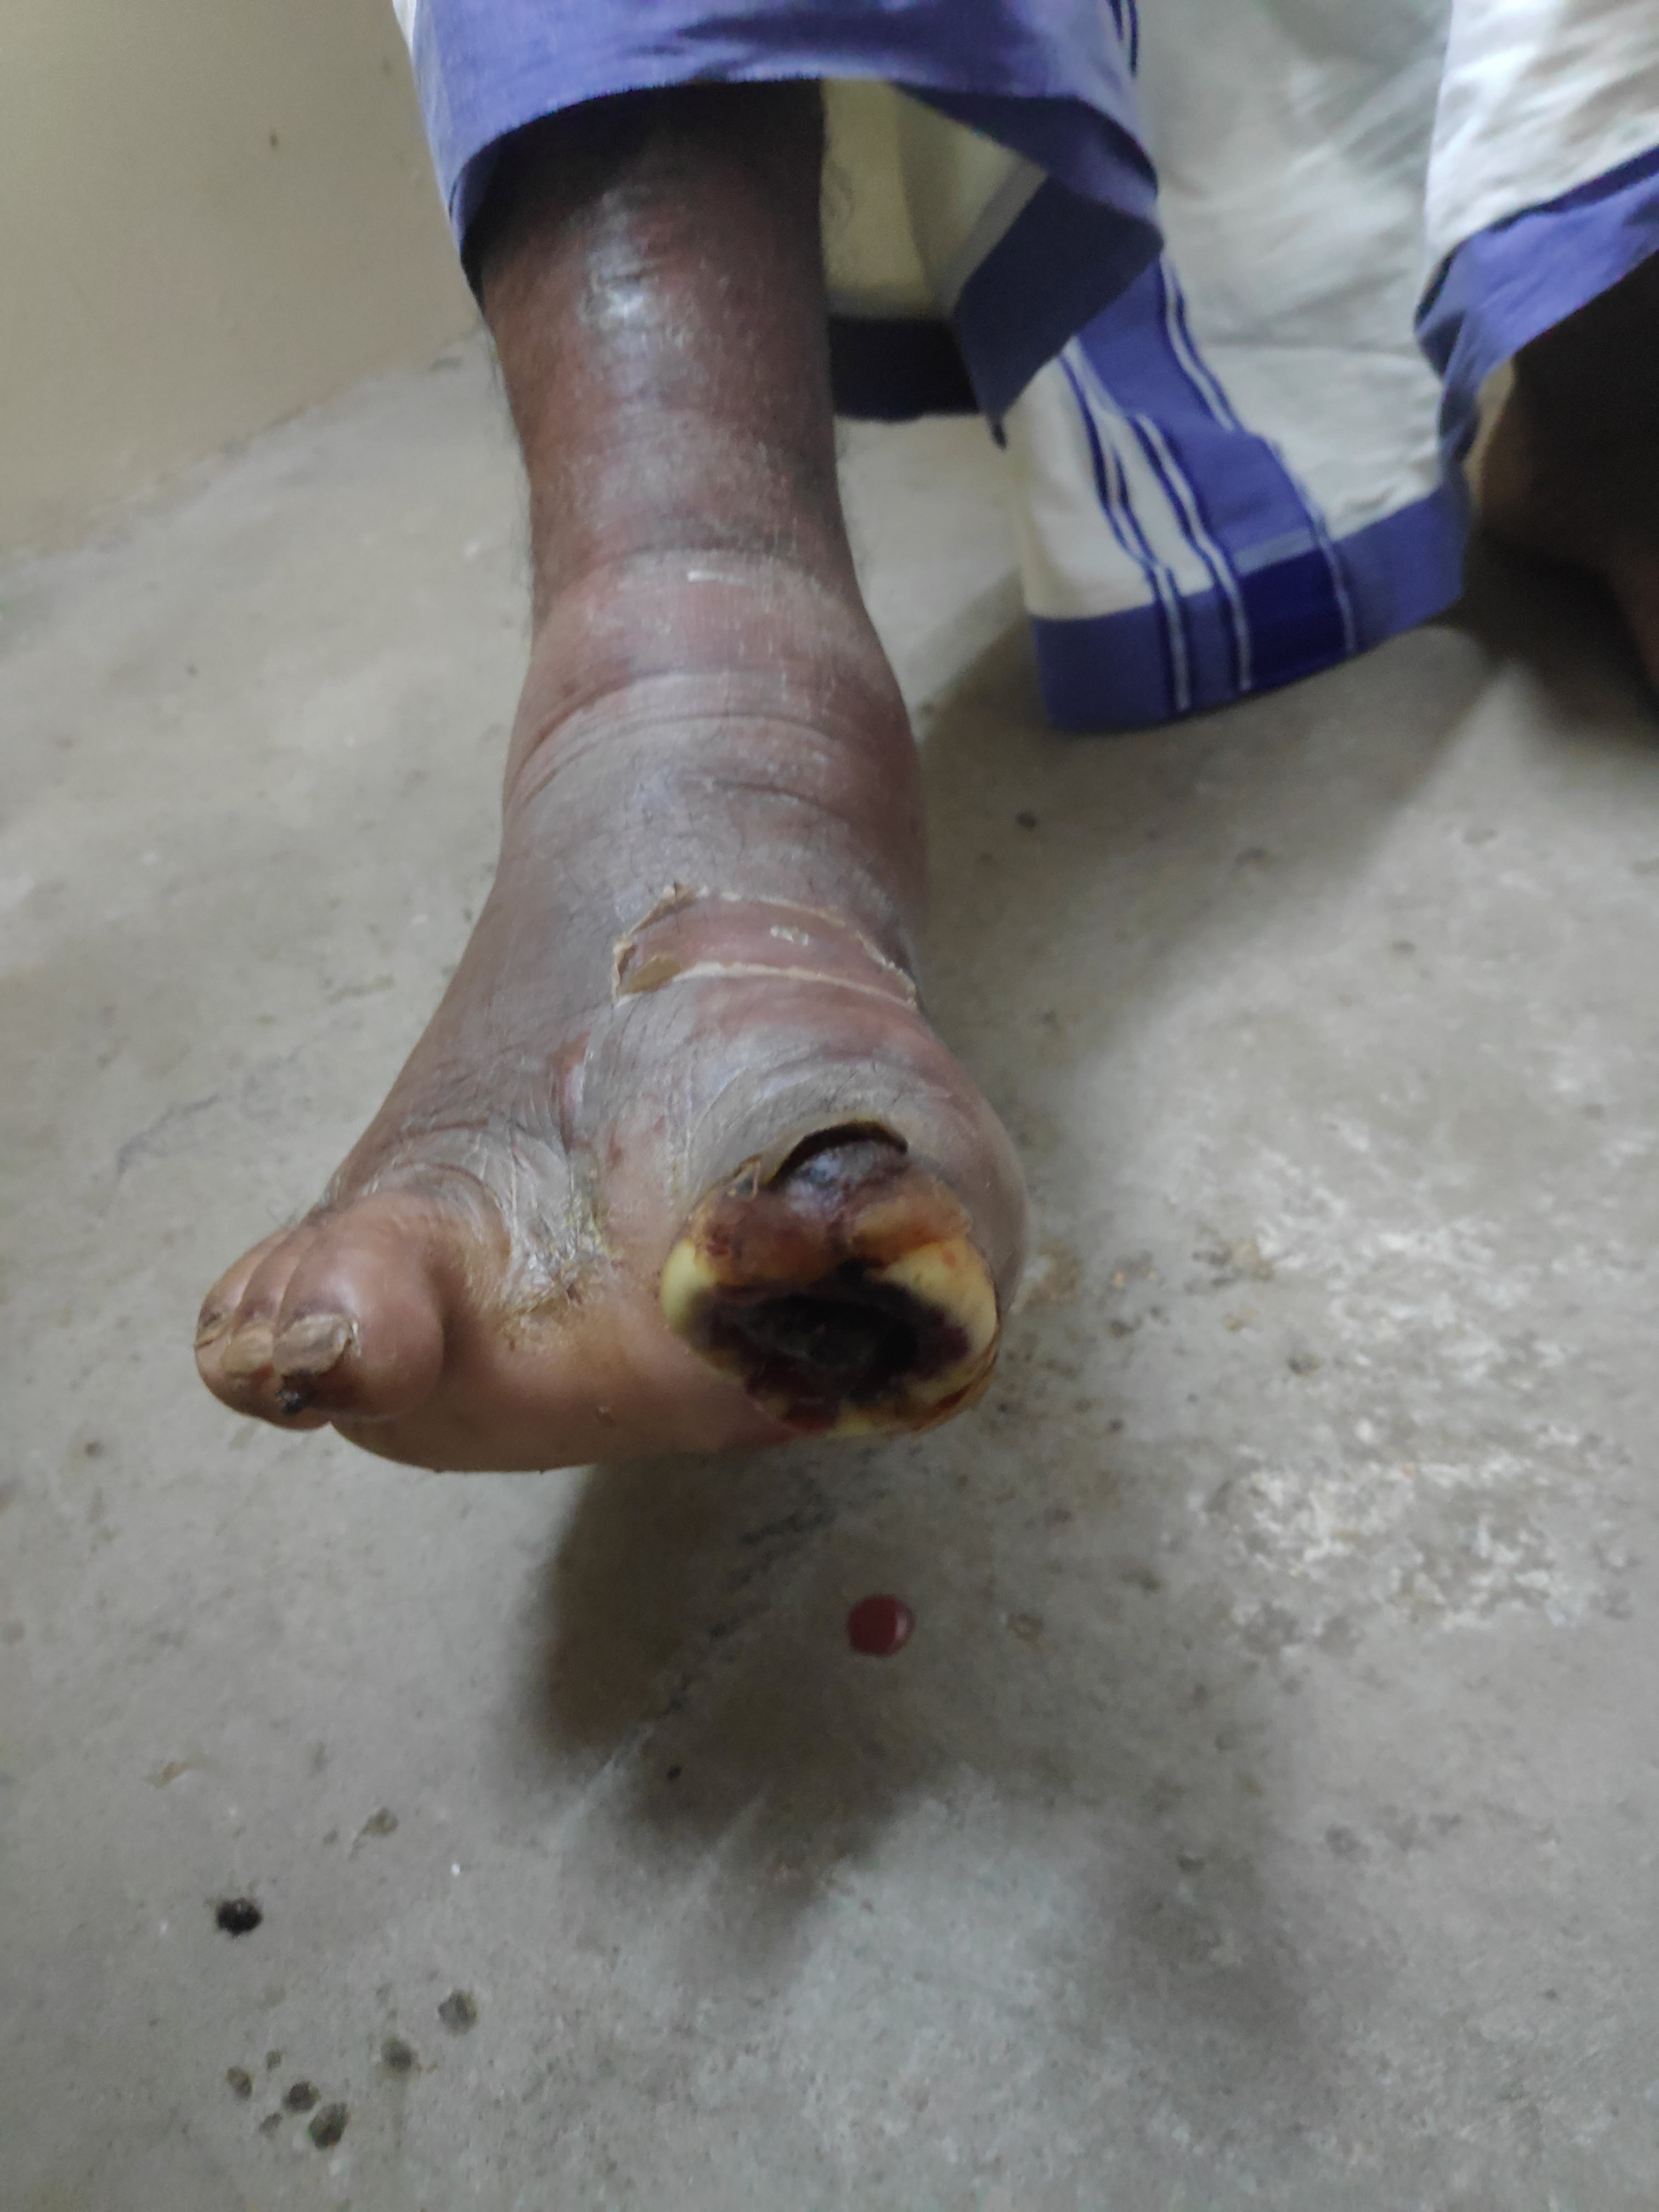
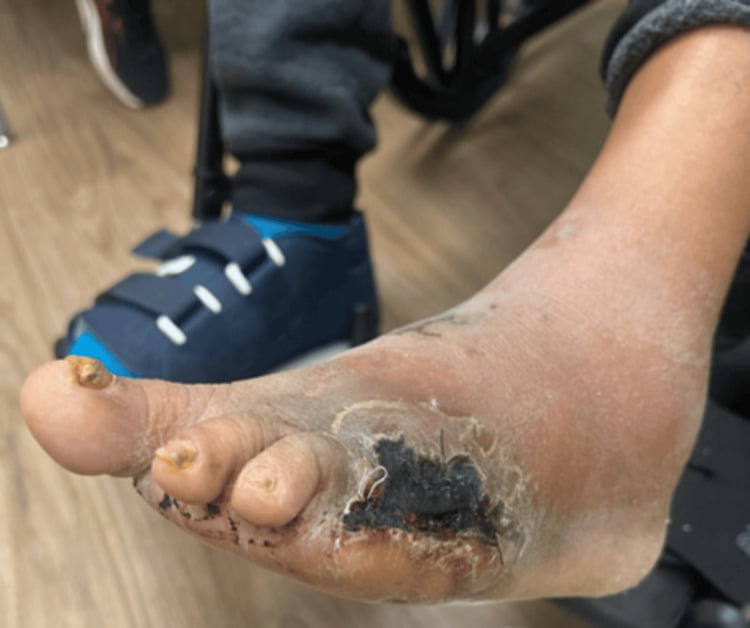
- Necrosis of forefoot (toes, metatarsals), demarcated
- Treatment Approach
- Partial foot amputation (toe, ray, transmetatarsal)
- Definition
- Extensive gangrene
- Clinical Features
- Necrosis involving entire foot, not salvageable
- Treatment Approach
- Major amputation (transtibial, transfemoral)
What Wagner cannot tell you. It does not account for ischaemia or infection severity. A grade 2 ulcer can be clean, or it can have severe necrotising fasciitis, and perfusion status, critical limb ischaemia against adequate flow, dramatically affects healing. That gap is what the Texas and PEDIS systems were developed to fill.
WIfI and SINBAD. Wagner and Texas remain the classic exam systems, but two newer systems are now the international tools for limb-threat stratification and audit.
WIfI (Wound, Ischaemia, foot Infection) is the Society for Vascular Surgery threatened-limb classification:
- Each of the three components is graded 0-3 (0 none, 3 severe): W = wound/ulcer size and depth (and gangrene), I = ischaemia (by ABI, ankle or toe pressure, or TcPO2), and fI = foot infection (by the IDSA criteria).
- The combination places the limb in one of four clinical stages (1-4) that estimate the 1-year amputation risk and the likely benefit of revascularisation - higher stages mean greater amputation risk and greater revascularisation benefit.
SINBAD (Site, Ischaemia, Neuropathy, Bacterial infection, Area, Depth) is an IWGDF-endorsed audit and communication score:
- Each of the six items scores 0 or 1 for a total of 0-6; a higher score predicts poorer healing and higher amputation risk.
- It is deliberately simple and needs no special equipment, which suits it to inter-centre audit and resource-limited settings.
Quote Wagner and Texas for the classic answer. WIfI is the one to cite when the question is how badly the limb is threatened and whether revascularisation will help; SINBAD is the one for audit and international comparison.
Clinical Assessment
History. Diabetes control (HbA1c, duration, complications) and the ulcer's timeline: when it was first noticed, how it has progressed, and any prior ulcers. Ask about pain, numbness and tingling, because a neuropathic ulcer is painless and an ischaemic one is painful; about walking ability and the distance before claudication; and about fever, rigors or confusion, the red flags of systemic infection. Living situation, mobility and the capacity to comply decide what treatment is realistic.
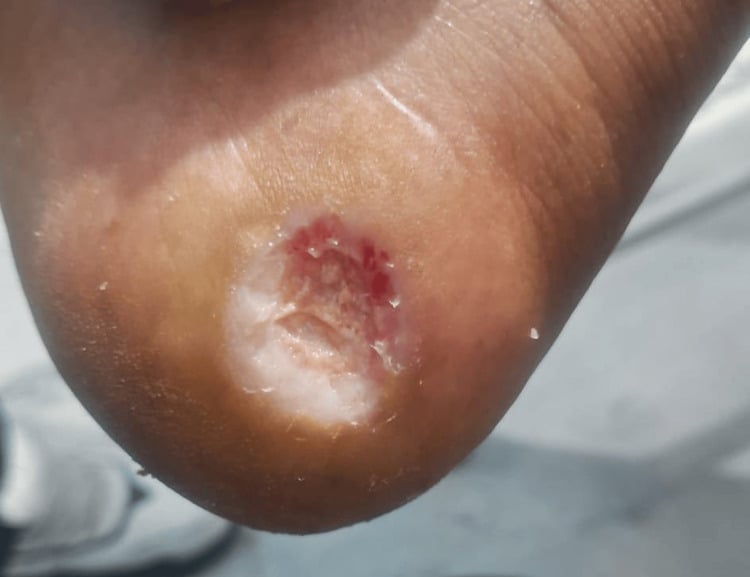
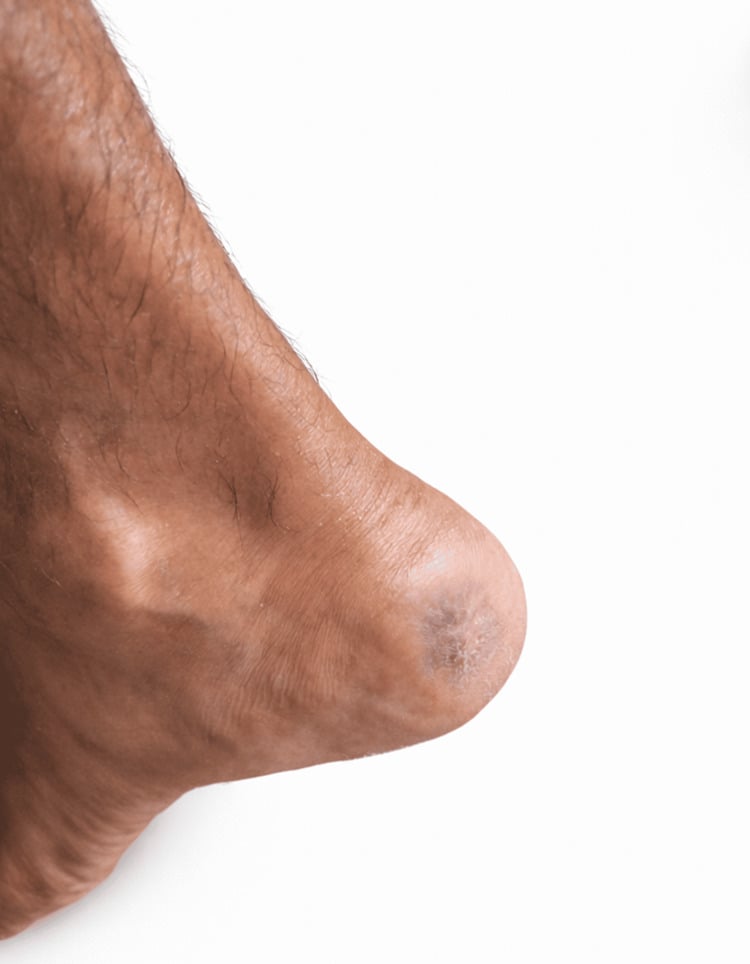
Examination. Inspect the ulcer: location (pressure points), size, depth, base (granulation, slough or necrosis) and edge (undermined, callused). Assess perfusion by the dorsalis pedis and posterior tibial pulses, capillary refill, temperature, ABI and toe pressure; sensation by the 10 g monofilament, vibration with a tuning fork and proprioception; and infection by the extent of erythema (measure and mark it), warmth, purulence, lymphangitis and crepitus. Always examine the contralateral foot for risk assessment.
Probe-to-bone. A sterile probe is passed into the ulcer after debridement; bone feels hard and gritty. Grayson et al (JAMA 1995) found that palpable bone on probing had a sensitivity of 66%, specificity of 85% and positive predictive value of 89% for osteomyelitis in a high-prevalence inpatient cohort, a positive likelihood ratio of roughly 4-5; later outpatient studies report a positive likelihood ratio of about 6, the 6.4 quoted in the summary. Bone felt on probing raises the probability of osteomyelitis substantially, but a negative test does not exclude it, and MRI is the gold standard if clinical suspicion remains high. The test is operator-dependent and requires adequate debridement first.
- Neuropathic
- Painless (loss of protective sensation)
- Ischaemic
- Painful, worse with elevation, relieved by dependency
- Neuropathic
- Plantar pressure points (metatarsal heads, heel)
- Ischaemic
- Distal tips of toes, lateral malleolus, heel
- Neuropathic
- Deep, punched out, surrounded by callus
- Ischaemic
- Shallow, irregular, pale base, no callus
- Neuropathic
- Warm, dry (autonomic neuropathy), good pulses
- Ischaemic
- Cool, hairless, atrophic, absent pulses
- Neuropathic
- Good if offloaded and infection controlled
- Ischaemic
- Poor without revascularisation
- How it mimics
- Warm, swollen, erythematous foot - looks like infection or cellulitis
- Key discriminator
- Often no ulcer/portal of entry; erythema settles on elevation; bony deformity
- Confirmatory test
- X-ray (fragmentation/dislocation), MRI bone oedema, temperature difference greater than 2°C
- How it mimics
- Deep ulcer probing to bone without systemic signs
- Key discriminator
- Probe-to-bone positive, chronicity, sausage toe, raised ESR
- Confirmatory test
- MRI (90% sensitive) and bone biopsy with culture/histology
- How it mimics
- Spreading erythema and warmth
- Key discriminator
- Diffuse, no underlying bone involvement, responds to antibiotics
- Confirmatory test
- Clinical; tissue culture; imaging to exclude deep collection
- How it mimics
- Hot, red, painful first MTP joint
- Key discriminator
- Severe pain (preserved sensation), rapid onset, prior attacks
- Confirmatory test
- Serum urate, joint aspirate for negatively birefringent crystals
- How it mimics
- Unilateral swelling, warmth, erythema
- Key discriminator
- Calf involvement, no ulcer, risk factors
- Confirmatory test
- Duplex ultrasound, D-dimer
- How it mimics
- Non-healing ulcer in a diabetic
- Key discriminator
- Location and surrounding skin (tips/lateral vs gaiter vs heel), pulses, oedema
- Confirmatory test
- ABI/TBI, toe pressure, venous duplex
Investigations
At the bedside. The 10 g Semmes-Weinstein monofilament is tested at 9 sites, and inability to feel it at 4 or more is loss of protective sensation. Probe-to-bone is done after debridement, as described above. Capillary glucose shows current control and guides insulin therapy. These three simple tests guide the immediate treatment decisions.
Vascular studies, within 24 hours. Whether the wound can heal at all depends on perfusion, so this assessment is essential:
- Ankle-brachial index (ABI): 0.9-1.3 is normal; less than 0.9 suggests PAD; greater than 1.3 suggests calcified vessels, common in diabetes, so use toe pressure instead
- Toe-brachial index: more reliable in diabetes; less than 0.6 suggests critical ischaemia
- Toe pressure: less than 30 mmHg is critical ischaemia and revascularisation is needed
- TcPO2 (transcutaneous oxygen): less than 30 mmHg suggests poor healing potential
- Duplex ultrasound: if the non-invasive studies are abnormal, to map the arterial disease for revascularisation planning
Imaging, within 48 hours. Plain radiographs (AP, lateral, oblique) are the first-line screen: look for gas in the soft tissues (necrotising infection), bone destruction (osteomyelitis) and Charcot change (fragmentation, dislocation). MRI is the gold standard for osteomyelitis, with sensitivity 90% and specificity 80%: infected marrow is dark on T1, bright on T2 and STIR, and enhances with gadolinium. CT with contrast is the alternative when MRI is contraindicated, less sensitive for osteomyelitis but good for surgical planning, and a labelled white-cell scan, in which the cells accumulate in infection, is for the case where MRI and CT are inconclusive.
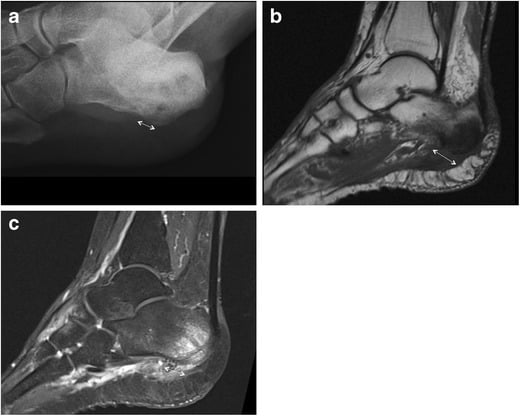
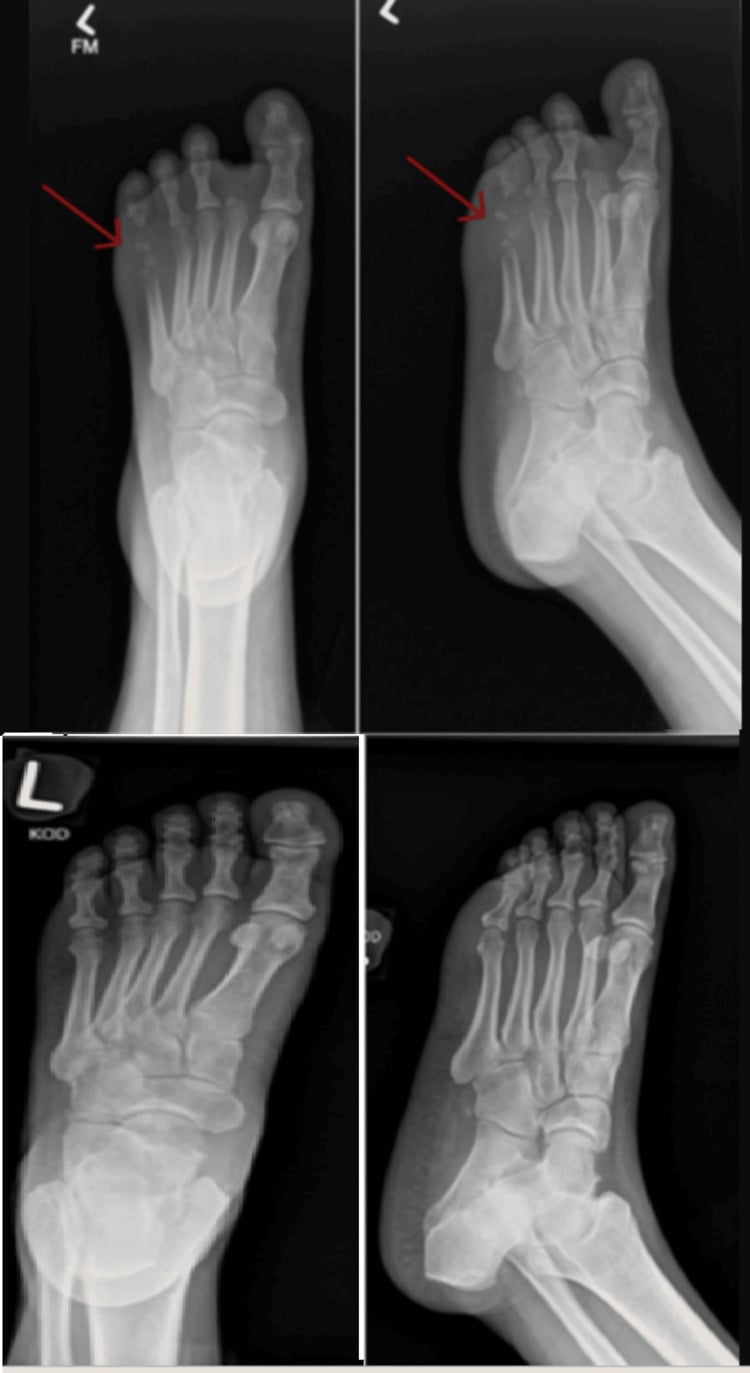
Laboratory, within 24 hours. HbA1c reflects control over three months, and the target for healing is below 7%. A full blood count shows the leukocytosis of systemic infection and the anaemia that is common in chronic disease. CRP and ESR are raised in infection, CRP the more specific and ESR the more sensitive, and are trended to assess response. Renal function matters because diabetic nephropathy is common and changes antibiotic dosing. Blood cultures are taken if there are systemic signs (fever, rigors, tachycardia, hypotension), and the culture that guides treatment is a deep tissue specimen taken after debridement, because swabs are unreliable.
Diagnosing osteomyelitis. Three clinical findings make the pre-test probability high:
- A positive probe-to-bone test
- ESR greater than 70 mm/h (sensitivity 28%, specificity 92%)
- Bone destruction on the plain radiograph, a late sign that is only 50% sensitive
MRI is the gold standard, but all three clinical features are wanted for a high pre-test probability. Bone biopsy with culture is definitive but rarely needed.
Revascularisation and the Angiosome Concept
The vascular thresholds determine whether a wound can heal; the next question, and the one that decides the operation, is how revascularisation is targeted.
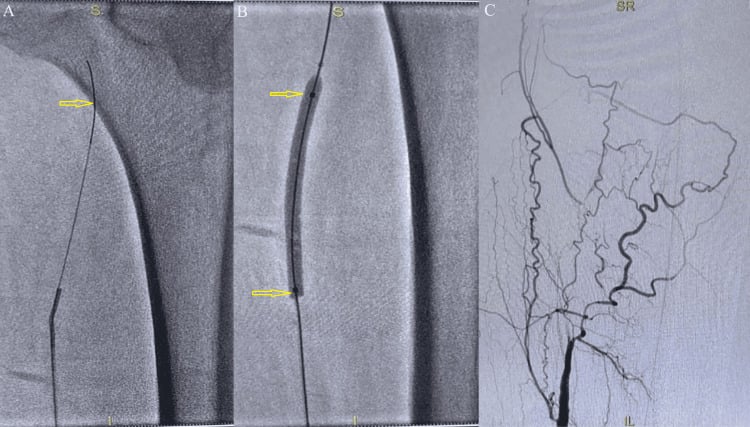
The angiosome concept. The foot and ankle are supplied by six angiosomes, three-dimensional blocks of tissue each fed by a source artery, derived from the three crural arteries: broadly, the posterior tibial (heel via the calcaneal branch, plus the medial and lateral plantar territories), the anterior tibial (dorsum of the foot via the dorsalis pedis), and the peroneal (lateral hindfoot and anterior ankle). Direct, angiosome-targeted revascularisation restores flow in the specific source artery feeding the angiosome that contains the wound; indirect revascularisation restores any line of flow and relies on collaterals. Direct revascularisation is associated with better wound healing and limb salvage in several series, although collateral quality and total flow also matter, so the principle is to re-establish in-line pulsatile flow to the wound's angiosome wherever feasible.
Strategy and timing. Control infection first: drain pus and debride or excise necrotic and infected tissue for source control before definitive revascularisation, then revascularise so that the now-clean wound (or amputation) can heal. An endovascular-first approach is common for focal disease and frailer patients, with distal bypass (for example to a tibial or pedal vessel using vein) reserved for long occlusions or failed endovascular treatment; the choice is individualised to anatomy, conduit availability and patient fitness. Either way, do not commit to a definitive amputation level until perfusion has been optimised.
Management Algorithm
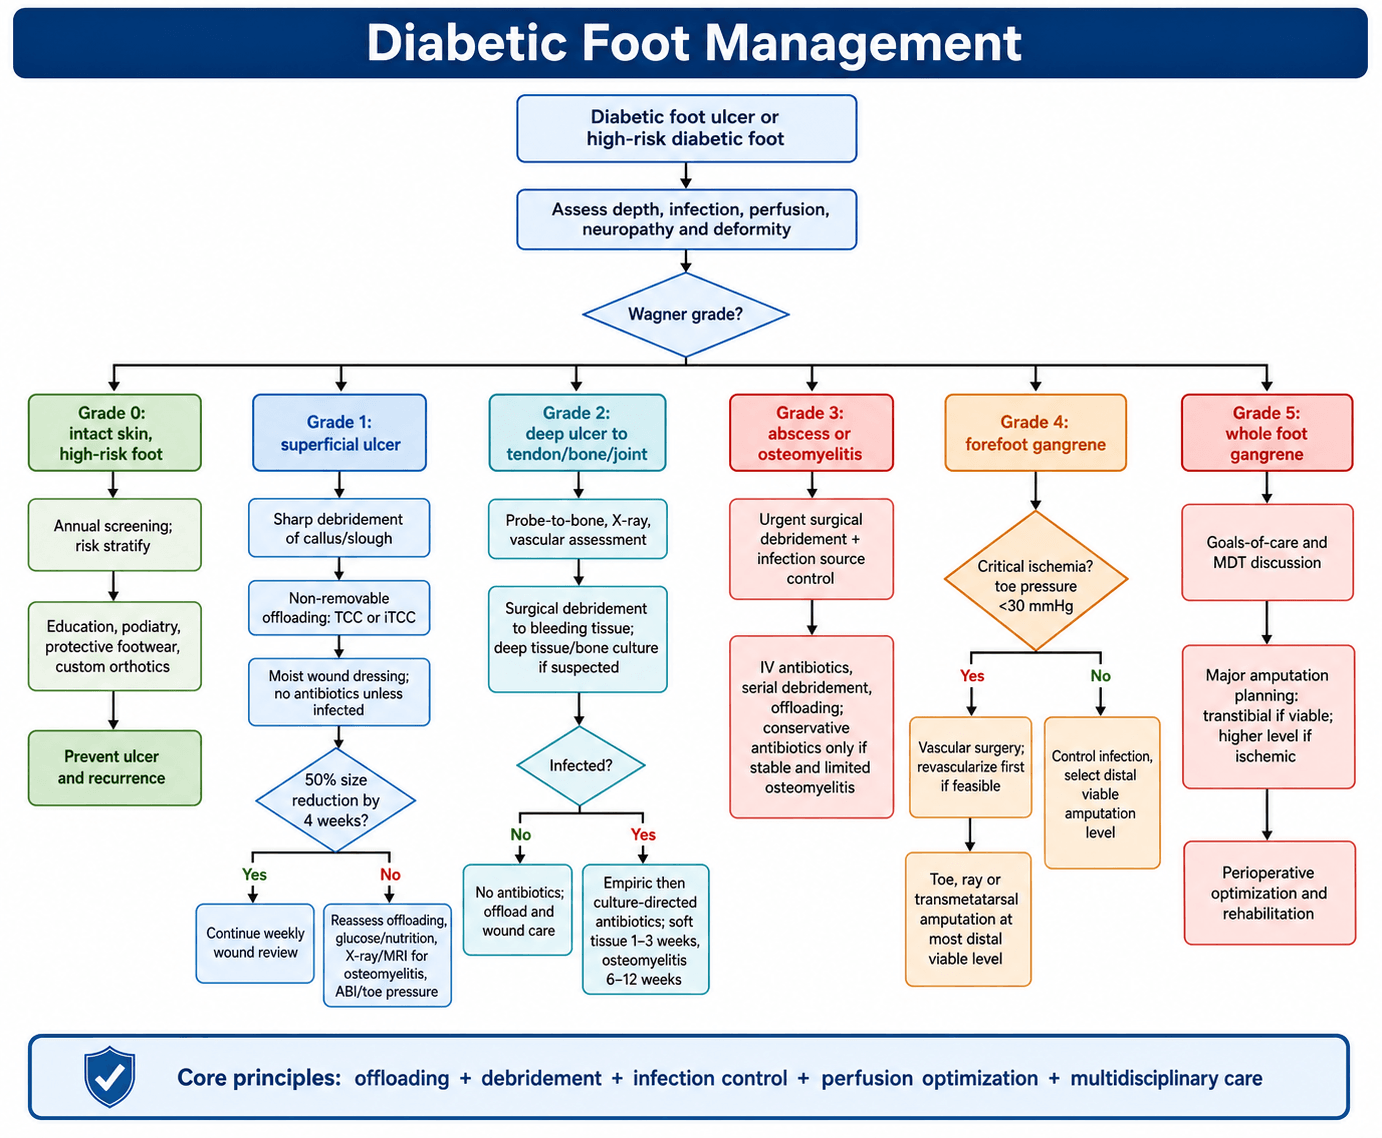
The Wagner grade sets the urgency. Grades 0 and 1 are managed in the clinic with prevention, offloading and wound care; deep ulcers often need surgery, without delay if infection is present; grades 4 and 5 are decisions about amputation level and goals of care. Infection and perfusion, the Texas stage, set the intensity of treatment at every grade.
Grade 0 is the high-risk foot and its treatment is prevention: risk stratification, education, podiatry, orthotics and footwear, set out under Prevention Strategies below. Prevention and early treatment stop progression to the deeper grades.
Grade 1, day 0. Sharp debridement of all callus and slough to a bleeding base; offloading in a total contact cast, the gold standard, or an instant TCC; a moist dressing (hydrocolloid, foam or hydrogel); and no antibiotics unless there are signs of infection. 90% heal with proper offloading alone.
Weekly review, weeks 1-12. Debride again weekly or more often if needed, measure length × width and photograph for documentation, and watch for any new erythema, purulence or warmth. A 50% reduction in size by 4 weeks predicts healing, and most heal in 6-12 weeks with compliant offloading.
Not healing at 4 weeks. A wound that has not shrunk has an underlying problem, so do not simply continue the same treatment. Check compliance with offloading, glucose control and nutrition; rule out osteomyelitis with probe-to-bone, a plain radiograph and MRI if in doubt; complete the vascular assessment (ABI, toe pressure) if not already done; and consider VAC or bioengineered skin if appropriate.
Infection Management
Infection, not colonisation. Every ulcer carries bacteria, so a positive swab means nothing on its own. The IDSA defines infection as purulence, or two or more of warmth, erythema (extending beyond the ulcer), lymphangitis (red streaking proximally), oedema and pain; an ulcer with bacteria on a swab but none of these signs is colonised, not infected, and gets no antibiotics. The culture that matters is a tissue specimen taken after debridement, because swab cultures are unreliable. The IDSA guidelines are the international standard for diabetic foot infection.
- Clinical Features
- No purulence or inflammation
- Microbiology
- Colonisation only (do NOT treat)
- Antibiotic Duration
- No antibiotics
- Clinical Features
- Local infection: erythema less than 2 cm from ulcer edge, superficial
- Microbiology
- Gram-positive (S. aureus, Streptococcus)
- Antibiotic Duration
- 1-2 weeks oral antibiotics
- Clinical Features
- Local infection: erythema greater than 2 cm, OR deep tissue involvement
- Microbiology
- Polymicrobial (add Gram-negative)
- Antibiotic Duration
- 2-3 weeks (IV initially, then oral)
- Clinical Features
- Systemic signs (SIRS) OR metabolic instability
- Microbiology
- Polymicrobial + anaerobes
- Antibiotic Duration
- 4-6 weeks IV antibiotics, may need longer
Empiric regimens (IDSA 2012). Mild, non-limb-threatening infection is treated orally:
- First line: cefalexin 500 mg QID or amoxicillin-clavulanate 875/125 mg BD
- MRSA cover: add TMP-SMX 160/800 mg BD or doxycycline 100 mg BD
- Penicillin allergy: moxifloxacin 400 mg daily (Gram-positive and Gram-negative cover)
- Duration 1-2 weeks, reassessed on clinical response
Moderate and severe infection are treated intravenously, and severe infection requires admission:
- Empiric broad-spectrum: piperacillin-tazobactam 4.5 g TDS or ticarcillin-clavulanate 3.1 g TDS
- MRSA suspected: add vancomycin 15-20 mg/kg BD (trough 15-20)
- Pseudomonas risk: add ciprofloxacin 400 mg BD or once-daily gentamicin
- Anaerobic cover: metronidazole 500 mg TDS if foul smell, crepitus or necrosis
- Duration 2-4 weeks, longer if osteomyelitis
Several international antibiotic guidelines recommend flucloxacillin plus metronidazole for mild-to-moderate infection, covering S. aureus and anaerobes, with piperacillin-tazobactam the common first-line broad-spectrum choice for severe infection. Always de-escalate on culture results and tailor to renal function, and avoid prolonged broad-spectrum therapy unless resistant organisms are culture-proven.
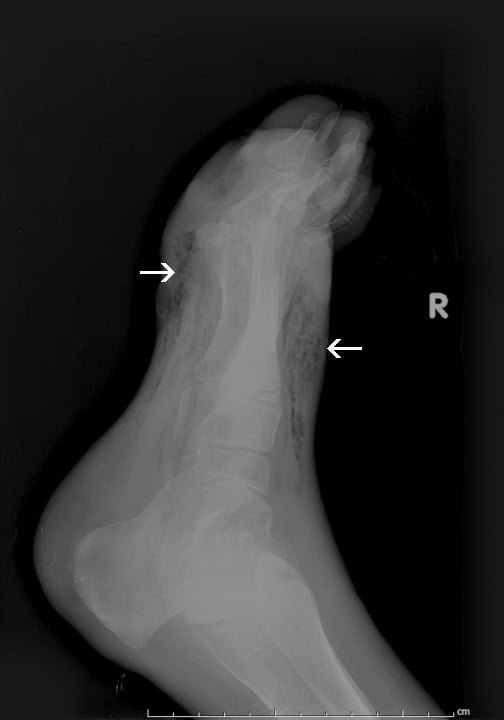
Osteomyelitis. The diagnosis is confirmed by MRI or bone biopsy with culture, and there are three ways to treat it.
Antibiotics alone suit a small area of osteomyelitis with no abscess and no necrotic bone, or a patient who prefers to avoid surgery: pathogen-directed therapy for 6 weeks minimum, often 12, monitored by serial CRP and ESR (expect a 50% reduction by 2 weeks) and clinical healing. Success is 60-80% in the compliant patient and depends on the organism and extent.
Surgical debridement is for necrotic bone, abscess, failed conservative therapy, or the unstable patient who needs source control: resect all infected and necrotic bone until bleeding healthy bone, send the specimen for culture and histology, and give 2-6 weeks of antibiotics afterwards. Success is 85-90% if all infected bone is removed, and it is the definitive treatment for most cases because it removes the infected focus.
Amputation is for extensive osteomyelitis, a non-salvageable foot, life-threatening sepsis or patient preference, at the most distal level with viable tissue (toe, ray, transmetatarsal, Syme or transtibial). It gives immediate source control and a short course of 7-14 days afterwards, at the cost of function, so discuss goals of care.
Recurrence. Diabetic foot osteomyelitis recurs in 20-30% even after treatment. Inadequate debridement, resistant organisms, persistent neuropathy and pressure, and poor glucose control are the risk factors, so every patient needs lifelong foot surveillance and pressure offloading even after cure.
Surgical Management and Amputation Levels
The rule is the most distal level with viable tissue. A higher level heals more reliably and functions worse, so the healing rates below are read against what the patient will be able to do afterwards.
- Indications
- Isolated toe gangrene, osteomyelitis confined to phalanx
- Healing Rate
- 90%
- Functional Impact
- Minimal - great toe removal affects push-off slightly
- Indications
- Osteomyelitis involving metatarsal, web space infection
- Healing Rate
- 80-90%
- Functional Impact
- Good if single ray; multiple rays cause transfer lesions
- Indications
- Forefoot gangrene, multiple ray involvement, salvageable hindfoot
- Healing Rate
- 50-70%
- Functional Impact
- Requires orthotics, equinus deformity risk
- Indications
- Extensive forefoot necrosis, Charcot midfoot
- Healing Rate
- 40-60%
- Functional Impact
- Poor function, high revision to BKA rate
Resect adequately. All infected and necrotic tissue until bleeding healthy bone, no exposed bone at the amputation site, a viable soft-tissue flap for coverage, and no tension on closure. Incomplete resection leads to failure.
Confirm perfusion. Toe pressure greater than 30 mmHg predicts healing, as does TcPO2 greater than 30 mmHg at the amputation level, and bleeding bone ends (the paprika sign) confirm it at operation. Ischaemic tissue will not heal, so if perfusion is borderline, revascularise first.
Transmetatarsal amputation. A TMA preserves weight-bearing on the plantar hindfoot but requires adequate perfusion, a toe pressure greater than 40 mmHg. Afterwards the Achilles is relatively stronger than the dorsiflexors and pulls the foot into equinus, so the patient needs a custom ankle-foot orthosis or a rocker-bottom shoe to prevent plantar ulceration at the stump. Failure to offload means a new ulcer, and a new ulcer means revision to a transtibial amputation.
Complications
- Incidence
- 20-30% of deep ulcers (Wagner 2+)
- Risk Factors
- Probe-to-bone positive, chronic ulcer over 2 weeks
- Management
- Surgical debridement (curative) or prolonged antibiotics (Infection Management)
- Incidence
- 0.1-0.9% of diabetics annually
- Risk Factors
- Peripheral neuropathy, trauma (often unrecognised)
- Management
- Acute phase: TCC immobilisation; chronic: custom AFO, possible fusion
- Incidence
- 15-30% (higher in TMA)
- Risk Factors
- Ischaemia, infection, tension on closure, malnutrition
- Management
- Debridement, VAC therapy, revision to higher level if needed
- Incidence
- 10-20%
- Risk Factors
- Diabetes, ischaemia, polymicrobial wound infection
- Management
- Antibiotics, surgical debridement, revise if bone infected
- Incidence
- 50-80% post-amputation
- Risk Factors
- Pre-amputation pain, acute amputation (vs planned), inadequate analgesia
- Management
- Gabapentin, pregabalin, mirror therapy, TENS, psychological support
- Incidence
- 20-30%
- Risk Factors
- Prolonged bed rest, inadequate physiotherapy
- Management
- Prevention: early mobilisation, splinting, stretching
- Incidence
- 30-50% at 3 years
- Risk Factors
- Bilateral neuropathy and PAD, poor glucose control, increased weight-bearing on the contralateral side
- Management
- Aggressive surveillance, bilateral offloading, glycaemic control
- Incidence
- 5-10% of severe infections
- Risk Factors
- Necrotising infection, delayed treatment, immunocompromised
- Management
- ICU admission, source control, broad-spectrum antibiotics, organ support
- Incidence
- 30-50% (depression, anxiety)
- Risk Factors
- Loss of limb, loss of independence, chronic illness burden
- Management
- Screen for depression, psychology referral, peer support groups
Recurrence is the norm, not the exception. Roughly 40% of healed ulcers recur within 1 year and around 65% within 5 years (Armstrong 2017), because the neuropathy, ischaemia and biomechanical abnormality that caused the first one persist, and continued neuropathy, poor offloading and non-compliance drive the next. Custom orthotics reduce recurrence but compliance is challenging, so every healed patient leaves with a prevention plan: lifelong surveillance, custom orthotics and education.
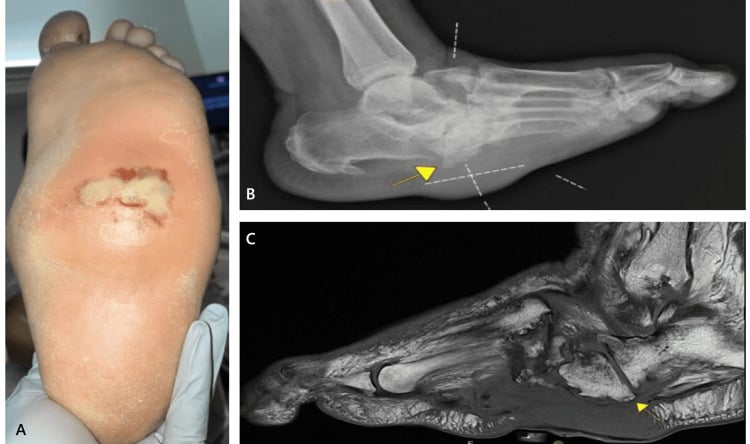
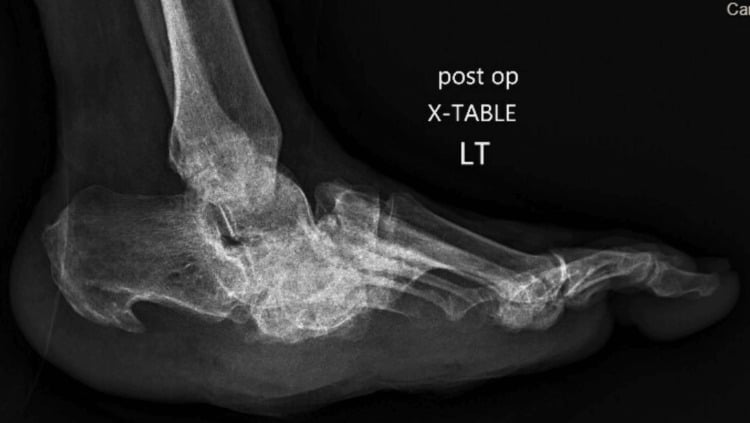
The Charcot foot. A warm, swollen, red foot in a neuropathic diabetic is easily mistaken for infection or DVT; the discriminators are in the differential table above. Early on the radiograph is normal and MRI bone oedema is the only sign, so a hot swollen neuropathic foot with a normal film is Charcot until proven otherwise, not a reason for reassurance. Management is non-weight-bearing in a total contact cast, typically 3-6 months, until the temperature difference falls below 2°C. Walking on an acute Charcot foot causes irreversible deformity, and a rocker-bottom midfoot then ulcerates over the prominence. Chronic deformity needs accommodative footwear or an AFO, and reconstruction (realignment arthrodesis) when bracing fails. The staging that governs the timing, Eichenholtz 0 to III for the disease process and Brodsky 1 to 3 for the anatomical pattern, is set out on the Charcot neuroarthropathy page.
Postoperative Care and Rehabilitation
After debridement or a minor amputation the care is intensive and prolonged, and it requires the patient's commitment.
Days 0-3. The open wound is packed with gauze soaked in saline or antiseptic, and the foot is offloaded in a total contact cast or kept non-weight-bearing. Culture-directed antibiotics continue for a duration set by the severity of infection. Glucose is held at 6-10 mmol/L because hyperglycaemia impairs healing, the diet is high-protein with vitamin C and zinc supplementation, and LMWH is given if the patient is not ambulating. The first phase is infection control and wound preparation.
Days 4-14, granulation. Return to theatre or debride at the bedside if necrotic tissue appears; consider VAC for a deep wound, which promotes granulation and reduces oedema; change dressings daily to every 2-3 days by exudate; and record measurements, photographs and any sign of infection. Mobilisation is non-weight-bearing or protected weight-bearing with a device. Granulation tissue should appear by week 1-2.
Weeks 2-6, epithelialisation. Measure weekly. Small wounds heal by secondary intention; large wounds may need a skin graft or flap. Weight-bearing progresses from non-weight-bearing to protected, with range-of-motion exercises and gait training. Most wounds heal or are ready for closure by 4-6 weeks.
Weeks 6-12, maturation. Once healed, the patient moves into prevention mode: custom insoles, extra-depth shoes with rocker soles, monthly podiatry for the first 3 months and then every 3 months, and daily foot checks with immediate reporting of new problems.
After a major amputation the rehabilitation is long, and outcomes vary widely.
Days 0-7. The drain usually comes out on day 2-3 and dressings are changed daily. Analgesia is multimodal (paracetamol, NSAIDs, opioids as required), with gabapentin or pregabalin if phantom pain develops. Position the limb to avoid hip and knee flexion contractures, with frequent extension, and mobilise early: chair on day 1, bed exercises, and work to maintain contralateral limb strength.
Weeks 1-6. Keep the stump clean and dry and watch for infection or breakdown; shape it with an elastic bandage or shrinker sock. Physiotherapy strengthens the hip extensors and abductors in particular, with range of motion and balance work, and mobility progresses from wheelchair to a walking frame on the contralateral limb. Screen for depression and offer peer support.
Weeks 6-12. As stump volume falls and the scar matures, an interim prosthesis (adjustable socket, pneumatic limb) is used for gait training: weight-bearing, balance, stairs and outdoor walking. The definitive prosthesis is fitted once the stump volume is stable, at 3-6 months, and the functional goals are walking indoors, transfers and activities of daily living.
Months 3-12. Regular prosthetic reviews and socket modifications, contralateral limb protection by surveillance and offloading, cardiac rehabilitation because amputation increases cardiac workload, vocational assessment where return to work is realistic, and ongoing diabetes, psychological and peer support.
Functional outcome. The ambulation rates are in the Major Amputations table: after a transtibial amputation 20-40% remain wheelchair-bound, after a transfemoral amputation 50-70% do, and bilateral amputees have very poor ambulation rates, below 20%. Age, cardiac status, contralateral limb function and cognitive status are the key predictors. Set realistic expectations early.
Outcomes and Prognosis
- Good Prognosis
- Toe pressure greater than 40 mmHg, palpable pulses
- Poor Prognosis
- Toe pressure less than 30 mmHg, critical ischaemia
- Good Prognosis
- Uninfected or mild infection
- Poor Prognosis
- Severe infection with systemic signs, osteomyelitis
- Good Prognosis
- Less than 2 cm diameter
- Poor Prognosis
- Greater than 5 cm diameter (longer healing time)
- Good Prognosis
- Less than 2 weeks
- Poor Prognosis
- Greater than 3 months (chronic wound, biofilm)
- Good Prognosis
- HbA1c less than 7.5%
- Poor Prognosis
- HbA1c greater than 10% (impaired healing)
- Good Prognosis
- Albumin greater than 35 g/L
- Poor Prognosis
- Albumin less than 30 g/L (malnutrition)
- Good Prognosis
- Adheres to offloading and follow-up
- Poor Prognosis
- Non-compliant (removes devices, misses appointments)
Predictors of amputation or death. Five findings mark the patient at highest risk:
- Texas stage D, infected and ischaemic, the worst cell of the grid
- Chronic kidney disease with eGFR less than 30, which doubles mortality risk
- Cardiac disease (prior MI, CCF), the major cause of death after amputation
- Age greater than 75, with higher perioperative mortality and lower rehabilitation potential
- Albumin less than 30 g/L, a marker of malnutrition and frailty
A patient with three or more of these has a very poor prognosis, and the palliative care discussion is essential.
Survival after major amputation. In Aulivola's 2004 series 30-day mortality was 5.7% after transtibial and 16.5% after transfemoral amputation, 8.6% overall; survival was 69.7% at 1 year and 34.7% at 5 years, falling to 30.9% with diabetes and 14.4% with end-stage renal disease; mortality at 3 years was 40%. The deaths are cardiac disease (50%), stroke (15%), renal failure (10%) and sepsis (10%), a survival similar to many stage III cancers. Major amputation is a marker of advanced systemic disease.
Quality of life. Independent living is maintained by 40-60%, and fewer than 20% of those working before the amputation return to work. 30-50% meet criteria for major depression, and psychological support is essential.
Many patients and families do not understand the poor prognosis after major amputation. It is our responsibility to explain: "After a below-knee amputation, about 1 in 3 patients will have died within 1 year, and about 2 in 3 within 5 years. Most deaths are from heart disease or stroke. About 6-8 out of 10 patients will be able to walk with a prosthetic leg, but it requires months of rehabilitation. Some patients may choose to focus on quality of life rather than limb salvage attempts." Document these discussions carefully for medicolegal protection.
Offloading and Wound Care
Offloading is treatment, not an adjunct. For a plantar diabetic foot ulcer it is the single most important intervention, and without it the ulcer does not heal whatever else is done. The total contact cast is the gold standard because it cannot be removed, which guarantees compliance. A non-removable walker is next best. Removable devices (CAM walker, half-shoe) fail because patients take them off at home; non-removable devices work.

- Pressure Reduction
- 80-90%
- Compliance
- 100% (non-removable)
- Indications
- Gold standard for plantar neuropathic ulcers
- Pressure Reduction
- 75-85%
- Compliance
- 100% (non-removable)
- Indications
- Fibreglass wrap over CAM walker - easier application
- Pressure Reduction
- 30-50%
- Compliance
- 30-50% (patients remove it)
- Indications
- Non-plantar ulcers, patient preference (but expect failure)
- Pressure Reduction
- 20-40%
- Compliance
- Variable
- Indications
- Prevention (Grade 0), healed ulcer recurrence prevention
- Pressure Reduction
- 40-60%
- Compliance
- Good (adhesive keeps in place)
- Indications
- Adjunct to other modalities, small ulcers
Sharp debridement. Remove all callus, slough and necrotic tissue down to bleeding healthy tissue, weekly or more often, and send deep tissue for culture if the wound is infected. Debridement converts a chronic wound into an acute one.
Moist wound healing. Dry gauze desiccates the wound bed. Use hydrogel, hydrocolloid, foam or alginate, selected by exudate level and changed per the manufacturer's instructions; a moist environment promotes epithelialisation.
Negative pressure. VAC therapy for deep wounds after debridement promotes granulation tissue and reduces oedema and bacterial load, changed every 48-72 hours. It is an adjunct to debridement, not a replacement for it.
Advanced therapies. Most have limited evidence:
- Hyperbaric oxygen: controversial, limited evidence
- Growth factors (becaplermin): modest benefit
- Bioengineered skin: Apligraf, Dermagraft
- Stem cells: experimental
Multidisciplinary Team Approach
Multidisciplinary diabetic foot clinics reduce major amputation rates by 50% compared with usual care, on evidence from multiple RCTs and cohort studies. The work is coordination between podiatry, vascular surgery, endocrinology, infectious disease, orthopaedics and rehabilitation, with weekly team meetings to review complex cases.
Who does what. The podiatrist assesses and debrides the wound and manages offloading; the vascular surgeon assesses for revascularisation; the endocrinologist optimises glucose control; infectious disease provides antibiotic stewardship; and the orthopaedic surgeon does the amputations and the Charcot reconstruction. Around them, the diabetes educator trains self-management, the dietitian optimises nutrition, the physiotherapist restores mobility and gait, the occupational therapist adapts activities of daily living, and the prosthetist fits the limb after amputation.
The system. Weekly multidisciplinary outpatient rounds, an inpatient service for acute admissions and surgical cases, home nursing for wound care and monitoring, community liaison to secure follow-up compliance, and a database that tracks outcomes for quality improvement. Organised systems deliver coordinated care.
Prevention Strategies
Screen every patient with diabetes annually with the monofilament, the pulses, and a check for deformity, callus and footwear, and stratify by the IWGDF categories:
- Low risk: normal sensation and palpable pulses
- Moderate risk: loss of protective sensation or PAD, not both
- High risk: both, or a prior ulcer or amputation
Educate the high-risk patient. Structured education reduces the incidence of a first ulcer, and it comes down to four habits:
- Daily foot inspection, with a mirror for the plantar surface
- Shoes always, never barefoot, and check inside them daily for foreign objects
- Report any new wound, redness, warmth or drainage at once
- Nails cut straight across, with thick nails and callus left to podiatry rather than self-treated
Preventive podiatry every 4-12 weeks. Callus is debrided every 4-6 weeks, with nail care; custom orthotics redistribute pressure away from the high-risk areas; accommodative footwear means extra-depth shoes, cushioned insoles and rocker soles; and prophylactic Achilles lengthening is considered for persistent forefoot overload. Podiatry reduces ulcer incidence in the high-risk foot.
Control the diabetes. The HbA1c target is below 7% for most patients, relaxed to below 8% in the elderly to avoid hypoglycaemia, alongside multifactorial risk reduction: blood pressure, lipids and smoking cessation. Good control prevents neuropathy progression.
After a healed ulcer. The patient wears the prescribed orthotics and accommodative shoes, inspects daily for redness, blisters and cuts, and reports any new wound, pain, swelling or drainage. Professionally: podiatry every 3 months for callus debridement, nail care and a shoe check; an annual diabetic review with monofilament test, vascular assessment and risk stratification; orthotics replaced every 12-18 months or when worn; endocrinology input for control; and the multidisciplinary clinic coordinating all of it. Prevention works, but it requires sustained effort from the patient and the health system.
- Recurrence Reduction
- 50% reduction in recurrence
- Evidence Level
- Level 1 (RCTs)
- Recurrence Reduction
- 30-50% reduction in first ulcer
- Evidence Level
- Level 1 (systematic review)
- Recurrence Reduction
- 40-60% reduction in amputation
- Evidence Level
- Level 2 (cohort studies)
- Recurrence Reduction
- 75% reduction in forefoot recurrence
- Evidence Level
- Level 2 (case-control)
Guidelines, Registries & Global Practice
- Pooled global diabetic foot ulcer prevalence 6.3%
- Estimated lifetime ulcer risk in diabetes 19-34% (Armstrong NEJM 2017)
- Recurrence ~40% at 1 year, ~65% at 5 years after healing
- North America 13.0%, Africa 7.2%, Asia 5.5%, Europe 5.1%, Oceania 3.0%
- Indigenous and lower-resource populations carry disproportionate amputation burden
Universal screening with region-tailored prevention is the consistent message.
Shared international principles (IWGDF, IDSA, NICE, AAOS/ACFAS):
- Annual risk stratification (loss of protective sensation + PAD)
- Treat infection, not colonisation; post-debridement tissue culture
- Non-removable offloading for plantar neuropathic ulcers
- Integrated multidisciplinary foot care to prevent amputation
Differences are mainly in antibiotic agents and service organisation, not principles.
- Scope / emphasis
- Prevention, classification (SINBAD/WIfI), offloading
- Key recommendation
- Risk-based screening; pressure-relieving therapeutic footwear; non-removable offloading first-line
- Evidence basis
- GRADE systematic reviews (mixed certainty)
- Scope / emphasis
- Diabetic foot infection and osteomyelitis
- Key recommendation
- Infection = 2+ inflammatory signs; severity-based empiric therapy; MRI for osteomyelitis
- Evidence basis
- Consensus guideline, low-moderate quality evidence
- Scope / emphasis
- Whole-pathway diabetic foot care
- Key recommendation
- Refer active diabetic foot problems to a multidisciplinary foot service within 1 working day
- Evidence basis
- Guideline with health-economic modelling
- Scope / emphasis
- Surgical management, amputation, Charcot
- Key recommendation
- Most distal viable amputation level; revascularise marginal perfusion before definitive level
- Evidence basis
- Expert consensus + cohort evidence
Modern international guidance increasingly uses SINBAD (Site, Ischaemia, Neuropathy, Bacterial infection, Area, Depth) for audit and communication, and WIfI (Wound, Ischaemia, foot Infection) for limb-threat and revascularisation-benefit stratification. Wagner and Texas remain the classic exam systems, but be able to mention SINBAD and WIfI as the contemporary registry/vascular tools.
High-resource settings emphasise revascularisation (endovascular or bypass), total contact casting, negative-pressure wound therapy and multidisciplinary clinics. Limited-resource settings see later presentation, higher rates of major amputation, less access to vascular intervention and offloading, and greater reliance on primary amputation for source control. Antibiotic choice also varies with local resistance patterns and formularies (e.g. flucloxacillin plus metronidazole vs amoxicillin-clavulanate vs co-trimoxazole for mild infection) - the principle of severity-based, culture-directed, de-escalated therapy is universal even where the specific agent differs.
Key documentation requirements:
- Annual foot screening: Document monofilament test, pulses, deformity. Failure to screen is negligent.
- High-risk foot referral: Document referral to podiatry or high-risk foot service. Delayed referral for high-risk foot is common litigation trigger.
- Informed consent for amputation: Document discussion of amputation level options, healing rates, functional outcomes, alternative of limb salvage vs definitive amputation. Patients must understand tradeoffs.
- DVT prophylaxis: All diabetic foot patients admitted with infection are high VTE risk. Document prophylaxis or reason for omission.
- Multidisciplinary involvement: Document vascular, infectious disease, endocrinology input for complex cases. Solo decision-making for complex limb salvage is high-risk.
Common litigation scenarios: Delayed amputation leading to sepsis; inadequate informed consent for amputation level; failure to attempt revascularization before amputation; amputation at wrong level (too distal) leading to failure and revision.
MCQ Practice Points
Q: A diabetic foot ulcer extending to bone but without signs of infection or ischemia is which Texas classification?
A: Texas 3A - grade 3 because it penetrates to bone or joint, stage A because there is neither infection nor ischaemia. Note the order and the axes: the number is the depth, the letter is the comorbidity, so "C0" is not a Texas grade at all. This is roughly Wagner 2-3, but with the added information that the wound is clean and perfused - and stage A was the one group in Armstrong's 360-patient validation series in which no amputations occurred. Treatment is sharp debridement and offloading, with imaging to exclude osteomyelitis: remember that a wound probing to bone raised the risk of a midfoot or higher amputation from 2.0% to 18.3% even before infection or ischaemia are counted.
Q: What are the IDSA diagnostic criteria for diabetic foot infection?
A: Purulence OR 2 or more of: warmth, erythema, lymphangitis, edema, pain. Importantly, a positive swab culture WITHOUT these clinical signs is colonization, not infection, and does not require antibiotics. Tissue culture after debridement is more reliable than swab culture.
Q: What is the gold standard offloading method for plantar diabetic foot ulcers?
A: Total contact cast (TCC), which reduces plantar pressure by 80-90%. The key advantage is that it is non-removable, ensuring 100% compliance. Removable devices (CAM walker, half-shoe) have poor compliance as patients remove them at home. Instant TCC (fiberglass wrap over CAM walker) is an easier alternative with similar efficacy.
Q: What is the sensitivity and specificity of MRI for diabetic foot osteomyelitis?
A: Sensitivity 90%, specificity 80%. MRI is the gold standard imaging modality. Look for: T1-weighted dark signal in bone marrow (edema), T2/STIR bright signal (inflammation), and gadolinium enhancement. Plain radiographs have 50% sensitivity (late sign - bone destruction visible after 2-4 weeks). Probe-to-bone test has positive likelihood ratio of 6.4.
Q: What toe pressure predicts healing after transmetatarsal amputation?
A: Toe pressure greater than 40 mmHg predicts reliable healing (some sources use greater than 30 mmHg as minimum threshold, but greater than 40 mmHg is more reliable). TcPO2 greater than 30 mmHg at the amputation level is also predictive. If perfusion is inadequate, revascularization (angioplasty or bypass) should be performed before amputation.
Q: What is the evidence for multidisciplinary diabetic foot care?
A: Multiple studies show 50% reduction in major amputation rate with multidisciplinary foot clinics compared to usual care. Key elements: podiatry, vascular surgery, endocrinology, infectious disease, orthopaedics working together. IWGDF guidelines (2019) give this a Grade A recommendation based on systematic review evidence.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 62-year-old man with type 2 diabetes (duration 15 years) presents with a 3-week history of a non-healing ulcer on the plantar aspect of his right first metatarsal head. He has no pain but noticed drainage on his sock. On examination, there is a 2 cm diameter ulcer with surrounding callus. You probe the ulcer and feel bone. There is no erythema beyond 1 cm from the ulcer edge, no purulent discharge. Pulses are palpable. What is your assessment and management?”
“A 70-year-old woman with diabetes presents with 48 hours of worsening right foot pain, swelling, and fevers (38.5°C). She has a chronic ulcer on her lateral forefoot. On examination, there is extensive erythema to mid-foot, purulent discharge, and crepitus in the forefoot. Her foot is cool with absent DP and PT pulses. Her WCC is 18, CRP 250. Plain radiograph shows gas in soft tissues and bone destruction of the 4th and 5th metatarsals. How would you manage this patient?”
“You have performed extensive debridement for forefoot gangrene in a 68-year-old diabetic man. After removing the 1st, 2nd, and 3rd rays, the residual foot has viable hindfoot tissue but questionable perfusion. Toe pressure is 32 mmHg. The patient asks whether you will be able to save the remaining foot or if he needs a below-knee amputation. How do you counsel him and what determines your decision?”
Key Classifications
- Wagner Grade 0 = intact skin (prevent); 1 = superficial; 2 = deep to bone; 3 = abscess/osteomyelitis; 4 = forefoot gangrene; 5 = whole foot gangrene
- Texas = 4x4 grid, written grade-then-stage: GRADE 0-3 is depth (0 pre-ulcerative, 1 superficial, 2 tendon/capsule, 3 bone/joint) and STAGE A-D is comorbidity (A clean, B infected, C ischaemic, D both). So 1A is clean and superficial, 3D is bone-deep, infected and ischaemic. Infection is a stage, never a depth
- IDSA infection: Mild (less than 2 cm erythema), Moderate (greater than 2 cm or deep), Severe (systemic signs)
- PEDIS = Perfusion + Extent + Depth + Infection + Sensation (research classification)
Diagnostic Tests
- Probe-to-bone: positive LR 6.4 for osteomyelitis (sterile probe feels hard gritty bone)
- MRI: gold standard for osteomyelitis (90% sensitive, 80% specific)
- Monofilament: 10g at 9 sites - unable to feel at 4+ sites = LOPS
- Toe pressure: greater than 30 mmHg minimum, greater than 40 mmHg reliable for healing
Treatment Algorithm
- Uninfected ulcer: offloading (TCC) + sharp debridement + moist dressing (NO antibiotics)
- Mild infection: oral antibiotics 1-2 weeks (cefalexin or amoxicillin-clavulanate)
- Severe infection: IV broad-spectrum (pip-tazo + vancomycin) + urgent surgical debridement
- Osteomyelitis: surgical debridement (curative) OR 6-12 weeks antibiotics (conservative)
Amputation Levels
- Toe 90%, Ray 80-90%, Transmetatarsal 50-70%, Syme 70-80%, Transtibial 80-90%, Transfemoral 90-95% healing
- Higher level = better healing but worse function - aim for most distal viable level
- TMA needs toe pressure greater than 40 mmHg + AFO post-op (prevent equinus ulcer)
- Major amputation mortality (Aulivola 2004): 30-day 5.7% BKA / 16.5% AKA; about 30% dead at 1 year, about 65% at 5 years
Critical Interventions
- Offloading: TCC reduces pressure 80-90%, non-removable ensures compliance
- Revascularization: do AFTER infection control (not before - risks spreading infection)
- Multidisciplinary care: reduces amputation by 50% (podiatry, vascular, endo, ID, ortho)
- Prevention: annual screening, therapeutic footwear, education - 84% of amputations are preceded by an ulcer, which is the interruptible step (Pecoraro)
Evidence Base and Key Trials
Guidelines on the Prevention of Foot Ulcers in Persons with Diabetes (IWGDF 2019 update)
- GRADE-based international guideline; supersedes the 2015 IWGDF prevention guideline
- Screen very-low-risk patients annually for loss of protective sensation and PAD; screen higher-risk patients more frequently
- Prescribe therapeutic footwear with a demonstrated plantar-pressure-relieving effect to prevent recurrence of plantar ulcers
- Provide integrated foot care for high-risk patients to prevent ulcer recurrence
- Suggests against nerve decompression procedures for prevention
Irremovable vs Removable Cast Walkers for Diabetic Foot Wounds (Armstrong 2005 RCT)
- RCT: 50 patients with University of Texas grade 1A neuropathic plantar ulcers
- 12-week healing (intention-to-treat): instant total contact cast (iTCC) 82.6% vs removable cast walker 51.9% (P = 0.02)
- Among healed ulcers, iTCC healed faster: 41.6 vs 58.0 days (P = 0.02)
- Rendering a removable walker irremovable enforces adherence and improves healing
2012 Infectious Diseases Society of America Clinical Practice Guideline for Diabetic Foot Infections
- Infection defined by 2 or more classic signs of inflammation or purulence; all wounds are colonised, so colonisation alone is not treated
- Severity classification: uninfected, mild, moderate, severe - drives admission, imaging and surgery decisions
- Obtain a post-debridement tissue specimen for aerobic and anaerobic culture; swabs are unreliable
- MRI is far more sensitive and specific than plain films for osteomyelitis; bone culture plus histology is the optimal standard
- Multidisciplinary foot teams improve outcomes
Major Lower Extremity Amputation: Outcome of a Modern Series (Aulivola 2004)
- Retrospective series of 959 major amputations in 788 patients (704 BKA, 255 AKA)
- Overall 30-day mortality 8.6%; worse for AKA (16.5%) than BKA (5.7%)
- Overall survival 69.7% at 1 year and 34.7% at 5 years
- Survival worse with diabetes (30.9% at 5 years) and end-stage renal disease (14.4% at 5 years)
- Only 9.4% of BKAs required conversion to AKA
Global Epidemiology of Diabetic Foot Ulceration: Systematic Review and Meta-analysis (Zhang 2017)
- Global pooled diabetic foot ulcer prevalence 6.3% (95% CI 5.4-7.3%)
- Higher in men (4.5%) than women (3.5%), and in type 2 (6.4%) than type 1 (5.5%) diabetes
- Marked regional variation: North America 13.0%, Africa 7.2%, Asia 5.5%, Europe 5.1%, Oceania 3.0%
- Ulcer patients were older, had longer diabetes duration, and more hypertension, retinopathy and smoking
Pathways to Diabetic Limb Amputation: Basis for Prevention (Pecoraro 1990)
- Dissected the causal pathways behind 80 consecutive first amputations and found 23 distinct routes - most amputations are multi-causal, and only acute critical ischaemia acted alone
- Component causes: ulceration 84%, faulty wound healing 81%, initial minor trauma 81%, neuropathy 61%, infection 59%, gangrene 55%, ischaemia 46%
- The sequence minor trauma, then cutaneous ulceration, then failure of wound healing accounted for 72% of amputations
- An identifiable, potentially preventable pivotal event - usually minor trauma breaking the skin - preceded 69 of 80 amputations
Validation of the University of Texas Wound Classification (Armstrong, Lavery & Harkless 1998)
- 360 patients graded for depth and staged for infection and ischaemia, then followed for 6 months to see whether an amputation was performed
- Amputation rose steadily with both increasing grade and increasing stage - the system works on both axes, which is what Wagner cannot do
- Probing to bone raised midfoot-or-higher amputation from 2.0% to 18.3% (OR 11.1, 95% CI 4.0-30.3)
- Infection plus ischaemia (stage D) raised it from 3.5% to 76.5% (OR 89.6, 95% CI 25-316)
- No amputation occurred in any clean, non-ischaemic (stage A) wound during follow-up
Diabetic Foot Ulcers and Their Recurrence (Armstrong, Boulton & Bus 2017)
- Authoritative review: lifetime incidence of foot ulcers in diabetes is estimated at 19-34%
- Recurrence is the norm - roughly 40% within 1 year and around 65% within 5 years of healing
- Five-year mortality after a diabetic foot ulcer is comparable to several common cancers
- Offloading, structured prevention and integrated foot care are the cornerstones of reducing recurrence
Probing to Bone in Infected Pedal Ulcers: A Clinical Sign of Osteomyelitis (Grayson 1995)
- Prospective study of 76 infected pedal ulcers in 75 hospitalised diabetic patients
- Palpable bone on probing had 66% sensitivity and 85% specificity for osteomyelitis
- Positive predictive value 89% in this high-prevalence (66%) inpatient population
- A positive probe-to-bone test makes additional imaging often unnecessary in this setting