Benign Fibro-Osseous Lesion | GNAS Mutation | Ground-Glass Appearance | Shepherd's Crook Deformity
- GNAS MUTATION at the Arg201 codon causes constitutive cAMP activation in bone
- GROUND-GLASS APPEARANCE on radiographs, with endosteal scalloping and loss of corticomedullary differentiation
- SHEPHERD'S CROOK DEFORMITY of the proximal femur, from repetitive microfractures in polyostotic disease
- McCUNE-ALBRIGHT SYNDROME: polyostotic fibrous dysplasia plus café-au-lait macules plus endocrinopathy
- CHINESE LETTERS PATTERN on histology - irregular woven bone trabeculae without osteoblastic rimming
- “Fibrous dysplasia is a developmental disorder, not a true neoplasm
- “Monostotic disease is about 20 times more common than polyostotic in some series
- “Malignant transformation occurs in under 1%, and is higher after radiation therapy
- “Bisphosphonates (pamidronate, zoledronic acid) are given for refractory bone pain; the one RCT showed no proven pain benefit and fracture-risk data are limited
Overview and Genetics
Fibrous dysplasia is a benign fibro-osseous developmental disorder in which normal medullary bone is replaced by fibrous tissue and immature woven bone. The cause is a postzygotic somatic mutation in the GNAS gene, and the bone that results remodels abnormally and is structurally weak.
The mutation. A somatic mutation at the Arg201 codon of GNAS, arising sporadically during early development; it is not inherited. Expressivity varies with the timing of the mutation.
Fibrous dysplasia is a developmental disorder, not a neoplasm, because it arises from a somatic mutation affecting bone development rather than uncontrolled cell proliferation. Lesions typically stabilise at skeletal maturity (monostotic form), supporting developmental rather than neoplastic nature.
Epidemiology. Fibrous dysplasia accounts for 5-7% of benign bone tumours. Monostotic disease has no sex predilection; polyostotic disease, and McCune-Albright syndrome in particular, shows a slight female predominance. Lesions usually stabilise after skeletal maturity.
Distribution. About 70% of cases are monostotic and 30% polyostotic, though the ratio is as high as 20:1 in some series. Craniofacial disease of the skull and facial bones accounts for 25% and is common in the polyostotic form. Age at presentation separates the two forms and is set out in the comparison table under Clinical Forms.
Pathophysiology and Histology
The cascade. Five steps take the mutation to the lesion:
- Mutation at Arg201 prevents the GTPase activity of Gsα
- Constitutive activation: Gsα remains in its active, GTP-bound state
- Excess cAMP: adenylyl cyclase is continuously activated
- Abnormal signalling: osteoblast function is dysregulated
- Fibro-osseous metaplasia: normal marrow is replaced by fibrous tissue
Effect on remodelling. Increased RANKL promotes osteoclast activity and decreased OPG reduces the inhibition of bone resorption, while the abnormal osteoblasts lay down immature woven rather than lamellar bone. The loss of normal lamellar architecture is the structural weakness.
Gross appearance. White-tan fibrous tissue replaces the marrow and is gritty from the bone spicules within it. There is no distinct capsule, the lesion blending into normal bone, and the stroma is vascular and can be haemorrhagic.
Histology: the Chinese letters pattern. Irregular trabeculae of woven bone, C-shaped, S-shaped or alphabet-like, lie in a bland fibrous stroma of spindle cells, and the bone content ranges from minimal to extensive. The trabeculae have no osteoblastic rimming, and that is the key differentiator from ossifying fibroma, which has similar trabeculae with prominent rimming. Low-grade osteosarcoma is separated by cytological atypia and permeative growth, and osteofibrous dysplasia by its cortical location and its osteoblastic rimming.
Clinical Forms and Syndromes
Three forms: monostotic, polyostotic, and polyostotic with the extraskeletal features of McCune-Albright syndrome. Mazabraud syndrome adds intramuscular myxomas to either bony form.
- Monostotic (70%)
- 70% of all cases
- Polyostotic (30%)
- 30% of cases
- Clinical Significance
- Monostotic 20:1 ratio in some series
- Monostotic (70%)
- Teens to 20s (adolescence)
- Polyostotic (30%)
- Childhood (under 10 years)
- Clinical Significance
- Polyostotic presents earlier
- Monostotic (70%)
- Ribs, femur, tibia, skull
- Polyostotic (30%)
- Craniofacial, femur, pelvis
- Clinical Significance
- Craniofacial involvement suggests polyostotic
- Monostotic (70%)
- None (isolated)
- Polyostotic (30%)
- McCune-Albright, Mazabraud
- Clinical Significance
- Polyostotic can have extraskeletal features
- Monostotic (70%)
- Stabilises at skeletal maturity
- Polyostotic (30%)
- May progress through adulthood
- Clinical Significance
- Polyostotic requires lifelong surveillance
- Monostotic (70%)
- Observation or curettage/graft
- Polyostotic (30%)
- Bisphosphonates, prophylactic fixation
- Clinical Significance
- Polyostotic needs medical and surgical
Monostotic disease. A single bone is involved. The common sites, in order:
- Ribs, the most common monostotic site
- Proximal femur
- Tibia
- Craniofacial bones
- Humerus
Between 50 and 70% are asymptomatic, found incidentally. The rest present with dull, aching bone pain that is worse with activity, with a pathological fracture through the weakened bone (sudden pain and deformity), or with swelling where an expansile craniofacial lesion sits. Deformity from progression is rare.
Polyostotic disease. Multiple bones are involved, with a unilateral predominance, especially in McCune-Albright syndrome. Craniofacial involvement is common, the long bones (femur, tibia) are frequently affected, and severe cases involve 20-30 or more bones. Patients present with progressive deformity (the shepherd's crook, limb bowing), multiple recurrent fractures at different sites, limb length discrepancy from the unilateral involvement, a limp or antalgic gait, and cranial nerve symptoms (vision, hearing loss) when the craniofacial skeleton is involved.
McCune-Albright syndrome. The classic triad, every element from the same GNAS mutation acting in a different tissue:
- Polyostotic fibrous dysplasia, with unilateral predominance
- Café-au-lait macules with irregular "coast of Maine" borders
- Endocrinopathy, most commonly precocious puberty
The endocrine manifestations:
- Precocious puberty, the most common, especially in girls, with recurrent ovarian cysts
- Hyperthyroidism from autonomous nodular thyroid disease
- Growth hormone excess / acromegaly, which worsens craniofacial disease and optic compromise
- Cushing syndrome, neonatal, from adrenal hyperactivity
- FGF23-mediated hypophosphataemia: dysplastic bone over-produces FGF23, driving renal phosphate wasting that correlates with skeletal disease burden and worsens osteomalacia and fracture risk
Hypophosphataemic osteomalacia compounds bone weakness and fracture risk, and it is easily missed. Always check serum phosphate in extensive or polyostotic disease and replace phosphate and active vitamin D when it is low: an under-used, evidence-based adjunct that treats a cause of pain and osteomalacia.
The skin. Café-au-lait spots are present at birth or in early infancy and follow Blaschko lines in a unilateral distribution. Their irregular "coast of Maine" border is what separates them from the smooth "coast of California" macules of neurofibromatosis.
McCune-Albright syndrome requires multidisciplinary management involving orthopaedics, endocrinology, and genetics. Screen for endocrinopathies with thyroid function, cortisol, growth hormone, and bone age studies.
CAFEMcCune-Albright Syndrome Triad
Hook:Drink CAFE and think of café-au-lait spots - McCune-Albright syndrome!
Mazabraud syndrome. Fibrous dysplasia, monostotic or polyostotic, with intramuscular myxomas: soft tissue masses in skeletal muscle adjacent to the affected bones, carrying the same GNAS mutation. It is rare, with fewer than 100 reported cases.
Examination
Inspection. Look for visible deformity (a varus femur, tibial bowing), measure true and apparent limb length for discrepancy, search the skin for the café-au-lait macules that would point to McCune-Albright syndrome, and watch the gait for an antalgic or Trendelenburg pattern.
Palpation. Bony expansion over the affected area, and tenderness if the lesion is symptomatic. Warmth is not typical unless there has been a fracture.
Named findings.
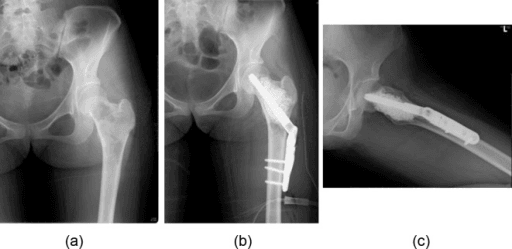
- Shepherd's crook deformity: proximal femoral varus with lateral bowing, produced by repetitive microfractures and abnormal stress remodelling in polyostotic disease, and progressing as a coxa vara
- Leonine facies: craniofacial expansion in severe polyostotic disease
- Limb atrophy: with chronic pain or disuse
Investigations and Imaging
Radiographs. The lesion is a homogeneous, hazy density likened to ground glass, smoky or frosted, with loss of the normal trabecular pattern and well-defined margins; this ground-glass appearance is pathognomonic. The bone around it changes in four ways:
- Endosteal scalloping with cortical thinning, but not cortical breakthrough
- Expansion of the medullary cavity
- Loss of corticomedullary differentiation
- No periosteal reaction unless there is a fracture
By site. In the proximal femur the lesion involves metaphysis and diaphysis, pathological fractures are common, and the bone drifts into varus with lateral bowing, the shepherd's crook. In the skull the diploë expands, the normal contour is lost, and the orbit or sinuses can be obliterated. In the rib it is an expansile lucency with ground-glass matrix.
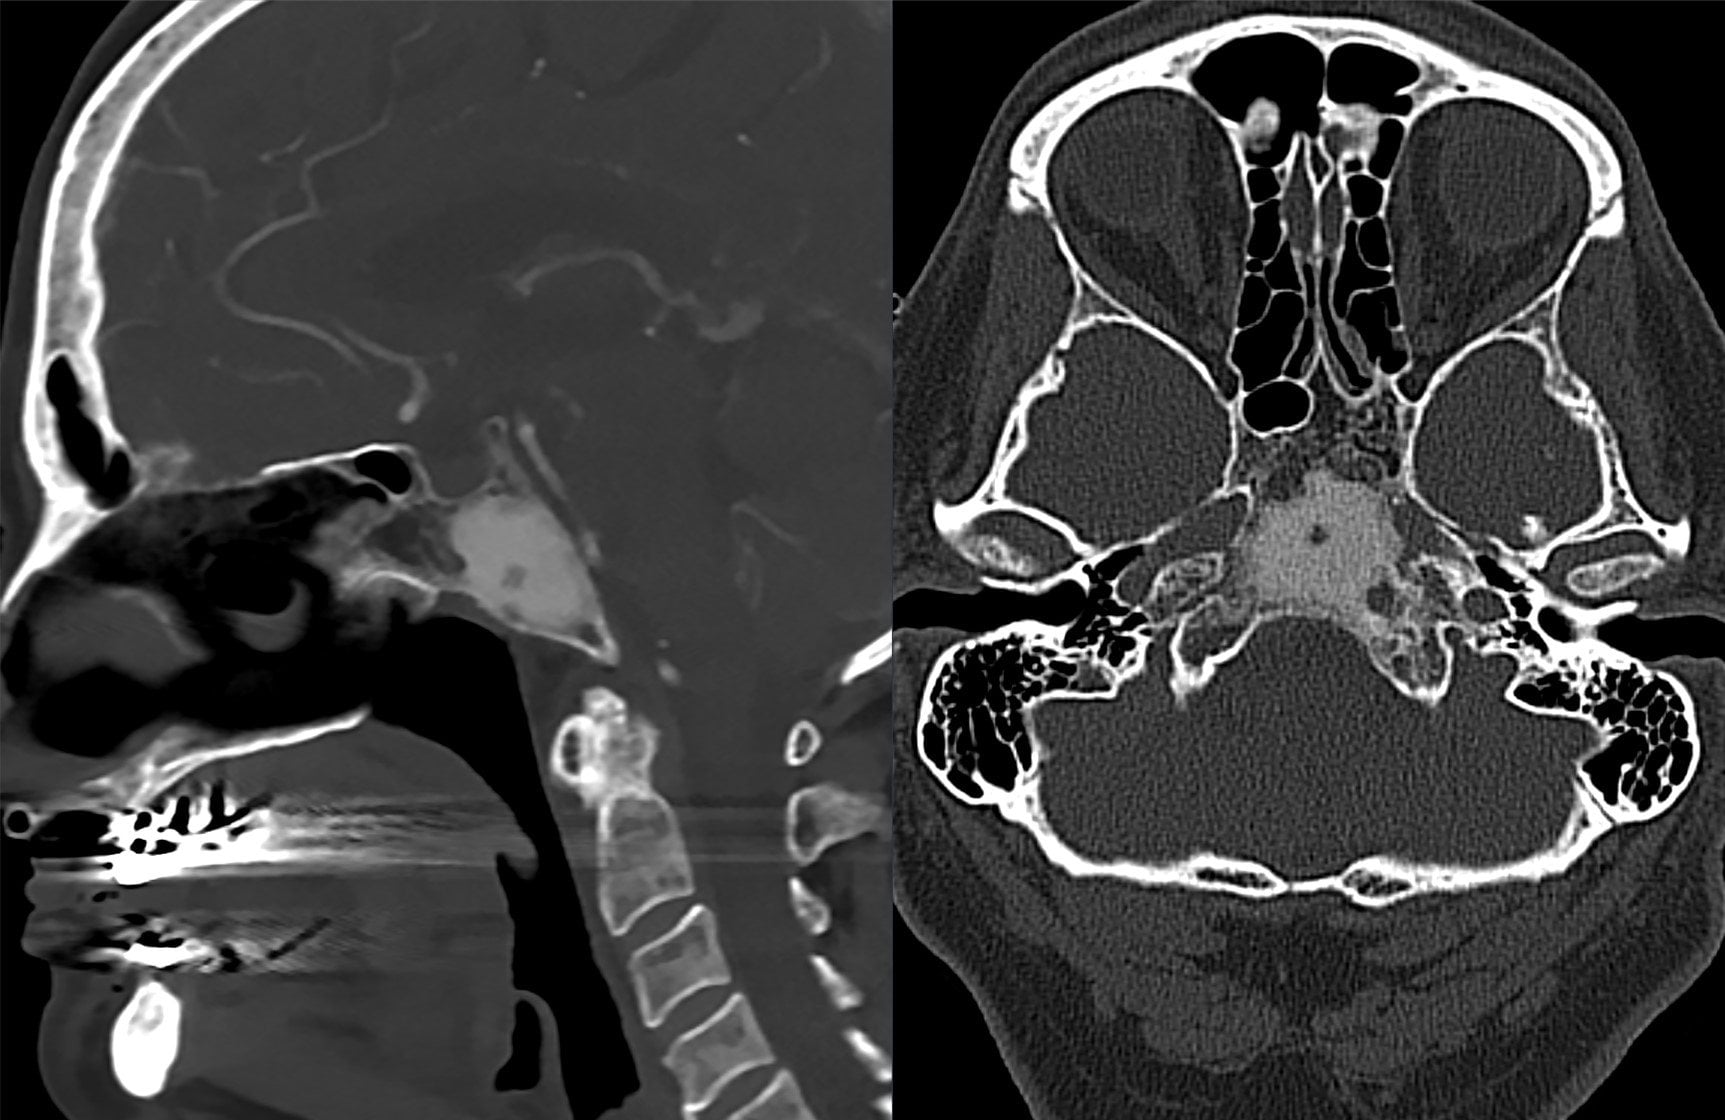
CT. Use it to define the extent of craniofacial involvement, to measure cortical thickness when judging fracture risk, and to plan curettage. The lesion has ground-glass attenuation of 100-150 HU, the endosteal scalloping is clearly seen, and 3D reconstruction helps in assessing deformity.
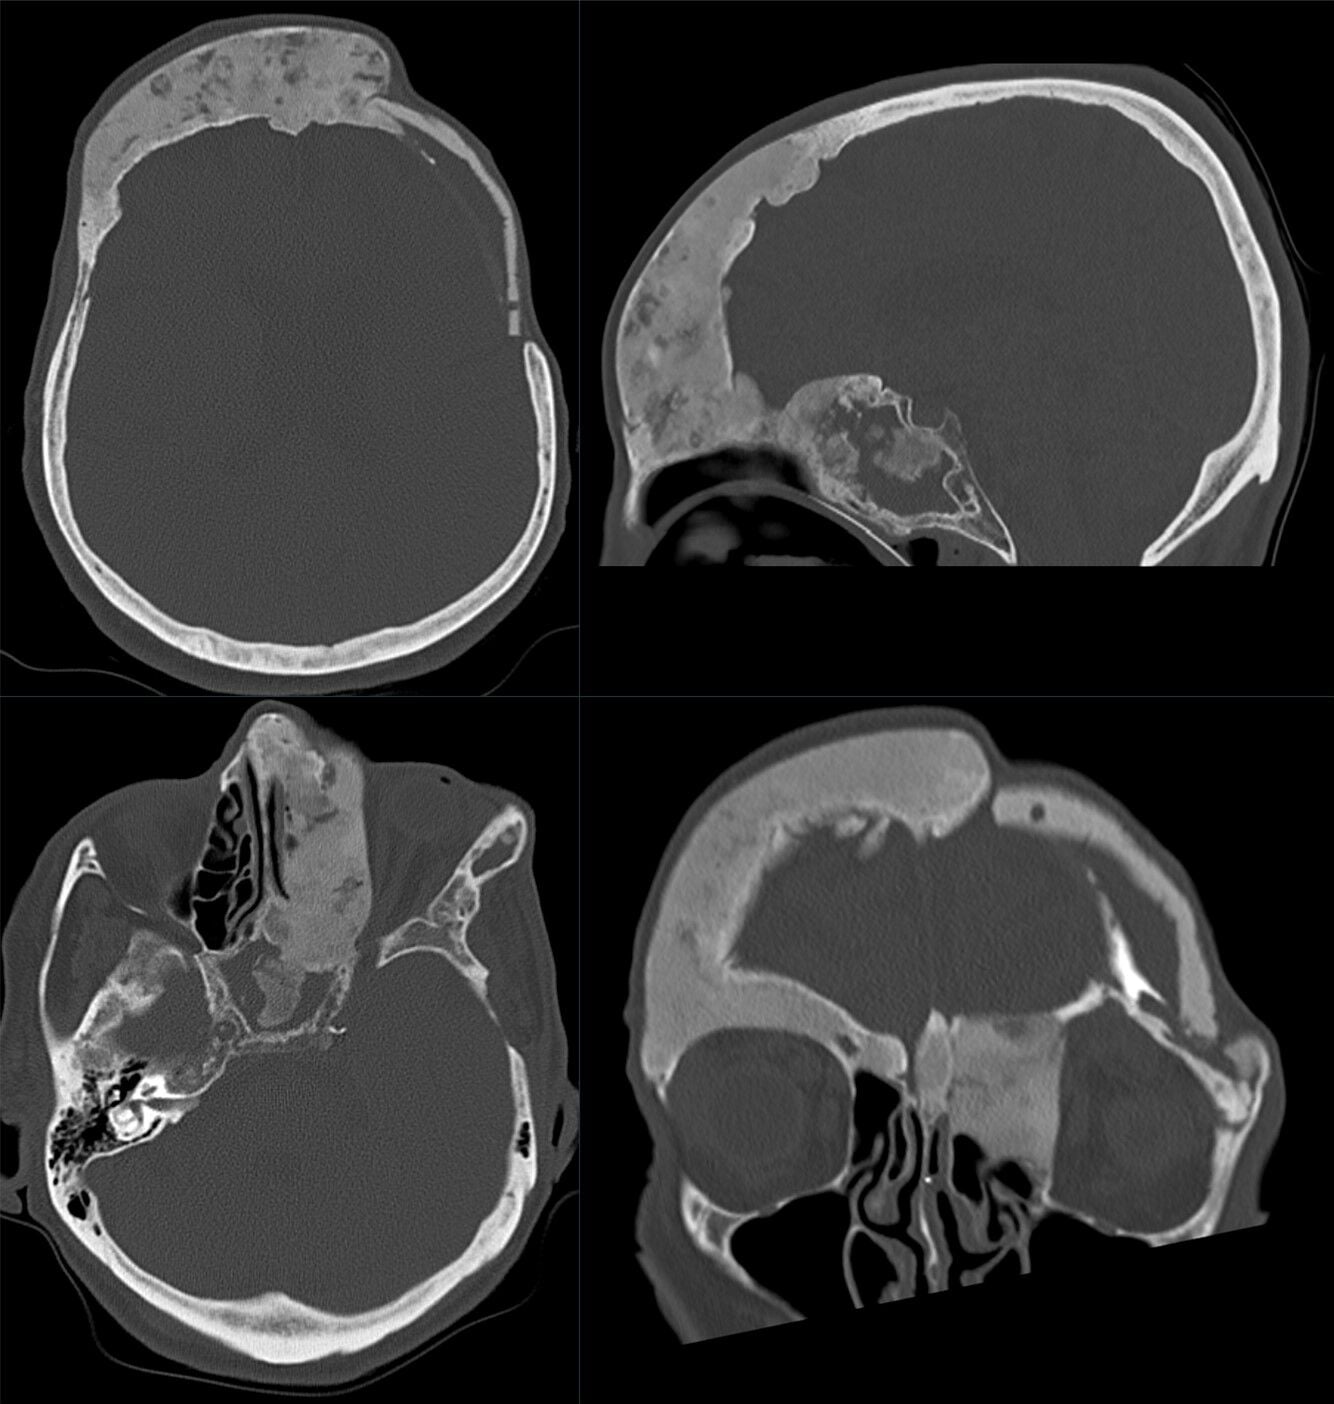
MRI. Requested to distinguish an atypical lesion from malignancy, to assess soft tissue extension in Mazabraud syndrome, and to evaluate spinal canal involvement. Signal characteristics:
- T1: low to intermediate
- T2: variable, low to high depending on fibrous versus cystic content
- STIR: high, oedema-like
- Enhancement: mild to moderate, heterogeneous
Bone scan (Tc-99m). When a single lesion is found, a bone scan screens for polyostotic disease: active lesions show increased uptake, and the scan identifies every site of involvement.
Laboratory tests. Alkaline phosphatase is often elevated, reflecting bone turnover; calcium is usually normal; phosphate may be low in extensive disease from the FGF23-mediated renal phosphate wasting described above, and must be checked actively. If McCune-Albright syndrome is suspected, screen the endocrine axes:
- Thyroid function (TSH, T4)
- Cortisol (24-hour urine free cortisol)
- Growth hormone and IGF-1
- Bone age, if there is precocious puberty
Biopsy. The indications:
- Atypical radiographic features, to rule out malignancy
- Pain without fracture, where sarcomatous transformation is a concern
- A lesion that progresses after skeletal maturity
- First diagnosis in polyostotic disease
A core needle biopsy is usually sufficient, with open biopsy if the sample is inadequate. The specimen goes for histology to look for the Chinese letters pattern.
Differential Diagnosis
- Fibrous Dysplasia
- Any bone, ribs/femur common
- Ossifying Fibroma
- Mandible/maxilla only
- Osteofibrous Dysplasia
- Tibia/fibula cortex
- Fibrous Dysplasia
- Chinese letters, NO rimming
- Ossifying Fibroma
- Chinese letters WITH rimming
- Osteofibrous Dysplasia
- Cortical lesion, osteoblastic rimming
- Fibrous Dysplasia
- Ground-glass, medullary
- Ossifying Fibroma
- Well-defined, mixed density
- Osteofibrous Dysplasia
- Intracortical lucency, sclerotic rim
- Fibrous Dysplasia
- Teens to 20s (monostotic)
- Ossifying Fibroma
- 20-40 years
- Osteofibrous Dysplasia
- Under 10 years (children)
- Fibrous Dysplasia
- Stabilises at maturity
- Ossifying Fibroma
- Slowly progressive
- Osteofibrous Dysplasia
- Can regress spontaneously
Paget disease. An older patient, over 50, with a "blade of grass" advancing lytic front, a "cotton wool" appearance in the later stages, and a markedly elevated alkaline phosphatase.
Aneurysmal bone cyst. Eccentric, with a blown-out appearance on the radiograph and fluid-fluid levels on MRI, and no ground-glass matrix.
Low-grade osteosarcoma. Permeative growth, periosteal reaction (Codman, sunburst), cytological atypia on histology, and an older patient or a history of radiation.
One further craniofacial fibro-osseous lesion is cherubism, which an examiner may use to test that you do not reflexively attribute every fibro-osseous jaw lesion to fibrous dysplasia. It is autosomal dominant, caused by SH3BP2 mutations and so carried with a positive family history, fundamentally different from the sporadic, somatic GNAS mutation of FD: cherubism is inherited, FD is not.
It presents as bilateral, symmetric, painless expansion of the mandible and maxilla in a young child, classically giving full cheeks and the "eyes turned to heaven" (cherubic) appearance, where FD is more often unilateral or asymmetric. The lesions are multilocular and giant-cell-rich rather than the woven-bone Chinese letters of FD, and typically multicystic or lytic on imaging rather than ground-glass. Cherubism characteristically stabilises and regresses after puberty, so management is usually observation or conservative contouring, with surgery reserved for functional or severe cosmetic problems, quite different from the progressive deformity of polyostotic FD.
Management
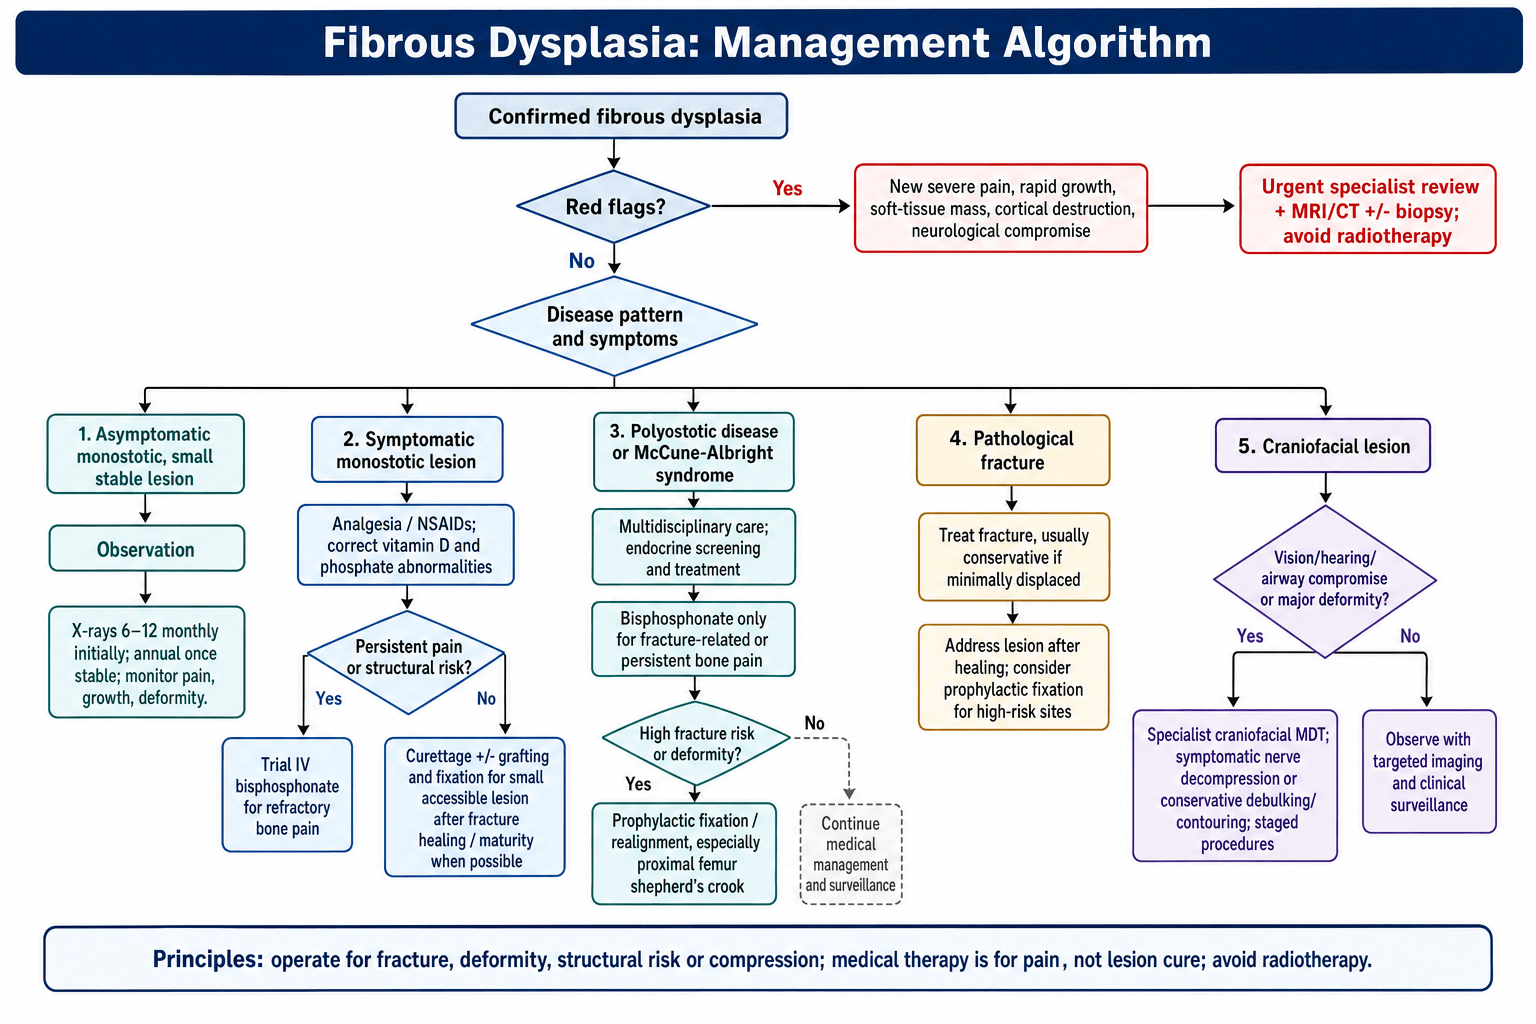
Observation. Asymptomatic monostotic lesions, small lesions without fracture risk, and stable disease after skeletal maturity are watched rather than treated: radiographs every 6-12 months initially, then annually once stable, looking for growth, pain and deformity.
Bisphosphonates. Indicated for symptomatic polyostotic disease, for bone pain not responding to NSAIDs, and to reduce fracture risk at high-risk sites. They inhibit osteoclast activity and reduce bone turnover.
- Pamidronate 30-60 mg IV every 3-6 months
- Zoledronic acid 4-5 mg IV annually
- Duration: several years, reassessed periodically
What they achieve. Reported pain relief in 60-80% of patients and a fall in alkaline phosphatase sit against the one placebo-controlled trial, the alendronate RCT (Boyce 2014), which reduced resorption markers and raised bone density but did not significantly improve pain or function. International consensus therefore reserves them for refractory or fracture-related bone pain, not as disease modification. They may reduce fracture risk, though the data are limited, and they do not reverse deformity. Side effects are flu-like symptoms after infusion, hypocalcaemia (supplement calcium and vitamin D), and rarely osteonecrosis of the jaw, so dental hygiene matters.
Newer agents. Denosumab, a RANKL inhibitor, has produced lesion regression in case reports of aggressive or refractory disease, but it has no controlled evidence and carries a serious rebound hypercalcaemia risk on discontinuation, particularly in children, so it is used only in specialist hands. Tocilizumab (anti-IL-6) is under investigation for FD-related pain.
Surgical indications.
- Pathological fracture: treat the fracture, then address the lesion
- Impending fracture: cortical thinning over 50%, or a lesion over 2.5 cm
- Progressive deformity (shepherd's crook)
- Neurological compromise from craniofacial lesions
- Refractory pain despite medical therapy
Curettage and Bone Grafting
Who. Symptomatic monostotic lesions, small accessible lesions, and lesions treated after a fracture has healed.
Technique.
- Direct exposure of the lesion
- Thorough curettage of the fibrous tissue
- Adjuvants optional: phenol, argon beam, PMMA
- Autograft or allograft cancellous bone
- Internal fixation if stability requires it
Outcomes. Pain relief in 70-90%. Recurrence runs at 10-30% in children and lower in adults, and is higher when the lesion is not fully mature and in polyostotic disease. The other complications are fracture through the graft site and infection in 1-2%.
Timing of surgery. After skeletal maturity when possible, because recurrence is lower; as an emergency for fractures and neurological compromise; and prophylactically for high-risk proximal femoral lesions.
Complications and Prognosis
Pathological fracture. The most common complication, occurring in 20-50% of polyostotic patients and most often in the proximal femur and tibia. Fractures are usually minimally displaced and are treated conservatively in a cast or brace where possible, with prophylactic fixation considered once they have healed.
Progressive deformity. The shepherd's crook, limb length discrepancy of up to 5-10 cm in severe cases, and angular deformity such as tibial bowing.
Cranial nerve compression. Decompress surgically if it progresses.
- Optic nerve: vision loss in 10% of craniofacial cases
- Auditory nerve: hearing loss
- Facial nerve: facial weakness
Beyond the classic sites of ribs, femur, skull and craniofacial bones, vertebral involvement is well recognised in polyostotic disease and is an examinable, easily-missed complication. Scoliosis is the commonest spinal manifestation and a recognised cause of progressive deformity in polyostotic FD and McCune-Albright syndrome: curves can progress, contribute to disability, and in severe untreated MAS are associated with increased morbidity and even mortality, so active spinal surveillance is part of polyostotic-disease follow-up. Vertebral lesions (ground-glass, expansile) can cause pathological vertebral fracture and, rarely, spinal canal compromise with cord or root compression requiring decompression and stabilisation.
Bracing has limited efficacy in dysplastic curves. Posterior instrumented fusion is used for progressive or large curves, recognising the poorer bone quality and graft-resorption tendency of FD bone, so instrumented load-sharing constructs are favoured, as in the long bones.
Malignant transformation. Under 1% at population level, with estimates commonly quoted as 0.4-1%. Referral series over-represent the risk: the Mayo Clinic cohort found 28 sarcomas among 1122 cases (Ruggieri 1994), and 46% of those transformations had received prior radiotherapy; radiation is the major avoidable risk factor. The risk is slightly higher in polyostotic and in craniofacial disease, and the craniofacial bones and the proximal femur are the commonest sites of transformation. The sarcomas in that series:
- Osteosarcoma, the most common, 19/28
- Fibrosarcoma, 5/28
- Chondrosarcoma, 3/28
- Malignant fibrous histiocytoma, 1/28
The warning signs in a long-standing lesion:
- New pain
- Rapid growth after skeletal maturity
- A soft tissue mass on imaging
- Periosteal reaction or cortical destruction
Avoid radiation therapy for fibrous dysplasia: it is the major avoidable risk factor for malignant transformation. Manage with surgery and, for refractory pain, bisphosphonates instead.
Prognosis in monostotic disease. Excellent. Lesions stabilise at skeletal maturity, surgery is curative in most cases, and recurrence after maturity is low, under 10%.
Prognosis in polyostotic disease. Variable, depending on extent, and the disease may progress through adulthood. Bisphosphonates improve quality of life, and functional outcomes are good with management.
Prognosis in McCune-Albright syndrome. Set by the endocrine complications. The skeletal disease is managed as for polyostotic disease, the endocrinopathy management is critical, and multidisciplinary follow-up is lifelong.
Guidelines, Registries & Global Practice
Global Epidemiology
Fibrous dysplasia is rare, with an estimated prevalence in the region of 1 in 4,000 to 1 in 10,000, accounting for roughly 5-7% of benign bone tumours. McCune-Albright syndrome is far rarer (estimated between 1 in 100,000 and 1 in 1,000,000). The full FD/MAS spectrum arises from the same somatic gain-of-function GNAS mutation; monostotic disease predominates (~70-80% of cases) and is distributed worldwide without strong geographic or ethnic clustering. Because the disorder presents across orthopaedics, endocrinology, ENT/craniofacial surgery and dentistry, under-recognition and wide variation in investigation and treatment are well documented internationally — the central problem the 2019 international consensus set out to address.
Side-by-Side Guidance
- Scope / Focus
- Definitive multidisciplinary best-practice consensus
- Key positions
- GNAS-informed diagnosis, endocrine screening in MAS, surgery for deformity/fracture (not lesion eradication), bisphosphonates only for refractory bone pain
- Evidence level
- Consensus statement (expert)
- Scope / Focus
- Medical therapy and endocrinopathy management
- Key positions
- Treat MAS endocrinopathies (precocious puberty, GH excess, thyroid, FGF23-mediated hypophosphataemia); RCT data show bisphosphonates reduce turnover but not proven to relieve pain
- Evidence level
- RCT-informed (Level II for bisphosphonates)
- Scope / Focus
- Surgical strategy and oncological vigilance
- Key positions
- Load-sharing intramedullary fixation over plates in long bones; correct deformity by osteotomy; avoid radiotherapy; biopsy any lesion with red-flag change
- Evidence level
- Largely Level IV (case series)
- Scope / Focus
- Optic nerve and craniofacial disease
- Key positions
- Prophylactic optic-nerve decompression NOT routinely recommended for asymptomatic encasement; operate for documented progressive visual loss; conservative contouring over radical resection
- Evidence level
- Consensus (expert)
Multidisciplinary management: Complex FD, and McCune-Albright syndrome in particular, requires coordinated orthopaedic surgery, endocrinology, ENT/craniofacial surgery, ophthalmology and genetics input. The consensus model is a designated multidisciplinary team or rare-bone-disease referral centre, an approach mirrored across European reference networks (e.g. ERN BOND) and major North American and Australasian paediatric centres.
Bisphosphonate access and use: Intravenous pamidronate and zoledronic acid (and oral alendronate) are widely available; international consensus restricts their use to fracture-related or persistent bone pain rather than disease modification, reflecting the Boyce 2014 RCT. Denosumab has been used off-label in refractory disease but lacks controlled evidence and carries a notable rebound-hypercalcaemia risk, especially in children. Intravenous bisphosphonates are administered in a hospital or specialist-supervised setting; the funding and access route for infused agents varies between health systems, but the clinical indication — specialist-supervised use for refractory or fracture-related bone pain — is consistent internationally.
Genetic testing: Somatic GNAS mutation testing on lesional tissue (or, with sensitive assays, peripheral blood in MAS) can confirm atypical cases. It is used for diagnostic confirmation and counselling — the disorder is sporadic and not heritable, so cascade family testing is not indicated.
Surveillance and registries: Plain radiographs remain first-line; CT aids craniofacial/surgical planning and bone scintigraphy or whole-body MRI maps polyostotic burden. There is no large dedicated FD/MAS arthroplasty-style registry; longitudinal cohorts (notably the NIH natural-history cohort) and the FD/MAS consortium provide the principal pooled outcome data, and patient organisations maintain international registries to support rare-disease research.
MCQ Practice Points
Q: What mutation causes fibrous dysplasia and what is its mechanism?
A: GNAS mutation at Arg201 codon (postzygotic somatic mutation) causing constitutive activation of Gsα protein and excess cAMP production. This drives abnormal osteoblast differentiation, replacing normal bone with fibrous tissue and immature woven bone. It is NOT inherited - occurs sporadically.
Q: What is the pathognomonic radiographic appearance of fibrous dysplasia?
A: Ground-glass opacity with homogeneous, hazy, smoky density. Loss of normal trabecular pattern with endosteal scalloping and cortical thinning (not cortical breakthrough). The lesion is expansile but well-circumscribed. No periosteal reaction unless complicated by fracture.
Q: What are the three classic features of McCune-Albright syndrome?
A: Polyostotic fibrous dysplasia plus café-au-lait macules (coast of Maine borders, irregular) plus precocious puberty (or other endocrinopathy such as hyperthyroidism, acromegaly, Cushing syndrome). All result from the same GNAS mutation affecting multiple tissue types.
Q: What is the classic histological pattern of fibrous dysplasia?
A: Chinese letters (alphabet soup) pattern - irregular trabeculae of woven bone in a fibrous stroma WITHOUT osteoblastic rimming. Absence of osteoblastic rimming distinguishes from reactive bone or ossifying fibroma. Trabeculae curve and branch in irregular patterns resembling Chinese characters.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old female undergoes chest X-ray for pneumonia screening. An incidental well-defined expansile lesion with ground-glass appearance is noted in the left 6th rib. She is completely asymptomatic. How would you manage this patient?”
“A 12-year-old boy with known polyostotic fibrous dysplasia presents with progressive left proximal femur deformity and limp. X-rays show shepherd's crook deformity with varus angulation and ground-glass appearance involving the proximal third of the femur. How would you approach this case?”
“A 45-year-old man with known fibrous dysplasia of the proximal humerus for 20 years presents with new onset pain over the past 3 months without trauma. X-rays show the known ground-glass lesion but with some ill-defined margins and possible soft tissue fullness. What are your concerns and how would you proceed?”
Genetics & Pathophysiology
- GNAS mutation at the Arg201 codon - a postzygotic somatic mutation
- Constitutive Gsα activation → excess cAMP → abnormal osteoblast function
- NOT inherited - a sporadic developmental disorder, not a true neoplasm
- Fibro-osseous metaplasia - normal marrow replaced by fibrous tissue and woven bone
Clinical Forms (3 Types)
- Monostotic (70%): a single bone, typically ribs or femur, presenting in the teens to twenties and stabilising at maturity
- Polyostotic (30%): multiple bones, childhood onset, with craniofacial involvement common
- McCune-Albright: polyostotic fibrous dysplasia + café-au-lait macules (coast of Maine borders) + endocrinopathy (precocious puberty)
Key Imaging Features
- Ground-glass opacity - a homogeneous hazy density, effectively pathognomonic
- Endosteal scalloping with cortical thinning, but not cortical breakthrough
- Loss of corticomedullary differentiation - a blurred inner cortex
- No periosteal reaction unless a fracture is present
- Shepherd's crook deformity - proximal femoral varus in polyostotic disease
Histology - Chinese Letters
- Irregular woven bone trabeculae in C, S and alphabet shapes
- NO osteoblastic rimming - the key distinction from ossifying fibroma, which does show rimming
- Fibrous stroma - bland spindle cells on a fibroblastic background
- Variable bone content, from minimal to extensive woven bone
Management Principles
- Asymptomatic monostotic disease: observe with serial radiographs - the commonest scenario
- Bisphosphonates (pamidronate, zoledronic acid): for pain in polyostotic disease
- Curettage and bone graft: for symptomatic monostotic disease after fracture
- Prophylactic intramedullary nail: for shepherd's crook deformity or impending fracture (over 50% cortical involvement)
- Avoid radiation therapy: the major avoidable risk factor for malignant transformation
Complications & Prognosis
- Pathological fracture - the most common complication, in 20-50% of polyostotic disease
- Malignant transformation - under 1% overall, with osteosarcoma the commonest
- Cranial nerve compression - vision or hearing loss in about 10% of craniofacial disease
- Monostotic prognosis is excellent - it stabilises at skeletal maturity
- Polyostotic disease is variable and may progress; bisphosphonates improve quality of life
Exam Viva Key Points
- A developmental disorder, NOT a neoplasm - the postzygotic mutation affects development
- Ground-glass appearance is effectively pathognomonic and differentiates it from most other lesions
- Monostotic disease is about 20 times more common than polyostotic
- Ossifying fibroma shows osteoblastic rimming; fibrous dysplasia does not
- McCune-Albright triad: fibrous dysplasia + café-au-lait macules + endocrinopathy (the CAFE mnemonic)
Evidence Base
Activating Mutations of the Stimulatory G Protein in McCune-Albright Syndrome
- Activating Gsα (GNAS) mutations at codon Arg201 (R201H and R201C) identified in all 4 MAS patients
- Mosaic tissue distribution supports a postzygotic somatic mutation early in embryogenesis
- Loss of GTPase activity drives constitutive Gsα activation and excess cAMP
- Established the unifying genetic basis for fibrous dysplasia and McCune-Albright syndrome
GNAS: Normal and Abnormal Functions (Gsα signalling and imprinting)
- Constitutive Gsα activation results from impaired GTP hydrolysis at Arg201/Gln227
- Same gene produces opposite phenotypes: activating → FD/MAS, inactivating → AHO
- Tissue-specific GNAS imprinting helps explain the variable endocrine phenotype
- Provides the molecular framework linking cAMP excess to abnormal osteoblast differentiation
Randomised Controlled Trial of Alendronate for Fibrous Dysplasia of Bone
- Alendronate lowered urinary NTX-telopeptide and raised areal BMD in FD lesions (both statistically significant)
- No significant effect on pain scores, skeletal disease burden or functional walk/strength tests
- Serum osteocalcin unchanged between groups
- Best evidence that bisphosphonates modulate bone turnover but are not proven to relieve FD pain or alter the lesion radiographically
Best Practice Management Guidelines for Fibrous Dysplasia / McCune-Albright Syndrome
- Defines best-practice diagnostic and monitoring pathways across orthopaedics, endocrinology and craniofacial care
- Surgery aims to correct/prevent deformity and fracture, not to 'cure' the lesion (grafts characteristically resorb)
- Bisphosphonates recommended for fracture-related or persistent bone pain, not as disease-modifying therapy
- Mandates endocrine screening and prophylactic optic-nerve management decisions in craniofacial MAS
Sarcomatous (Malignant) Transformation in Fibrous Dysplasia
- 28 sarcomas in 1122 referral cases of FD; osteosarcoma the most common transformation (19/28)
- 46% of transformations followed prior radiotherapy — a key avoidable risk factor
- Craniofacial bones and proximal femur were the commonest sites of malignant change
- Population-level malignant transformation risk is under 1%; this referral cohort over-represents it
Curettage, Bone-Grafting and Realignment for Proximal Femoral Fibrous Dysplasia
- 22 patients / 27 femora; grafts uniformly resorbed and lesions persisted
- Curettage + grafting offered no advantage over realignment osteotomy alone
- Valgus osteotomy with internal fixation, performed early, is the treatment of choice for shepherd's crook deformity
- Polyostotic disease with calcar involvement had worse bone quality and outcomes