Excision Arthroplasty | Salvage Procedure | Definitive or Staging
- Primary indication: Periprosthetic joint infection (PJI) not suitable for DAIR
- Named after Gathorne Robert Girdlestone (1881-1950)
- Results in significant LLD (4-6cm) and functional limitation
- Can be definitive or interim (2-stage revision)
- Harris hip score improves with reimplantation
- “Trendelenburg gait expected post-procedure
- “Hip abductors critical for stability of pseudarthrosis
- “Spacer preferred for interim if reimplantation planned
- “Higher success rate when combined with adequate antibiotics
Overview and Epidemiology
The Girdlestone procedure, or excision arthroplasty, resects the femoral head and neck and puts nothing back. It is now used mainly as a salvage procedure for periprosthetic joint infection (PJI) when other options have failed or are contraindicated.
History. G.R. Girdlestone (1881-1950) described excision arthroplasty in 1943 for tuberculosis of the hip. In the pre-antibiotic era it was the primary treatment for the septic hip. It is now reserved for salvage of the infected arthroplasty, or for the patient who is not a candidate for replacement.
The indication today. The core indication is PJI where DAIR has failed or is contraindicated. The patient must still be medically fit for surgery and able to tolerate prolonged antibiotics. The resection may be definitive, a permanent hip, or interim, clearing the infection before reimplantation.
Indications and Contraindications
- Context
- Early infection, debridement insufficient
- Type
- Staging or definitive
- Context
- Recurrent infection despite reimplantation
- Type
- Definitive
- Context
- Fungal, MDR bacteria
- Type
- Definitive or long-term antibiotic
- Context
- High surgical risk, poor functional reserve
- Type
- Definitive
- Context
- Insufficient stock for reconstruction
- Type
- Definitive
- Context
- Unable to complete antibiotic course
- Type
- Definitive with suppression
Failed DAIR. Failure of DAIR (debridement, antibiotics and implant retention) is an indication in its own right. It means persistent positive cultures, a persisting sinus tract, ongoing clinical infection, or CRP and ESR that fail to normalise despite an adequate course.
Fungal infection. Fungi sit among the difficult organisms above, but the fungal systematic review in the evidence below found recurrence in 53.1% after resection arthroplasty against 47.7% after two-stage exchange. In fungal PJI a Girdlestone is not the higher-certainty option.
Beyond PJI. The rare indications are:
- Native hip septic arthritis after failed treatment
- Tuberculosis, historically, and rarely now
- Severe avascular necrosis not suitable for THR
- Certain malignancies, as palliation
RESCUEIndications for Girdlestone
Hook:When patient needs RESCUE from failed hip, consider Girdlestone!
When to consider alternatives. Consider another route first in these situations:
- Why Not Girdlestone
- Unacceptable functional outcome
- Alternative
- 2-stage revision
- Why Not Girdlestone
- DAIR may succeed
- Alternative
- DAIR first
- Why Not Girdlestone
- May still need immediate resection
- Alternative
- Girdlestone may be indicated
- Why Not Girdlestone
- Wound healing concerns
- Alternative
- Optimise first, then decide
No absolute contraindication. The Girdlestone is often the last resort, and there is no absolute contraindication to it as such. The relative ones are a patient unwilling to accept the disability and a patient medically unstable for any surgery; for the severely ill, palliative suppression is sometimes the only option. Discuss functional expectations thoroughly and weigh the patient's overall goals before deciding.
Pathophysiology and Mechanisms
What comes out and what stays. Everything infected is removed, and the structures that will stabilise the hip afterwards are kept wherever they are viable.
- Preserve/Remove
- PRESERVE
- Rationale
- Abductor attachment crucial for stability
- Preserve/Remove
- REMOVE
- Rationale
- Source of infection, resect to healthy bone
- Preserve/Remove
- REMOVE
- Rationale
- Biofilm eradication requires complete removal
- Preserve/Remove
- PRESERVE
- Rationale
- Trendelenburg gait worsens if lost
- Preserve/Remove
- VARIABLE
- Rationale
- May help contain pseudarthrosis
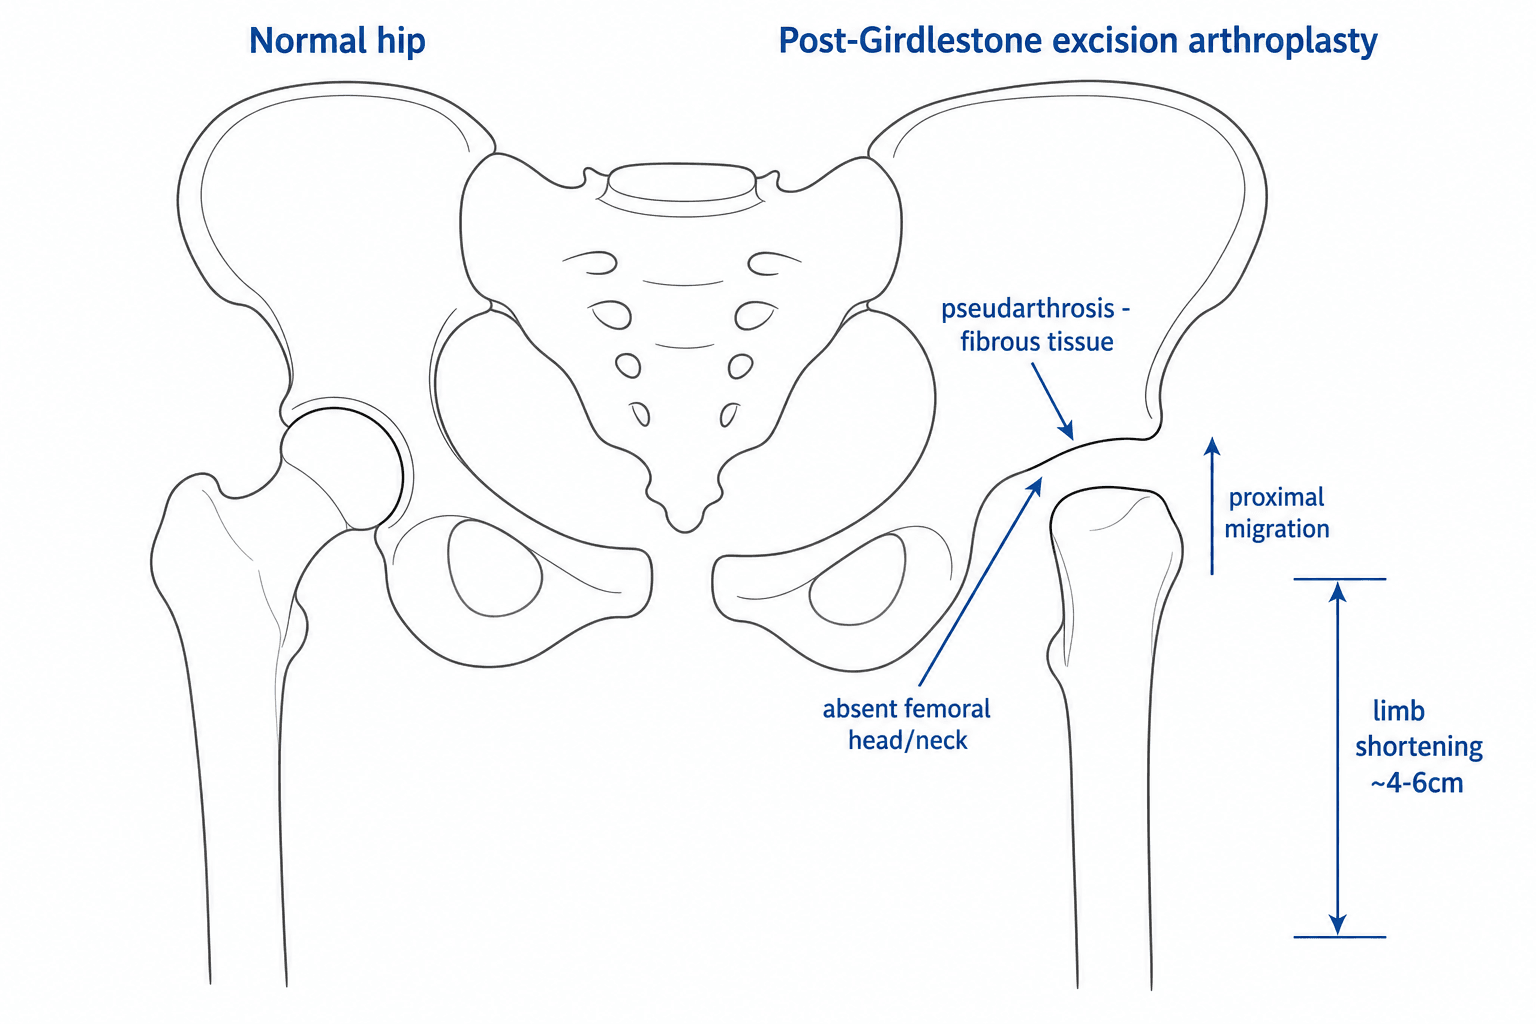
The pseudarthrosis. After resection a fibrous pseudarthrosis develops. The proximal femoral stump migrates superiorly until it articulates with the ischium or ilium, the acetabulum is defunctioned, and weight is borne through the ischium. Excessive bone resection allows more proximal migration and gives worse function. Shortening of 4-6 cm is typical.
The abductors. Gluteus medius and minimus insert on the greater trochanter, and this abductor mechanism must be preserved for the pseudarthrosis to be stable. Abductor function determines stability: if it is preserved, the patient may achieve limited ambulation.
Classification Systems
Type of infection. PJI is classified by timing and onset, which helps predict treatment success and guides surgical planning.
- Timing
- Less than 4 weeks post-op
- Typical Organism
- S. aureus, gram-negatives
- Management
- DAIR often successful
- Timing
- Greater than 4 weeks, less than 12 months
- Typical Organism
- S. epidermidis, low virulence
- Management
- DAIR may work, often 2-stage
- Timing
- Any time, acute onset
- Typical Organism
- S. aureus, streptococcus
- Management
- DAIR if less than 3 weeks symptoms
- Timing
- Established infection
- Typical Organism
- Any organism
- Management
- 2-stage or Girdlestone
DAIR or excision. DAIR succeeds with an acute infection (under 4 weeks), a sensitive organism, a well-fixed prosthesis and a healthy host. The Girdlestone indications are failed DAIR, chronic infection, resistant organisms and poor host status.
Type of Girdlestone. The resection is classified by its intent, which helps determine the approach and how the patient is counselled.
- Intent
- Temporary before reimplantation
- Typical Patient
- Fit patient, good bone stock
- Outcome Goal
- Infection control, then revise
- Intent
- Permanent solution
- Typical Patient
- Unfit for revision, failed 2-stage
- Outcome Goal
- Pain relief, infection control
- Intent
- Maintains soft tissue tension
- Typical Patient
- Planned reimplantation
- Outcome Goal
- Better interim function
- Intent
- Maximum debridement
- Typical Patient
- Definitive or complex infection
- Outcome Goal
- Focus on eradication
Clinical Assessment
History. Establish the infection, its course and the host:
- Presenting symptoms of pain, swelling and sinus drainage, and whether they are acute or chronic
- Previous surgery, including the number of revisions and the organisms grown
- Antibiotic history: previous treatment and allergies
- Comorbidities such as diabetes and immunosuppression
Examination. Inspect the wound for a sinus tract, drainage and erythema, and assess the joint for warmth, effusion and range of movement. Record sciatic nerve function, the current limb-length discrepancy, and gait and ambulatory status.
- Significance
- Definitive (pathognomonic) for PJI
- Action Required
- No further testing needed for diagnosis; proceed to treatment planning
- Significance
- Highly suspicious
- Action Required
- Aspiration and imaging
- Significance
- Suggestive
- Action Required
- Full workup needed
- Significance
- Supportive evidence
- Action Required
- Correlate with clinical picture
Investigations
Blood tests. CRP is the most sensitive marker, with the ESR alongside it, and serial values monitor the response to treatment. The white cell count is often normal in chronic infection. Take blood cultures if there are systemic symptoms, and albumin, prealbumin and HbA1c to assess nutrition and glycaemic control.
Aspiration. Synovial fluid is sent for white cell count (threshold over 3000/μL), PMN percentage (over 80%) and culture, with alpha-defensin if available. Cultures are held for 14 days, which improves detection of slow-growing organisms such as Propionibacterium acnes, and samples are taken before antibiotics.
Imaging. Radiographs show component loosening, bone loss and periosteal reaction. CT assesses bone defects and the location of cement. MRI is rarely needed, to look for a soft-tissue collection, and nuclear medicine is kept for the case where the diagnosis remains uncertain.
The diagnosis. The MSIS criteria make it: one major criterion, or four of the six minor criteria.
- Criteria
- Sinus tract OR 2+ cultures same organism
- Interpretation
- Definitive diagnosis
- Criteria
- Elevated ESR/CRP
- Interpretation
- Supportive evidence
- Criteria
- Elevated synovial WCC (greater than 3000)
- Interpretation
- Supportive evidence
- Criteria
- Elevated synovial PMN% (greater than 80%)
- Interpretation
- Supportive evidence
- Criteria
- Positive histology (greater than 5 PMN/HPF)
- Interpretation
- Supportive evidence
- Criteria
- Positive single culture
- Interpretation
- Supportive evidence
- Criteria
- Purulence
- Interpretation
- Supportive evidence
Differential Diagnosis
A painful or failing hip arthroplasty is not always infected. Distinguishing PJI from aseptic causes is the pivotal decision before resection — an unnecessary Girdlestone for aseptic loosening is a catastrophic error.
- Discriminating Features
- Sinus, rest pain, raised CRP/ESR, early loosening
- Key Test
- Aspiration (synovial WCC/PMN%, culture), MSIS score
- Why It Matters
- Mandates debridement/resection, not simple revision
- Discriminating Features
- Activity-related pain, normal inflammatory markers
- Key Test
- Serial radiographs (lucency, migration), normal aspirate
- Why It Matters
- Treated by revision, NOT resection
- Discriminating Features
- Metal bearing, pseudotumour, rising cobalt/chromium
- Key Test
- Metal ions, MARS-MRI
- Why It Matters
- Revision of bearing, not infection pathway
- Discriminating Features
- Trauma, acute pain, deformity
- Key Test
- Radiographs, Vancouver classification
- Why It Matters
- Fixation/revision, not excision
- Discriminating Features
- Spinal stenosis, GTPS, hernia, vascular claudication
- Key Test
- Targeted exam, imaging, diagnostic injection
- Why It Matters
- Avoids unnecessary hip surgery
- Discriminating Features
- Mechanical clunk, recurrent subluxation
- Key Test
- Component-position CT, dynamic exam
- Why It Matters
- Component revision, not resection
Always exclude aseptic loosening, ALTR and extra-articular pain before committing to excision arthroplasty. A negative aspirate, normal CRP/ESR and no sinus point away from infection. Resection arthroplasty for a misdiagnosed aseptic hip needlessly inflicts permanent shortening and aid-dependence.
What Makes a 'Good' vs a 'Poor' Girdlestone: the Biomechanics of the Pseudarthrosis
- Resection level is the single biggest surgeon-controlled variable. The femur is resected only as far distal as infection/removal demands - conserving length keeps the femoral stump abutting the ischium/ilium rather than riding high. A high resection (short stump) allows greater proximal migration, worsens the lever arm and produces a longer, more unstable limb-shortening; a more distal, length-preserving resection (consistent with clearing the infection) gives a shorter migration and a more stable articulation. The 4-6 cm shortening is the price; making it worse than necessary is avoidable.
- The abductor lever arm is what powers gait. A pseudarthrosis is stabilised dynamically, not by bone - so an intact abductor complex on a preserved greater trochanter lets the patient generate a functional (if Trendelenburg) gait, whereas a detached/non-viable trochanter or a deficient abductor mass produces a flail hip, a lurching or non-functional gait and aid-dependence or wheelchair use. Preserving the trochanter and its attachment whenever it is viable is therefore a functional imperative, not a cosmetic one.
- Soft-tissue interposition and scar create the fibrous articulation. A broad, well-vascularised soft-tissue envelope between the proximal femur and pelvis (capsule remnants, vastus/glutei, sometimes a formal muscle interposition) matures into a stable fibrous pseudarthrosis and cushions the bone-on-bone contact that causes pain; extensive dead space or a bare femoral stump against pelvis gives instability and pain.
- Host and disease factors set the ceiling. Even with perfect technique, bilateral disease, poor abductors from prior surgery, neuromuscular disease, uncontrolled pain and low functional reserve cap the achievable result - which is why the honest counselling statement is that every patient in these series walked with aids, and many barely walked at all.
Q: What does the surgeon control that determines whether a Girdlestone hip is stable and walkable? A: Three things. (1) Resection level - resect only as far as infection clearance requires; a length-preserving resection keeps the stump against the pelvis and limits proximal migration, whereas a high/short stump gives more migration, more shortening and instability. (2) The abductor lever arm - a preserved, viable greater trochanter with intact abductors gives a functional Trendelenburg gait; a detached/deficient abductor mass gives a flail, non-ambulatory hip. (3) Soft-tissue interposition - a broad vascularised muscle/capsule envelope matures into a stable, less painful fibrous pseudarthrosis. Host factors (bilateral disease, neuromuscular status, reserve) then set the ceiling.
Converting a Girdlestone Back to a Hip: Delayed Reimplantation
- When it is done, and the prerequisites. Conversion is considered once the infection is truly eradicated (normalised inflammatory markers, negative aspirate/intra-operative samples, an interval off antibiotics) in a host now fit and motivated for a major reconstruction. It is the "second stage" that a spacer was meant to facilitate - and the longer the hip has been left as a bare Girdlestone (no spacer), the harder it becomes.
- The soft tissues are the enemy. After months of a shortened, migrated hip the abductors and capsule contract and scar, the femur sits proximal, and restoring length re-tensions a chronically shortened neurovascular envelope - so conversion carries a real risk of sciatic/femoral nerve traction injury when length is regained, and full LLD correction is often not achievable in one sitting. Heterotopic bone and dense scar further obscure planes.
- Bone stock and fixation are compromised. Repeated debridements and the original resection leave deficient femoral and acetabular bone, frequently needing revision/reconstruction implants (long stems, cup-cage/augments, sometimes a proximal femoral replacement) rather than a primary THA.
- Abductor deficiency drives instability - the dominant complication. The scarred, shortened, often-deficient abductor mechanism makes the converted hip prone to dislocation, so constrained or dual-mobility bearings are frequently used; overall complication, dislocation and re-infection rates are markedly higher, and functional outcomes poorer, than a primary THA - though still usually better than a retained Girdlestone in a suitable host.
Q: What are the specific challenges of converting a healed Girdlestone to a THA? A: Only after confirmed infection eradication in a fit host. Expect contracted, scarred, deficient abductors and capsule (high dislocation risk - consider dual-mobility/constrained), proximal femoral migration so that regaining length risks sciatic/femoral nerve traction injury and full LLD correction is often incomplete, deficient femoral/acetabular bone stock needing revision implants (long stems, cup-cage/augments, sometimes proximal femoral replacement), and heterotopic bone/scar. Complication, dislocation and re-infection rates exceed a primary THA and function is poorer - which is part of why a definitive Girdlestone is accepted in the unfit or unreconstructable host.
Management Algorithm
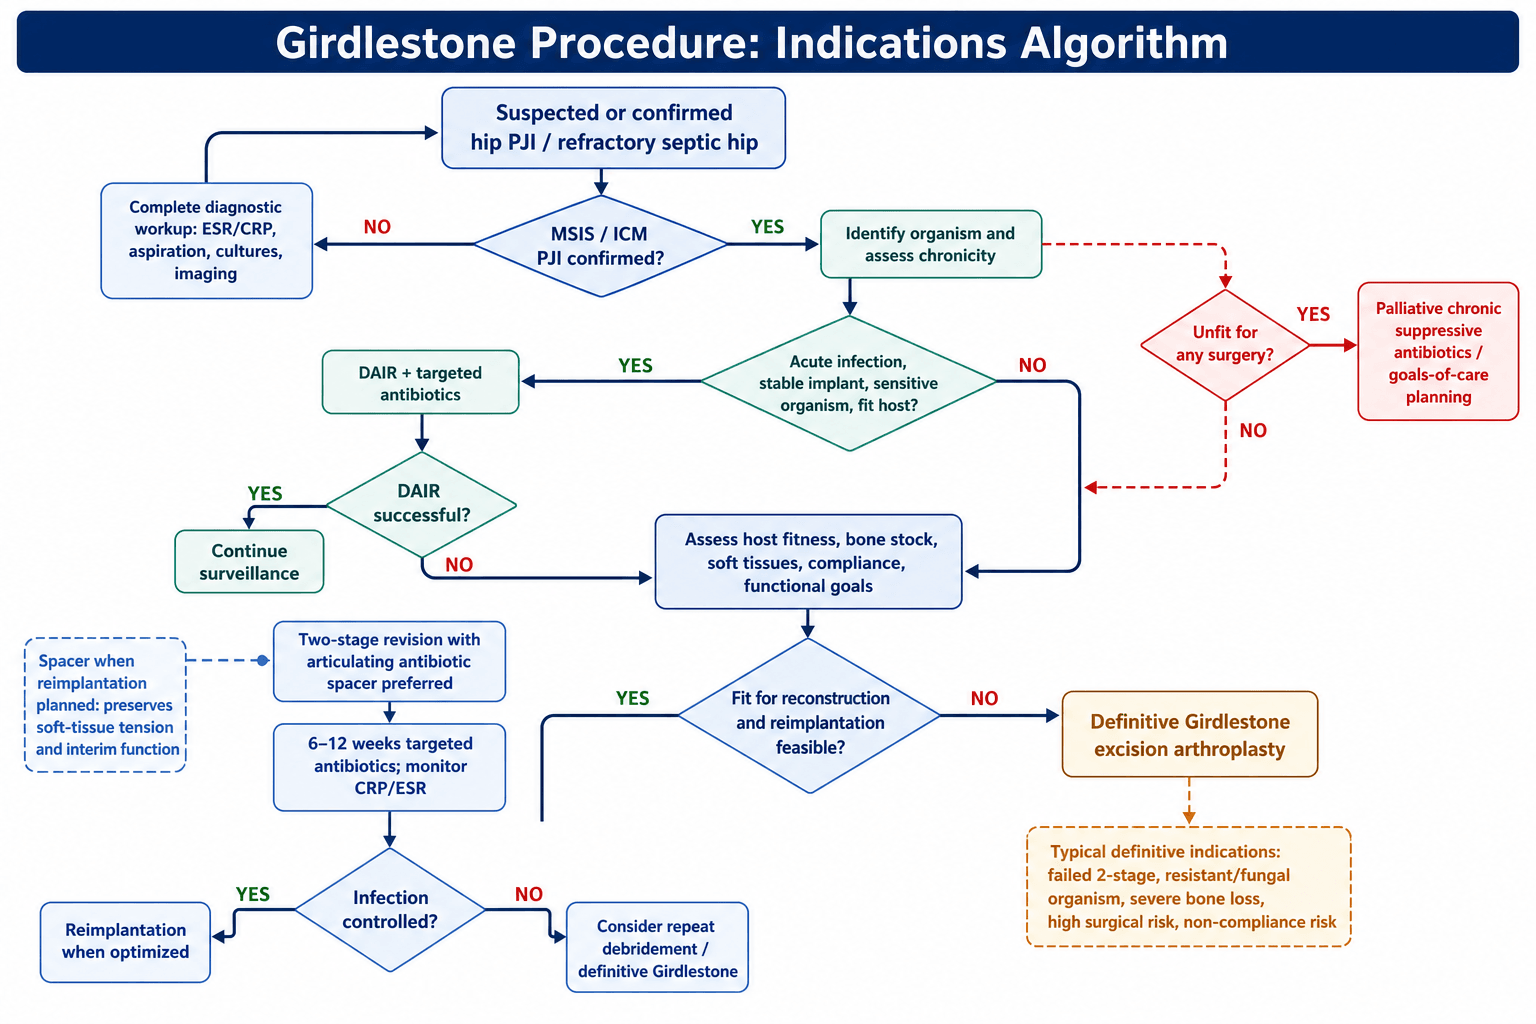
The sequence. Confirm PJI by the MSIS criteria and identify the organism if possible. Then assess the patient: medical fitness for surgery, bone stock, social support and compliance, and functional expectations. Multidisciplinary discussion with infectious diseases, microbiology and the patient is essential.
- Recommended Treatment
- DAIR first
- Rationale
- High success rate, preserves function
- Recommended Treatment
- 2-stage with spacer preferred
- Rationale
- Fit for revision; organism sensitive and identifiable
- Recommended Treatment
- 2-stage with spacer
- Rationale
- Good outcomes, aims for reimplantation
- Recommended Treatment
- Girdlestone (possibly definitive)
- Rationale
- Prioritises infection control
- Recommended Treatment
- Definitive Girdlestone
- Rationale
- Prioritises infection control
- Recommended Treatment
- Definitive Girdlestone + suppression
- Rationale
- Prioritises infection control
- Recommended Treatment
- Chronic suppression
- Rationale
- Palliative approach
The rung above resection. The table names two-stage revision as the reconstructive route. The INFORM trial in the evidence below found that, in suitable hosts, single-stage revision matched two-stage for medium-term outcome, so resection is reserved for patients unfit for, or failed by, reconstruction.
Spacer or no spacer. If reimplantation is planned, an articulating antibiotic-loaded spacer is preferred. It maintains soft-tissue tension, which a Girdlestone loses, and gives better function while the infection is treated. A true Girdlestone is for definitive cases or when a stable spacer cannot be achieved, and a static spacer is the other definitive option. The spacer adds cost where the Girdlestone is simpler, and both are effective if the debridement is adequate.
Preoperative Planning
Confirm the infection by the MSIS criteria, as set out under Investigations.
Identify the organism. The pathogen determines antibiotic selection and duration. In refractory cases consider resistant organisms, fungi or mycobacteria, and liaise with microbiology and infectious diseases early.
Optimise the patient. Nutrition (albumin over 3 g/dL, total lymphocyte count), glycaemic control (HbA1c under 8%) and smoking cessation, with cardiac and renal comorbidities addressed.
Plan the operation. Review previous incisions and the bone loss on imaging, and consider whether a spacer or a definitive resection is intended. Discuss realistic functional expectations with the patient, including the need for walking aids and the leg-length discrepancy.
Surgical Technique
Anaesthesia. General or regional anaesthesia, prepared for a potentially lengthy procedure, with adequate IV access and invasive monitoring if indicated.
Position. The lateral decubitus position is most common and allows access to both acetabulum and femur, with the pelvis secured in supports. Supine on a fracture table is the alternative if the procedure is combined with another.
Preparation. Standard prep and drape, exposing the entire limb so length can be assessed, and mark previous incisions. Plan an extensile approach if a cemented prosthesis will need aggressive cement removal.
Complications
- Incidence
- 10-30%
- Prevention/Management
- Adequate debridement, appropriate antibiotics, suppression if needed
- Incidence
- 15-25%
- Prevention/Management
- Optimise nutrition, meticulous closure, manage dead space
- Incidence
- Common (inherent)
- Prevention/Management
- Expected outcome - brace/abduction pillow initially
- Incidence
- 5-10%
- Prevention/Management
- Careful technique, prophylactic fixation if needed
- Incidence
- 1-3%
- Prevention/Management
- Careful dissection, identify and protect nerve
- Incidence
- Variable
- Prevention/Management
- Chemical and mechanical prophylaxis
Persistent infection. 10-30% may have persistent infection despite adequate surgery. The risk factors are resistant organisms, inadequate debridement, retained cement or foreign material, and immunocompromise.
When infection persists. Work through the causes before choosing between repeat debridement, long-term suppression and accepting a chronic wound:
- Confirm that the initial debridement was adequate
- Review antibiotic sensitivities and compliance
- Consider repeat surgery for retained material
- Long-term oral antibiotic suppression may control the infection but not eradicate it
Postoperative Care
Postoperative Protocol
Pain management, wound monitoring and drain management, and DVT prophylaxis begins. A hip abduction pillow or brace is used for comfort. IV antibiotics continue, guided by the cultures.
Sit out of bed at day 1-2 and begin protected weight bearing with a frame or crutches. Physiotherapy maintains muscle function. Inspect the wound, and remove staples at 2 weeks.
IV antibiotics continue, with transition to oral antibiotics if appropriate. Mobilisation progresses, and a shoe raise addresses the leg-length discrepancy.
Complete the antibiotic course, and monitor inflammatory markers; the CRP should normalise. Consider reimplantation if the procedure was staged. Finalise walking aids and orthotics.
Mobilisation. Weight bearing is as tolerated with aids, a walker or crutches. The programme includes hip abduction strengthening, gait training for the leg-length discrepancy and a shoe raise of 3-5 cm, and patients progress to a single stick over months.
Antibiotics. A minimum of 6 weeks of IV antibiotics is followed by oral therapy. The duration depends on the organism, the response and whether reimplantation is planned, and the regimen is set with infectious diseases. Monitor for drug toxicity: renal and ototoxicity with aminoglycosides, hepatic toxicity with rifampicin.
Monitoring. CRP weekly at first, then monthly. Assess the wound, function and pain at each visit, watch for antibiotic side effects, and image if retained material is suspected.
Outcomes and Prognosis
- Girdlestone (Definitive)
- 71% (65/91, Sabelle)
- 2-Stage with Reimplantation
- No eradication rate reported by the RCT on this page
- Girdlestone (Definitive)
- mean 64, range 25-83 (Stoklas)
- 2-Stage with Reimplantation
- Not measured in the sources cited here
- Girdlestone (Definitive)
- All patients used aids; mean 175m walked
- 2-Stage with Reimplantation
- Not measured in the sources cited here
- Girdlestone (Definitive)
- Variable
- 2-Stage with Reimplantation
- Higher
- Girdlestone (Definitive)
- 4-6cm
- 2-Stage with Reimplantation
- 1-2cm (correctable)
What the patient gains. Pain relief is usually achieved, though only a third of Stoklas's patients were fully pain free, and sitting tolerance is usually preserved. The result is better than ongoing sepsis or repeated failed surgery, and substantially worse than a successful reimplantation.
What it costs. Expect significant disability. Mean shortening was 5.7 cm in Sabelle's refractory-PJI series and 3.8 cm in Stoklas's mixed-indication series, and every patient in Stoklas's series had a positive Trendelenburg sign and used walking aids. The patient should expect a marked limp, permanent use of a stick or frame, and severe restriction of activity. The mean walking distance of 175 m in Sabelle's series carries a standard deviation of 350, meaning many walk almost nothing.
Good and poor results. A good result is pain control, an eradicated infection, independence in activities of daily living, walking with aids, and a patient satisfied with the outcome given the alternatives. A poor one is persistent infection, a chronic wound or sinus, a non-ambulatory patient, intractable pain and a poor quality of life.
Guidelines, Registries & Global Practice
Hip PJI affects roughly 1-2% of primary and up to 4-5% of revision total hip replacements worldwide. As arthroplasty volumes rise, the absolute burden of PJI is growing, and resection arthroplasty persists as the salvage of last resort across all health systems.
- Diagnostic Framework
- MSIS 2011 + 2018 validated weighted scoring; ICM consensus
- Position on Resection Arthroplasty
- Salvage for unreconstructable or multiply-failed PJI; spacer preferred if reimplantation feasible
- Diagnostic Framework
- Two-test screening (ESR + CRP), then aspiration; aligns with MSIS
- Position on Resection Arthroplasty
- Resection acceptable when host/limb cannot tolerate reconstruction
- Diagnostic Framework
- Multidisciplinary PJI MDT; aspiration before empirical antibiotics
- Position on Resection Arthroplasty
- Single- or two-stage favoured (INFORM RCT); resection reserved for non-reconstructable hips
- Diagnostic Framework
- EBJIS definition (confirmed/likely/unlikely PJI)
- Position on Resection Arthroplasty
- Resection or definitive Girdlestone for refractory infection or unfit host
- National registries (NJR England/Wales, AOANJRR, SHAR/Swedish, AJRR US, NZJR) track revision-for-infection rates
- Infection is a leading cause of early hip revision in all major registries
- Resection/excision is recorded but represents a small minority of revision outcomes
- Registry data confirm rising absolute PJI burden with increasing arthroplasty volume
- High-resource: 2-stage with antibiotic spacer, OPAT, alpha-defensin/D-dimer, specialist PJI MDT
- Limited-resource: Girdlestone often used as definitive primary salvage (no spacer, limited microbiology)
- TB and chronic septic native hip still managed by primary excision in endemic regions
- Prolonged IV antibiotics may be replaced by early oral therapy (OVIVA-supported) where OPAT unavailable
Examiners worldwide will expect: PJI diagnosis by MSIS/EBJIS criteria, the indication hierarchy (DAIR → single/two-stage → resection), surgical steps with the tissue-sampling protocol, antibiotic principles, and honest counselling of functional outcomes (shortening, Trendelenburg, aid-dependence).
Controversies & Areas of Uncertainty
With megaprostheses, cup-cage constructs and single-stage revision now feasible, the threshold for definitive excision keeps rising. Debate centres on whether borderline hosts are better served by a complex reconstruction attempt or by accepting a stable, infection-free pseudarthrosis.
Articulating spacers improve interim function and soft-tissue tension, but no high-level RCT proves superior infection eradication over a true Girdlestone. Spacer-related complications (dislocation, fracture, mechanical failure) are real, especially with major bone loss.
The INFORM RCT found no medium-term difference in patient-reported outcome between single- and two-stage hip revision, with single-stage offering faster recovery and lower cost. This narrows, but does not abolish, the role of staged management and resection.
Traditional 6-week IV courses are challenged by trial evidence (e.g. OVIVA) supporting early oral switch for bone and joint infection. Optimal duration after resection, and the value of lifelong suppression, remain unresolved.
MCQ Practice Points
Q: What is the most common indication for Girdlestone excision arthroplasty today? A: Periprosthetic joint infection (PJI) where DAIR has failed or is contraindicated, or as interim/definitive salvage for multiply recurrent infection. It was originally described for tuberculosis of the hip.
Q: What leg length discrepancy is typically expected after Girdlestone procedure? A: 4-6cm shortening - The proximal femur migrates superiorly until it articulates with the pelvis at a pseudarthrosis. This results in significant shortening requiring shoe raise and walking aids.
Q: How many tissue samples should be obtained during revision for PJI? A: Minimum 5 tissue samples from different locations (membrane, capsule, acetabulum, femoral canal, collections). Take BEFORE antibiotics. Send for aerobic, anaerobic, and extended culture.
Q: What is the main advantage of an articulating antibiotic spacer over Girdlestone as interim procedure? A: Maintains soft tissue tension - Preserves abductor length, improves interim function, and facilitates subsequent reimplantation by keeping soft tissues at appropriate tension and length.
Q: What are the major criteria for PJI diagnosis according to MSIS? A: Two major criteria: (1) Sinus tract communicating with the prosthesis, OR (2) Same organism isolated on 2 or more separate tissue/fluid samples. Either one confirms PJI.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 72-year-old diabetic man has had 2 previous revisions for infected THA over 5 years. He now presents with recurrent infection (MRSA), draining sinus, and HbA1c of 9.5%. He is a widower living alone with minimal family support.”
“A 58-year-old otherwise healthy woman presents with infected THA (Staphylococcus epidermidis, susceptible) 2 years post primary. DAIR failed after 6 weeks. She is motivated for best functional outcome and wants to return to golf.”
“During first stage of 2-stage revision for PJI, you encounter severe acetabular bone loss with a cavitary defect and pelvic discontinuity. The femur has reasonable stock. What do you do?”
“Culture from hip aspiration grows Candida albicans in a 65-year-old immunocompetent patient with painful THA. No previous surgery. What is your management?”
Core Concepts
- Excision arthroplasty = SALVAGE for infected THA
- Named after GR Girdlestone (TB of hip, 1943)
- Can be DEFINITIVE or INTERIM (2-stage)
- Spacer preferred if reimplantation planned
Indications (RESCUE)
- Failed DAIR or 2-stage revision
- Resistant/difficult organisms (MDR, fungal)
- Medical comorbidities precluding revision
- Severe bone loss preventing reconstruction
Surgical Pearls
- 5+ tissue samples BEFORE antibiotics
- Remove ALL cement (biofilm reservoir)
- Preserve ABDUCTORS (stability of pseudarthrosis)
- Copious lavage (minimum 9L)
Outcomes
- Infection eradication: 71% (65/91); ~47% in fungal PJI
- LLD: 4-6cm (need shoe raise)
- All patients aid-dependent; mean 175m walked
- Harris Hip Score mean 64 (range 25-83)
Exam Pearls
- MSIS criteria for PJI diagnosis
- Minimum 6 weeks IV antibiotics
- Trendelenburg gait expected
- Better than ongoing sepsis
Evidence Base
Sabelle A et al. Results of the Girdlestone Procedure for Refractory Hip Prosthesis Infections
- Single-centre series of 88 patients (91 hips) with refractory PJI. Infection eradicated in 65/91 (71%). Mean limb shortening 5.7cm; mean walking distance 175m; mean Merle d'Aubigné-Postel score 9.3/18. Corticosteroid use (HR 6), preoperative fever (HR 4.1) and polymicrobial infection (HR 2.5) were independent predictors of failure. Infection-related mortality 7%.
Stoklas J, Rozkydal Z. Resection of Femoral Head and Neck According to Girdlestone
- 28 hips in 26 patients treated by Girdlestone resection (mixed septic, tubercular, post-traumatic and CP indications). Pain relief in 84%; all patients required walking aids and all had a positive Trendelenburg sign. Mean limb shortening 3.8cm (range 1.5-6.5cm). Mean Harris Hip Score 64 (range 25-83); no excellent outcomes. 74% satisfied given alternatives.
Goldman AH, Abdel MP et al. Definitive Resection Arthroplasty of the Knee for Intractable Infection
- 25 knees treated with resection arthroplasty for recalcitrant PJI after a mean of 5 prior operations. 84% free of infection at mean 4-year follow-up; only 1 amputation. 45% community ambulators, 35% household, 20% transfer-only — all required bracing and assistive devices.
Blom AW et al. Single-stage vs Two-stage Revision for Hip PJI (INFORM RCT)
- Pragmatic multicentre RCT of 140 patients with hip PJI. No difference in WOMAC at 18 months between single- and two-stage revision; single-stage was better at 3 months, had fewer intraoperative complications (8% vs 27%) and was cost-effective. Markers of possible ongoing infection were similar (14% vs 11%).
Parvizi J et al. New Definition for Periprosthetic Joint Infection (MSIS Workgroup)
- Original standardized MSIS definition of PJI. Major criteria: sinus tract communicating with prosthesis, OR same organism on 2 separate cultures. Minor criteria (4 of 6): elevated ESR/CRP, elevated synovial WCC, elevated synovial PMN%, positive histology, single positive culture, purulence.
Parvizi J et al. The 2018 Definition of Periprosthetic Hip and Knee Infection (Validated Scoring Criteria)
- Evidence-based, externally validated scoring system. Major criteria (sinus tract or 2 positive cultures) remain diagnostic. Weighted minor criteria: serum CRP/D-dimer/ESR and synovial WCC, alpha-defensin, leukocyte esterase, PMN%, synovial CRP; aggregate score of 6 or more = infected. Sensitivity 97.7% vs 79.3% for the 2011 MSIS criteria.
Shang G et al. Burden and Treatment Challenges of Fungal PJI: Systematic Review of 489 Joints
- 489 joints across 24 studies. Candida albicans was the commonest organism (41.5%); 50.5% had concurrent bacterial coinfection. Recurrence by strategy: DAIR 81.4%, resection arthroplasty 53.1%, two-stage 47.7%. Mean systemic antifungal duration 12.8 weeks (fluconazole commonest); amphotericin B was the dominant cement additive.