Control | Correct | Compensate | Protect
- Functions: Control (motion), Correct (deformity), Compensate (weakness), Protect (healing)
- Three-point pressure = biomechanical basis of all corrective orthoses
- AFO types: Solid (blocks motion), Hinged (allows DF), Ground-reaction (extends knee)
- FRAFO = Floor Reaction AFO - uses ground reaction force to extend knee
- Spinal orthoses named by levels covered (LSO, TLSO, CTLSO)
- “Solid AFO for spastic equinus (blocks plantarflexion)
- “Hinged AFO allows tibial progression in stance (better gait)
- “Ground-reaction AFO for crouch gait (knee extension moment)
- “TLSO for thoracolumbar fractures (T9-L3 coverage)
- “Halo vest = only reliable cervical immobilization (greater than 90%)
Overview
An orthosis is an externally applied device used to control, correct, compensate for, or protect musculoskeletal dysfunction. Understanding orthotic prescription is essential for the orthopaedic surgeon managing neurological conditions, fractures, deformity correction and rehabilitation.
Four functions. Orthoses are classified by what they do:
- Control - limits unwanted motion in specific planes, as in spasticity or instability
- Correct - applies forces to correct a deformity
- Compensate - substitutes for weak or absent muscles, replacing lost function
- Protect - shields healing structures, after a fracture or an operation
The prescription. An orthotic prescription must specify the diagnosis, the joints to control, the motion to allow or block, the corrective forces needed, the material (plastic, metal or carbon fibre) and the footwear requirements.
Nomenclature and Classification
Naming. The International Organization for Standardization (ISO 8549) names orthoses systematically by the anatomical region and the joints they cross.
- Orthosis
- FO - foot orthosis
- Extent and typical use
- Insoles, arch supports, metatarsal pads
- Orthosis
- AFO - ankle-foot orthosis
- Extent and typical use
- Crosses the ankle joint; controls foot position
- Orthosis
- KAFO - knee-ankle-foot orthosis
- Extent and typical use
- Extends from thigh to foot; controls the knee
- Orthosis
- HKAFO - hip-knee-ankle-foot orthosis
- Extent and typical use
- Adds hip joint control
- Orthosis
- KO - knee orthosis
- Extent and typical use
- Braces for knee instability or unloading
- Orthosis
- WHO - wrist-hand orthosis
- Extent and typical use
- Wrist splints, resting hand orthoses
- Orthosis
- EWHO - elbow-wrist-hand orthosis
- Extent and typical use
- Extends to the elbow
- Orthosis
- SEWHO - shoulder-elbow-wrist-hand orthosis
- Extent and typical use
- Full upper limb
- Orthosis
- CO - cervical orthosis
- Extent and typical use
- Soft or rigid collars
- Orthosis
- CTO - cervicothoracic orthosis
- Extent and typical use
- Extends to the upper thorax
- Orthosis
- CTLSO - cervicothoracolumbosacral orthosis
- Extent and typical use
- Full spine control
- Orthosis
- TLSO - thoracolumbosacral orthosis
- Extent and typical use
- Thoracolumbar control
- Orthosis
- LSO - lumbosacral orthosis
- Extent and typical use
- Lower lumbar and sacral control
Materials. The material is part of the prescription, and each group has its own properties and uses.
- Material
- Polypropylene
- Properties and use
- Most common; heat-mouldable, durable
- Material
- Low-temperature plastics
- Properties and use
- Custom-moulded at lower temperatures
- Material
- Carbon-fibre composites
- Properties and use
- Lightweight, energy-storing (athletic use)
- Material
- Aluminium
- Properties and use
- Lightweight, adjustable
- Material
- Steel
- Properties and use
- Heavy-duty, adjustable; traditional KAFOs
- Material
- Titanium
- Properties and use
- Lightweight, strong (specialty applications)
- Material
- Neoprene
- Properties and use
- Compression, warmth, proprioceptive feedback
- Material
- Foam
- Properties and use
- Padding, pressure distribution
- Material
- Leather
- Properties and use
- Traditional, breathable, adjustable
Principles of Orthotic Biomechanics
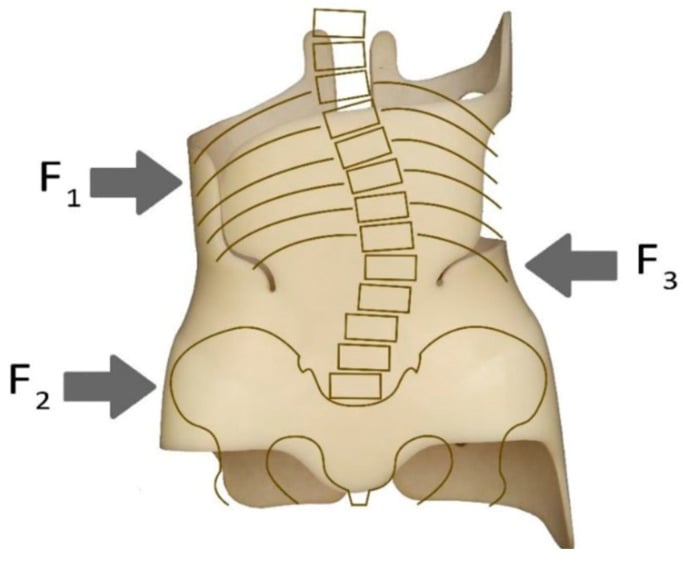
Three-point pressure. This is the biomechanical basis of all corrective orthoses. A central corrective force at the apex of the deformity is opposed by two counter-forces, one proximal and one distal to it, and together they create a bending moment that corrects or controls the deformity.
Lever arm and skin. The distance between the forces is the moment arm, and it sets the mechanical advantage: the longer the lever arm, the greater the advantage. The force must be distributed over a large surface area to prevent pressure ulcers, and soft-tissue tolerance limits the maximum corrective force a device can apply.
The same system appears throughout the body:
- TLSO for scoliosis - lateral pad at the curve apex, counter-pads at the iliac crest and axilla
- AFO for equinus - posterior force at the calf, anterior force at the tibial crest, and the foot plate
- Knee orthosis for valgus - lateral force at the knee, medial forces at the thigh and calf
Ground reaction force. The ground reaction force (GRF) passes through the centre of pressure. A GRF passing anterior to the knee creates a knee extension moment; one passing posterior to the knee creates a flexion moment. Ground-reaction orthoses, the floor-reaction AFO (FRAFO) among them, manipulate the GRF vector relative to the joint centres to position the GRF anterior to the knee and extend it in stance.
Crouch gait. Crouch gait is excessive knee flexion in stance, common in cerebral palsy, and weak quadriceps cannot hold the knee extended. The FRAFO blocks ankle dorsiflexion and moves the GRF anterior to the knee, and the resulting external knee extension moment compensates for the weak quadriceps.
Lever arms. A long lever gives greater control: a KAFO controls the knee better than a short KO, and a full-length thigh cuff gives better rotational control, at the cost of more weight and reduced function. A short lever gives greater mobility: a supramalleolar AFO (SMAFO) allows more tibial motion and a short KAFO allows easier sitting, at the cost of less control of the proximal joints.
Ankle-Foot Orthoses (AFOs)
AFO selection depends on the specific gait abnormality. The solid AFO blocks ankle motion, the hinged AFO allows dorsiflexion while blocking plantarflexion, and the ground-reaction AFO uses the ground reaction force to extend the knee.

Design. A rigid plastic shell runs from below the knee to the foot plate and blocks all ankle motion, dorsiflexion and plantarflexion alike. The foot plate extends to the metatarsal heads, or to the toes for spasticity.
What it does. It prevents plantarflexion in swing, which clears the foot, and gives mediolateral ankle stability. It also prevents dorsiflexion in stance, which may limit tibial progression.
What it costs. Blocked tibial progression in stance shortens step length, the absent plantarflexion reduces push-off power, and the knee compensates by hyperextending in mid-stance.
Indications:
- Spastic equinus (cerebral palsy, stroke, TBI)
- Severe ankle instability
- Complete foot drop with spasticity
- Fixed equinus contracture, where it blocks further progression
Contraindications:
- Intact plantarflexors, whose push-off power it blocks
- Patients who need to squat or climb stairs
- Skin breakdown risk at the calf or anterior tibia


Knee-Ankle-Foot Orthoses (KAFOs)
Indications. A KAFO is prescribed for three groups of problem:
- Knee instability - quadriceps weakness (polio, muscular dystrophy, SCI), ligamentous instability with neurological impairment, or knee hyperextension with loss of sensation
- Knee and ankle weakness - combined quadriceps and dorsiflexor weakness, a flail limb with complete paralysis below the knee, or myelomeningocele with high-level paralysis
- Deformity control - knee flexion contracture (serial casting with a KAFO), genu varum or valgum with weakness, and post-surgical protection
Construction. A thigh cuff or full-contact thigh shell carries medial and lateral uprights to the knee joint; its length determines rotational control. The ankle-foot section is usually a solid ankle or locked in dorsiflexion and may include adjustable ankle joints, with a stirrup connecting to the shoe or a moulded foot section.
The knee joint can be:
- Locked knee - maximum stability, swing-through gait
- Drop-lock - unlocked manually for sitting, locks automatically
- Offset knee joint - provides hyperextension stability
- Polycentric knee - more anatomical motion
- Stance-control (SCKAFO) - locks in stance, free in swing
The stance-control KAFO. The knee joint locks automatically during stance and unlocks during swing to allow normal knee flexion, combining stability with a more natural gait pattern. The lock is triggered by weight (it extends with axial load), by ankle motion (ankle dorsiflexion triggers the knee lock), or electronically, by sensors that detect the gait phase.
What it gains over a locked KAFO. Gait pattern improves with knee flexion in swing, walking velocity increases (consistently demonstrated), stair climbing and sitting are easier, and cosmesis and patient acceptance improve. A reduction in energy cost is the claim that does not hold up consistently; see the metabolic energy cost section below.
Spinal Orthoses
Collars. A cervical orthosis (collar) spans C1-C7 and gives limited control.
Soft collar. A foam collar with minimal motion restriction, acting as a proprioceptive reminder and giving comfort and warmth. It is used for whiplash, minor strain and psychological support. It does not immobilise, and must not be used for unstable injuries.
Rigid collar (Philadelphia, Aspen, Miami J). A two-piece rigid plastic collar, anterior and posterior, for stable cervical fractures, post-operative care and transport. It does not adequately immobilise C0-C2 or C7-T1.
Cervicothoracic orthosis (CTO). A collar with a thoracic extension (sternal and posterior plates), which improves control of the lower cervical spine, C5-T1. It is used for lower cervical fractures and after fusion; the SOMI brace and the Minerva orthosis are examples.
Halo vest. A ring fixed to the skull with 4 pins and connected to a vest. It is the most restrictive cervical orthosis available, restricting greater than 90% of cervical motion and giving the best cervical control, C0-C7; the upper cervical spine requires a halo. Indications are unstable cervical fractures, C1-C2 injuries and protection after odontoid fixation. Complications include pin-site infection (20%), pin loosening and respiratory compromise.
- Flex/Ext
- 5-10%
- Lateral Bend
- 5%
- Rotation
- 5%
- Flex/Ext
- 70-80%
- Lateral Bend
- 50%
- Rotation
- 50%
- Flex/Ext
- 80-90%
- Lateral Bend
- 60%
- Rotation
- 60%
- Flex/Ext
- greater than 95%
- Lateral Bend
- greater than 95%
- Rotation
- greater than 95%

Differential Selection: Matching the Device to the Problem
A frequent exam trap is prescribing the wrong device for a presentation that "looks like foot drop" or "looks like a crouch". The table contrasts presentations that are easily confused and the discriminating feature that drives device choice.
- Key discriminator
- Swing-phase only deficit, normal push-off
- Correct device
- Hinged AFO / posterior leaf spring
- Common wrong choice
- Solid AFO (loses push-off)
- Key discriminator
- Stance-phase equinus thrust, high tone (MAS 3-4)
- Correct device
- Solid AFO
- Common wrong choice
- Hinged AFO (hinge is overpowered)
- Key discriminator
- Excess knee flexion in stance, GRF posterior to knee
- Correct device
- Ground-reaction / floor-reaction AFO
- Common wrong choice
- Hinged AFO (allows DF, worsens crouch)
- Key discriminator
- Correctable deformity, normal ankle dorsiflexors
- Correct device
- UCBL or SMO
- Common wrong choice
- Solid AFO (over-treats, blocks ankle)
- Key discriminator
- No posterior tension-band injury, no deficit
- Correct device
- TLSO or early mobilisation
- Common wrong choice
- Jewett brace (flexion control only)
- Key discriminator
- Disruption above C2, poorly controlled by collars
- Correct device
- Halo vest or surgical fixation
- Common wrong choice
- Rigid collar (inadequate immobilisation)
Clinical Relevance: Condition-Specific Prescriptions
Neurological Conditions
Stroke (hemiplegia). In the flaccid phase a hinged AFO prevents foot drop and allows dorsiflexion. In the spastic phase a solid AFO is used if there is equinus and a hinged one if spasticity is mild, with tone-reducing features such as a contoured footplate considered. In the upper limb, a resting hand splint prevents contracture.
Cerebral palsy. Spastic diplegia with crouch gait takes a ground-reaction AFO, and spastic hemiplegia a solid or hinged AFO depending on tone. For equinus use a solid AFO, considering serial casting first. A KAFO is rarely tolerated (high energy cost, poor acceptance).
Poliomyelitis and post-polio syndrome. The weakness is flaccid. An AFO is prescribed if the ankle dorsiflexors are weak and a KAFO, locked or stance-control, if the quadriceps are weak; lightweight materials are preferred.
Spinal cord injury. In complete paraplegia a reciprocating gait orthosis (RGO) provides therapeutic standing and walking. In an incomplete injury, an AFO or KAFO is chosen by muscle power.
Fractures
Tibial shaft fracture. A PTB cast or PTB AFO allows protected weight-bearing, followed by a functional (Sarmiento) brace after initial healing, which allows knee and ankle motion while protecting the tibia.
Ankle fracture after fixation. A CAM (controlled ankle motion) walker boot allows protected weight-bearing and is removable for wound care and physiotherapy.
Thoracolumbar fracture. A TLSO for stable burst or compression fractures, typically for 8-12 weeks, custom-moulded for unstable patterns.
Cervical fracture. A halo vest for unstable C1-C2 injuries, worn for 8-12 weeks; a rigid collar for stable subaxial injuries.
Paediatric Conditions
Developmental dysplasia of the hip. The Pavlik harness (0-6 months) holds the hips in flexion and abduction, and an abduction orthosis after the Pavlik maintains hip position.
Clubfoot after correction. Denis Browne boots and bar (Ponseti protocol), the boots set in external rotation and dorsiflexion, maintain the correction achieved by casting. They are worn 23 hours a day for 3 months, then at night.
Blount disease. A KAFO with a valgus force at the knee has a theoretical benefit in infantile Blount (under 3 years), with limited evidence for efficacy.
Orthosis-Tissue Interface: Pressure Tolerance and Skin Protection
Pressure is the limit. Every corrective force an orthosis applies must ultimately be transmitted through skin and soft tissue. Because pressure equals force divided by area, the single most important protective principle is to spread each force over the largest tolerant surface possible and to keep it off bony prominences.
Why skin fails. Sustained interface pressure that exceeds the skin's capillary perfusion pressure (classically around 32 mmHg at the arteriolar end, the Landis value) causes local ischaemia, and if unrelieved this progresses to a pressure ulcer. Skin tolerance is the rate-limiting constraint on how much correction a device can safely deliver.
The prominences to relieve or offload:
- Ankle-foot orthoses - medial and lateral malleoli, tibial crest, navicular tuberosity, base of the fifth metatarsal, and the fibular neck, where a poorly contoured proximal trimline or KAFO upright can compress the common peroneal nerve and cause an iatrogenic foot drop
- KAFOs - femoral condyles, patella and the proximal thigh cuff
- Spinal orthoses - iliac crests, anterior superior iliac spines, sternum and pubis (the Jewett three-point pads), and the sacrum
Total contact. Total-contact fitting deliberately maximises contact area so that no single point carries a disproportionate load, the same principle that underlies the total-contact cast for the neuropathic foot. Shear and friction compound direct pressure, so a device that pistons or migrates is as dangerous as one that is too tight.
Insensate skin. This is the danger case. Patients with diabetic neuropathy, spinal cord injury or spina bifida cannot feel a developing sore, so relief must be engineered into the device and reviewed by inspection, not by symptoms.
The skin check on removal. Blanchable erythema that fades within a few minutes is acceptable. Non-blanching erythema persisting beyond 20 to 30 minutes signals excessive local pressure and mandates modification before further wear.
Q: A patient returns two weeks after a new solid AFO with a fixed red mark over the lateral malleolus that does not fade. What does this mean and what do you do? A: An impending pressure ulcer. Stop wearing the device, inspect for skin breakdown, and return it to the orthotist for relief/padding or re-moulding over the malleolus. Re-examine the fit, the trimlines and any pistoning.
Metabolic Energy Cost of Braced Gait
Why it matters. A biomechanically perfect orthosis is useless if the patient will not wear it, and the commonest reason a technically sound brace is abandoned is that walking in it costs too much energy. Energy cost is therefore a core prescription principle.
What drives the cost. The more proximal and the more locked the device, the higher the demand. A locked-knee KAFO forces energy-expensive compensations, hip-hitching, circumduction and vaulting, to clear a stiff limb in swing. Reciprocating gait orthoses and bilateral KAFOs for thoracic-level paraplegia impose an energy cost so high that most adult users ultimately choose a wheelchair for community distances.
Weight. Every gram matters, so carbon fibre and aluminium are favoured where weight, not durability, is the limiting factor.
Measuring it. The Physiological Cost Index (PCI), walking heart rate minus resting heart rate divided by walking speed, is the common clinic surrogate for oxygen cost when formal calorimetry is unavailable.
The stance-control paradox. Stance-control KAFOs reliably increase walking velocity by allowing free knee flexion in swing, yet do not consistently reduce the metabolic cost or PCI of walking compared with a locked KAFO (Davis 2010). Their defensible benefits are faster, more natural gait and easier sitting and stair use, not a guaranteed energy saving.
Prescribing within reserve. A device should be prescribed only when the resulting gait cost falls within the patient's cardiopulmonary reserve. Otherwise a lighter device, a less restrictive joint or a wheeled alternative is the honest recommendation.
Q: A young adult with thoracic-level paraplegia has well-fitted KAFOs but uses a wheelchair for everything except therapy. Has the orthosis failed? A: Not biomechanically - it provides the standing stability it was designed for. It has failed the energy-cost test: braced ambulation at this level carries a very high metabolic demand, so the wheelchair is the rational choice for community mobility, while the KAFOs retain value for therapeutic standing (bone loading, pressure relief, psychological and physiological benefits). Recognising energy cost as a legitimate prescription endpoint, and choosing the lightest adequate device, is the mature answer.
Guidelines, Registries & Global Practice
Global Epidemiology of Orthotic Need
The major drivers of orthotic demand are common worldwide: stroke (around 12 million new strokes/year, the leading cause of acquired adult foot drop), cerebral palsy (roughly 2 per 1,000 live births, the most common cause of childhood physical disability), diabetic neuropathy and Charcot foot (rising with the global diabetes burden), adolescent idiopathic scoliosis (around 2-3% of adolescents, around 10% of whom need treatment), and osteoporotic and traumatic spinal fractures. Need outstrips supply: the WHO estimates only around 1 in 10 people who need assistive products, including orthoses, currently have access, with the largest gaps in low- and middle-income countries.
Side-by-Side Guidance
- Domain
- AIS bracing
- Key position
- Brace skeletally immature curves around 25-40 degrees (Risser low); target wear time and in-brace correction drive success
- Domain
- Paediatric / CP orthotics
- Key position
- AFO selection matched to gait deviation; bracing as part of multilevel CP management
- Domain
- Stroke rehab, spinal trauma
- Key position
- Offer AFO for persistent foot drop affecting gait; mobilize stable thoracolumbar fractures, brace selectively
- Domain
- Thoracolumbar fractures
- Key position
- Stable AO-A injuries (intact PLC, no deficit) suit non-operative care; bracing optional given equivalence data
- Domain
- Fracture orthotics
- Key position
- Functional bracing principles (Sarmiento) for selected diaphyseal fractures
A recurring theme is convergence on biomechanics with divergence on whether to brace at all for stable spinal injuries, reflecting the Bailey equivalence data.
Standards and Registry Notes
- Orthosis nomenclature follows ISO 8549; device terminology and classification follow ISO 22523. These are the global reference standards regardless of country.
- Most orthoses are regulated as low-risk (Class I) medical devices by national regulators (e.g. FDA in the US, MHRA/UKCA in the UK, CE marking in the EU, TGA in Australia).
- Unlike arthroplasty, orthoses have no large international outcome registry; the evidence base rests on RCTs (BrAIST, Bailey) and gait-laboratory studies rather than registry survival data.
High- versus Limited-Resource Practice
- High-resource settings: custom thermoplastic and carbon-fibre devices, instrumented 3D gait analysis to guide AFO/GRAFO prescription, certified orthotists embedded in MDT clinics, and 3D-printed custom orthoses emerging.
- Limited-resource settings: reliance on prefabricated or locally fabricated devices, limited orthotist availability, and greater use of early mobilization without bracing - directly supported by the Bailey trial showing equivalence of "no orthosis" for stable burst fractures. WHO's GATE initiative promotes a priority assistive products list to widen access.
Related pages: Foot and Ankle Orthotics, Bracing and AFOs for the foot-specific prescribing detail and accommodative-versus-functional orthosis selection; Adolescent Idiopathic Scoliosis for the disease behind the BrAIST evidence and the curve thresholds that trigger bracing; Thoracolumbar Fractures and Burst Fractures for the injuries the Bailey equivalence trial addresses and, importantly, the unstable patterns it excludes; Cerebral Palsy and Cerebral Palsy Gait and SEMLS for crouch gait and where a ground-reaction AFO sits against surgery; Spinal Cord Injury for the energy-cost argument that decides KAFO against wheelchair; Diabetic Foot for offloading and the insensate foot at the orthosis interface; and Prosthetic Limb Components for the amputation side of the same biomechanics.
Controversies & Areas of Uncertainty
Do stable burst fractures need a brace at all? The Bailey RCT showed a TLSO to be equivalent to no orthosis for neurologically intact AO-A3 fractures with an intact PLC. Many surgeons still brace for comfort or where PLC integrity is uncertain. The genuine uncertainty is patient selection, not the biomechanics.
How much does AFO type matter in stroke? The meta-analyses disagree. A broad analysis (Choo 2021) shows clear gains in speed and ambulation, while an RCT-only analysis (Shahabi 2019) found low-quality, non-significant effects on walking speed, and the optimal AFO type for a given patient remains unresolved.
Floor-reaction AFOs for crouch: who responds? Effectiveness is debated. Only around half of children respond, and gait-analysis-guided selection (slow gait, weak plantarflexors) improves the yield; in Bohm's series joint contractures were not a contraindication, which is worth setting against the fixed knee flexion limit in the ground-reaction AFO contraindications above. Whether GRAFOs delay rather than prevent surgery is unsettled.
Lumbar supports for low back pain. Evidence for an LSO or corset in non-specific chronic low back pain is weak, and any benefit is likely proprioceptive and short-term. Concern about disuse atrophy with prolonged wear persists but is not well quantified.
The halo in the elderly. Once the gold standard for the unstable cervical spine, the halo carries significant morbidity in older patients (pin-site infection, respiratory and swallowing complications), shifting practice towards early surgical stabilisation in many centres.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 65-year-old man is 3 months post-stroke with left hemiplegia. He has MRC grade 2 ankle dorsiflexors, grade 3 plantarflexors, and mild ankle spasticity (Modified Ashworth Scale 1+). He is currently walking with a quad cane and foot drop. What orthosis would you prescribe and why?”
“A 55-year-old woman fell from a ladder and sustained an L1 burst fracture. CT shows 40% anterior height loss, 25% canal compromise, intact posterior ligamentous complex (no widening of interspinous distance), and she is neurologically intact. The spine surgeon has decided on conservative management. What orthosis would you prescribe?”
“A 10-year-old boy with spastic diplegic cerebral palsy (GMFCS Level II) presents with progressive crouch gait over the past year. Examination shows bilateral knee flexion of 25 degrees in stance, ankle dorsiflexion to 15 degrees with knee extended, hip extension to neutral, and hamstring tightness (popliteal angle 45 degrees). He currently wears hinged AFOs. How would you approach his orthotic management?”
Nomenclature
- AFO = Ankle-Foot Orthosis
- KAFO = Knee-Ankle-Foot Orthosis
- TLSO = Thoracolumbosacral Orthosis
- Named by joints crossed (ISO 8549)
Functions
- Control - limit unwanted motion
- Correct - apply corrective forces
- Compensate - replace muscle function
- Protect - allow healing
AFO Selection
- Solid AFO = spastic equinus
- Hinged AFO = foot drop, intact PF
- Ground-reaction = crouch gait
- FRAFO = floor reaction, extends knee
Spinal Levels
- TLSO controls T9-L3 effectively
- Above T9 needs CTLSO (sternal)
- Below L3 needs thigh extension
- Halo vest for C0-C7 (best cervical)
Biomechanics
- Three-point pressure = all correction
- Longer lever arm = greater control
- GRAFO moves GRF anterior to knee
- Force distribution prevents ulcers
Prescription Must Include
- Diagnosis and functional goal
- Joints to control
- Motion to allow/block
- Material and footwear requirements
Evidence Base
BrAIST Trial - Bracing for Adolescent Idiopathic Scoliosis
- Multicentre trial (randomized + preference cohorts, 242 patients analysed) in high-risk AIS
- Treatment success (skeletal maturity without curve reaching 50 degrees): 72% bracing vs 48% observation overall
- Intention-to-treat in randomized cohort: 75% success bracing vs 42% observation (OR 4.11)
- Significant dose-response between hours of brace wear and success (P less than 0.001)
- Trial stopped early for efficacy of bracing
AFO Effectiveness in Stroke - Meta-analysis
- Meta-analysis of 19 studies (434 participants) of AFO use in stroke gait
- AFO improved walking speed (SMD 0.50, 95% CI 0.34-0.66)
- Improved cadence, step length and stride length
- Largest effect on Functional Ambulation Category score (SMD 1.61)
- Improved ankle angle at initial contact; body sway not significantly changed
TLSO versus No Orthosis for Thoracolumbar Burst Fractures (RCT)
- Multicentre randomized equivalence trial, AO Type A3 burst fractures T11-L3, neurologically intact, kyphosis under 35 degrees
- TLSO (n=47) versus no orthosis with early ambulation (n=49)
- Roland-Morris Disability score at 3 months: 6.8 (TLSO) vs 7.7 (no orthosis)
- 95% CI (-1.5 to 3.2) fell within the predefined equivalence margin
- Six patients required later surgical stabilization (similar between groups)