Low Bone Mass | Fragility Fractures | DEXA Diagnosis
- T-score at or below -2.5 diagnoses osteoporosis only in populations for whom T-scores are appropriate; use Z-scores and clinical context in younger adults
- Hip or vertebral fragility fracture usually warrants treatment assessment regardless of BMD; not every low-energy fracture proves osteoporosis
- Choose therapy by fracture risk, renal function, comorbidity, route, adherence and prior treatment rather than one universal first-line drug
- Denosumab requires a planned antiresorptive transition when delayed or stopped to limit rebound bone loss and multiple vertebral fractures
- Anabolic-first then antiresorptive is considered for very high risk, while lower-risk patients may start an antiresorptive
- “Interpret DXA site, artefact and population before applying a T-score
- “Investigate secondary causes and mimics before prescribing
- “FRAX intervention thresholds are country- and guideline-specific
- “Hip-fracture mortality and loss of independence vary by population and care system
Overview and Epidemiology
Osteoporosis is a systemic skeletal disease characterised by low bone mass and microarchitectural deterioration, leading to increased bone fragility. It is the most common metabolic bone disease, and it is under-diagnosed and under-treated.
Who and how many. About 200 million people are affected globally, and there are 1.5 million fragility fractures a year in the US. Women are affected more than men because of postmenopausal oestrogen loss.
Where it breaks. The vertebra is the most common fracture site and the hip the most morbid. Second-fracture risk is 20% within 1 year, and the healthcare cost is enormous.
Fragility fracture needs context. Hip and vertebral fragility fractures usually identify high treatment risk. Distal radius, proximal humerus and other low-energy fractures trigger bone-health assessment but do not make every patient osteoporotic by definition.
Every orthopaedic surgeon must screen, investigate and treat. Prevention and treatment save lives.
Pathophysiology and Bone Anatomy
Remodelling. Bone is constantly remodelled by osteoclasts, which resorb it, and osteoblasts, which form it, in a cycle of 3-6 months: resorption, then formation. Osteoporosis results from an imbalance favouring resorption. Peak bone mass is achieved by age 30, and after this net bone loss begins.
Cortical and trabecular bone. Cortical bone is the dense outer layer, 80% of the skeleton, with slow turnover. Trabecular bone is the spongy interior, the remaining 20%, with rapid turnover.
Why the balance tips. Three routes lead to the same imbalance:
- Oestrogen deficiency after the menopause increases osteoclast activity
- Age reduces osteoblast function
- Secondary causes, listed below
Secondary causes. Check for them in all young patients or in severe disease.
- Glucocorticoids
- Hyperthyroidism and hyperparathyroidism
- Alcohol, and aromatase inhibitors
- Low body weight (BMI less than 19)
- Male hypogonadism (testosterone deficiency)
- Early menopause, before 45
- Renal and gastrointestinal disease: CKD, malabsorption
- Rheumatoid and other inflammatory arthritis
- Type 1 diabetes, although BMD may be normal
Classification Systems
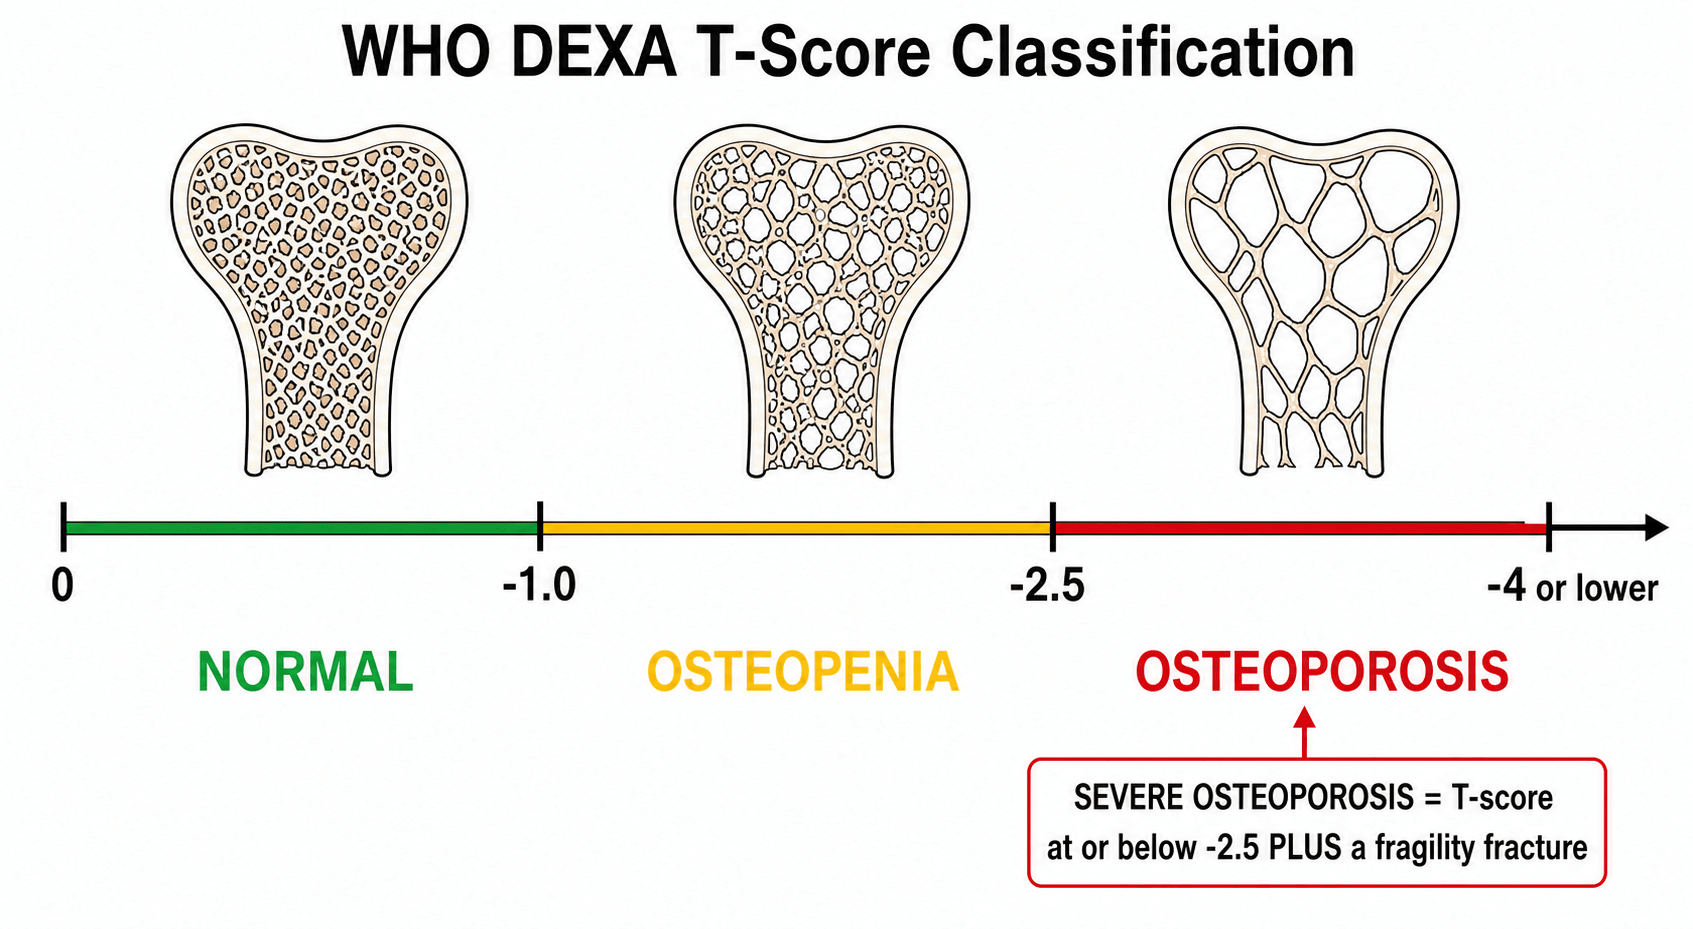
The T-score compares the patient's BMD with the young adult (20-30 years) mean. The WHO categories built on it apply to postmenopausal women and men aged 50 years or older; younger adults are read by the age-matched Z-score.
WHO DEXA Classification
- T-Score
- At or above -1.0
- Interpretation
- Normal bone density
- Action
- Lifestyle measures, rescreen 5-10 years
- T-Score
- -1.0 to -2.5
- Interpretation
- Low bone mass
- Action
- Calculate FRAX, treat if high risk
- T-Score
- At or below -2.5
- Interpretation
- Osteoporosis
- Action
- Pharmacotherapy indicated
- T-Score
- At or below -2.5 + fracture
- Interpretation
- Established osteoporosis
- Action
- Consider anabolic therapy first
Clinical Assessment
History. A prior fracture is the strongest risk factor. Ask about hip fracture in a parent, smoking, alcohol and low calcium intake, early menopause, and thyroid, parathyroid or rheumatoid disease. The drug history includes steroids, aromatase inhibitors and PPIs. A comprehensive history is what identifies the high-risk patient.
Examination. Examine for vertebral fractures and for fall risk.
- Measure height, and look for thoracic kyphosis (dowager's hump), quantified by the wall-occiput distance
- A reduced rib-pelvis distance points to vertebral fractures
- Romberg's test assesses balance for fall risk
- The Timed Up and Go test assesses functional mobility
Only 30% of vertebral fractures are clinically apparent. Height loss greater than 2cm suggests vertebral fracture; that or new kyphosis should prompt vertebral imaging (lateral spine X-ray or VFA on DEXA).
Investigations
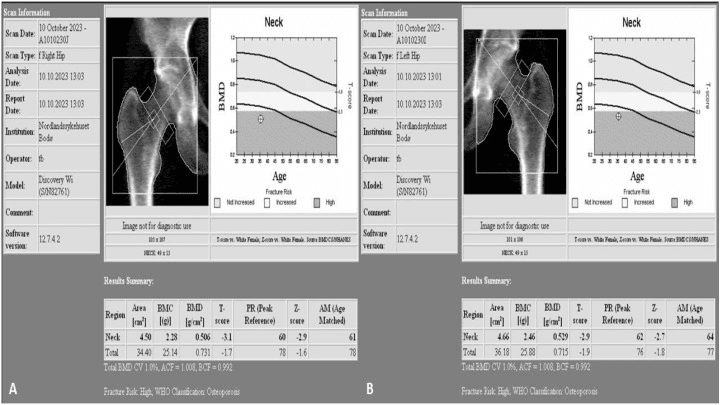
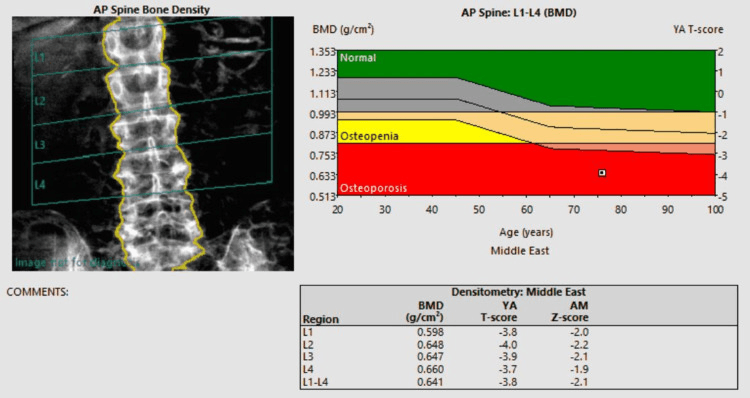
DEXA. DEXA is the gold standard for diagnosis. Measure the femoral neck and the lumbar spine and use the lowest T-score; the femoral neck is preferred for treatment decisions.
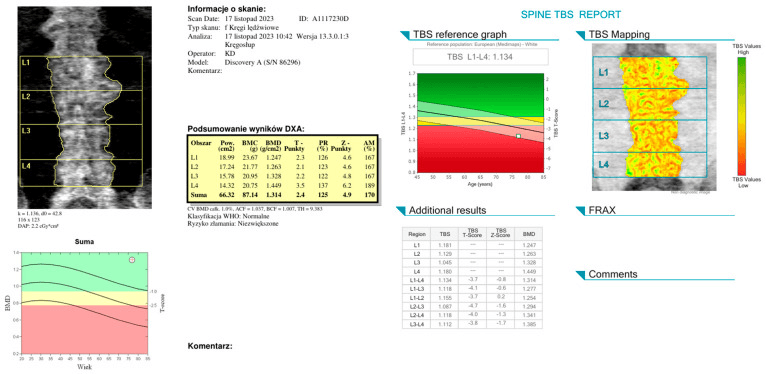
Reading the report. A DXA report needs clinical interpretation. Degenerative artefact may elevate lumbar BMD, while the trabecular bone score (TBS) can show degraded texture in the same spine.
Bloods. The aim is to exclude secondary causes: calcium, phosphate, vitamin D, PTH, renal function, thyroid function, FBC and LFTs. Consider testosterone in men and coeliac serology.
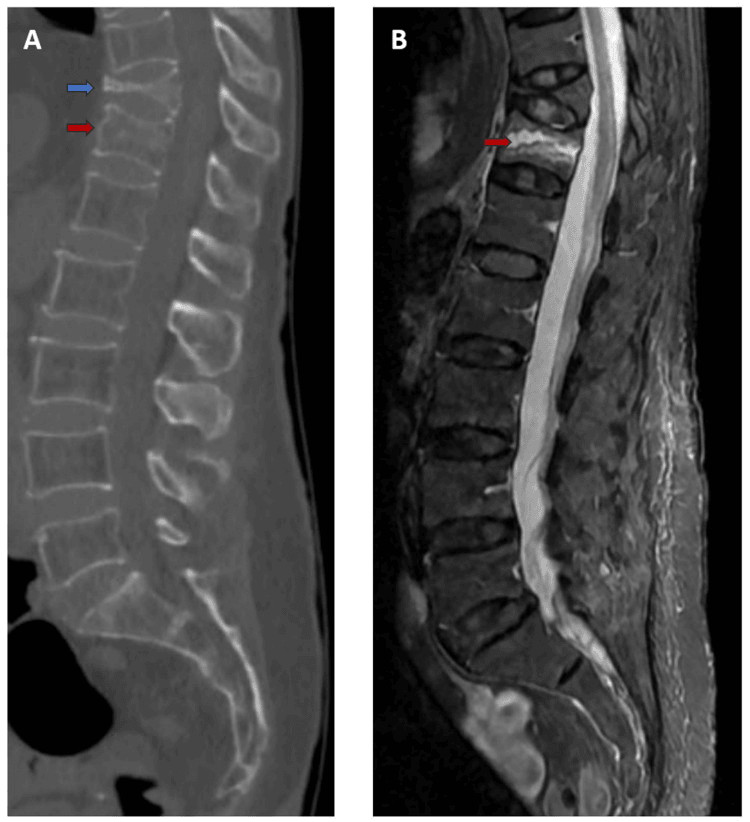
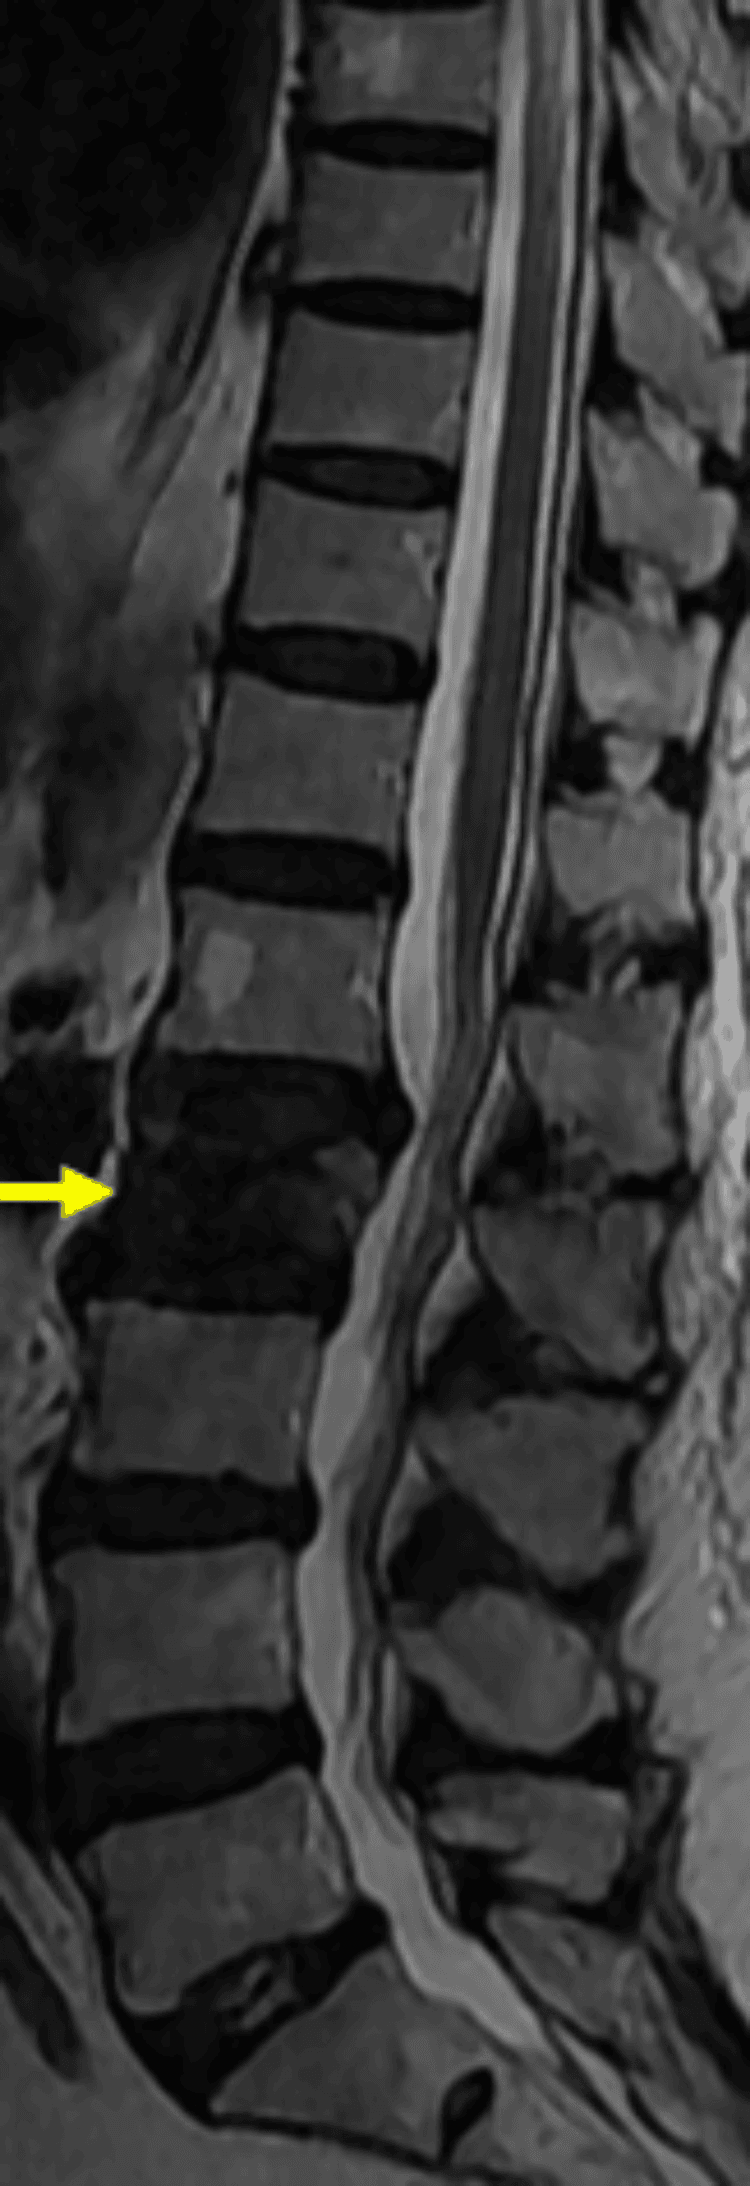
Vertebral imaging. A lateral spine X-ray or VFA identifies prevalent vertebral fractures once height loss or kyphosis has raised the question. On MRI, marrow signal separates an acute fracture from a chronic one.
Understanding FRAX: Inputs and Limitations
FRAX computes the 10-year probability of a major osteoporotic fracture and of a hip fracture from clinical risk factors, with femoral-neck BMD optional, so it works without DEXA. It is one component of decision-making, not a diagnosis or a universal treatment threshold.
Thresholds are national. Intervention thresholds vary by national model, age and guideline, so apply the threshold from the relevant country model and guideline. The 3%/20% thresholds are US thresholds, not universal constants.
Its clinical inputs.
- Note
- Core demographics
- Note
- One of the strongest factors
- Note
- Family history
- Note
- Yes/no
- Note
- Yes/no (current or recent)
- Note
- A validated secondary cause
- Note
- e.g. type 1 diabetes, hypogonadism, malabsorption
- Note
- Yes/no
- Note
- Improves accuracy; omitted if no DEXA
What FRAX cannot see. Almost every input is yes/no, so FRAX is blind to dose and severity and can under-estimate risk. When any of these blind spots applies, clinical judgement must override a reassuring FRAX:
- Glucocorticoid dose: high-dose steroids are under-weighted, so adjust upward
- The number, recency and site of prior fractures: a recent or vertebral fracture confers very high imminent (near-term) risk that FRAX flattens
- Falls, the dominant driver of hip fracture in the very old
- Lumbar-spine BMD: FRAX uses femoral-neck BMD only, and discordant low spine BMD can be added with TBS
- Treatment: FRAX is not validated in patients already on treatment
Differential Diagnosis of Low Bone Mass / Fragility Fracture
Low BMD or an apparent fragility fracture is not always primary osteoporosis. The mimics change management entirely, so distinguish them before prescribing.
- Key discriminator
- Low BMD, normal biochemistry, fragility fracture
- Calcium / Phosphate / ALP
- Normal Ca, PO4, ALP
- Action
- Antiresorptive or anabolic
- Key discriminator
- Bone pain, proximal myopathy, Looser zones
- Calcium / Phosphate / ALP
- Low/normal Ca, low PO4, high ALP, low vitamin D
- Action
- Correct vitamin D / phosphate first
- Key discriminator
- Cortical (forearm) bone loss, stones, fatigue
- Calcium / Phosphate / ALP
- High Ca, low PO4, high PTH
- Action
- Treat parathyroid disease
- Key discriminator
- Lytic lesions, pathological fracture, weight loss
- Calcium / Phosphate / ALP
- High Ca, high ALP if blastic, raised ESR/paraprotein
- Action
- Biopsy / oncology workup
- Key discriminator
- Bone deformity/expansion, isolated high ALP
- Calcium / Phosphate / ALP
- Normal Ca/PO4, markedly high ALP
- Action
- Bisphosphonate for active disease
- Key discriminator
- Young patient, blue sclerae, family history
- Calcium / Phosphate / ALP
- Normal biochemistry
- Action
- Genetic / specialist; bisphosphonates
Before labelling low BMD as osteoporosis, check biochemistry. A high ALP, low phosphate or high calcium should redirect the workup. An unexpected pathological fracture in a patient with weight loss demands exclusion of myeloma and metastasis.
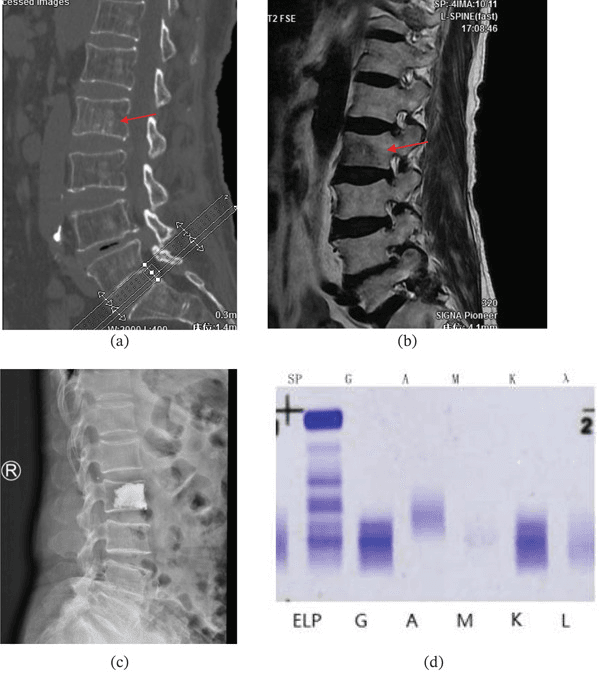
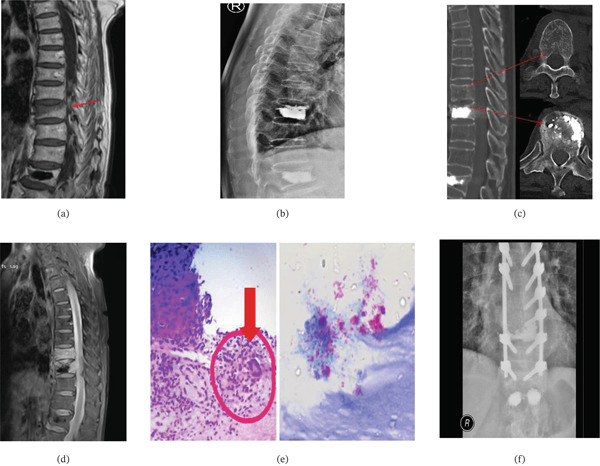
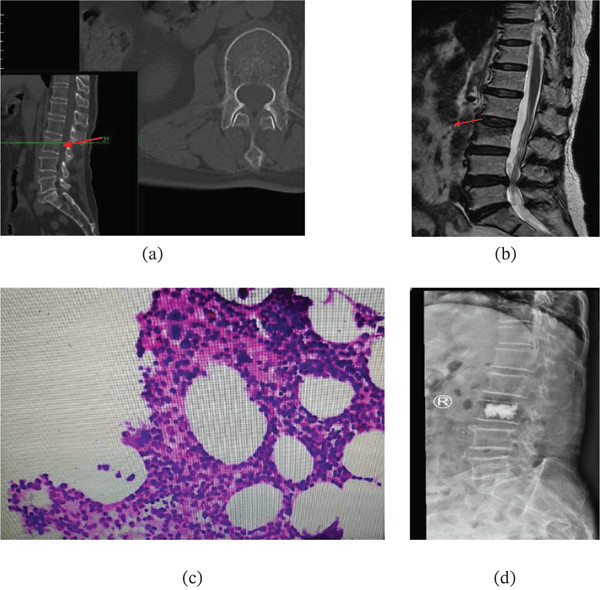
Vertebral mimics. Myeloma, tuberculous spondylitis and pyogenic spondylitis can each look at first like an osteoporotic compression fracture. What gives them away is the laboratory result, the pathology or a course that does not behave.
Management Algorithm
Lifestyle, for every patient. Lifestyle measures are the foundation for all patients.
- Calcium 1000-1200mg/day and vitamin D 800-2000 IU/day, from food where possible and supplemented if intake is inadequate. Correct deficiency without automatic megadosing.
- Regular weight-bearing and resistance exercise (walking, dancing, strength training) improves BMD and reduces falls.
- A fall prevention programme: home hazard assessment, vision check, medication review and balance training.
- Stop smoking, limit alcohol to less than 2 drinks a day and maintain a healthy body weight.
Choosing a drug. There is no one universal first-line drug. Bisphosphonates are common first antiresorptives when risk, renal function, gastrointestinal tolerance, adherence and route make them suitable; very-high-risk patients may benefit from anabolic-first sequencing, set out in the next section.
- Examples
- Alendronate, zoledronic acid
- Mechanism
- Inhibit osteoclasts
- Duration
- 5 years oral, 3 years IV
- Key Points
- Common first antiresorptive when suitable
- Examples
- Denosumab
- Mechanism
- Block osteoclast formation
- Duration
- Indefinite or transition
- Key Points
- Cannot stop abruptly; needs an exit plan
- Examples
- Teriparatide
- Mechanism
- Anabolic (stimulates osteoblasts)
- Duration
- 2 years maximum
- Key Points
- Severe disease; follow with antiresorptive
- Examples
- Romosozumab
- Mechanism
- Most potent anabolic
- Duration
- 1 year maximum
- Key Points
- Follow with antiresorptive; cardiovascular risk
Denosumab needs an exit plan. Do not delay or stop denosumab without arranging sequential antiresorptive therapy. The FREEDOM extension data in the evidence section are more specific than the word "rebound": turnover markers rise above baseline, BMD falls back to baseline and the vertebral fracture rate returns to the untreated rate. What is peculiar to denosumab is that the fractures which follow tend to be multiple, concentrated in susceptible patients, especially those with a prior vertebral fracture.
Drug holidays. A holiday may be considered after 3-5 years of bisphosphonate if the patient is stable. Denosumab and the anabolics have no holiday concept.
- T-score
- BMD and clinical risk reassuring
- Treatment
- Exercise, nutrition and fall-risk measures
- Key Action
- Repeat testing only when it will change care
- T-score
- -1.0 to -2.5 where T-score applies
- Treatment
- Country-specific absolute-risk assessment
- Key Action
- Treat according to risk and guideline
- T-score
- At or below -2.5 where applicable
- Treatment
- Risk-stratified antiresorptive or anabolic sequence
- Key Action
- Exclude secondary causes and plan duration
- T-score
- Any BMD
- Treatment
- Prompt secondary-prevention assessment
- Key Action
- Hip/vertebral fracture usually high risk; classify other sites carefully
Treatment Sequencing: Why Anabolic-First
The order in which drugs are given is one of the most important modern concepts, and the basis of the ARCH trial and of the ESCEO/AACE "very high risk" pathway.
Two classes, opposite actions. Anabolics, teriparatide (PTH 1-34) and romosozumab (anti-sclerostin), build new bone. Their effect is front-loaded and wanes over roughly 12-24 months, the so-called anabolic window; romosozumab is dual-action, increasing formation and decreasing resorption at the same time. Antiresorptives, bisphosphonates and denosumab, preserve bone by suppressing osteoclasts.
Why anabolic first, then antiresorptive.
- Building bone first and then giving an antiresorptive consolidates ("locks in") the newly formed bone, producing larger, more durable BMD and strength gains.
- A potent antiresorptive given first blunts the later anabolic response: teriparatide works less well, and more slowly, after a bisphosphonate or denosumab has suppressed the remodelling it acts on.
- Anabolic gains are lost if not followed by an antiresorptive. As with denosumab, an anabolic course must always be consolidated with a bisphosphonate or denosumab.
The trial. ARCH showed exactly this: romosozumab-then-alendronate beat alendronate-throughout for fracture reduction in high-risk women.
Surgical Technique
Osteoporotic bone requires modified fixation strategies.
Fixation principles.
- Longer plates spread load over more screws
- Locking plates give angular stability and reduce toggle
- Use multiple points of fixation, with more screws if needed
- Consider cement augmentation for poor bone
- Avoid cortical stress risers by keeping transitions smooth
- Protect the fracture: early motion, but protected weight-bearing
Screw augmentation. PMMA cement placed around screws increases pullout strength 2-3x and is useful in spine and periarticular fractures.
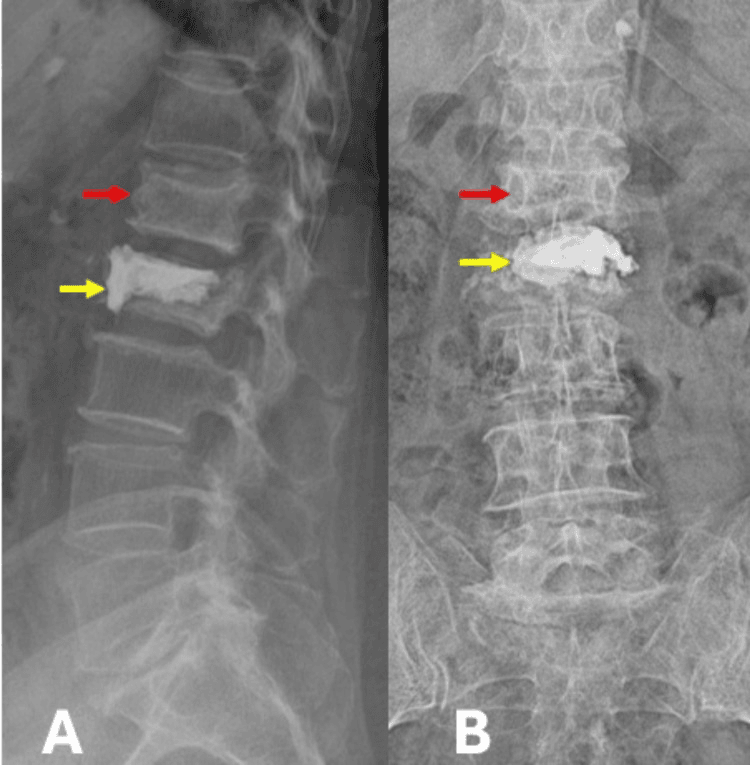
Vertebroplasty and kyphoplasty. Both inject cement into the vertebral body of a painful vertebral compression fracture; kyphoplasty restores some height.
Complications
- Risk
- 1 in 10000 to 1 in 100000
- Management
- Dental check before starting. Stop if surgery.
- Risk
- Less than 1 in 1000 per year
- Management
- Monitor for thigh pain. Drug holiday after 5 years.
- Risk
- 10-20%
- Management
- Take fasting with water. Consider IV.
- Risk
- Severe if stopped
- Management
- NEVER stop abruptly. Transition to bisphosphonate.
- Risk
- Signal in ARCH trial
- Management
- Regulators advise avoiding within 12 months of MI or stroke.
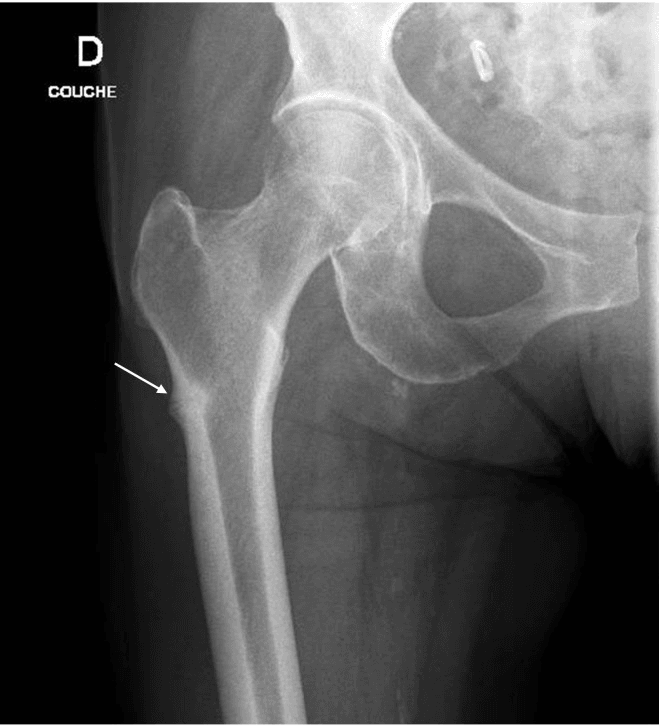
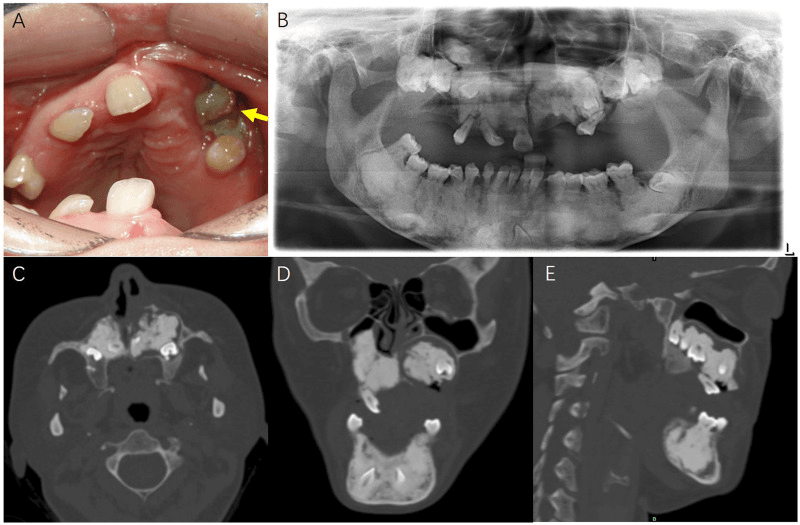
Rare but serious. ONJ and atypical femoral fractures are rare but serious, and for patients with osteoporosis the benefits of treatment far outweigh the risks. Lateral-cortical thickening and a transverse lucent line are the characteristic warning findings of an atypical femoral fracture.
Postoperative Care
Post-Fracture Osteoporosis Management
Treat the fracture appropriately, with fixation adequate for osteoporotic bone.
DEXA if not done, laboratory workup for secondary causes, and referral to the FLS if available.
Start a bisphosphonate or an anabolic, with adequate calcium and vitamin D. Zoledronic acid can be given 2 weeks post-fracture.
Monitor DEXA at 2-3 years, assess for new fractures, and consider modifying treatment if the patient is not responding.
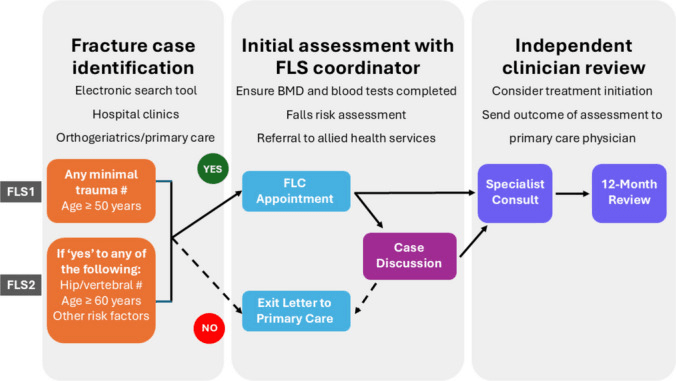
Fracture Liaison Service. The FLS is the evidence-based model for making sure eligible fragility-fracture patients are investigated and treated. FLS programmes improve case finding, investigation and treatment initiation, but referral does not mean every fracture patient receives the same drug.
Outcomes and Prognosis
Fracture risk reduction. The reductions quoted for each class:
- Bisphosphonates: 40-50% for hip and vertebral fractures
- Denosumab: 40-70%
- Teriparatide: 65% vertebral, 50% non-vertebral
- Romosozumab: 70%+ vertebral
After hip fracture. These are the commonly quoted rates, though mortality and loss of independence vary by population and care system. Early treatment prevents second fractures and mortality.
- Rate
- 20%
- Rate
- 50%
- Rate
- 20%
- Rate
- 5-10%
Guidelines, Registries & Global Practice
Global Epidemiology:
- An estimated 500 million people worldwide have osteoporosis; roughly 1 in 3 women and 1 in 5 men over 50 will sustain a fragility fracture
- Lifetime hip-fracture risk approaches that of breast cancer in women; the global hip-fracture burden is projected to rise sharply with population ageing, with the largest increases in Asia
- Bone mineral density thresholds (T-score) are universal, but fracture incidence varies by region (higher in Northern Europe/Scandinavia, lower in parts of Africa and Asia), reflecting genetics, body habitus, vitamin D status and fall rates
Major Guidelines — Side by Side:
- Treatment threshold
- T-score at or below -2.5, prior hip/vertebral fracture, or high FRAX
- First-line
- Bisphosphonate; anabolic first if very high risk
- Notable position
- Risk-stratified ('very high risk') pathway favouring anabolic-first sequencing
- Treatment threshold
- FRAX-based intervention thresholds (age-dependent)
- First-line
- Oral bisphosphonate (alendronate/risedronate)
- Notable position
- FRAX integrated into thresholds; anabolic for very high risk
- Treatment threshold
- FRAX or QFracture above intervention threshold
- First-line
- Alendronate / risedronate
- Notable position
- Health-economic appraisal drives sequencing; romosozumab via technology appraisal
- Treatment threshold
- FRAX-based; 'very high risk' category
- First-line
- Bisphosphonate or anabolic by risk
- Notable position
- Champions anabolic-first then antiresorptive in very high risk
- Treatment threshold
- Fragility fracture = treat
- First-line
- Antiresorptive plus FLS pathway
- Notable position
- Surgeon-led case-finding and bone health after fracture
Across all major bodies the core message is consistent: a fragility fracture warrants treatment irrespective of BMD, FRAX (or QFracture) guides therapy in osteopenia, and bisphosphonates remain first-line for most, with anabolic-first sequencing reserved for very high risk.
- National hip-fracture registries/audits (UK National Hip Fracture Database, Australian and New Zealand Hip Fracture Registry, and similar programmes) consistently link timely surgery, orthogeriatric co-care and bone-health assessment to lower mortality and re-fracture
- Capture–the–Fracture (IOF) benchmarks FLS programmes internationally
- Well-resourced settings: DEXA, FRAX, FLS, and access to denosumab and anabolics (teriparatide, romosozumab) are standard
- Limited-resource settings: DEXA may be scarce — diagnosis relies on fragility-fracture history and clinical risk; generic oral/IV bisphosphonates and calcium/vitamin D form the backbone; FRAX can be used without BMD input
- Failure to investigate and treat after a fragility fracture is a recognised care gap and a medicolegal exposure worldwide
- Document the osteoporosis discussion and FLS/bone-health referral for every fragility-fracture patient
Related pages: DEXA and Bone Densitometry for how the T-score this page treats as a threshold is actually acquired and where it misleads; Bisphosphonates for the drug class in detail, including the holiday decision this page only summarises; Denosumab for the agent whose discontinuation behaviour is the single most examinable prescribing rule here; Atypical Femoral Fractures and Medication-Related Osteonecrosis of the Jaw for the two rare harms that drive the holiday decision; Osteomalacia for the mineralization defect that must be excluded before starting an antiresorptive, since bisphosphonates given to an osteomalacic patient worsen it; Vitamin D Deficiency for the repletion required before any antiresorptive; Glucocorticoid-Induced Osteoporosis for the commonest secondary cause, which is treated at a higher BMD threshold; Osteoclasts and Bone Resorption and Osteoblasts and Bone Formation for the RANKL and sclerostin biology every drug on this page targets; and Transient Osteoporosis of the Hip for the self-limiting mimic that must not be treated as this disease.
Controversies and Areas of Uncertainty
Anabolic-first versus antiresorptive-first. Trials (ARCH, and teriparatide-then-antiresorptive data) and ESCEO/AACE favour an anabolic-first sequence in very-high-risk patients. The threshold defining "very high risk", and cost, remain debated.
The denosumab exit. That protection is lost after stopping denosumab is established, but the best transition (timing of zoledronic acid, single versus repeated dosing, the role of bone-turnover markers) is not fully settled. Most guidance gives a bisphosphonate around 6 months after the last denosumab dose.
Drug holidays. A bisphosphonate holiday balances falling atypical-fracture risk against rising fracture risk. There is no validated tool to time resumption, so the decision rests on BMD, fracture history and clinical judgement.
Calcium and vitamin D supplements. Routine supplementation in community-dwelling, replete adults gives uncertain fracture benefit and a debated cardiovascular and renal-stone signal. Its value is clearest in deficient or institutionalised populations and as an adjunct to active drug therapy.
Osteopenia and the very elderly. FRAX-guided treatment of osteopenia is widely endorsed, yet the cost-effective threshold varies by country. Evidence in the very old and those with limited life expectancy is thinner, favouring agents with rapid benefit such as zoledronic acid.
Romosozumab's cardiovascular signal. The excess cardiovascular events against alendronate in ARCH, not seen against placebo in FRAME, remain incompletely explained, and the underlying mechanism is unresolved.
MCQ Practice Points
Q: What T-score defines osteoporosis? A: At or below -2.5. T-score -1.0 to -2.5 is osteopenia. At or above -1.0 is normal.
Q: What determines the first osteoporosis drug? A: Fracture-risk category, recent/multiple vertebral fractures, renal function, contraindications, route, adherence, prior therapy and patient preference. A bisphosphonate is common for suitable high-risk patients; very-high-risk patients may start an anabolic followed by antiresorptive consolidation.
Q: What is the risk of stopping denosumab abruptly? A: Rebound vertebral fractures. Rapid bone loss occurs. MUST transition to bisphosphonate.
Q: What is the prognosis after hip fracture? A: Mortality, loss of independence and second-fracture risk are substantial but vary by age, frailty, population and care system. Quote local audit data rather than one universal percentage.
Q: When should a bisphosphonate drug holiday be considered? A: After 5 years of oral or 3 years of IV therapy if not high-risk. Monitor for atypical fracture risk. Resume if new fracture.
Q: When should FRAX be used? A: In osteopenia (T-score -1.0 to -2.5) to determine treatment threshold. Treat if 10-year hip fracture risk at or above 3% or major osteoporotic fracture risk at or above 20%.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 75-year-old woman is in hospital following ORIF for intertrochanteric hip fracture from a simple fall. How do you manage her osteoporosis?”
“A 68-year-old woman has a DEXA showing T-score -2.1 at femoral neck and -2.8 at lumbar spine. She has no prior fractures. How do you interpret this and what is your management?”
“A patient on denosumab for 3 years wants to stop treatment. Her last injection was 7 months ago (1 month overdue). What are your concerns and management?”
Diagnosis
- DEXA T-score at or below -2.5 = osteoporosis
- Fragility fracture = clinical osteoporosis
- FRAX for treatment decision in osteopenia
- Exclude secondary causes (bloods)
Treatment
- Ensure adequate calcium intake and correct vitamin-D deficiency
- Bisphosphonate or other antiresorptive when suitable
- Denosumab requires reliable dosing and an exit plan
- Consider anabolic-first therapy for very-high-risk disease
Key Drugs
- Alendronate: Oral weekly
- Zoledronic acid: IV yearly
- Denosumab: SC 6-monthly (rebound risk)
- Teriparatide/Romosozumab: Anabolic
Complications
- ONJ: Rare (1 in 10000+)
- Atypical fracture: Drug holiday after 5 years
- Denosumab rebound: Must transition to bisphosphonate
- GI upset with oral bisphosphonates (take upright)
Post-Fracture
- Eligible fragility fractures trigger bone-health assessment
- FLS or equivalent coordination improves the treatment pathway
- Start treatment according to fracture acuity, medical status and drug choice
- Hip-fracture outcome data vary across populations
Evidence Base
FIT (Fracture Intervention Trial) — vertebral fracture arm
- 2027 postmenopausal women with low femoral-neck BMD and at least one existing vertebral fracture; alendronate vs placebo over 36 months
- New morphometric vertebral fracture 8.0% vs 15.0% (RR 0.53)
- Hip fracture relative hazard 0.49 (95% CI 0.23-0.99) and wrist 0.52 (0.31-0.87)
- Any clinical fracture relative hazard 0.72 (0.58-0.90); clinically apparent vertebral fracture 2.3% vs 5.0%
HORIZON-PFT
- 7765 women (mean age 73); once-yearly IV zoledronic acid 5mg vs placebo over 3 years
- Morphometric vertebral fracture reduced 70% (3.3% vs 10.9%; RR 0.30)
- Hip fracture reduced 41% (1.4% vs 2.5%; HR 0.59)
- Nonvertebral, clinical and clinical vertebral fractures reduced 25%, 33% and 77% respectively (P less than 0.001 for all)
- Serious atrial fibrillation more frequent with zoledronic acid (50 vs 20 patients, P less than 0.001)
FREEDOM
- 7868 women aged 60-90 with T-score below -2.5 but not below -4.0 at lumbar spine or total hip; denosumab 60mg SC 6-monthly vs placebo over 36 months
- New vertebral fracture reduced 68% (2.3% vs 7.2%; RR 0.32)
- Hip fracture reduced 40% (0.7% vs 1.2%; HR 0.60, 95% CI 0.37-0.97, P=0.04) - an absolute difference of 0.5 percentage points over three years
- Nonvertebral fracture reduced 20% (6.5% vs 8.0%); no cases of osteonecrosis of the jaw and no increase in cancer, infection or cardiovascular disease
FREEDOM/Extension discontinuation analysis
- THREE THINGS BEHAVE DIFFERENTLY AFTER A MISSED DOSE, and conflating them is what produces the myth: bone turnover markers rise ABOVE baseline by 6 months, BMD falls BACK to baseline by 12 months, and the vertebral fracture rate returns to the UNTREATED rate - only the first of the three genuinely overshoots
- 1001 participants who stopped denosumab: vertebral fracture rate rose from 1.2 to 7.1 per 100 participant-years off treatment
- CRITICAL COMPARATOR: participants who stopped PLACEBO had 8.5 per 100 participant-years - so the rate returns to the untreated level, it does not exceed it
- What IS specific to denosumab is MULTIPLICITY: of those fracturing off treatment, 60.7% had more than one vertebral fracture vs 38.7% after placebo (p=0.049), an absolute risk of multiple vertebral fracture of 3.4% vs 2.2%
- Odds of multiple vertebral fracture were 3.9x higher (2.1-7.2) in those with a prior vertebral fracture, and rose 1.2x per 1% annualised total hip BMD lost; nonvertebral rates were similar (2.8 vs 3.8)
ARCH
- 4093 postmenopausal women with osteoporosis and a fragility fracture; 12 months romosozumab then alendronate vs alendronate throughout
- New vertebral fracture at 24 months reduced 48% (6.2% vs 11.9%)
- Hip fracture reduced 38% (2.0% vs 3.2%); clinical fracture reduced 27%
- More adjudicated serious cardiovascular events in year 1 with romosozumab (50 of 2040, 2.5%, vs 38 of 2014, 1.9%) - reported as a count difference with no P value
Teriparatide pivotal trial (Fracture Prevention Trial)
- 1637 postmenopausal women with prior vertebral fractures; teriparatide (PTH 1-34) 20 or 40mcg daily vs placebo (median 21 months)
- New vertebral fracture 5% (20mcg) vs 14% placebo (RR 0.35)
- New nonvertebral fragility fracture reduced ~50% (RR 0.47)
- Lumbar spine BMD rose 9 percentage points more than placebo at 20mcg (13 at 40mcg); femoral neck 3 points (6 at 40mcg) - but the 40mcg dose REDUCED radial shaft BMD by 2 points
- The 40mcg dose raised BMD more than 20mcg yet produced the SAME fracture reduction with more side effects - this, not efficacy, is why 20mcg became standard
Fracture Liaison Services meta-analysis
- 74 controlled studies (16 RCTs, 58 observational) of FLS vs usual care
- BMD testing 48.0% vs 23.5%; treatment initiation 38.0% vs 17.2%; adherence 57.0% vs 34.1%
- Re-fracture: meta-analytic absolute risk reduction 5 percentage points (95% CI -0.08 to -0.03); unweighted arm rates were 13.4% control vs 6.4% FLS
- Mortality: meta-analytic absolute reduction 3 percentage points (95% CI -0.05 to -0.01); unweighted arm rates 15.8% vs 10.4%