Mechanically-Assisted Crevice Corrosion at Head-Neck Junction
- Trunnionosis = mechanically-assisted crevice corrosion (MACC) at head-neck taper
- Risk factors: large heads (36mm+), high offset, long necks, Ti stems, mixed metals
- Cobalt more systemically toxic than chromium (cardiotoxicity, neurotoxicity)
- MARS MRI is investigation of choice - detects soft tissue destruction
- Revision must address soft tissue debridement AND component considerations
- “Cobalt greater than 7 ppb and Cr greater than 5 ppb are concerning thresholds
- “MoP with large CoCr head on Ti stem = highest risk combination
- “ALTR = Adverse Local Tissue Reaction (umbrella term)
- “ARMD = Adverse Reaction to Metal Debris (same entity, different name)
Overview and Epidemiology
Trunnionosis is mechanically-assisted crevice corrosion (MACC) at the modular head-neck taper junction of a total hip arthroplasty. The metal debris it releases provokes an adverse local tissue reaction (ALTR). It is distinct from bearing-surface wear in metal-on-metal articulations.
How common. Trunnionosis is reported in 2-4% of modular THA overall, with higher rates, up to 10%, in specific designs. Joint registry data show elevated revision rates for certain stem-head combinations.
How it came to light. Modularity was introduced in the 1980s for surgical flexibility, and attention first fell on bearing-surface failures in metal-on-metal hips. Taper corrosion was recognised as a distinct entity around 2010, recognition increased dramatically after that, and MHRA alerts and recalls highlighted the problem. It now affects metal-on-polyethylene and ceramic-on-polyethylene combinations too.
Risk Factors
Implant factors. Head size is the key modifiable risk factor, and combined with a titanium stem the risk is multiplicative.
- Low Risk
- 28-32mm
- High Risk
- 36mm+
- Mechanism
- Larger head = greater taper moment
- Low Risk
- CoCr stem
- High Risk
- Titanium stem
- Mechanism
- Ti has inferior taper performance
- Low Risk
- Matched metals
- High Risk
- CoCr head on Ti stem
- Mechanism
- Galvanic couple accelerates corrosion
- Low Risk
- Standard
- High Risk
- Long (+5, +10)
- Mechanism
- Increased lever arm at taper
- Low Risk
- Standard
- High Risk
- High offset
- Mechanism
- Greater bending moment at taper
- Low Risk
- Manufacturer matched
- High Risk
- Mismatch or poor design
- Mechanism
- Taper angle/roughness mismatch
High-offset (lateral offset) stems increase torsional loads as well as the bending moment.
A large CoCr head (36mm+) on a high-offset titanium stem with an extended neck is the worst combination. National joint registry data (AOANJRR, NJR, AJRR) confirm these combinations have the highest revision rates for ALTR. Avoid this combination or implement surveillance protocols.
Taper geometry. Angular mismatch between head and trunnion shifts contact toward one end of the taper, increasing local stress and micromotion instead of sharing load along the interface. Distal and proximal engagement also place the contact patch at different moment arms from the head centre, one reason offset, head size and mismatch amplify bending and fretting.
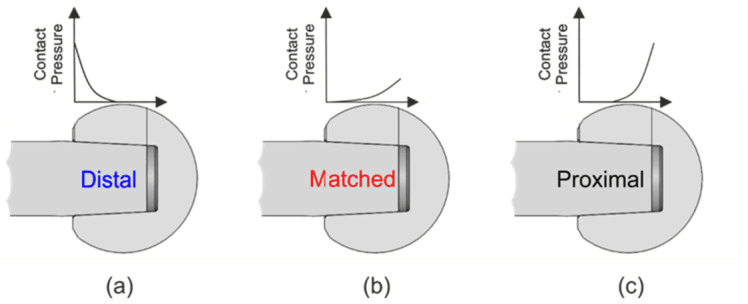
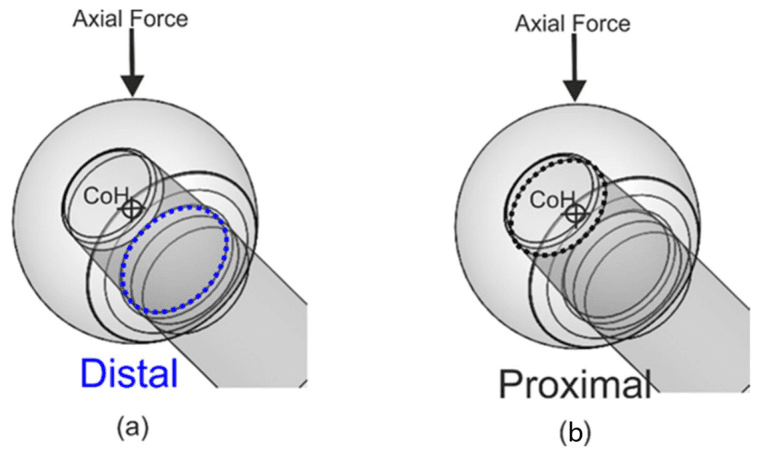
Patient factors. Male sex may carry a higher risk, attributed to higher activity levels and the larger heads used in men. The other patient risk factors:
- Younger, more active patients
- Higher BMI (increased joint loads)
- Bilateral THA (cumulative exposure)
- A history of metal hypersensitivity
Activity. High-demand activities increase the number of loading cycles and impact sports amplify the peak loads. A greater range of motion increases taper micromotion.
Assembly technique. How the taper is assembled matters:
- A dry taper is essential; blood or fluid reduces the cold weld
- Adequate impaction force; studies suggest 4-8 kN
- Clean taper surfaces; debris interferes with seating
- Correct orientation, avoiding toggle during impaction
Component position. Excessive femoral anteversion may increase torsional loads, and combined version affects the loading pattern.
The table applies these factors to common clinical scenarios.
- Risk Level
- Low
- Recommended Action
- Standard surveillance
- Key Point
- Small head, matched metals = low risk
- Risk Level
- High
- Recommended Action
- Annual metal ions + clinical review
- Key Point
- Large head on Ti = high risk combination
- Risk Level
- Moderate
- Recommended Action
- Annual metal ions, clinical review
- Key Point
- Bearing surface wear, not taper
- Risk Level
- Critical
- Recommended Action
- Urgent MARS MRI + revision planning
- Key Point
- High ions with symptoms = tissue damage likely
Pathophysiology
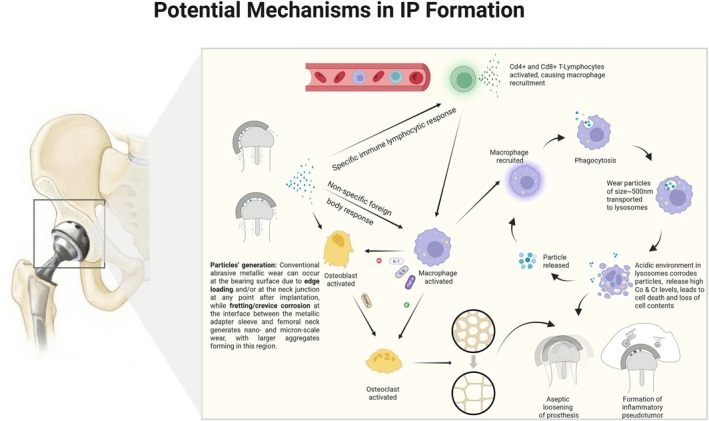
The cascade. Fretting disrupts the protective oxide layer, and the crevice environment prevents the surface from repassivating. Metal ions are released, causing local tissue toxicity (ALTR) and possibly systemic toxicity.
The Morse taper. The head is held on the trunnion by an interference fit, created by cold welding, and the impaction force is critical to that initial fixation. The taper angle varies between manufacturers, 5°44' being common, and taper length affects the contact area and stability.
Loads on the junction. Three kinds of load reach the taper in service:
- Axial loads from body weight
- Torsional loads from gait (internal and external rotation)
- Bending moments from offset and neck length
Moment = Force × Distance. Larger heads increase the lever arm from hip centre to taper junction. This amplifies bending moments and torsional stresses at the taper, increasing fretting micromotion. A 36mm head generates approximately 30% more moment than a 28mm head.

Clinical Presentation
Local symptoms. Patients may present with groin pain, which may be insidious in onset, or hip pain with activity. Patients may also describe clicking, squeaking or grinding, or swelling from a pseudotumour. Abductor destruction causes progressive weakness; patients may also report a sense of instability or recurrent dislocation.
Systemic symptoms. The patient may report fatigue and malaise, cognitive change (memory and concentration), peripheral neuropathy, visual or hearing change, palpitations or dyspnoea from cardiomyopathy, symptoms of hypothyroidism, or depression.
PUNCHSystemic Effects of Cobalt
Hook:Cobalt can really PUNCH you - systemic toxicity is serious!
Clinical stages. The disease runs from silent ion release to systemic toxicity.
Progression of Trunnionosis
Metal ion release begins. Patient asymptomatic. May only be detected on surveillance bloods. Tissue changes minimal.
Groin or hip pain develops. May be mistaken for other causes. Early soft tissue changes on MRI. Metal ions typically elevated.
Pseudotumour formation. Abductor destruction. Bone loss possible. Significant functional impairment. High metal ions.
Cobaltism develops. Cardiac, neurological, thyroid manifestations. May be irreversible. Urgent revision required.
Systemic cobalt toxicity requires urgent action. Cobalt levels are often greater than 20 ppb, and it can be fatal if not addressed. Echo and cardiology referral are essential.
Investigations
Ions screen; imaging decides. Cobalt and chromium levels guide management, but imaging (MARS MRI) determines the extent of tissue damage and drives the surgical decision.
Metal ions. Take whole-blood samples; serum alone is not enough.
- Normal
- Less than 1 ppb
- Concerning
- Greater than 4 ppb
- Action Threshold
- Greater than 7 ppb = imaging required
- Normal
- Less than 1 ppb
- Concerning
- Greater than 4 ppb
- Action Threshold
- Greater than 5 ppb = imaging required
- Normal
- Approximately 1:1
- Concerning
- Greater than 2:1
- Action Threshold
- High ratio suggests taper source
Reading the result. A Co:Cr ratio greater than 2:1 suggests taper corrosion rather than bearing wear. Levels can fluctuate, so the trend is important.
MHRA guidance. The UK guidance, widely adopted, treats Co or Cr greater than 7 ppb as a concern requiring imaging and recommends annual surveillance for at-risk implants.
MARS MRI. Metal artefact reduction sequence MRI is the gold-standard imaging for ALTR. It reduces metal artefact enough to show the soft tissues, detects pseudotumours, fluid collections and muscle atrophy, and grades the severity of tissue destruction. The report should cover:
- Pseudotumour: cystic or solid mass, which may be large
- Fluid collections around the prosthesis
- Abductor status: atrophy, fatty infiltration, detachment
- Bone involvement: osteolysis, cortical erosion
- Muscle necrosis: signal change indicating tissue death
The Anderson classification grades pseudotumours, and higher types correlate with worse tissue damage:
- Type 1: thin-walled cystic
- Type 2a: thick-walled cystic, atypical contents
- Type 2b: thick-walled, mixed solid and cystic
- Type 3: predominantly solid
A pseudotumour is not in itself an indication for surgery. In Hart's case-control study (Evidence Base) pseudotumours were common even in well-functioning metal-on-metal hips, with no significant difference in prevalence from painful ones, so the decision integrates symptoms, ion trend and lesion type.
Other imaging. The other modalities are summarised below.
- Role
- Baseline, component position, osteolysis
- Key Findings
- Head position, stem subsidence, bone loss
- Role
- Bone detail, surgical planning
- Key Findings
- Osteolysis extent, bone stock assessment
- Role
- Screening for fluid collections
- Key Findings
- Pseudotumours, bursae, can guide aspiration
- Role
- Rule out loosening, infection
- Key Findings
- Non-specific uptake, limited value
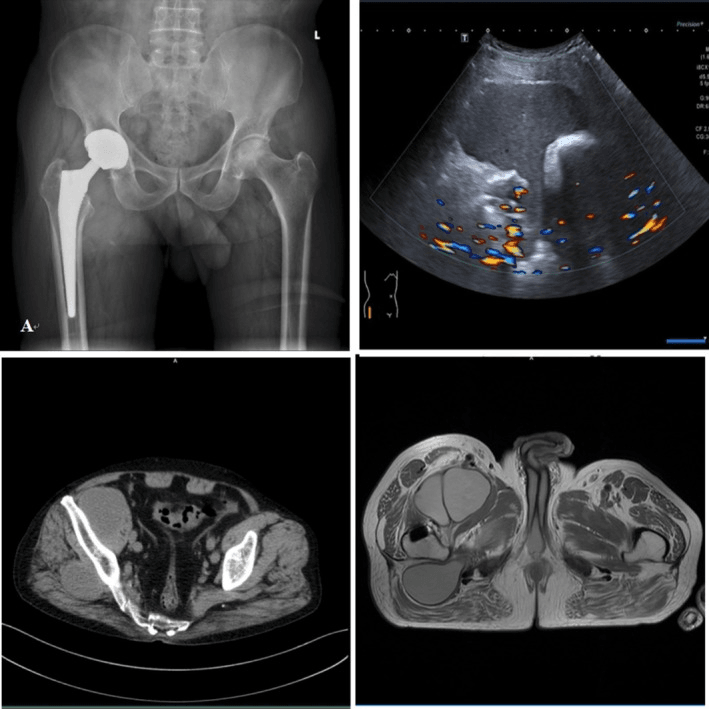
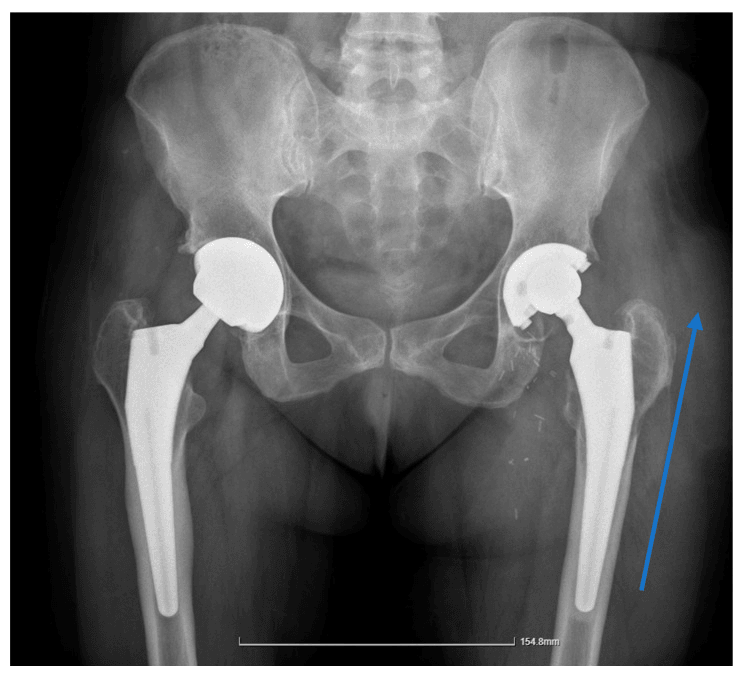
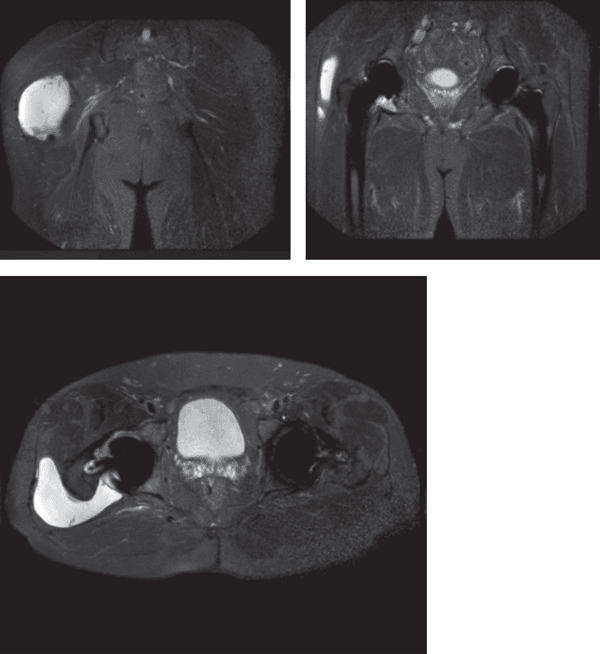
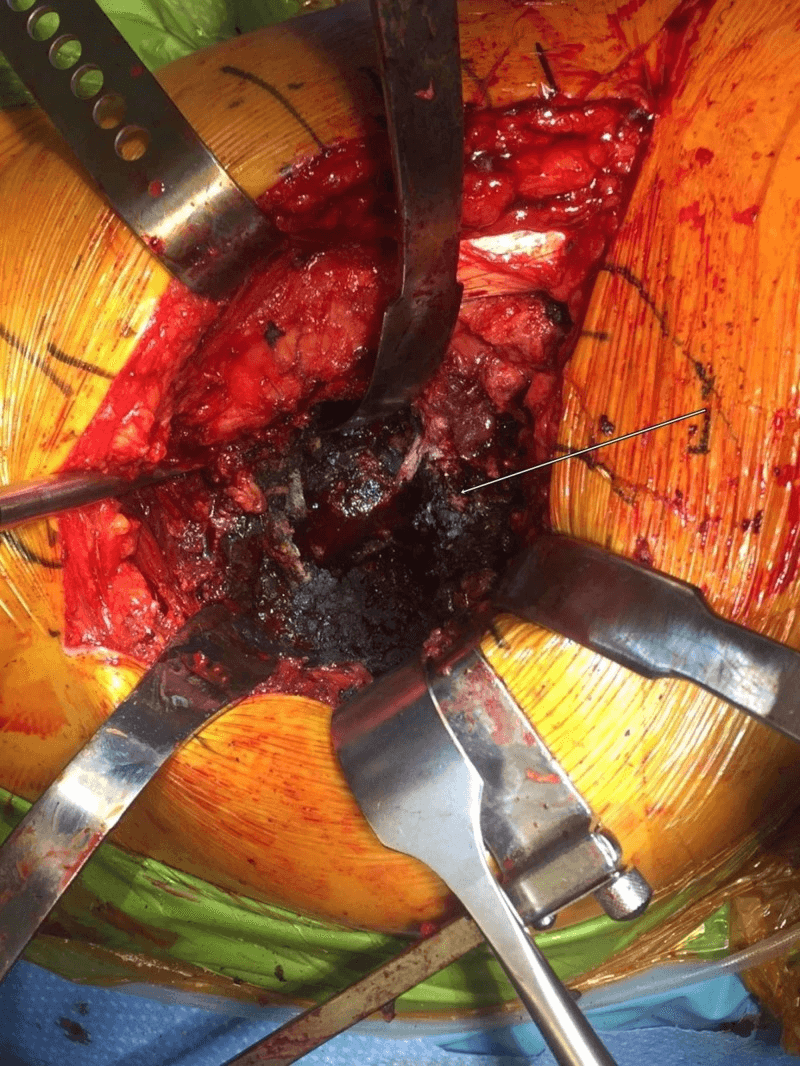
Aspiration. Aspirate to rule out infection, which is essential before revision; it also relieves symptoms from a large effusion and provides fluid for analysis. Characteristic ALTR fluid is dark grey or black, metallic-stained and often sterile. Send it for:
- Cell count and differential
- Gram stain and culture
- Metal ion levels in fluid (research use)
- Crystal analysis
- Whole-blood metal ions (Co and Cr)
- Plain radiographs
- MARS MRI if ions elevated or symptoms persist
- Aspiration to rule out infection before surgery
Do not skip the aspiration: occult infection can coexist.
Differential Diagnosis
Metal ions with MARS MRI distinguish trunnionosis from the other causes of a painful THA.
- Key Features
- Elevated metal ions, pseudotumour on MRI
- Distinguishing Investigation
- Metal ions + MARS MRI
- Key Features
- Fever, elevated CRP/ESR, positive cultures
- Distinguishing Investigation
- Aspiration, WBC count, culture
- Key Features
- Start-up pain, progressive, radiolucent lines
- Distinguishing Investigation
- Serial X-rays, bone scan
- Key Features
- Recurrent dislocation, sense of giving way
- Distinguishing Investigation
- Clinical exam, X-ray, CT for version
- Key Features
- Acute pain after trauma, may be subtle
- Distinguishing Investigation
- X-ray, CT if needed
- Key Features
- Back pain, radicular symptoms
- Distinguishing Investigation
- Spine imaging, selective injection
- Key Features
- Anterior groin pain, worse with flexion
- Distinguishing Investigation
- CT (cup position), lidocaine injection
Must distinguish ALTR from infection before revision. Both can present with pain and elevated inflammatory markers, so aspiration is MANDATORY. Infection requires completely different management.
Management
Surveillance. Surveillance without immediate revision suits:
- The asymptomatic patient with an at-risk implant
- Low-grade metal ion elevation (Co less than 7 ppb)
- No significant ALTR on MARS MRI
- Well-fixed, well-positioned components
The protocol is annual clinical review and annual metal ions (Co and Cr), with MARS MRI every 1-2 years if the ions are elevated, and patient education on the warning symptoms. Upgrade to revision on symptomatic progression, a rising metal ion trend, ALTR progression on MRI or the development of systemic symptoms.
Absolute indications for revision
- Symptomatic ALTR with tissue destruction
- Progressive pseudotumour
- Systemic cobalt toxicity (cobaltism)
- Component loosening
- Recurrent dislocation due to abductor failure
Relative indications
- Significantly elevated metal ions (Co greater than 10-15 ppb)
- Asymptomatic but enlarging pseudotumour
- Progressive bone loss
- Patient anxiety affecting quality of life
Surgery is favoured in a younger, active patient with good bone stock, abductors that are still salvageable and minimal systemic symptoms.
Planning the revision. Revision is complex, and the preparation reflects it:
- MARS MRI to map tissue destruction
- CT for bone stock assessment
- Cardiac evaluation if cobalt is very elevated
- Infection work-up (aspiration, bloods)
- Blood products available; the surgery is often bloody
The single most important factor for revision success is complete debridement of necrotic tissue. Retained necrotic/reactive tissue leads to persistent inflammation, poor healing, and high complication rates. Be aggressive with debridement.
Surgical Technique Considerations
Approach. An extensile approach is required, one that shows the full extent of the pseudotumour: posterior, with an extended capsulotomy, and a trochanteric osteotomy if needed for access. A direct lateral approach may limit access posteriorly.
Exposure and debridement. The key steps:
- Identify and protect the sciatic nerve, often displaced by the pseudotumour
- Decompress large collections before dislocation, sending fluid for culture to rule out infection
- Evacuate the pseudotumour contents carefully and excise its wall completely; it may extend into the pelvis, so be aware of the vascular structures
- Complete capsulectomy and synovectomy
- Debride all necrotic tissue back to bleeding margins
- Lavage thoroughly to remove debris
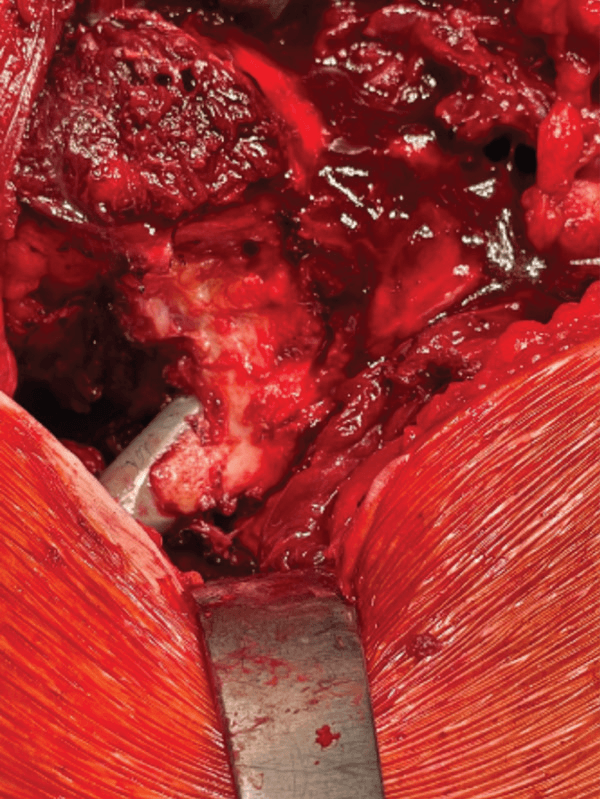
Abductors. Gluteus medius is often damaged or necrotic, so assess how much viable muscle remains. The abductors may need augmentation or reconstruction, and tensor fascia lata advancement is possible. Consider a constrained liner if they are deficient.
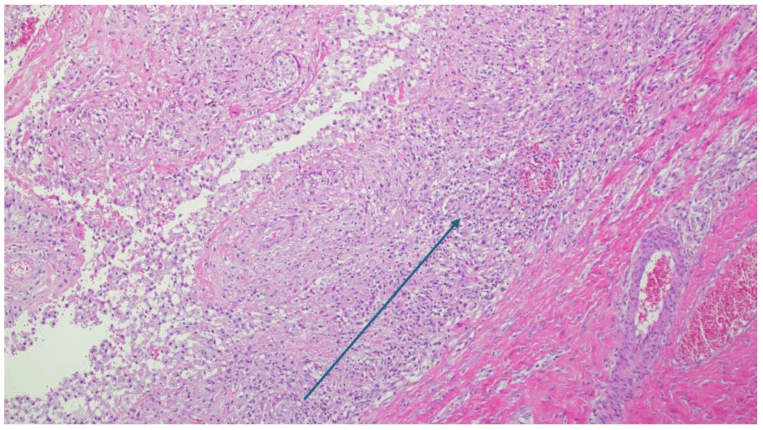
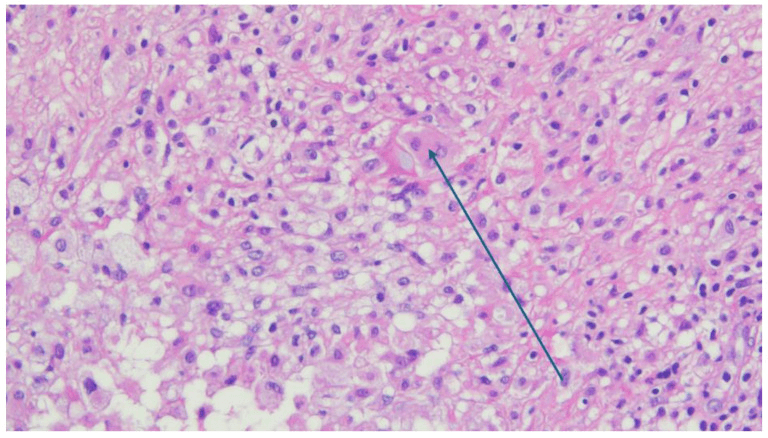
Histology. Send tissue for histopathology. The ALVAL score provides prognostic information, and frozen section helps rule out occult infection.
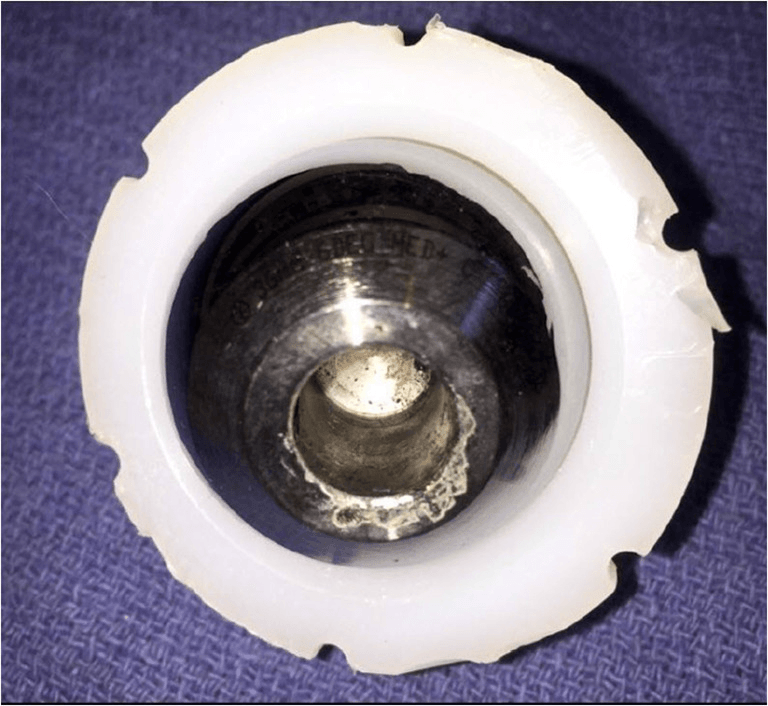
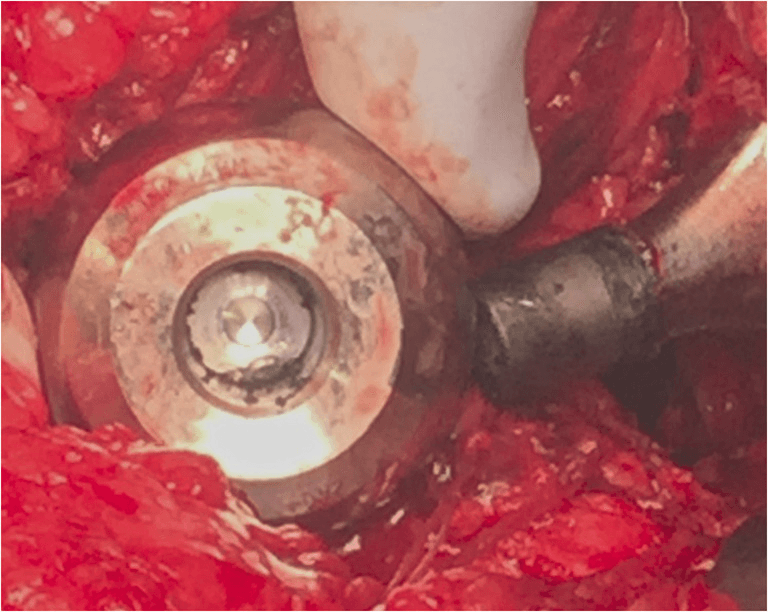
The stem. Remove the corroded head and trunnion adapter, then check the taper condition carefully and document the findings for registry reporting. A well-fixed stem with moderate corrosion can be kept, with a titanium adapter sleeve under a new ceramic head; severe trunnion corrosion or a loose stem needs stem revision. The Goldberg score (below) grades the taper for this decision. With a modular-neck stem, consider modular neck exchange if available.
The cup. Assess its position and fixation, and revise it only if loose or malpositioned. A well-fixed metal-on-metal cup can have its liner exchanged to ceramic-on-polyethylene.
The bearing. Avoid metal-on-metal at all costs; the table sets out the default at each level.
- Preferred Choice
- Ceramic-on-polyethylene
- Rationale
- Eliminates metal ion generation
- Preferred Choice
- 32mm or smaller
- Rationale
- Reduces taper moment
- Preferred Choice
- Ceramic (BIOLOX)
- Rationale
- No corrosion, excellent tribology
- Preferred Choice
- Ti sleeve if available
- Rationale
- Salvages damaged stem taper
- Preferred Choice
- Keep if well-fixed, taper salvageable
- Rationale
- Avoid unnecessary morbidity
- Preferred Choice
- May need increased constraint
- Rationale
- Abductor insufficiency common
Ceramic heads. A ceramic head produces no metallic corrosion products and is a hard bearing surface with excellent wear characteristics. The caution is fracture, rare with modern ceramics.
Ti sleeve/adapter devices allow retention of a well-fixed stem with damaged trunnion. The sleeve covers the corroded taper and provides a new surface for head impaction. This avoids stem revision morbidity in selected cases. Check manufacturer compatibility.
Complications
After revision for ALTR. Revision for ALTR has higher complication rates than routine revision THA. The dislocation rate reflects abductor deficiency, and the patient should be counselled that constrained components, a brace or assistive devices may be needed long-term.
- Rate
- 10-25%
- Risk Factors
- Abductor loss, revision surgery
- Management
- Constrained liner, bracing, re-revision
- Rate
- 5-10%
- Risk Factors
- Necrotic tissue, prolonged surgery
- Management
- Debridement, antibiotics, staged revision
- Rate
- 2-5%
- Risk Factors
- Scarring, pseudotumour displacement
- Management
- Careful dissection, may recover
- Rate
- 15-30%
- Risk Factors
- Incomplete debridement, tissue damage
- Management
- May need re-revision
- Rate
- 20-40%
- Risk Factors
- Pre-existing damage from ALTR
- Management
- Gait aids, reconstruction options limited
- Rate
- 2-5%
- Risk Factors
- Bone loss, osteolysis
- Management
- May need additional fixation
Outcomes and Prognosis
Prognostic factors. A better prognosis goes with:
- Early diagnosis before extensive tissue damage
- Intact or recoverable abductors
- Good bone stock
- Low metal ion levels
- Complete surgical debridement achieved
A worse prognosis goes with:
- Delayed diagnosis with extensive destruction
- Abductor loss or atrophy
- Significant bone loss
- Very high metal ion levels (cobaltism)
- Systemic toxicity (cardiac, neurological)
- Multiple prior revisions
Re-revision is common after ALTR revision - registry data (NJR) show 13.5% re-revision at a mean of 1.2 years and only ~84% implant survival at 4 years, worse than for many other revision indications. Dislocation and infection are the leading reasons for re-revision. Early diagnosis and meticulous, complete revision optimise outcomes.
Guidelines, Registries & Global Practice
Global Epidemiology
- Trunnionosis-related ALTR is reported across all major modular THA designs and bearing couples, including conventional metal-on-polyethylene, not only MoM
- True incidence is uncertain because many cases are subclinical; symptomatic revision for ALTR remains a small but rising proportion of all revisions
- Large-head MoM THA (36mm and over) and large-diameter resurfacings concentrated the early failures that drew attention to the modular junction
- Recognition surged after 2010 following retrieval studies and regulatory alerts; conventional MoP taper corrosion is now an established differential for the painful THA worldwide
Side-by-Side Guidance
- Region
- UK
- Key Recommendation
- Whole-blood Co/Cr; 7 micrograms/L (≈7 ppb) trigger for cross-sectional imaging; lifelong follow-up for large-head MoM
- Region
- USA
- Key Recommendation
- Symptom-led metal-ion testing and MARS MRI for symptomatic MoM hips; no single mandated ion threshold
- Region
- USA
- Key Recommendation
- Differential cobalt-over-chromium elevation points to taper source; ceramic-head exchange at revision
- Region
- Europe
- Key Recommendation
- Risk-stratified surveillance using implant type, symptoms, ion trend and imaging
The widely quoted 7 micrograms/L (≈7 ppb) trigger derives from UK MHRA guidance and large-head MoM retrieval data. US regulators favour a symptom-led approach without a single fixed cut-off. The unifying principle globally is the same: ion levels SCREEN, imaging (MARS MRI) and symptoms DECIDE. A differential cobalt-greater-than-chromium pattern specifically localises the problem to the taper rather than the bearing.
Registry Evidence
- MoM bearings carry the highest revision rate of any bearing couple across the AOANJRR (Australia), NJR (UK) and AJRR (US)
- Large-head MoM THA performs worse than resurfacing, and ceramic-on-polyethylene / ceramic-on-ceramic show the lowest revision rates
- Registries flagged specific titanium-stem plus large-CoCr-head combinations for surveillance and informed device withdrawals
- Registry data underpins the global shift toward smaller ceramic heads on polyethylene at primary and revision surgery
High- vs Limited-Resource Practice
- Surveillance / Diagnosis
- Routine whole-blood Co/Cr, MARS MRI, registry-linked recall
- Practical Reality
- Structured surveillance programmes; ceramic heads readily available
- Surveillance / Diagnosis
- Clinical review and plain radiographs; ion assays and MARS MRI may be unavailable
- Practical Reality
- Reliance on symptoms and effusion/mass on ultrasound; ceramic/sleeve supply may be constrained
Patients with recalled or high-risk implants (large-head MoM THA and certain conventional THA stem-head combinations) should be identified, notified and enrolled in surveillance. Maintaining an accurate implant register for every patient is the foundation of safe long-term follow-up, whatever the healthcare setting.
Related pages: Metal-on-Metal Complications covers the bearing-driven adverse reaction to metal debris that trunnionosis is constantly confused with - the distinction matters because the taper produces ALTR in hips with no metal bearing at all; Corrosion Mechanisms sets out mechanically-assisted crevice corrosion, fretting and galvanic coupling in full, and Cobalt-Chrome Alloys with Titanium Alloys explain why a mixed-alloy couple corrodes more than a matched one; Tribology and Wear and Wear Mechanisms hold the mechanics behind the lever-arm argument, with THA Bearing Surfaces, Ceramics and Polyethylene UHMWPE and XLPE covering the ceramic-head-on-titanium-sleeve construct that is the reference revision; THA Wear and Osteolysis and THA Aseptic Loosening are the particle-driven differentials for the painful arthroplasty, and Periprosthetic Joint Infection with THA Complications: Infection must be excluded before any metal debris diagnosis is made, since ALTR and infection can raise the same inflammatory markers; Revision THA covers the reconstruction, and THA Complications: Dislocation with THA Dual Mobility address the instability that follows abductor destruction and drives re-revision after ARMD surgery.
Controversies & Areas of Uncertainty
Metal ion thresholds. The 7 micrograms/L trigger is pragmatic, not absolute. Some patients develop florid ALTR at near-normal ions (hypersensitivity), while others tolerate very high levels, so the trend and the Co:Cr ratio matter more than any single number. Cooper's dual-taper series makes the point: mean serum cobalt was 6.0 ng/mL in hips that all needed revision.
The asymptomatic patient. When to revise an asymptomatic patient with a rising ion level or an enlarging pseudotumour is unresolved. Prophylactic revision must be balanced against the high complication rate of ALTR revision surgery.
Titanium sleeve or stem revision. Retaining a well-fixed stem with a ceramic head and titanium sleeve avoids morbidity but leaves the original, damaged trunnion in situ. The long-term durability of the sleeve construct against full stem revision remains debated.
Chelation and systemic cobaltism. Evidence for chelation therapy in arthroprosthetic cobaltism is weak and largely anecdotal. Source control by revision to cobalt-free implants is the mainstay, and the reversibility of cardiac and neurological injury is variable.
Be ready to argue both sides: "Would you revise an asymptomatic patient with cobalt of 12 ppb?" There is no single right answer. Demonstrate a structured, individualised approach integrating symptoms, ion trend, imaging (lesion type), abductor status, patient factors and the morbidity of revision.
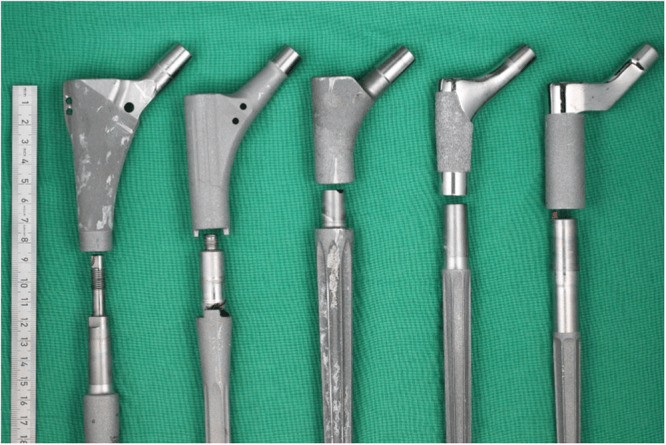
The Neck-Body (Dual-Taper) Junction: A Second Modular Corrosion Site
A second junction. In a dual-taper (modular-neck) stem the surgeon selects a separate modular neck, adjusting version, offset and length independently of stem fixation. That adds a neck-body (neck-stem) junction, distinct from the head-neck taper. It sits closer to the fixed stem, carries large cantilever bending moments and is a corrosion site in its own right, the mechanism behind the withdrawal of several dual-taper designs (for example the Rejuvenate and ABG II modular-neck stems).
Why it fails. The classic pairing is a cobalt-chromium modular neck on a titanium-alloy stem body, a mixed-alloy (galvanic) couple. The long lever arm and cyclic bending drive fretting that disrupts passivation, then crevice corrosion in the oxygen-depleted junction: the same MACC process as at the head-neck taper. Because the junction is proximal and load-bearing, failure can occur early, within the first post-operative year, and rarely the modular neck can also fatigue-fracture.
Presentation mirrors head-neck trunnionosis: new groin or thigh pain, effusion, pseudotumour and ALTR on MARS MRI.
Cooper - ALTR from Corrosion at the Modular Neck-Body Junction (Dual-Taper Stems)
- 12 hips (11 patients) with ALTR from corrosion at the modular neck-body junction of a dual-taper stem
- All had a titanium-alloy stem with a cobalt-chromium modular neck; new-onset pain at a mean of 7.9 months
- Serum cobalt (mean 6.0 ng/mL) was elevated more than chromium (0.6) or titanium (3.4)
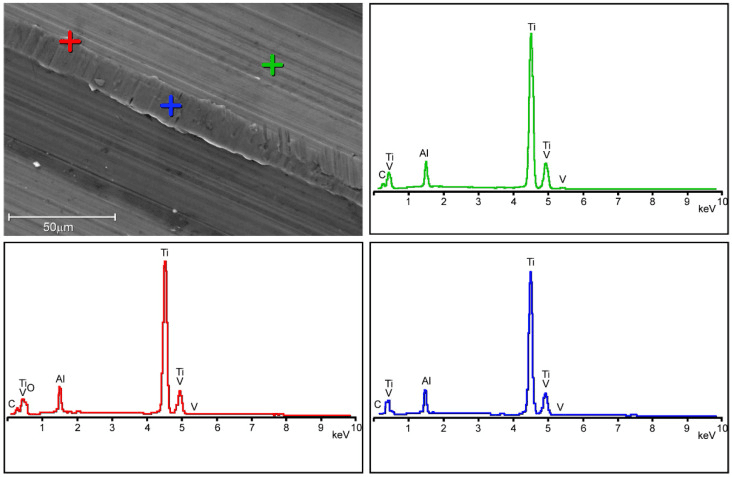
- MARS MRI showed adverse reactions; SEM confirmed fretting and crevice corrosion at the neck-body interface
When the examiner hands you a modular-neck stem, remember there are two modular junctions. A cobalt-over-chromium elevation still localises the problem to a taper, but you must ask which one, because head-neck versus neck-body changes the whole operation. The ion pattern is again cobalt-dominant, but serum titanium may also rise from the Ti stem side of the couple; a concurrent titanium rise is a clue that the neck-body junction, not just the head-neck taper, is involved. A ceramic head on a titanium sleeve does not treat this junction: source control usually means exchanging the modular neck and often revising the stem.
Grading Taper Damage: the Goldberg Retrieval Score
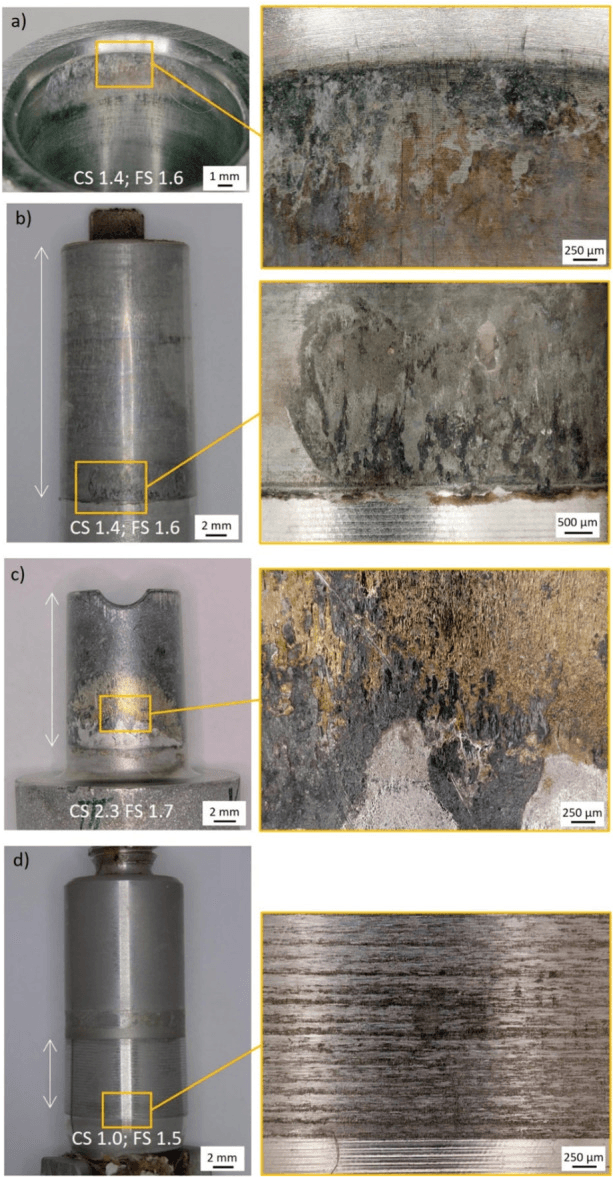
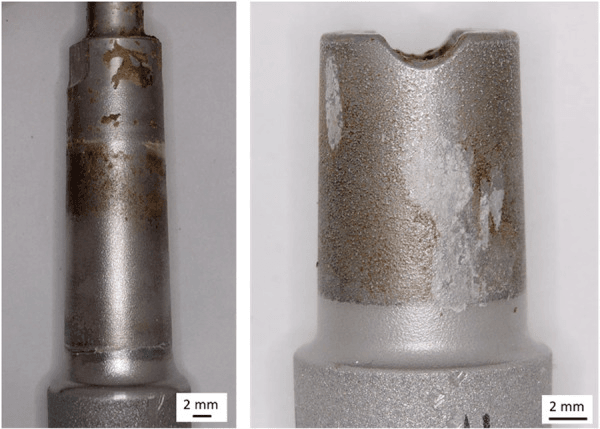
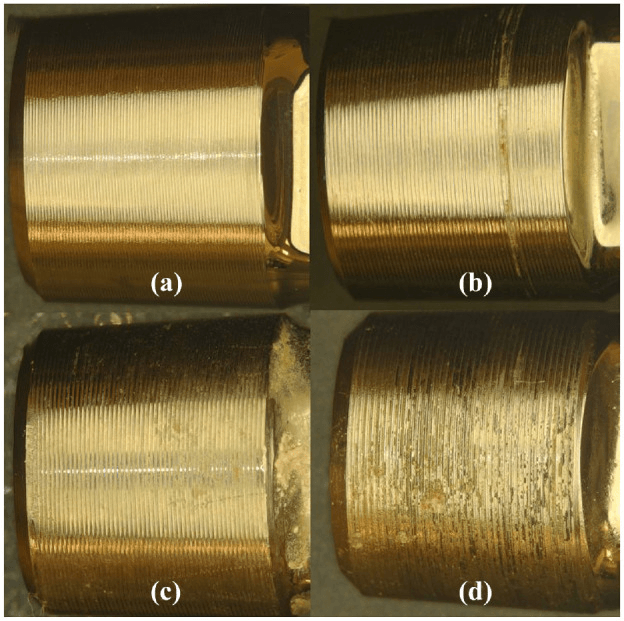
Why grade the taper. Keeping the stem with a titanium sleeve for moderate corrosion, or revising it for severe corrosion, needs an objective way to grade the taper. The reference tool is the Goldberg semiquantitative fretting-and-corrosion score, a four-point visual scale applied to each taper surface (the femoral head bore and the stem trunnion), read by quadrant.
- Appearance
- Bright machined surface, no fretting scars or corrosion
- Revision Implication
- Trunnion salvageable; ceramic head on titanium sleeve acceptable
- Appearance
- Isolated fretting scars or single small patch of discolouration
- Revision Implication
- Usually salvageable with a clean sleeve construct
- Appearance
- Fretting/corrosion over up to roughly a third of the surface, visible pits or black debris
- Revision Implication
- Higher-risk taper; weigh sleeve against stem revision
- Appearance
- Extensive pitting, etched/matte surface, heavy black corrosion product
- Revision Implication
- Damaged beyond reliable reuse; favour stem revision
What the retrieval study showed. The landmark study that defined the score also produced the mechanistic evidence behind the risk factors in this topic. Mixed-alloy couples corrode more than matched couples, heads tend to corrode more than necks, and neck flexural rigidity and implantation time predict damage: the mechanical basis for the head-size, offset and titanium-stem warnings.
Goldberg - Multicentre Retrieval Study Defining Taper Corrosion Scoring
- 231 retrieved modular hip implants scored for fretting and corrosion by taper quadrant (the 4-point Goldberg scale)
- Moderate-to-severe head corrosion in 42% of mixed-alloy versus 28% of similar-alloy couples
- Heads corroded more than necks; implantation time and neck flexural rigidity predicted damage
- Findings attributed in-vivo taper damage to mechanically-assisted crevice corrosion (MACC)
Grade the trunnion before you commit. A Goldberg grade 1-2 (bright or minimally scarred) trunnion on a well-fixed stem can accept a new ceramic head on a titanium adapter sleeve. Grade 3 is where the sleeve is weighed against stem revision. A grade 4 trunnion - pitted, etched, coated in black corrosion product - or any loose stem should push you toward stem revision, because a ceramic head impacted onto a damaged taper risks poor seating and ceramic fracture. The score also explains prevention: avoid mixed CoCr-on-titanium couples and very slim necks.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 58-year-old man is 5 years post primary THA with a 36mm cobalt-chrome head on a titanium uncemented stem. He is currently asymptomatic but was referred for surveillance due to implant concerns. How would you assess and counsel this patient?”
“A 62-year-old woman presents with progressive right hip pain and weakness 7 years after THA. She has a 38mm metal-on-polyethylene bearing on a titanium stem. Her cobalt is 18 ppb and chromium is 6 ppb. MARS MRI shows a large posterolateral pseudotumor with abductor muscle atrophy. How would you manage this patient?”
“A 55-year-old man presents with fatigue, hearing loss, and peripheral neuropathy. He had bilateral THA 6 years ago (large head MoM). His cobalt level is 85 ppb. MARS MRI shows bilateral pseudotumors. His cardiologist has diagnosed new cardiomyopathy. How would you approach this complex case?”
Definition
- Mechanically-assisted crevice corrosion (MACC) at head-neck taper
- ALTR = Adverse Local Tissue Reaction (umbrella term)
- ARMD = Adverse Reaction to Metal Debris (same entity)
- ALVAL = histological pattern of metal hypersensitivity
Risk Factors
- Titanium stem (Ti has worse taper performance)
- Head size large (36mm+ increases taper moment)
- Offset increased / Long neck
- Lateral offset designs
- Taper mismatch / Mixed metals (CoCr on Ti)
Corrosion Mechanisms
- Fretting: micromotion disrupts oxide layer
- Crevice: oxygen-depleted environment accelerates corrosion
- Galvanic: dissimilar metals create electrochemical gradient
- All three combine in MACC
Metal Ion Thresholds
- Cobalt greater than 7 ppb = concern, imaging required
- Chromium greater than 5 ppb = concern
- Co:Cr ratio greater than 2:1 suggests taper source
- Very high levels (greater than 20 ppb) = check for systemic toxicity
MARS MRI Findings
- Pseudotumor (cystic or solid)
- Muscle atrophy (abductors)
- Fluid collections
- Bone involvement/osteolysis
Revision Principles
- Complete debridement of necrotic tissue (most important)
- Ceramic head to eliminate metal ions
- Smaller head size (32mm)
- Ti adapter sleeve if stem well-fixed but taper damaged
- Consider constrained liner if abductors deficient
Systemic Cobalt Toxicity (PUNCH)
- Peripheral neuropathy
- Unexplained fatigue
- Neuro-ocular toxicity (vision/hearing)
- Cardiomyopathy (can be fatal)
- Hypothyroidism
Evidence Base and Key Studies
Cooper / Della Valle - Head-Neck Taper Corrosion Causing ALTR in MoP THA (Landmark)
- 10 metal-on-polyethylene THAs revised for corrosion at the modular head-neck taper
- All presented with pain/swelling; 2 with recurrent instability from abductor destruction
- Serum cobalt characteristically elevated more than chromium (differential Co greater than Cr)
- Treated with debridement plus ceramic head and titanium sleeve; cobalt fell to mean 1.61 ng/mL
Langton - Trunnion-Taper Failure in Large-Diameter MoM THR
- ASR total hip replacement failed at 48.8% at 6 years (vs 25% for the resurfacing)
- 26.1% of patients had serum cobalt greater than 7 micrograms/L
- Some THRs had low articular wear but marked damage at the trunnion-taper interface
- Wear at the modular junction is an important driver of adverse tissue reactions
Langton - Taper Junction Mechanics: Lever Arm Drives Failure
- Coordinate-measured taper material loss in 126 failed large-diameter MoM prostheses
- Primary driver of taper failure is the increased lever arm at the junction
- Varus stems, laterally engaging taper systems and larger head diameters all contributed
- Quantified the mechanical basis for the head-size and offset risk relationship