Mechanisms, Resistance and Biofilm in Orthopaedics
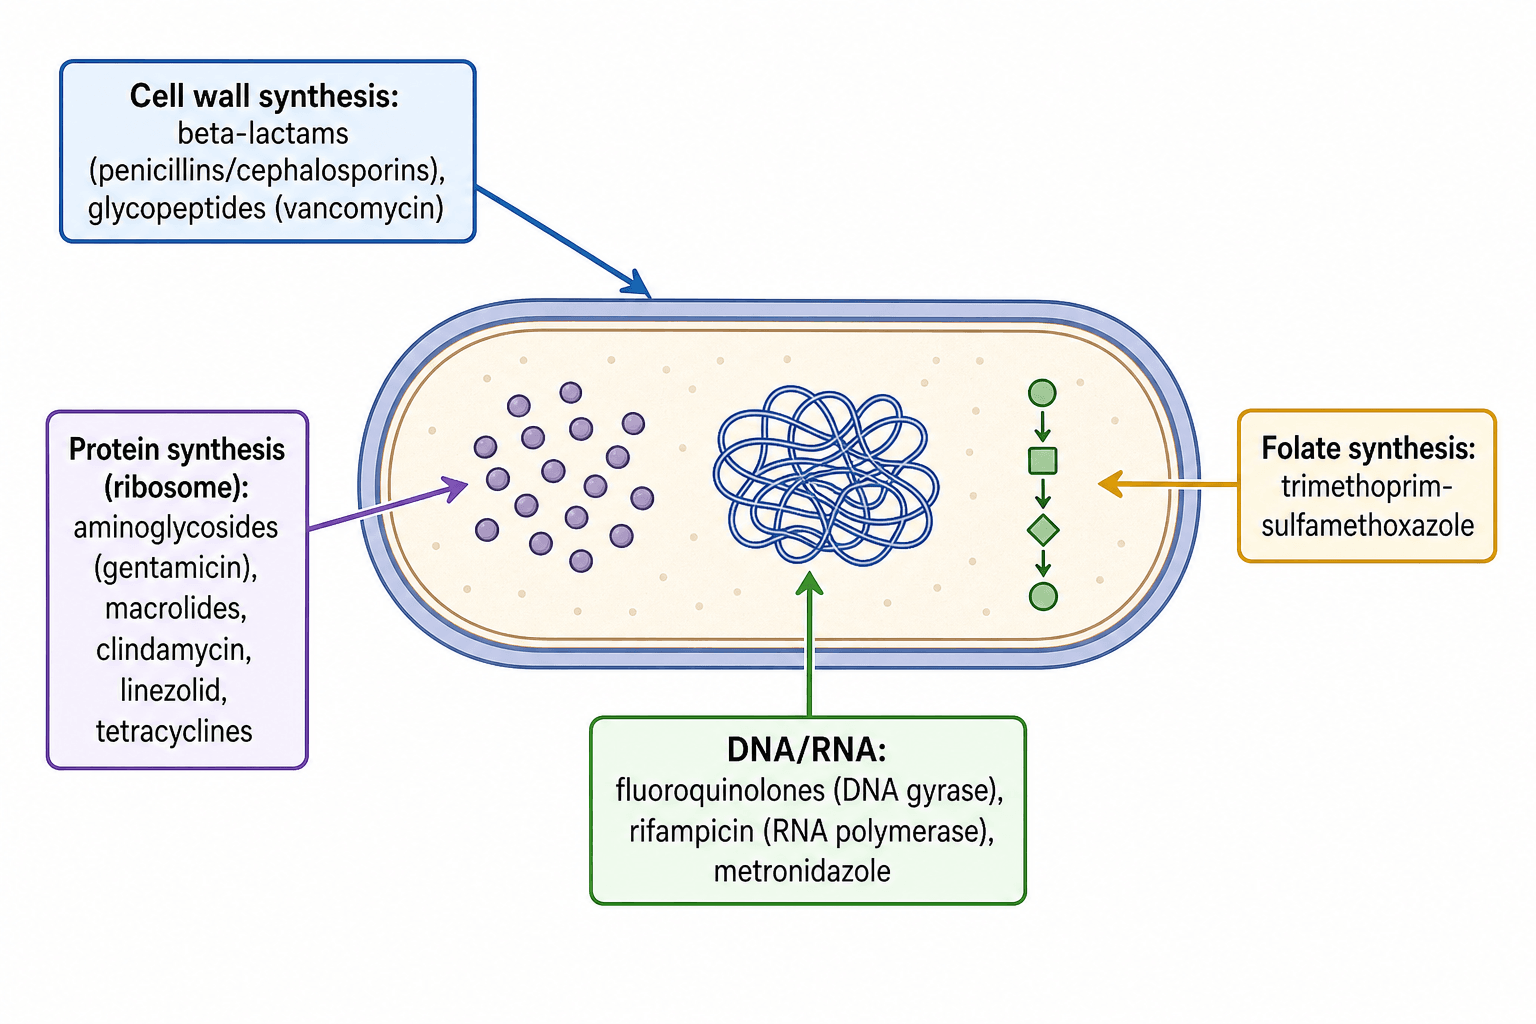
- Antibiotics are grouped by their TARGET: CELL-WALL synthesis (BETA-LACTAMS - penicillins/cephalosporins/carbapenems inhibit penicillin-binding proteins; GLYCOPEPTIDES like vancomycin bind D-ala-D-ala); PROTEIN synthesis at the ribosome (AMINOGLYCOSIDES, MACROLIDES, CLINDAMYCIN, LINEZOLID, TETRACYCLINES); DNA/RNA (FLUOROQUINOLONES inhibit DNA gyrase, RIFAMPICIN inhibits RNA polymerase, metronidazole); and FOLATE synthesis (trimethoprim-sulfamethoxazole).
- Antibiotics are BACTERICIDAL (kill, e.g. beta-lactams, glycopeptides, aminoglycosides, fluoroquinolones, rifampicin) or BACTERIOSTATIC (inhibit growth, e.g. tetracyclines, macrolides, clindamycin, linezolid); killing is either CONCENTRATION-DEPENDENT (aminoglycosides, fluoroquinolones - high peak matters) or TIME-DEPENDENT (beta-lactams, glycopeptides - time above MIC matters), which guides dosing.
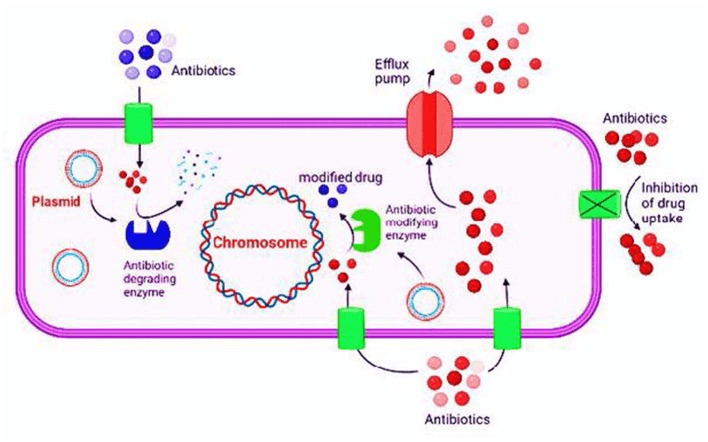
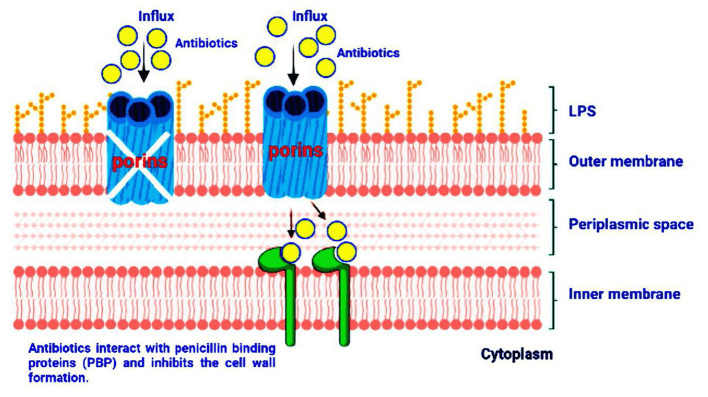
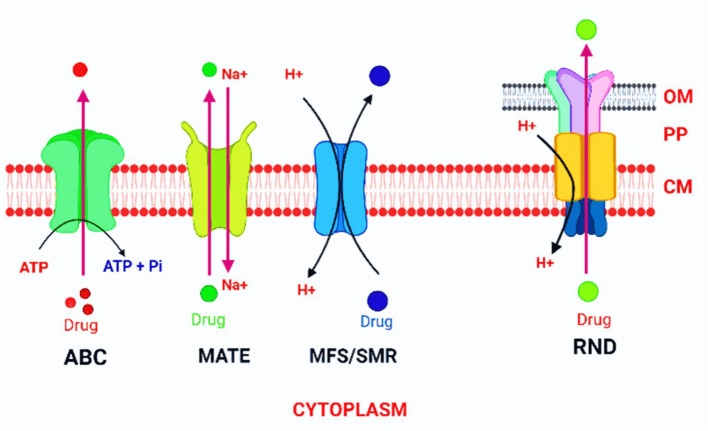
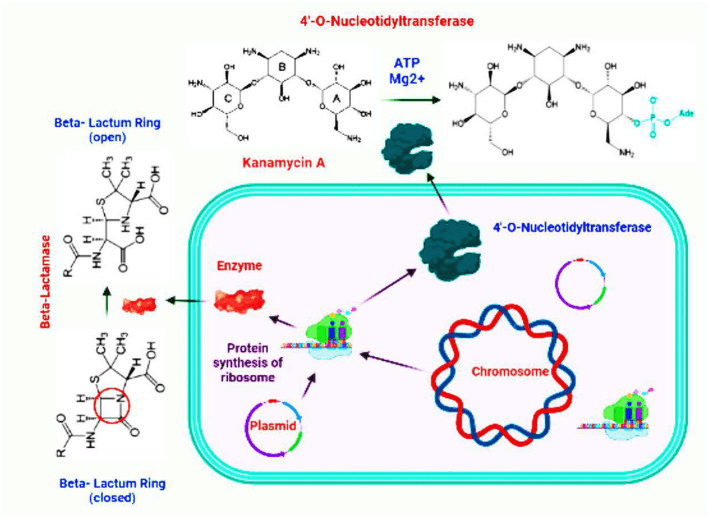
- RESISTANCE arises by four mechanisms: (1) ENZYMATIC INACTIVATION (beta-lactamases, including ESBL and carbapenemases), (2) TARGET MODIFICATION (altered penicillin-binding protein PBP2a in MRSA via mecA; altered D-ala-D-lac in VRE via vanA; gyrase/ribosomal mutations), (3) REDUCED UPTAKE/decreased permeability (porin loss) and (4) EFFLUX PUMPS; resistance genes spread by plasmids/transposons (horizontal gene transfer), producing MRSA, VRE, ESBL and multidrug-resistant gram-negatives.
- BIOFILM is the key orthopaedic concept: bacteria on an implant or dead bone form a structured community embedded in a self-produced extracellular matrix (glycocalyx), which confers antibiotic TOLERANCE (distinct from genetic resistance) through REDUCED antibiotic PENETRATION, SLOW-GROWING/dormant PERSISTER cells and SMALL-COLONY VARIANTS, and an altered microenvironment.
- Because of biofilm tolerance, ANTIBIOTICS ALONE typically FAIL against implant-associated infection (periprosthetic joint infection, implant-related osteomyelitis) - effective treatment requires SURGICAL removal/debridement of the biofilm (and often the implant) PLUS antibiotics; this is why source control is paramount.
- RIFAMPICIN is special: it penetrates the STAPHYLOCOCCAL biofilm and intracellular bacteria well, so it is a key agent for staphylococcal implant infection - but it must ALWAYS be used in COMBINATION (never as monotherapy) because resistance to rifampicin develops rapidly; fluoroquinolones (good bone penetration) are common rifampicin partners for susceptible gram-negative/staph PJI.
- “Targets: cell wall (beta-lactams, vancomycin), ribosome (aminoglycosides/macrolides/clindamycin/linezolid/tetracyclines), DNA/RNA (fluoroquinolones, rifampicin), folate (TMP-SMX).
- “Resistance: enzyme (beta-lactamase), target modification (MRSA PBP2a/mecA, VRE vanA), efflux, reduced uptake; spread by plasmids.
- “Biofilm = TOLERANCE (not resistance): reduced penetration + persisters/small-colony variants → antibiotics alone fail → need SURGERY + antibiotics. Rifampicin penetrates staph biofilm (ALWAYS combination).
Overview & Clinical Relevance
Antibiotic pharmacology is examined as basic science but practised as orthopaedic decision-making. Three clinical problems recur throughout this topic.
Prophylaxis and empirical choice. Both depend on knowing which class hits which target, and which resistance mechanisms are circulating locally (MRSA, ESBL, resistant gram-negatives).
Implant-associated infection. This is a biofilm disease, and the distinction between genetic resistance and phenotypic tolerance is what explains its behaviour and decides its treatment.
Route and duration. Both have been transformed by trial evidence. Early oral switch (OVIVA) and rifampicin-combination therapy for stable-implant staphylococcal infection (Zimmerli) are now defensible standards rather than shortcuts.
Scope. This page covers class mechanisms, bactericidal versus bacteriostatic and concentration- versus time-dependent killing, the four resistance mechanisms, biofilm tolerance, and the toxicities that change surgical practice. Prophylaxis regimens, timing and the penicillin-allergy pathway are developed in Perioperative Antibiotics; treatment regimens, duration and the oral-versus-intravenous evidence in Orthopaedic Antibiotic Therapy; cement and beads in Local Antibiotic Delivery. Periprosthetic Joint Infection and Osteomyelitis cover the diseases this pharmacology serves, and the pharmacology that drives all of them sits here.
Antibiotic Classes & Mechanisms
Antibiotics work on four main bacterial targets.
Cell-wall synthesis. The beta-lactams (penicillins, cephalosporins, carbapenems) block the penicillin-binding proteins (transpeptidase). The glycopeptides (vancomycin, teicoplanin) bind the D-ala-D-ala terminus and are key for gram-positives and MRSA.
Protein synthesis. The ribosome is the target of the aminoglycosides (gentamicin: 30S, bactericidal, used in cement and beads), the macrolides, clindamycin, linezolid (for MRSA and VRE) and the tetracyclines.
DNA and RNA. Fluoroquinolones inhibit DNA gyrase, rifampicin inhibits RNA polymerase, and metronidazole covers anaerobes. Their bone penetration, oral absorption and, for rifampicin, biofilm penetration are taken up in the sections below.
Folate synthesis. Trimethoprim-sulfamethoxazole inhibits the folate pathway.
Two further agents for resistant gram-positive infection. Daptomycin is a cyclic lipopeptide that inserts into the membrane in a calcium-dependent manner and depolarises it. It is bactericidal against MRSA and VRE, and is classically inactivated by pulmonary surfactant, so it is never used for pneumonia. Fusidic acid blocks elongation factor G.
Resistance Mechanisms
Bacteria resist antibiotics by four mechanisms.
- Enzymatic inactivation. Beta-lactamases (penicillinases, extended-spectrum beta-lactamases or ESBL, carbapenemases) and aminoglycoside-modifying enzymes destroy the drug.
- Target modification. MRSA carries an altered penicillin-binding protein, PBP2a, encoded by mecA. VRE builds an altered cell-wall precursor, D-ala-D-lac, via vanA. A mutated DNA gyrase (fluoroquinolone resistance) or ribosome is target modification too.
- Reduced uptake. Gram-negatives lose outer-membrane porins, decreasing permeability.
- Efflux pumps. The drug is actively pumped out of the cell.
How resistance spreads. Resistance genes move between bacteria on plasmids and transposons (horizontal gene transfer). This is what produces MRSA, VRE, ESBL and multidrug-resistant gram-negatives, and it is why resistance is relevant to surgical prophylaxis and to the empirical treatment of infection.
Biofilm: The Orthopaedic Key
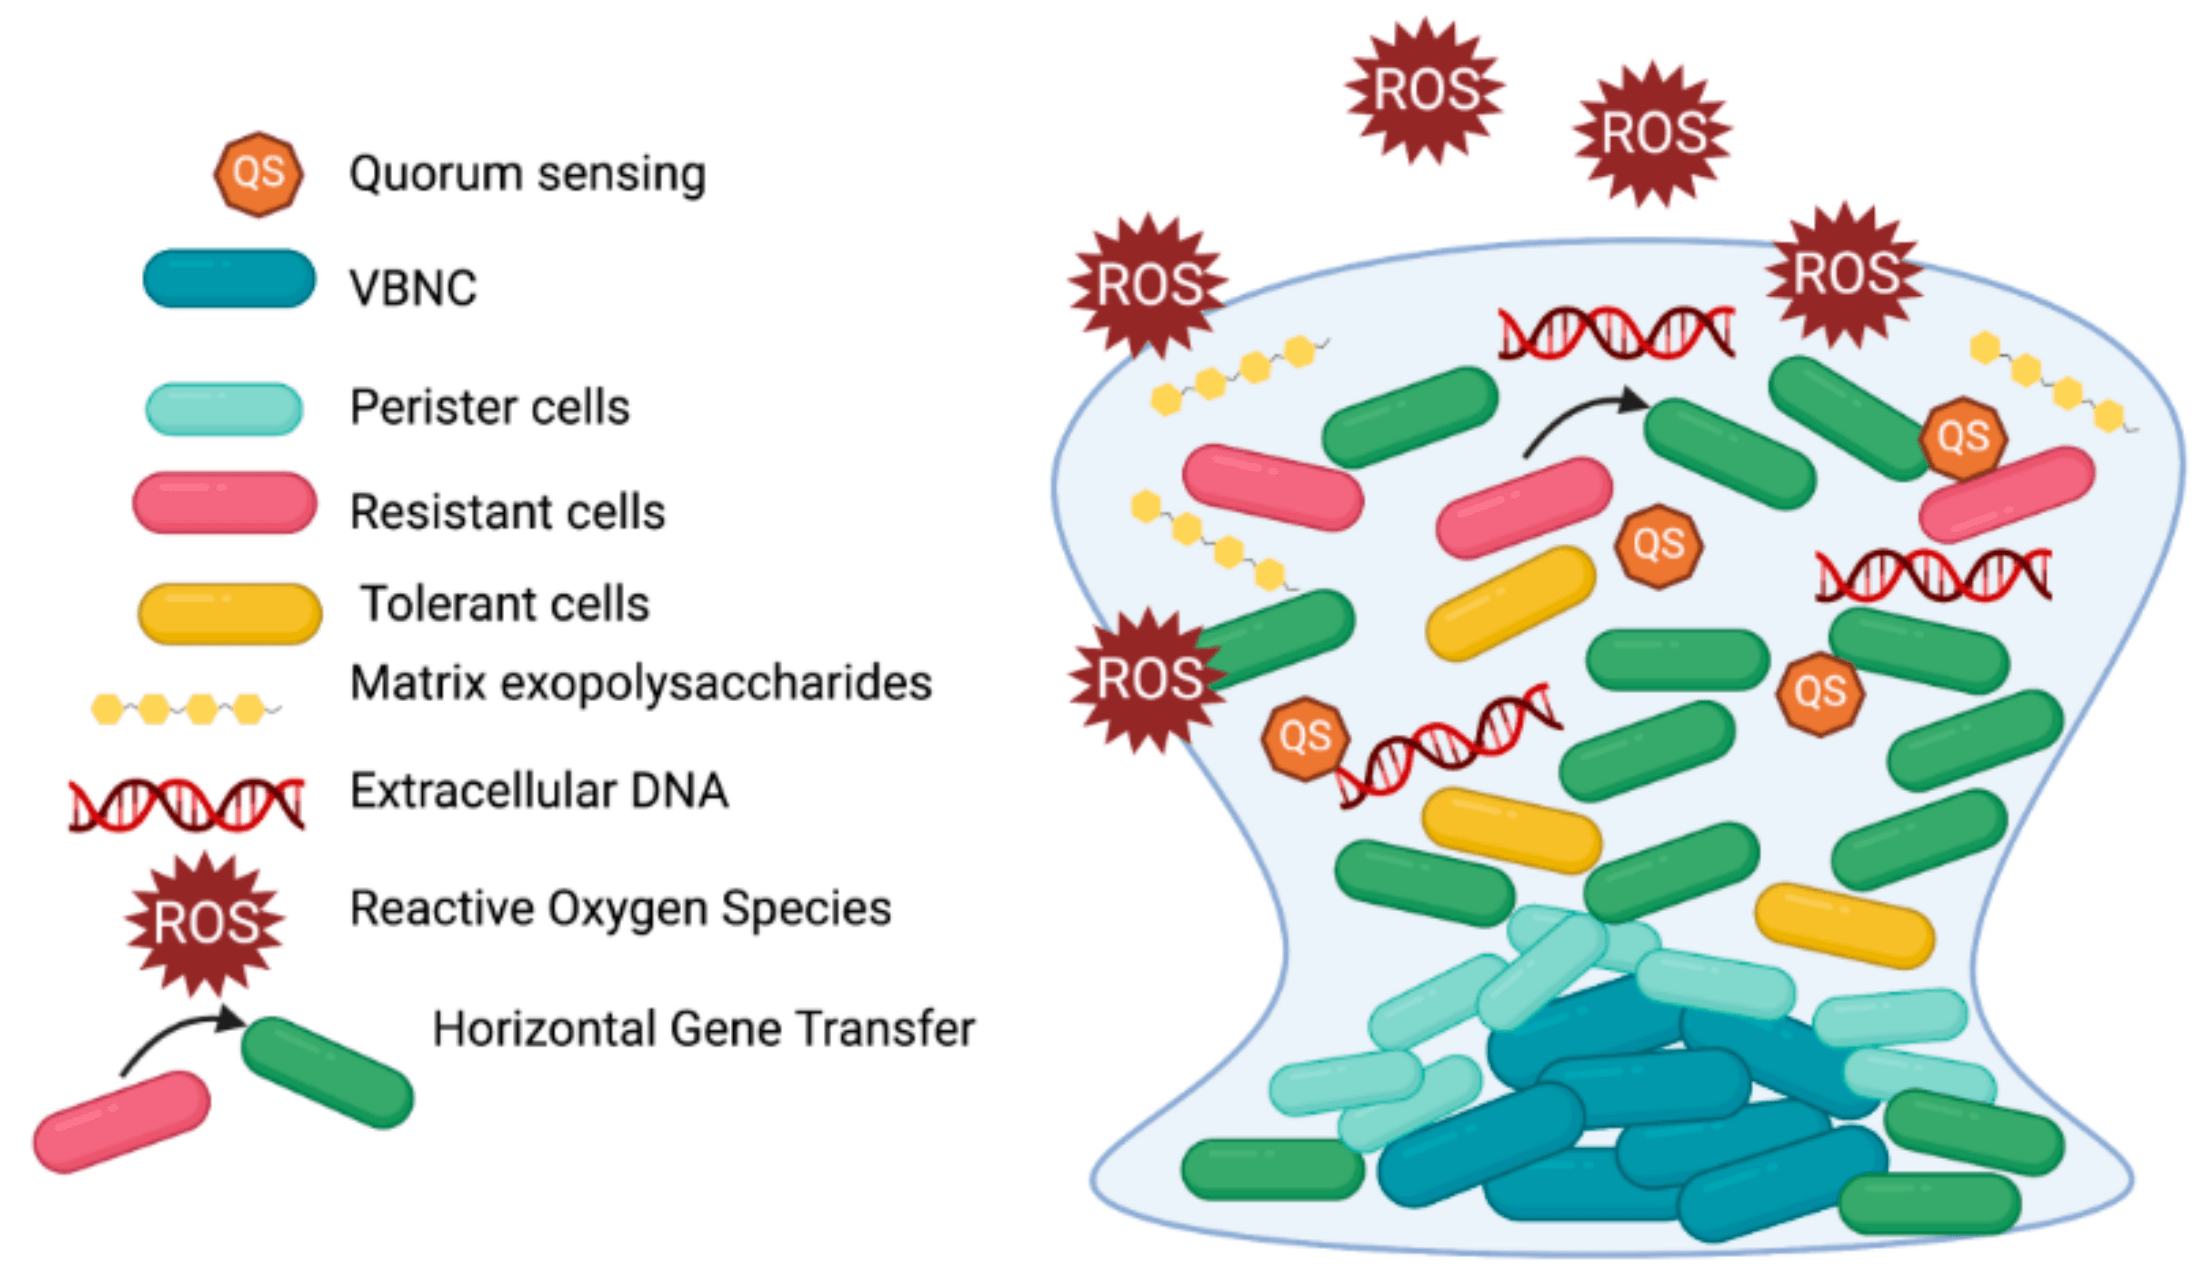
What a biofilm is. A structured community of bacteria adherent to a surface (an implant, or dead bone such as a sequestrum) within a self-produced extracellular matrix (glycocalyx). It causes antibiotic tolerance, a phenotypic, reversible survival that is distinct from genetic resistance.
How tolerance arises. The biofilm protects its bacteria through:
- Reduced antibiotic penetration into the matrix
- Slow-growing or dormant persister cells and small-colony variants that survive antibiotic exposure
- An altered local microenvironment
Why the laboratory report misleads. Tolerance is quantified by the MBEC (minimum biofilm eradication concentration), which may be hundreds to over a thousand times the MIC of the same organism grown planktonically. A report of "sensitive", derived from a planktonic MIC, says almost nothing about whether the drug will clear a biofilm.
Why implant infection needs surgery. Tolerance is the reason antibiotics alone fail to clear implant-associated infection, and the reason surgical source control (debridement and often implant removal) is essential, combined with antibiotics. Suppressive antibiotics may control, but rarely eradicate, biofilm infection when the implant is retained. Local delivery (gentamicin or vancomycin cement or beads) is used as an adjunct.
Rifampicin. Its penetration of the staphylococcal biofilm and of intracellular bacteria is excellent, which makes it a key agent for staphylococcal implant infection.
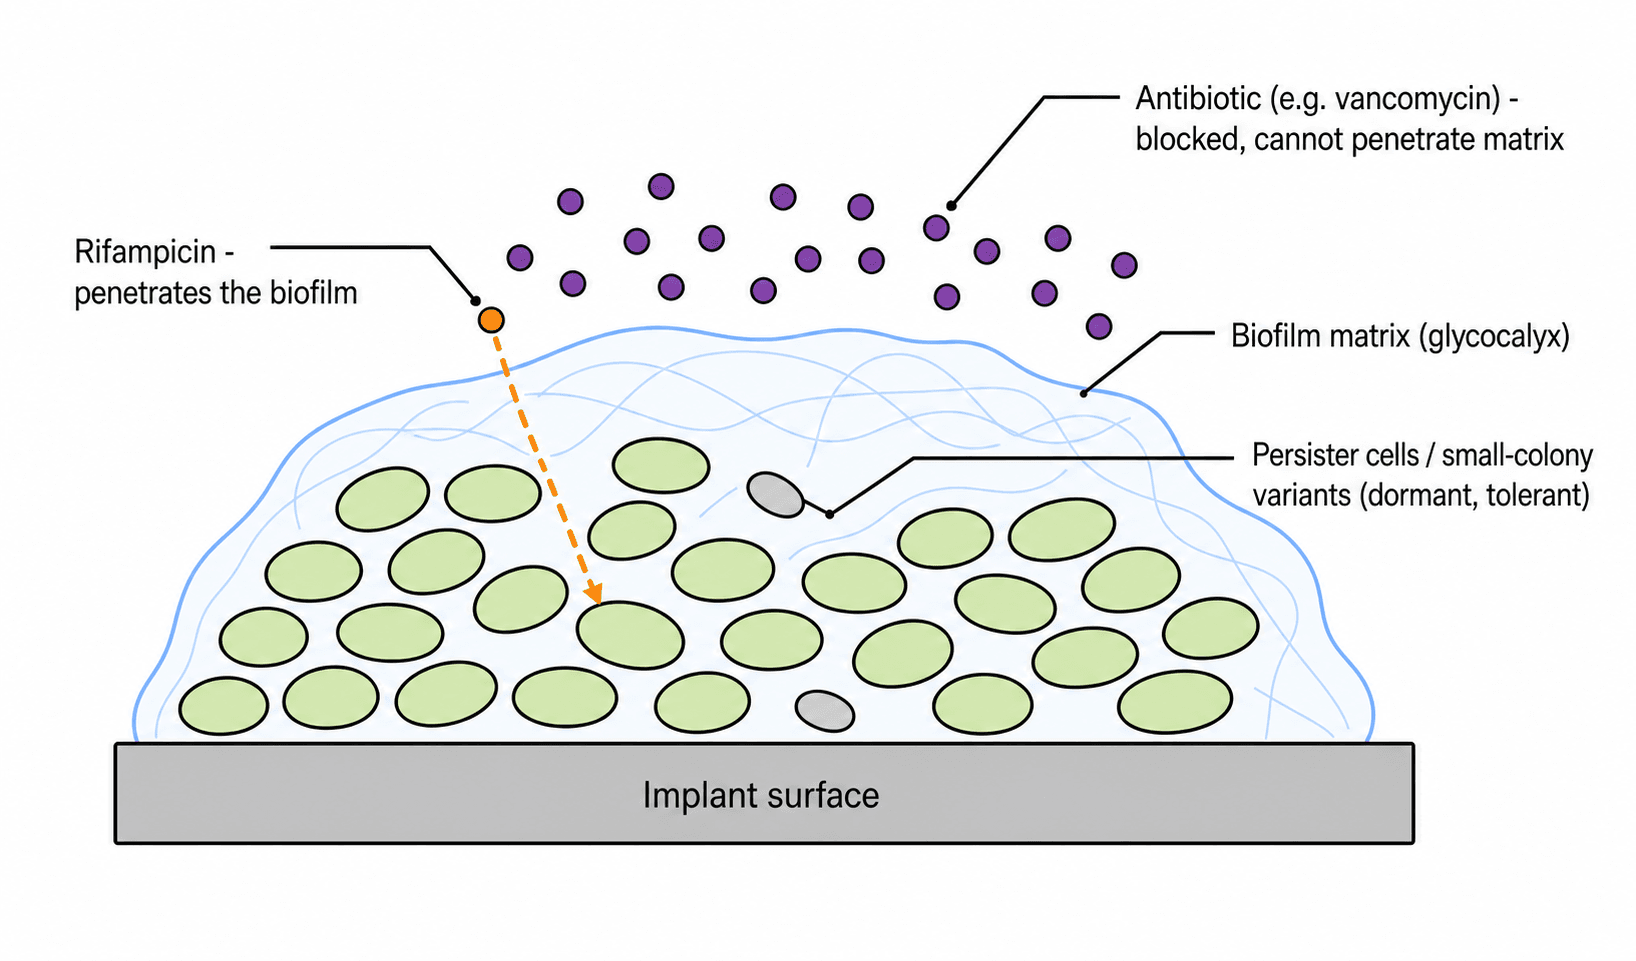
Two cardinal rules in implant infection. First, rifampicin is never used as monotherapy: resistance emerges rapidly, so it is always combined with another biofilm-relevant agent, commonly a fluoroquinolone for susceptible organisms. Second, antibiotics cannot 'sterilise' a mature biofilm on a foreign body: durable cure needs surgical debridement and (usually) implant removal or exchange alongside antibiotics.
Toxicities & Monitoring the Surgeon Must Know
These are the toxicities that change orthopaedic practice and require monitoring. The surgeon-facing high-yield ones are fluoroquinolone tendinopathy and the aminoglycoside and vancomycin toxicity that needs level monitoring.
- Fluoroquinolones. Tendinopathy and tendon rupture, classically the Achilles, highly relevant to the orthopaedic patient; also QT prolongation, dysglycaemia, C. difficile, and a cartilage/arthropathy caution in children (a relative contraindication in the growing patient).
- Aminoglycosides (gentamicin). Dose-related nephrotoxicity and ototoxicity (vestibular and cochlear), hence therapeutic drug monitoring; relevant to systemic use and to high local cement and bead loads.
- Vancomycin. Nephrotoxicity, and the rate-related "red man" infusion reaction, which is not a true allergy; hence level/AUC monitoring.
- Rifampicin. A potent hepatic enzyme inducer (drug interactions: it reduces warfarin, oral contraceptives and many other drugs), hepatotoxicity, and orange discolouration of secretions.
- Linezolid. With prolonged use, myelosuppression (thrombocytopenia), peripheral and optic neuropathy, and serotonin syndrome, as it is a weak MAO inhibitor.
- Clindamycin. The classic association with C. difficile colitis.
- Beta-lactams. Allergy and anaphylaxis, with a low penicillin-cephalosporin cross-reactivity.
PK/PD & Bone Penetration: Operationalising the Dosing
Two ways of classifying a drug. Drugs are classed as bactericidal or bacteriostatic, and as concentration-dependent (aminoglycosides, fluoroquinolones) or time-dependent (beta-lactams, glycopeptides) killers, which determines dosing. The MIC (minimum inhibitory concentration) and MBC (minimum bactericidal concentration) underpin "bactericidal versus bacteriostatic".
Concentration-dependent killing. It is optimised by a high peak relative to the MIC (Cmax/MIC) and by the AUC/MIC ratio. Aminoglycosides are therefore given as a high once-daily dose, which also exploits the post-antibiotic effect, and fluoroquinolones are dosed to AUC/MIC.
Time-dependent killing. It depends on the time the concentration stays above the MIC, so beta-lactams benefit from more frequent dosing or extended or continuous infusions. Vancomycin is dosed to an AUC/MIC target, now roughly 400-600, which has largely replaced trough-only monitoring because it tracks efficacy while limiting nephrotoxicity.
Bone penetration. Fluoroquinolones, clindamycin, rifampicin, linezolid and fusidic acid penetrate bone well, which makes them useful oral options for osteomyelitis, PJI and oral switch. Beta-lactams, and especially glycopeptides (vancomycin), penetrate bone relatively poorly. This informs agent and route choice, and explains the appeal of bone-penetrating oral agents.
Oral bioavailability. This is why an oral switch is possible at all. Fluoroquinolones, linezolid, metronidazole and fusidic acid approach near-complete oral bioavailability, and clindamycin and rifampicin are well absorbed too. For these drugs the oral route achieves serum concentrations close to intravenous, so an oral regimen is a pharmacological equivalent rather than a compromise.
Vancomycin is the exception. It is not absorbed orally at all: oral vancomycin treats C. difficile within the gut lumen and has no systemic activity whatever.
Redosing. Intra-operative redosing is a pharmacokinetic decision driven by half-life. A further dose is due once the operation exceeds roughly two half-lives of the agent, or after major blood loss, because the aim is a tissue concentration above the MIC for the whole time the wound is open. Obesity raises the volume of distribution and is the usual reason a standard dose under-doses.
Synergy. Some combinations kill better than either agent alone, classically a beta-lactam (or vancomycin) plus an aminoglycoside in enterococcal infection, where cell-wall disruption lets the aminoglycoside reach its ribosomal target.
Reading a Susceptibility Report, and Stewardship
The microbiology report is where pharmacology meets the ward round, and it is routinely over-interpreted.
"Sensitive" is a planktonic statement. Breakpoints (S/I/R) are set against a planktonic MIC and a set of assumptions about achievable serum concentration at a standard dose. They say nothing about whether the drug reaches bone, and nothing about a biofilm on an implant, which is precisely why an organism reported sensitive to vancomycin can persist on a prosthesis. Read the report alongside the site of infection and whether a foreign body is present.
"Intermediate" is usually a dosing statement. It is not a prohibition: it generally means the agent may work at a higher dose or where the drug concentrates.
Sample before antibiotics. Antibiotics given before deep samples are taken substantially reduce culture yield, and are a common reason for a culture-negative bone or joint infection. Unless the patient is septic, hold antibiotics until adequate deep samples, usually multiple, have been obtained.
Selective pressure and collateral damage. Every course selects resistance in the patient's own flora. Clindamycin, fluoroquinolones and broad-spectrum cephalosporins carry the strongest association with C. difficile, and broad gram-negative cover selects ESBL and resistant Pseudomonas. Choosing the narrowest effective agent is a clinical decision, not an administrative one.
Stewardship. In orthopaedic terms it means:
- Prophylaxis is a single perioperative course, not a post-operative drip continued "until the drains are out"
- Empirical therapy is de-escalated once cultures return
- Duration is defined at the outset rather than open-ended
- The oral switch is taken as soon as the agent's bioavailability and bone penetration allow
Mnemonics & Memory Aids
WRDF (targets)
Hook:Antibiotic targets = Wall, Ribosome, DNA/RNA, Folate (WRDF).
TREE (resistance)
Hook:Resistance grows on the TREE: Target, Reduced uptake, Enzyme, Efflux - spread by plasmids.
MCQ Practice Points
Q: A patient with an MRSA prosthetic joint infection is started on vancomycin. By what mechanism does it act, and what is the resistance mechanism in VRE? A: Vancomycin binds the D-ala-D-ala terminus of the cell-wall precursor, blocking transpeptidation. VRE substitutes D-ala-D-lac (via the vanA operon), collapsing glycopeptide binding affinity. MRSA resistance is different again - an altered penicillin-binding protein, PBP2a, encoded by mecA.
Q: Why must rifampicin never be used as monotherapy against an implant infection, and what evidence supports its role? A: Rifampicin resistance emerges rapidly by rpoB mutation when used alone, so it is always combined (classically with a fluoroquinolone). Its role rests on its biofilm and intracellular penetration and on the Zimmerli 1998 RCT: ciprofloxacin-rifampin cured 12/12 versus 7/12 with ciprofloxacin-placebo in debrided, stable-implant staphylococcal infection.
Q: Is prolonged intravenous therapy required for bone and joint infection? A: No - OVIVA (NEJM 2019, n=1,054) showed oral therapy noninferior to IV for the first 6 weeks (failure 13.2% vs 14.6%), with fewer catheter complications. The pharmacological basis is the near-complete oral bioavailability and good bone penetration of agents such as fluoroquinolones, linezolid and rifampicin.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“Classify antibiotics by mechanism, and explain the main mechanisms of bacterial resistance.”
“What is biofilm, and why does it mean an infected implant usually cannot be cured by antibiotics alone?”
Classes by target
- Cell wall: beta-lactams (PBPs), glycopeptides (vancomycin - D-ala-D-ala)
- Ribosome: aminoglycosides, macrolides, clindamycin, linezolid, tetracyclines
- DNA/RNA: fluoroquinolones (gyrase), rifampicin (RNA pol), metronidazole; folate: TMP-SMX
Killing
- Bactericidal (beta-lactams, glycopeptides, aminoglycosides, fluoroquinolones, rifampicin) vs bacteriostatic
- Concentration-dependent (aminoglycosides, fluoroquinolones)
- Time-dependent (beta-lactams, glycopeptides)
Resistance
- Enzymatic (beta-lactamases/ESBL/carbapenemases)
- Target modification (MRSA mecA/PBP2a; VRE vanA; gyrase mutation)
- Reduced uptake (porin loss); efflux pumps; spread by plasmids
Biofilm (orthopaedic key)
- Matrix on implant → tolerance (reduced penetration, persisters, small-colony variants)
- Antibiotics alone FAIL → surgical debridement/implant removal + antibiotics
- Rifampicin penetrates staph biofilm (ALWAYS combination); use bone-penetrating agents + local delivery
Evidence & Key Studies
Tolerant Small-colony Variants Form Prior to Resistance Within a Staphylococcus aureus Biofilm Based on Antibiotic Selective Pressure
- In periprosthetic joint infection, bacteria survive antibiotics through biofilm-mediated TOLERANCE, resistance and persistence - antibiotics in isolation are typically ineffective.
- Rifampicin penetrates the S. aureus biofilm whereas vancomycin penetrates poorly; tolerant small-colony variants emerge under antibiotic selective pressure.
- Biofilm-mediated tolerance explains why treatments relying on antibiotics to clear residual biofilm fail - reinforcing the need for surgical source control.
Comparison of Staphylococcus aureus tolerance between antimicrobial blue light, levofloxacin, and rifampin
- Antimicrobial efficacy differs markedly between planktonic and biofilm phenotypes of S. aureus (ATCC 6538) for levofloxacin, rifampin and antimicrobial blue light (aBL).
- aBL showed the largest planktonic-versus-biofilm efficacy disparity (a 2.5 log10 unit difference); levofloxacin efficacy plateaued against biofilm as dosage increased.
- Studied on an osseointegrated percutaneous implant model - the bacterial phenotype (biofilm) is a key determinant of treatment efficacy.
Role of rifampin for treatment of orthopedic implant-related staphylococcal infections: a randomized controlled trial
- Randomised, placebo-controlled, double-blind trial of 33 patients with culture-proven staphylococcal infection of stable orthopaedic implants, all debrided, with short symptom duration.
- Of the 24 who completed the protocol, cure was 12 of 12 (100%) with ciprofloxacin-rifampin versus 7 of 12 (58%) with ciprofloxacin-placebo (P=.02) at ~3 years.
- Nine patients dropped out (6 adverse events); 7 of 9 were subsequently treated with rifampin combinations and 5 cured without implant removal.
Oral versus Intravenous Antibiotics for Bone and Joint Infection (OVIVA)
- 1,054 adults with bone or joint infection at 26 UK centres, randomised within 7 days of surgery to IV versus oral antibiotics for the first 6 weeks.
- Definitive treatment failure at 1 year: 14.6% IV versus 13.2% oral - oral noninferior (difference -1.4 percentage points, 90% CI -4.9 to 2.2; margin 7.5).
- Catheter complications were more common with IV therapy (9.4% vs 1.0%); serious adverse events did not differ.
Therapeutic monitoring of vancomycin for serious MRSA infections: revised consensus guideline (ASHP/IDSA/PIDS/SIDP)
- Recommends AUC-guided vancomycin dosing and monitoring for serious MRSA infection, targeting an AUC/MIC of 400-600 (assuming a broth microdilution MIC of 1 mg/L).
- AUC-guided monitoring largely replaces trough-only targets because it maintains efficacy while reducing nephrotoxicity.
- Trough-only monitoring is no longer recommended for serious MRSA infections in adults.
The central role of biofilm-mediated tolerance (with persister cells/small-colony variants) in periprosthetic joint infection, and rifampicin's biofilm penetration versus vancomycin's poor penetration, come from the cited Manasherob study, and the planktonic-versus-biofilm efficacy difference from the cited Ong study. The antibiotic-class mechanisms, bactericidal/bacteriostatic and concentration-/time- dependent killing, and the four resistance mechanisms (including MRSA mecA and VRE vanA) are standard, well-established pharmacology. (See also our Periprosthetic Joint Infection, Osteomyelitis, Local Antibiotic Delivery and Septic Arthritis topics.)