C1-C2 Degeneration | Occipitocervical Pain | Rotatory Loss | C1-C2 Fusion
- C1-C2 provides 50% of cervical rotation - arthritis causes profound functional loss
- Rheumatoid arthritis is most common inflammatory cause (30-40% prevalence)
- ADI over 3.5mm in adults = transverse ligament incompetence = instability
- SAC under 13mm = high myelopathy risk = surgical threshold
- Harms technique (C1 lateral mass + C2 pedicle screws) is gold standard fusion
- “Atlantoaxial joint: 50% rotation, 10% flexion-extension contribution
- “Transverse ligament is primary stabiliser - RA pannus causes erosion
- “Dynamic flexion-extension radiographs essential for diagnosis
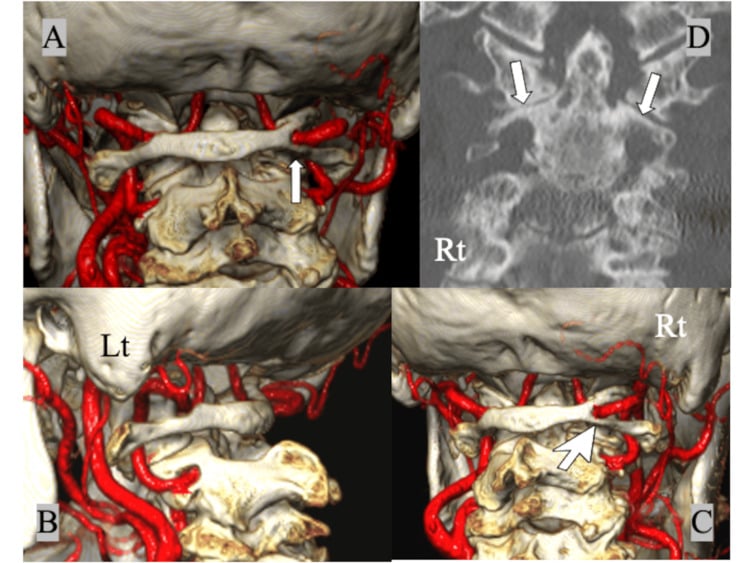
- “Vertebral artery runs lateral to C1 lateral mass and through C2 pedicle
Overview and Epidemiology
Atlantoaxial arthritis is degenerative or inflammatory change in the C1-C2 articulation. The joint is unusual: it provides approximately 50% of total cervical rotation and 10% of flexion-extension, yet bears minimal axial load. That high-mobility, low-load environment makes primary osteoarthritis uncommon, and inflammatory arthritis, especially rheumatoid, is the predominant aetiology.
Deep dive. This page covers the atlantoaxial pathology (degenerative and rheumatoid involvement, instability, Crowned Dens, the Ranawat classification). For the operative technique — indications, vertebral-artery anatomy, and the Magerl-versus-Goel-Harms decision — see atlantoaxial C1-C2 fusion.
Who gets it. Rheumatoid arthritis accounts for 80% of inflammatory atlantoaxial disease, and 30-40% of patients with RA develop C1-C2 involvement. Rheumatoid cases follow the onset of systemic disease and affect women twice as often as men (2:1). Degenerative disease peaks at 60-70 years; primary osteoarthritis is uncommon, and secondary degeneration follows odontoid fracture nonunion or os odontoideum.
What it costs the patient. A deficit of up to 50% of cervical rotation impairs daily activities such as driving and checking blind spots. Three further figures are conventional teaching estimates rather than measured rates from a single defined cohort:
- Chronic occipitocervical pain in 90% of symptomatic cases
- Spinal cord compression (myelopathy) in 5-10% without treatment
- Fusion required in 15-20% of patients with rheumatoid atlantoaxial disease
The measured figures on this page are the 30-40% rate of rheumatoid atlantoaxial involvement and the series outcomes in the Evidence section.
Anatomy
The joints. C1 and C2 meet at three synovial joints: the median atlantoaxial joint, between the odontoid process (the dens of C2) and the anterior arch of C1, and the paired lateral atlantoaxial joints, between the inferior facets of C1 and the superior facets of C2. Posteriorly, the posterior membrane connects the posterior arch of C1 to the C2 lamina.
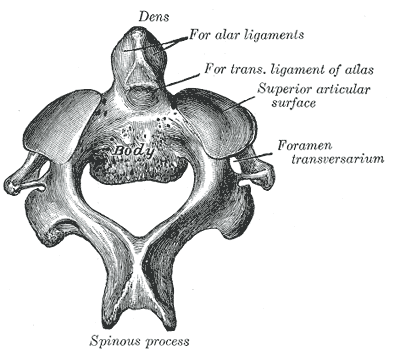
The ligaments. The transverse ligament is the primary stabiliser. It spans the C1 lateral masses behind the dens and prevents anterior translation of C1. The paired alar ligaments connect the dens to the occipital condyles and limit rotation and lateral flexion; the apical ligament runs from the dens tip to the foramen magnum and has only a minimal stabilising role.
Motion. The odontoid process is the central axis about which C1 rotates, 45 degrees to each side. Flexion-extension totals 10 degrees, and lateral flexion is minimal and coupled with rotation.
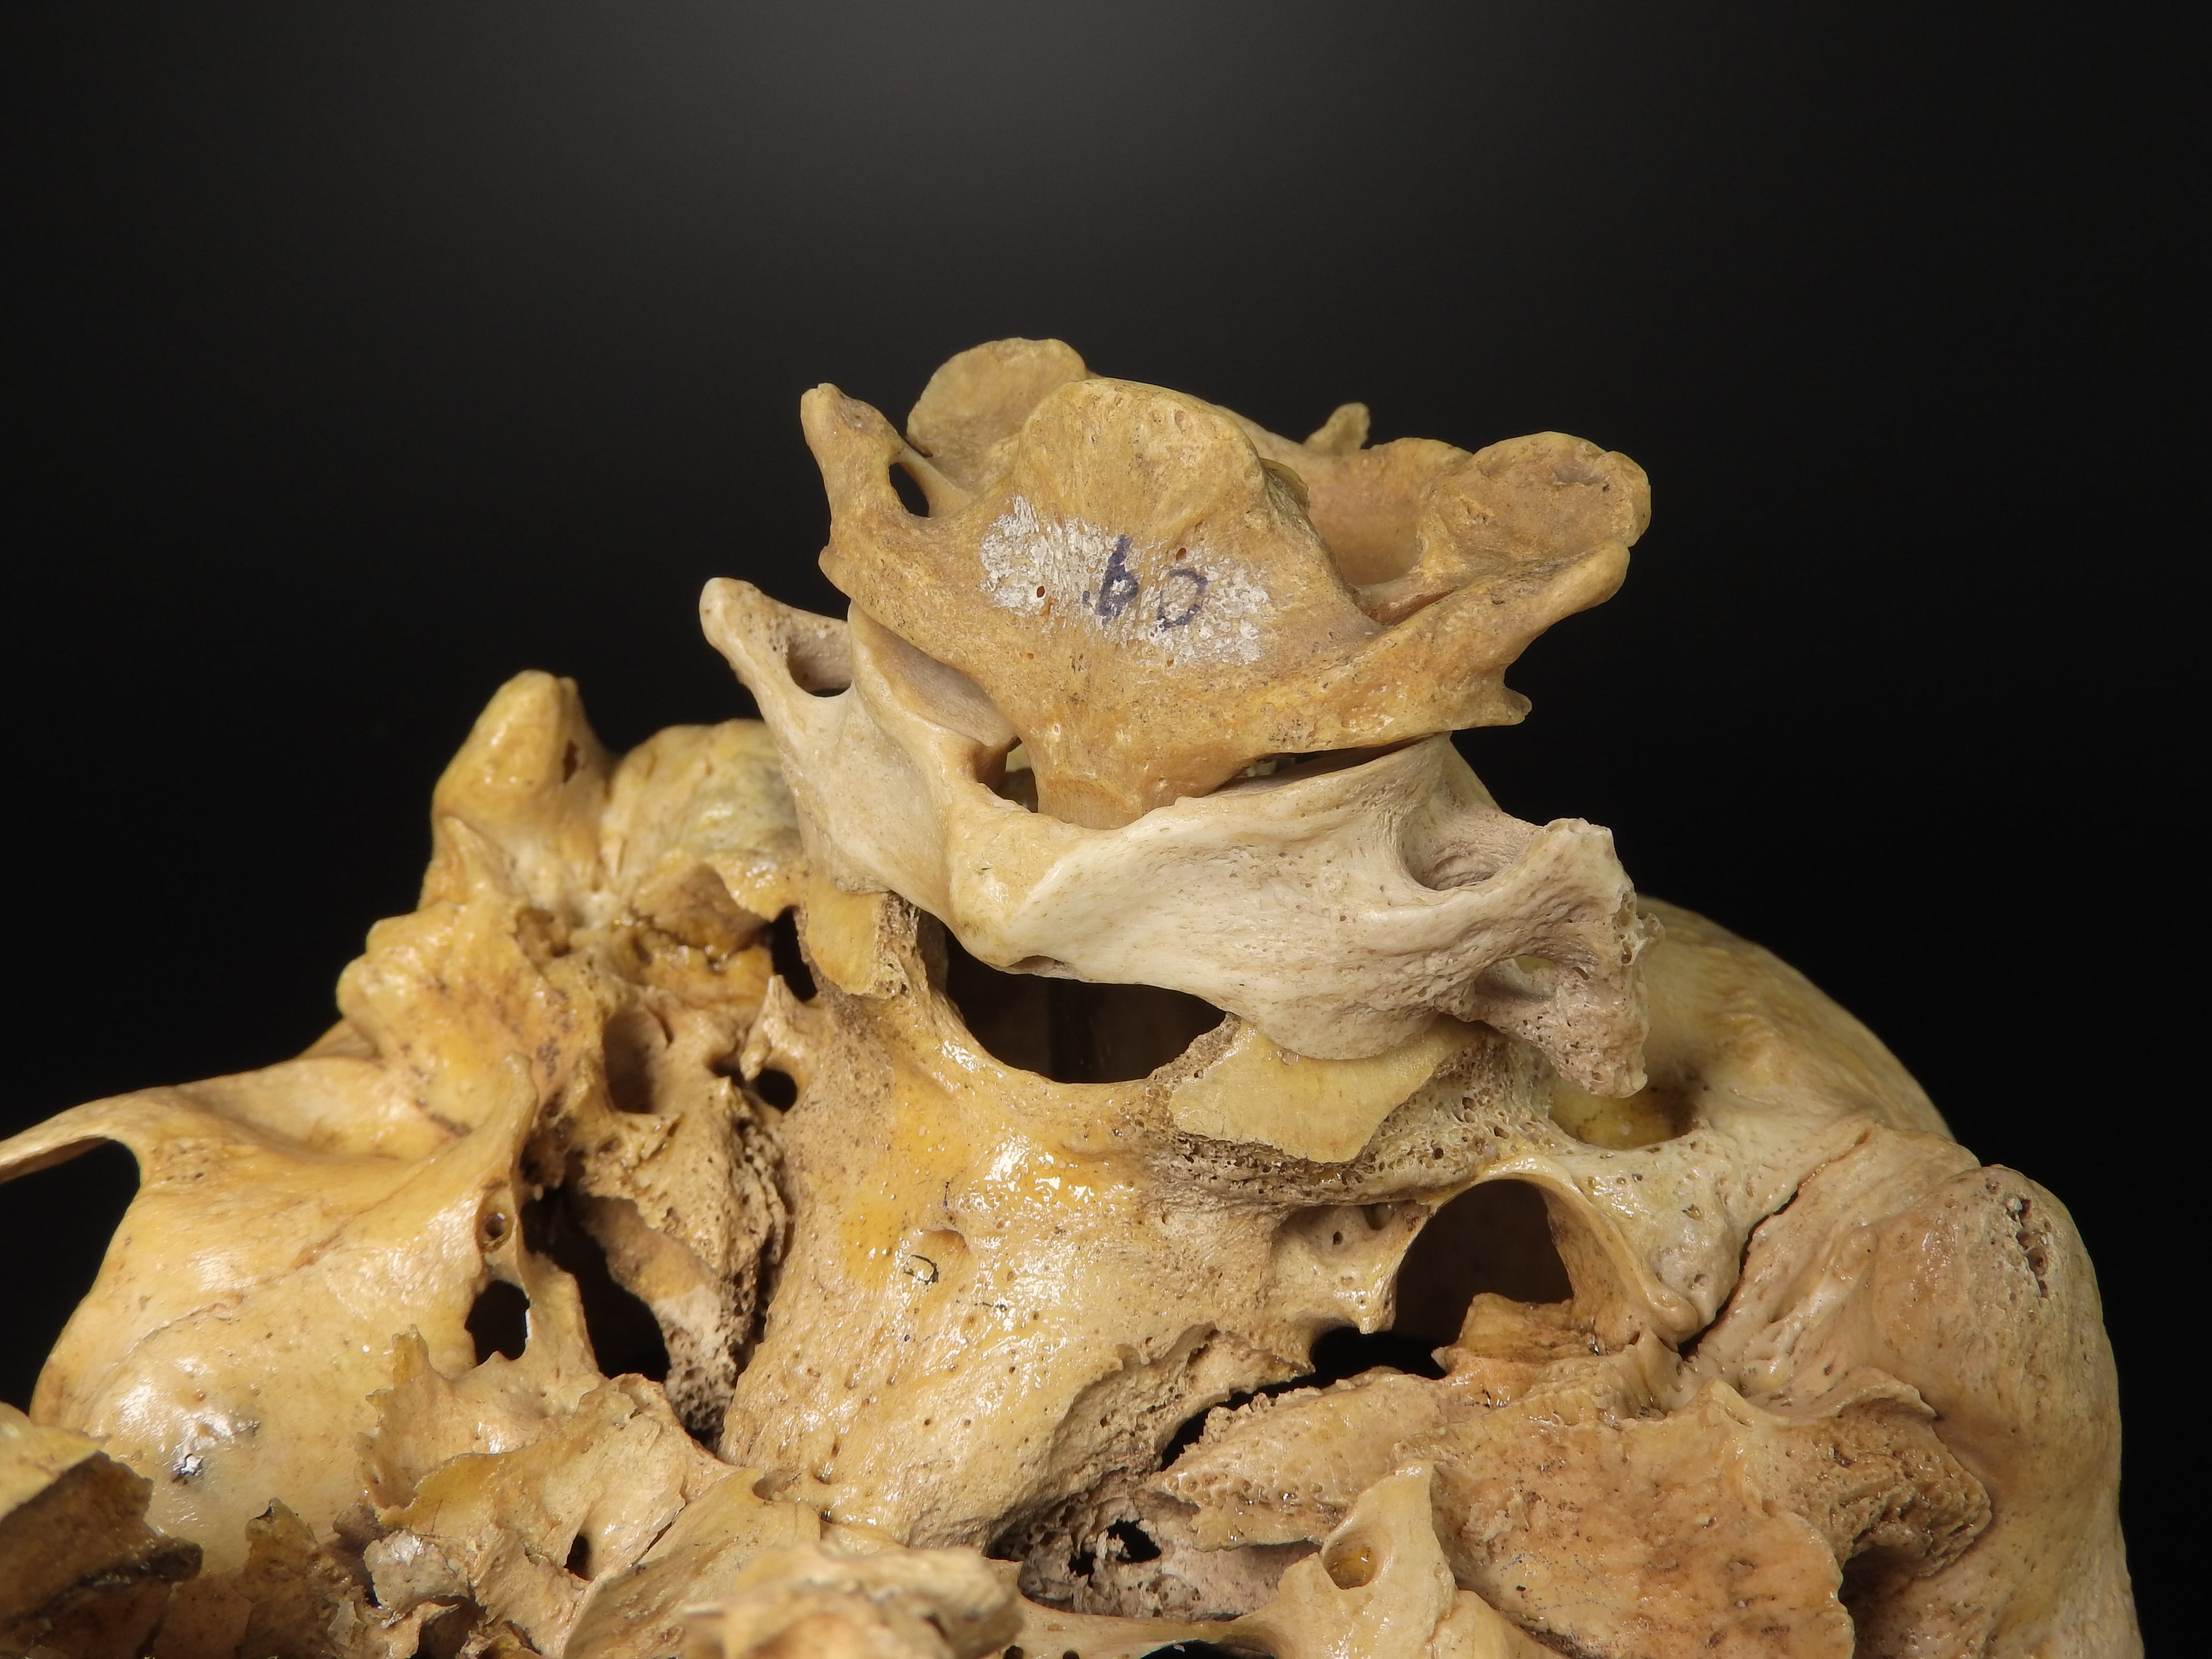
The vertebral artery. The vertebral arteries run lateral to the C1 lateral masses and through the C2 pedicles, so screw fixation requires precise trajectories.
Pathophysiology
Degenerative disease. When the joint does degenerate, the change typically affects the lateral atlantoaxial facet joints, where rotatory shear erodes the cartilage. The sequence:
- Cartilage degradation: repetitive rotatory shear causes chondrocyte dysfunction and matrix breakdown
- Subchondral sclerosis: loss of cartilage protection leads to bony eburnation
- Marginal osteophytes at the joint margins
- Joint space narrowing as cartilage loss progresses
- Secondary instability: advanced degeneration may lead to ligamentous laxity
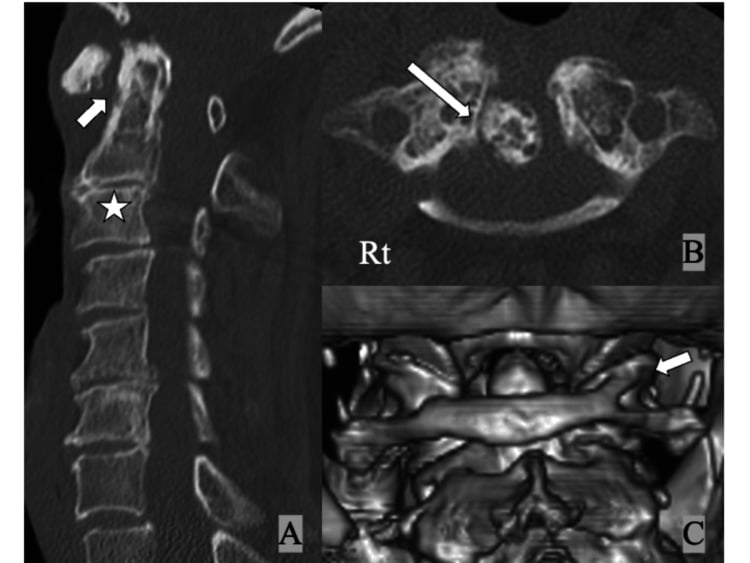
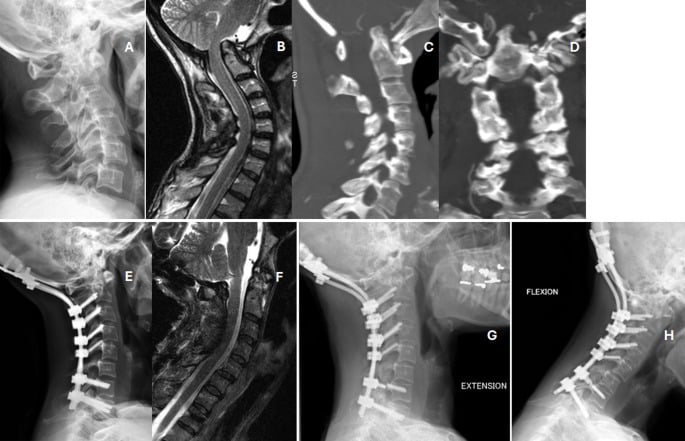
Rheumatoid disease. Pannus forms within the atlantoaxial synovial joints and erodes the transverse ligament directly, along with the cartilage and subchondral bone of the lateral atlantoaxial facets. Failure of the transverse ligament allows C1 to translate anteriorly and the ADI to widen. Collapse of the lateral masses allows the odontoid to migrate superiorly into the foramen magnum, and either path can end in neural compression.
The rheumatoid atlantoaxial patterns:
- Anterior subluxation (60%) - transverse ligament erosion; the most common presentation
- Vertical migration (30%) - lateral mass collapse allows the odontoid to migrate into the foramen magnum (basilar invagination)
- Posterior subluxation (10%) - odontoid erosion allows C1 to translate posteriorly
- Lateral subluxation - asymmetric lateral mass erosion causes rotatory deformity
Below the axis, subaxial subluxation produces the C3-C7 staircase deformity.
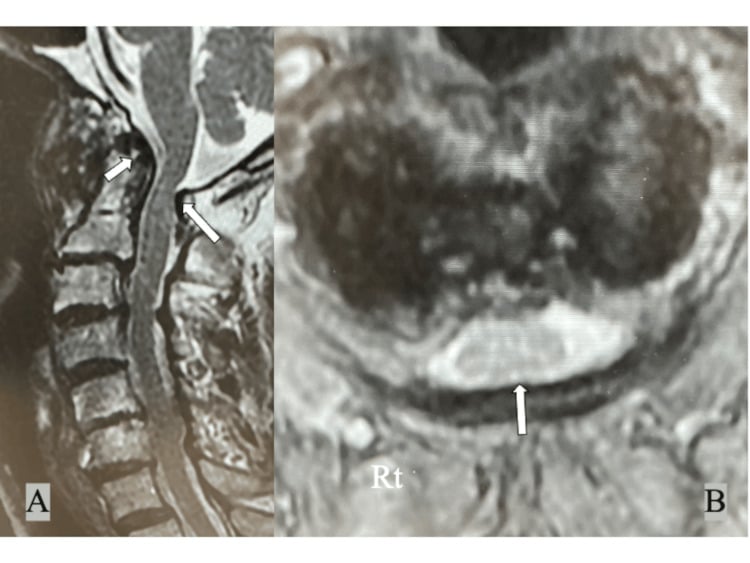
Neurological consequences. Instability threatens the cord in two ways. Compression is dynamic when flexion increases the ADI and compresses the cord intermittently, and static when vertical migration compresses the brainstem persistently. The cervicomedullary junction is particularly vulnerable: compression there affects the respiratory centres, upper motor neuron pathways and posterior column function.
The atlantoaxial complex is immediately adjacent to the cervicomedullary junction. Posterior subluxation or superior odontoid migration can directly compress the brainstem, causing respiratory compromise and quadriplegia.
Classification Systems
- Rotatory Position
- Rotatory fixation without anterior shift
- ADI
- Under 3mm
- Management
- Conservative or C1-C2 fusion if chronic
- Rotatory Position
- Rotatory fixation with anterior subluxation
- ADI
- 3-5mm
- Management
- C1-C2 fusion recommended
- Rotatory Position
- Rotatory fixation with significant anterior shift
- ADI
- Over 5mm
- Management
- Occiput-C2 fusion
- Rotatory Position
- Posterior atlantoaxial subluxation
- ADI
- Variable
- Management
- Occiput-C2 fusion
Fielding and Hawkins (J Bone Joint Surg Am 1977) described this classification for atlantoaxial rotatory fixation. Note the eponym trap: Grisel syndrome, post-inflammatory atlantoaxial rotatory subluxation in children after pharyngitis or ENT surgery, is a cause of rotatory fixation, not the name of this four-type classification.
Clinical Presentation
History. Occipitocervical pain radiates to the vertex and is worse with rotation, and the loss of rotation is progressive: the patient has difficulty turning the head to look sideways. Look also for:
- Clicking or clunking with head rotation
- Paraesthesia in the C2 distribution
- Gait instability if myelopathic
- Red flags of brainstem compression: bowel or bladder dysfunction, drop attacks, dysphagia
Examination.
- Look: head fixed in rotation, the cock-robin position if there is rotatory subluxation
- Move: rotation reduced to under 45 degrees in each direction, with pain at the extremes
- Feel: tenderness over C1-C2, 2cm below the occiput
- Neurology: upper motor neuron signs if myelopathic (hyperreflexia, Hoffmann sign, Babinski, gait ataxia)
- Sharp-Purser test: anterior C1 translation with head flexion; now rarely used
Progressive myelopathy from atlantoaxial instability is insidious: hand clumsiness, gait imbalance, hyperreflexia. Once established, it may not fully reverse after fusion. Urgent surgical consultation if the SAC is under 13mm or neurological signs are present.
- Discriminating Features
- Occipitocervical pain, rotation loss, RA history; UMN signs if myelopathic
- Key Investigation
- Dynamic lateral radiographs (ADI), CT, MRI (SAC, pannus)
- Discriminating Features
- Fixed cock-robin torticollis, often paediatric or post-pharyngitis/ENT surgery
- Key Investigation
- Dynamic CT in rotation (fixed C1 on C2)
- Discriminating Features
- Painless or post-traumatic instability, mobile ossicle separate from C2 body
- Key Investigation
- CT (dens morphology), flexion-extension radiographs
- Discriminating Features
- Acute severe neck pain, fever, raised inflammatory markers in the elderly
- Key Investigation
- CT showing calcification around the dens; responds to NSAIDs/colchicine
- Discriminating Features
- Subaxial degeneration, no instability, normal ADI
- Key Investigation
- MRI/CT showing subaxial rather than C1-C2 pathology
- Discriminating Features
- Night pain, constitutional symptoms, destructive lesion
- Key Investigation
- MRI with contrast, CT for bony destruction
Crowned Dens Syndrome: Crystal Arthritis of the C1-C2 Region
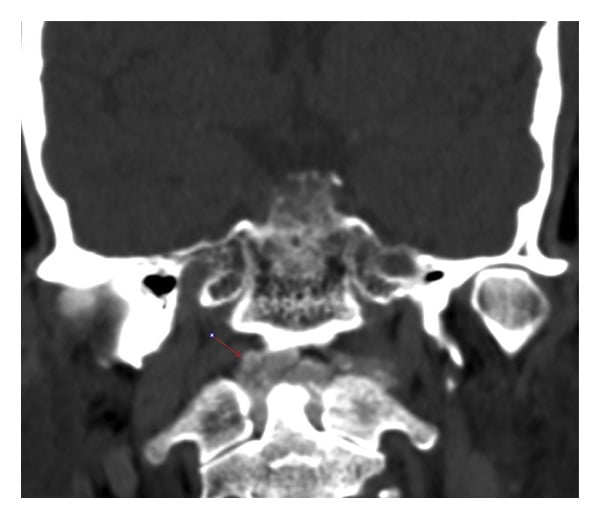
Crowned dens syndrome is the crystalline form of atlantoaxial arthritis and the classic acute mimic that catches the unwary. Calcium pyrophosphate dihydrate (CPPD), and less commonly basic calcium phosphate or hydroxyapatite, is deposited in the ligaments encircling the odontoid (the transverse and alar ligaments and the peri-odontoid tissues), producing a "crown" or "halo" of calcification around the dens on CT.
The patient. Typically an older adult, often female, with acute or subacute severe upper neck and occipital pain, marked stiffness and painfully restricted rotation. Low-grade fever and markedly raised CRP and ESR make it a convincing mimic of meningitis, giant cell arteritis, polymyalgia rheumatica, pseudogout elsewhere, or septic or infective arthritis of the craniovertebral junction. There is often a history of CPPD or chondrocalcinosis at other joints (knee, wrist, symphysis).
Fever, neck stiffness and high inflammatory markers mean crowned dens syndrome is frequently misdiagnosed as meningitis or septic arthritis, leading to unnecessary lumbar puncture, prolonged antibiotics, or even surgery. Recognising it spares the patient invasive work-up and gives rapid relief with anti-inflammatory treatment.
Diagnosis. CT is the key investigation, showing crown- or halo-shaped calcification around the odontoid, best appreciated on axial and coronal reconstructions. Plain radiographs and MRI frequently miss the calcification; MRI shows non-specific peri-odontoid soft-tissue change or oedema, so a normal MRI does not exclude the diagnosis. There is no true instability: the ADI is normal and dynamic films are stable, which distinguishes it from rheumatoid or degenerative atlantoaxial disease.
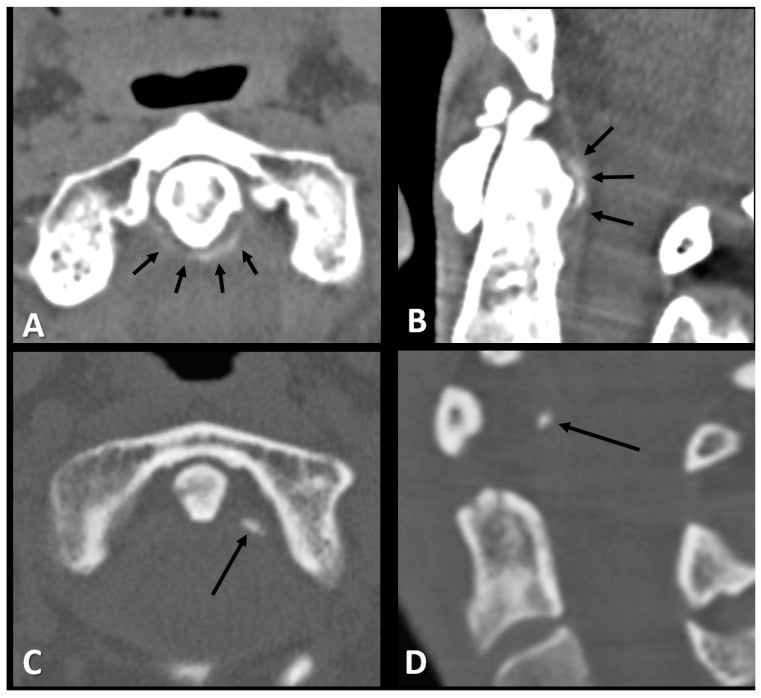
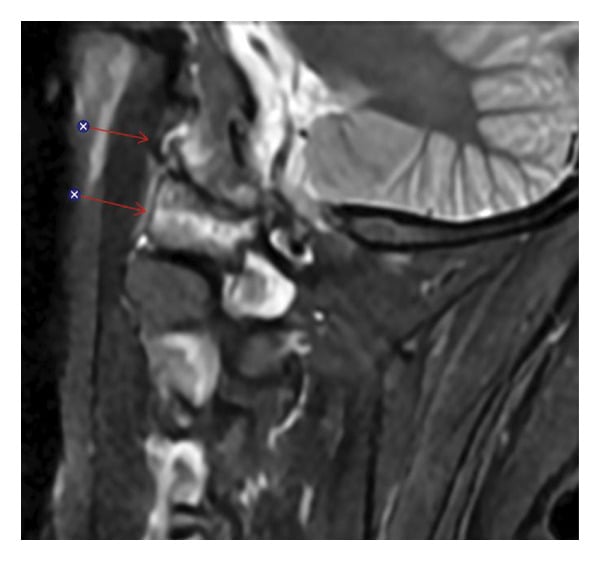
Management is medical, not surgical. The syndrome is self-limiting and responds rapidly to NSAIDs, colchicine, or a short course of low-dose corticosteroids, usually settling within days to a couple of weeks. Fusion has no role; the value of the diagnosis is precisely that it converts an alarming surgical or infective presentation into a treatable crystal arthropathy.
Investigations
Radiographs come first:
- AP and lateral cervical spine - atlantoaxial alignment and the ADI
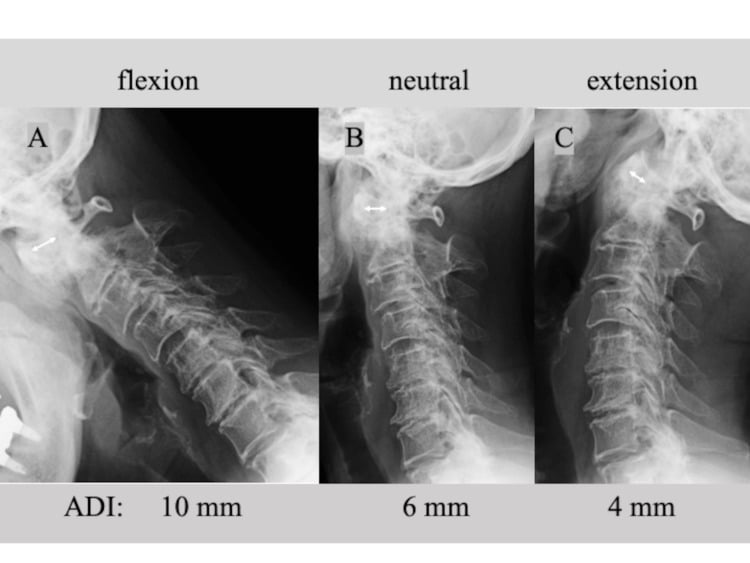
- Flexion-extension laterals - dynamic instability
- Open-mouth odontoid - lateral mass symmetry and dens integrity
In rheumatoid arthritis, annual flexion-extension cervical radiographs are mandatory for screening.
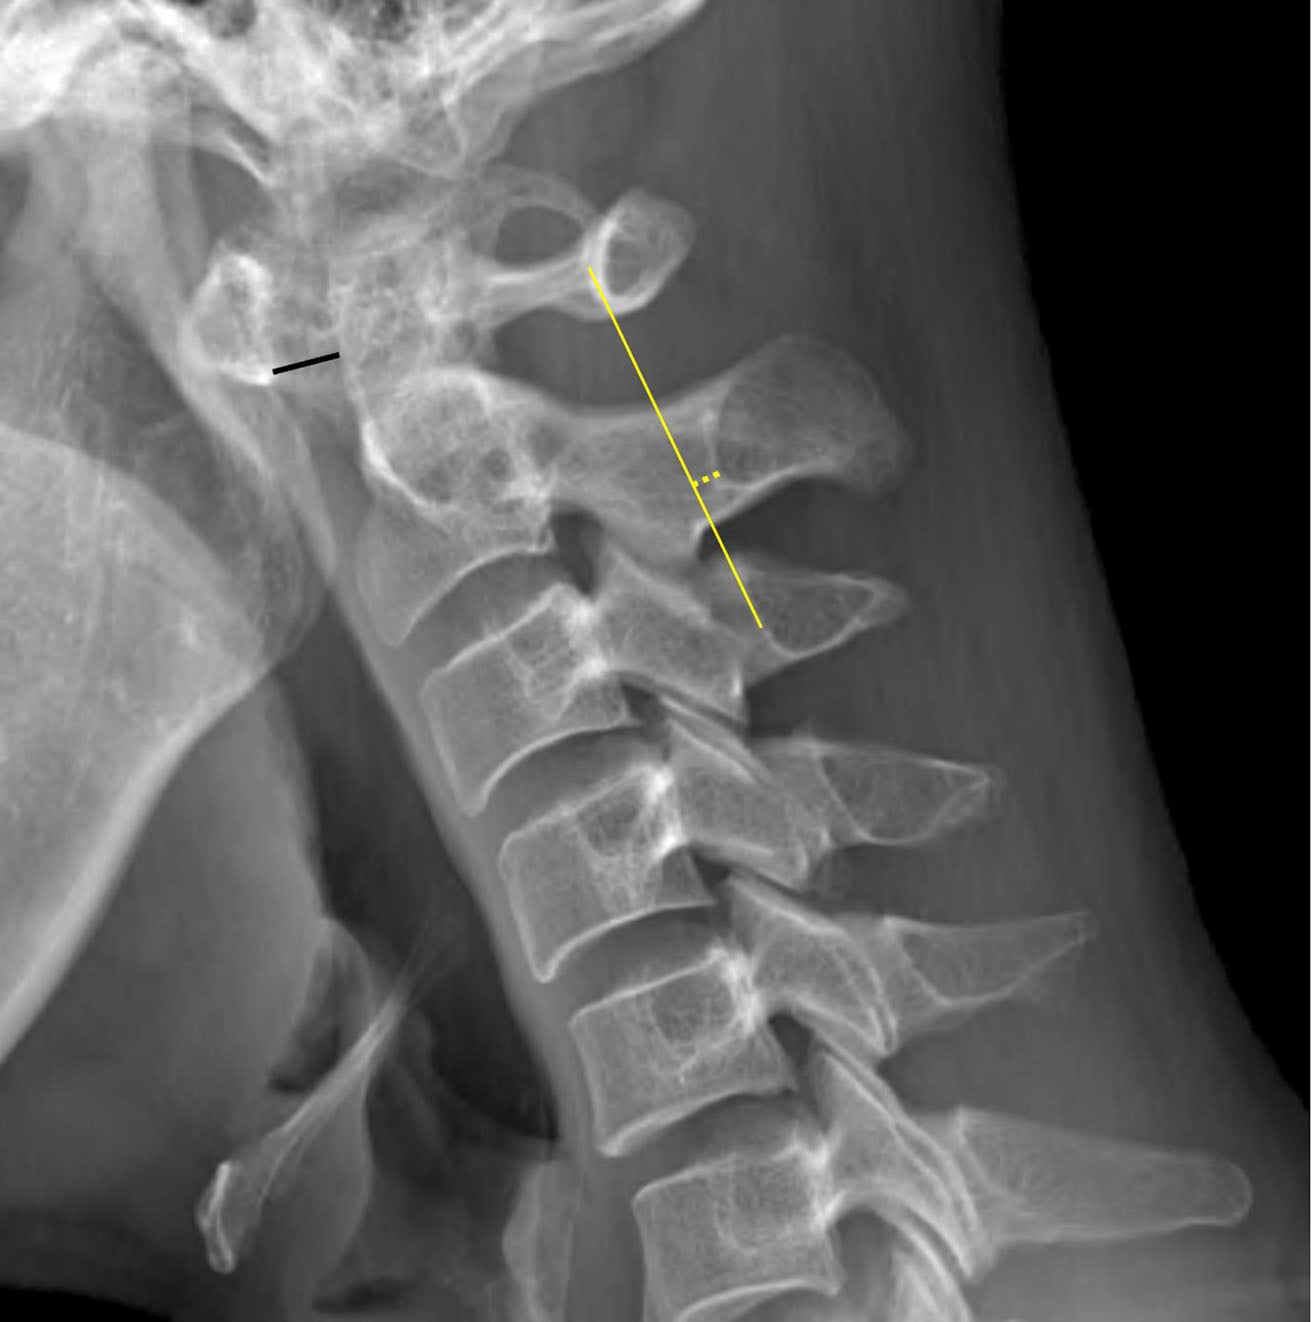
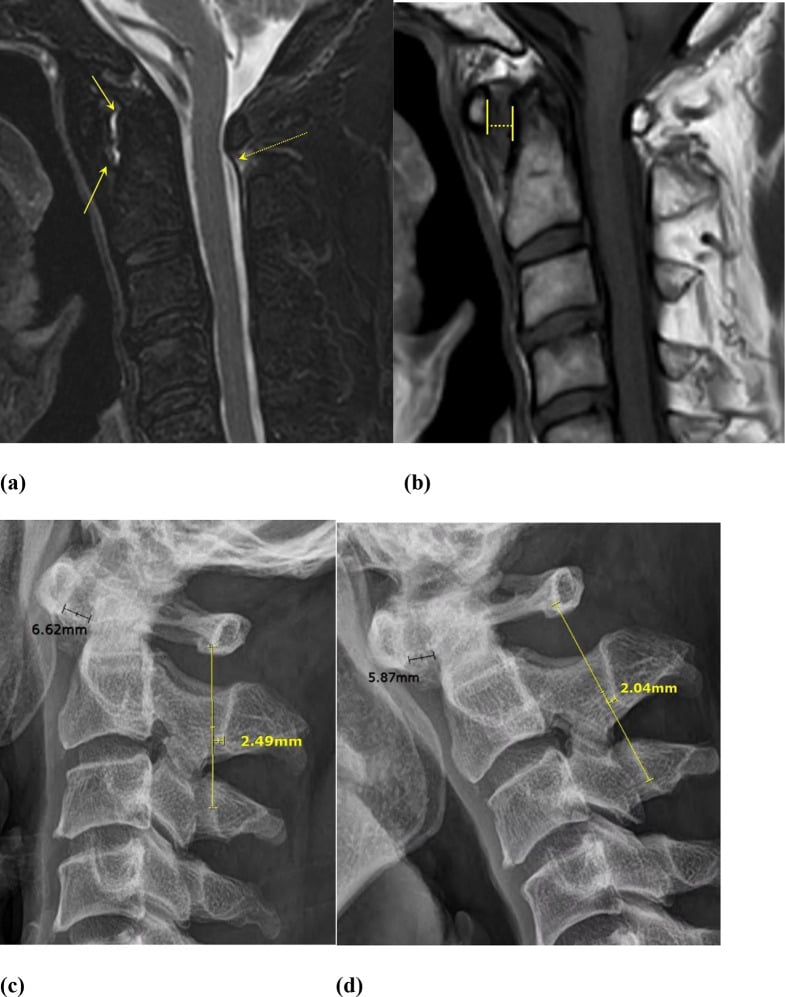
Measuring the ADI. The ADI is measured on the lateral radiograph from the posterior cortex of the anterior C1 arch to the anterior cortex of the odontoid, in neutral, flexion and extension. An increase of over 2mm between positions indicates dynamic instability and ligament failure.
CT is the gold standard for bony anatomy: odontoid morphology, lateral mass dimensions, and C2 pedicle anatomy for surgical planning. Sagittal and coronal reconstructions show vertical migration and basilar invagination.
MRI assesses the cord: the SAC, and T2 signal within the cord, where hyperintensity indicates myelomalacia. It also shows the soft tissues, the pannus (which enhances with gadolinium in RA) and the integrity of the transverse ligament.
- Normal Value
- Adult under 3mm, Child under 5mm
- Pathological Threshold
- Adult over 3.5mm, Child over 5mm
- Clinical Implication
- Transverse ligament incompetence
- Normal Value
- Over 13mm
- Pathological Threshold
- Under 13mm
- Clinical Implication
- High myelopathy risk - surgical threshold
- Normal Value
- -
- Pathological Threshold
- Under 14mm operative threshold; under 10mm predicts poor recovery (13mm if invagination superimposed)
- Clinical Implication
- The measurement that actually predicts paralysis and recovery
ADI or PADI. Boden showed that the posterior interval, the PADI, predicts paralysis and recovery far better than the anterior ADI, which did not correlate. The PADI and the SAC are the same space, so the two cord-space figures on this page sit side by side: an SAC under 13mm is quoted as the myelopathy-risk and surgical threshold, and a PADI under 14mm is Boden's operative threshold.
Management Algorithm
Who. Mild degenerative change without instability (ADI under 3mm), early inflammatory arthritis with intact ligaments, and the patient medically unfit for surgery.
Conservative Protocol
NSAIDs: naproxen 500mg BD or celecoxib 200mg daily. A soft collar only temporarily (under 2 weeks) for acute flares, because prolonged use causes muscle atrophy. Avoid extreme rotation and extension.
Physiotherapy with gentle range of motion and postural training; avoid forceful manipulation. Periscapular and deep neck flexor strengthening. Neutral cervical posture at the workstation.
Clinical reassessment of pain scores and neurology. Repeat flexion-extension radiographs if symptoms worsen. Surgical threshold: ADI over 3.5mm, new neurological signs, or refractory pain.
- Imaging Findings
- Joint space narrowing, ADI under 3mm
- Treatment
- NSAIDs, collar for flares, physiotherapy
- Key Pearl
- Trial conservative 3-6 months with repeat imaging
- Imaging Findings
- ADI 3.5-5mm, SAC over 13mm, no myelopathy
- Treatment
- Consider C1-C2 fusion
- Key Pearl
- Counsel about 50% rotation loss vs continued pain
- Imaging Findings
- ADI over 5mm, SAC under 13mm
- Treatment
- Urgent occiput-C2 fusion
- Key Pearl
- Myelopathy may not fully reverse - do not delay
Lateral Atlantoaxial Osteoarthritis and Image-Guided Intra-articular Injection
Degenerative wear of the lateral atlantoaxial facet joints is the substrate of primary C1-C2 osteoarthritis. In the non-instability, degenerative subset there is a well-established intermediate step between NSAIDs and physiotherapy and fusion: recognising the pain syndrome of unilateral lateral atlantoaxial OA and treating it with an image-guided intra-articular injection.
The syndrome. Unilateral lateral atlantoaxial osteoarthritis characteristically produces suboccipital pain referred to the occiput and vertex, painful restricted rotation towards the affected side, and focal tenderness roughly 2cm below and lateral to the occiput. The C2 dorsal root ganglion and the greater occipital nerve lie immediately behind the lateral atlantoaxial joint, so an osteophytic or synovitic joint irritates them. Lateral C1-C2 OA is a recognised, and frequently overlooked, cause of C2 (greater occipital) neuralgia and cervicogenic headache.
No instability. The ADI is normal and dynamic films are stable, which is what separates this degenerative picture from rheumatoid subluxation. Unilateral suboccipital or occipital pain with painful rotation and a normal ADI in an older patient is lateral atlantoaxial OA until proven otherwise.
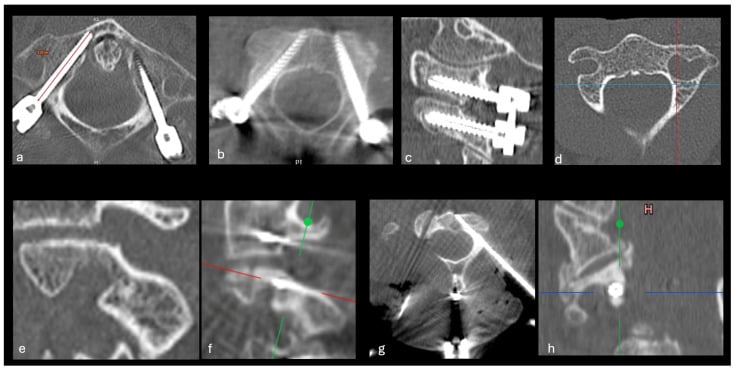
The injection. An image-guided intra-articular corticosteroid injection is both diagnostic and therapeutic. Under fluoroscopic or CT guidance with contrast confirmation, a small volume of local anaesthetic and corticosteroid is delivered into the lateral atlantoaxial joint; abolition of pain confirms the joint as the source, and many patients gain durable relief that defers or avoids fusion. It is a technically demanding block performed by experienced interventionalists because the vertebral artery and the C2 nerve and ganglion lie at the injection target, so contrast, real-time imaging and meticulous needle control are mandatory.
Where it sits. For the degenerative patient who is mechanically painful, neurologically intact and stable and who fails simple measures, the injection is the reasonable next step before surgery. If injections give only transient relief and pain remains disabling, C1-C2 (Harms) fusion remains the definitive option, accepting the trade of pain relief for the expected loss of rotation.
Surgical Technique
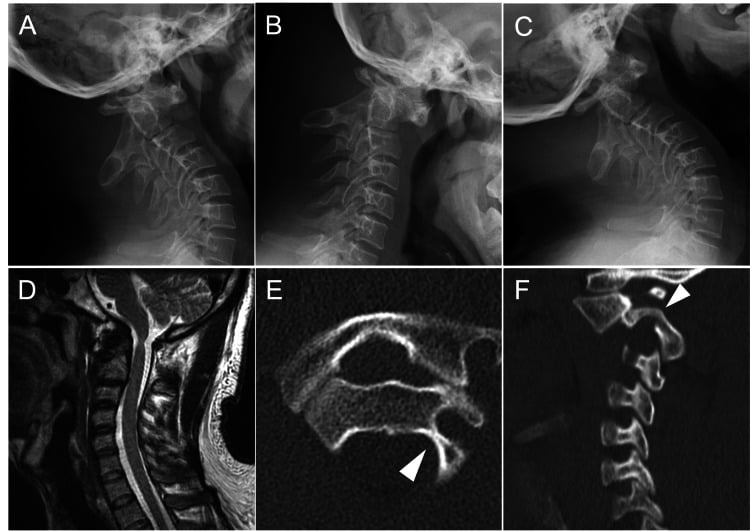
Positioning Checklist
Prone on a Jackson table or Wilson frame. Head in a Mayfield 3-pin clamp, with neutral alignment confirmed on a lateral C-arm image; avoid flexion, which narrows the spinal canal. Arms padded at the sides, chest rolls under the thorax.
SSEP and MEP baselines before incision. Alert thresholds: a 50% amplitude drop or a 10% latency increase.
Expose from the inion to the C7 spinous process. Drape the posterior iliac crest if autograft is planned. Confirm that AP and lateral imaging are possible.
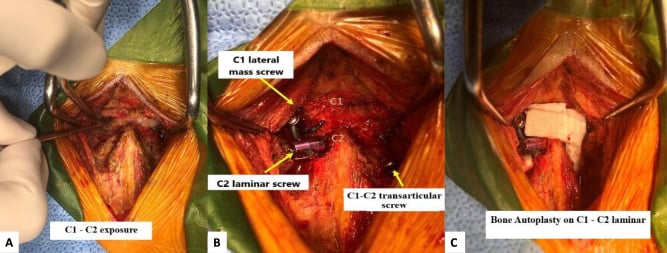
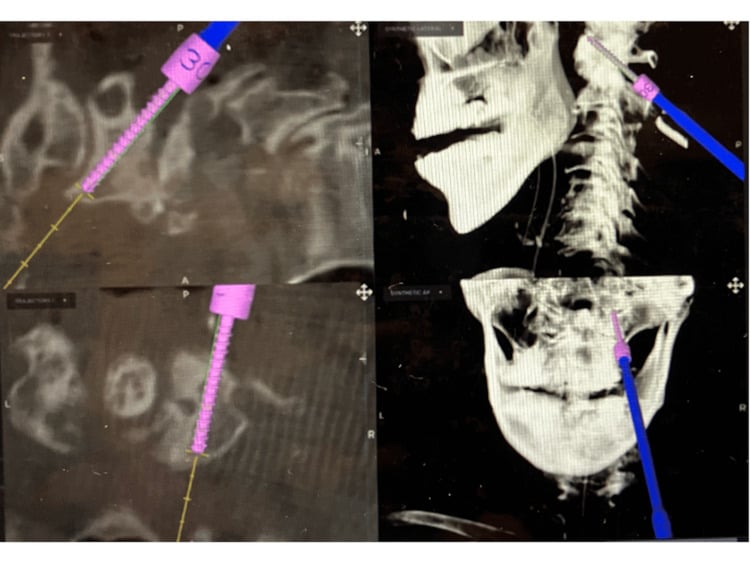
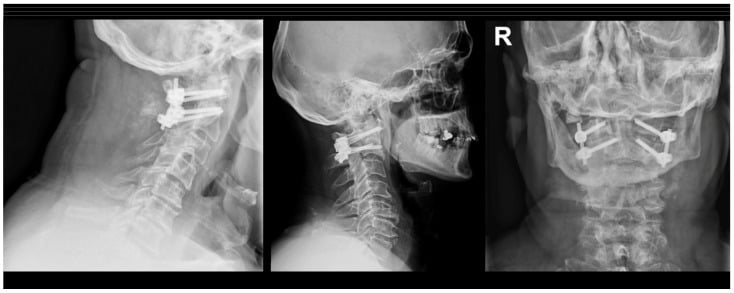
Complications
- Incidence
- 2-4%
- Risk Factors
- Anomalous VA, small C2 pedicle, screw malposition
- Management
- Intraoperative steps in the alert below; vascular surgery if bilateral or symptomatic, otherwise observe
- Incidence
- 5-10%
- Risk Factors
- Excessive retraction, screw malposition
- Management
- Occipital numbness, dysesthesias - usually resolves over 6 months
- Incidence
- 5-10%
- Risk Factors
- Smoking, osteoporosis, inadequate fixation
- Management
- Revision fusion with bone graft, consider rhBMP-2
- Incidence
- 3-5%
- Risk Factors
- Osteoporosis, early collar removal
- Management
- Revise if painful or progressive, otherwise observe
The incidence ranges are conventional teaching figures consistent with the cited series (for example Gluf: 5 vertebral artery injuries in 191 patients, about 2.6%); they are not measured rates from a single defined cohort.
A unilateral injury is usually tolerated because of the contralateral supply; a bilateral injury can cause posterior circulation stroke. If there is brisk arterial bleeding during drilling, pack with gel foam and do not pursue the bleeding or attempt repair (risk of exsanguination). Complete the contralateral screw and consider postoperative angiography.
Postoperative Care and Rehabilitation
Postoperative Protocol
ICU observation, especially after occiput-C2 fusion (respiratory risk). Out of bed on day 1 in the rigid collar, with physiotherapy and occupational therapy assessment.
Wound check, with staples or sutures removed at 10-14 days.
CT to assess fusion progress (early bridging bone). The collar continues full-time if there is no solid fusion; activities of daily living increase gradually.
CT to confirm solid fusion, with bridging bone across the C1-C2 facets. If fusion is solid, the collar is weaned gradually over 4-6 weeks.
Restrictions after fusion:
- Rigid collar full-time for 12 weeks, except for showering (with assistance)
- Lifting under 2kg for 6 weeks and under 5kg for 12 weeks
- No driving until off the collar, because of the vision impairment from the collar and the rotation loss
- Return to sedentary work at 6-8 weeks and to manual labour at 3-6 months
- Swimming at 3 months and non-contact sport at 6 months; no contact sport ever (risk of hardware failure)
Outcomes and Prognosis
- Expected Result
- 80-85% significant improvement (conventional range)
- Time to Plateau
- 6-12 months
- Notes
- Occipitocervical pain resolves in majority
- Expected Result
- 94.8% improved at least one Ranawat class after C1-C2 stabilisation (Peppelman 1993)
- Time to Plateau
- 12-24 months
- Notes
- Determined by SEVERITY of deficit at operation, not by its duration (Boden)
- Expected Result
- 90-95% solid fusion
- Time to Plateau
- 12 months
- Notes
- CT shows bridging bone across C1-C2 facets
C1-C2 fusion eliminates 50% of cervical rotation. Patients must turn the entire body to look sideways, for example to check the blind spot while driving. Most accept this trade-off for pain relief and stability, but preoperative counselling and informed consent are critical.
Guidelines, Registries & Global Practice
Global epidemiology
- Rheumatoid arthritis affects roughly 0.5-1% of adults worldwide (female:male ~2-3:1); historically 30-40% of established RA developed atlantoaxial subluxation, though the incidence has fallen markedly in the biologic-DMARD era due to earlier, tighter disease control.
- Primary degenerative C1-C2 osteoarthritis is uncommon but rises with age; secondary degeneration follows odontoid nonunion, os odontoideum and prior trauma. Type II odontoid fracture nonunion is a leading cause in the elderly.
- Reduced operative demand for rheumatoid cervical disease in high-income settings contrasts with later presentation (and more vertical migration/myelopathy at first contact) where access to early rheumatology and screening imaging is limited.
Side-by-side guidance
- Emphasis
- Treat-to-target to suppress synovitis and limit structural cervical damage
- Practical recommendation
- Tight inflammatory control reduces atlantoaxial instability; image the cervical spine before any general anaesthetic in established RA
- Emphasis
- Operative thresholds driven by neural compromise, not pain alone
- Practical recommendation
- PADI/SAC under 14mm and myelopathy are operative; favour rigid screw-rod constructs
- Emphasis
- Pre-anaesthetic cervical assessment and MDT decision-making in RA
- Practical recommendation
- Lateral flexion-extension radiographs before intubation; refer instability to a spinal unit
- Emphasis
- Standardised craniovertebral junction surgical technique and training
- Practical recommendation
- Preoperative CT angiography of the vertebral artery before C1-C2 instrumentation; navigation for aberrant anatomy
Registries and resource variation
- There is no large dedicated atlantoaxial-fusion registry comparable to arthroplasty registries; evidence rests on institutional series and the upper-cervical literature, so individual surgeon CT-angiographic planning matters more than registry implant data here.
- High-resource settings: routine preoperative CT angiography, intraoperative neuromonitoring and image guidance/navigation; biologic DMARDs have shifted RA cervical disease from a common to an uncommon operative problem.
- Limited-resource settings: later presentation with established vertical migration/myelopathy; transarticular or wiring constructs may predominate where polyaxial screw-rod systems or navigation are unavailable - careful patient selection and preoperative imaging remain the key safety levers.
- RA cervical screening: Flexion-extension lateral radiographs in symptomatic or long-standing RA, and before any general anaesthetic
- Surgical planning: Preoperative CT (and CT angiography) of the C2 isthmus and vertebral artery before C1-C2 instrumentation
- Intraoperative: Neuromonitoring (SSEP/MEP) and fluoroscopic/navigated screw confirmation
- Consent: Document the expected 50% rotation loss, fusion rate and pseudarthrosis, neurological and vertebral artery risk
- Delayed diagnosis: Failure to obtain dynamic views in RA with new neck pain or pre-intubation
- Anatomy ignored: Instrumenting without assessing vertebral artery course or a high-riding/aberrant VA
- Operating too late: Allowing superior odontoid migration or PADI under 10mm before fusion, when recovery potential is lost
- Inadequate consent: Not explaining functional rotation loss and the body-turn it requires
- 50% rotation loss (patient understands functional impact - driving, checking blind spots)
- Fusion rate (90-95%) and pseudarthrosis risk (5-10%)
- Vertebral artery injury risk (2-4%) and management if occurs
- Neurologic outcome (myelopathy may not fully reverse)
- Alternative treatments considered (conservative vs surgical)
- Failure to diagnose atlantoaxial instability in RA (delayed flexion-extension imaging)
- VA injury without documented anatomic assessment or navigation consideration
- Inadequate consent regarding rotation loss
Controversies and Areas of Uncertainty
ADI or PADI as the decisive measure. The anterior ADI is the classic teaching threshold, but modern practice increasingly weights the PADI or SAC and MRI cord signal over a single ADI number.
Asymptomatic instability: when to fix. Whether to fuse a radiographically unstable but neurologically intact RA patient is unsettled. The arguments for early fusion, preventing irreversible myelopathy and operating at lower risk before vertical migration, compete with the morbidity of fusing a patient who may never deteriorate, especially now that disease control is better.
Harms or transarticular (Magerl). Both give about 95-98% fusion. The Harms screw-rod construct allows intraoperative reduction and tolerates an aberrant vertebral artery on one side; transarticular screws need an unobstructed trajectory bilaterally. No randomised trial settles superiority, and the choice is driven by anatomy and surgeon.
C2 nerve root: sacrifice or preserve. Deliberate sacrifice of the C2 ganglion improves joint exposure and access to the fusion bed and reduces venous bleeding, at the cost of occipital numbness. Preservation avoids the sensory deficit but risks more bleeding and screw malposition. The evidence is mixed and practice varies.
Reducing basilar invagination. Whether vertical migration should be actively reduced (traction, intraoperative distraction, anterior release) or simply stabilised in situ with occipitocervical fusion remains debated, balancing decompression against neurovascular risk at the craniovertebral junction.
BMP and navigation. rhBMP-2 and intraoperative navigation or robotics may raise fusion and screw-accuracy rates, but they add cost and, for BMP, off-label use and concerns about swelling at this level; their routine role is not established.
MCQ Practice Points
Q: What percentage of total cervical rotation occurs at the atlantoaxial joint? A: 50% - C1-C2 contributes ~50% of cervical rotation (45 degrees each side) and 10% of flexion-extension. This is why C1-C2 fusion causes profound functional loss.
Q: What is the pathologic ADI threshold in adults? A: 3.5mm - Normal adult ADI is under 3mm. ADI over 3.5mm indicates transverse ligament incompetence. In children, threshold is 5mm.
Q: What SAC measurement indicates high myelopathy risk? A: Under 13mm - SAC (space available for cord) is measured from posterior odontoid to anterior C1 posterior arch. Under 13mm correlates with myelopathy and is a surgical threshold.
Q: What percentage of RA patients develop atlantoaxial subluxation? A: 30-40% - Atlantoaxial involvement is most common cervical manifestation of RA, due to pannus erosion of transverse ligament.
Q: What screw trajectory angles for C2 pedicle in Harms technique? A: 25 degrees medial and 25 degrees cephalad - Following anatomic C2 pedicle axis. Entry point is medial-superior quadrant of C2-C3 facet.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old woman with longstanding rheumatoid arthritis presents with 6 months of progressive occipitocervical pain and difficulty turning her head while driving. Flexion-extension lateral cervical radiographs show ADI of 4mm. How do you assess and manage?”
“Walk me through your technique for C1-C2 fusion using the Harms method. Focus on screw trajectories and danger structures.”
“During C2 pedicle screw placement, you encounter brisk arterial bleeding from the drill hole. How do you manage this intraoperatively?”
Key Anatomy
- C1-C2 = 50% cervical rotation, 10% flexion-extension
- Transverse ligament = primary stabilizer, prevents anterior C1 translation
- Vertebral artery: lateral to C1 lateral mass, through C2 pedicle
- C2 ganglion: over C2 lamina, ligate venous plexus to access C1-C2 joint
Instability Thresholds
- ADI: Adult over 3.5mm pathologic, Child over 5mm
- SAC: Under 13mm = high myelopathy risk, surgical threshold
- McGregor line: Dens tip over 5mm above = basilar invagination
- Dynamic: ADI increase over 2mm flexion to extension = instability
Surgical Indications
- Absolute: Myelopathy, ADI over 5mm, SAC under 13mm, basilar invagination
- Relative: Refractory pain 6 months, ADI 3.5-5mm symptomatic
- C1-C2 fusion: Atlantoaxial instability without basilar invagination
- Occiput-C2: Basilar invagination, severe instability
Harms Technique
- C1 screw: 10 degrees medial, 0 cephalad, 26-30mm, entry 1mm inferior-medial to C1 arch midpoint
- C2 screw: 25 degrees medial, 25 cephalad, 18-22mm, entry medial-superior C2-C3 facet
- Palpate medial pedicle wall before screw insertion
- Gentle compression, decorticate facets, bone graft, collar 12 weeks
Complications
- VA injury 2-4%: Pack, do not pursue, complete contralateral, observe
- C2 nerve 5-10%: Occipital numbness, resolves over 6 months
- Pseudarthrosis 5-10%: Smoking, osteoporosis, inadequate fixation
- Rotation loss 50%: Counsel preop, patient turns body not head
Evidence Base and Key Trials
Harms Technique: Polyaxial Screw-Rod C1-C2 Fusion (Original Description)
- Original description of individual C1 lateral mass + C2 pars/pedicle polyaxial screws connected by rods
- 37 patients: solid fusion in all on early clinical and radiographic follow-up
- No neural or vascular injury attributable to the technique
- Permits intraoperative reduction of fixed subluxation and avoids the transarticular vertebral-artery-at-risk trajectory