Disc Degeneration and Lower Back Pain
- Discogenic pain: axial, deep, worse with flexion and loading, better lying down
- Degeneration is normal ageing - 37% of asymptomatic 20-year-olds and 96% of asymptomatic 80-year-olds have it, so imaging never makes the diagnosis on its own
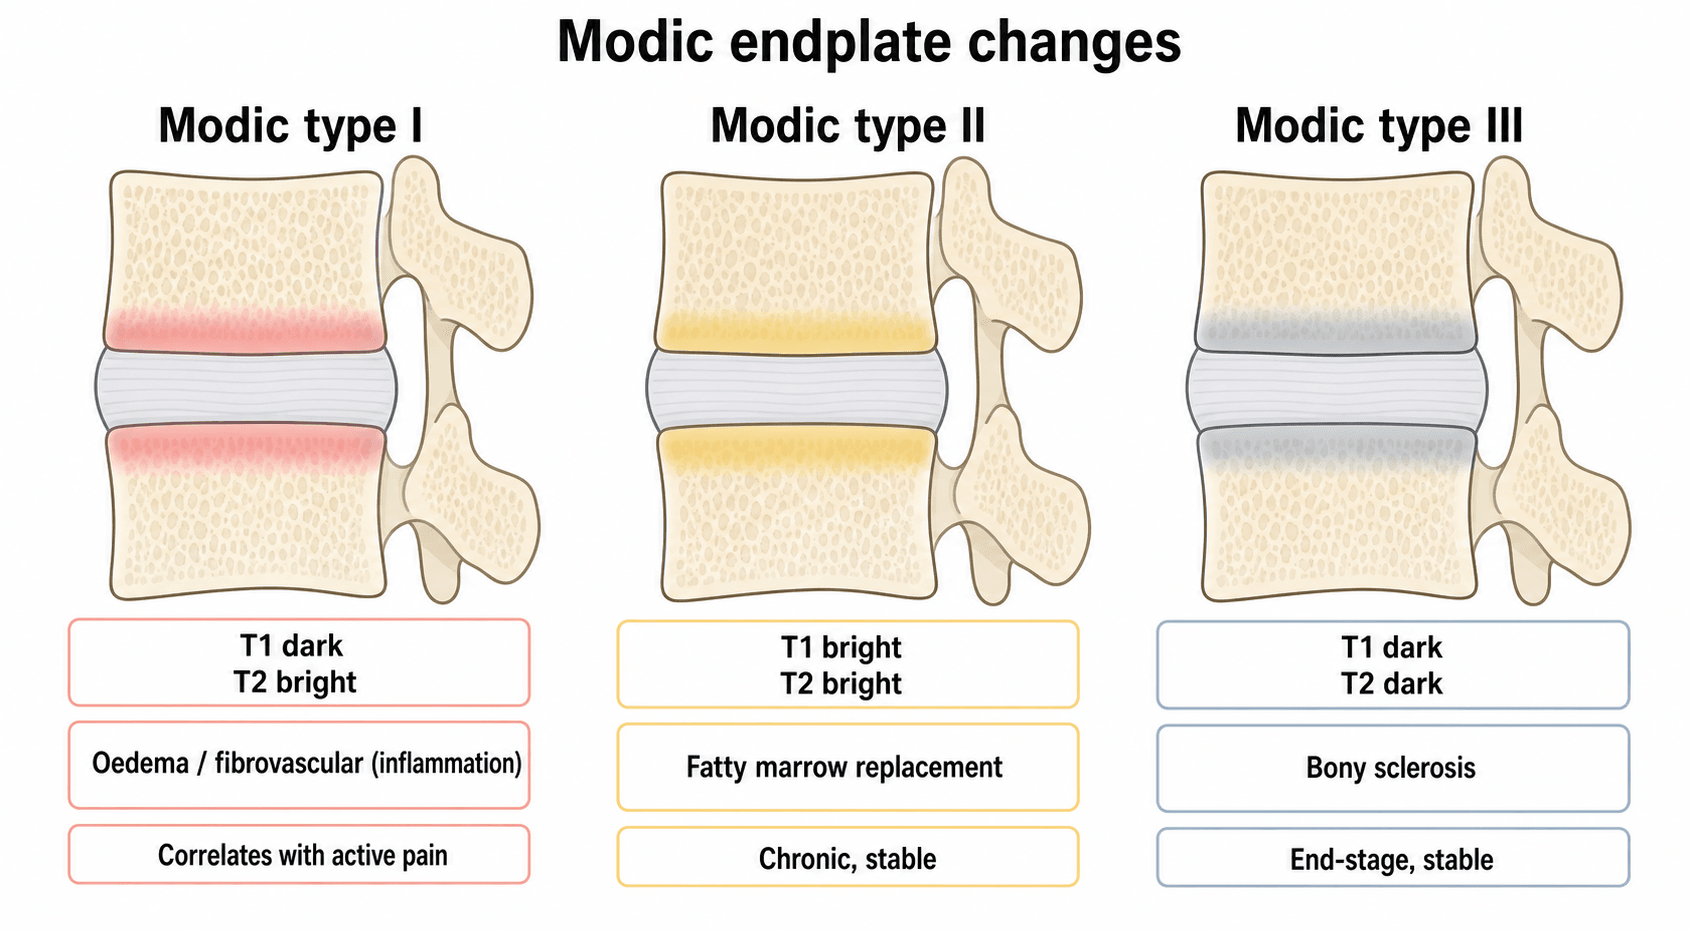
- Modic type I (oedema) is the endplate change that tracks with active pain; type II is fat and type III is sclerosis
- Kirkaldy-Willis cascade: dysfunction to instability to stabilisation - and pain often falls as the segment stiffens
- Conservative care for 6-12 months first; fusion buys a partial improvement, not a cure, and NICE advises against it for axial back pain outside a trial
- “Modic I indicates active inflammation and is the change linked to pain
- “A dark disc is not a diagnosis - correlate with concordant symptoms or you will operate on normal ageing
- “Discography is not a prerequisite for surgery, and it accelerates degeneration in the discs it punctures
- “Quote fusion outcomes as the trial reported them: 63% much better or better versus 29% with non-operative care
Overview and Epidemiology
Degenerative disc disease is a clinical syndrome: pain and dysfunction arising from the natural ageing of the intervertebral disc. Ageing and disease sit on one continuum, and what separates them is the presence of symptoms, a disproportionate loss of function and an effect on quality of life. Degeneration on a scan is, by itself, neither.
How common. Degeneration is ubiquitous with age. In Brinjikji's review of 3,110 asymptomatic people it was present in 37% of 20-year-olds, 80% of 50-year-olds and 96% of 80-year-olds. Symptomatic disease is less common but is a leading cause of disability worldwide, and back pain is the single leading cause of disability globally.
Who gets it. Genetics is the strongest predictor, with about 70% heritability, far outweighing occupational factors: twin studies show strong concordance, and the key genes are vitamin D receptor, aggrecan and collagen IX polymorphisms. Age is the other non-modifiable factor. The modifiable ones are:
- Smoking, critically important: nicotine inhibits chondrocyte proliferation and constricts the subchondral vascular network, starving the disc
- Obesity: increases the mechanical load and creates a systemic pro-inflammatory state
- Occupation: long-term whole-body vibration (truck driving) and heavy lifting
- Diabetes: microvascular disease impairs endplate nutrition
Natural history. The course is typically relapsing-remitting, and over decades pain tends to improve as the spine proceeds to the stabilisation phase of the degenerative cascade. That is why elderly patients often have less back pain but signs of stenosis, neurogenic claudication from osteophytes.
A dark disc alone is not an indication for surgery: it is the expected finding for the patient's age. Pathology must correlate with concordant pain, and treating an MRI report rather than a patient is the commonest route to a failed fusion.
Pathophysiology
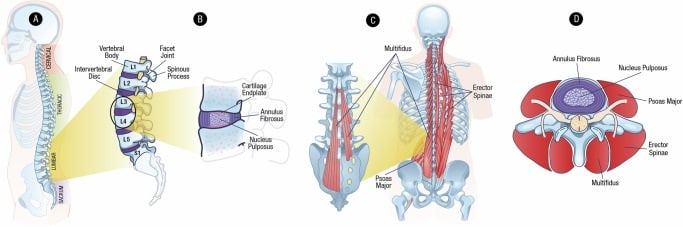
The disc. The intervertebral disc is the largest avascular structure in the body and relies on diffusion for its nutrition. It has three parts.
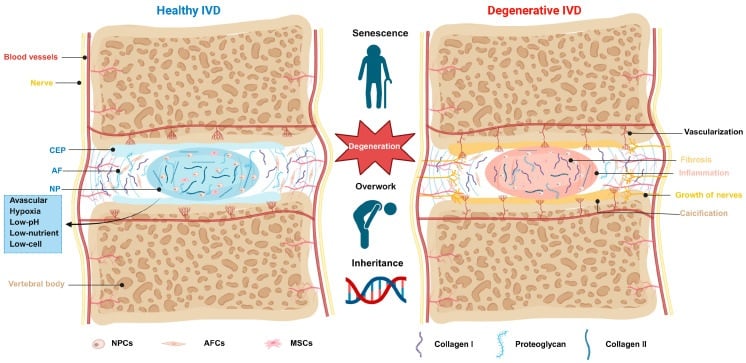
- Nucleus pulposus: the central gelatinous core, made of type II collagen and proteoglycan (aggrecan). Aggrecan is highly hydrophilic; the water content is 80% in youth, and the resulting hydrostatic pressure resists axial compression and distributes load
- Annulus fibrosus: the tough peripheral ring, arranged in lamellar sheets, in which type I collagen dominates for tensile strength. It contains the nucleus and attaches to the vertebral endplates through Sharpey's fibres
- Vertebral endplate: the hyaline cartilage interface between disc and bone, and the route for nutrition. Glucose and oxygen diffuse from the marrow capillaries of the vertebral body through the endplate to the disc cells, and endplate sclerosis blocks that supply
Nutritional failure is the final common pathway of degeneration. Atherosclerosis, the vasoconstriction of smoking and vibration all impede diffusion from the marrow.
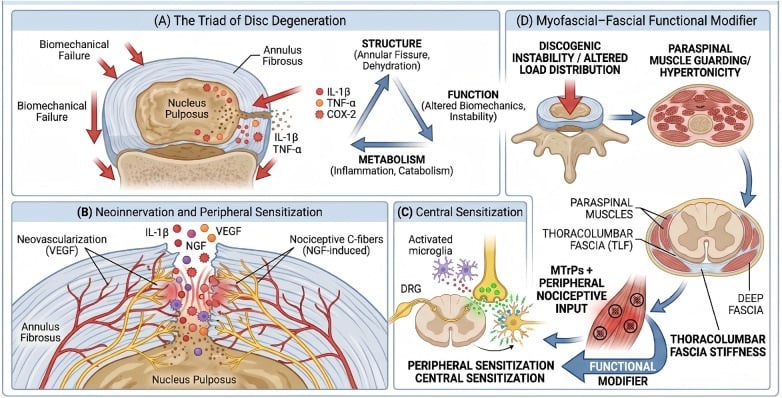
Innervation. The sinuvertebral (recurrent meningeal) nerve supplies the posterior longitudinal ligament and the outer third of the annulus; in a healthy disc the inner annulus and nucleus are aneural. In painful degeneration nerve fibres grow deep into the nucleus, accompanied by blood vessels (neovascularisation) and driven by neurotrophins (NGF, BDNF) expressed by degenerative chondrocytes. That neoneurogenesis is how a structure with no nerve supply of its own becomes the source of significant pain.
Biochemistry. Degeneration is a shift from anabolic to catabolic metabolism.
- Proteoglycan loss: aggrecan synthesis falls and the molecule fragments, water-binding capacity drops, and the nucleus loses turgor and height
- Collagen switch: type II (cartilage-like) gives way to type I (fibrotic) collagen in the nucleus, and the distinction between nucleus and annulus blurs
- Enzymatic degradation: upregulated MMPs and ADAMTS enzymes digest the matrix
- Inflammation: TNF-alpha, IL-1beta and IL-6 released from the degenerating nucleus can sensitise the sinuvertebral nerve endings in the outer annulus, causing pain even without compression
The Kirkaldy-Willis cascade is the classic three-stage model of spinal degeneration, and its third stage is the reason pain often recedes with age while stenosis arrives.
- Pathophysiology
- Circumferential annular tears, endplate separation, synovitis, minor herniation.
- Clinical Features
- Intermittent axial pain, "acute back strains".
- Imaging
- Normal X-ray, MRI showing "black disc" (desiccation).
- Pathophysiology
- Resorption of disc, loss of height, facet capsule laxity.
- Clinical Features
- Catching pain, giving way, severe episodes.
- Imaging
- Traction spurs, vacuum phenomenon, dynamic instability (translation).
- Pathophysiology
- Osteophyte formation, fibrosis, stiffening.
- Clinical Features
- Reduced back pain, developing stenosis symptoms from hypertrophy.
- Imaging
- Bridging osteophytes, severe disc collapse, foraminal stenosis.
Classification
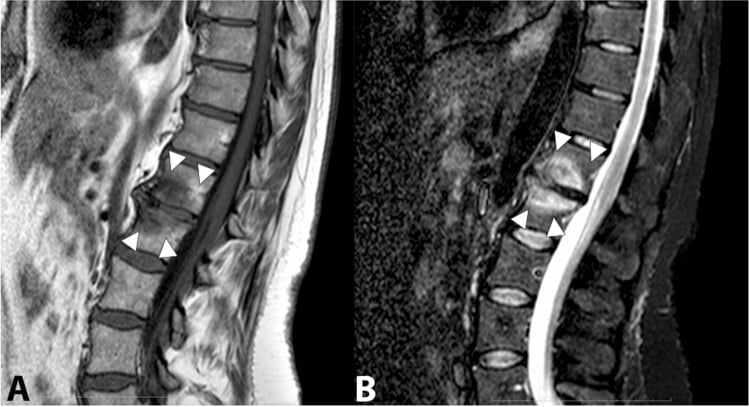
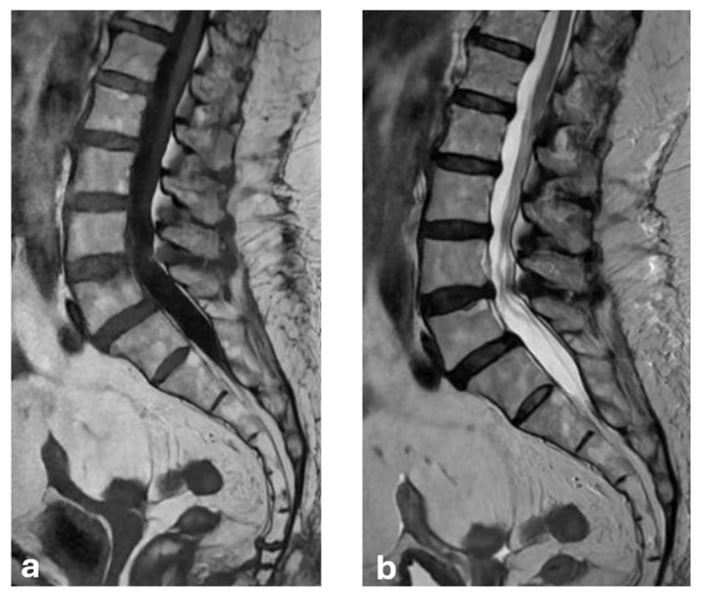
Two MRI systems are used. Pfirrmann grades the disc itself, on T2 structure and signal intensity; Modic describes the marrow of the vertebral endplates on either side of it. Modic type I is the one that matters clinically: oedema, T1 dark and T2 bright, the change that correlates with active pain and therefore the signal for localising the symptomatic level. Type II is fatty replacement, chronic and stable; type III is sclerosis, end-stage and stable.
Pfirrmann grades the degree of disc degeneration on T2-weighted MRI by structure, signal intensity and height.
- Structure
- Homogeneous
- Signal Intensity
- Hyperintense (bright)
- Disc Height
- Normal
- Description
- Juvenile/normal
- Structure
- Heterogeneous (streak)
- Signal Intensity
- Hyperintense
- Disc Height
- Normal
- Description
- Early adult
- Structure
- Heterogeneous
- Signal Intensity
- Intermediate (grey)
- Disc Height
- Normal/slight loss
- Description
- Degenerative
- Structure
- Heterogeneous
- Signal Intensity
- Hypointense (dark)
- Disc Height
- Moderate loss
- Description
- "Black disc"
- Structure
- Collapsed
- Signal Intensity
- Hypointense (black)
- Disc Height
- Collapsed
- Description
- End-stage
Clinical Presentation
The pain. The cardinal feature is axial, midline low back pain: deep, aching and dull, sometimes severe ("toothache in the back"), and quite unlike the sharp, electric pain of a radiculopathy. It is a loading pain. Flexion, sitting and bending forward aggravate it, as do lifting, standing still for long periods and Valsalva (coughing and sneezing raise intrathecal pressure, though that is also a feature of herniation). Extension, lying supine and walking relieve it.
Why sitting hurts. Nachemson measured intradiscal pressure in vivo with standing set at 100%: supine is roughly 25%, unsupported sitting about 140%, and standing while leaning forward holding a weight higher still. That is the measured reason a discogenic patient prefers to stand or lie down and dreads a long drive.
Pattern. Intermittent flare-ups lasting weeks, settling to baseline, with morning stiffness (the gel phenomenon) lasting minutes. Screen for yellow flags, fear avoidance, catastrophising and depression, because these predict disability better than any imaging grade.
Red flags to exclude before calling it degenerative:
- Weight loss, night pain, a history of cancer: malignancy
- Fever, intravenous drug use, immunosuppression: infection
- Significant trauma: fracture
- Saddle anaesthesia, bladder dysfunction: cauda equina syndrome
Examination. Findings in pure disc disease are often non-specific, and the examination is there to rule out other pathology, the hips and the nerve roots. Look for a loss of lordosis (a flat back from muscle spasm and guarding) and a lateral shift. Palpate for midline tenderness over the spinous processes and interspinous spaces and for paraspinal spasm ("washboarding"). Flexion is often limited and painful, measured as fingertip-to-floor distance, while extension may be preserved unless there is facet arthropathy; catching or a painful arc on the return from flexion suggests instability.
Neurology and provocation. Neurology is usually normal in isolated disc disease; check for a concordant radiculopathy, which requires nerve root compression. Axial compression may reproduce the back pain, and straight leg raise is usually negative in pure discogenic pain unless a herniation is present.
Investigations
Radiographs. AP and lateral views assess alignment, scoliosis and lordosis. The degenerative signs are loss of disc height, endplate sclerosis, osteophytes (traction spurs) and the vacuum phenomenon, nitrogen gas within the disc cleft. The vacuum sign marks advanced degeneration and argues against infection, where the disc space fills with fluid rather than gas.
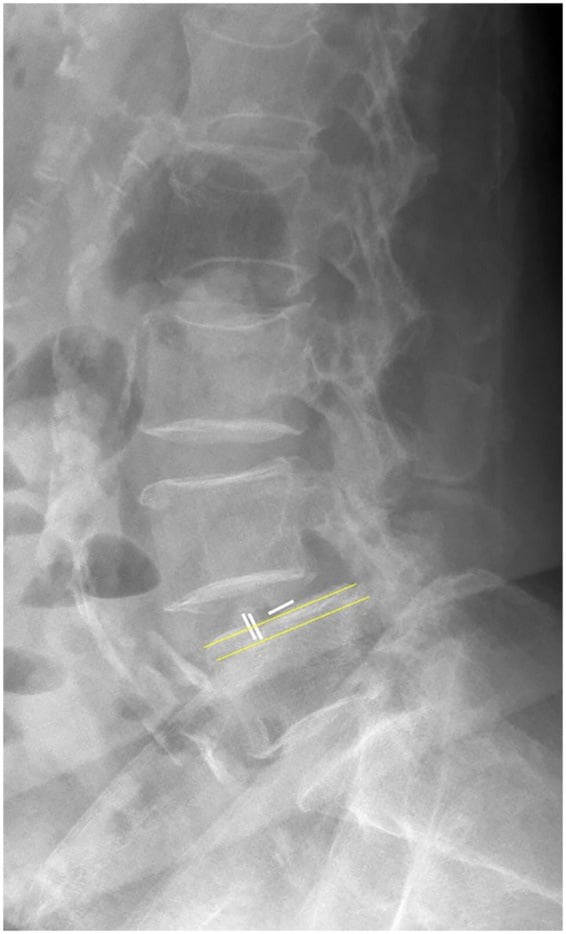
Flexion-extension views are critical before any fusion, to rule out instability (spondylolisthesis): translation greater than 3 mm or angulation greater than 10 degrees. One position can underestimate it, so upright, supine, flexion and extension images each add something, provided the same posterior vertebral landmarks are measured every time.
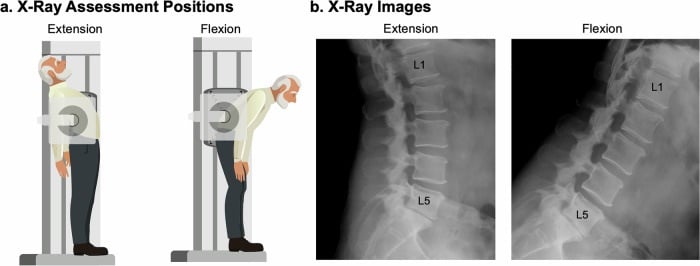
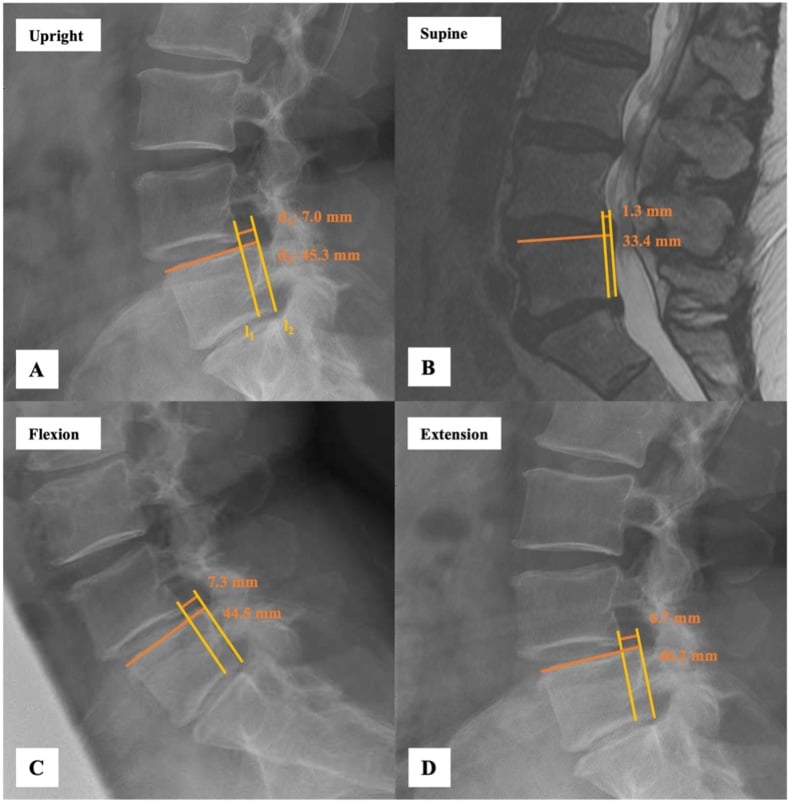
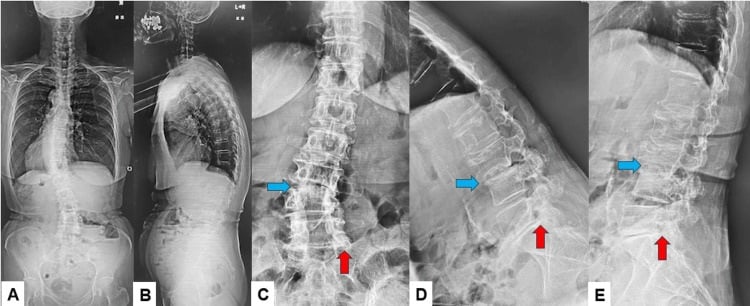
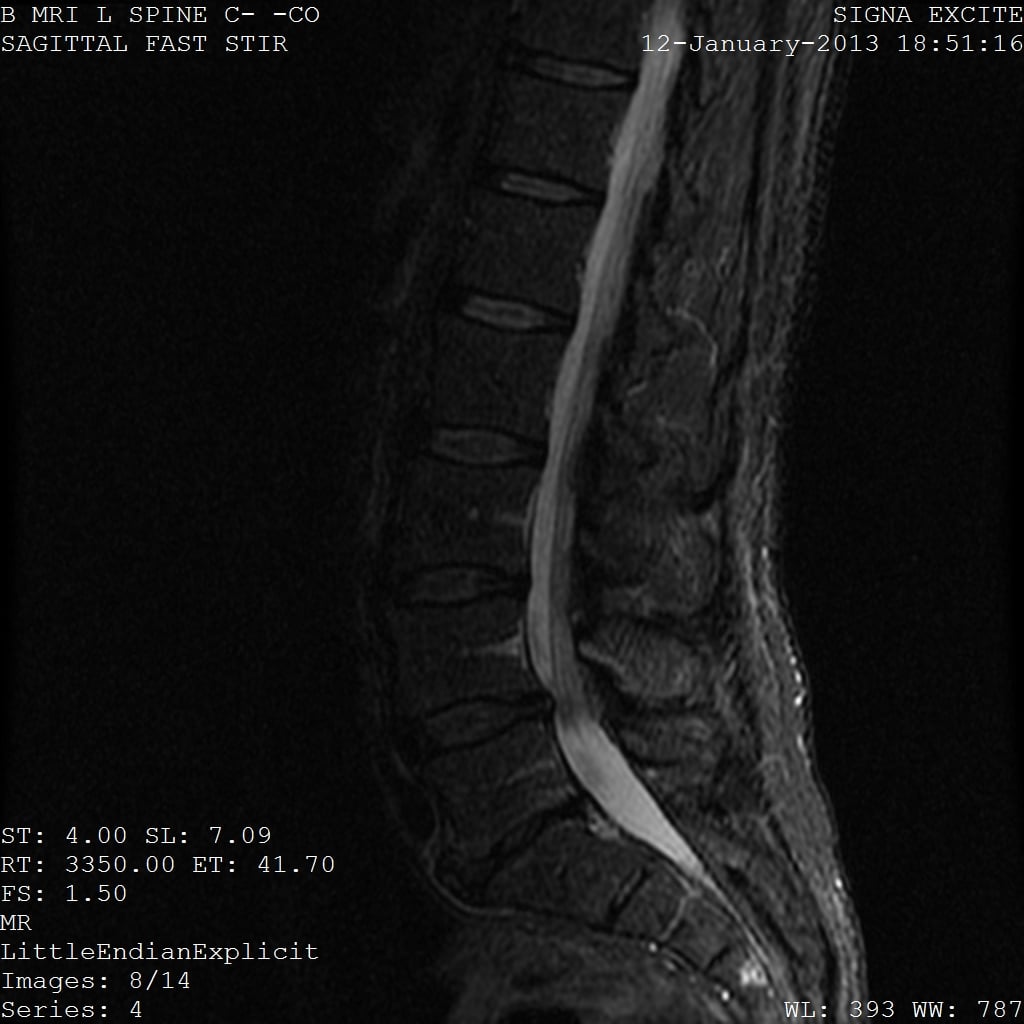
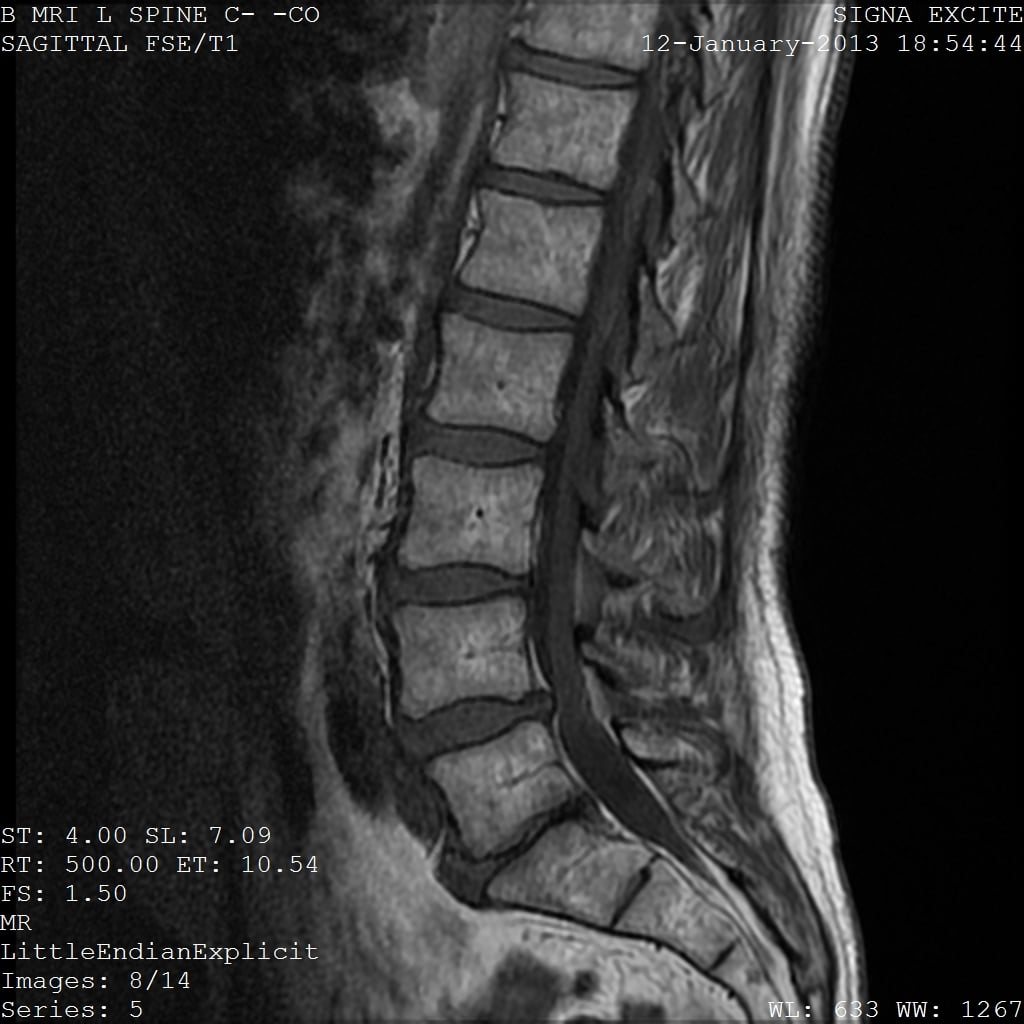
MRI is the gold standard, with high sensitivity and poor specificity: it is abnormal in most asymptomatic adults. The T2 sagittal is the sequence for hydration and the Pfirrmann grade. Look for the black disc, loss of height, bulging and any nerve root compression; for Modic change at the endplates; and for a high intensity zone, a bright spot in the posterior annulus on T2 that correlates with an annular tear and has high specificity for discogenic pain, though that remains controversial.
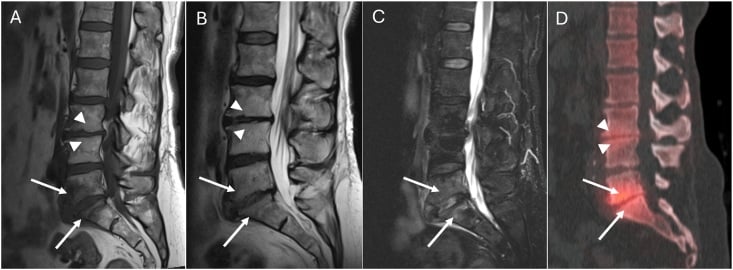
SPECT-CT may show hot uptake at an actively degenerating level and can help localise when plain MRI shows several equally degenerate discs.
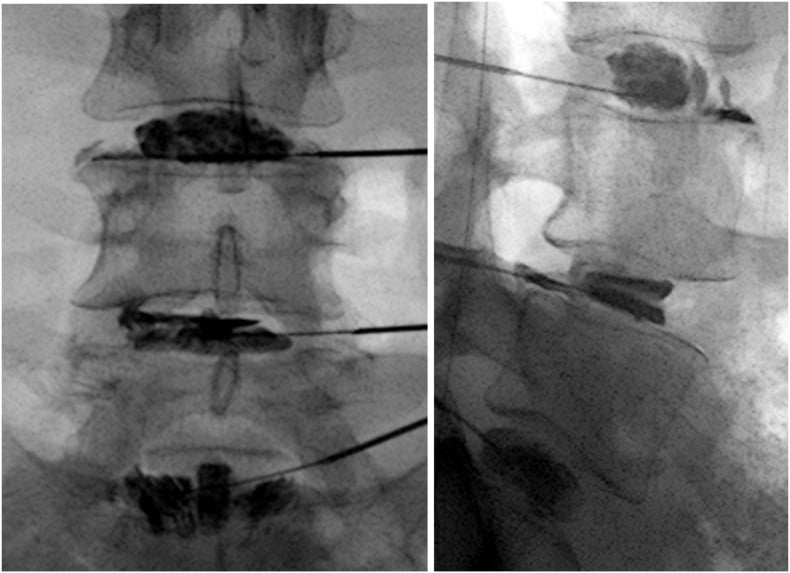
Discography injects contrast or saline into the nucleus under fluoroscopy. A positive test needs three things: reproduction of the patient's exact familiar pain (concordant pain), morphological degeneration, and a negative control level; the control disc is what separates a test from a suggestion. False-positive rates are high in people with psychological distress or chronic pain elsewhere.
Why it has fallen out of favour, with the numbers. Carragee's 10-year matched cohort (50 discography subjects, 52 matched controls) found that the punctured discs did worse on every parameter measured, and this was with modern small-gauge, low-pressure technique:
- Progression of degeneration in 35% versus 14% of discs (P=0.03)
- 55 new herniations versus 22 (P=0.0003), falling disproportionately on the side of the annular puncture (P=0.0006)
- Greater loss of disc height (P=0.05) and signal (P=0.001)
Where that leaves it. A test that injures the disc it examines, in a condition where the operation it selects for has only a modest advantage. It is not a prerequisite for surgery, and it should be reserved for the genuinely indeterminate multi-level case after the risk has been discussed.
Differential Diagnosis
Back pain is a symptom with many causes, and the first sort is mechanical from non-mechanical.
Mechanical
- Facet joint arthropathy: worse with extension and rotation, paramedian tenderness
- Spondylolisthesis: instability pain, a step-off on examination
- Lumbar strain: acute muscle injury, self-limiting
- Sacroiliac joint dysfunction: pain below L5, positive Fortin's finger test, Patrick's FABER test
Non-mechanical
- Tumour: multiple myeloma and metastases (breast, lung, prostate, kidney, thyroid); night pain
- Infection: discitis or osteomyelitis; fever and unremitting pain. Modic I change can mimic infection
- Inflammatory: axial spondyloarthritis or ankylosing spondylitis. Insidious onset before age 45, morning stiffness longer than 30 minutes, pain that improves with exercise and not with rest, night pain waking in the second half of the night, and a good response to NSAIDs
Do not use "young man" as the filter for inflammatory disease. Axial spondyloarthritis is close to evenly distributed between the sexes, and the male stereotype is a documented cause of years of diagnostic delay in women.
Visceral referral
- Abdominal aortic aneurysm: pulsatile mass, cardiovascular risk factors
- Renal: kidney stones (colic), pyelonephritis (fever, CVA tenderness)
- Pancreatitis: penetrating back pain
Management
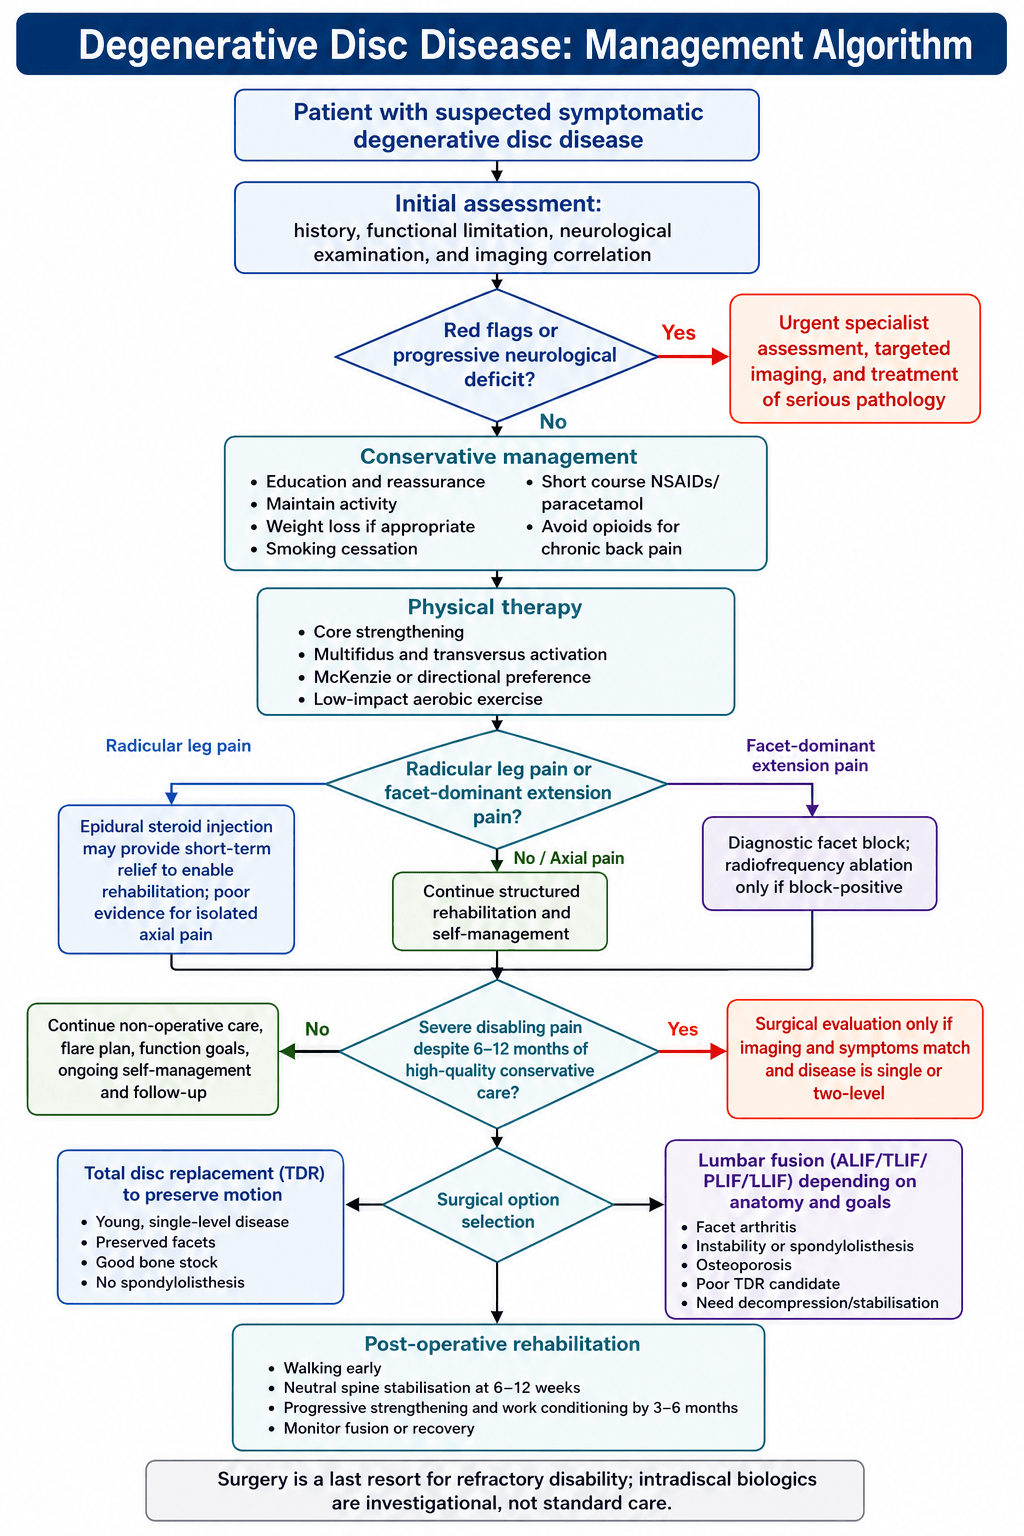
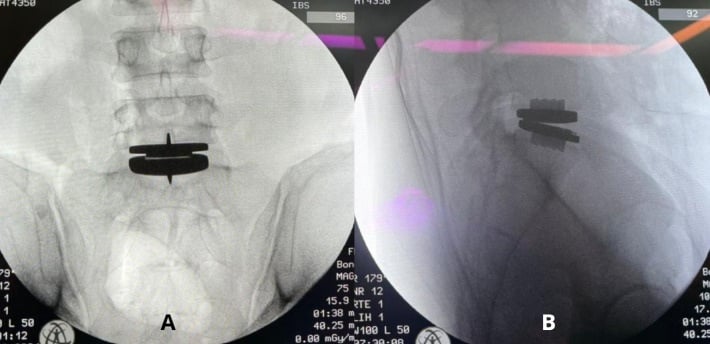
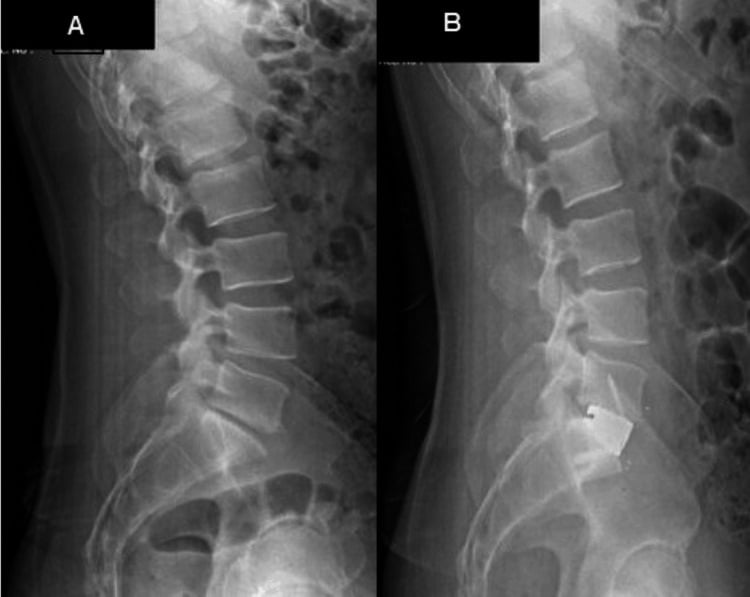
Vertebrogenic Pain and Basivertebral Nerve Ablation
A distinct and increasingly recognised source of chronic axial low back pain is the vertebral endplate itself: vertebrogenic pain, mechanistically separate from discogenic pain even though the two overlap.
The nerve. The damaged endplate is innervated by the basivertebral nerve, a branch of the sinuvertebral nerve that enters the posterior vertebral body through the basivertebral foramen and ramifies centrally near the endplates. Endplate damage with Modic type I or II change is the imaging signature of vertebrogenic pain, so the same signal change carries two meanings: it marks which disc level is painful, and it marks the endplate itself as a pain generator in its own right.
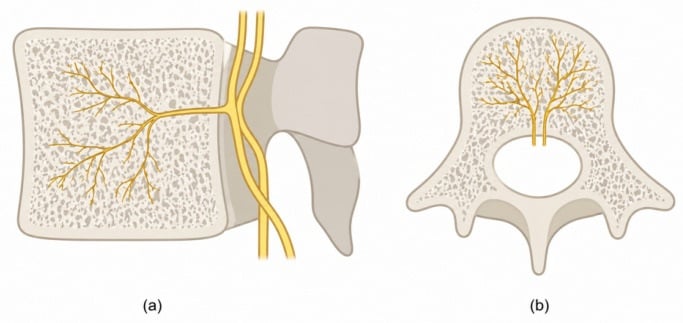
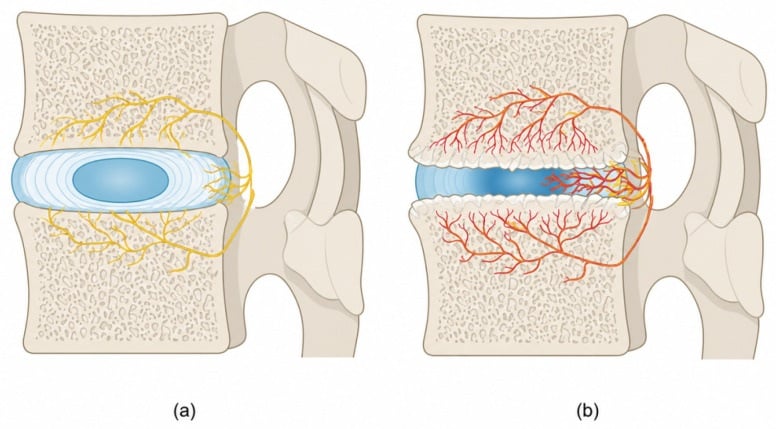
Basivertebral nerve ablation (the Intracept procedure) is a minimally invasive transpedicular radiofrequency ablation of the nerve within the vertebral body, denervating the endplate. The typical candidate has chronic (longer than 6 months) axial low back pain with Modic type I or II change at L3-S1, refractory to conservative care, without a dominant radicular or instability picture. A sham-controlled randomised trial (the SMART trial) and subsequent studies reported significant, durable improvements in disability and pain, and the procedure now features in some chronic low back pain pathways.
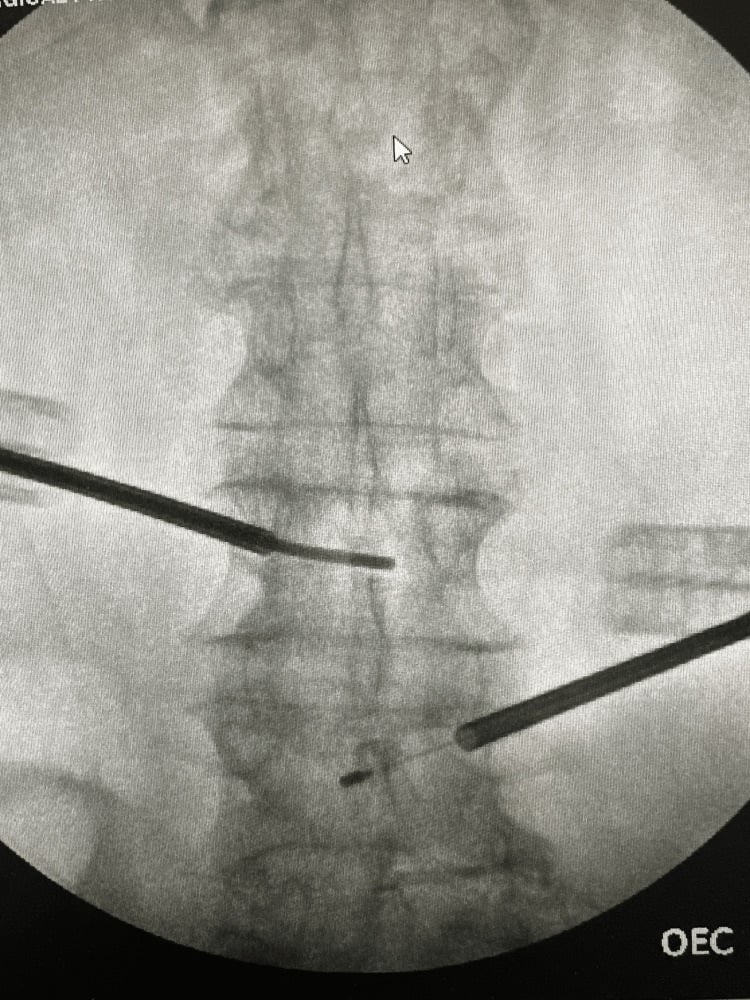
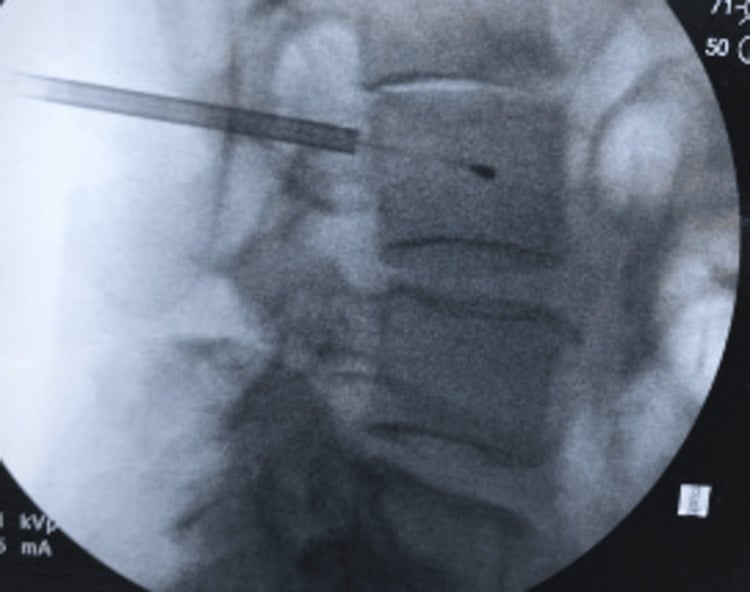
Not all axial back pain is discogenic: the endplate, signalled by Modic I/II change and carried by the basivertebral nerve, is a second generator, and its ablation is a motion-preserving alternative to fusion.
Are Modic Changes an Infection? The Antibiotic Question
Patients arrive having read that back pain is caused by a low-grade disc infection with Cutibacterium acnes and curable with antibiotics. It is a fair question with a specific answer, and it turns on two trials that reached opposite conclusions.
The proposition. Anaerobic organisms, chiefly C. acnes, seed a disc through the neovascularisation that follows a herniation, and the resulting low-grade infection produces the endplate oedema seen as Modic type I change. If so, antibiotics should treat it.
Albert's 2013 trial supported it, dramatically. 162 patients with chronic back pain after a previous herniation and Modic I change, randomised to 100 days of amoxicillin-clavulanate or placebo. Disability (RMDQ) fell from 15 to 5.7 in the antibiotic arm and from 15 to 14 on placebo, with improvement continuing after treatment stopped and a suggestion of dose-response.
The AIM trial did not replicate it. 180 patients, six Norwegian hospitals, double-blind, three months of amoxicillin 750 mg three times daily versus placebo, with the minimal clinically important RMDQ difference predefined at 4 points. The observed difference at one year was -1.6 (95% CI -3.1 to 0.0): statistically borderline and well below the predefined clinical threshold. In the type I subgroup it was -2.3, still short of 4; in type II it was -0.1. Meanwhile 56% of the antibiotic group had a drug-related adverse event versus 34% on placebo.
Where that leaves you. The larger, independent, prospectively powered trial that set its clinical threshold in advance did not find a clinically important benefit, and found more harm. Antibiotics are not indicated for chronic low back pain with Modic changes outside a trial. The discipline to take from it is the difference between a statistically significant difference and a clinically important one: AIM's primary result had a P value of 0.04 and is still a negative trial, because the effect was smaller than the difference the investigators had declared in advance to be worth having.
A candidate who quotes AIM's P value and concludes that antibiotics work has misread the trial. Always ask what difference the investigators declared in advance to be clinically meaningful, and whether the confidence interval excludes it; here the entire interval sits below the threshold.
Spinopelvic Alignment and Sagittal Balance
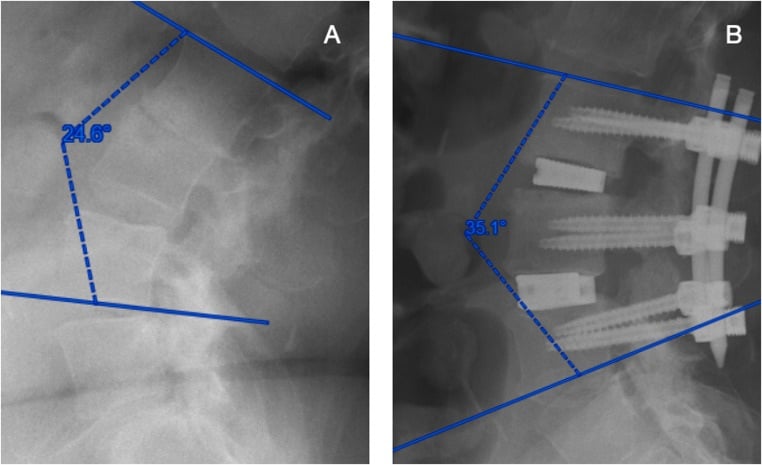
Whenever a level is fused for disc disease, restoring lordosis is as important as achieving union. Getting the union and losing the alignment is a technically successful operation that leaves the patient worse.
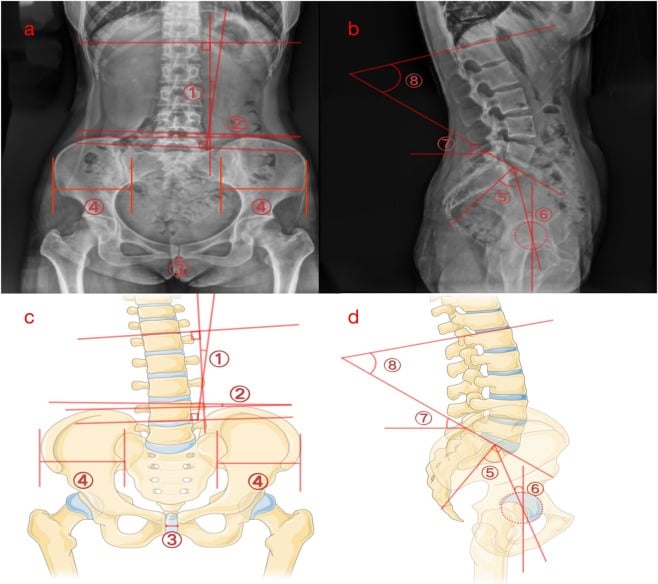
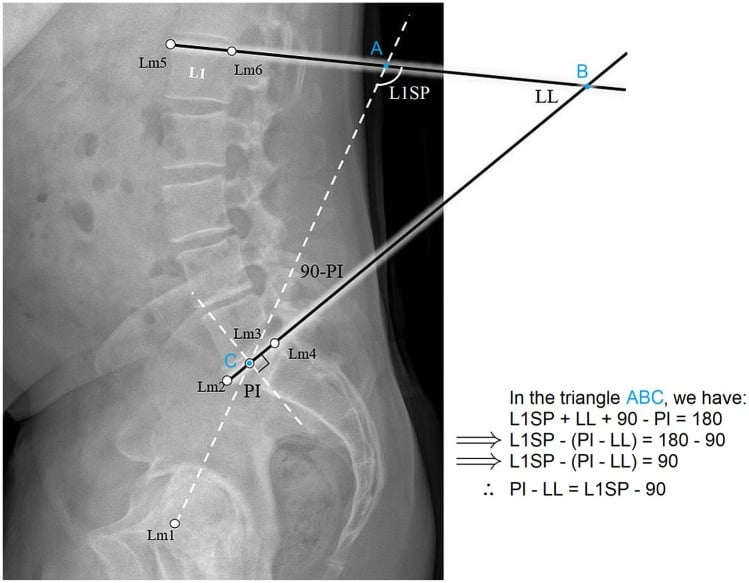
The parameters. Pelvic incidence is a fixed, morphological parameter equal to pelvic tilt plus sacral slope (PI = PT + SS), and it sets how much lumbar lordosis a given pelvis needs. Pelvic tilt and sacral slope are positional, and change as the pelvis rotates. Lumbar lordosis should approximately match the pelvic incidence, with a PI-LL mismatch of less than about 10 degrees as the goal.
Why it matters. A segment fused in insufficient lordosis, or a generalised flat lumbar spine, produces iatrogenic flatback and a PI-LL mismatch that correlates strongly with pain and disability. The body compensates with pelvic retroversion (increased PT), hip extension and knee flexion to stay upright, which is energy-costly and unsustainable, and the malalignment increases shear and stress at the adjacent levels, accelerating adjacent segment disease. This is why anterior-column techniques, ALIF or LLIF with lordotic cages, that restore segmental lordosis are favoured when alignment must be corrected, rather than a posterior-only fusion in situ.
PI = PT + SS; aim for a PI-LL mismatch under about 10°. Plan segmental lordosis, don't just "fuse the painful disc."
Complications
Any spinal operation carries infection (1-3%), dural tear with CSF leak, nerve root injury, and DVT or PE.
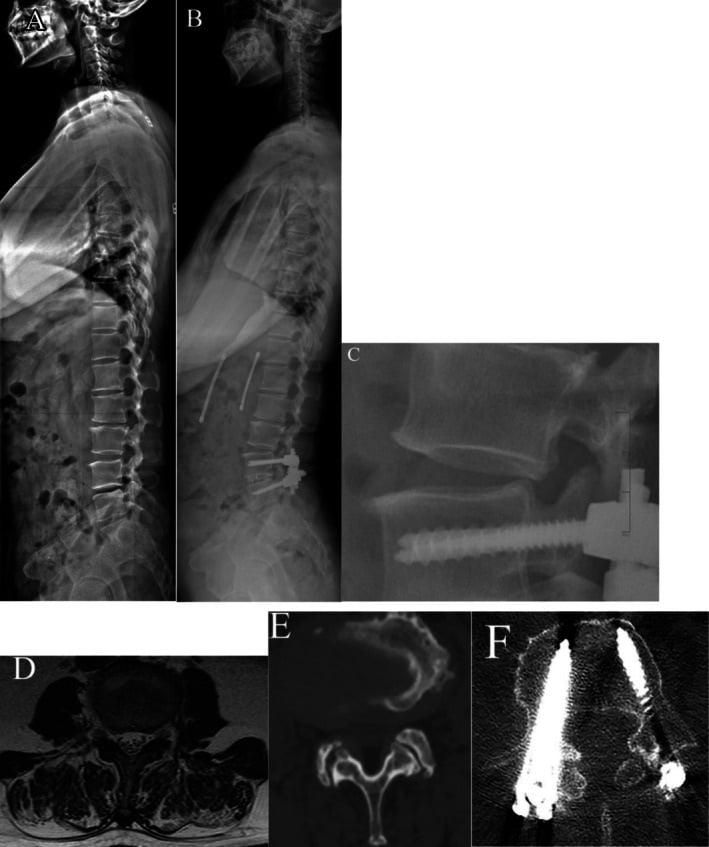
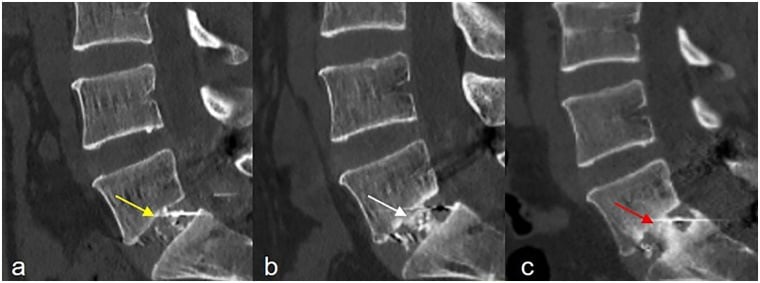
Fusion. Pseudarthrosis is failure of the bone to fuse; smoking, NSAIDs and diabetes are the risk factors, and it causes persistent pain that leads to revision. Hardware failure means screw loosening or cage migration. Adjacent segment disease is accelerated degeneration at the level above or below a fusion: Ghiselli's 215-patient series predicted symptomatic disease requiring decompression or further fusion in 16.5% at 5 years and 36.1% at 10 years, about 2-3% a year, but quote the 10-year figure when counselling a young patient, because that is the one they will live to meet.
Arthroplasty. Implant migration or subsidence, heterotopic ossification (auto-fusion), polyethylene wear debris (rare), and a difficult revision through anterior scar tissue, the "vascular disaster" risk.
The anterior approach (ALIF and disc replacement) adds vascular injury to the iliac vein or artery, which is life-threatening; retrograde ejaculation from injury to the superior hypogastric plexus in males, at 1-5%; and, rarely, ureteral injury.
Outcomes and Prognosis
Natural history is favourable: many patients settle as the segment stiffens into the stabilisation phase, and most reach acceptable function without an operation. Fusion, where it is offered, buys improvement rather than cure, and the trial figures to counsel with are set out under Surgical Management.
Predictors of a poor outcome. Psychosocial factors (yellow flags, workers' compensation, depression), smoking, obesity and multi-level disease.
Guidelines, Registries & Global Practice
Global Epidemiology
- Low back pain is the single leading cause of years lived with disability worldwide (Global Burden of Disease).
- Disc degeneration on imaging rises with age (37% at 20 years to 96% at 80 years; Brinjikji 2015) and is largely asymptomatic - prevalence is similar across populations, so it is a global aging phenomenon rather than a regional disease.
- Genetics carries the strongest weight in heritability studies, outweighing occupational mechanical load.
Society Guidance (Side by Side)
- Position on Imaging
- Do not routinely offer imaging in non-specialist settings; reserve MRI for suspected serious pathology or when result changes management
- Position on Surgery for Axial DDD
- Do not offer spinal fusion for low back pain outside a randomised trial; emphasise exercise and combined physical/psychological programmes
- Position on Imaging
- MRI is the modality of choice when red flags or failed conservative care; degeneration alone is non-diagnostic
- Position on Surgery for Axial DDD
- Fusion reserved for carefully selected refractory single/two-level disease after failed structured non-operative care
- Position on Imaging
- Correlate imaging strictly with concordant symptoms; discography controversial
- Position on Surgery for Axial DDD
- Motion-preserving arthroplasty an option in young patients with intact facets and single-level disease
Consistent global message: at least 3-6 months (commonly up to 12) of structured non-operative care; never operate on imaging alone; document concordant clinical correlation before any fusion or arthroplasty.
Registry & Outcome Notes
- Spine procedures are tracked in national registries such as the British Spine Registry, Swespine (Sweden) and the Norwegian (NORspine) registry. Registry data consistently show smaller, more variable benefit for fusion in pure axial discogenic pain than for radiculopathy or deformity.
- Symptomatic adjacent segment disease requiring further surgery runs at roughly 2-3% per year, reaching 16.5% at 5 years and 36.1% at 10 years in long-term cohort follow-up (Ghiselli).
High- vs Limited-Resource Variation
- High-resource settings: ready MRI access (with attendant risk of over-imaging), multidisciplinary pain programmes, and access to arthroplasty implants.
- Limited-resource settings: emphasis on clinical diagnosis, exercise and analgesia; imaging and instrumented surgery rationed to red-flag or instability cases. Across all settings the core principle is unchanged: conservative-first, image only to change management, operate only on concordant refractory disease.
MCQ Practice Points
Q: What MRI finding helps identify the symptomatic disc level in degenerative disc disease?
A: Modic Type I changes (bone marrow oedema appearing as T1 hypointense, T2 hyperintense) correlate most strongly with active inflammation and symptomatic disc degeneration. Type II (fatty replacement) and Type III (sclerosis) are less commonly associated with active symptoms.
Q: What is the role of provocative discography in degenerative disc disease?
A: Provocative discography identifies concordant pain (reproduction of typical symptoms) to localise the painful level before fusion. However, it has high false positive rates (up to 40% in asymptomatic individuals) and is controversial. Best used when imaging shows multi-level disease and clinical localisation is uncertain.
Q: What does the evidence show for fusion surgery vs non-operative treatment in degenerative disc disease?
A: Evidence is mixed and the benefit is modest. The Swedish Lumbar Spine Study (Fritzell 2001) showed fusion reduced pain and disability more than unstructured non-operative care, but later RCTs comparing fusion with intensive structured/multidisciplinary rehabilitation found little or no clear advantage for fusion. (Note: the SPORT trials studied disc herniation, spinal stenosis and degenerative spondylolisthesis - not axial discogenic pain - so they do not address fusion for DDD.) Surgery is therefore reserved for patients with failed prolonged conservative treatment (greater than 6-12 months), confirmed single-level disease, and concordant clinical correlation.
Q: When is disc arthroplasty (artificial disc replacement) indicated over fusion?
A: Disc arthroplasty is indicated for single-level disease, intact facet joints, no significant instability, and younger patients (typically less than 60 years). Contraindications include: multi-level disease, facet arthropathy, instability, osteoporosis, or previous posterior surgery at that level.
Self-Assessment Quiz
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 40-year-old labourer presents with 2 years of worsening mechanical back pain. MRI shows L5/S1 dark disc with Modic I changes. He wants a 'fusion' so he can return to heavy work.”
“A 65-year-old female had an L4/5 fusion 10 years ago. She presents with recurrence of back pain and new L3 radiculopathy (pain radiating to anterior thigh/knee).”
Pathology Facts
- Water Loss: Proteoglycan/Aggrecan loss leads to dehydration
- Collagen: Type II (nucleus) replaced by Type I (fibrosis)
- Kirkaldy-Willis: Dysfunction to Instability to Stabilization
Imaging & Signs
- Modic I: Edema (T1 Dark, T2 Bright) - Painful
- Modic II: Fat (Bright/Bright) - Stable
- Pfirrmann: MRI Grading I-V of disc height/signal
- HIZ: High Intensity Zone - Posterior annular tear
Management Rules
- First line: structured conservative care for 6-12 months - where most of the benefit lies
- Never operate on imaging alone - 37% of asymptomatic 20-year-olds and 96% of 80-year-olds have degeneration
- Commonest operation: interbody fusion (ALIF/TLIF) for concordant single-level refractory pain
- Alternative: disc arthroplasty in the young patient with intact facets
- Outcome: 63% much better or better at 2 years versus 29% non-operative (Fritzell). Improvement, not cure
- NICE advises against fusion for axial low back pain outside a randomised trial
- Discography is not required before surgery and accelerates degeneration in the discs it punctures
Evidence Base
Swedish Lumbar Spine Study (2001 Volvo Award)
- RCT of 294 patients with severe chronic LBP and L4-S1 disc degeneration: fusion vs non-surgical care
- Back pain reduced 33% with fusion vs 7% non-surgical at 2 years (P=0.0002)
- 63% of surgical patients rated 'much better/better' vs 29% non-surgical (P less than 0.0001)
- Net back-to-work rate favoured surgery (36% vs 13%); early surgical complication rate 17%
ProDisc-L FDA IDE Trial
- RCT of 286 patients: ProDisc-L total disc replacement vs circumferential fusion for 1-level DDD (L3-S1)
- At 24 months ODI improvement in 91.8% of TDR vs 84.5% of fusion patients
- Neurological success and patient satisfaction superior in TDR group (P=0.034, P=0.015)
- Functional range of motion maintained in 93.7% of TDR patients (mean 7.7 degrees)
MRI Degeneration in Asymptomatic Individuals
- Systematic review of 33 studies, 3110 asymptomatic individuals
- Disc degeneration prevalence rose from 37% at age 20 to 96% at age 80
- Disc bulge prevalence rose from 30% at age 20 to 84% at age 80
- Degenerative imaging features are largely part of normal aging
Modic Endplate Changes Classification
- Defined Type I (T1 dark/T2 bright, edema-fibrovascular) and Type II (T1 bright, fatty marrow) endplate changes
- All endplate changes associated with degenerative disc disease at that level
- Type I converted to Type II over 14 months to 3 years in 5 of 6 patients followed
- Type II changes remained stable over 2-3 years
Kirkaldy-Willis Degenerative Cascade
- Described the three-phase model of segmental spinal degeneration
- Dysfunction phase: annular tears, facet synovitis, minor instability
- Instability phase: disc resorption, height loss, capsular laxity and abnormal motion
- Stabilization phase: osteophytosis and fibrosis reduce motion and often reduce axial pain
Discography Accelerates the Degeneration It Measures (2009 ISSLS Prize)
- 10-year matched cohort: 50 subjects who underwent L3/4, L4/5 and L5/S1 discography in 1997 versus 52 matched controls, all re-imaged with a blinded protocol MRI
- Progression of disc degeneration in 54 discs (35%) after discography versus 21 (14%) in controls (P=0.03)
- 55 new disc herniations versus 22 in controls (P=0.0003), disproportionately on the side of the annular puncture (P=0.0006)
- Greater loss of disc height (P=0.05) and signal intensity (P=0.001), using modern small-gauge low-pressure technique
Adjacent Segment Disease After Lumbar Fusion - Long-Term Survivorship
- 215 posterior lumbar arthrodeses, mean follow-up 6.7 years, with adjacent-level surgery as the endpoint
- 59 patients (27.4%) developed adjacent-level degeneration and underwent further decompression (15) or arthrodesis (44)
- Kaplan-Meier predicted symptomatic adjacent segment disease in 16.5% at 5 years and 36.1% at 10 years
- No correlation with length of fusion or with the preoperative arthritic grade of the adjacent segment
Antibiotics for Modic Changes - the AIM Trial
- 180 patients with chronic low back pain, previous disc herniation and type 1 (n=118) or type 2 (n=62) Modic changes, randomised to 3 months of amoxicillin 750 mg three times daily or placebo across six Norwegian hospitals
- Minimal clinically important between-group RMDQ difference predefined as 4 points
- Observed difference at 1 year was only -1.6 (95% CI -3.1 to 0.0, P=0.04); -2.3 in the type 1 subgroup and -0.1 in type 2
- Drug-related adverse events in 50 patients (56%) on amoxicillin versus 31 (34%) on placebo
References
- Fritzell P, Hagg O, Wessberg P, Nordwall A. 2001 Volvo Award Winner in Clinical Studies: Lumbar fusion versus nonsurgical treatment for chronic low back pain: a multicenter randomized controlled trial from the Swedish Lumbar Spine Study Group. Spine. 2001;26:2521-2532.
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015;36(4):811-6.
- Modic MT, Steinberg PM, Ross JS, et al. Degenerative disk disease: assessment of changes in vertebral body marrow with MR imaging. Radiology. 1988;166:193-199.
- Kirkaldy-Willis WH, Farfan HF. Instability of the lumbar spine. Clin Orthop Relat Res. 1982;(165):110-23.
- Zigler J, Delamarter R, Spivak JM, et al. Results of the prospective, randomized, multicenter Food and Drug Administration investigational device exemption study of the ProDisc-L total disc replacement versus circumferential fusion for the treatment of 1-level degenerative disc disease. Spine. 2007;32:1155-1162.