Avascular Tissue | Limited Intrinsic Healing | Repair Strategies
- Articular cartilage is avascular - no blood supply limits healing
- Partial thickness injuries do not heal due to no marrow access
- Full thickness defects heal with fibrocartilage (Type I collagen)
- Fibrocartilage is biomechanically inferior to hyaline cartilage
- Surgical strategies aim to restore hyaline-like tissue
- “Type II collagen in hyaline vs Type I in fibrocartilage repair
- “Chondrocytes have minimal mitotic activity in adults
- “Synovial fluid provides nutrition via diffusion
- “Subchondral bone breach necessary for any spontaneous repair
Overview
Articular cartilage is a specialised connective tissue built for load bearing and joint articulation. The composition and structure that give it excellent mechanical function also leave it with virtually no intrinsic healing capacity.
Why it matters. Cartilage injuries are common, affecting up to 60% of patients undergoing knee arthroscopy. Because the tissue cannot heal spontaneously, injury leads to progressive joint degeneration and osteoarthritis, and understanding its biology is essential for choosing a treatment rationally.
Hunter's warning. Hunter's 1743 statement that "ulcerated cartilage is a troublesome thing, once destroyed it is not repaired" remains relevant. Modern surgical techniques try to overcome this biological limitation through a range of regenerative strategies.
Structure and Composition
The matrix. Articular cartilage consists of chondrocytes embedded in an extensive extracellular matrix (ECM), which makes up about 95% of tissue volume; the chondrocytes are only 5%. By wet weight the matrix is:
- Water, 65-80%, trapped by the charge of the proteoglycans, which gives compressive stiffness through fluid pressurisation
- Collagen, 10-20%, predominantly Type II, arranged in zone-specific orientations to provide tensile strength and the tissue's architecture, with smaller amounts of Types IX and XI
- Proteoglycans, 5-10%, chiefly aggrecan, bound to hyaluronic acid; glycosaminoglycans (chondroitin sulphate, keratan sulphate) create the negative charge that attracts water
The zones. Collagen orientation, cell shape and function change with depth from the surface, down to a calcified layer that makes the transition to subchondral bone.
- Depth from Surface
- 10-20%
- Collagen Orientation
- Parallel to surface
- Cell Shape
- Flat, elongated
- Function
- Shear resistance, joint lubrication
- Depth from Surface
- 40-60%
- Collagen Orientation
- Random/oblique
- Cell Shape
- Rounded
- Function
- Transition zone, shock absorption
- Depth from Surface
- 30%
- Collagen Orientation
- Perpendicular
- Cell Shape
- Columnar
- Function
- Resist compression, anchor to bone
- Depth from Surface
- Variable
- Collagen Orientation
- Into subchondral bone
- Cell Shape
- Hypertrophic
- Function
- Transition to subchondral bone
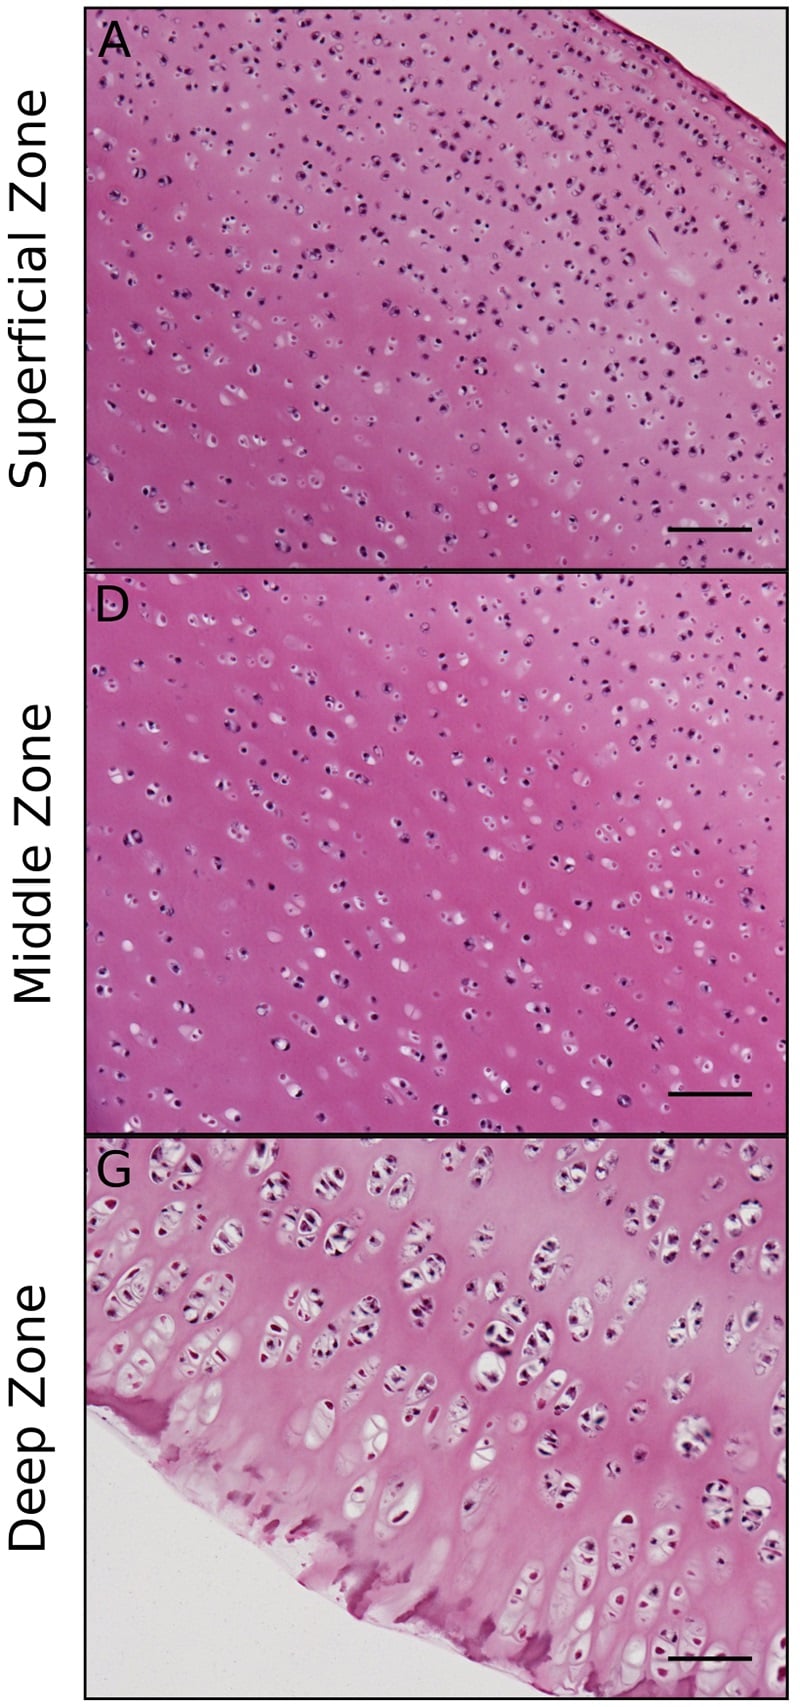
Why Cartilage Cannot Heal
Nothing arrives to repair it. Articular cartilage is avascular, aneural and alymphatic, and adult chondrocytes have minimal mitotic activity. With no blood supply there is no inflammatory response and no marrow-derived stem cells. Nutrition reaches the chondrocytes only by diffusion from synovial fluid, and matrix turnover is extremely slow.
AAAAWhy Cartilage Cannot Self-Repair
Hook:Four As = Four reasons cartilage cannot heal!
Partial-thickness injury. An injury confined to cartilage above the tidemark has no access to:
- Blood supply, so no inflammatory cells
- Bone marrow, so no mesenchymal stem cells
- Clotting factors, so no fibrin scaffold
The chondrocytes beside the injury have limited mitotic capacity and cannot migrate to fill the defect. Proteoglycan is depleted around the rim of the lesion, and that leads to progressive degeneration.
The tidemark separates calcified from non-calcified cartilage. Injuries above the tidemark (partial thickness) cannot heal. Only injuries penetrating through the calcified cartilage to subchondral bone can access marrow elements for any repair response.
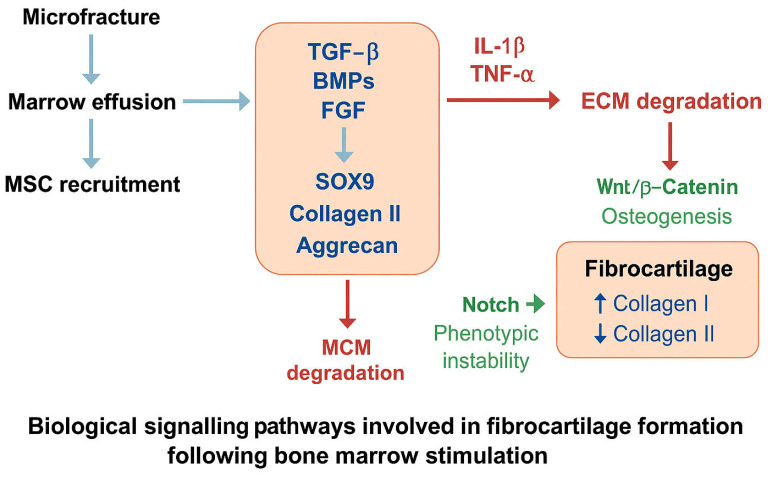
Full-thickness injury. When the injury penetrates subchondral bone, marrow elements reach the defect and a repair sequence follows:
- Haemorrhage and clot formation, which lays down a fibrin scaffold
- An inflammatory response, with macrophages and growth factors
- Migration of marrow-derived stem cells (MSCs) into the defect
- Differentiation of those cells into fibrochondrocytes, forming fibrocartilage
- Production of Type I collagen, and an inferior repair tissue
What that repair is worth. The result is fibrocartilage, made of Type I collagen, in place of hyaline cartilage made of Type II. It is less stiff in compression, resists wear poorly and tends to deteriorate over time under load.
Assessment and Differential Diagnosis
A diagnosis of exclusion. A focal chondral defect is a clinical diagnosis of exclusion. Several conditions mimic its presentation of mechanical knee pain, effusion and catching, and they must be distinguished because management differs entirely.
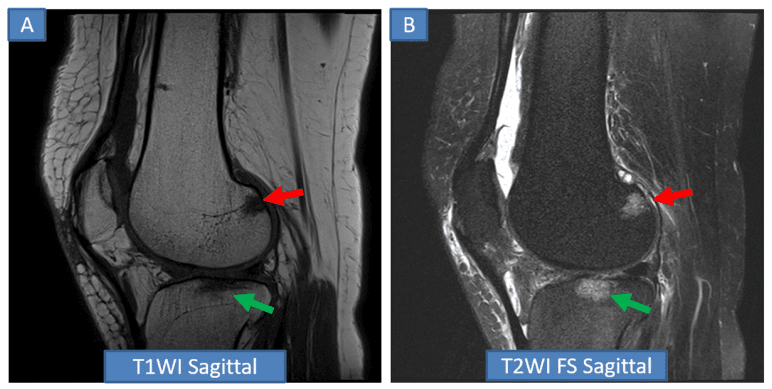
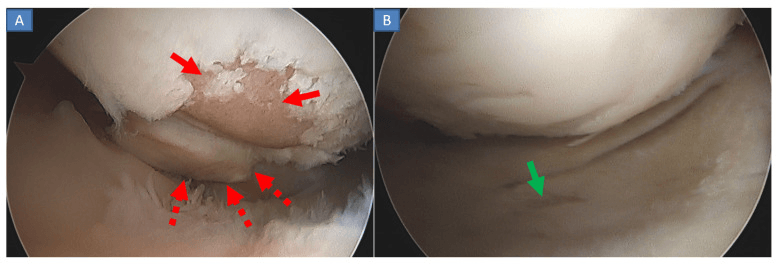
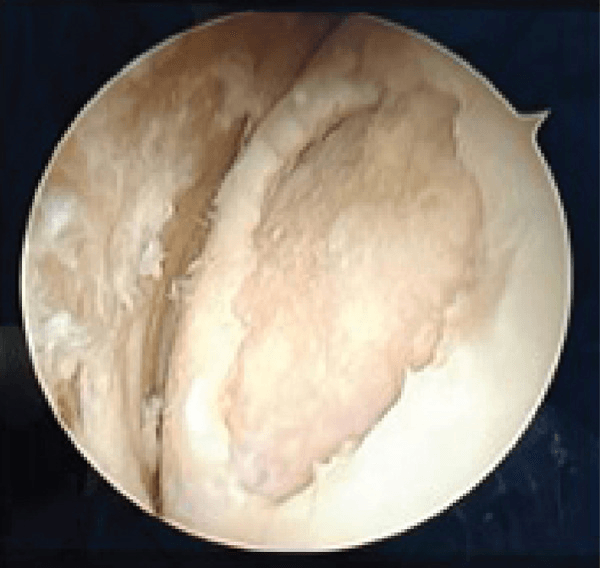
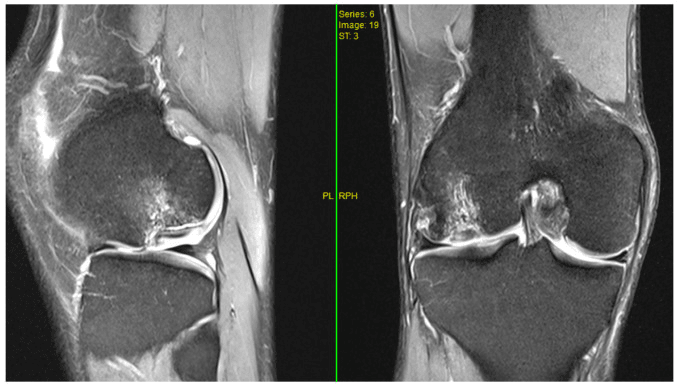
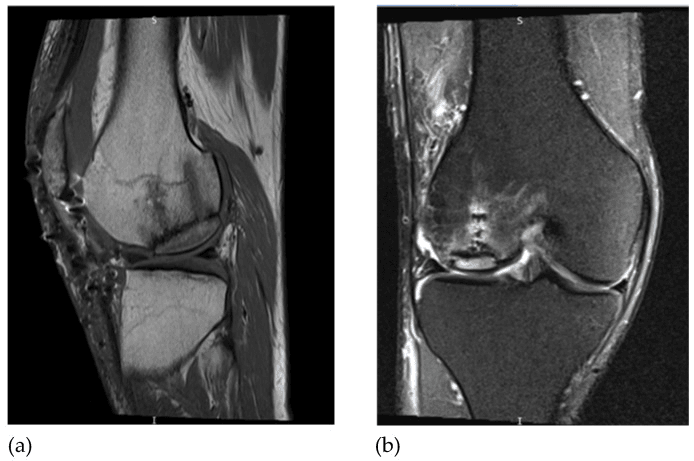
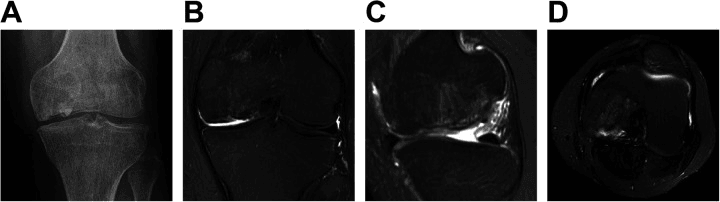
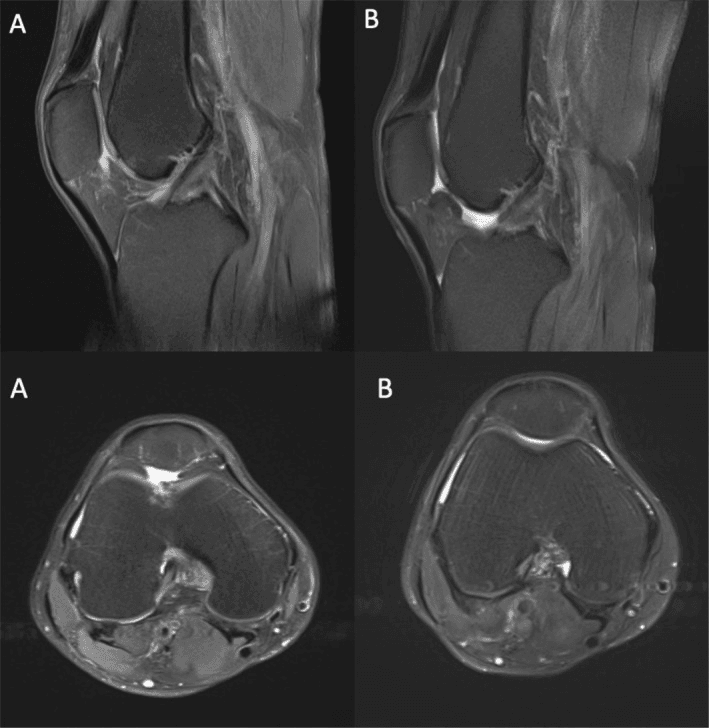
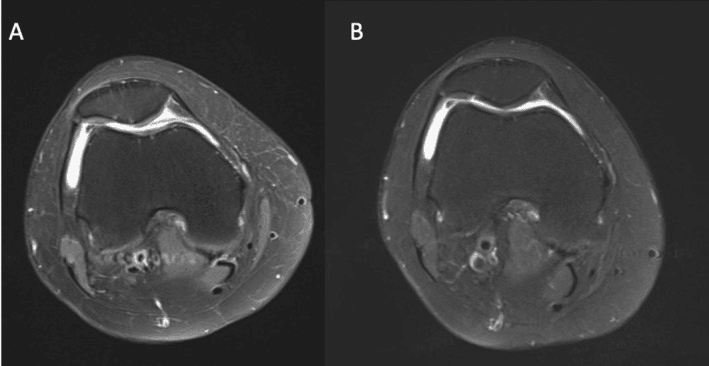
Defining the lesion. MRI localises a focal osteochondral lesion and its subchondral response, which distinguishes a contained repair target from diffuse cartilage loss. Direct arthroscopic inspection defines lesion size, containment and unstable tissue more accurately than surface imaging alone, and associated findings such as a loose body or tibial damage also change the repair plan.
- Key Distinguishing Feature
- Discrete injury event, well-defined lesion edges
- Imaging Hallmark
- Full-thickness defect with stable shoulders on MRI
- Implication for Repair
- Candidate for marrow stimulation, OAT or ACI
- Key Distinguishing Feature
- Adolescent/young adult, insidious onset
- Imaging Hallmark
- Subchondral bone fragment +/- separation; bone oedema
- Implication for Repair
- Subchondral bone must be addressed — favours OAT/OCA, not isolated microfracture
- Key Distinguishing Feature
- Older patient, multi-compartment, malalignment
- Imaging Hallmark
- Joint-space narrowing, osteophytes, bipolar wear
- Implication for Repair
- Contraindication to focal repair; treat as OA (osteotomy/arthroplasty)
- Key Distinguishing Feature
- Sudden onset, risk factors (steroids, alcohol)
- Imaging Hallmark
- Subchondral crescent sign, geographic marrow oedema
- Implication for Repair
- Requires osteochondral allograft or arthroplasty, not cell therapy
- Key Distinguishing Feature
- Joint-line pain, positive provocative tests
- Imaging Hallmark
- Meniscal signal reaching articular surface
- Implication for Repair
- Treat meniscus; an unaddressed tear undermines any cartilage repair
Before committing to any cartilage repair, confirm a stable, well-aligned, ligament-competent knee with intact menisci. Malalignment, instability or meniscal deficiency are the commonest reasons a technically good repair fails — they must be corrected concurrently (osteotomy, ligament reconstruction, meniscal repair/transplant).
Repair Strategies
The goal. Every surgical option aims to restore hyaline-like tissue. Microfracture produces fibrocartilage; osteochondral autograft (OATS) and fresh osteochondral allograft (OCA) transplant true hyaline cartilage; autologous chondrocyte implantation (ACI/MACI) aims for hyaline-like regeneration, with variable success.
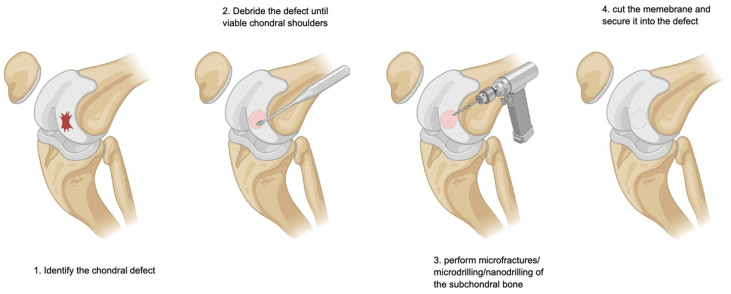
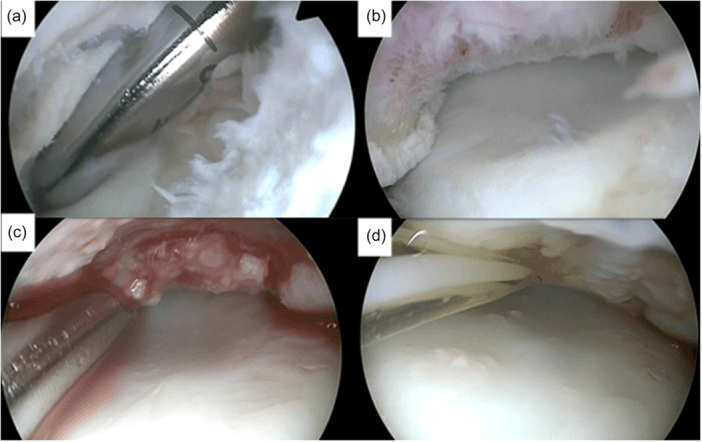
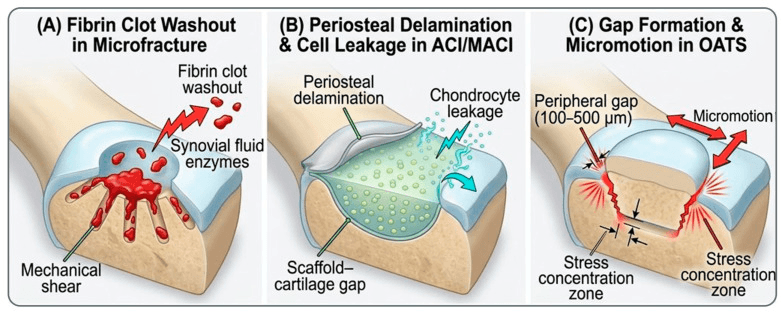
Microfracture. Microfracture is the most commonly performed cartilage repair procedure, and widely used because it is simple and cheap. Holes of 3-4mm are made in the subchondral bone at 3-4mm intervals, and marrow bleeding into the defect supplies MSCs, growth factors and a fibrin scaffold for the repair tissue, which is fibrocartilage.
Indications. It suits smaller defects, under 2-4 cm², that are contained with stable shoulders, and many centres use it as first-line treatment.
Outcomes. Short-term results are good, but they deteriorate at 5-8 years as the fibrocartilage degenerates under load.
Osteochondral Allograft
Why it is not rejected. Fresh osteochondral allograft transplants donor cartilage without HLA matching or immunosuppression, which is surprising for an allograft. Because cartilage is avascular, aneural and alymphatic, and its dense matrix physically shields the chondrocytes from the host immune system, it is relatively immunoprivileged and is not rejected the way a vascularised organ graft would be. Donor grafts are screened for disease transmission and matched for size and topography to restore the joint contour, but need no blood-group or HLA matching.
Viability is the currency. The transplanted chondrocytes must survive to maintain the matrix, and viability declines with storage time. Fresh grafts are therefore used within roughly 28 days, and a viability above about 70% is the commonly cited target for a usable graft.
What integrates. The bone is a non-living scaffold that the host revascularises and remodels by creeping substitution. The cartilage does not "heal in" but delivers mature hyaline function from the start, which is why OCA suits large (over 4 cm²) or osteochondral defects, salvage and AVN, where the subchondral bone must also be replaced.
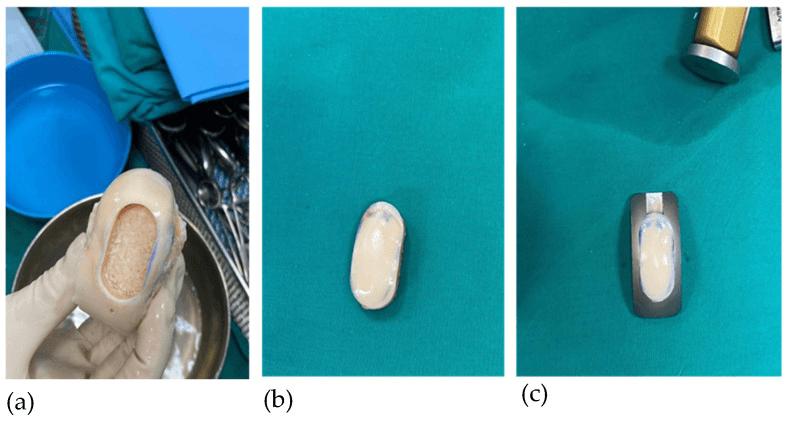
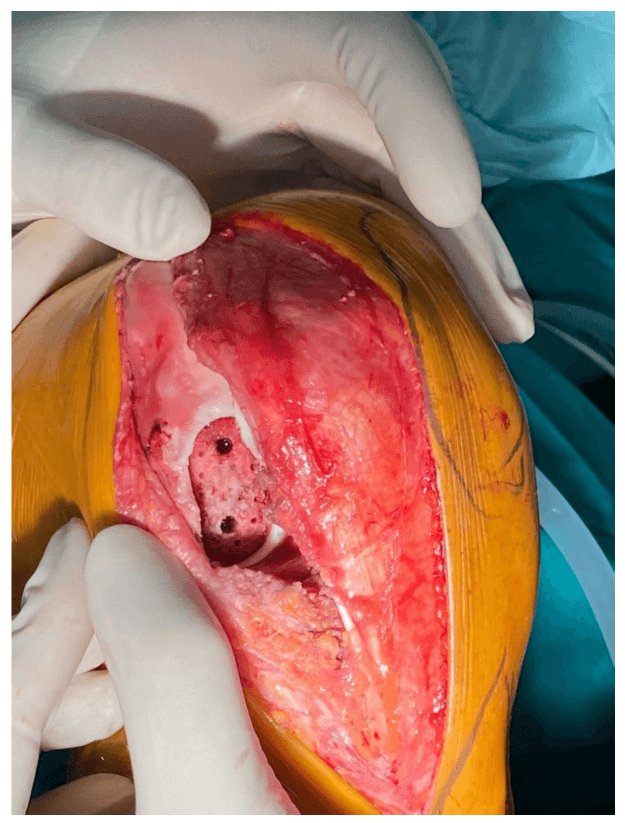
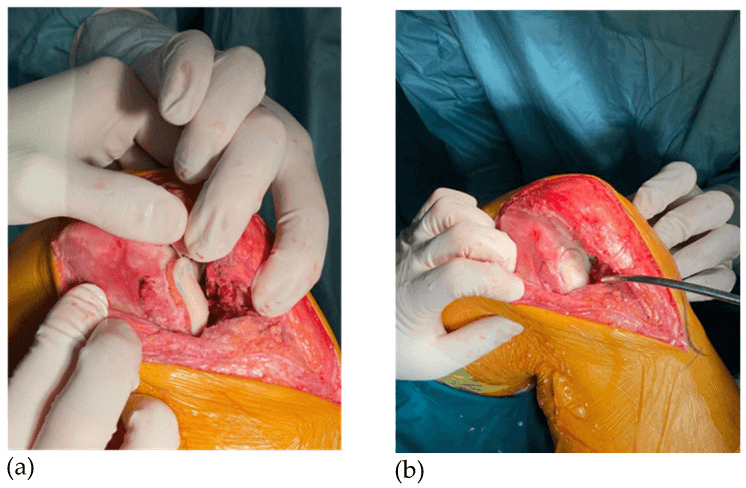
Technique. Planning and implantation rest on four points:
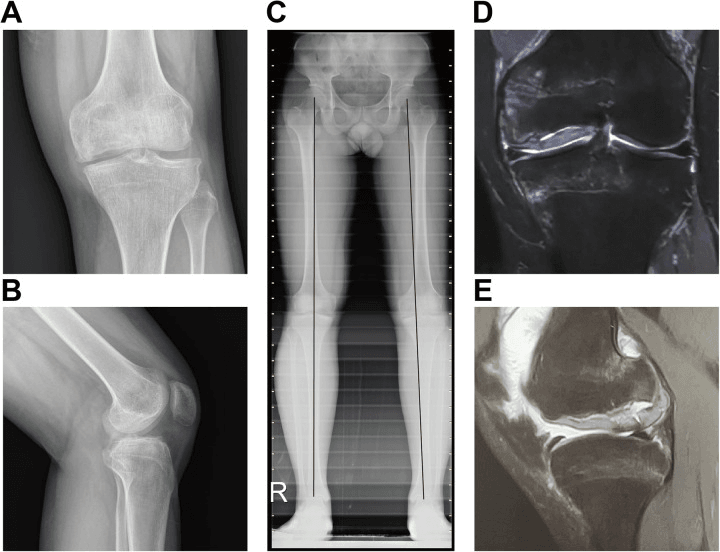
- Weight-bearing radiographs, long-leg alignment and MRI define the defect dimensions, bone loss, joint-space condition and mechanical environment before a structural graft is selected
- The donor cartilage-bone segment is cut to final dimensions and trialled against the recipient template so that contour, thickness and orientation match before implantation
- The diseased osteochondral unit is reamed to a stable bed of known depth, allowing a press-fit graft without proud or recessed cartilage edges
- The graft is inserted in its planned orientation and tamped flush with the surrounding cartilage, minimising step-off and shear at the host-graft interface
Choosing a Technique
- Defect Size
- Under 2-4 cm²
- Repair Tissue
- Fibrocartilage (Type I)
- Stages
- Single
- Durability
- 5-8 years good results
- Defect Size
- Under 3-4 cm²
- Repair Tissue
- Hyaline (transferred)
- Stages
- Single
- Durability
- Good long-term if matched
- Defect Size
- Over 4 cm²
- Repair Tissue
- Hyaline (donor)
- Stages
- Single
- Durability
- Variable, depends on viability
- Defect Size
- 2-10 cm²
- Repair Tissue
- Hyaline-like
- Stages
- Two
- Durability
- Good 10-15 year data emerging
Beyond defect size. The size ranges in the table overlap, and the rest of the choice turns on these:
- Microfracture: first-line for smaller defects, low cost, single stage
- OATS: smaller defects where hyaline cartilage is wanted in a single stage, limited by donor tissue
- ACI/MACI: larger defects in younger patients willing to undergo two operations
- OCA: large defects, salvage and AVN, and it requires fresh tissue to be available
Is there a size threshold? The historical 2 cm² cut-off between microfracture and ACI is not firmly evidence-based. The SUMMIT trial used 3 cm², while registries suggest microfracture underperforms even below 2 cm² in high-demand patients. The true threshold is patient- and lesion-specific, not a fixed number.
Does microfracture do harm? Perforating the subchondral plate can produce intralesional osteophytes, subchondral cysts and bony overgrowth, and may compromise later procedures. Some surgeons now prefer subchondral-sparing nanofracture or microdrilling, with smaller-diameter, deeper channels, to reduce thermal necrosis and plate damage, but high-level comparative data remain limited.
Biological augmentation. Platelet-rich plasma (PRP) and bone marrow aspirate concentrate (BMAC) are widely used to "augment" marrow stimulation, but the evidence is heterogeneous and largely low-level. No standardised preparation exists, and robust RCT data do not yet support routine use.
Repair versus natural history. Many small, asymptomatic chondral lesions found incidentally at arthroscopy may never become symptomatic, so over-treatment is a genuine risk. The decision to intervene should be driven by symptoms attributable to the lesion, not by its mere presence on MRI.
Management Algorithm
Rehabilitation After Cartilage Repair
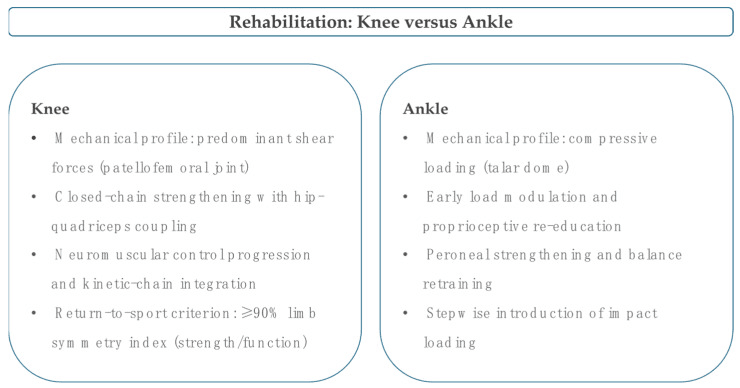
Why it decides the result. Rehabilitation after cartilage repair is decisive and easily overlooked, and the durability data above hinge on it. Repair tissue matures slowly and is vulnerable to premature loading.
The maturation window. Repair tissue, fibrocartilage after marrow stimulation or hyaline-like tissue after ACI/MACI, is soft and disorganised at first and remodels over roughly 12 to 18 months. Rehabilitation protects it while it matures.
Early motion. Salter's work established that continuous passive motion (CPM) nourishes chondral repair tissue and promotes a more hyaline-like result than immobilisation. Early protected motion is therefore standard after most cartilage procedures, within joint-specific limits.
Weight-bearing follows the lesion location.
- Femoral condyle or tibial (weight-bearing) lesions: restricted or protected weight-bearing, touch or partial, for about 6 to 8 weeks with early full range of motion, so the repair is moved but not compressed
- Patellofemoral (trochlea or patella) lesions: weight-bearing in extension is usually allowed, but flexion is restricted with a brace to keep shear and load off the repair during the vulnerable phase
Return to sport. Impact and pivoting sport are resumed deliberately late, commonly around 6 to 9 months after microfracture and 9 to 18 months after ACI/MACI or osteochondral procedures. Premature return is a leading cause of repair failure.
Match the weight-bearing and range-of-motion restriction to the lesion location, and respect the long maturation window: a technically perfect repair fails if it is loaded too soon.
Guidelines, Registries & Global Practice
Global Epidemiology
Focal chondral or osteochondral lesions are found in roughly 60% of knee arthroscopies, with full-thickness (ICRS grade III-IV) lesions in around 5-11%. They are most common in active patients in the third and fourth decades, and a substantial minority are associated with concurrent ligament or meniscal injury — reinforcing that cartilage damage is rarely an isolated problem.
Side-by-Side Guidance
- Position
- ACI supported for defined defects with adequate evidence and governance; arthroscopic washout not recommended for OA
- Practical Emphasis
- Cell therapy concentrated in specialist centres with audit; resist its use in established OA
- Position
- Evidence-based work groups acknowledge multiple effective options but note limited high-level comparative data
- Practical Emphasis
- Shared decision-making; technique tailored to lesion size and patient demand
- Position
- Algorithm by defect size, depth, location and patient factors; address subchondral bone and joint environment
- Practical Emphasis
- Size-based selection (marrow stimulation small, OAT small-medium, ACI/OCA large)
- Position
- Emphasise treating malalignment, instability and meniscal deficiency concurrently
- Practical Emphasis
- A repair in a hostile joint will fail — correct the environment first
Registry & Resource Notes
- Dedicated cartilage registries (e.g. the German Cartilage Registry / KnorpelRegister DGOU and national procedure registries) track repair outcomes; unlike arthroplasty, cartilage procedures are not consistently captured in joint-replacement registries.
- High-resource settings: full menu available — matrix-assisted ACI, fresh osteochondral allograft, and biologic augmentation in specialist centres.
- Limited-resource settings: marrow stimulation (microfracture/microdrilling) and osteochondral autograft dominate because they are single-stage, low-cost and need no cell-culture facility or tissue bank. Fresh allograft availability is constrained by tissue-banking infrastructure and short chondrocyte viability windows.
MCQ Practice Points
Q: Why does articular cartilage have limited intrinsic healing capacity?
A: Articular cartilage is avascular, aneural, and alymphatic with low cellularity (chondrocytes comprise only 1-5% of tissue volume). Without blood supply, there is no inflammatory response or access to mesenchymal stem cells. Chondrocytes have limited proliferative capacity and are trapped in the dense ECM, unable to migrate to injury sites. This contrasts with bone which heals through vascular-mediated inflammation.
Q: What is the mechanism of cartilage repair with microfracture, and what type of repair tissue forms?
A: Microfracture creates 3-4mm deep holes through subchondral bone, allowing bone marrow blood and mesenchymal stem cells (MSCs) to access the chondral defect. A fibrin clot forms and MSCs differentiate into chondrocyte-like cells. However, the repair tissue is fibrocartilage (predominantly Type I collagen) rather than hyaline cartilage (Type II collagen), with inferior biomechanical properties and durability.
Q: What are the indications for OATS vs ACI/MACI for cartilage defects?
A: OATS (osteochondral autograft): Small contained defects (1-4 cm²), single lesion, young active patients. ACI/MACI: Larger defects (2-10 cm²), failed prior treatment, young patients. OATS provides immediate mature hyaline cartilage but is limited by donor site morbidity and available graft. ACI/MACI generates hyaline-like cartilage but requires two surgeries (harvest then implantation) and specialized cell culture facilities.
Q: What are the key differences between fibrocartilage and hyaline cartilage repair tissue?
A: Hyaline cartilage: Type II collagen (90-95%), proteoglycan-rich with organized columnar structure, superior compressive stiffness and durability. Fibrocartilage: Type I collagen predominates, disorganized fibrous structure, lower proteoglycan content, inferior biomechanical properties, prone to degeneration under repetitive loading. Clinical significance: Fibrocartilage repair (from microfracture) deteriorates after 2-5 years, while hyaline-like repair (from ACI/MACI) has better long-term durability.
Q: What is the "super clot" concept in cartilage repair?
A: The super clot involves augmenting the basic microfracture blood clot with biologics to improve repair tissue quality. Components may include: PRP (growth factors), bone marrow aspirate concentrate (BMAC) for additional MSCs, hyaluronic acid scaffold for cell retention, and fibrin glue for clot stability. The goal is to create an enhanced biologic environment that promotes differentiation toward hyaline-like cartilage rather than fibrocartilage.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Explain why articular cartilage has poor intrinsic healing capacity and how this influences treatment strategies.”
“A 28-year-old footballer has a 2.5 cm squared full thickness cartilage defect on the medial femoral condyle. What are your treatment options?”
“The literature is full of cartilage repair studies. How would you critically appraise the evidence, and what does it tell you about choosing between microfracture and cell-based repair?”
Why Cartilage Cannot Heal (AAAA)
- Avascular - no blood supply
- Aneural - no nerve supply
- Alymphatic - no lymphatics
- Amitotic - minimal cell division
Composition
- Water 65-80%
- Aggrecan (proteoglycan)
- Type II collagen
- ECM 95% of volume
- Rare cells (chondrocytes 5%)
Repair Tissue Comparison
- Hyaline = Type II collagen (native)
- Fibrocartilage = Type I collagen (repair)
- Fibrocartilage biomechanically inferior
- Deteriorates under load over time
Treatment Options
- Microfracture - marrow stim, fibrocartilage
- OATS - autograft, hyaline, single stage
- Cell-based (ACI/MACI) - hyaline-like
- Hyaluronic scaffolds - matrix-assisted
- Allograft (OCA) - large defects
Evidence Base
Knutsen et al — ACI vs Microfracture RCT (5-year)
- Multicentre RCT: 80 patients with a single femoral condyle defect randomised to ACI or microfracture
- Both groups improved significantly vs baseline at 2 and 5 years
- Satisfactory results in 77% of patients in both arms at 5 years — no significant difference between techniques
- Failures rose from 1-2 at 2 years to 9 (23%) per arm at 5 years; one-third had early radiographic OA at 5 years
- No correlation between histological repair quality and clinical outcome - BUT with a qualifier the summary usually drops: none of the patients with the best-quality (predominantly hyaline) cartilage at 2 years went on to fail. Younger patients did better in both groups.
Saris et al — SUMMIT MACI vs Microfracture (2-year)
- RCT of 144 patients with symptomatic defects 3 cm squared or larger (Outerbridge III-IV), mean lesion 4.8 cm squared
- KOOS pain and function improved significantly more with MACI than microfracture at 2 years (p=0.001)
- Treatment failures (non-responders): MACI 12.5% vs microfracture 31.9% (p=0.016)
- MRI/histology repair tissue quality good in both arms with no significant structural difference
Brittberg et al — SUMMIT Extension (5-year)
- 5-year follow-up of the SUMMIT RCT; 128 of 144 patients continued (65 MACI, 63 microfracture)
- Superiority of MACI over microfracture in KOOS pain and function maintained at 5 years (p=0.022)
- Activities-of-daily-living advantage persisted (p=0.007); QOL and other symptoms favoured MACI but lost significance
- MRI defect fill improved in both arms with no significant between-group structural difference
Mithoefer et al — Microfracture Systematic Review
- Systematic review of 28 studies, 3122 patients (6 RCTs), mean follow-up 41 months
- Microfracture reliably improves knee function within the first 24 months
- Reports on durability of that improvement were conflicting, with possible functional deterioration
- Smaller defects, younger age and good macroscopic repair quality predicted better outcomes