The Classic Cavus Foot Neuropathy
- Cavovarus Foot: Hindfoot varus driven by plantarflexed first ray.
- Coleman Block Test: Determines if hindfoot varus is forefoot driven (supple).
- Peroneus Brevis: First muscle affected (weak evertors).
- Surgical Principle: Soft tissue if supple, bony if rigid.
- CMT1A: Most common type, PMP22 duplication.
- “Coleman block test is essential
- “Weakness pattern: peroneus brevis first
- “Classic appearance: champagne bottle calves
- “Surgery depends on flexibility
Overview and Epidemiology
Charcot-Marie-Tooth disease (CMT), also called hereditary motor and sensory neuropathy (HMSN), is the most common inherited peripheral neuropathy, with a prevalence of 1 in 2,500. It causes progressive distal weakness and sensory loss, and orthopaedic management centres on the cavovarus foot it produces.
Inheritance. Autosomal dominant inheritance is the most common, but autosomal recessive and X-linked forms also occur. CMT1A is the most common subtype (70%), caused by duplication of the PMP22 gene on chromosome 17p.
Presentation. Patients typically present in childhood or adolescence with foot deformity and gait abnormalities.
Pathophysiology and Mechanism
Muscle imbalance. The cavovarus foot is the work of strong muscles overpulling weak ones. Peroneus brevis is affected first and tibialis anterior next, while tibialis posterior and peroneus longus are strong. The components of the deformity follow:
- Varus - peroneus brevis, the evertor, is weaker than tibialis posterior, the invertor
- Cavus - as tibialis anterior weakens, tibialis posterior and peroneus longus (the plantarflexor of the first ray) overpower it and the arch rises
- Hindfoot varus is secondary - the plantarflexed first ray drives the hindfoot into varus, a forefoot-driven hindfoot varus
- Claw toes - from intrinsic muscle weakness
PMP22 Gene Dosage and the Reciprocal HNPP
Why a duplication causes disease. The CMT1A locus is a segment of roughly 1.4 megabases on chromosome 17p11.2 (Lupski's landmark report gave 1.5 Mb) that contains PMP22, peripheral myelin protein 22, a structural protein of Schwann-cell myelin. A tandem duplication of the segment gives three copies of PMP22 instead of two, so the Schwann cell over-expresses it. The protein is normal and its dose is not, which is what "gene-dosage disorder" means.
What the extra dose does. PMP22 over-expression destabilises compact myelin, causing the demyelination, slowed conduction and secondary axonal loss of CMT1A.
The reciprocal deletion. The same unequal crossover that duplicates the segment in one offspring deletes it in the reciprocal product. A single, haploinsufficient copy of PMP22 causes hereditary neuropathy with liability to pressure palsies (HNPP).
How HNPP differs. Where CMT1A is a diffuse demyelinating neuropathy with a cavovarus foot, HNPP presents with recurrent, painless focal palsies at common entrapment sites, provoked by minor compression or stretch: for example the peroneal nerve at the fibular head, the ulnar nerve at the elbow and the median nerve at the wrist. Biopsy shows tomaculous ("sausage-like") focal thickenings of the myelin.
Classification
The types are separated by pathology and nerve conduction velocity, then by gene.
- Pathology
- Demyelinating
- NCV
- Slow, often less than 38 m/s
- Genetics
- CMT1A: PMP22 duplication (17p). CMT1B: MPZ (P0) mutation
- Clinical
- Onset in the first decade, progressive weakness
- Pathology
- Axonal degeneration, myelin preserved
- NCV
- Normal or near-normal
- Genetics
- Multiple genes (MFN2, NEFL, etc.)
- Clinical
- Often later onset, milder
- Pathology
- Severe demyelinating
- NCV
- Markedly slow
- Genetics
- PMP22, MPZ or EGR2 mutations
- Clinical
- Onset in infancy, severe weakness, wheelchair-dependent
- Pathology
- X-linked
- NCV
- Intermediate
- Genetics
- GJB1 (connexin 32) mutation
- Clinical
- Males more severely affected, females mild or asymptomatic
Clinical Assessment
History. Ask about the age of onset, the progression and the family history, then about foot pain, instability, calluses and previous surgery.
Examination. The patient walks with a steppage gait because the dorsiflexors are weak. Then examine, in turn:
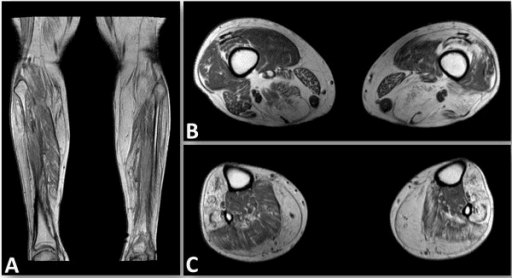
- The legs - distal atrophy with normal proximal bulk, the "champagne bottle" or "inverted champagne bottle" calves
- The feet - a high arch (cavus), hindfoot varus and claw toes
- Flexibility of the hindfoot, the first ray and the ankle, including the Coleman block test
- Sensation, diminished distally, and reflexes, diminished or absent
- The hands, involved late, with intrinsic wasting and a claw hand
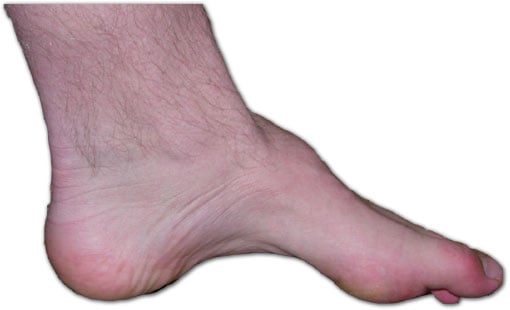
The Coleman block test is essential, because it determines the surgical approach. The patient stands on a block and the first ray is allowed to drop, which eliminates the effect of forefoot pronation. There are two results:
- Corrects (positive) - the hindfoot varus resolves, so the deformity is forefoot-driven by the plantarflexed first ray and is supple: soft-tissue procedures
- Does not correct (negative) - the hindfoot varus persists, a fixed hindfoot deformity that is rigid: bony surgery (osteotomy or fusion)
Investigations
Nerve conduction studies make the first split, between the slow velocities of CMT1 and the normal or near-normal velocities of CMT2 (see Classification).
Genetic testing is confirmatory, and in CMT1A the finding is the PMP22 duplication. Because CMT1A and HNPP are disorders of PMP22 dosage, PMP22 dosage testing, not just sequencing, is the key investigation.
Radiographs. Weight-bearing radiographs of the foot, assessing:
- Meary's angle (the talo-first metatarsal angle)
- Calcaneal pitch
- Hindfoot alignment
Differential Diagnosis
A cavovarus foot is a neurological diagnosis until proven otherwise. CMT is the most common cause, but the examiner will expect you to exclude the alternatives below. Bilateral symmetric deformity with a positive family history points to CMT; a unilateral or rapidly progressive cavus foot should prompt MRI of the neuraxis to exclude a tethered cord or intraspinal tumour.
- Lesion type
- Peripheral neuropathy (LMN)
- Laterality / pattern
- Bilateral, symmetric, slowly progressive
- Discriminating features
- Family history, distal atrophy, absent reflexes, slow NCV (CMT1), PMP22 duplication
- Lesion type
- Spinocerebellar degeneration
- Laterality / pattern
- Bilateral, progressive
- Discriminating features
- Cerebellar ataxia, dysarthria, hypertrophic cardiomyopathy, diabetes, GAA repeat in FXN
- Lesion type
- UMN / mixed
- Laterality / pattern
- Often unilateral or asymmetric
- Discriminating features
- Back signs, bowel/bladder change; mandates whole-spine MRI — especially if unilateral
- Lesion type
- UMN (cerebral)
- Laterality / pattern
- Hemiplegic or diplegic
- Discriminating features
- Spasticity, brisk reflexes, clonus, birth history; equinovarus more typical than pure cavovarus
- Lesion type
- Anterior horn cell (LMN)
- Laterality / pattern
- Asymmetric, flaccid
- Discriminating features
- Non-progressive after acute illness, preserved sensation, endemic exposure
- Lesion type
- Structural
- Laterality / pattern
- Unilateral or bilateral
- Discriminating features
- Normal neurology, history of CTEV; diagnosis of exclusion
Management
The principle. Soft tissue if the foot is supple, bone if it is rigid, and the Coleman block test tells you which. The supple-foot list below still includes a first metatarsal dorsiflexion osteotomy.
Non-operative care. Physiotherapy for stretching and strengthening, an ankle-foot orthosis (AFO) for weak dorsiflexors, accommodative footwear, and avoiding high-impact activities.
The supple foot (Coleman positive). The operation rebalances the muscles and corrects the first ray:
- Plantar fascia release, to address the first ray plantarflexion
- First metatarsal dorsiflexion osteotomy, to correct the first ray
- Peroneus longus to brevis transfer, to rebalance eversion
- Tibialis posterior transfer to the dorsum, if needed
- Claw toe correction: the Jones procedure (EHL to the first metatarsal, with IP fusion); the Hibbs procedure (EDL to the lateral column)
The rigid foot (Coleman negative). The fixed deformity needs bone cut or fused:
- Dwyer calcaneal osteotomy, a lateral closing wedge, to correct the hindfoot varus
- First metatarsal osteotomy, if the ray is still plantarflexed
- Triple arthrodesis for severe rigid deformity
- Tendon transfers, as for the supple foot
Surgical Techniques
Plantar fascia release. Indicated when first ray plantarflexion contributes to the cavus. Through a medial incision the plantar fascia is released from the calcaneus, and the release may be combined with other procedures. Afterwards the patient weight-bears in an orthotic.
Dwyer osteotomy. A lateral closing-wedge calcaneal osteotomy for fixed hindfoot varus. Through a lateral approach a laterally based wedge is removed from the calcaneal tuberosity and the gap closed to correct the varus, then fixed with a staple or screw. The patient is non-weight-bearing for 6 weeks.
Triple arthrodesis. For severe rigid cavovarus, usually in adults or severe cases. Through medial and lateral approaches the subtalar, talonavicular and calcaneocuboid joints are fused, with the alignment corrected during the fusion. The patient is non-weight-bearing for 6-12 weeks, until fusion.
Complications and Outcomes
- Context
- Common due to progressive disease
- Management
- Monitor, repeat surgery may be needed
- Context
- Valgus/planovalgus
- Management
- Avoid overcorrection
- Context
- Osteotomy or fusion
- Management
- Revise with bone graft
- Context
- After triple arthrodesis
- Management
- Expected
- Context
- Casts, braces, insensate areas
- Management
- Careful orthotic management
Outcomes. CMT is progressive, so orthopaedic problems may recur. Soft-tissue procedures give good results in supple feet, though recurrence is possible. Bony procedures are more durable but sacrifice motion, and triple arthrodesis is definitive but stiff.
Beyond the Foot: Hip Dysplasia and Spinal Deformity
CMT is not only a foot disease, and two proximal manifestations are screened for in any patient with it.
Hip dysplasia. Acetabular dysplasia occurs in roughly 6 to 10 percent of children with CMT, far above the background rate. It is frequently asymptomatic until secondary changes appear, so it is easily missed if the focus stays distal, and missing an asymptomatic dysplastic hip is a recognised pitfall.
Why the newborn screen is not enough. The dysplasia is thought to arise from neuromuscular imbalance about the hip during growth, and it usually presents later, in childhood or adolescence, rather than in the neonate. A normal newborn screen does not exclude it.
Screening the hip. Obtain a screening AP pelvis in children diagnosed with CMT and keep a low threshold to repeat it. The general assessment and the reconstructive options (periacetabular or pelvic, and femoral osteotomy) are covered in the developmental dysplasia of the hip topics.
Spinal deformity. Scoliosis, and kyphoscoliosis, is more common in CMT than in the general population, again related to the underlying neuromuscular weakness, and the curves may behave more like neuromuscular than idiopathic curves. Examine the spine and consider a screening view in adolescents. Curve assessment and the bracing-versus-fusion decision follow the neuromuscular scoliosis principles covered in that topic.
Postoperative Care
- Cast or boot; non-weight-bearing for osteotomies and fusions, earlier weight-bearing after isolated soft-tissue releases
- Wound and neurovascular surveillance; elevation and swelling control
- Transition out of the cast as union progresses on radiographs
- Physiotherapy: range of motion first, then progressive strengthening of the transferred tendons
- Orthotics often needed long-term (AFO, custom insoles) to protect the correction as the neuropathy progresses
- Surveillance for recurrence of cavus or hindfoot varus; screen hips and spine at review
Guidelines, Registries & Global Practice
Global epidemiology
- CMT is the most common inherited neuromuscular disorder worldwide, prevalence approximately 1 in 2,500 across populations (Pareyson and Marchesi, Lancet Neurol — PubMed).
- CMT1A (PMP22 duplication) accounts for the majority of demyelinating disease; CMTX (GJB1) is the second most common overall. Subtype frequency varies modestly by region and by founder effects.
Guidance, side by side
- Emphasis
- Diagnostic algorithm: clinical pattern + inheritance + NCS, then targeted genetics (PMP22 first); no disease-modifying drug recommended
- Emphasis
- Cavovarus work-up is a neurological diagnosis; flexibility-based (Coleman block) operative algorithm — soft tissue if supple, osteotomy/fusion if rigid
- Emphasis
- Multidisciplinary neuromuscular pathway; unilateral or rapidly progressive cavus mandates neuraxis MRI
- Emphasis
- High-quality evidence that ascorbic acid does not modify CMT1A (Gess et al. — PubMed); rehabilitation and surgery remain the mainstays
Registries and trial networks
- No arthroplasty-style implant registry applies. The Inherited Neuropathies Consortium (INC) and CMT-TRIAAL/CMT-TRAUK networks provide natural-history and trial data using validated outcomes (CMT Neuropathy Score, CMTPedS in children).
High- vs limited-resource practice variation
- Well-resourced settings: confirmatory genetic panels, gait-lab assessment, custom AFOs, joint-sparing reconstruction with intra-operative pedobarography/fluoroscopy.
- Limited-resource settings: diagnosis is clinical and electrophysiological; management leans on bracing and a smaller menu of durable bony procedures (Dwyer osteotomy, triple arthrodesis) where follow-up and orthotic supply are constrained. The flexibility-based principle is universal regardless of resources.
Controversies and Areas of Uncertainty
- Timing of surgery in children. Whether to intervene early (while flexible, hoping to prevent fixed deformity) or to delay until growth and deformity stabilise is unresolved. Early soft-tissue balancing may need revision as the progressive neuropathy continues; there are no randomised data to settle the question.
- Soft-tissue reconstruction vs early arthrodesis. Long-term joint-sparing series (Ward et al. — PubMed) show durable function and lower arthritis rates than historical triple-arthrodesis cohorts, shifting practice toward osteotomy-and-transfer reconstruction. The threshold at which a foot is "too rigid" to reconstruct, and the role of midfoot tarsectomy versus triple fusion, remains debated.
- Tibialis posterior transfer. Routine transfer of tibialis posterior to the dorsum to address dropfoot is favoured by some surgeons and avoided by others who prefer to preserve it and use an AFO, given the progressive nature of the weakness.
- No disease-modifying therapy. Despite promising animal data, no drug (including ascorbic acid, definitively negative in Cochrane meta-analysis) alters the neuropathy. Gene-targeted therapies for CMT1A (PMP22 down-regulation) are in early-phase trials and are not yet standard of care.
- Genetic testing strategy. With next-generation sequencing panels now covering scores of CMT genes, the role of staged single-gene testing (PMP22 first) versus upfront panel testing is evolving and resource-dependent.
MCQ Practice Points
Q: The most common CMT type is caused by which genetic abnormality? A: PMP22 duplication (CMT1A) on chromosome 17p.
Q: What does a positive Coleman block test indicate? A: The hindfoot varus is forefoot-driven and supple. Soft tissue surgery is appropriate.
Q: Which muscle is affected first in CMT? A: Peroneus brevis (weak eversion → varus).
Q: What osteotomy corrects fixed hindfoot varus? A: Dwyer osteotomy (lateral closing wedge calcaneal osteotomy).
Q: What tendon transfer is done to address weak eversion in CMT? A: Peroneus longus to peroneus brevis transfer.
Q: What procedure is used for claw toes in CMT? A: Jones procedure (EHL transfer to first metatarsal head with IP fusion).
Self-Assessment Quiz
Additional Quiz Questions
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“14-year-old with bilateral cavus feet, claw toes, and weak ankle dorsiflexion. Family history of similar foot shape. Coleman block test shows hindfoot varus corrects when the first ray is allowed to drop.”
“Same patient 10 years later. Now 24. Feet have become rigid. Coleman block test negative. Recurrent ankle sprains, lateral foot pain.”
“How do you classify CMT?”
GENETICS
- CMT1A: PMP22 duplication
- Most common inherited neuropathy
- Autosomal dominant
- 1 in 2,500
CLINICAL
- Cavovarus foot
- Claw toes
- Champagne bottle calves
- Weak dorsiflexion
COLEMAN TEST
- Positive (corrects) = Supple
- Negative = Rigid
- Guides surgery
- Essential exam finding
SUPPLE FOOT SURGERY
- Plantar fascia release
- First MT osteotomy
- Peroneus longus to brevis
- Jones procedure
RIGID FOOT SURGERY
- Dwyer osteotomy
- Calcaneal closing wedge
- Triple arthrodesis
- Tendon transfers
EXAM PEARLS
- Peroneus brevis first affected
- NCV: CMT1 slow, CMT2 normal
- Progressive disease
- Recurrence common
Evidence Base
Lupski et al. — DNA duplication in CMT1A
- Identified a 1.5 Mb tandem duplication on chromosome 17p11.2 (PMP22 locus) completely linked to CMT1A
- Established CMT1A as a gene-dosage disorder caused by PMP22 over-expression
- Duplication detectable across different ethnic origins, enabling DNA-based diagnosis
Pareyson and Marchesi — Diagnosis, natural history and management of CMT
- Authoritative review confirming CMT as the most common inherited neuromuscular disorder with marked genotypic and phenotypic heterogeneity
- Diagnosis rests on clinical pattern, inheritance, nerve-conduction studies and DNA testing
- No disease-modifying drug exists; rehabilitation and surgery for skeletal deformity remain the mainstays of care