Anterior Compartment | Deep Peroneal Nerve (L5,S1) | Primary Toe Extensor
- Deep peroneal nerve innervation - injury causes foot drop
- Pain with passive toe plantarflexion = compartment syndrome sign
- Juncturae tendinae (85-90%) affect isolated testing
- EDL to 5th toe = preferred tendon transfer donor
- “Largest muscle in anterior compartment after TA
- “Block adjacent toes to test isolated EDL function
- “Fasciotomy must ensure muscle herniation
- “Accessory hallux slip may compensate for weak EHL
Extensor Digitorum Longus Anatomy
Overview
The extensor digitorum longus (EDL) is a pennate muscle of the anterior compartment of the leg, supplied by the deep peroneal nerve. It is the primary extensor of the lateral four toes and contributes to ankle dorsiflexion and foot eversion.
Why it matters. EDL sits at the centre of anterior compartment syndrome, where the fasciotomy must release all its fascial attachments, and it is a potential tendon transfer donor, including for foot drop reconstruction.
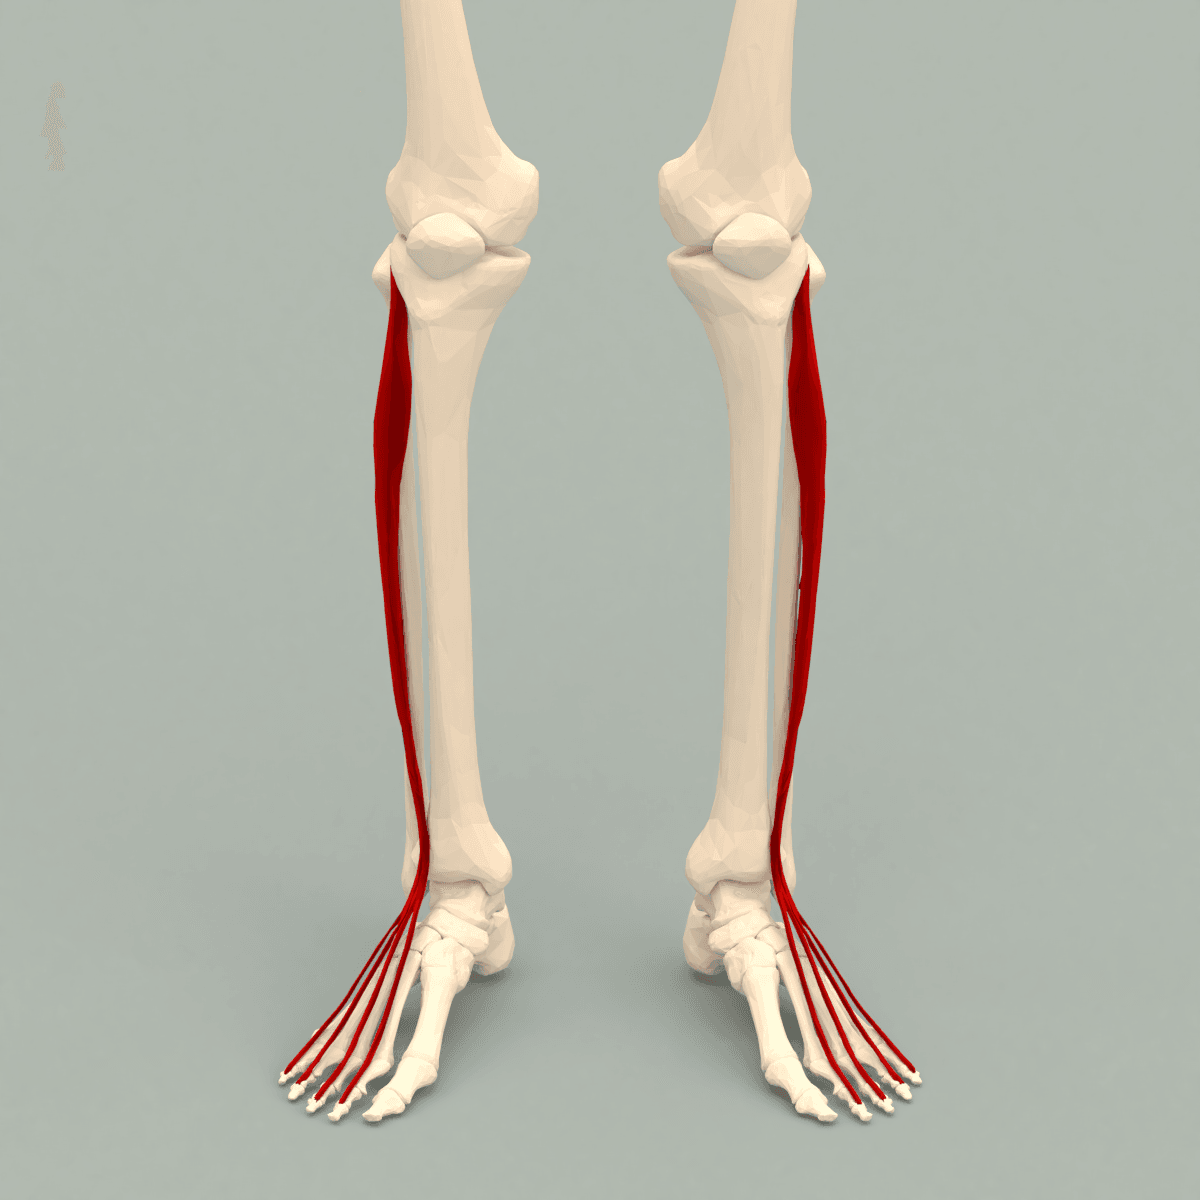
Position and Relations
In the compartment. EDL lies lateral to tibialis anterior and medial to peroneus tertius, when that muscle is present. Posteriorly the interosseous membrane separates it from the deep posterior compartment. The deep peroneal nerve descends between EDL and tibialis anterior, accompanying the anterior tibial artery.
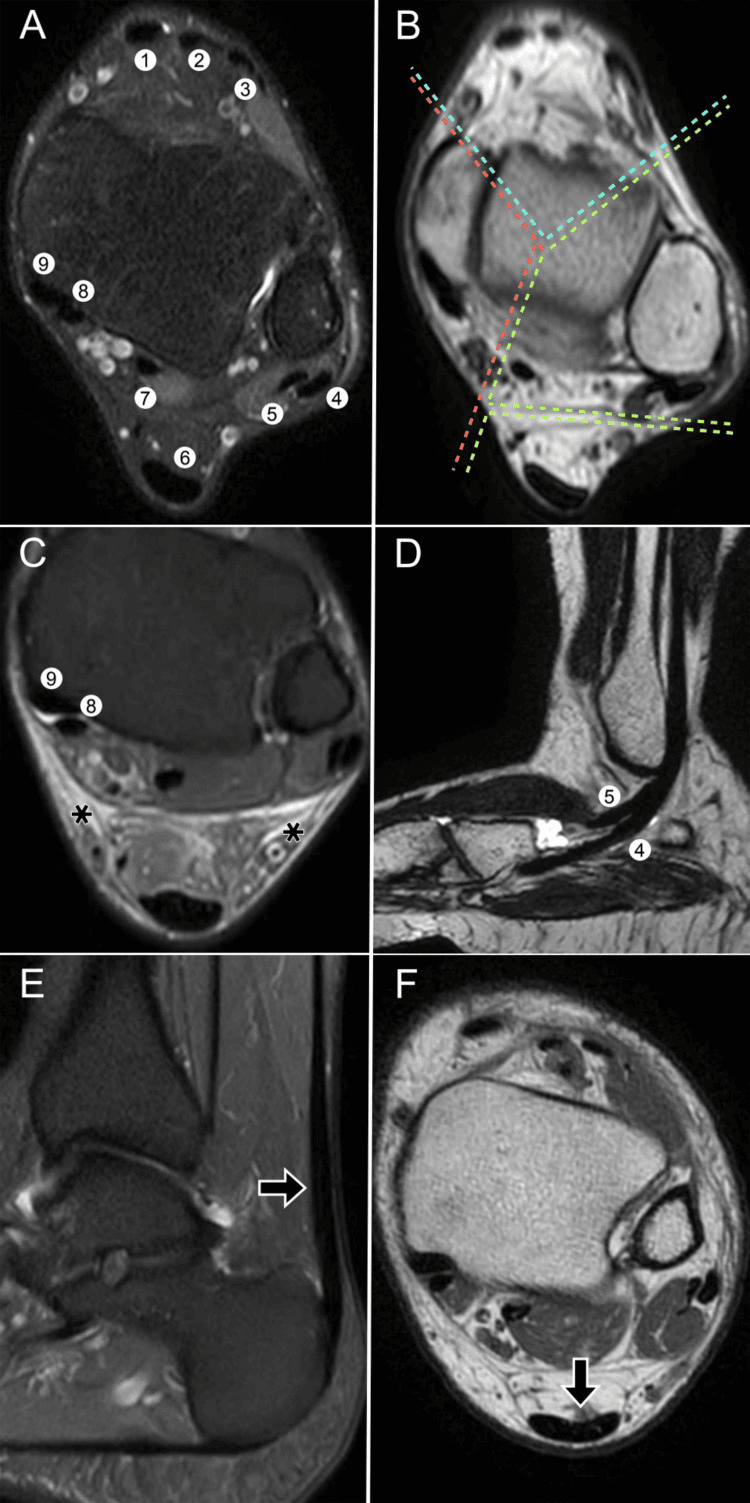
At the ankle. Tibialis anterior, EHL and EDL lie from medial to lateral, with the peroneals lateral and the flexors posterior. EDL is the most lateral of the three long extensors before it divides on the dorsum; only peroneus tertius, when present, lies lateral to it.
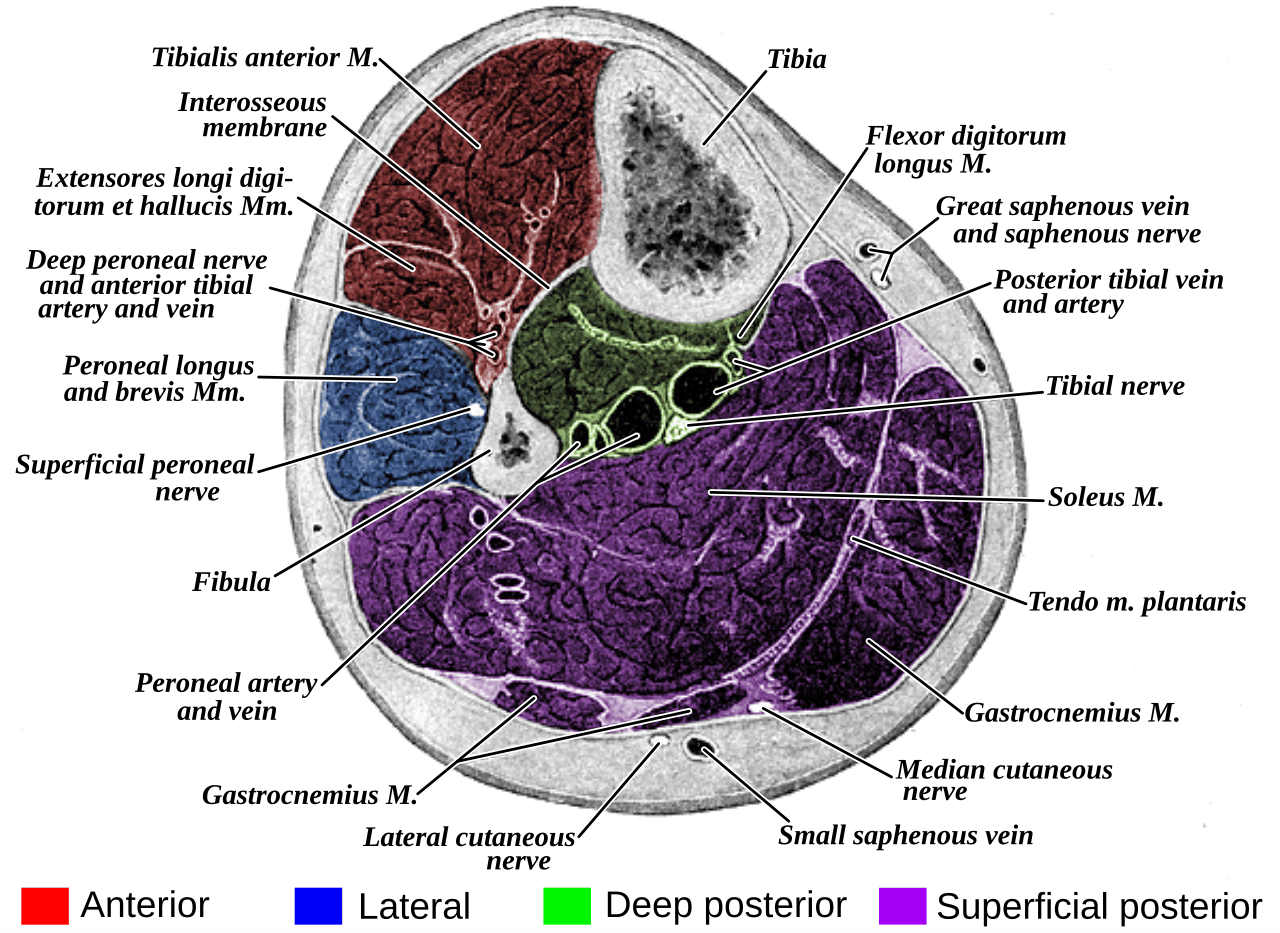
Origin and Architecture
A broad origin. EDL arises from several sites, which gives redundancy and distributes force during contraction. The fibula is the main origin in most individuals and typically the most substantial component.
- Tibia: the anterolateral surface of the lateral condyle and the upper three-quarters of the anterior tibial surface; the strongest attachment point medially
- Fibula: the anterior surface of the shaft (upper three-quarters) and its medial aspect
- Interosseous membrane: its anterior surface, a variable contribution of 20-40% of the origin
- Deep fascia: the anterior and lateral intermuscular septa, continuous with the crural fascia, which provide the compartmental boundaries
The fascia also anchors the muscle, holding it in position during contraction and preventing bowstringing during dorsiflexion. Those same fascial attachments are what a fasciotomy has to release.
Architecture. The fibres insert obliquely onto a central tendon. This pennate arrangement maximises force production while keeping enough excursion for the large range of motion required at the toe joints.
The pennation angle of EDL increases proximally to distally (8° to 15°), optimising force production at the origin and excursion distally where tendons split for individual toes. This graduated architecture is unique among anterior compartment muscles.

Tendons and the Extensor Expansion
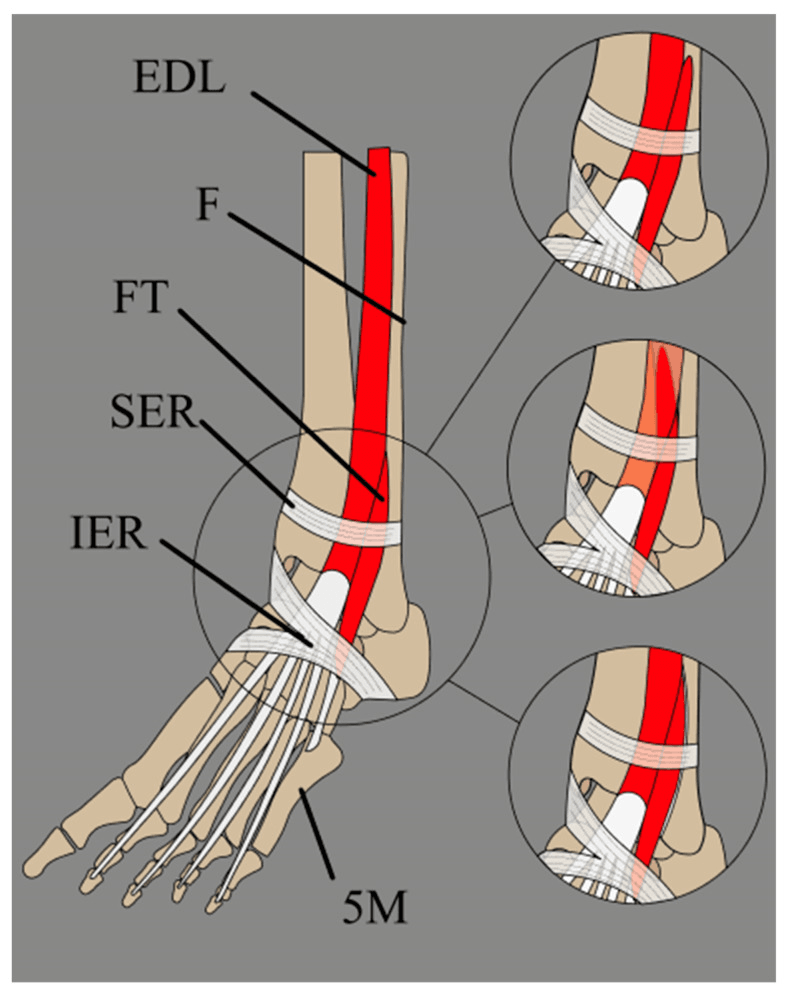
From muscle to tendon. The belly tapers distally and becomes tendon in the distal third of the leg, typically 8-12 cm proximal to the ankle joint. The single tendon then divides into four slips, at a level that varies:
- At the ankle - 60%, the most common
- In the distal leg (early division) - 25%
- On the dorsum of the foot (late division) - 15%
The tendons pass deep to the superior and inferior extensor retinacula, and under the inferior retinaculum each tendon passes through a separate compartment. They then diverge over the dorsum toward the second to fifth toes. On the dorsum they are subcutaneous, covered only by skin and superficial fascia, so they are easily palpable and visible during dorsiflexion and equally exposed to laceration, crush, contusion and inflammatory conditions.
Juncturae tendinum. Cross-connections between the EDL tendons on the dorsum are present in 85-90% of people and limit independent toe extension. They must be divided for independent toe testing, and they can mask an isolated EDL tendon laceration.
The extensor expansion. At the metatarsophalangeal joint each tendon broadens into a fibrous aponeurotic hood over the dorsum of the toe, which gives insertion to the intrinsic muscles and makes toe extension a complex mechanism.
- Central slip - the primary EDL insertion, onto the dorsal base of the middle phalanx; it extends the proximal and middle interphalangeal joints
- Lateral bands - two bands from the hood margins that receive the interossei and lumbricals, conjoin distal to the PIP joint and insert onto the base of the terminal phalanx
- Extensor digitorum brevis - its tendons join the lateral aspect of the EDL hood, a combined extensor mechanism for toes 2-4
- Interossei - pass dorsal to the deep transverse metatarsal ligament and insert onto the lateral aspects of the hood, giving triplanar control of toe position
The sling. Because the interossei insert proximal to the MTP axis, they flex the MTP joint dynamically while extending the interphalangeal joints through the lateral bands. The arrangement allows independent control of MTP and IP motion, which is critical for balanced toe function during gait.
Nerve Supply
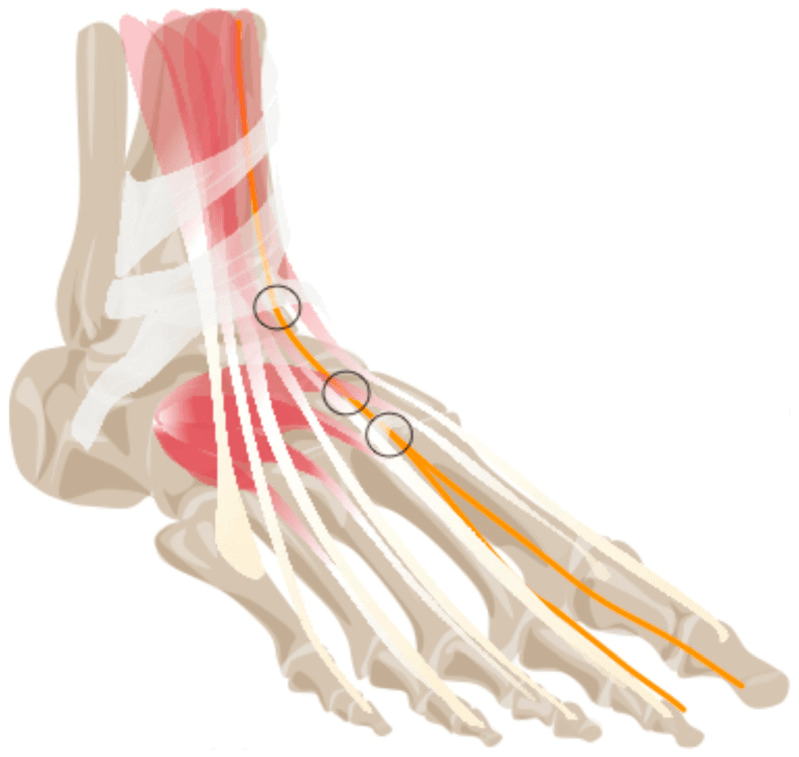
The nerve. EDL is supplied by the deep peroneal (deep fibular) nerve, typically from L5 and S1 with some contribution from L4. It is a terminal branch of the common peroneal nerve, which divides at the fibular neck, and it passes down through the anterior compartment giving sequential branches to EDL, EHL, tibialis anterior and peroneus tertius.
Entry into the muscle. The nerve enters EDL from its posterior aspect, with multiple motor branches in the proximal third and an average of 3-4 motor entry points per muscle.
On the dorsum. The nerve reaches the dorsum of the foot under the inferior extensor retinaculum, passes beneath extensor hallucis brevis and continues to the first web space. Each fascial crossing is a compression point in anterior tarsal tunnel syndrome.
Blood Supply
Arterial supply. Several sources overlap to make a redundant network. The anterior tibial artery is the main supply, through multiple perforating branches, on average 4-6 muscular branches, that enter the muscle from its medial aspect.
- Proximally, branches of the recurrent tibial artery supply the upper belly and anastomose with the inferior lateral genicular artery
- Distally, the continuation into the dorsalis pedis supplies the tendinous portion and is critical for tendon healing after injury
The artery runs between tibialis anterior medially and EDL laterally for most of its length, which makes it vulnerable during surgical approaches to the anterior compartment.
Venous drainage. Drainage parallels the arteries. Paired venae comitantes accompany the anterior tibial artery, receive multiple perforating veins from the muscle and empty into the popliteal vein proximally. Superficially, the dorsal venous arch and the great saphenous system are important for distal tendon viability.
Dissection planes. Vessels are sparse lateral to the EDL belly, and the plane between EDL and EHL is relatively avascular. Deep to the extensor retinaculum is a vascular plane that calls for caution.
Function and Gait
- Action
- Dorsiflexion (secondary)
- Range
- 15-20° contribution
- Power
- 30% of total dorsiflexion force
- Notes
- TA is primary dorsiflexor
- Action
- Eversion (tertiary)
- Range
- 5-8° contribution
- Power
- Minimal isolated action
- Notes
- Works with peroneus tertius
- Action
- Extension (primary)
- Range
- 60-80° at 2nd-5th MTPs
- Power
- Main extensor force
- Notes
- Essential for toe clearance
- Action
- Extension (shared)
- Range
- Variable by toe position
- Power
- Via extensor expansion
- Notes
- Requires intrinsic muscle cooperation
The EDL has a smaller moment arm for ankle dorsiflexion compared to tibialis anterior (4 cm vs 5 cm), making it less efficient for pure ankle dorsiflexion but more effective for toe extension due to its direct line of pull to the digits.
Swing. EDL prevents the toes dragging as the limb advances, working with tibialis anterior for foot clearance. It is most active at mid-swing (60-75% of swing) and holds the toes extended throughout.
Heel strike and loading. An eccentric contraction, with tibialis anterior, controls the descent of the foot, decelerates plantarflexion and prevents foot slap after heel contact. Activity falls rapidly after the loading response.
Stance. EDL is quiet in mid-stance, with some activation in terminal stance as it positions the toes for push-off.
Loss of function. Without EDL the toes drag in swing, seen as a steppage gait or frequent toe stubbing. The deficit is most noticeable when tibialis anterior is also weak, as in deep peroneal nerve palsy.
Development and Variations
Development. EDL comes from the dorsal muscle mass of the embryonic limb bud:
- Week 5 - the limb bud appears
- Week 6 - the dorsal muscle mass forms
- Week 7 - EDL differentiates from the common extensor mass
- Week 8 - the individual tendons form
- Week 12 - mature muscle architecture is established
EDL separates from EHL and peroneus tertius late in development, and that separation is subject to individual variation, which explains the common variations seen in practice. Absence of EDL itself is extremely rare (reported in less than 0.1%); congenital absence of a tendon is more common (0.5-1%). These developmental abnormalities are associated with fibular or tibial hemimelia and usually present as toe extension weakness noticed in childhood.
Variations. They matter when planning anterior compartment surgery or tendon transfers, when dissecting for a surgical approach, and when toe extension is weak without an obvious cause. Do not assume four separate tendons will be present at harvest. Fibularis tertius, which separates late from EDL, may insert on the fifth metatarsal, spread toward the fourth, or divide between them.
- Prevalence
- 30-40%
- Anatomy
- Tendon from EDL to hallux base (extensor hallucis brevis substitute)
- Clinical significance
- May compensate for weak EHL; consider in EHL repairs
- Prevalence
- 10-15%
- Anatomy
- Slip from EDL to the first metatarsal
- Clinical significance
- May compensate for weak EHL
- Prevalence
- 15-20%
- Anatomy
- No EDL tendon to little toe; the commonest absent slip
- Clinical significance
- Usually asymptomatic; EDB or peroneus tertius compensates
- Prevalence
- 25-30%
- Anatomy
- Tendon splits in distal leg
- Clinical significance
- Affects retinacular passage; consider in ankle surgery
- Prevalence
- 15-20%
- Anatomy
- Origin extends to knee joint capsule
- Clinical significance
- May affect anterior compartment volume
- Prevalence
- 10-15%
- Anatomy
- Shared origin or muscle belly
- Clinical significance
- Consider during compartment release or transfers
- Prevalence
- 5-8%
- Anatomy
- Compensatory increase in tibial attachment
- Clinical significance
- Usually clinically insignificant
- Prevalence
- 5-8%
- Anatomy
- Additional muscle belly in compartment
- Clinical significance
- May increase compartment syndrome risk
- Prevalence
- Rare (less than 3%)
- Anatomy
- Shared muscle belly proximally
- Clinical significance
- May complicate tendon transfers
The most clinically significant variation is the accessory slip to the hallux, present in one-third of individuals. This can mask EHL weakness and must be tested by asking the patient to extend only the great toe while the examiner blocks EDL action by plantarflexing the lateral four toes.
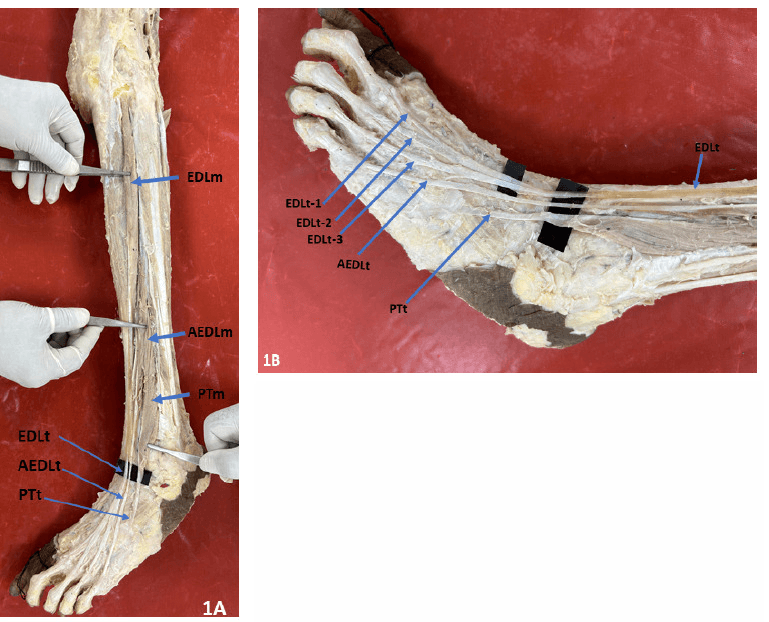
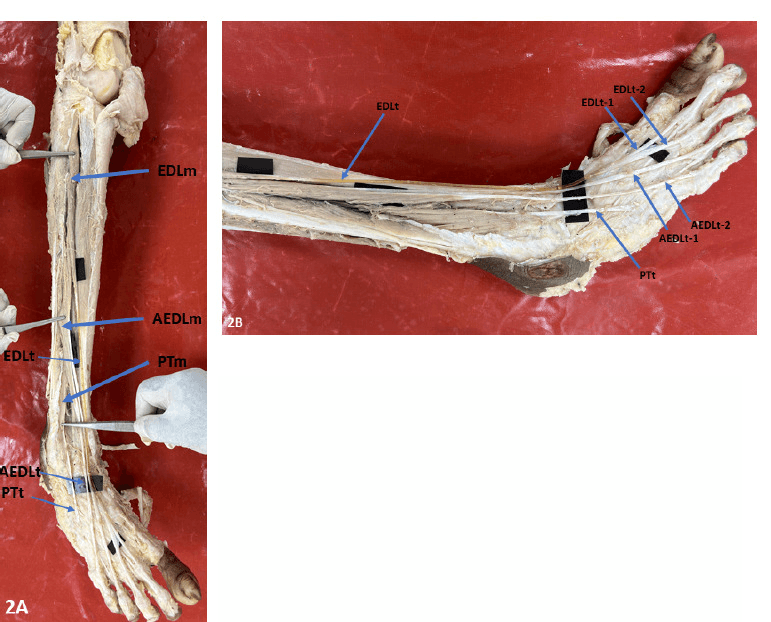
Posnik et al. (2025) - Anterior compartment morphological variability review
- Comprehensive PubMed-based review of anterior leg compartment muscle morphology
- Well-documented variants of tibialis anterior, EHL and EDL exist alongside the highly variable fibularis tertius
- Knowledge of these variants is critical for tendon-graft harvest and pre-operative imaging interpretation
Olson et al. (2025) - Bilateral EDL and fibularis tertius variation
- Cadaveric finding of EDL missing its 5th-digit tendon bilaterally
- An enlarged fibularis tertius split into three slips, the most medial replacing the absent EDL tendon to the 5th toe
- Documents how peroneus/fibularis tertius and EDB can substitute for an absent EDL slip
Tendon Pathology
Tendonitis and tenosynovitis. EDL tendonitis is less common than tibialis anterior or peroneal tendonitis, but it does occur. The causes are overuse (running, hiking), compression from tight shoe laces, inflammatory arthropathy (rheumatoid arthritis, the seronegative spondyloarthropathies) and direct contusion. The patient has pain over the anterior ankle and dorsum of the foot, swelling along the tendon, pain on resisted toe extension and on passive toe plantarflexion, and occasionally crepitus. Diagnosis rests on tenderness along the tendon, with the ultrasound and MRI findings described under Investigations.
Treatment of tendonitis. The prognosis is generally excellent, and most patients respond to activity modification and anti-inflammatory measures within 6-8 weeks, the length of the conservative trial.
- Rest, NSAIDs, activity modification and changes to shoe lacing
- Immobilisation for 2-3 weeks in severe cases
- Physiotherapy: eccentric exercises and stretching
- Corticosteroid injection, used with caution near tendons
- Surgical debridement for chronic cases, rarely
Rupture and laceration. Rupture is uncommon. Laceration is the most common mechanism (lawn mower, glass); spontaneous rupture is rare and associated with quinolone use or inflammatory disease; avulsion follows forceful plantarflexion against resisted dorsiflexion. Active toe extension is lost, with a palpable gap in acute lacerations, while ankle dorsiflexion is preserved because tibialis anterior is intact. Passive toe extension may remain through the juncturae and EDB.
Making the diagnosis. The patient cannot actively extend individual toes once the adjacent toes are blocked to remove the juncturae contribution. Ultrasound or MRI confirms the rupture and localises it.
Treatment of rupture. An isolated single slip is often observed, because the other slips compensate; for multiple slips surgical repair is recommended.
- Acute laceration - primary repair within 2 weeks, direct end-to-end
- Gap greater than 2 cm - tendon graft
- Augmentation - with an adjacent EDL slip or EDB
- Fixation - Pulvertaft weave for a secure tendon-to-tendon repair; setting the tension too tight is the pitfall
- Chronic rupture - tendon transfer or reconstruction
After repair. The foot is splinted for 4-6 weeks, with gradual range of motion from 6 weeks and strengthening at 8-12 weeks. Primary repair gives good outcomes in 90%+, with technique and timing determining the result, and most patients regain useful toe extension for gait; the juncturae compensate for what is lost.
Entrapment and impingement. EDL tendons can be caught at specific sites, which usually present as chronic pain and functional limitation. Imaging is essential for the diagnosis, and refractory cases may need surgery.
- Anterior ankle impingement - hypertrophic anterior tibiotalar osteophytes compress the tendons at the ankle joint and cause pain with dorsiflexion; treated by arthroscopic or open debridement
- Retinacular entrapment - thickening or scarring of the inferior extensor retinaculum after trauma restricts excursion and may need retinacular release
- Post-traumatic - heterotopic ossification after ankle fracture, malunited distal tibial or fibular fractures, or scarring from previous surgery; complex reconstruction may be needed
- Inflammatory - rheumatoid synovial proliferation, the seronegative spondyloarthropathies and tophaceous gout; treated with disease-modifying therapy plus local measures
Anterior Compartment Syndrome
Why EDL. EDL is the largest muscle in the anterior compartment after tibialis anterior. Its central position and large volume make it the first muscle to show necrosis when anterior compartment syndrome goes untreated.
The sequence. Muscle swelling raises the intracompartmental pressure. Venous outflow is obstructed first (30 mmHg): the venae comitantes are compressed and interstitial pressure climbs further. Arterial inflow is compromised only at higher pressures (40-50 mmHg), and irreversible muscle damage begins at 6-8 hours.
The signs. Pain out of proportion is the hallmark. Pain on passive toe plantarflexion, which stretches EDL, is the other early sign, and the anterior compartment is tense and swollen. Weakness of toe extension is a late finding.
Never rely solely on pulses or capillary refill to rule out compartment syndrome. The anterior tibial artery may remain patent even with established muscle ischaemia. Pain with passive stretch is the most reliable early clinical sign.
The diagnosis is primarily clinical. Compartment pressure monitoring is for the uncertain case, with continuous monitoring for patients at risk. A delta P (diastolic blood pressure minus compartment pressure) of less than 30 mmHg is an indication for fasciotomy. When the diagnosis is clear, do not delay for investigations or pressures: fasciotomy is immediate and releases all four compartments.
Fasciotomy. The fascial attachments of EDL must be completely released so the muscle can herniate and the pressure fall; incomplete fascial release is a common cause of recurrence.
- Two incisions (preferred) - an anterior incision for the anterior compartment and a lateral one for the lateral compartment, giving better visualisation
- Single incision - a lateral incision from the fibular head to the lateral malleolus, identifying the intermuscular septum and releasing the lateral and anterior compartments
Releasing the anterior compartment. Work in this order:
- Make a longitudinal incision over the anterior compartment, medial to the fibula
- Incise skin and subcutaneous tissue
- Identify the deep fascia (white, glistening)
- Make a 2-cm transverse opening in the fascia
- Insert scissors under the fascia
- Cut the fascia along its entire length, from the fibular head to the malleoli
- Confirm that the muscle bulges through the fasciotomy; EDL should visibly herniate if decompression is adequate
- Check all four compartments
Common errors are a fascial incision that is too short, failure to release the intermuscular septa, missing the deep posterior compartment, and a skin incision too small, which causes skin necrosis.
During anterior compartment fasciotomy, the deep peroneal nerve lies on the interosseous membrane deep to EDL. Blind dissection or aggressive retraction can cause nerve injury. Always visualise the nerve before releasing the interosseous membrane if indicated.
Vascular injury. The anterior tibial artery can be injured during compartment release, usually at the proximal or distal extent of the fasciotomy. It can be ligated if distal perfusion is adequate, with the dorsalis pedis present.
After fasciotomy. The wound is never closed primarily. It is managed with negative pressure (VAC) or dressings, closed after a delay of 48-72 hours or skin grafted if needed, and watched for wound complications; range of motion starts early once it is closed. Wound healing is usually complete.
Complications and outcome. Timing decides the result: early fasciotomy gives excellent results and delayed fasciotomy poor ones, with good muscle recovery if it is done within 6 hours and irreversible damage beyond 8 hours. A missed or delayed release leaves permanent muscle loss with Volkmann contracture and a permanent foot drop, and possibly the need for a tendon transfer.
- Prevention
- Early fasciotomy
- Management
- Debridement
- Prevention
- Careful dissection
- Management
- Observation/repair
- Prevention
- Full-length incision
- Management
- Revision fasciotomy
Surgical Approaches and Tendon Transfer
Anterolateral approach to the tibia. EDL is a key landmark. The longitudinal incision runs over the anterior tibia, centred between the tibial crest and the fibula, and can extend the full length of the tibia. The plane between tibialis anterior and EDL is developed; it is often called internervous, although both muscles are supplied by the deep peroneal nerve. Function is preserved because no muscle is divided, and the exposure is excellent.
- Incise the deep fascia longitudinally
- Retract tibialis anterior medially and EDL laterally
- Expose the anterior tibial surface, elevating periosteum as needed
- Protect the anterior tibial vessels, which lie deep to the muscles
- Preserve the deep peroneal nerve, which runs with the vessels
The key is protecting the neurovascular bundle medial to EDL. To reach the lateral malleolus or distal fibula, retract EDL medially to protect the anterior tibial artery.
The approach is used for:
- Tibial shaft fracture ORIF (plates)
- Tibial osteotomy
- Anterior ankle arthrodesis
- Access to the distal tibia (pilon fractures)
Tendon transfer. EDL tendons are commonly used for transfer, for posterior tibial tendon dysfunction (PTTD) reconstruction, drop foot correction (anterior transfer to the os calcis) and correction of toe deformity. The slip to the fifth toe is harvested because it is the least functional, and taking the wrong slip brings morbidity. It is routed through the interosseous membrane and attached to the navicular or the tibialis posterior tendon, augmenting inversion and plantar flexion.
Technique. The four slips give abundant graft length, but the anterior tibial vessels and deep peroneal nerve lie deep: stay on the tendon and identify every slip before division. Preserve enough length for tensioning, because the tension is critical. Keep the proximal vascular pedicle and the paratenon, since the distal tendon draws its supply from the paratenon. Allow 6-8 weeks of immobilisation and healing before loading, and physiotherapy for motor re-education is essential.
Results and choice of donor. Results are good in properly selected patients. Donor-site morbidity is minimal, the loss of fifth-toe extension, and the juncturae compensate. The case for EDL over FDL is a similar vector and adequate strength without a plantar incision, at the price of tunnelling through the interosseous membrane. FDL is nonetheless the standard transfer for flexible PTTD, and the contribution of EDL slips as donors is modest and not supported by high-level comparative evidence (see Controversies below).
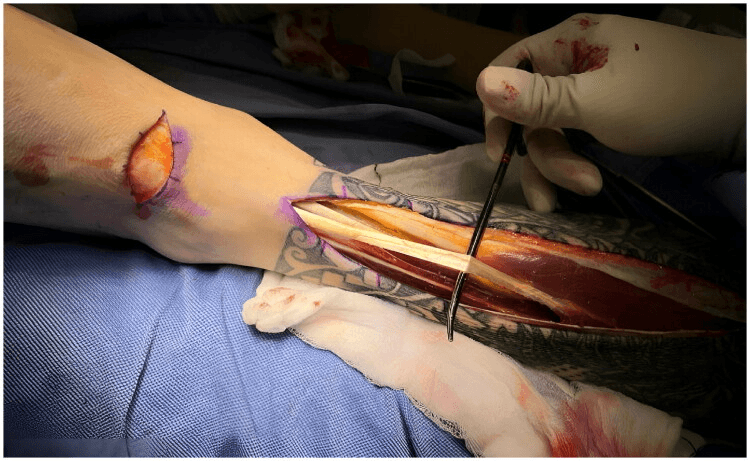
Reis et al. (2011) - Posterior tibial tendon transfer for foot drop
- 13 patients with foot drop from nerve palsy IN LEPROSY underwent posterior tibial tendon transfer (circumtibial route)
- Stanmore functional score: good or excellent in 10 of 13 feet (77%), moderate in 2, poor in 1
- Restored functional dorsiflexion and gait without altering resting foot posture; all patients satisfied
Clinical Assessment
Surface anatomy. The muscle belly is palpable in the proximal and middle leg, lateral to the tibial crest. The tendons stand out on the dorsum with active toe extension, most prominently against resistance and in thin individuals. Palpate systematically, comparing with the other side for subtle findings:
- Seat the patient with the knee flexed 90°
- Palpate the belly in the lateral half of the anterior compartment
- Follow the tendon distally to the ankle
- Palpate the four tendons over the metatarsals
- Feel for continuity, tenderness and masses
Abnormal findings and what they suggest:
- Swelling - tendonitis, compartment syndrome
- Tenderness - inflammatory conditions, overuse
- A gap - tendon rupture
- A mass - ganglion, tumour
- Bowstringing - retinacular insufficiency
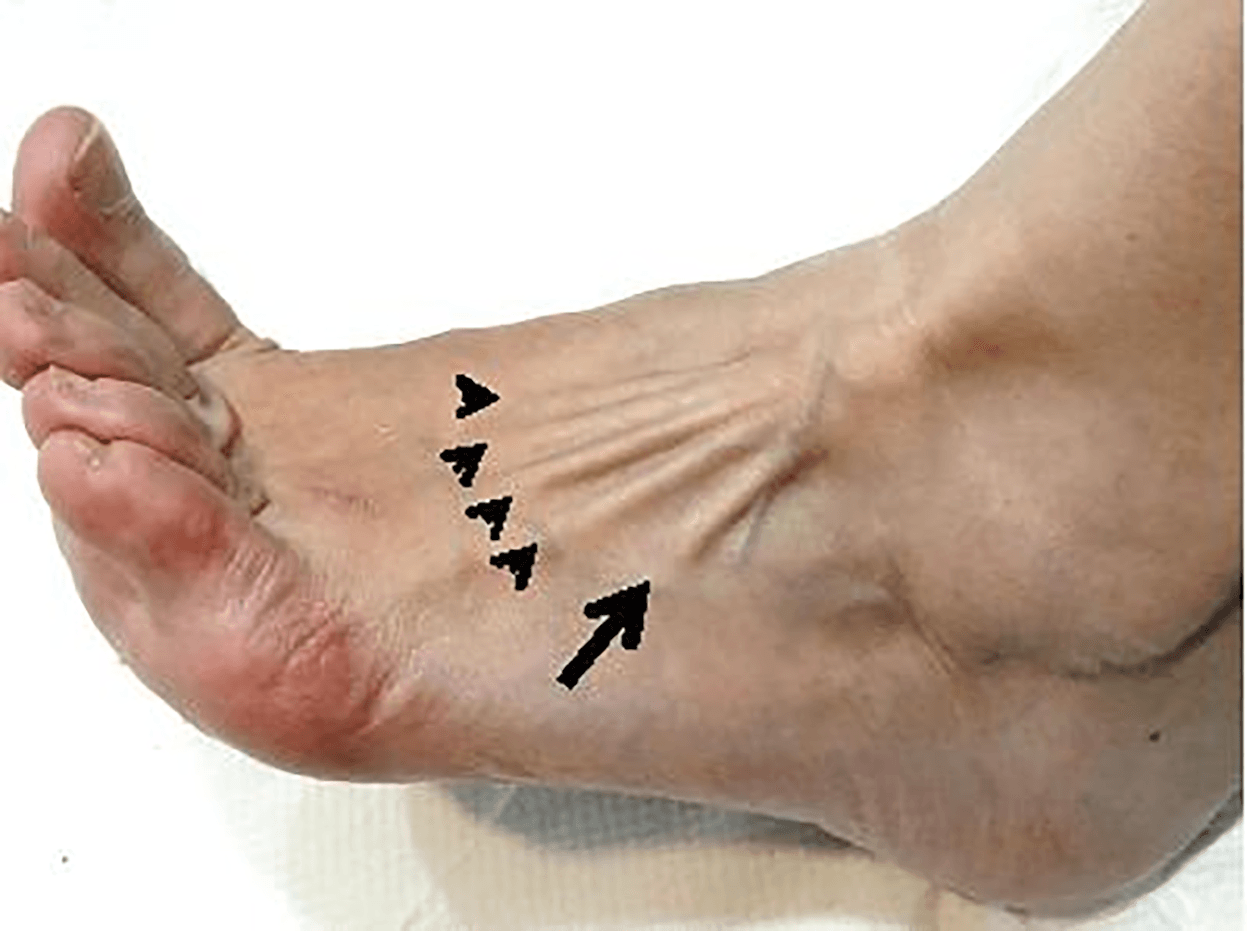
Testing toe extension. Start with the patient seated and the foot relaxed, ask for extension of all the toes, and observe range and strength. Isolated testing then has to remove the compensating structures:
- Block ankle dorsiflexion with a hand on the dorsum of the foot
- Plantarflex the adjacent toes to block the juncturae
- Ask the patient to extend the individual toe
- Test each toe separately
- Compare with the other side
Strength is graded on the MRC scale:
- 0 - no visible contraction
- 1 - flicker of movement only
- 2 - movement with gravity eliminated
- 3 - movement against gravity
- 4 - movement against some resistance
- 5 - normal strength
Errors in testing. Failing to block the juncturae gives a false negative for a laceration. Failing to stabilise the ankle lets tibialis anterior contribute to apparent toe extension, and testing with the knee extended changes the muscle's length-tension relationship.
How much loss matters. Isolated loss of EDL causes minimal disability in most patients, because extensor digitorum brevis and the juncturae compensate. Subtle deficits still affect athletic performance.
Functional assessment. Functional tests give more clinically relevant information than isolated manual muscle testing and help guide rehabilitation.
- Gait - toe clearance in swing, toe drag or a steppage gait, asymmetry between sides, and scuffing on the footwear from toe drag
- Single-limb stance - EDL contributes to ankle stability, so weakness makes the position hard to hold, although compensatory hip and knee strategies may mask it
- Heel walk - needs maximum dorsiflexion with EDL and tibialis anterior both active; inability suggests significant weakness
- Toe tapping - rapid extension-flexion cycles test endurance and coordination; fatigue suggests neuromuscular pathology, and the test is useful for monitoring recovery
Special tests. No single test is definitive for EDL pathology, and each is read with the imaging and the rest of the examination.
- Passive stretch - maximal passive plantarflexion of the ankle and toes; pain suggests EDL tendonitis or compartment syndrome, and it is the most sensitive early sign of compartment syndrome
- Resisted extension - resist toe extension while palpating EDL. Pain at the musculotendinous junction suggests strain or tendonitis, pain over the tendon tendonitis or a partial tear; weakness with pain is pathological, weakness without pain neurological
- Tenodesis - passive ankle plantarflexion should extend the toes; loss suggests tendon discontinuity, but the test is not reliable with intact juncturae
- Differential block - a local anaesthetic block of the deep peroneal nerve eliminates EDL function, separating it from the contribution of EDB or the juncturae; useful before planning a tendon transfer
Deep peroneal nerve palsy. A complete palsy produces:
- Loss of ankle dorsiflexion (tibialis anterior)
- Loss of great toe extension (EHL)
- Loss of lesser toe extension (EDL)
- Sensory loss in the first web space
- A foot drop gait pattern
A partial palsy may involve muscles selectively, depending on the level and nature of the injury, and EDL is often affected together with tibialis anterior. Recovery is variable and depends on the mechanism (traction, laceration, compression) and the severity (neurapraxia, axonotmesis, neurotmesis). EDL recovery typically parallels that of tibialis anterior, because they share their innervation.
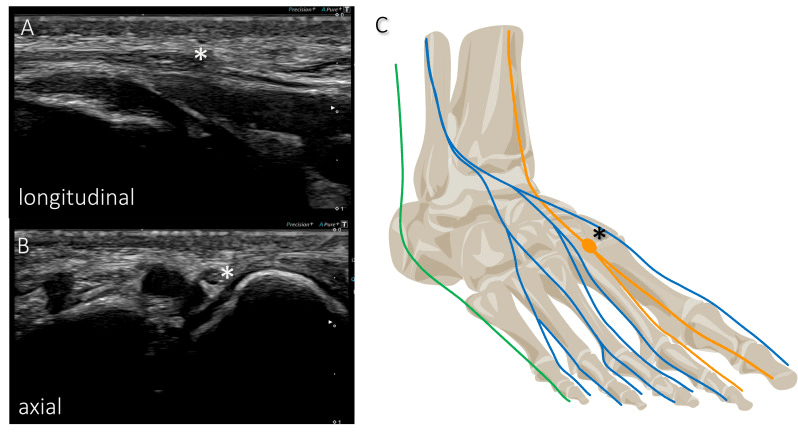
Investigations. The modality follows the question:
- Ultrasound - tendon continuity and tendonitis (thickening, hypoechoic areas, fluid in the sheath); dynamic and cheap
- MRI - the detailed study for complex pathology: complete and partial tears, muscle oedema from denervation and associated pathology, with increased T2 signal and peritendinous oedema in tendonitis
- EMG and nerve conduction - for nerve injury. EMG shows denervation (fibrillations, positive sharp waves) and reduced recruitment on volitional testing; nerve conduction studies confirm the level. Both are useful for prognosis and surgical planning
Differential Diagnosis
Toe-extension weakness or anterior leg/foot pain involving EDL must be separated from neighbouring causes. The key discriminators are the pattern of motor loss, sensory signature, and provocative findings.
- distinguishing
- Pain out of proportion; severe pain on passive toe plantarflexion; tense compartment
- motor
- Progressive loss of toe and ankle dorsiflexion (late)
- keyTest
- Delta P less than 30 mmHg; clinical diagnosis - do not wait
- distinguishing
- Foot drop plus weak eversion; sensory loss over dorsum and lateral leg
- motor
- EDL, TA, EHL AND peroneals weak
- keyTest
- Eversion weak; sensory loss wider than first web space
- distinguishing
- Foot drop with PRESERVED eversion; sensory loss first web space only
- motor
- EDL, TA, EHL weak; peroneals spared
- keyTest
- Eversion intact; first web-space anaesthesia
- distinguishing
- Back/buttock pain; weakness extends to hip abduction; dermatomal sensory loss
- motor
- EHL and EDL weak; also gluteus medius
- keyTest
- Positive straight-leg raise; weak hip abduction; reflexes preserved
- distinguishing
- Discrete trauma; localised gap; normal sensation and ankle dorsiflexion
- motor
- Loss of isolated toe extension only
- keyTest
- Block adjacent toes (eliminate juncturae) before concluding intact
- distinguishing
- Activity-related dorsal pain; swelling along tendon; no neuro deficit
- motor
- Pain-limited rather than true weakness
- keyTest
- Pain on resisted extension; ultrasound shows sheath fluid
Peroneus (Fibularis) Tertius
The peroneus (fibularis) tertius runs through this whole topic - it is the muscle noted "when present," the structure that compensates for an absent EDL slip to the 5th toe, and the subject of two of the EvidenceCards (Posnik, Olson) - yet it is never actually defined.
- What it is. Peroneus tertius is effectively a partially separated distal, lateral part of the EDL: it arises from the lower third of the anterior fibula and the interosseous membrane, shares the EDL belly, and its tendon runs with the EDL tendons under the extensor retinaculum to insert on the dorsal base of the fifth metatarsal (rather than onto a toe).
- Innervation and action. Like EDL it is supplied by the deep peroneal nerve (L5, S1); it is a weak dorsiflexor and evertor of the foot. Because it inserts on the fifth metatarsal and not a phalanx, it does not extend the toes.
- Variability. It is highly variable and effectively unique to humans (well developed in relation to bipedal gait) - present in roughly 80-95% of limbs and absent in the remainder, with frequent accessory slips. Its absence is asymptomatic, and (as the Olson cadaveric case shows) an enlarged tertius can send a slip to the fifth toe to replace a missing EDL tendon.
- Why it matters here. It explains the topic's repeated point that an absent EDL slip to the 5th toe is usually silent (tertius and EDB compensate), it is a recognised tendon-graft donor (why the variation literature matters to surgeons), and it lies in the same anterior-compartment plane and neurovascular territory as EDL.
Q: What is peroneus (fibularis) tertius and how does it relate to EDL? A: It is a partially separated distal-lateral slip of EDL arising from the lower anterior fibula and interosseous membrane, running with the EDL tendons under the extensor retinaculum to insert on the dorsal base of the fifth metatarsal. It shares the deep peroneal nerve (L5, S1) and acts as a weak dorsiflexor/evertor but does not extend the toes. It is variable (present in about 80-95%, effectively unique to humans), its absence is asymptomatic, and it can compensate for an absent EDL slip to the fifth toe.
The Extensor Retinacula and Anterior Tarsal Tunnel
- The superior extensor retinaculum is a simple transverse thickening of the deep fascia just above the ankle that binds down the anterior-compartment tendons (tibialis anterior, EHL, EDL and peroneus tertius) and the deep peroneal neurovascular bundle.
- The inferior extensor retinaculum is the important one: it is a Y-shaped band over the front of the ankle with a stem attached laterally to the calcaneus dividing into an upper and lower limb that sweep medially. It forms separate loops/compartments for the tendons - EDL and peroneus tertius share the most lateral loop - which is why an EDL tendon has its "own compartment" and why retinacular scarring restricts tendon excursion.
- The anterior tarsal tunnel is the space deep to the inferior extensor retinaculum through which the deep peroneal nerve (the EDL's nerve) and the dorsalis pedis vessels pass. Compression here - by the retinaculum, dorsal osteophytes, a ganglion, tight footwear or trauma - causes anterior tarsal tunnel syndrome: dorsal foot pain and first web-space sensory loss, with wasting of extensor digitorum brevis if the motor branch is involved. This is distinct from the posterior (medial) tarsal tunnel, which transmits the tibial nerve.
- Why it matters here. These retinacula are what hold the EDL tendons down (preventing bowstringing) during dorsiflexion, the site of the "retinacular entrapment" the topic mentions, and - via the anterior tarsal tunnel - a cause of deep-peroneal symptoms that can mimic the more proximal lesions in the differential.
Q: Describe the extensor retinacula and the anterior tarsal tunnel. A: The superior extensor retinaculum is a transverse fascial band just above the ankle binding the anterior-compartment tendons; the inferior extensor retinaculum is a Y-shaped band with a lateral calcaneal stem that forms separate loops for the tendons (EDL and peroneus tertius share the lateral loop). The space deep to the inferior retinaculum transmitting the deep peroneal nerve and dorsalis pedis is the anterior tarsal tunnel; compression there (retinaculum, osteophytes, ganglion, tight boots) causes anterior tarsal tunnel syndrome - dorsal foot pain and first web-space sensory loss, with possible extensor digitorum brevis wasting - distinct from the posterior (tibial nerve) tarsal tunnel.
Guidelines, Registries & Global Practice
Global Epidemiology
- Acute compartment syndrome complicates approximately 1-10% of tibial diaphyseal fractures, the commonest setting in which the EDL-containing anterior compartment is decompressed; young men are disproportionately affected.
- In the largest monitored series, 17.9% of monitored tibial diaphyseal fractures underwent fasciotomy for acute compartment syndrome (McQueen, JBJS Am 2013).
- Isolated EDL pathology (tendonitis, single-slip laceration) is uncommon and largely reported as small series and cadaveric studies; anatomical variants (accessory hallux slip ~30-40%, absent 5th-toe slip ~15-20%, juncturae tendinum ~85-90%) are consistently described across populations.
Side-by-Side Guidance
- focus
- Diagnosis and management of compartment syndrome of the limbs
- position
- Clinical diagnosis is paramount; low threshold for fasciotomy; document serial assessment; decompress urgently
- evidence
- Consensus standard of care
- focus
- Fasciotomy technique for the leg
- position
- Full-length two-incision four-compartment release; ensure muscle herniation; never close primarily
- evidence
- Expert / technique consensus
- focus
- Pressure monitoring threshold
- position
- Delta P less than 30 mmHg indicates decompression; continuous monitoring high accuracy in unreliable examination
- evidence
- Prospective + large cohort
- focus
- Acute compartment syndrome
- position
- Pain out of proportion and pain on passive stretch are key early signs; pulses unreliable
- evidence
- Consensus / review
Registry & Resource-Setting Notes
- There is no implant registry for soft-tissue EDL surgery; relevant outcome data derive from trauma databases (e.g. the Edinburgh prospective trauma database underpinning the compartment-pressure work) and small case series.
- High-resource settings can offer continuous compartment monitoring, negative-pressure wound therapy for staged fasciotomy closure, and subspecialist foot-and-ankle reconstruction (tendon transfer, deformity correction).
- Limited-resource settings rely on repeated clinical examination and prompt fasciotomy; transfer time to a facility capable of decompression is a critical determinant of outcome, mirroring the rural/remote challenge worldwide. Tendon transfer remains the principal salvage for irrecoverable drop foot where nerve repair or grafting is unavailable.
Controversies & Areas of Uncertainty
- Absolute vs differential compartment pressure. Although the delta P less than 30 mmHg threshold (McQueen, JBJS Br 1996) is the most widely adopted rule, some units still use absolute thresholds of 30-45 mmHg. Over-reliance on any single number risks both unnecessary fasciotomy and missed cases; serial clinical assessment remains primary.
- Role of continuous monitoring. High accuracy in obtunded or block-anaesthetised patients is established, but continuous monitoring is not universally available and is not a substitute for repeated examination in the alert patient.
- Choice of donor for dorsiflexion / PTTD reconstruction. Tibialis posterior transfer is the established workhorse for irrecoverable drop foot; flexor digitorum longus transfer is the standard for flexible PTTD flatfoot but is biomechanically inferior to lateral column lengthening for deformity correction (Zanolli, JBJS Am 2014). The contribution of EDL slips as donors is modest and not supported by high-level comparative evidence.
- Threshold for repairing isolated EDL slip lacerations. Because juncturae tendinum, EDB and an enlarged fibularis tertius frequently compensate, many isolated single-slip injuries are managed non-operatively; the level at which repair changes outcome is not defined by controlled data.
- Naming conventions. "Peroneal" and "fibular" nerve/muscle terminology coexist internationally (Terminologia Anatomica favours "fibular"); candidates should be fluent in both for global exams.
MCQ Practice Points
Q: What is the innervation of extensor digitorum longus?
A: Deep peroneal nerve (L4, L5, S1). This nerve also supplies tibialis anterior, extensor hallucis longus, extensor digitorum brevis, and peroneus tertius. Deep peroneal nerve injury causes foot drop with loss of ankle and toe dorsiflexion. Sensory loss limited to first web space.
Q: In which compartment of the leg does extensor digitorum longus reside?
A: Anterior compartment of the leg, along with tibialis anterior, extensor hallucis longus, and peroneus tertius. The anterior compartment is most susceptible to compartment syndrome due to its tight fascial boundaries. Deep peroneal nerve and anterior tibial artery run within this compartment.
Q: What is the insertion pattern of extensor digitorum longus?
A: EDL splits into four tendons inserting into lateral four toes via the extensor expansion (dorsal hood). Each tendon trifurcates: central slip to middle phalanx base, two lateral slips to distal phalanx base. This mechanism similar to hand extensors; damage causes mallet toe or claw toe deformities.
Q: What muscles contribute to the extensor expansion of the toes?
A: Extensor digitorum longus (extrinsic), extensor digitorum brevis (intrinsic), lumbricals, and interossei. The lumbricals and interossei flex the MTP joint while extending IP joints. Loss of intrinsic function creates claw toe deformity with MTP hyperextension and IP flexion.
Q: What is the blood supply to extensor digitorum longus?
A: Primarily from anterior tibial artery branches. The muscle receives segmental perforators throughout its length. Understanding vascular anatomy important for free flap harvest (rarely used) and fasciotomy planning in compartment syndrome. Anterior tibial artery runs between EDL and tibialis anterior.
Summary
The extensor digitorum longus is a critical muscle of the anterior compartment with essential roles in toe extension and gait mechanics. Understanding its detailed anatomy - including origin from the lateral tibial condyle and anterior fibula, insertion via the extensor expansion, and neurovascular supply from the deep peroneal nerve and anterior tibial artery - is fundamental for orthopaedic practice.
Key clinical applications include recognition and treatment of anterior compartment syndrome, where EDL is the largest muscle volume and pain with passive toe plantarflexion is the most sensitive test. Surgical anatomy is essential for the anterolateral approach to the tibia, fasciotomy technique, and tendon transfer procedures for posterior tibial tendon dysfunction.
Common variations such as accessory slips to the hallux and juncturae tendinae affect clinical examination and must be considered when testing isolated EDL function. The muscle's relatively minor individual contribution to function means that isolated EDL loss is well-compensated, but its role in compartment syndrome and as a donor for tendon transfers makes it clinically significant.
For exam preparation, focus on the anatomical relationships in the anterior compartment, clinical diagnosis of compartment syndrome, fasciotomy technique, and tendon transfer applications. Understanding the biomechanics and functional anatomy allows for comprehensive management of pathology affecting this important structure.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 23-year-old male presents 4 hours after a tibial shaft fracture with severe anterior leg pain. Walk me through your assessment of the extensor digitorum longus and the anterior compartment.”
“You are planning an EDL tendon transfer to augment tibialis posterior function in a 55-year-old woman with stage 2 posterior tibial tendon dysfunction. Describe the surgical anatomy and technique.”
“A 40-year-old presents with a new foot drop after prolonged squatting. How do you use the extensor digitorum longus and its innervation to localise the lesion?”
Origin & Insertion
- Origin: Lateral tibial condyle, anterior fibula (upper 3/4), interosseous membrane, intermuscular septa
- Insertion: 4 tendons to middle/distal phalanges of toes 2-5 via extensor expansion
- Central slip to middle phalanx, lateral bands to distal phalanx
- Extensor hood receives intrinsic muscle insertions (complex mechanism)
Neurovascular Supply
- Nerve: Deep peroneal nerve (L5, S1) - 3-4 motor entry points in proximal third
- Artery: Anterior tibial artery (4-6 muscular branches) - main supply
- Additional: Recurrent tibial artery (proximal), dorsalis pedis (distal tendons)
- Veins: Venae comitantes of anterior tibial artery (compressed first in compartment syndrome)
Actions & Function
- Primary: Toe extension at MTP joints (toes 2-5)
- Secondary: Ankle dorsiflexion (contributes 30% of total dorsiflexion force)
- Tertiary: Foot eversion (minimal contribution with peroneus tertius)
- Gait: Essential for toe clearance in swing phase, prevents toe drag
Clinical Relations
- Anterior compartment syndrome: Pain with passive toe plantarflexion (most sensitive test)
- Compartment borders: Lateral to TA, medial to peroneus tertius, superficial to interosseous membrane
- Surgical plane: Between TA and EDL is internervous plane for anterolateral approach to tibia
- Fasciotomy: Must ensure muscle herniation through fascial release for adequate decompression
Key Variations (High-Yield)
- Accessory slip to hallux: 30-40% (may mask EHL weakness - block to isolate)
- Absent slip to 5th toe: 15-20% (usually asymptomatic, EDB compensates)
- Juncturae tendinae: 85-90% (interconnections limit independent toe testing)
- High tendon division: 25-30% (splits in distal leg rather than at ankle)
Examination Pearls
- Isolate testing: Block adjacent toes to eliminate juncturae contribution
- Passive stretch test: Plantarflex ankle and toes - pain suggests pathology
- Deep peroneal palsy: Loss of TA, EHL, and EDL function with first web space sensory loss
- Tendon laceration: Passive extension may be preserved (EDB and juncturae compensate)
Surgical Considerations
- Tendon transfer: EDL to 5th toe preferred donor (minimal morbidity)
- Fasciotomy landmarks: Lateral to tibial crest, full length, ensure all four compartments
- Safe dissection: Retract EDL medially to protect anterior tibial vessels
- Repair timing: Primary repair if within 2 weeks; reconstruction/transfer if chronic
Evidence Base & Landmark Trials
The two highest-yield evidence streams relevant to EDL are the compartment-pressure threshold studies (which define when the anterior compartment containing EDL must be decompressed) and the anatomical variation literature (which underpins clinical testing and tendon harvest). The Edinburgh group's work on the differential (delta) pressure threshold remains the single most cited body of evidence guiding fasciotomy decisions worldwide.
McQueen & Court-Brown (1996) - Pressure threshold for decompression (landmark)
- Prospective continuous monitoring of anterior compartment pressure in 116 tibial diaphyseal fractures
- A differential (diastolic minus compartment) pressure threshold of less than 30 mmHg gave NO missed cases of acute compartment syndrome
- Absolute thresholds of 30 or 40 mmHg would have led to 43% and 23% of patients undergoing unnecessary fasciotomy
McQueen, Christie & Court-Brown (1996) - Outcome of monitored vs unmonitored ACS
- 25 tibial fractures complicated by acute compartment syndrome; 13 monitored, 12 not
- Mean injury-to-fasciotomy delay 16 h (monitored) vs 32 h (unmonitored)
- No sequelae in monitored survivors; 10 of 11 unmonitored survivors had muscle weakness and contractures
McQueen, Duckworth, Aitken & Court-Brown (2013) - Accuracy of continuous monitoring
- 850 monitored tibial diaphyseal fractures; 152 (17.9%) had fasciotomy
- Continuous intracompartmental pressure monitoring: estimated sensitivity 94%, specificity 98%
- Positive predictive value 93%, negative predictive value 99%