Verdan Zones | Mallet Finger | Boutonnière | Elson's Test
- Verdan Zones: Odd = Joints (I=DIP, III=PIP, V=MCP, VII=Wrist). Even = Bones
- Mallet (Zone I): Stack splint DIPJ extension 6-8 weeks. Bony mallet: DIPJ subluxation, not fragment size alone, is the strongest surgical indication; greater than 1/3 articular without subluxation can be splinted
- Boutonnière (Zone III): Central slip rupture → lateral bands migrate volar → PIPJ flexion, DIPJ hyperextension
- Elson's Test: Flex PIPJ 90°, extend against resistance. Intact = floppy DIP. Torn = rigid DIP (lateral bands tighten)
- Sagittal Band (Zone V): 'Boxer's knuckle' - tendon subluxates ulnarly between knuckles
- “Active DIP flexion exercises MANDATORY in Boutonnière splinting (pulls lateral bands dorsal)
- “Juncturae tendinum can mask proximal lacerations - test each finger independently
- “Zone V lacerations often penetrate joint capsule - requires washout
- “Relative Motion Splinting (Yoke) favoured for Zone V-VI repairs, though most evidence is Level IV
Extensor Tendon Injuries
Overview & Epidemiology
Extensor tendon injuries are among the most frequently encountered hand tendon injuries. In a 10-year US population-based study, acute traumatic hand and wrist tendon injuries occurred at 33.2 per 100,000 person-years, with extensor injuries more common than flexor injuries, a peak at age 20-29 and a male predominance (de Jong 2014).
Who and where. The most common extensor injury site overall is Zone III of the index finger. About 25% of injuries are work-related, in construction, food preparation and transport, which is worth knowing when counselling about return to work.
Mechanism. The most common closed tendon injury is the mallet finger (Zone I), typically from forced flexion of the extended DIPJ, the ball-sport "jamming" injury. The mechanism predicts the lesion:
- Lacerations from glass and knives dominate open dorsal injuries
- Closed avulsions cause the mallet and boutonnière deformities
- Direct blows cause sagittal band rupture
Pathophysiology & Functional Anatomy
A flat, low-excursion system. Unlike the round, gliding flexors, the extensor mechanism is thin and broad, with little excursion, and it tolerates little gapping. Even 1-2 mm of lengthening at a repair site produces a clinically significant extensor lag, which is what drives much of management.
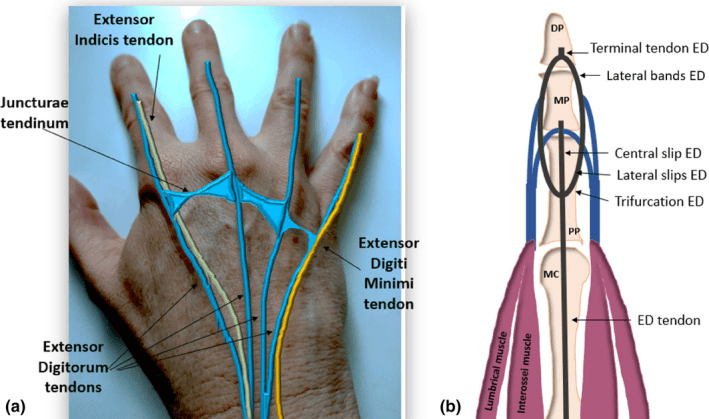
Extrinsic and intrinsic. The extrinsic extensors (EDC, EIP, EDM, EPL, ECRL/B, ECU) arise in the forearm. The intrinsic muscles, the lumbricals and interossei, contribute the lateral bands.
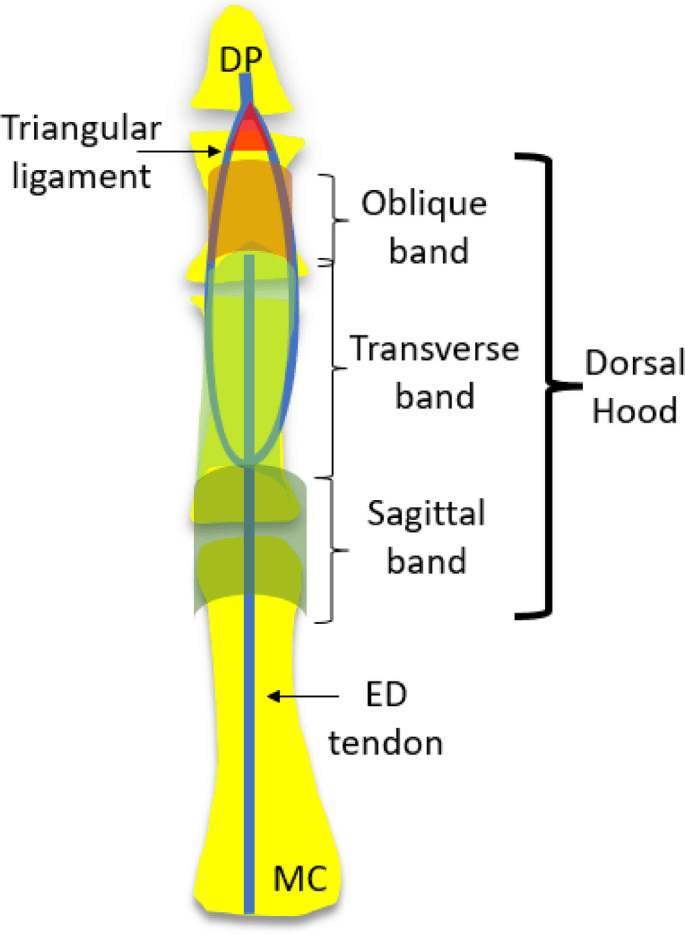
Over the finger. Over the proximal phalanx the EDC splits. The central slip inserts on the base of the middle phalanx and extends the PIPJ. The two lateral bands join the intrinsics as the conjoined lateral bands and continue as the terminal tendon to the distal phalanx, which extends the DIPJ.
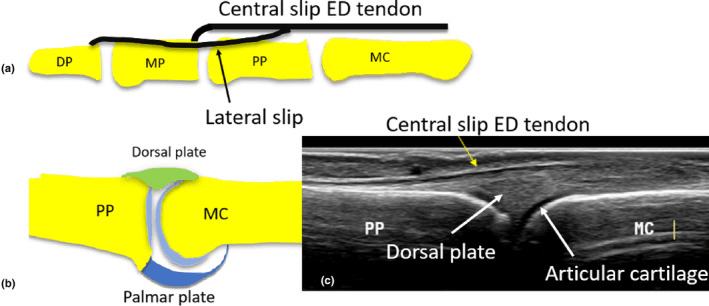
At the MCPJ. The sagittal bands tether the EDC centrally over the joint. When they rupture the tendon subluxes ulnarwards, the "boxer's knuckle".
Between the tendons. The juncturae tendinum interconnect the EDC tendons over the dorsum of the hand, which is why they can mask a laceration (see Examination).
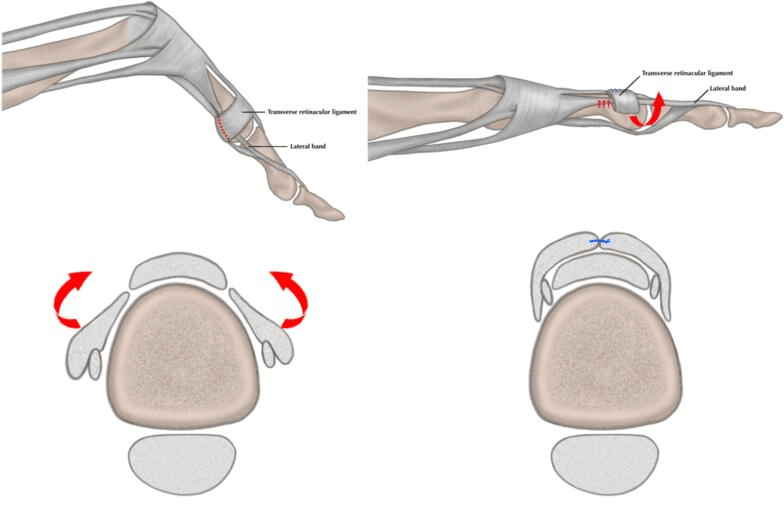
The restraints at the PIP and DIP. The triangular ligament lies dorsally and distally and keeps the lateral bands dorsal. The transverse retinacular ligament and the oblique retinacular ligament (ORL, of Landsmeer) restrain them volar-ward and mechanically couple PIP and DIP motion. The ORL runs volar to the PIP axis and dorsal to the DIP axis, so PIP extension tightens it and assists DIP extension.
Classification: Verdan Zones
Across the digits, Zones I-V alternate between joint levels (I, III, V) and phalangeal segments (II, IV); Zone VI is the metacarpal dorsum, VII the wrist and extensor retinaculum, VIII the distal forearm and IX the musculotendinous junction. Odd numbers are joints and even numbers bones, but tendon calibre, excursion, contamination risk and adjacent-joint involvement, not an odd/even mnemonic alone, determine repair and rehabilitation.
- Level
- DIP joint
- What lies there
- Terminal tendon: mallet finger
- Level
- Middle phalanx
- What lies there
- Level
- PIP joint
- What lies there
- Central slip: boutonnière
- Level
- Proximal phalanx
- What lies there
- Level
- MCP joint
- What lies there
- Sagittal bands: boxer's knuckle
- Level
- Metacarpal (dorsum of hand)
- What lies there
- Juncturae tendinum
- Level
- Carpus
- What lies there
- Extensor retinaculum: high adhesion and tethering risk
- Level
- Distal forearm
- What lies there
- Muscle bellies: repair to muscle is harder
- Level
- Musculotendinous junction
- What lies there
- Proximal forearm
Clinical Presentation and Examination
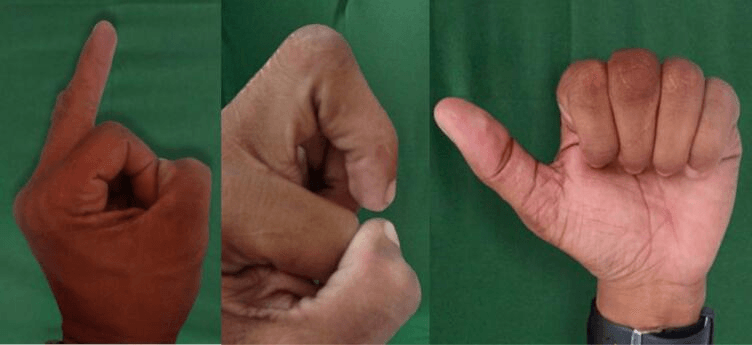
Extensor injuries are largely a clinical diagnosis. Assess active extension against gravity and resistance at each zone; for the central slip, the aim is to make the diagnosis before the deformity appears.
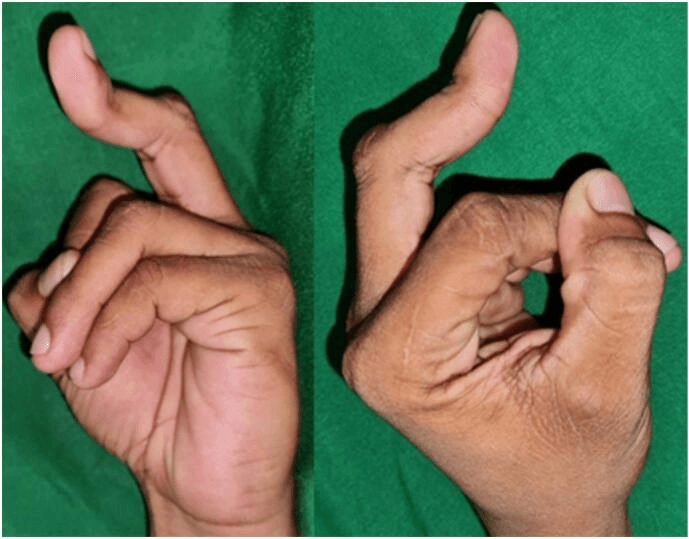
Elson's test (central slip, Zone III). Flex the PIP to 90° over the edge of a table and ask the patient to extend it against resistance. If the central slip is intact, extension is strong and the DIP stays floppy, because the lateral bands are loose. If it is torn, extension is weak and the DIP goes rigid in fixed extension, because the extensor force is diverted to the lateral bands.
Floppy is fine, rigid is ruptured. Elson's is the reference early test, and it matters because an acute Zone III injury should be diagnosed before a boutonnière develops.
Boyes' test (central slip, late sign). Hold the PIP in passive extension and ask the patient to flex the DIP actively. Inability to flex the DIP suggests a central-slip injury with tight, contracted lateral bands. It turns positive later than Elson's, which is why Elson's is preferred acutely.
EDC versus EIP and EDM. Ask the patient to extend the index or little finger while the other fingers are held in a fist. Only the independent extensors, EIP to the index and EDM to the little finger, can do this, because EDC is slack when the other MCPs are flexed. The test confirms an intact independent extensor and identifies EIP as available for transfer.
Test each digit on its own. Through the juncturae tendinum an intact adjacent EDC can extend a finger with a proximal (zone V-VI) laceration and mask the injury, so a finger that extends does not prove its own tendon is intact.
Sagittal band (Zone V). The patient cannot initiate MCP extension from a flexed position but can hold it once the finger is placed there passively. Watch for the tendon snapping ulnarwards into the intermetacarpal valley.
Investigations
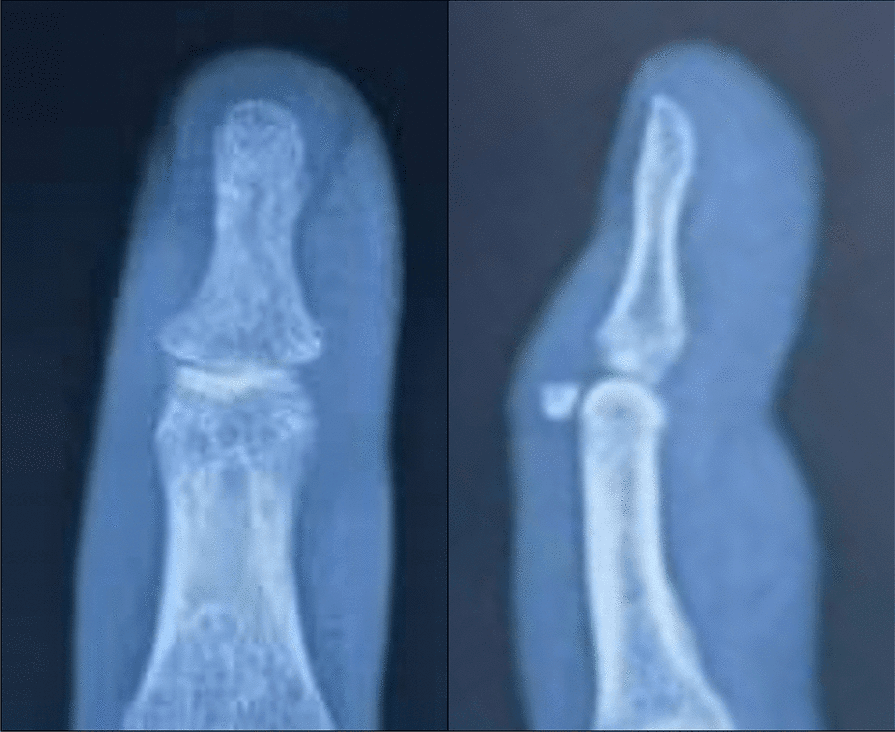
Radiographs. AP and true lateral films are mandatory for any suspected mallet. They quantify the fragment size as a percentage of the articular surface and show any volar subluxation of the distal phalanx, the key surgical trigger. They also exclude an associated fracture or dislocation and, in a laceration, a radiopaque glass foreign body.
Wound exploration is the definitive investigation for an open dorsal injury. Examine the tendon through the full range of motion: a tendon divided with the finger in flexion retracts out of the wound when the finger is extended.
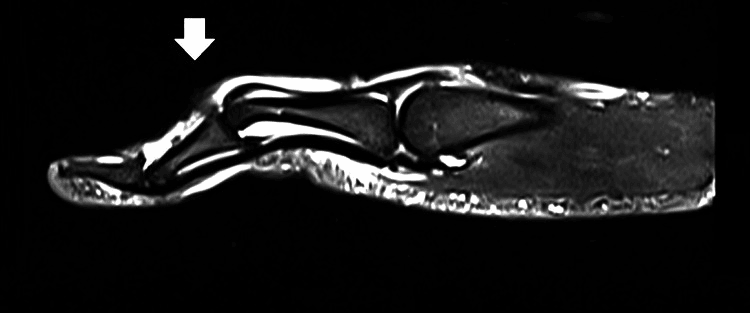
Ultrasound and MRI are reserved for chronic, occult or zone VII-VIII injuries where the level of disruption or adhesion is unclear. They are not routine in the acute setting.
Differential Diagnosis of Loss of Active Finger Extension
The cardinal sign of an extensor injury, inability to actively extend a digit, has several mimics. Distinguishing them changes management entirely.
- Key feature
- Cannot actively extend AND cannot hold passively-corrected position
- Discriminator
- Wound on dorsum; clear deficit at corresponding zone
- Management
- Repair (open) or zone-specific splinting (closed)
- Key feature
- Cannot INITIATE extension from flexion, but HOLDS extension once placed
- Discriminator
- Tendon snaps ulnar-ward into intermetacarpal valley; middle finger
- Management
- Extension/relative-motion splint if acute; reconstruction if chronic
- Key feature
- Mechanical block to motion, not a tendon deficit
- Discriminator
- Radiographs; passive motion also restricted
- Management
- Reduction +/- open release
- Key feature
- Multiple digits lose MCP extension; wrist extends radially
- Discriminator
- Tenodesis intact; no wound; sensation normal
- Management
- Investigate cause (mass, fracture, neuritis); not a tendon repair
- Key feature
- DIP flexion deformity from bony/physeal injury, often open with nail-bed disruption
- Discriminator
- Paediatric; radiograph shows physeal separation; nail plate out of fold
- Management
- Open injury — irrigation, antibiotics, reduction; NOT simple splinting
Management
The lesion. Rupture of the terminal extensor tendon at its insertion, with or without a bony avulsion (the bony mallet).
Closed soft-tissue mallet. A Stack or other extension splint holds the DIPJ in full extension only, leaving the PIPJ free. It is worn continuously for 6-8 weeks, then at night for 2-4 weeks. Any episode of DIP flexion, however brief, resets healing.
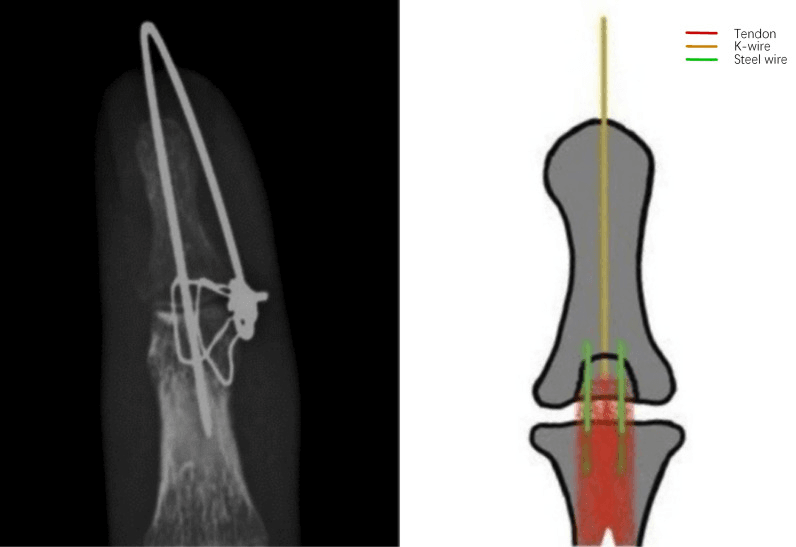
Bony mallet. The long-held rule that a fragment of more than one-third of the articular surface needs surgery is increasingly questioned. The strongest surgical indication is now DIPJ subluxation or instability, not fragment size alone:
- Without subluxation, splinting is appropriate even for large fragments: comparative data show outcomes matching surgery at lower cost and complication (Gumussuyu 2021)
- With volar subluxation or joint instability, extension-block pinning (Ishiguro) or ORIF
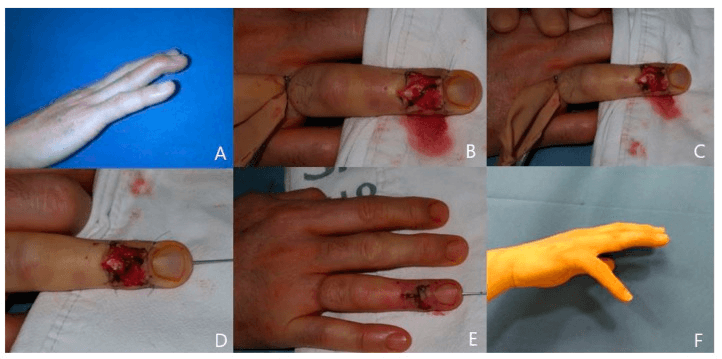

Chronic mallet. Tenodermodesis, or a Fowler central slip tenotomy for a secondary swan-neck.
Epidemiology of Hand & Wrist Tendon Injuries
- 10-year US population-based cohort: acute traumatic tendon injury incidence 33.2 per 100,000 person-years
- Extensor tendon injuries occurred MORE frequently than flexor tendon injuries
- Most common extensor injury site: zone III of the index finger; peak incidence at age 20-29; male predominance
- Work-related injuries accounted for 24.9%, most often in construction/extraction occupations
Splinting for Mallet Finger (Cochrane Review)
- Four randomised/quasi-randomised trials, 278 participants with 283 mallet injuries
- Insufficient evidence to show any custom-made or off-the-shelf finger splint is superior to a standard Stack splint
- No significant difference between Kirschner-wire fixation and splinting (Pryor & Howard) for the single comparative trial
- Patient adherence to continuous splint use and splint durability identified as central to success
Elson's Test for Central Slip Rupture (Original Description)
- Closed central slip rupture is easily missed until a late buttonhole (Boutonnière) deformity appears
- From a PIP flexed 90° over a table edge, the patient extends against resistance
- Absent PIP extension force WITH fixed (rigid) extension at the DIP indicates complete central slip rupture
- Detects injury earlier than Boyes' test, which only becomes positive late
Pin-Block vs Extension Orthosis for Bony Mallet
- 39 closed mallet fractures with greater than 1/3 articular involvement WITHOUT subluxation (Wehbe-Schneider IB/IC); 21 pin-block vs 18 extension orthosis
- No significant difference in clinical outcome, extension lag, DIPJ flexion, pain or aesthetic scores at mean 18-month follow-up
- Conservative group had a more frequent dorsal bump but fewer complications (no pin-tract infection/nail dystrophy)
- Direct, indirect and total costs were significantly higher in the surgical group
Extension Block Pinning (Ishiguro) vs Single K-Wire for Bony Mallet
- 98 surgically treated mallet fractures comparing the Ishiguro extension-block technique with a single-wire 'umbrella' technique, assessed at 1 year by the Crawford method
- Both percutaneous techniques achieved good results overall
- Better outcomes in younger patients and those treated early, regardless of technique
- Technique selection should be guided by fragment size/displacement (Wehbe-Schneider type) and time from injury
ICAM / Relative-Motion Yoke Orthosis for Zone IV-VII Repairs
- Describes the Wyndell Merritt immediate controlled active motion (ICAM) relative-motion yoke orthosis for zone IV-VII extensor repairs
- The yoke holds the repaired digit in relative MCP extension, offloading the repair while permitting immediate active hand use
- Case experience showed early restoration of composite motion and grip strength comparable to the uninjured hand by ~10 weeks
- Offers a low-profile alternative to bulky dynamic/static forearm-based splinting, without wrist immobilisation
Relative Motion Flexion Orthosis for Boutonnière
- 23 patients managed with a relative-motion flexion (RMF) orthosis: 8 acute Boutonnière (6 weeks) and chronic cases after serial casting (3 months)
- Greater MCP flexion increases dorsal EDC pull on the lateral bands, drawing them dorsally and relaxing the volar lumbrical pull
- All patients met Strickland-Steichen 'excellent' criteria, with a mean 35° increase in range of motion
- Both acute and selected chronic Boutonnière improved, supporting a trial of non-operative RMF before surgery
Complications
- Site
- Zone I, II, III
- Cause
- Tendon lengthening/gapping
- Management
- Accept if functional, Re-repair/Shortening
- Site
- Zone VII (Retinaculum), IV
- Cause
- Immobilisation
- Management
- Tenolysis
- Site
- Zone I (Chronic Mallet)
- Cause
- DIP flexion, lateral bands migrate dorsal, then PIP hyperextension
- Management
- Central slip tenotomy (Fowler)
Guidelines, Registries & Global Practice
Global Epidemiology
- Acute traumatic hand/wrist tendon injuries occur at ~33 per 100,000 person-years (10-year US population study); extensor injuries are more common than flexor, peaking at age 20-29 with male predominance (de Jong 2014).
- Zone III of the index finger is the most common extensor injury site; mallet finger (Zone I) is the most common closed tendon injury and a frequent ball-sport (cricket, basketball, baseball) and occupational injury worldwide.
- ~25% of hand tendon injuries are work-related, concentrated in construction/extraction, food preparation, and transport occupations — relevant for return-to-work planning in any health system.
Side-by-Side Guidance
- Position on extensor injuries
- Continuous DIP-extension splinting for soft-tissue mallet; surgery reserved for subluxation/large unstable fragments; early controlled motion regimens for zone IV-VII repairs
- Position on extensor injuries
- Zone-based management; splinting first-line for mallet and acute closed Boutonnière; primary repair with epitendinous augmentation for open lacerations
- Position on extensor injuries
- Endorses relative-motion (ICAM/yoke) and early-active-motion protocols for dorsal hand repairs to reduce adhesions
- Position on extensor injuries
- Harmonises Verdan zone terminology and outcome reporting across regions
There is broad international agreement: closed soft-tissue mallet and acute Boutonnière are splinted; open lacerations are repaired; relative-motion rehabilitation is favoured for zone IV-VII. Differences are mainly in operative thresholds for bony mallet and in availability of certified hand therapy.
Registry & Outcome Notes
- Unlike arthroplasty, extensor tendon injuries are not tracked in implant registries; evidence rests on cohort series and the single Cochrane review (Handoll 2004), which highlights the lack of high-level trial data — a recognised research gap.
- Outcome reporting uses Strickland-Steichen / Miller criteria, extensor lag, and total active motion (TAM); standardised PROMs (e.g. MHQ) increasingly supplement these.
High- vs Limited-Resource Practice
- Well-resourced settings: certified hand therapists, custom thermoplastic and relative-motion orthoses, early-active-motion protocols, and ready microsurgical repair.
- Limited-resource settings: reliance on prefabricated/improvised extension splints (aluminium-foam, Stack), static immobilisation when therapy is scarce, and longer travel for specialist repair — making adherence-friendly, low-cost splinting and clear patient education disproportionately important.
- Universal first principles: tetanus status, wound irrigation and prophylactic antibiotics for contaminated/bite wounds, and a low threshold to exclude joint penetration in dorsal lacerations.
The Extensor Mechanism as a Balanced System (Why the Deformities Interconvert)
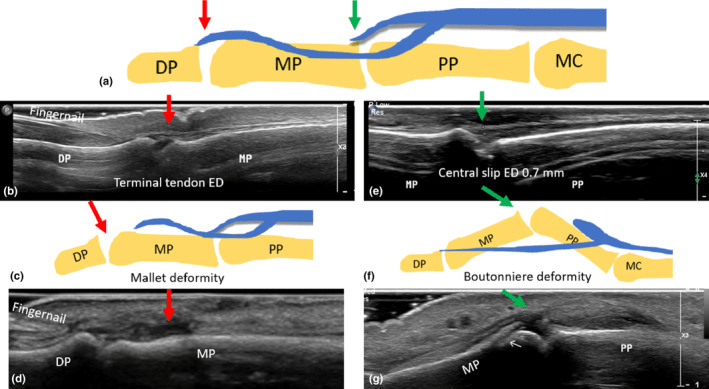
One balance, three deformities. PIP extension is driven by the central slip, dorsally; DIP extension by the conjoined lateral bands and terminal tendon. Mallet, boutonnière and swan-neck are all failures of that same central-slip, lateral-band and ORL balance, and boutonnière and swan-neck are mirror-image PIP/DIP postures:
- Mallet (Zone I). The terminal tendon is lost; the DIP rests flexed and cannot be actively extended.
- Boutonnière (Zone III). The central slip fails and the lateral bands slip volar to the PIP axis. They now flex the PIP and, being tight, hyperextend the DIP.
- Swan-neck. The balance tips the other way and the PIP hyperextends while the DIP flexes. The causes are a chronic mallet (the terminal tendon lost, so extensor force is thrown proximally onto the central slip), volar plate laxity, or intrinsic tightness. This is why an untreated mallet can evolve into a secondary swan-neck.
The therapeutic corollary. The coupling explains the treatments used elsewhere in this topic. Active DIP flexion during boutonnière splinting draws the lateral bands back dorsally; a Fowler central-slip tenotomy deliberately weakens PIP extension to rebalance a mallet-driven swan-neck; and over-correcting a boutonnière risks tipping the finger into a swan-neck. Each established deformity is developed in its own topic.
Controversies & Areas of Uncertainty
Mallet splint and duration. The Cochrane review (Handoll 2004) found no splint type superior. Six to eight weeks of continuous splinting is convention rather than high-level evidence, and the trade-off between rigid adherence and skin maceration is unresolved.
Relative-motion versus traditional splinting. For zone IV-VII repairs, relative-motion (yoke/ICAM) protocols are compared with dynamic or static splinting, but most of the evidence is Level IV and high-quality randomised comparison data are still limited.
Capsular exploration in zone V lacerations. Whether every dorsal MCP laceration mandates formal joint exploration, or only those with a fight-bite mechanism or a visible capsular breach, remains a point of judgement. The cost of a missed septic joint drives a low threshold.
MCQ Practice Points
Q: What are the extensor tendon zones and why are they important?
A: 8 zones (odd numbers over joints, even over bones): Zone 1 (DIP), Zone 2 (middle phalanx), Zone 3 (PIP), Zone 4 (proximal phalanx), Zone 5 (MCP), Zone 6 (metacarpals), Zone 7 (wrist), Zone 8 (forearm). Importance: Treatment varies by zone - Zone 1-2 often splinted, Zone 3+ usually repaired. Zones over joints have thinner tendons and less surrounding tissue, making repair more challenging and prone to adhesions.
Q: What is a mallet finger and how is it treated?
A: Mallet finger: Zone 1 injury with disruption of terminal extensor tendon, causing DIP flexion deformity (15-45°). Types: Tendinous (closed injury, forced flexion); Bony (avulsion fracture of distal phalanx dorsum). Treatment: Closed/small bony mallet: Splinting in DIP extension (Stack splint) for 6-8 weeks continuous, followed by 4 weeks night splinting. Bony mallet with greater than 30% articular surface or subluxation: Consider K-wire or ORIF.
Q: What is a boutonniere deformity and what causes it?
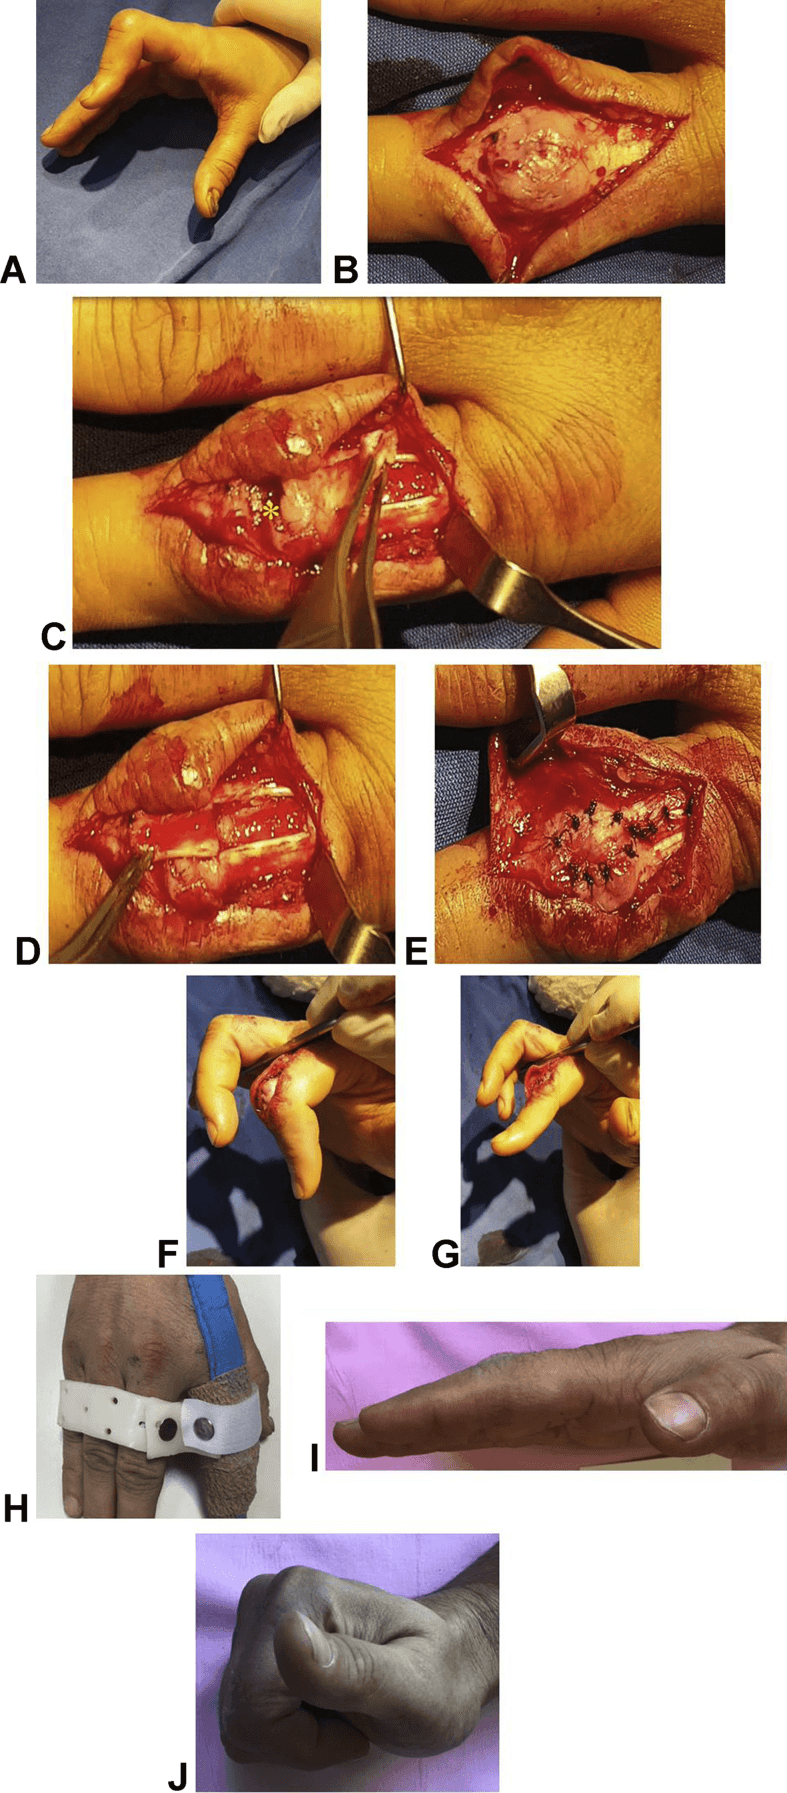
A: Boutonniere deformity: PIP flexion + DIP hyperextension, caused by Zone 3 injury (central slip disruption). Mechanism: Central slip disruption causes lateral bands to migrate volar to PIP axis, becoming flexors at PIP and increasing extension at DIP. Acute treatment: Splint PIP in extension (DIP free) for 6 weeks. Chronic boutonniere: Surgical reconstruction (lateral band mobilization, extensor tenolysis, central slip reconstruction) with variable results.
Q: What is the Elson test and what does it assess?
A: Elson test assesses central slip integrity (Zone 3). Technique: PIP flexed 90° over table edge, patient attempts to extend against resistance. Positive test: Weak PIP extension with rigid DIP (due to lateral bands substituting via intact lateral bands). Negative test: Strong PIP extension with floppy DIP. A positive Elson test in acute injury indicates central slip rupture requiring splinting to prevent boutonniere deformity.
Q: What is a sagittal band rupture and how does it present?
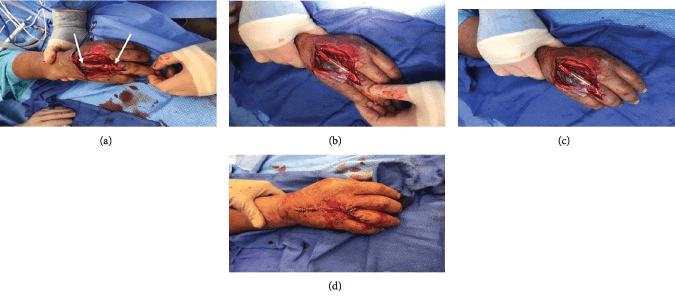
A: Sagittal band stabilizes extensor tendon over MCP joint (Zone 5). Rupture causes extensor subluxation (tendon subluxates ulnarly, usually over middle finger). Presentation: Painful snapping over MCP with finger extension; May be unable to initiate extension from flexed position. Causes: Trauma (punch), inflammatory arthritis. Treatment: Acute (less than 3 weeks) - splinting MCP in extension; Chronic - surgical repair/reconstruction of sagittal band.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 30-year-old woman cut the back of her hand on glass. She has a 2cm laceration over the 3rd MCP joint. She cannot extend the middle finger at the MCPJ. X-ray is normal. How do you manage this?”
“A 28-year-old basketball player presents 2 days after jamming his right ring finger. He has a flexion deformity at the DIP joint and cannot actively extend it. X-rays show an avulsion fracture involving approximately 40% of the articular surface of the distal phalanx with 2mm of volar subluxation of the distal phalanx. What is your assessment and management approach?”
“A 45-year-old presents with a longstanding deformity of his left index finger that occurred after a basketball injury 18 months ago. He was told it was just a 'jammed finger' and it was not treated initially. Examination shows fixed PIP joint flexion contracture of 40 degrees and DIP joint hyperextension of 30 degrees. He cannot actively extend the PIP joint beyond 40 degrees of flexion and passive correction is limited to 20 degrees. X-rays show no arthritis. He requests treatment as the deformity affects his hand function and appearance. What would you discuss?”
Zones
- I: DIP (Mallet)
- III: PIP (Central Slip/Boutonnière)
- V: MCP (Sagittal Band)
- Odd = Joints
Tests
- Elson's Test: For Zone III (Central slip)
- Bouvier Test: For Ulnar Claw (Intrinsics)
Treatments
- Mallet: Splint DIP only 6-8w
- Boutonnière: Splint PIP extension 6w (Active DIP flexion)
- Open V/VI: Repair + Early Motion
References
- Elson RA. Rupture of the central slip of the extensor hood of the finger. A test for early diagnosis. J Bone Joint Surg Br. 1986;68(2):229-31. PMID 3958008.
- Handoll HHG, Vaghela MV. Interventions for treating mallet finger injuries. Cochrane Database Syst Rev. 2004;(3):CD004574. PMID 15266538.
- de Jong JP, Nguyen JT, Sonnema AJM, et al. The incidence of acute traumatic tendon injuries in the hand and wrist: a 10-year population-based study. Clin Orthop Surg. 2014;6(2):196-202. PMID 24900902.
- Gumussuyu G, Asoglu MM, Guler O, et al. Extension pin block technique versus extension orthosis for acute bony mallet finger; a retrospective comparison. Orthop Traumatol Surg Res. 2021;107(5):102764. PMID 33333280.
- Burns MC, Derby B, Neumeister MW. Wyndell Merritt immediate controlled active motion (ICAM) protocol following extensor tendon repairs in zone IV-VII. Hand (N Y). 2013;8(1):17-22. PMID 24426888.
- Merritt WH. The relative motion concept in acute and chronic boutonniere deformity: invited commentary. J Hand Ther. 2023;36(2):258-268. PMID 37045641.
- Rocchi L, Fulchignoni C, De Vitis R, et al. Extension block pinning vs single Kirschner wiring to treat bony mallet finger. Acta Biomed. 2022;92(S3):e2021535. PMID 35604272.
- Doyle JR. Extensor tendons: acute injuries. In: Green's Operative Hand Surgery.