Congenital localised gigantism of digits following nerve territory distribution - staged surgical management
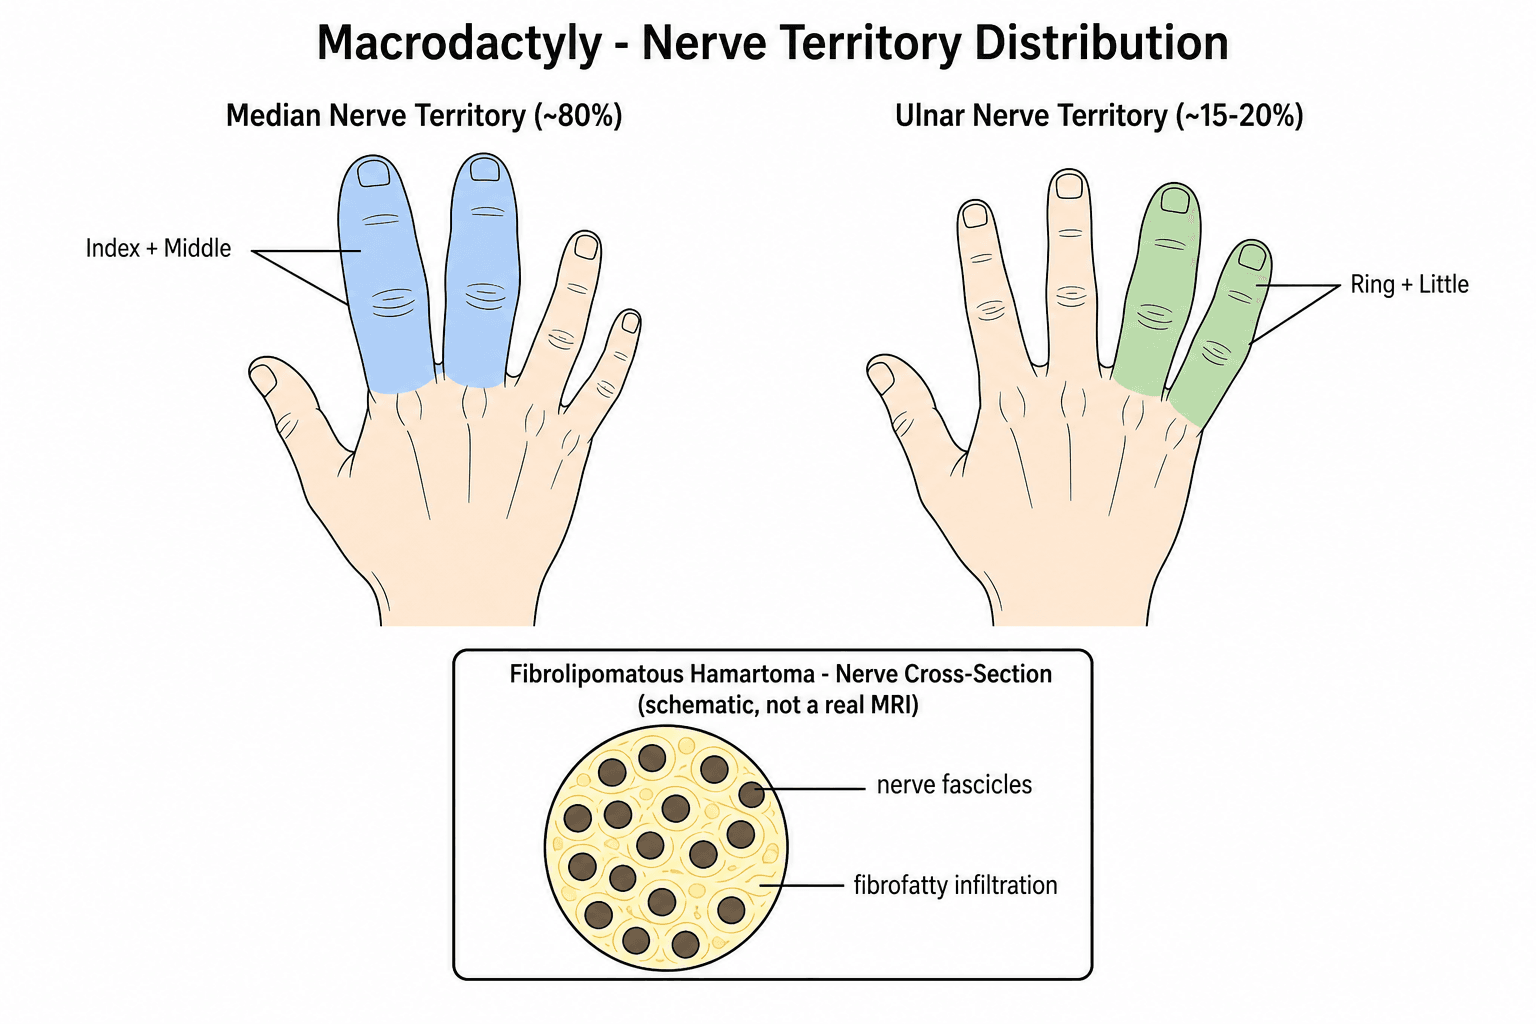
- Nerve-territory oriented in about 80% of hands (median) and 91% of feet (medial plantar) - characteristic, not pathognomonic
- All mesenchymal elements enlarged (bone, nerve, fat, skin, vessels)
- Two types: Static (proportional growth) vs Progressive (accelerated growth)
- Staged debulking preferred - preserve neurovascular structures
- Epiphysiodesis before skeletal maturity to prevent further length discrepancy
- “Index and middle finger = median nerve; ring and small = ulnar nerve
- “MRI shows intraneural lipomatosis (high T1 signal in enlarged nerve)
- “Ray amputation may be best option for severe, non-functional digits
- “Progressive type has higher recurrence and worse functional outcomes
Macrodactyly
Overview and Epidemiology
Macrodactyly is a rare congenital disorder in which all the mesenchymal elements of a digit or digits overgrow, leaving the digit disproportionately enlarged. The enlargement typically follows a nerve territory, most commonly the median. Management turns on careful timing, with staged debulking and possible ray amputation for severe cases, and early recognition and multidisciplinary planning optimise both function and appearance.
How rare. Macrodactyly is exceptionally rare. The conventional figures are an incidence of about 1 in 100,000 live births and a share of roughly 1% of congenital upper-limb anomalies, but neither is traceable to a population denominator in the sources cited here, so quote them as convention rather than measurement.
Classic operative experience in macrodactyly
- Foundational operative series establishing macrodactyly as a rare overgrowth of all digital tissue elements (bone, nerve, fat, skin)
- Macrodactyly accounts for roughly 1% of congenital upper-limb anomalies
- Described staged debulking combined with osteotomy and epiphysiodesis to control size and length
Several digits, side by side. What the large series do show is that multiple digits are affected far more often than a single digit: 3.9 times more often in a 170-case hand-and-foot cohort and 2.0 times more often in 95 feet. The affected digits are usually adjacent, the index and middle fingers dominating in the hand and the second and third toes in the foot.
Clinical characteristics of 170 cases of macrodactyly
- Affected fingers were in the median nerve territory in 79.4%; affected toes in the medial plantar nerve territory in 89.1%
- PROGRESSIVE macrodactyly outnumbered static in this cohort, and most progressive cases were noticed at birth
- Multiple-digit involvement was 3.9 times more frequent than single-digit; metacarpal involvement occurred only in the progressive type
- Blood DNA was negative in all 12 patients whose overgrowth tissue carried a PIK3CA mutation
The hand and the foot are not the same disease. The two large cohorts describe the same territory logic driven by different tissue. In the hand the finger sits in the median territory and the nerve itself is the lesion: grossly enlarged, fat-infiltrated, and the structure that dictates the operation. In the foot the toe sits in the medial plantar territory but the picture is lipomatous, with adipose overgrowth dominating, a milder neural component, and the nerve reported as normal in 10 of 95 feet.
That is why foot series read as debulking-and-reconstruction problems while hand series read as nerve problems, and why a toe result should not be transferred to a finger.
Isolated macrodactyly of the foot in 93 children (95 feet)
- Static overgrowth in 63% - the reverse of the hand cohort, where progressive predominated
- Affected toes and forefeet lay in the medial plantar nerve territory in 91%; the forefoot was involved in 90 of 95 feet
- Nerves were enlarged in 49 feet, fat-infiltrated in 25, tortuous in 1 and NORMAL in 10; muscle was involved in only 6
- Phalanges enlarged in 92 feet, metatarsals in 57, advanced bone maturation in 63; syndactyly in 22 cases
Associated conditions. Macrodactyly may occur as an isolated finding or in association with other conditions. Approximately 10-15% of patients have associated syndactyly of the affected digits. The recognised syndromic associations are neurofibromatosis type 1, which requires careful evaluation for café-au-lait spots and family history, Proteus syndrome (asymmetric overgrowth with connective tissue naevi) and Klippel-Trenaunay-Weber syndrome (capillary malformations with venous and lymphatic anomalies).
Pathophysiology and Anatomy
The molecular basis. Isolated macrodactyly is now recognised as part of the PIK3CA-Related Overgrowth Spectrum (PROS). The driver is a somatic, mosaic gain-of-function mutation in PIK3CA, the gene encoding the p110-alpha catalytic subunit of PI3K, which constitutively activates the PI3K-AKT-mTOR pathway and produces unregulated tissue growth.
Why the overgrowth is segmental. The mutation is post-zygotic and mosaic, so the overgrowth follows the affected cell lineage rather than a Mendelian inheritance pattern. The same pathway underlies the broader PROS family (CLOVES, fibroadipose hyperplasia, hemihyperplasia-multiple lipomatosis), and recognising macrodactyly as a forme fruste of PROS prompts screening for associated overgrowth and vascular anomalies.
Somatic PIK3CA mutations drive isolated macrodactyly
- Mosaic activating PIK3CA mutations detected in 10 of 12 patients with isolated macrodactyly
- Recurrent oncogenic hotspot variants (H1047R, H1047L, E545K, E542K) at low mutant allele fraction (7-27%)
- Adipose tissue had the highest mutation-detection rate, followed by nerve and skin
Every tissue enlarges. All the mesenchymal elements grow disproportionately. The bone shows accelerated growth, with widened phalanges, widened medullary canals and early physeal closure in some cases; the skin is thickened and thrown into redundant folds; ligaments and tendons hypertrophy; and vascularity increases, with tortuous vessels.
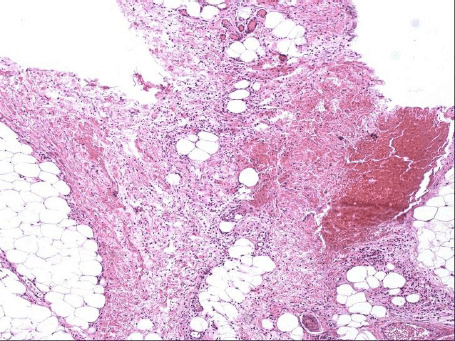
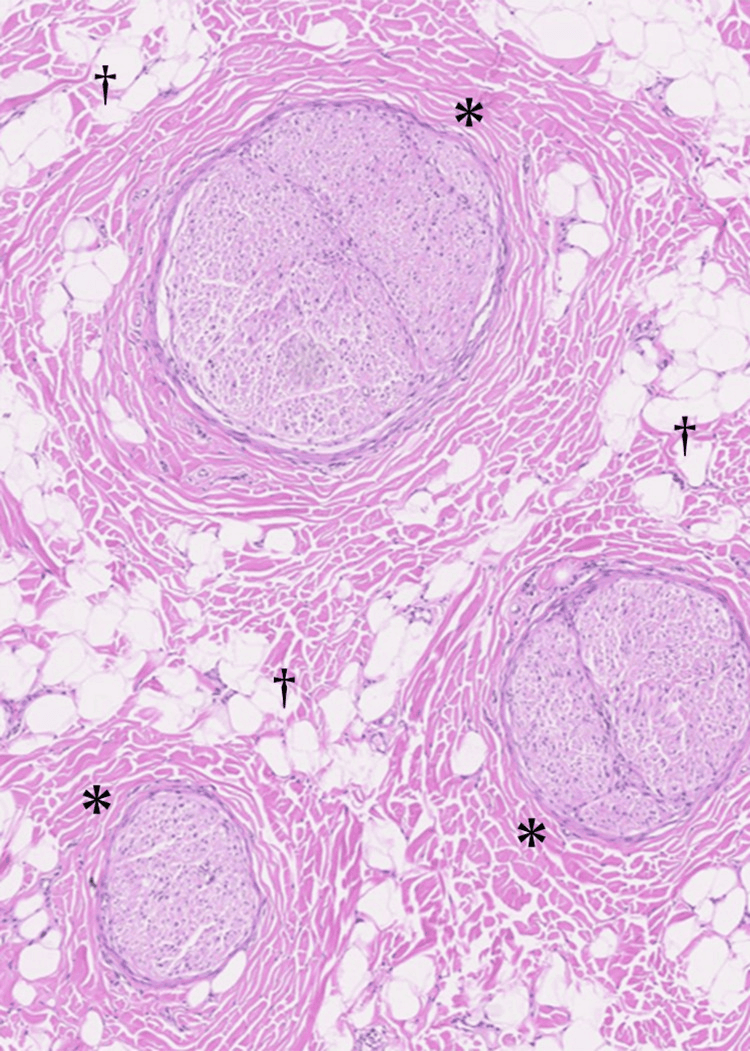
Fat is the hallmark. Adipose proliferation is the hallmark finding. Histology shows extensive fibrofatty proliferation within and around the peripheral nerves (lipomatous macrodystrophy), and a massive fibrofatty proliferation fills the subcutaneous tissue.
The nerve. In the hand the peripheral nerve is the structure that defines macrodactyly. The affected nerve is grossly enlarged and tortuous, with a diameter that may be 3-5 times normal, and microscopy shows adipose tissue infiltrating between the fascicles (intraneural lipomatosis), increased epineurial connective tissue, and normal myelinated axons interspersed with excessive perineural fat.
This neural lipomatous infiltration distinguishes macrodactyly from other causes of localised gigantism, with the foot, where adipose overgrowth dominates, the exception described above.
Classification
The most exam-relevant classification divides macrodactyly by growth behaviour, which directly informs surgical timing and prognosis. The static (type I) digit is fully manifest at birth and grows proportionally with the child. The progressive (type II) digit grows at an accelerated, disproportionate rate, often worsening during growth spurts.
In the 170-case referral series most progressive cases were nonetheless noticed at birth, and metacarpal involvement occurred only in the progressive type. Confirm static versus progressive from the growth history and serial measurements: it is the single most useful prognostic discriminator.
- static
- Full manifestation present
- progressive
- Mild or subtle findings
- static
- Proportional to body growth
- progressive
- Accelerated, disproportionate
- static
- Predominant in the foot (63% of 95 feet)
- progressive
- Predominant in the 170-case hand-led referral series
- static
- Clearly defined distribution
- progressive
- May cross nerve territories
- static
- Elective, staged procedures
- progressive
- Earlier intervention needed
- static
- Better functional outcomes
- progressive
- Higher recurrence, worse function
Clinical Presentation
History. Parents typically present with enlargement noticed at birth or in early childhood. The question that matters is the growth history: whether the disproportion, evident from birth, has grown in step with the child, as in the static type, or has become increasingly apparent with age, particularly during growth spurts, as in the progressive type.
Examination. One or more digits are disproportionately enlarged, with every tissue involved: skin, subcutaneous tissue, bone and nail. The digit feels doughy from the excess subcutaneous fat, and skin folds may be prominent with redundant tissue. Document the nerve territory carefully, since it is the most useful single observation supporting the diagnosis. A systematic assessment covers:
- Extent - examine from fingertip to forearm
- Nerve territory - which digits are affected, correlated with the median, ulnar and radial distributions
- Function - grip strength, pinch, range of motion and activities of daily living
- Comparative measurement - digital calliper measurements against the contralateral normal digits
- Associated findings - syndactyly, café-au-lait spots (neurofibromatosis), vascular malformations
- Growth - serial measurements and photographs to document progression
Function. Deficits vary with the degree of enlargement and the digits involved. The common problems are difficulty with fine motor tasks, reduced grip strength from abnormal digit mechanics, impaired pinch when the thumb or index finger is involved, and psychosocial concerns about appearance. As the child grows, the enlarged digit may interfere with writing, using utensils and keyboard use.
Nerve function. Despite the massive enlargement of the nerve, neurological function is typically preserved. Two-point discrimination is usually normal, though some patients may report hyperaesthesia or altered sensation, and the intrinsic muscles supplied by the affected nerve are generally normal unless there has been previous surgery.
Investigations
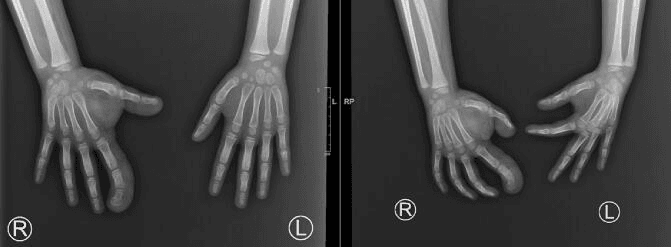
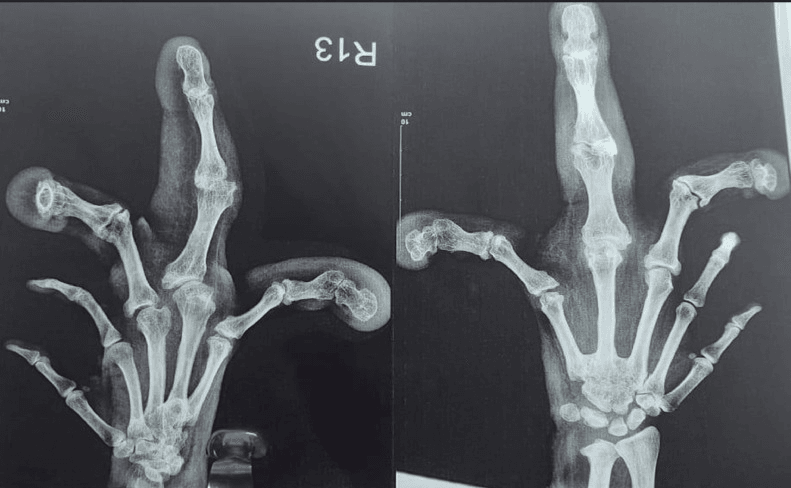
Radiographs. Plain radiographs of the hand are essential for initial assessment and surgical planning. Anteroposterior and lateral views show soft-tissue prominence, widened phalanges with cortical thickening, splayed epiphyses, and occasionally skeletal maturation in the affected digit advanced beyond the adjacent normal digits.
Original description and radiographic classification of macrodactyly
- Defined the static versus progressive growth dichotomy that remains the standard classification
- Radiographic hallmarks: soft-tissue enlargement, widened/thickened phalanges, splayed epiphyses
- Advanced skeletal maturation of the affected digit relative to adjacent normal digits
Serial films. Serial radiographs monitor growth velocity and time the epiphysiodesis. The bone age of the affected digit may be advanced beyond the chronological age, particularly in progressive macrodactyly, and phalangeal width, length and angulation should be documented for comparison over time.
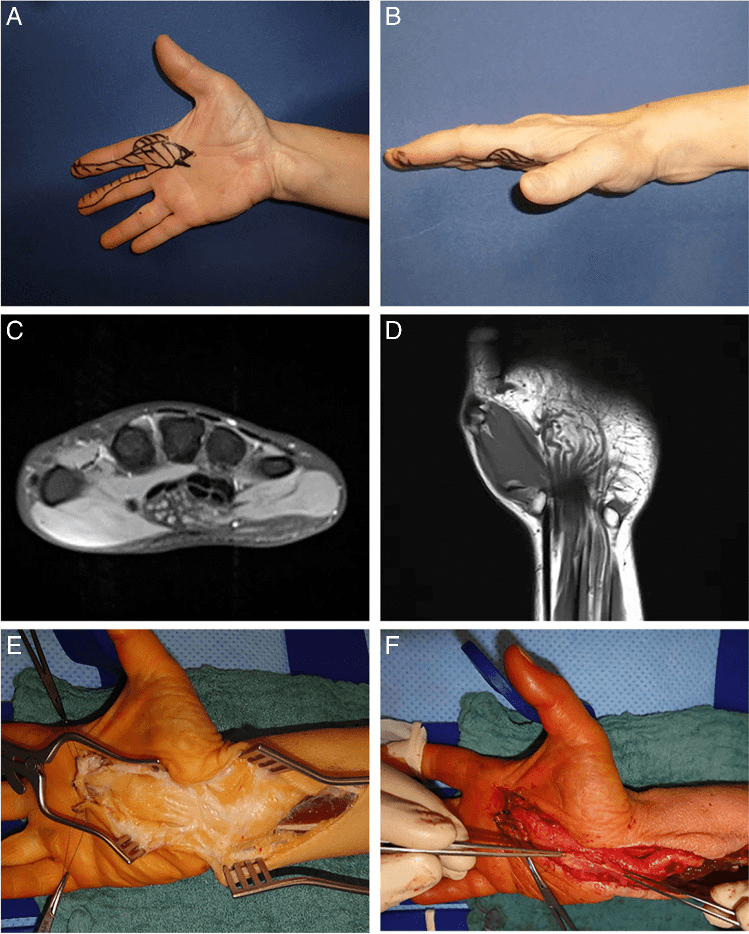
MRI. MRI characterises the soft tissues and informs surgical planning. It shows the extent of fibrofatty infiltration, nerve enlargement with intraneural lipomatosis (characteristic high signal on T1-weighted images), the vascular anatomy, and the relationship of the enlarged structures to joints and tendons.
It is particularly valuable when debulking is being considered, because it delineates the neurovascular bundles precisely and allows the excision to be planned. Fat-suppressed sequences help differentiate lipomatous tissue from other soft-tissue elements.
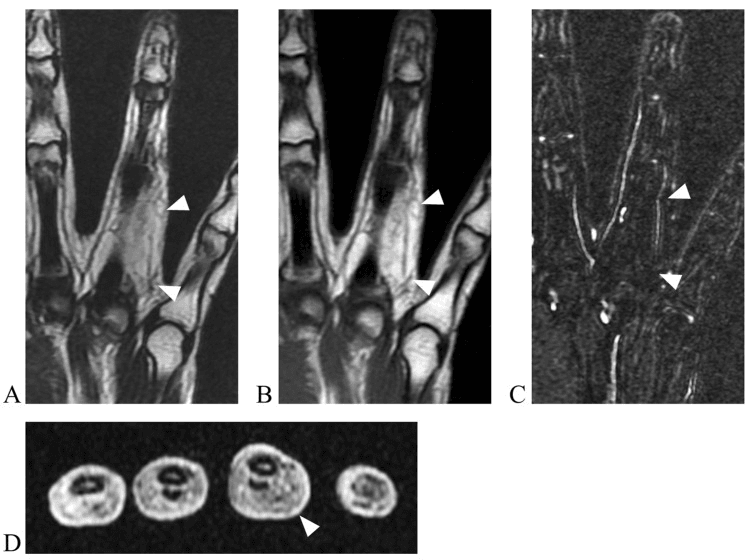
Vascular studies. Doppler ultrasound or MR angiography may be considered when vascular anomalies are suspected or extensive debulking is planned. These studies identify the course of the digital arteries, assess for arteriovenous malformations, and help predict vascular complications during surgery.
Differential Diagnosis
Localised digital or limb gigantism has a focused differential. What marks true macrodactyly is enlargement of all tissue elements in a nerve-territory distribution with intraneural lipomatosis.
- clue
- All tissues enlarged; nerve-territory distribution; doughy fat
- keyTest
- MRI - intraneural lipomatous nerve (high T1); somatic PIK3CA in tissue
- distinguisher
- Enlarged tortuous nerve is the hallmark
- clue
- Cafe-au-lait macules, axillary freckling, plexiform neurofibromas, family history
- keyTest
- NF1 gene; whorled neurofibroma on MRI/histology
- distinguisher
- Plexiform neurofibroma, not simple fatty overgrowth
- clue
- Bluish/warm, compressible, bruit or thrill, may enlarge with dependency
- keyTest
- Doppler ultrasound, MR angiography
- distinguisher
- Flow voids/feeding vessels; tissue not uniformly fatty
- clue
- Diffuse pitting/non-pitting swelling, no bony enlargement
- keyTest
- Lymphoscintigraphy; normal bone on X-ray
- distinguisher
- No phalangeal widening or bone overgrowth
- clue
- Asymmetric segmental overgrowth crossing nerve territories, connective-tissue/cerebriform nevi
- keyTest
- Clinical criteria; AKT1 (Proteus) mutation
- distinguisher
- Crosses nerve territories; disproportionate, progressive, mosaic
- clue
- Capillary (port-wine) stain, varicosities, limb overgrowth
- keyTest
- Imaging of venous/lymphatic anomaly
- distinguisher
- Capillary-venolymphatic malformation with limb hypertrophy
Macrodactyly of the Foot and Toes
A different set of goals. Macrodactyly of the foot is a distinct clinical problem. The enlargement follows the plantar nerve territories, medial plantar more often than lateral plantar, and the second toe is the most commonly affected, frequently with adjacent-toe involvement. The goal is not fine dexterity but a plantigrade foot that fits a normal shoe and allows painless weight-bearing.
What the enlarged toe costs. A grotesquely enlarged toe causes footwear difficulty, ambulation problems, ulceration over pressure points and psychosocial distress, rather than loss of pinch or grip.
A lower threshold for ray resection. The functional cost of losing a toe is far lower than that of losing a finger, so surgeons hold a lower threshold for ray resection or amputation in the foot, and a normal-width forefoot is often prioritised over the number of digits. The reconstructive ladder mirrors the hand, with staged soft-tissue defatting, epiphysiodesis or physeal ablation to arrest length, shortening and narrowing osteotomies, and terminal (Syme-type) amputation of the distal phalanx, but it is deployed with footwear and forefoot width as the endpoints.
Shared biology, newer options. The same PIK3CA/PROS biology underlies both, and the two-stage defatting-plus-phalangectomy strategy validated in the hand was applied to toes in the same historic series. Microsurgical composite (toenail flap) reconstruction has more recently been described as an alternative to amputation for the severely enlarged toe.
Microsurgical toenail composite-flap reconstruction (severe macrodactyly)
- 10 paediatric patients; macrodactyly dissected into a vascularised composite flap to reconstruct a near-normal digit
- AOFAS score improved from 33.3 to 76.3 (p less than 0.001)
- All reconstructed digits remained viable with satisfactory function and appearance
Ray resection is far better tolerated than in the hand, so a non-salvageable, footwear-limiting toe is a legitimate early candidate for ray amputation rather than repeated debulking. Epiphysiodesis is still timed to the expected adult length, so the reconstructed forefoot matches the contralateral side.
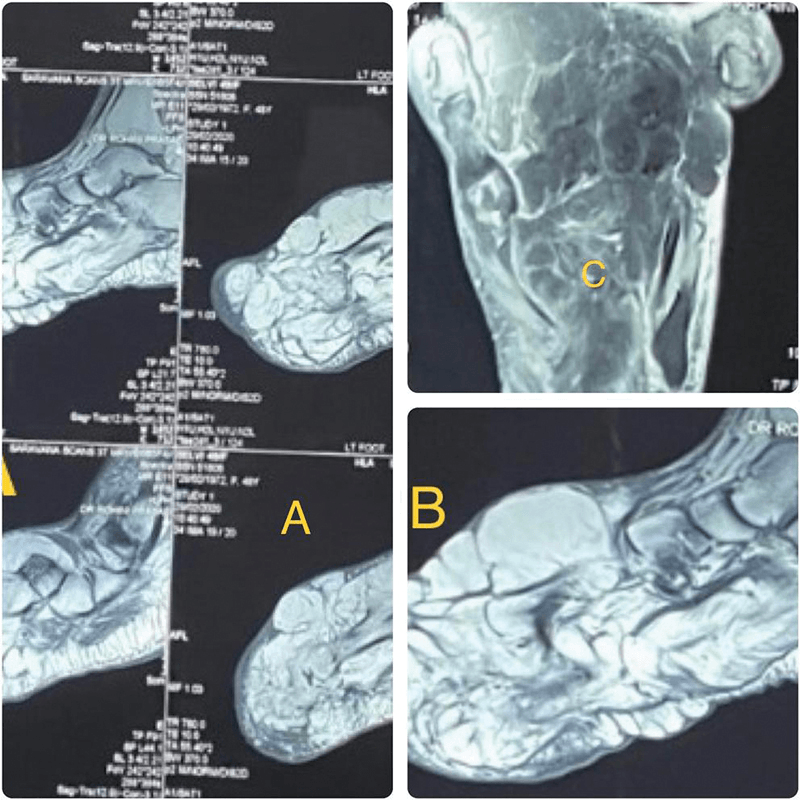
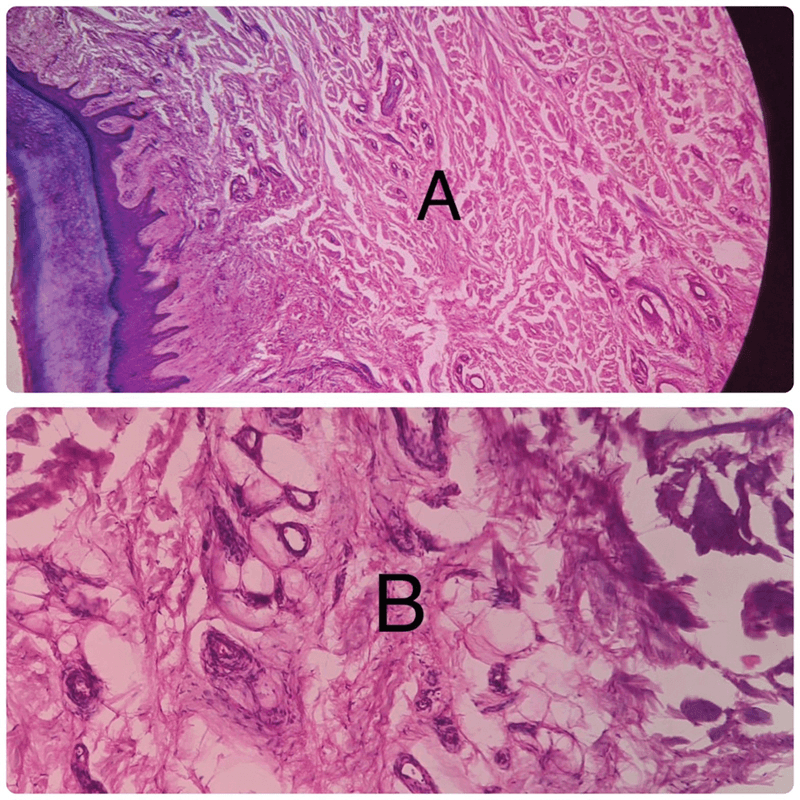
Fibrolipomatous Hamartoma of Nerve (Macrodystrophia Lipomatosa)
One lesion, many names. The grossly enlarged, lipomatous nerve of macrodactyly is itself a named entity: fibrolipomatous hamartoma of nerve, also termed lipofibromatous hamartoma, neural fibrolipoma, lipomatosis of nerve or, when it drives bony overgrowth, macrodystrophia lipomatosa. It is a benign, non-neoplastic proliferation of mature fibrofatty tissue within the epineurium and perineurium, infiltrating between and separating the nerve fascicles.
Why the median nerve. The median nerve is by far the most common site, with a predilection for the volar wrist and hand, which is exactly why median-territory macrodactyly dominates the hand series.
The nerve lesion is not the overgrowth. The two do not always travel together. Only about 30-60% of nerves with this lesion develop overgrowth in their territory at all, and Blackburn found the same activating PIK3CA hotspot variants in 4 of 4 cases that had no territory overgrowth, at allele fractions that did not predict the phenotype. Something other than the mutation decides whether a digit enlarges.
PIK3CA mutations in lipomatosis of nerve with and without territory overgrowth
- Hotspot activating PIK3CA variants in 12 of 14 histologically confirmed cases, across median, ulnar, plantar, sciatic, peroneal nerves and brachial plexus
- Mutations present in 4 of 4 cases that had NO nerve-territory overgrowth, so the mutation alone does not produce macrodactyly
- Variant allele frequency (6-32%) did not correlate with the overgrowth phenotype; three intraneural lipomas had no mutation
Carpal tunnel syndrome. The infiltrated median nerve can produce a compression neuropathy as the fatty bulk enlarges within the carpal canal, so macrodactyly and nerve compression can coexist.
On axial images the low-signal fascicles surrounded by high-signal T1 fat give a "coaxial cable" appearance; on the coronal or longitudinal plane the fascicles running through fat produce a "spaghetti" pattern, and the fatty component suppresses on fat-saturated sequences. The MRI appearance is effectively diagnostic, so biopsy is usually unnecessary.
Management. Do not attempt complete excision of the mass. The hamartoma is inseparable from the functioning nerve, and radical resection risks devastating sensorimotor loss. Treatment is symptom-directed: carpal tunnel or nerve decompression for compressive symptoms, and careful debulking of the fibrofatty tissue with the fascicles preserved: the same principle of nerve preservation over aggressive resection that governs the operation on the digit.
Management
Surgical management is challenging and demands meticulous planning. The goals are to improve function, enhance appearance, control progression, and above all preserve neurovascular structures, and they translate into four working rules:
- Staged, not single-stage - multiple sequenced procedures across childhood outperform one radical operation
- Function over cosmesis - preserve a sensate, mobile digit where possible
- Half at a time - debulk only one side of a digit per stage, to protect the dominant neurovascular bundle and skin perfusion
- Set expectations early - recurrence is common, particularly in the progressive type
The choice between debulking and ray amputation depends on the functional deficit and the patient's age.
- indication
- Moderate enlargement, good skeletal alignment
- technique
- Excision of subcutaneous fat, nerve decompression
- outcomes
- Improved cosmesis, high recurrence risk
- indication
- Longitudinal overgrowth, skeletal immaturity
- technique
- Physeal ablation of affected digit
- outcomes
- Prevents further length discrepancy
- indication
- Phalangeal widening, angular deformity
- technique
- Wedge osteotomy, longitudinal bone excision
- outcomes
- Corrects alignment, reduces width
- indication
- Severe deformity, poor function, family preference
- technique
- Complete digit and metacarpal excision
- outcomes
- Definitive treatment, immediate correction
Management Algorithm
Complications
The dissection. Neurovascular injury, digital nerve or artery damage during dissection, is the most feared complication of debulking, and it demands meticulous dissection with loupe magnification.
Early. The other early complications arise at the wound and from the extent of the operation. Wound healing problems include skin-edge necrosis, dehiscence and infection, and excessive skin excision or tension risks necrosis, so plan incisions with tissue viability in mind. Compartment syndrome is rare but possible with extensive debulking.
After neurolysis. Nerve dysaesthesia may occur after neurolysis. It is usually temporary, but counsel families preoperatively.
Late. The late list is longer:
- Recurrence of soft-tissue overgrowth - 30-50% after soft-tissue debulking, particularly in the progressive type; plan for staged revisions from the outset
- Joint stiffness and contracture - common after extensive soft-tissue procedures; aggressive hand therapy is essential
- Growth disturbance if the physes are injured
- Chronic pain or hypersensitivity
- Functional loss
Functional outcomes. Outcomes are variable and depend on the type (static versus progressive), the extent of involvement, the number and type of procedures performed, and compliance with therapy. Static macrodactyly generally achieves better function than the progressive type, and early intervention with staged procedures tends to yield better results than delayed single-stage radical debulking.
What has actually been measured. No long-term series cited here measures function. The best available follow-up is Kotwal's 23 patients at a mean of nine years, and its endpoint was cosmesis graded by the surgeons: good in 12 and satisfactory in 7 of the 21 who were assessable, with 2 poor results that went on to amputation.
Grip, pinch, sensation and patient-reported outcome were not recorded there or anywhere else in this literature, so the functional comparisons in the paragraph above rest on no measured functional outcome. Quote the cosmetic result, and be explicit that the functional result is unmeasured.
Guidelines, Registries & Global Practice
Macrodactyly is too rare to feature in arthroplasty registries, and there are no formal society guidelines or randomised trials - practice is guided by expert consensus and case series across centres worldwide.
Global Epidemiology
- Estimated incidence about 1 in 100,000 live births; roughly 1% of congenital upper-limb anomalies.
- Usually unilateral - the often-quoted "70% unilateral" is not supported by the largest series: Chen's cohort was 95 feet in 93 children, so only two were bilateral.
- Sex predilection is unsettled: Chen found 60% female with a left-sided predominance (56%), while the 170-case series found incidence similar across sex and geography. Both are single-centre and ethnically narrow.
- Median-nerve territory predominates in the hand (about 80%), index and middle fingers most affected; medial plantar territory in 91% of feet, second and third toes most affected.
Side-by-Side Practice Positions
- focus
- Staged debulking, function over cosmesis, nerve preservation
- position
- Surgery is first-line for the localised digit; ray amputation for non-salvageable border digits
- focus
- Skeletal control - epiphysiodesis and osteotomy timing
- position
- Time length-control to predicted adult digit length; stable fixation in older children
- focus
- Molecular diagnosis and screening
- position
- Test overgrowth tissue for PIK3CA; screen for wider PROS phenotype
- focus
- PI3K-alpha inhibition (alpelisib)
- position
- Reserve targeted drugs for severe/diffuse PROS; not standard for isolated digits
High- versus Limited-Resource Practice
- High-resource settings: multidisciplinary clinics (paediatric hand/plastic surgery, occupational therapy, clinical genetics, psychology), MRI-based planning, access to molecular testing and - selectively - PI3K-inhibitor trials.
- Limited-resource settings: diagnosis is clinical and radiographic; staged debulking and osteotomy remain feasible and effective, while MRI, genetic testing and targeted drugs may be unavailable. Early ray amputation of a non-functional digit can be a pragmatic single-stage solution where repeated staged surgery and long follow-up are impractical.
Long-term follow-up into adolescence and early adulthood is important everywhere for monitoring recurrence and psychosocial outcomes, with planned transition to adult hand services.
Controversies & Areas of Uncertainty
When to operate first. Most advocate early debulking, at 2-4 years, to limit the functional and psychosocial impact, but earlier surgery carries higher technical difficulty and recurrence, and some delay until a clearer functional deficit emerges. No randomised data exist; all the guidance is Level IV.
Debulking or early ray amputation for a border digit. Repeated debulking has diminishing returns against the recurrence rate given under Complications, and some argue that early ray amputation of a non-functional border digit gives a better, single definitive result. The decision remains individualised and value-sensitive.
How far to go with the nerve. How aggressively to neurolyse, or even resect and graft, the lipomatous nerve is debated, trading bulk reduction against sensory loss. Many now favour preserving the nerve and accepting residual bulk.
Targeted medical therapy. PI3K-alpha inhibitors (alpelisib) are an emerging therapy for diffuse PROS, but their role, if any, in isolated digital macrodactyly is unresolved, as are their long-term safety in growing children and how they integrate with surgery.
Molecular testing in routine practice. Whether every isolated macrodactyly warrants PIK3CA testing, and on which tissue, or whether testing should be reserved for atypical and syndromic cases, is not standardised across centres.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 3-year-old boy presents with enlargement of the index and middle fingers present since birth. The fingers are functional but parents are concerned about appearance and anticipate functional problems as he grows. How would you assess and manage this patient?”
“A 7-year-old girl with known macrodactyly affecting her ring and small fingers has had two previous debulking procedures. The digits continue to grow disproportionately and now interfere with hand function. Parents ask about further options. How would you counsel them?”
“A 2-year-old has isolated macrodactyly of the index finger. The parents ask whether this is genetic, whether their next child is at risk, and whether there is any 'medicine' rather than surgery. How do you respond?”
Definition and Characteristic Features
- Localized gigantism of all mesenchymal tissue elements following nerve territory distribution (median nerve 80%)
- Hallmark histology: fibrofatty proliferation with intraneural lipomatosis
- Incidence: 1 in 100,000 live births
Classification - Barsky Types
- TYPE I (Static): full manifestation at birth, proportional growth - the majority in FOOT series (63% of 93 feet)
- TYPE II (Progressive): accelerated disproportionate growth - outnumbers static in the 170-case HAND series
- Also classified by nerve territory (median/ulnar/radial) and anatomic extent (digital/metacarpal/forearm)
Clinical Presentation Pearls
- Digital enlargement from birth or early childhood, doughy feel due to subcutaneous fat, follows nerve distribution
- Median territory: index and middle fingers
- Ulnar territory: ring and small fingers
- Function typically preserved despite appearance
Investigation Protocol
- Plain radiographs (AP/lateral): widened phalanges, splayed epiphyses, advanced bone age
- MRI: extent of fibrofatty infiltration, nerve enlargement (high T1 signal), surgical planning
- Vascular studies if planning extensive debulking
Surgical Treatment Algorithm
- STAGED APPROACH preferred
- Ages 2-4 years: First soft tissue debulking
- Ages 7-10 years: Epiphysiodesis to control length
- Ages 8-12 years: Skeletal procedures (osteotomies)
- RAY AMPUTATION: Severe deformity, border digits, failed debulking, progressive type
Key Complications
- Recurrence (30-50%, especially progressive type)
- Neurovascular injury during debulking
- Joint stiffness post-surgery
- Skin necrosis with excessive excision
- Nerve dysesthesia after neurolysis
- Growth disturbance if physes injured
Differential Diagnosis
- Neurofibromatosis (café-au-lait spots, family history, plexiform neurofibromas)
- Hemihypertrophy (crosses nerve territories)
- Vascular malformations (AVM, lymphatic)
- Proteus syndrome (connective tissue nevi, asymmetric overgrowth)
- Lymphedema (pitting edema, no bone involvement)
Viva Talking Points
- Say nerve-territory oriented, not pathognomonic - about 80% of hands and 91% of feet, and progressive disease may cross territories
- Discuss staged versus single-stage approach (staged preferred)
- Know epiphysiodesis timing (ages 7-10 years)
- Ray amputation indications (border digits, failed debulking)
- Recurrence common, set realistic expectations
- Multidisciplinary approach essential
Evidence Base & Key Literature
The evidence for macrodactyly is dominated by Level IV case series and expert opinion - there are no randomised trials, reflecting the rarity of the condition. The most important recent shift is the molecular reclassification of macrodactyly within the PIK3CA-Related Overgrowth Spectrum (PROS), which has opened targeted medical therapy as a research direction.
PROS consensus: diagnostic and testing framework
- NIH consensus that unified macrodactyly, CLOVES, FAO and related entities under the umbrella term PROS
- Defined clinical diagnostic features and eligibility criteria for PIK3CA molecular testing
- Recommended testing affected (overgrowth) tissue rather than blood given somatic mosaicism
Systematic review: surgical and pharmacological treatment of PROS
- 16 studies synthesised; surgery beneficial mainly for the localised macrodactyly subgroup of PROS
- PI3K/mTOR pathway inhibition reduced hypertrophy and systemic symptoms across studies
- Overall evidence quality limited (mostly retrospective, medium risk of bias)