Common Paediatric Foot Deformity
- Heel-bisector method describes forefoot adduction severity
- Passive flexibility, hindfoot alignment and symptoms matter more than age alone
- Neutral or mildly valgus hindfoot helps distinguish metatarsus adductus from clubfoot
- Examine the hips and use national DDH screening criteria for selective imaging
- Do not conflate metatarsus adductus with skewfoot, which includes hindfoot valgus and midfoot displacement
- “Differentiate from Skewfoot (Z-deformity) and Clubfoot (Hindfoot Varus)
- “Flexible deformity generally improves without casting
- “Rigid or persistent deformity does not acquire an automatic six-month casting indication
- “Surgery is rare; symptoms, rigidity, apex, skeletal maturity and prior treatment determine timing and osteotomy
Overview and Epidemiology
Metatarsus adductus is medial deviation of the forefoot at the tarsometatarsal region with a neutral or mildly valgus hindfoot. The hindfoot separates it from its two look-alikes: clubfoot (TEV) includes hindfoot varus and equinus, and skewfoot combines forefoot adduction with hindfoot valgus and more complex midfoot displacement (a Z-deformity).
Aetiology. Likely multifactorial. Intrauterine position, familial predisposition and soft-tissue or bony shape may contribute, but individual findings do not prove one mechanism. It is one of the "packaging" disorders, alongside hip dysplasia and torticollis, so finding it prompts a look for the others.
Epidemiology. Reported frequency varies with the case definition, including whether mild flexible newborn feet are counted. Bilateral disease is common, and most flexible feet improve during growth.
How practice changed. Long-term follow-up shifted practice away from forceful correction and broad soft-tissue release toward observation, selective casting or orthosis, and rare deformity-specific osteotomy. The long-term cohorts support avoiding overtreatment, while rigid symptomatic feet are less predictable.
Pathoanatomy
Where the deformity lies. Primarily at the Lisfranc (tarsometatarsal) joint. All the metatarsals are adducted relative to the cuneiforms and cuboid, and the first is often the most severely affected.
The tarsal bones. The medial cuneiform is often misshapen, trapezoidal or wedge-shaped with its base lateral, and that bony shape helps maintain adduction of the first ray. In metatarsus adductus the navicular position is relatively normal or slightly lateral.
The hindfoot (subtalar joint) is the critical feature. The calcaneus and talus keep their normal divergent relationship or sit in slight valgus, and the talocalcaneal angle is normal. This is the key differentiator from clubfoot and skewfoot.
The soft tissues. Medially, the abductor hallucis muscle, the tibialis posterior tendon and the medial tarsometatarsal joint capsules are tight. Laterally, the peroneal muscles (peroneus brevis and longus) and the lateral soft tissues are attenuated, or lengthened.
The First Ray: Metatarsus Primus Varus and the Hallux Valgus Question
The first ray's share. The first ray may contribute substantially, but the deformity can involve several metatarsals and tarsometatarsal relationships.
Hallux valgus. A long-held teaching links untreated metatarsus adductus to later hallux valgus and lateral-column overload. That association is now considered weak and debated: the relationship is inconsistent, and the long-term Iowa data did not show hallux valgus as a common outcome. Avoid counselling that a flexible childhood foot will become a bunion.
Classification Systems
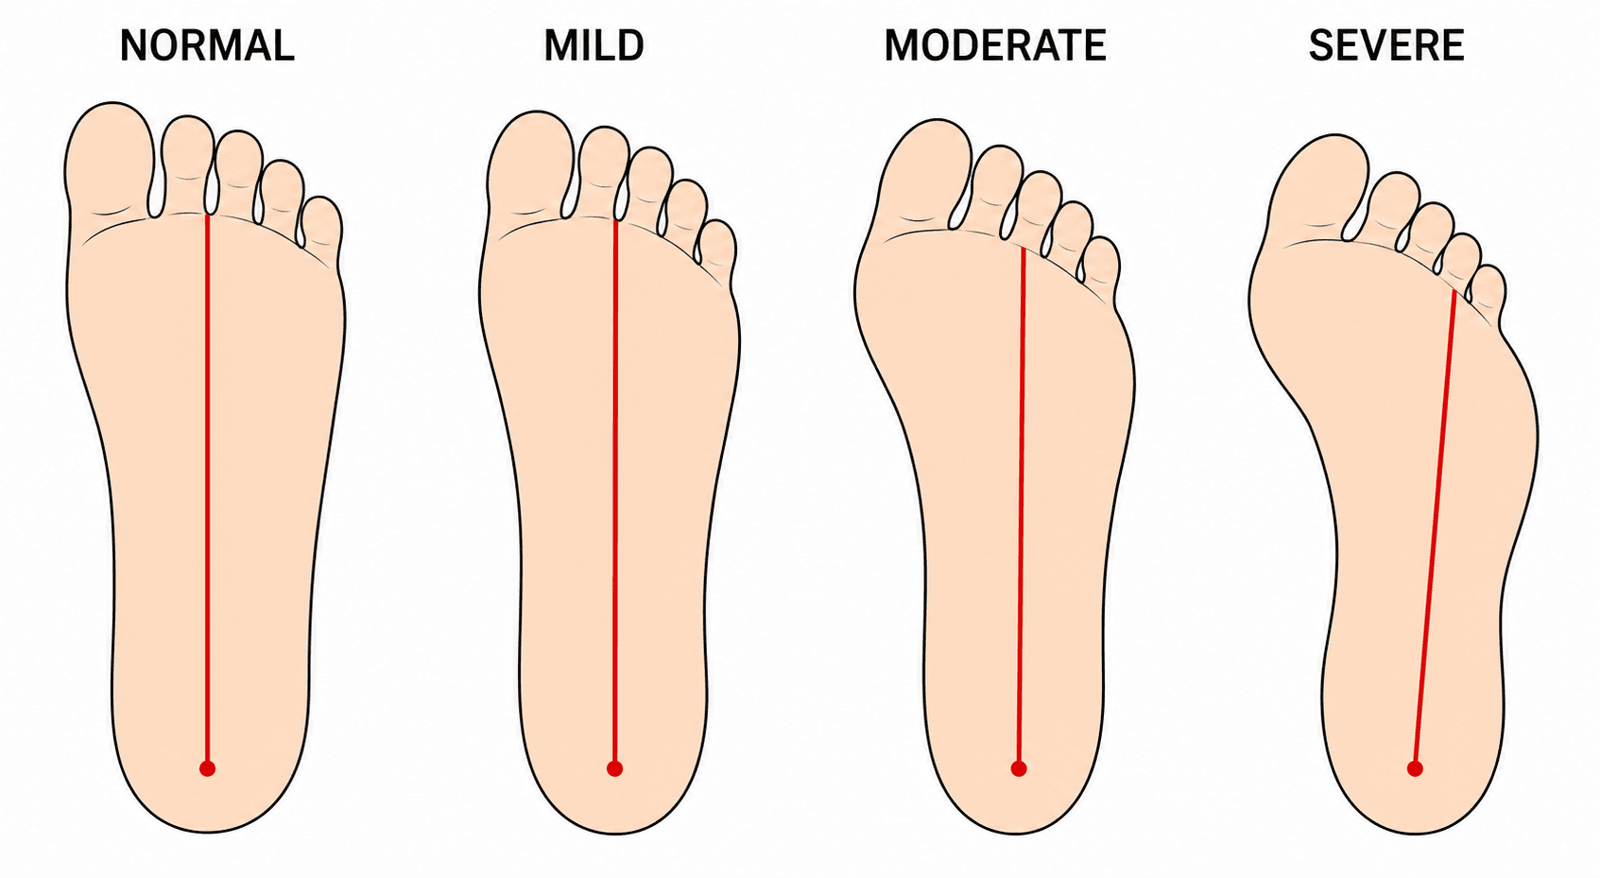
Bleck's heel bisector is the most clinically useful classification and grades severity. It describes shape, but grade does not by itself predict symptoms or mandate treatment, so read the treatments set against each grade in the summary above with that in mind: passive flexibility is the main treatment discriminator. Berg's classification is less commonly used but describes complex deformities.
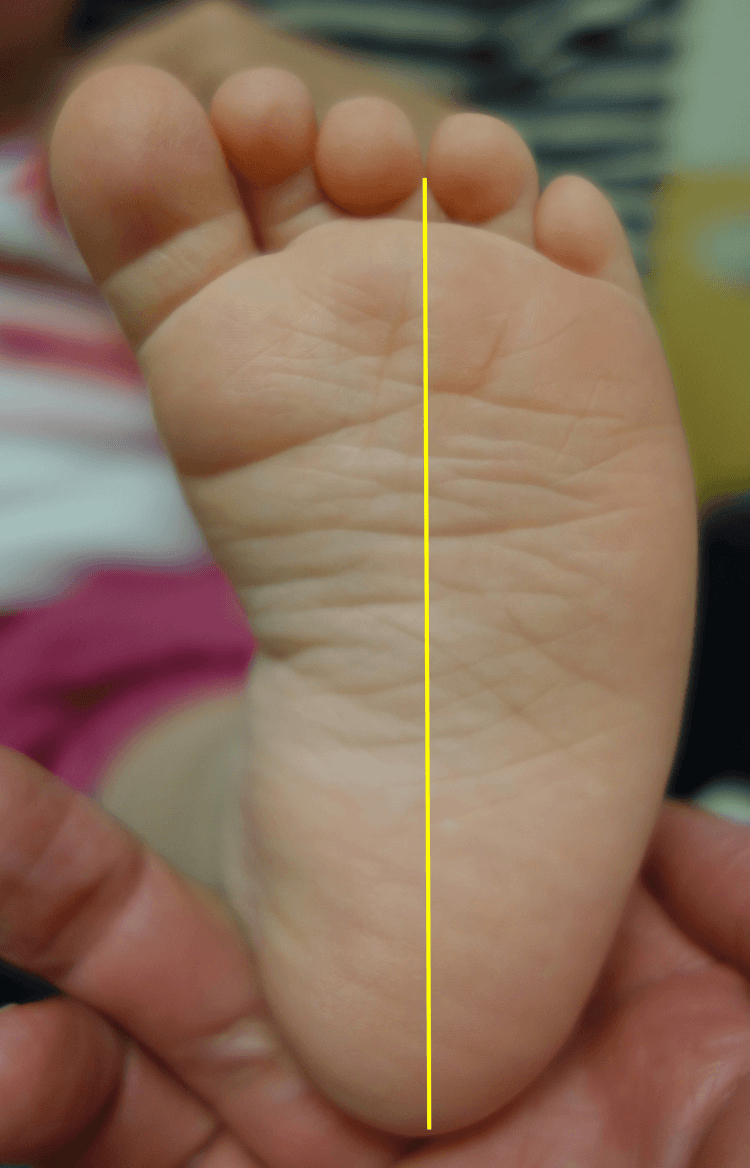
Technique. With the child prone and the knees flexed 90 degrees, imagine a line bisecting the elliptical heel pad and extend it distally to the toes. The line moves laterally as severity increases:
- Normal: between the 2nd and 3rd toes
- Mild: through the 3rd toe
- Moderate: through the 3rd-4th webspace
- Severe: through the 4th-5th webspace
Clinical Assessment
History. The points that matter are when it appeared, the family, the pregnancy and, in a walking child, the gait.
- Onset: when the deformity was first noticed, at birth or later; late onset suggests localised pathology or a mimicking condition
- Family history: foot deformities, hip dysplasia or other packaging problems in siblings or parents
- Pregnancy: breech presentation, oligohydramnios, a first obstetric event
- Gait: the foot progression angle (intoeing); parents often report that the child "trips over their own feet"
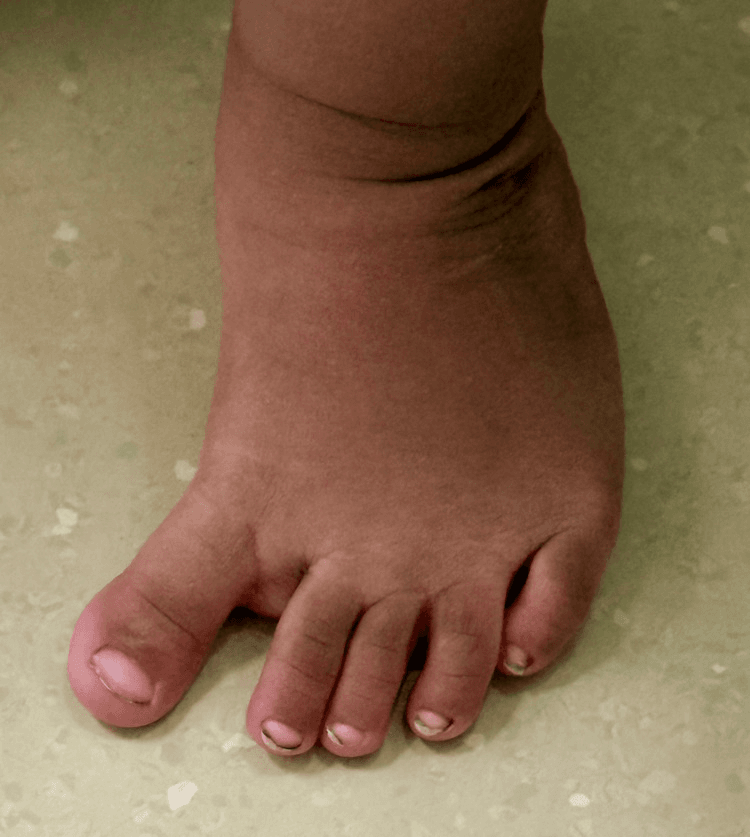
Inspection. The adducted forefoot gives a kidney-bean shape with a convex lateral border and a prominent styloid at the base of the fifth metatarsal. A deep medial midfoot crease suggests rigidity. The toes are often splayed, with a widened gap between the first and second resembling a thumb separation.
The hindfoot is the critical step. Verify that it is neutral or in slight valgus. Varus suggests clubfoot; severe valgus with a rigid adducted forefoot suggests skewfoot.
Severity and flexibility. With the child prone, determine the Bleck grade. Then test flexibility as described under Classification: whether the forefoot reaches neutral, or passes it, dictates management.
Lateral border stimulation (the tickle test). Stroke the lateral border of the foot. A flexible foot actively abducts as the peroneal muscles contract; a rigid foot does not.
Hips, neck and spine. Examine the hips for instability and range in an age-appropriate way, document the findings, and image selectively according to the applicable DDH screening pathway; metatarsus adductus alone does not mandate identical imaging everywhere. Examine the neck, spine and neurology when the history or findings suggest torticollis, neuromuscular or dysraphic disease, or when the deformity is atypical, rigid, asymmetric or accompanied by neurological or cutaneous signs.
Intoeing. Forefoot adduction may contribute to intoeing, but the rotational profile from the hip and tibia must be assessed separately.
Dynamic Metatarsus Adductus (the 'Searching' Hallux)
What it is. In some toddlers the forefoot, especially the great toe, adducts only during active weight-bearing or stance, pulled medially by an overactive abductor hallucis (sometimes with tibialis anterior), and corrects fully at rest and on passive examination. This "searching toe", or dynamic hallux varus, is a functional deformity rather than a structural one: a distinct and easily confused variant, given that the abductor hallucis is repeatedly implicated in metatarsus adductus and the tickle test relies on active muscle pull.
Recognising it. The foot looks straight when relaxed or non-weight-bearing, but the hallux and forefoot swing medially when the child stands or initiates gait. There is no fixed contracture, no deep medial crease and full passive correction, unlike structural (rigid) metatarsus adductus. The tickle test rests on the same peroneal and abductor dynamics: the foot abducts with peroneal firing, confirming a dynamic, flexible deformity rather than a rigid one.
Management. Document flexibility and gait, and in most cases reassure. Observe when the foot is fully flexible and asymptomatic, and avoid casting a foot that has no fixed contracture. A persistent, symptomatic dynamic deformity warrants reassessment of the entire rotational profile and of footwear and loading rather than a reflex cast.
Investigations
The diagnosis is clinical. Radiographs are generally not indicated in infants, whose tarsal bones are largely cartilaginous and not visible.
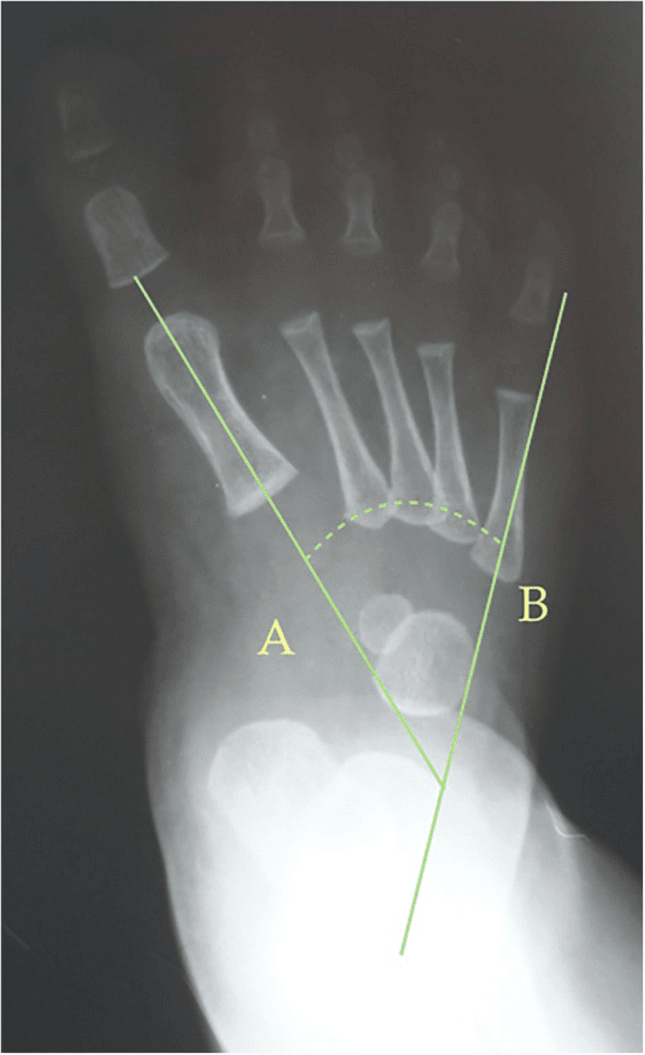
Radiographs. Weight-bearing AP and lateral views. The measurements:
- Metatarsus adductus angle: between the axis of the tarsus and the metatarsals; greater than 20 degrees is abnormal
- Engel's angle: between the second metatarsal and the intermediate cuneiform; normal is less than 24 degrees
- Talocalcaneal (Kite's) angle: 20-40 degrees (divergent) in the normal foot and in metatarsus adductus; parallel (less than 15 degrees) in clubfoot; increased (greater than 40 degrees) in skewfoot, because of the hindfoot valgus
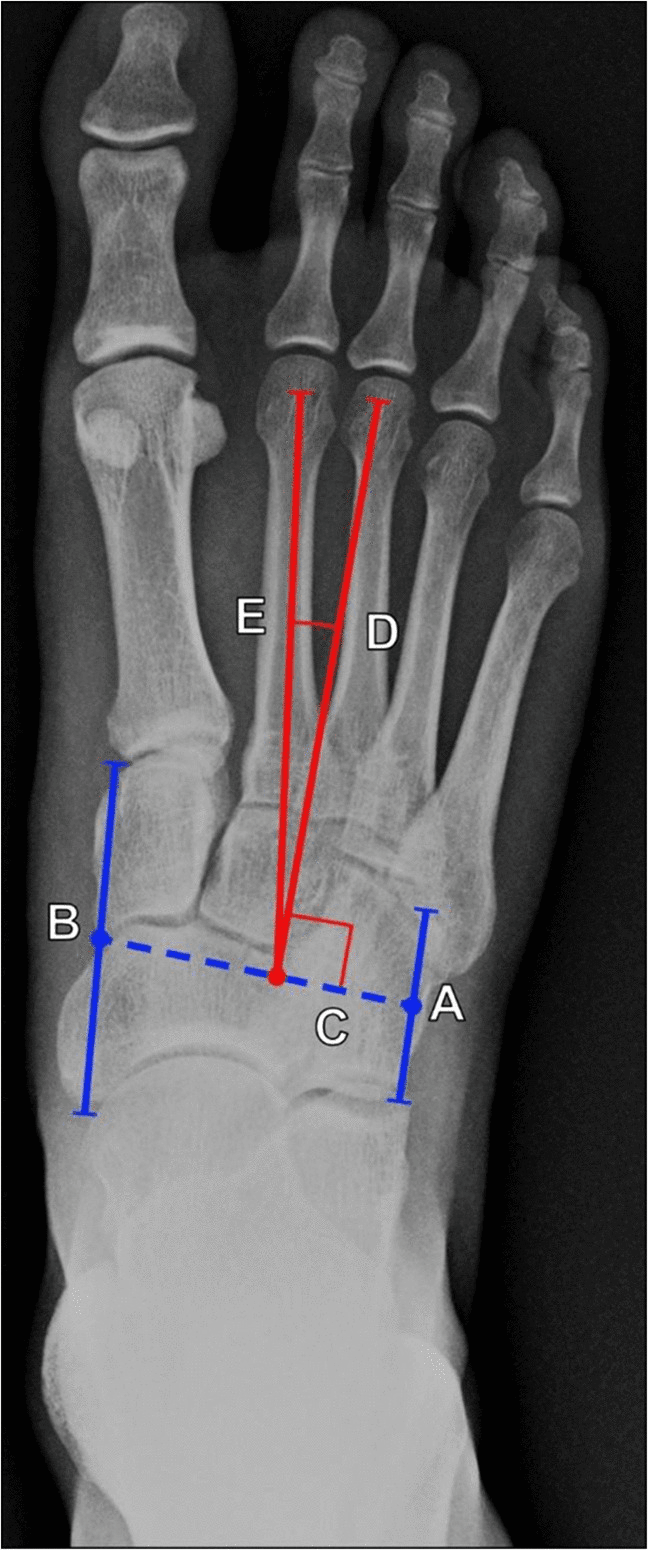
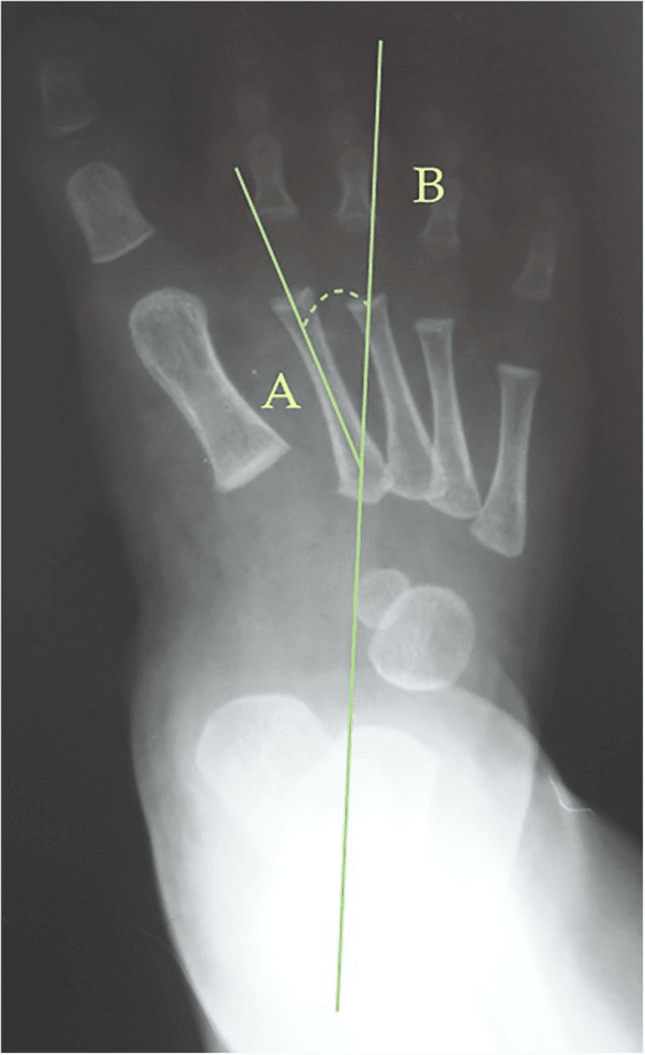
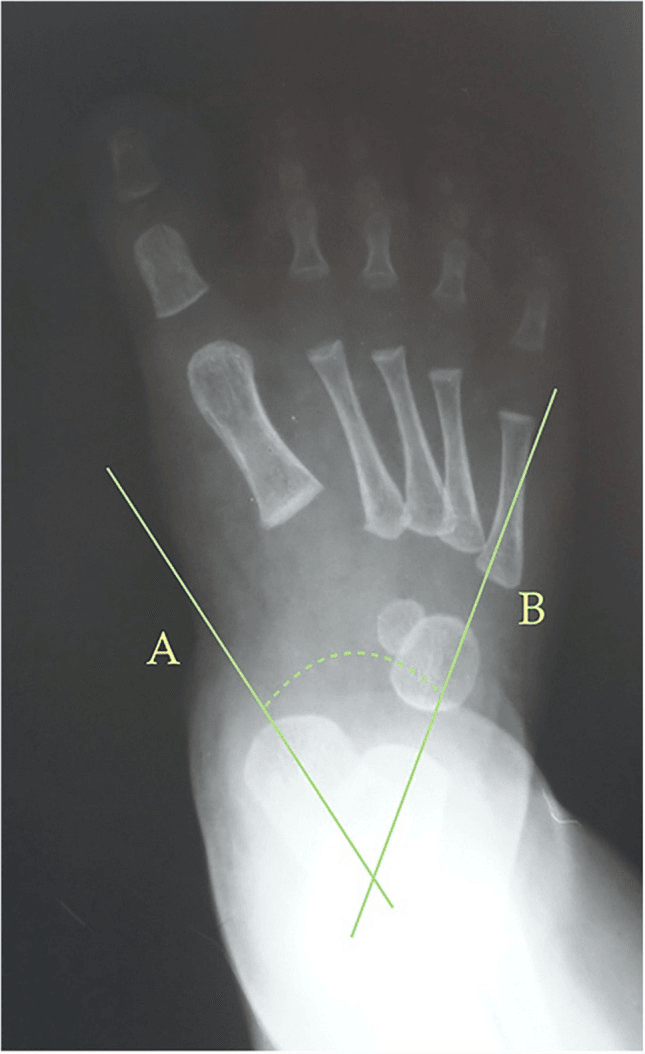
Hip ultrasound. Indicated for any infant with metatarsus adductus if there are clinical risk factors or uncertain hip examination findings. How strong the underlying association is follows below.
CT and MRI. Rarely indicated. They may be used for a complex tarsal coalition workup if rigidity is unexplained.
The Hip: How Strong Is the DDH Association?
The old figure. The 10 to 15% figure is one of the most repeated numbers in paediatric orthopaedics, and it comes from small, selected, largely historical series. A prospective cohort of 60,844 children born in one Norwegian county gives a much lower figure: DDH occurred in 0.8% of the whole population, and among children with a foot deformity metatarsus adductus carried a 1.5% risk, described by the authors as a marginal increase. Talipes calcaneovalgus carried 6.1% and clubfoot 3.5% (DOI, level II).
The association is still real. The same paper confirmed foot deformity overall as a genuine DDH risk factor (p less than 0.001), and the authors say so explicitly. What the data change is the magnitude for this particular deformity, and therefore what follows from finding it.
The two errors are not symmetrical. Over-stating the risk drives universal hip ultrasound for a very common, usually self-resolving foot posture: cost, parental alarm, and incidental findings of physiological immaturity that invite unnecessary treatment. Under-stating it risks a missed DDH, and that is the irreversible error. A hip diagnosed late needs open reduction and often femoral or pelvic osteotomy, carries a real risk of osteonecrosis, and shapes the rest of that child's life.
So the examination stays and the scan becomes selective. The clinical hip examination is never optional in any infant with metatarsus adductus: Ortolani, Barlow, abduction range, leg lengths, thigh creases, and continued surveillance at every well-child check. What becomes defensible is selective rather than universal ultrasound in isolated flexible metatarsus adductus with a normal examination and no other risk factor. Calcaneovalgus and clubfoot are the deformities that genuinely warrant a lower imaging threshold, and it is worth being able to say which is which.
Differential Diagnosis
The cardinal exam discriminator is the hindfoot. Examine it first.
- Hindfoot
- Neutral or slight valgus
- Forefoot
- Adducted, lateral border convex
- Key Distinguishing Feature
- Flexible in most; isolated forefoot problem; no equinus
- Hindfoot
- Fixed VALGUS
- Forefoot
- Rigid adduction + lateral midfoot translation
- Key Distinguishing Feature
- S-shaped foot; talocalcaneal angle increased; can be iatrogenic from casting
- Hindfoot
- VARUS + equinus
- Forefoot
- Adducted + cavus
- Key Distinguishing Feature
- Rigid; calcaneus high and inverted; emptyheel; talocalcaneal angle parallel
- Hindfoot
- Normal
- Forefoot
- Normal foot shape
- Key Distinguishing Feature
- Intoeing from rotation, not foot deformity; thigh-foot angle internal
- Hindfoot
- Normal
- Forefoot
- Normal foot shape
- Key Distinguishing Feature
- Squinting patellae; intoeing in older toddler; W-sitting
- Hindfoot
- Normal
- Forefoot
- Isolated great-toe medial deviation
- Key Distinguishing Feature
- Only the hallux deviates; rest of forefoot normal
Management Algorithm
Who. Infants under 6 months with Type I/II flexibility.
Observation is the mainstay of treatment. Explain to the parents that over 90% resolve spontaneously; what it needs is reassurance and patience.
Stretching. The abduction stretch: a parent stabilises the heel with one hand and gently pushes the forefoot into abduction with the other, holding for 5-10 seconds and repeating five times at each nappy change. There is limited evidence that it changes the natural history, but it empowers parents ("active waiting").
Follow-up. Review in 3-4 months to ensure resolution, and escalate if the foot is becoming rigid.
The counselling matters as much as the treatment. This is the commonest paediatric foot referral and most of it needs nothing. A confident explanation prevents years of unnecessary shoe modifications and clinic visits.
Surgical Technique
Find the apex first. Surgical planning must locate the actual apex of the deformity. Metatarsal, cuneiform and cuboid osteotomies solve different patterns and should not be bundled automatically.
Principle. Multiple metatarsal osteotomies (Berman-Gartland) realign the forefoot by cutting the metatarsal bases. The specific hazard in a child is the physis: the first metatarsal grows from its proximal physis and the lesser metatarsals from their distal physes. Operating in a child over 5 avoids damaging the proximal physis of the first metatarsal, and the osteotomies and fixation must be planned to avoid crossing the physes, or the correction is bought at the cost of a growth arrest and a shortened ray.
Set-up. Supine, under tourniquet control, with fluoroscopy available, though the procedure is often done clinically.
Approach. Two or three dorsal longitudinal incisions, one between the first and second rays and one between the third and fourth. Protect the branches of the superficial peroneal nerve and the extensor tendons.
The osteotomies.
- First metatarsal: at the proximal metaphysis, often as a medial opening wedge to add length and correct adduction; a small bone-graft wedge (bank or local) can be inserted
- Second, third and fourth metatarsals: closing wedges at the bases, with the wedge base lateral, so that closing them swings the metatarsals laterally
- Fifth metatarsal: an oblique osteotomy
Fixation and closure. Smooth K-wires (1.6mm or similar), either retrograde from the metatarsal head into the tarsus or crossed at the osteotomy site. Plate fixation is difficult in bones this small but possible in older children. Close in layers and apply a well-moulded short-leg cast.
Complications
- Risk factors
- Forced abduction of the forefoot against a valgus hindfoot during casting
- Prevention and management
- Prevention: proper casting technique, stabilising the hindfoot in neutral or varus while abducting the forefoot; do not simply "crank" the foot laterally. Management: surgical correction (calcaneal osteotomy) if rigid.
- Risk factors
- Poor cast moulding, inadequate padding, a tight cast
- Prevention and management
- Prevention: careful padding of the bony prominences (base of the fifth metatarsal, heel) and frequent cast checks. Management: remove the cast, wound care, bivalve the next cast.
- Risk factors
- Surgical damage to the proximal physis of the first metatarsal
- Prevention and management
- Prevention: perform osteotomies in older children (over 5 years) and identify the physis on fluoroscopy. Management: epiphysiodesis if the discrepancy is significant.
- Risk factors
- Inadequate duration of treatment, failure to use maintenance shoes
- Prevention and management
- Prevention: ensure overcorrection (past neutral) before stopping casting, and use reverse-last shoes. Management: recasting or osteotomies.
- Risk factors
- Imbalance of tibialis anterior or FHL; a complication of TMT resection
- Prevention and management
- Prevention: avoid extensive TMT releases (Heyman-Herndon) and use osteotomies instead. Management: tibialis anterior transfer or osteotomy.
- Risk factors
- Intrusion into the TMT joints during surgery
- Prevention and management
- Prevention: extra-articular osteotomies are preferred over capsulotomies. Management: physiotherapy, analgesia.
- Risk factors
- Altered forefoot mechanics after osteotomy
- Prevention and management
- Prevention: anatomical realignment. Management: orthotics, offloading pads.
Postoperative Care
0-2 weeks. A non-weight-bearing short-leg cast or backslab is applied in theatre. Strict elevation for the first 48 hours minimises oedema and pain, and routine checks of toe perfusion, sensation and movement guard against compartment syndrome, though it is rare in the foot.
2-6 weeks. At 2 weeks the initial cast or splint is removed to inspect the incisions, and non-absorbable sutures come out. A definitive fibreglass short-leg cast holds the corrected position, and the child stays non-weight-bearing for 6 weeks so the osteotomies unite without displacement.
6 weeks: union. If percutaneous K-wires were used, they are removed in clinic, or under sedation if buried. Radiographs check for callus and union, and the child moves to a weight-bearing walking cast or a stiff-soled shoe (for example a Darco shoe) for a further 2-4 weeks if needed, depending on radiographic consolidation.
From 3 months. Return to normal footwear, with broad toe-box shoes recommended, and a gradual return to running and sport. Review annually until skeletal maturity to monitor for recurrence or growth disturbance.
Outcomes and Prognosis
Natural history. Excellent. In the Iowa long-term cohort (Farsetti, Weinstein and Ponseti, mean follow-up 32.5 years), every passively correctable foot resolved spontaneously and 90% of conservatively treated rigid feet had good results, with no poor results. Mild residual adduction is often compatible with normal function and shoe wear.
Non-operative treatment. Serial casting and graded orthosis pathways achieve a success rate greater than 90% for flexible and rigid deformities, best when started in the first year of life.
Operative treatment. Good cosmetic correction and generally good functional outcomes, but with a long-term risk of midfoot stiffness and metatarsalgia.
Guidelines, Registries & Global Practice
Global epidemiology:
- Most common congenital foot deformity; reported incidence roughly 1 in 1000 live births, with prospective newborn screening series finding higher prevalence (up to 5 in 1000, Rocca 2022) because mild flexible cases are otherwise underdiagnosed.
- Bilateral in 50-60%; more frequent in firstborns and with intrauterine crowding (oligohydramnios, multiple gestation, breech) — part of the "packaging" cluster with DDH and torticollis.
Side-by-side guidance (where bodies comment):
- Position on flexible MA
- Observation + reassurance; natural history excellent
- Position on rigid MA
- Serial casting; orthoses as adjunct
- Hip screening stance
- Examine hips routinely; image if exam abnormal or risk factors
- Position on flexible MA
- Reassurance, parent stretching as "active waiting"
- Position on rigid MA
- Casting/bracing in casting clinics (often physio-led)
- Hip screening stance
- Clinical hip exam mandatory; selective ultrasound
- Position on flexible MA
- Observe; avoid overtreatment
- Position on rigid MA
- Three-point molded casting, then maintenance shoes
- Hip screening stance
- Screen per national DDH program
- Position on flexible MA
- Conservative; early treatment favoured if intervening
- Position on rigid MA
- Graded manipulation then orthosis or cast
- Hip screening stance
- Hip surveillance integrated with national DDH screening
- Registry / cohort signal: Large population data (Norwegian birth cohort, Håberg 2020) reclassify MA as a low-magnitude DDH risk factor relative to other foot deformities — informing more proportionate hip-imaging policy.
High- vs limited-resource practice variation:
- High-resource: Newborn orthopaedic screening, casting clinics, adjustable braces (Bebax/Wheaton), and ultrasound hip surveillance are available; emphasis is on avoiding overtreatment of self-limiting flexible feet.
- Limited-resource: Diagnosis is clinical; mainstays are parental education, manipulation, and simple straight-last/reverse-last footwear. Serial plaster casting is low-cost and effective where braces are unavailable. Rare surgical cases may present late, increasing the role of osteotomy over early conservative care.
Always examine the hips. Missing a dislocated hip because you focused on the foot is a fail — even though the absolute DDH risk with isolated flexible metatarsus adductus is now known to be low.
Controversies & Areas of Uncertainty
- Magnitude of the DDH association: The classic teaching of a 10-15% DDH rate derives from small, selected, often historical series. The 60,844-child Norwegian cohort (Håberg 2020) found metatarsus adductus carried only a marginal 1.5% DDH risk, far lower than calcaneovalgus or clubfoot. Whether every infant with isolated flexible MA needs hip ultrasound (versus careful clinical hip exam and selective imaging) is therefore debated — but the hip exam itself is never optional.
- Does stretching change natural history? Parental passive stretching is widely taught for flexible feet, yet high-quality evidence that it alters the (already excellent) natural history is lacking. It is best framed as low-cost "active waiting" and reassurance, not a disease-modifying treatment.
- Casting vs dynamic orthoses for rigid feet: Serial casting is the traditional gold standard, but braces (Bebax, Wheaton) and graded manipulation pathways report comparable correction with fewer skin issues (Rocca 2022). Optimal modality is not settled; early initiation is the consistent predictor of success across studies.
- Surgery threshold and technique: Surgery is rare and reserved for the symptomatic older child. Soft-tissue (Heyman-Herndon) releases have fallen out of favour due to stiffness and dorsal bunion; metatarsal/cuneiform osteotomies are preferred but carry physeal and metatarsalgia risks. Optimal age and bony procedure remain individualised.
- Hallux valgus link: Long quoted as an adult sequela, but the Iowa long-term data found hallux valgus was NOT common, undermining a routine "this will become a bunion" counselling line.
MCQ Practice Points
Q: What is the radiographic reference line for Metatarsus Adductus severity? A: Heel Bisector Line. Normal = 2nd toe. Mild = 3rd toe. Moderate = 3rd/4th webspace. Severe = 4th/5th toe.
Q: When should casting be initiated for rigid Metatarsus Adductus? A: Ideally before 8 months of age. After 1 year, casting is less effective due to bone ossification.
Q: How do you differentiate MA from Skewfoot? A: In MA, the hindfoot is neutral/valgus. In Skewfoot (Serpentine Foot), the hindfoot is in severe valgus AND the forefoot is adducted (Z-deformity).
Q: What is the most common differential diagnosis for Metatarsus Adductus? A: Clubfoot (Talipes Equinovarus). Metatarsus Adductus has a neutral or valgus hindfoot.
Q: A Heel Bisector Line passing through the 4th/5th toe webspace indicates what severity? A: Severe. Normal is 2nd toe. Mild is 3rd toe. Moderate is 3rd/4th webspace.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Parents bring six-week-old infant with intoeing. They are worried about clubfoot. How do you assess?”
“8-month-old with rigid Metatarsus Adductus. Heel bisector through 4th toe. Stretches failed. Plan?”
“6-year-old with painful rigid metatarsus adductus. Failing shoe wear. Parents request surgery. Discuss.”
Key Features
- Kidney Bean Foot
- Medial Crease
- Lateral Border Convex
- Normal Hindfoot (Neutral)
Classification
- Flexible (Corrects past midline)
- Partly Flexible (To midline)
- Rigid (Fixed Adduction)
- Resistant (Severe)
X-ray Findings
- Metatarsus Adductus Angle greater than 20
- Heel Bisector Line (Bleck)
- Lateral to 2nd toe space
- Normal Hindfoot Valgus
Management
- Observation (Flexible)
- Strethcing (Careful)
- Serial Casting (Rigid)
- Operation (Rare, greater than 4yrs)
Associated Conditions
- DDH (about 1.5%, not 10-15%)
- Torticollis
- Plagiocephaly
- Packaging Disorders
Evidence Base
Farsetti, Weinstein, Ponseti - Long-Term Natural History
- 31 patients (45 feet) followed a mean of 32.5 years (Iowa cohort)
- All 16 passively correctable (untreated) feet had good results; 26/29 (90%) conservatively treated feet were good, with no poor results
- Hallux valgus was NOT a common late outcome; residual medial cuneiform-metatarsal obliquity was frequent but asymptomatic
Rocca et al - Conservative Treatment Algorithm
- 2,156 newborns screened; 124 diagnosed with congenital metatarsus varus (prevalence 5/1000), graded by Bleck classification
- 122 flexible/semi-flexible feet treated with manipulation (52 corrected) then Bebax-type braces (70); only 2 feet were non-flexible at birth, of which just 1 required plaster casting
- Only 2 superficial skin ulcerations, all healed within a week
Camin et al - Randomised Orthosis Comparison
- 25 children (41 feet) randomised to static vs dynamic anti-varus orthosis, scored on the Bleck scale
- Both orthosis types were effective; the best results were achieved with EARLY treatment
- No child had residual deformity interfering with daily activities at minimum 2-year follow-up (IOWA score)