Forearm Ring Concept | Bado Classification | Fracture of Necessity | Fix the Bone, Reduce the Joint
- Forearm ring concept: PRUJ + IOM + DRUJ - if one bone fractured with displacement, disruption must occur elsewhere
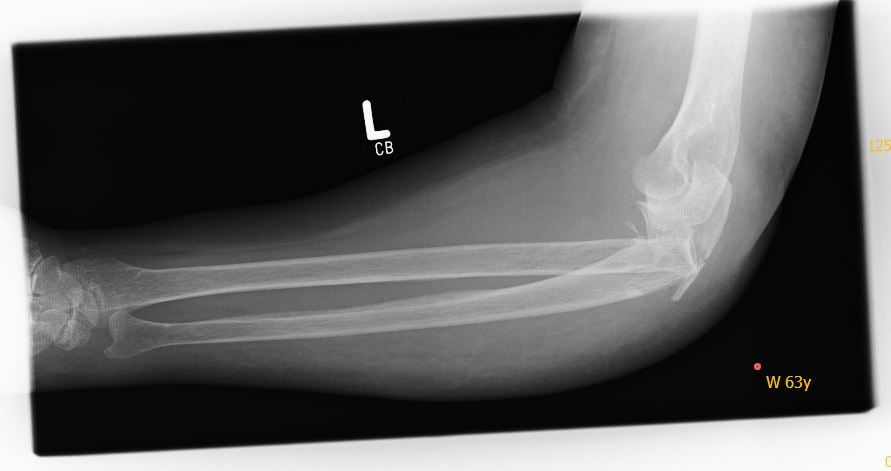
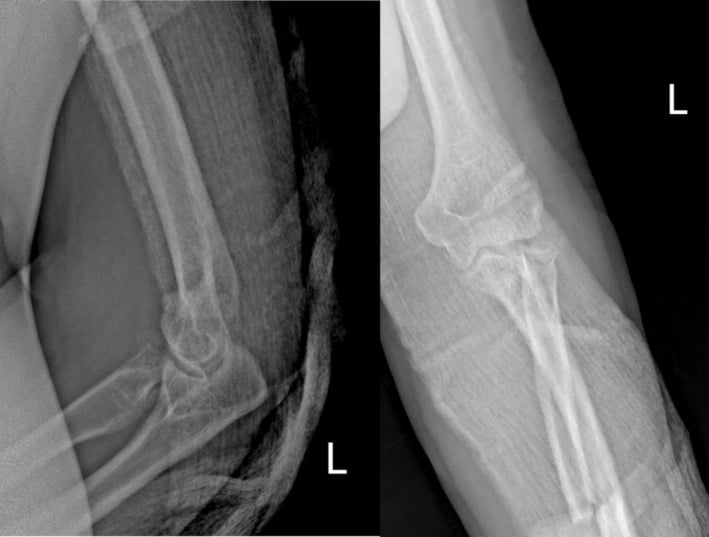
- Monteggia = proximal Ulna fracture + radial head dislocation (M = Misses radial head at elbow)
- Galeazzi = distal Radius fracture + DRUJ disruption (G = Got the wrist DRUJ) - 'fracture of necessity'
- Radiocapitellar line: Draw along radial neck/shaft axis - must pass through capitellum on ALL views
- Key principle: Fix the fractured bone anatomically and the joint usually reduces spontaneously
- “Bado classification for Monteggia: Type I anterior (most common overall), Type II posterior (commonest in adults; radial head and coronoid fractures), Type III lateral (the PIN palsy type), Type IV both bones
- “'Any isolated ulna fracture is a Monteggia until proven otherwise' - always image the elbow
- “Galeazzi DRUJ assessment: After ORIF radius, stress test in neutral/pronation/supination - supination is most stable
- “Missed Monteggia = major medico-legal issue - chronic radial head dislocation has poor reconstruction outcomes
Monteggia and Galeazzi Fractures
Overview and Epidemiology
Monteggia and Galeazzi fractures are the two classic forearm fracture-dislocations, and both test the ring concept: because the radius and ulna are bound at both ends and along the shaft, a displaced fracture of one bone mandates a corresponding joint or bony disruption elsewhere. Missing the associated joint injury is the central pitfall in both. Across all settings the governing principle is identical: fix the fractured bone anatomically and the joint usually reduces.
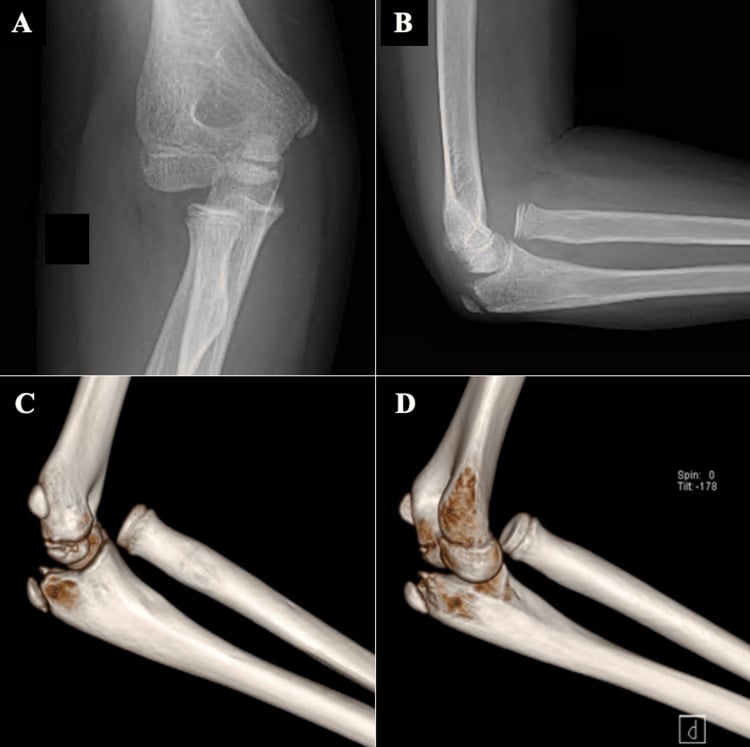
Monteggia. A fracture of the proximal ulna with dislocation of the radial head, classified by Bado into types I to IV. Type I (anterior) is the most common overall and the dominant paediatric pattern; Type II (posterior) is the commonest pattern in adults (Ring, JBJS Am 1998). Monteggia lesions account for roughly 1-2% of forearm fractures, with a bimodal distribution: a paediatric peak after a fall on the outstretched hand and an adult peak after higher-energy trauma, often Bado II.
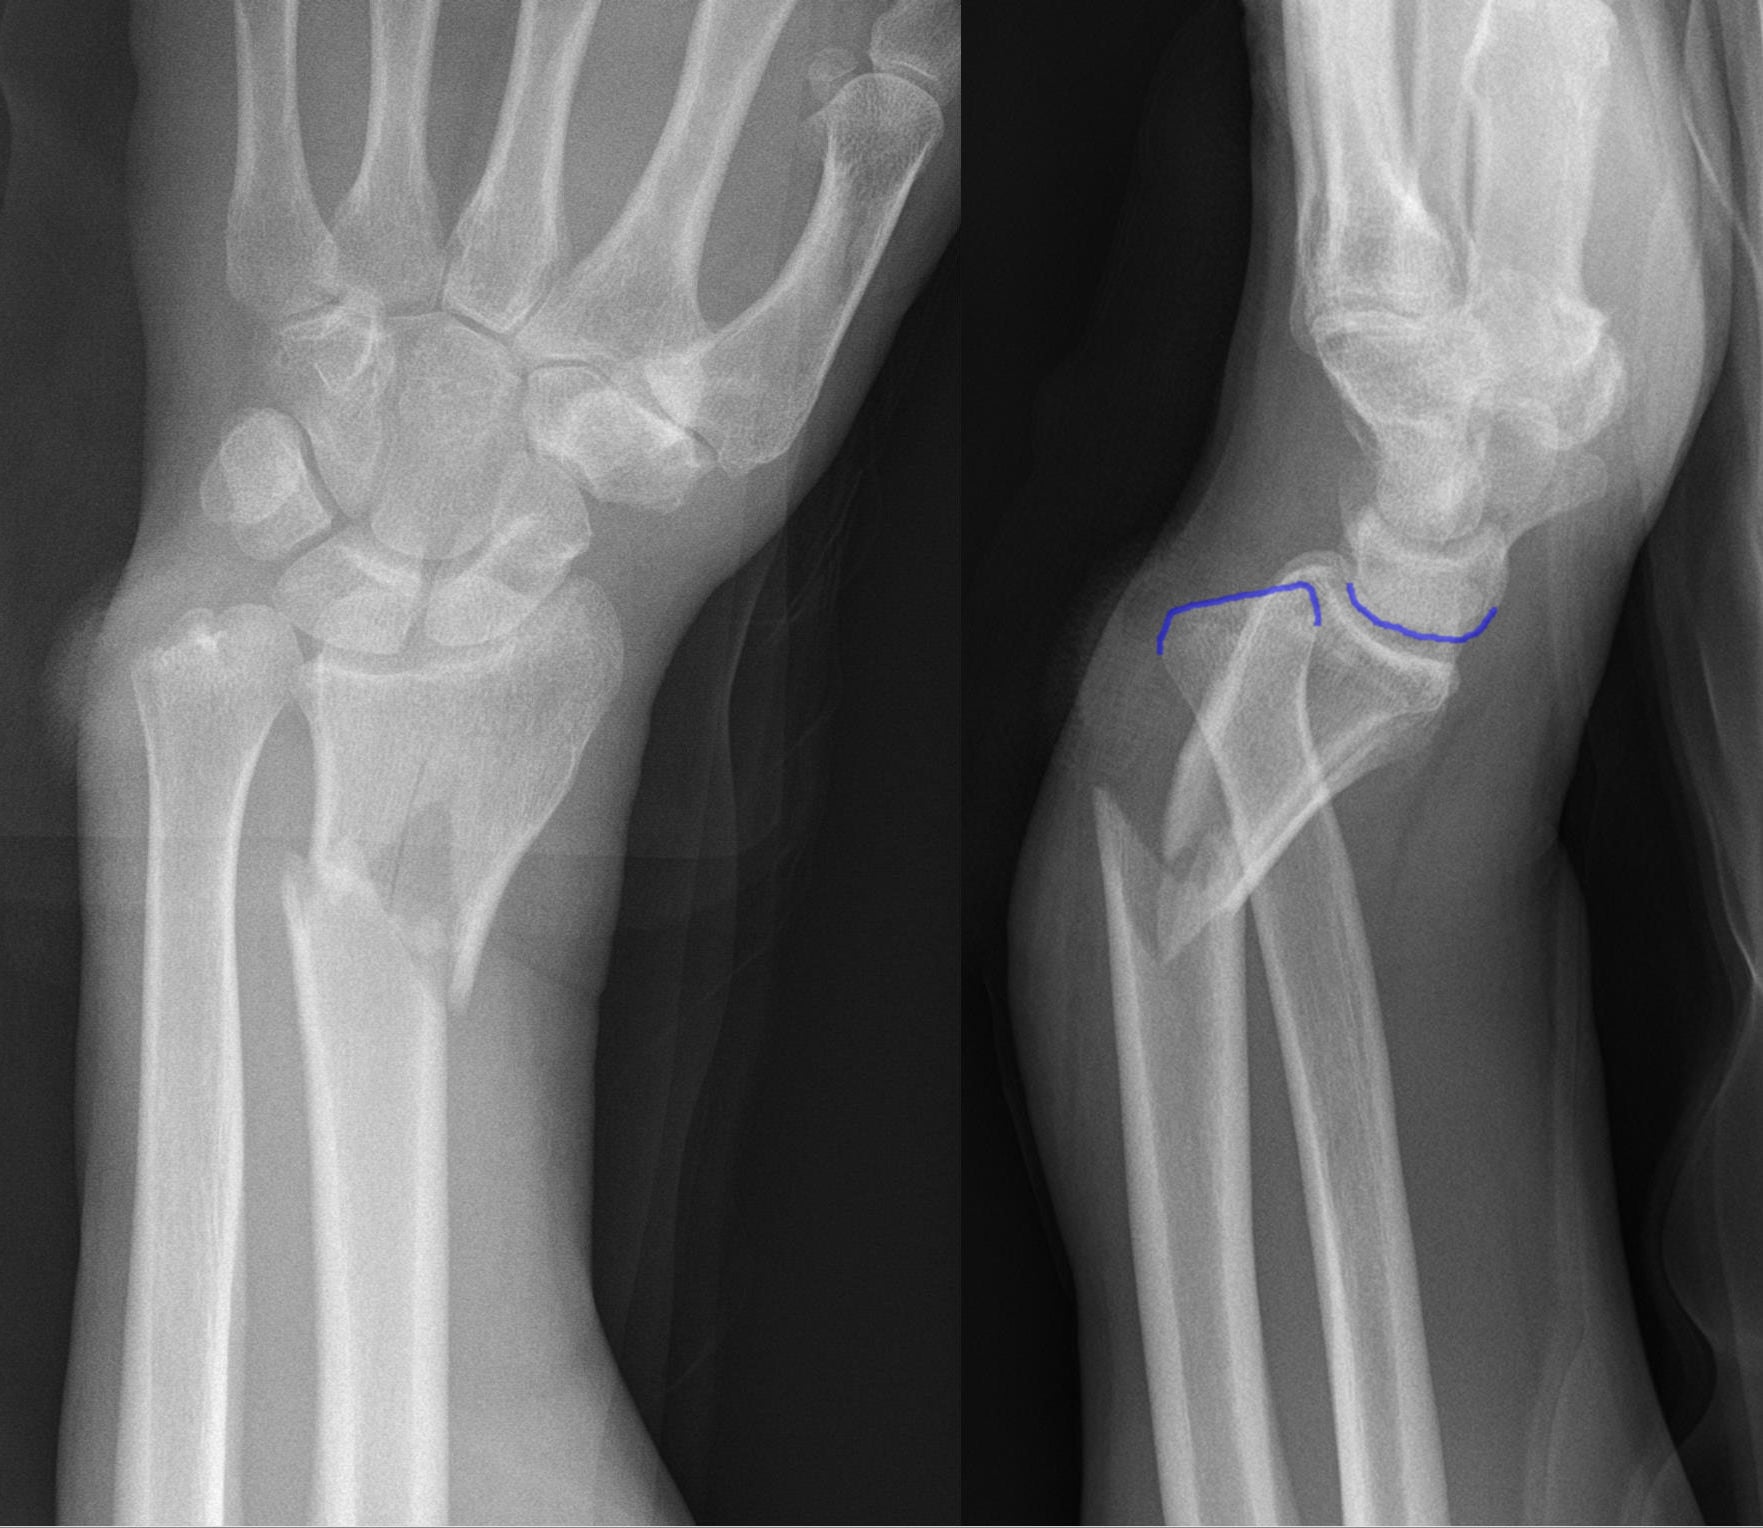
Galeazzi. A fracture of the distal third of the radius with disruption of the DRUJ. It is the "fracture of necessity": conservative treatment fails in about 80% of adults (Mikic, JBJS Am 1975), so adults require ORIF. Galeazzi fracture-dislocations comprise about 3-7% of forearm fractures, predominantly in adults aged 30-50, and are frequently work- or sport-related.
Anatomy and Biomechanics
The forearm ring. The forearm functions as a closed ring whose three links must all be intact for normal rotation. If one bone fractures and displaces, the ring must fail elsewhere, either in the other bone or at a joint, and any distal radius fracture therefore demands assessment of the DRUJ.
- Proximal radioulnar joint (PRUJ) - the radial head in the radial notch of the ulna, stabilised by the annular ligament. Disrupted in Monteggia.
- Interosseous membrane (IOM) - its central band transmits about 70% of axial load from the radius to the ulna. The key longitudinal stabiliser, lost in the Essex-Lopresti lesion.
- Distal radioulnar joint (DRUJ) - the ulnar head in the sigmoid notch of the radius. Disrupted in Galeazzi.
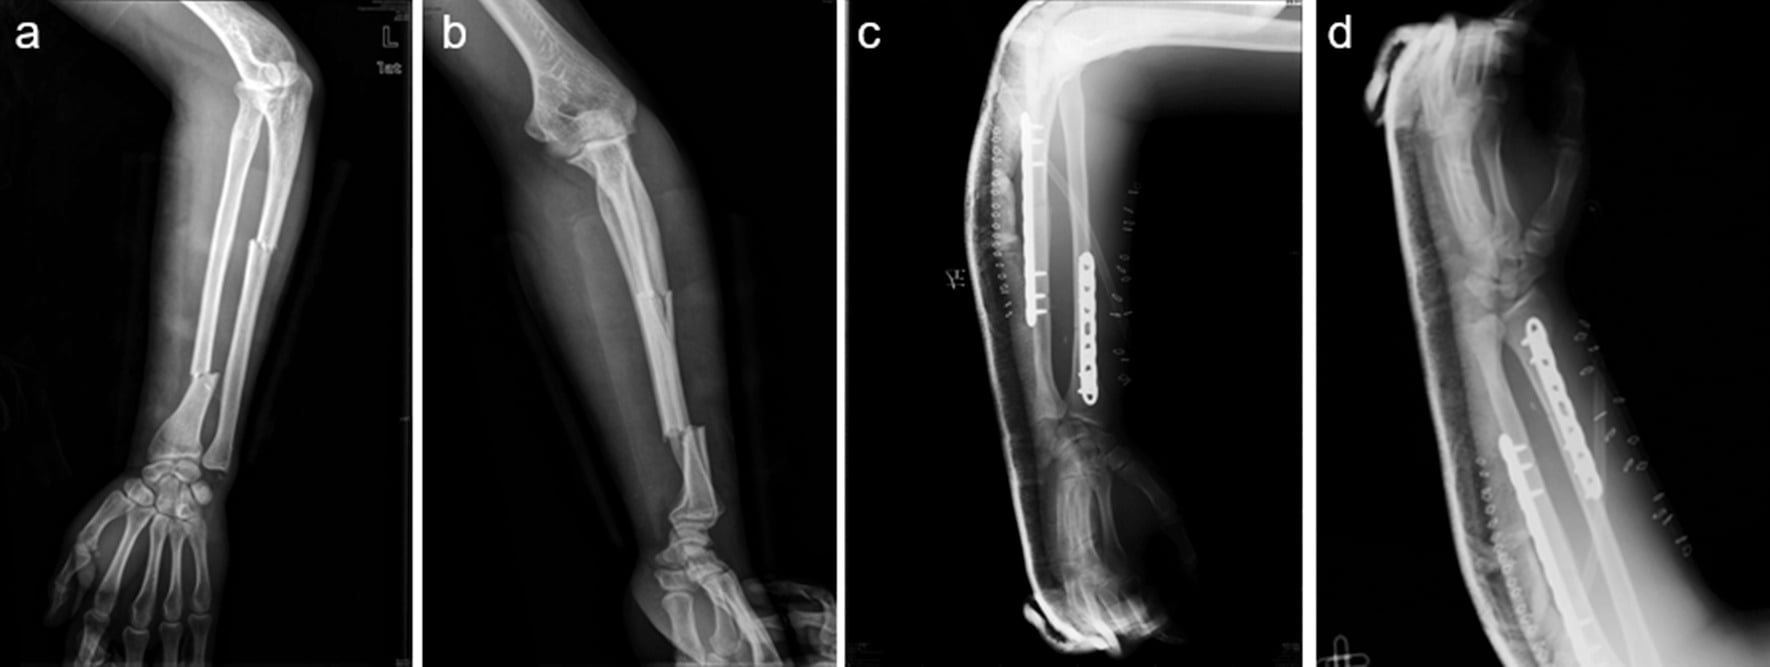
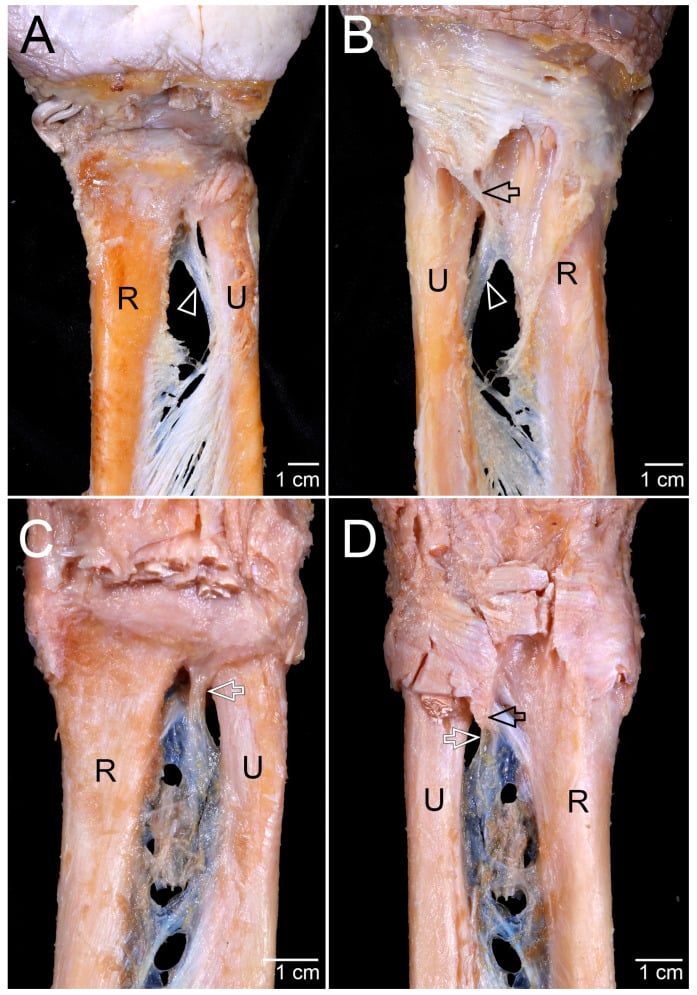
The DRUJ stabilisers. The TFCC is the primary stabiliser, through its dorsal and palmar radioulnar ligaments; the interosseous membrane, pronator quadratus and the ECU subsheath add to it. The distal interosseous membrane may contain a discrete distal oblique bundle running from ulna to radius near the DRUJ, and together with the TFCC it resists longitudinal separation and abnormal translation after a radial-shaft injury. Restoring radial length, bow and rotation retensions this linkage, and persistent malalignment leaves the DRUJ incongruent.
Rotation and DRUJ stability. The DRUJ is most stable in supination, when the palmar radioulnar ligament and the DRUJ capsule are tight. It is moderately stable in neutral and least stable in pronation. Supination is the position of immobilisation for an unstable Galeazzi DRUJ.
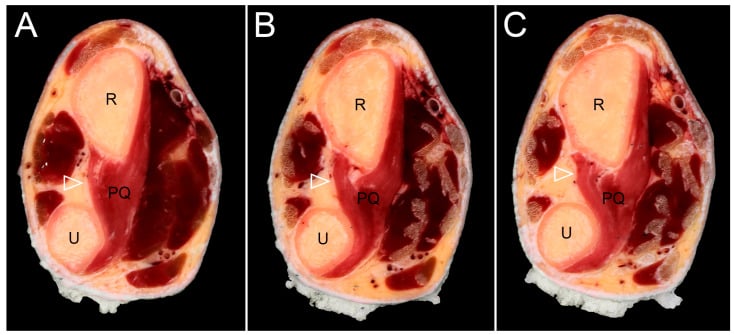
If the IOM is disrupted (the Essex-Lopresti lesion: radial head fracture, IOM rupture and DRUJ disruption), excising the radial head causes proximal radial migration and ulnocarpal impaction. Treat it with radial head replacement, never excision, and protect or reconstruct the IOM.
Mechanism of Injury
Monteggia. Three mechanisms are described:
- A fall on the outstretched hand with forced hyperpronation, classically producing Type I (anterior)
- A direct blow to the posterior proximal forearm
- Axial load through a supinated forearm, associated with Type II in adults
Galeazzi. Three mechanisms are described here too:
- A fall on the outstretched hand with the forearm pronated
- A direct dorsoradial blow to the wrist
- Axial load with rotation
Classification Systems
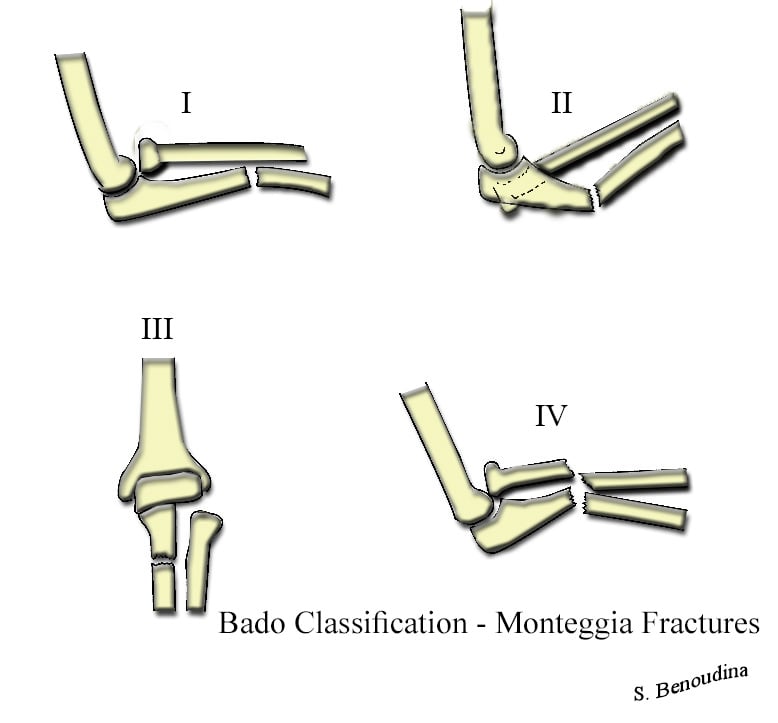
Bado. Monteggia lesions are classified by the direction of radial head dislocation and the pattern of the associated ulna fracture.
- Radial head
- Anterior
- Ulna fracture
- Anterior angulation
- Note
- Commonest overall / dominant paediatric pattern
- Radial head
- Posterior / posterolateral
- Ulna fracture
- Posterior angulation
- Note
- Commonest in adults; radial head + coronoid fractures
- Radial head
- Lateral / anterolateral
- Ulna fracture
- Metaphyseal
- Note
- Largely paediatric
- Radial head
- Anterior
- Ulna fracture
- Both radius and ulna, proximal third
- Note
- Rare
Type II in adults. The posterior pattern is frequently associated with radial head and coronoid fractures. In Ring's series 26 of 38 Type II injuries had a radial head fracture, and that combination, not the Bado number, is what predicted an unsatisfactory result.
Clinical Assessment
Monteggia. Pain, swelling and deformity of the proximal forearm and elbow, with a palpable, dislocated radial head and reduced elbow flexion-extension and forearm rotation. Always test PIN function, in every type and with the highest suspicion in Type III, and document it before and after surgery; the examination is described under nerve injuries below.
Galeazzi. Wrist pain and swelling with tenderness over the DRUJ and the ulnar fovea. The ulnar head is prominent, dorsally or palmarly depending on rotation, and forearm rotation is painful and restricted. Assess the median nerve and AIN, which lie in the volar surgical territory.
Investigations
Radiographs. Always image the entire forearm, including the joint above and the joint below; missing a joint injury is a major pitfall.
- AP and lateral of the entire forearm
- Dedicated elbow views (AP, lateral) - mandatory for any ulna fracture
- Dedicated wrist views (PA, lateral) - mandatory for any distal radius fracture
- Contralateral comparison views - invaluable for ulnar variance and DRUJ width
The rule. Any isolated ulna fracture is a Monteggia until proven otherwise. Obtain dedicated elbow views and check the radiocapitellar line on every one of them.
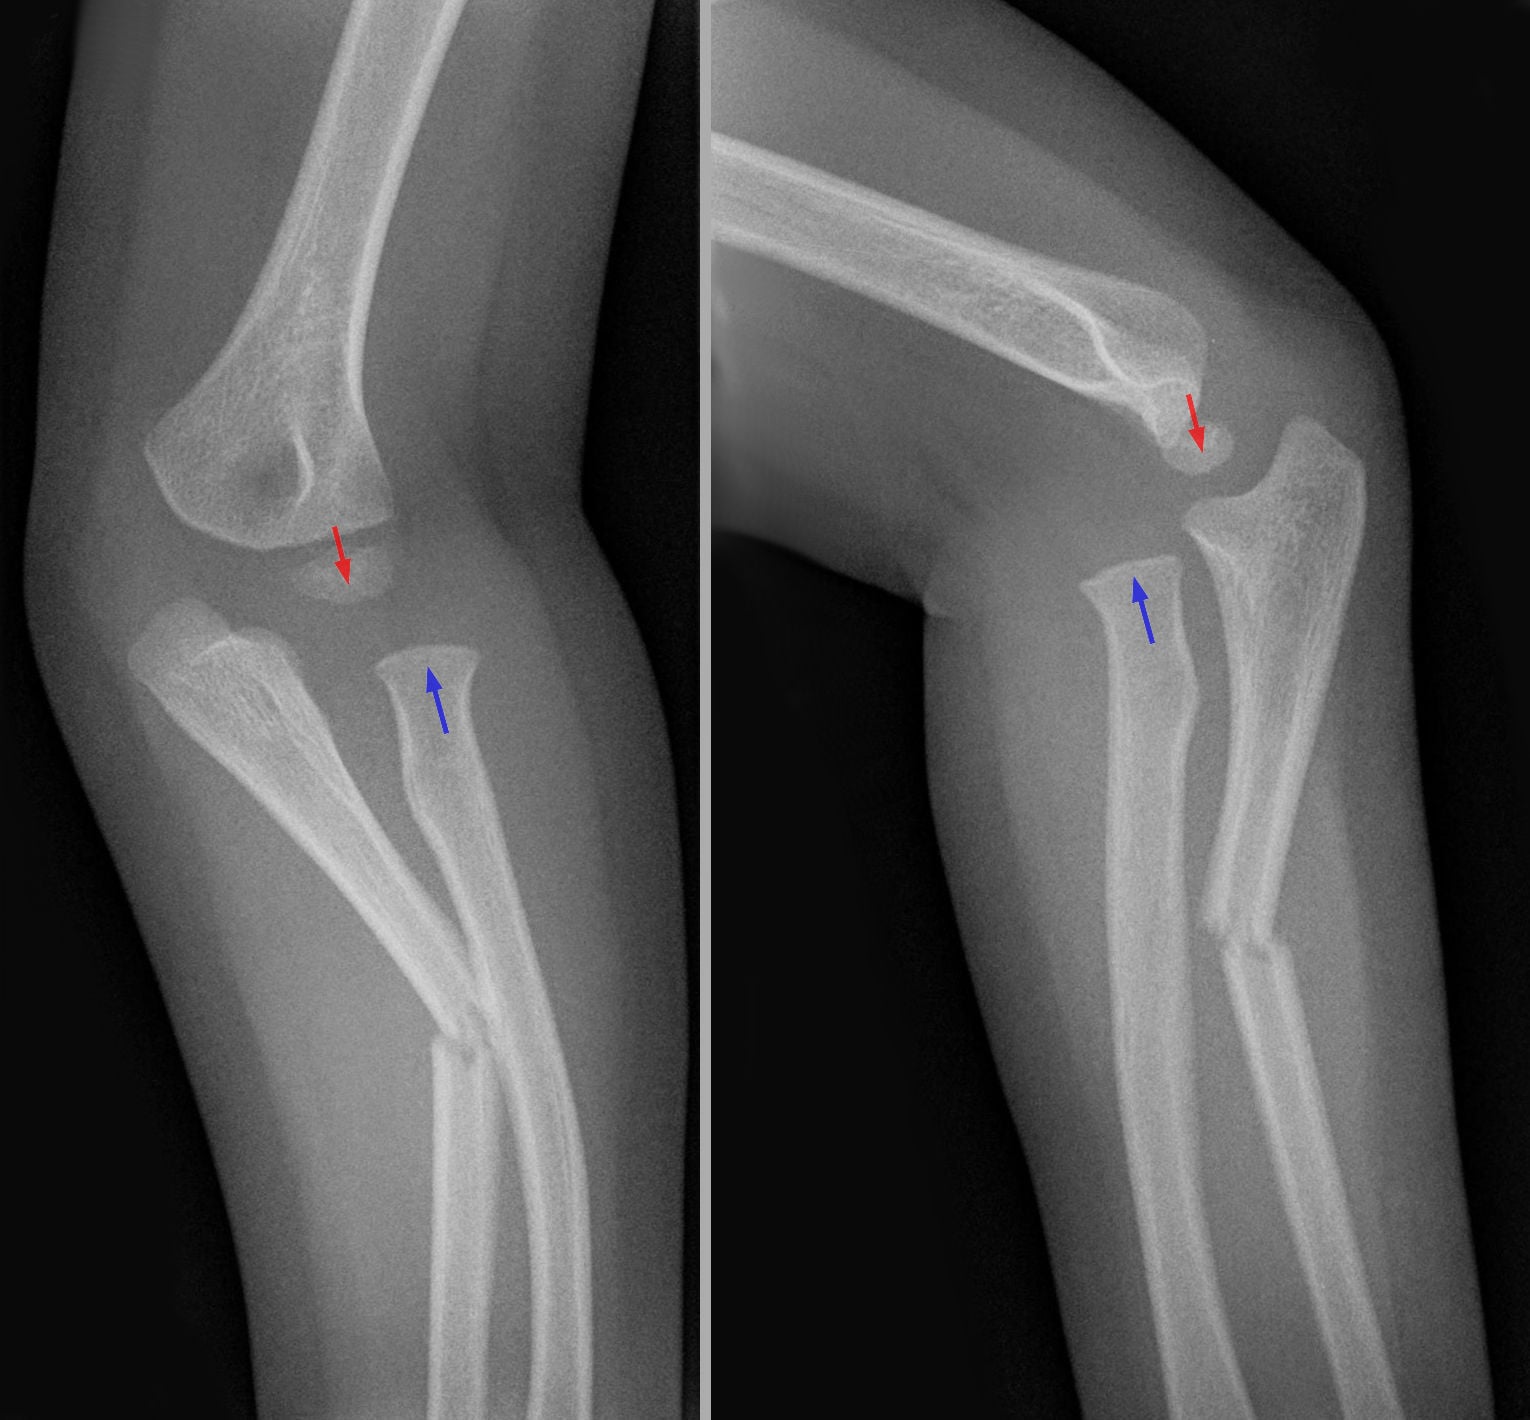
On every elbow view (AP, lateral, oblique), a line drawn along the axis of the radial neck/shaft must pass through the centre of the capitellum. If it misses, the radial head is dislocated. This single check is how missed Monteggia injuries are caught.
- Monteggia
- Proximal ulna, with angulation
- Galeazzi
- Distal third of radius (middle/distal third junction)
- Monteggia
- Radial head position
- Galeazzi
- DRUJ
- Monteggia
- Radiocapitellar line disrupted on at least one view
- Galeazzi
- DRUJ widening over 2mm vs contralateral; radial shortening / loss of radial height
- Monteggia
- Coronoid and radial head fractures in Bado II
- Galeazzi
- Ulnar styloid base fracture, suggesting foveal TFCC avulsion
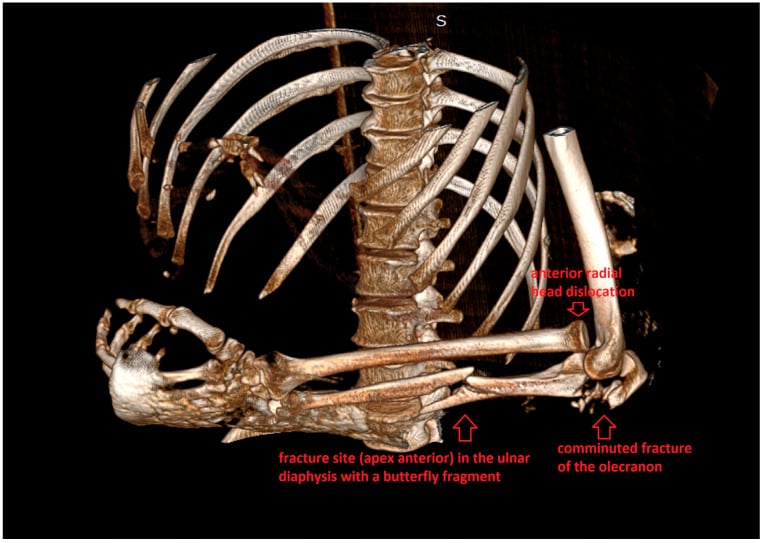
CT is for complex adult patterns and operative planning, not a substitute for complete initial radiographs. It is indicated for:
- Complex or comminuted proximal ulna or radial head fractures (Bado II planning)
- Articular involvement of the radial head or DRUJ
- Assessment of chronic malunion before reconstruction
Differential Diagnosis
The differential is about recognising the whole injury rather than the obvious fracture, and distinguishing the fracture-dislocations from their mimics.
- Fracture
- Proximal ulna
- Joint disruption
- Radial head (PRUJ)
- Distinguishing feature
- Radiocapitellar line disrupted on elbow views
- Fracture
- Distal radius
- Joint disruption
- DRUJ
- Distinguishing feature
- DRUJ widening, radial shortening, ulnar styloid base fracture
- Fracture
- Ulna shaft, minimally displaced
- Joint disruption
- None
- Distinguishing feature
- Radial head congruent on all views (must exclude Monteggia)
- Fracture
- Radial head
- Joint disruption
- DRUJ + IOM
- Distinguishing feature
- Longitudinal pain; IOM ruptured
- Fracture
- Radius + ulna shafts
- Joint disruption
- Usually none
- Distinguishing feature
- Two shaft fractures without a joint dislocation
- Fracture
- None
- Joint disruption
- Chronic radial head dislocation
- Distinguishing feature
- Bilateral, dome-shaped/hypoplastic capitellum, convex radial head, no trauma
Management Algorithm
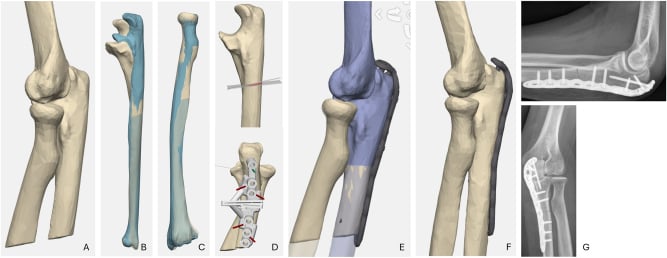
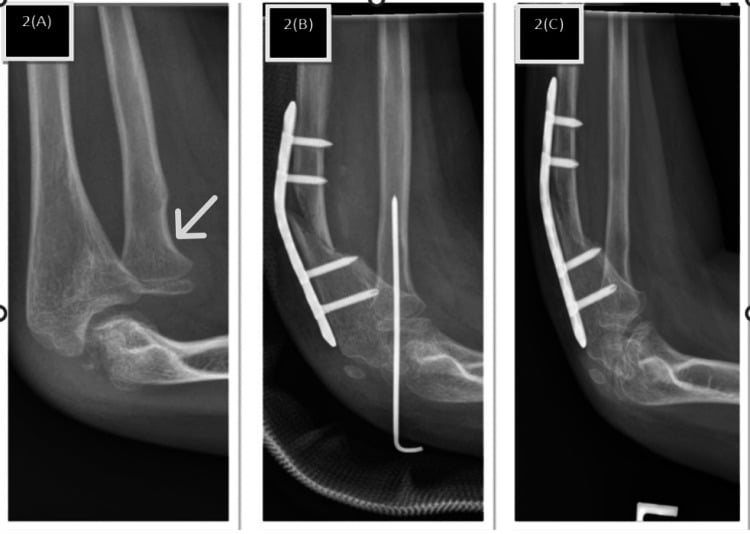
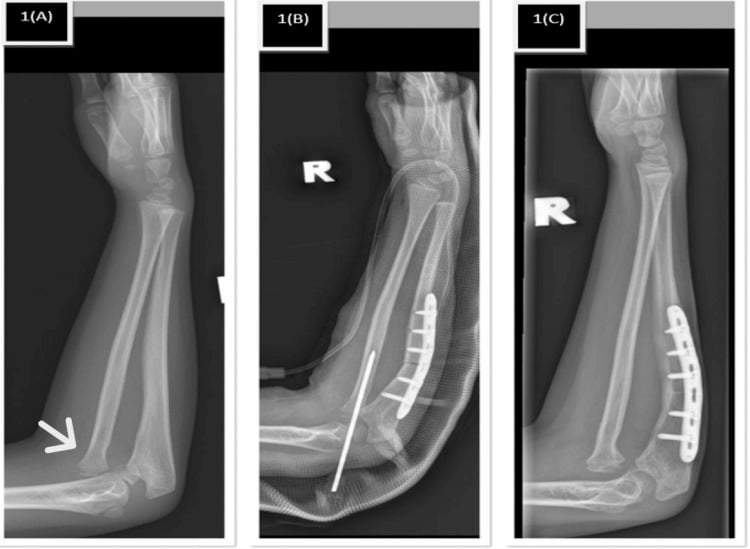
Monteggia in adults. Operative. ORIF of the ulna restores length, alignment and IOM tension, and anatomic reduction of the ulna is the single most important step. The radial head is then assessed, and in Bado II the associated radial head and coronoid fractures are addressed.
Monteggia in children. Closed reduction of the ulna often restores the radial head. Fix the ulna, with a flexible nail or a plate, if the reduction is unstable or the pattern is length-unstable.
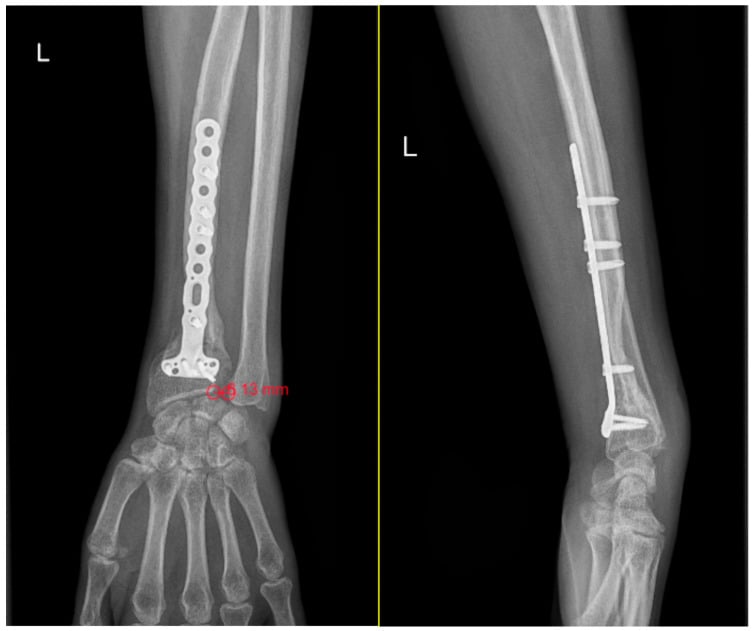
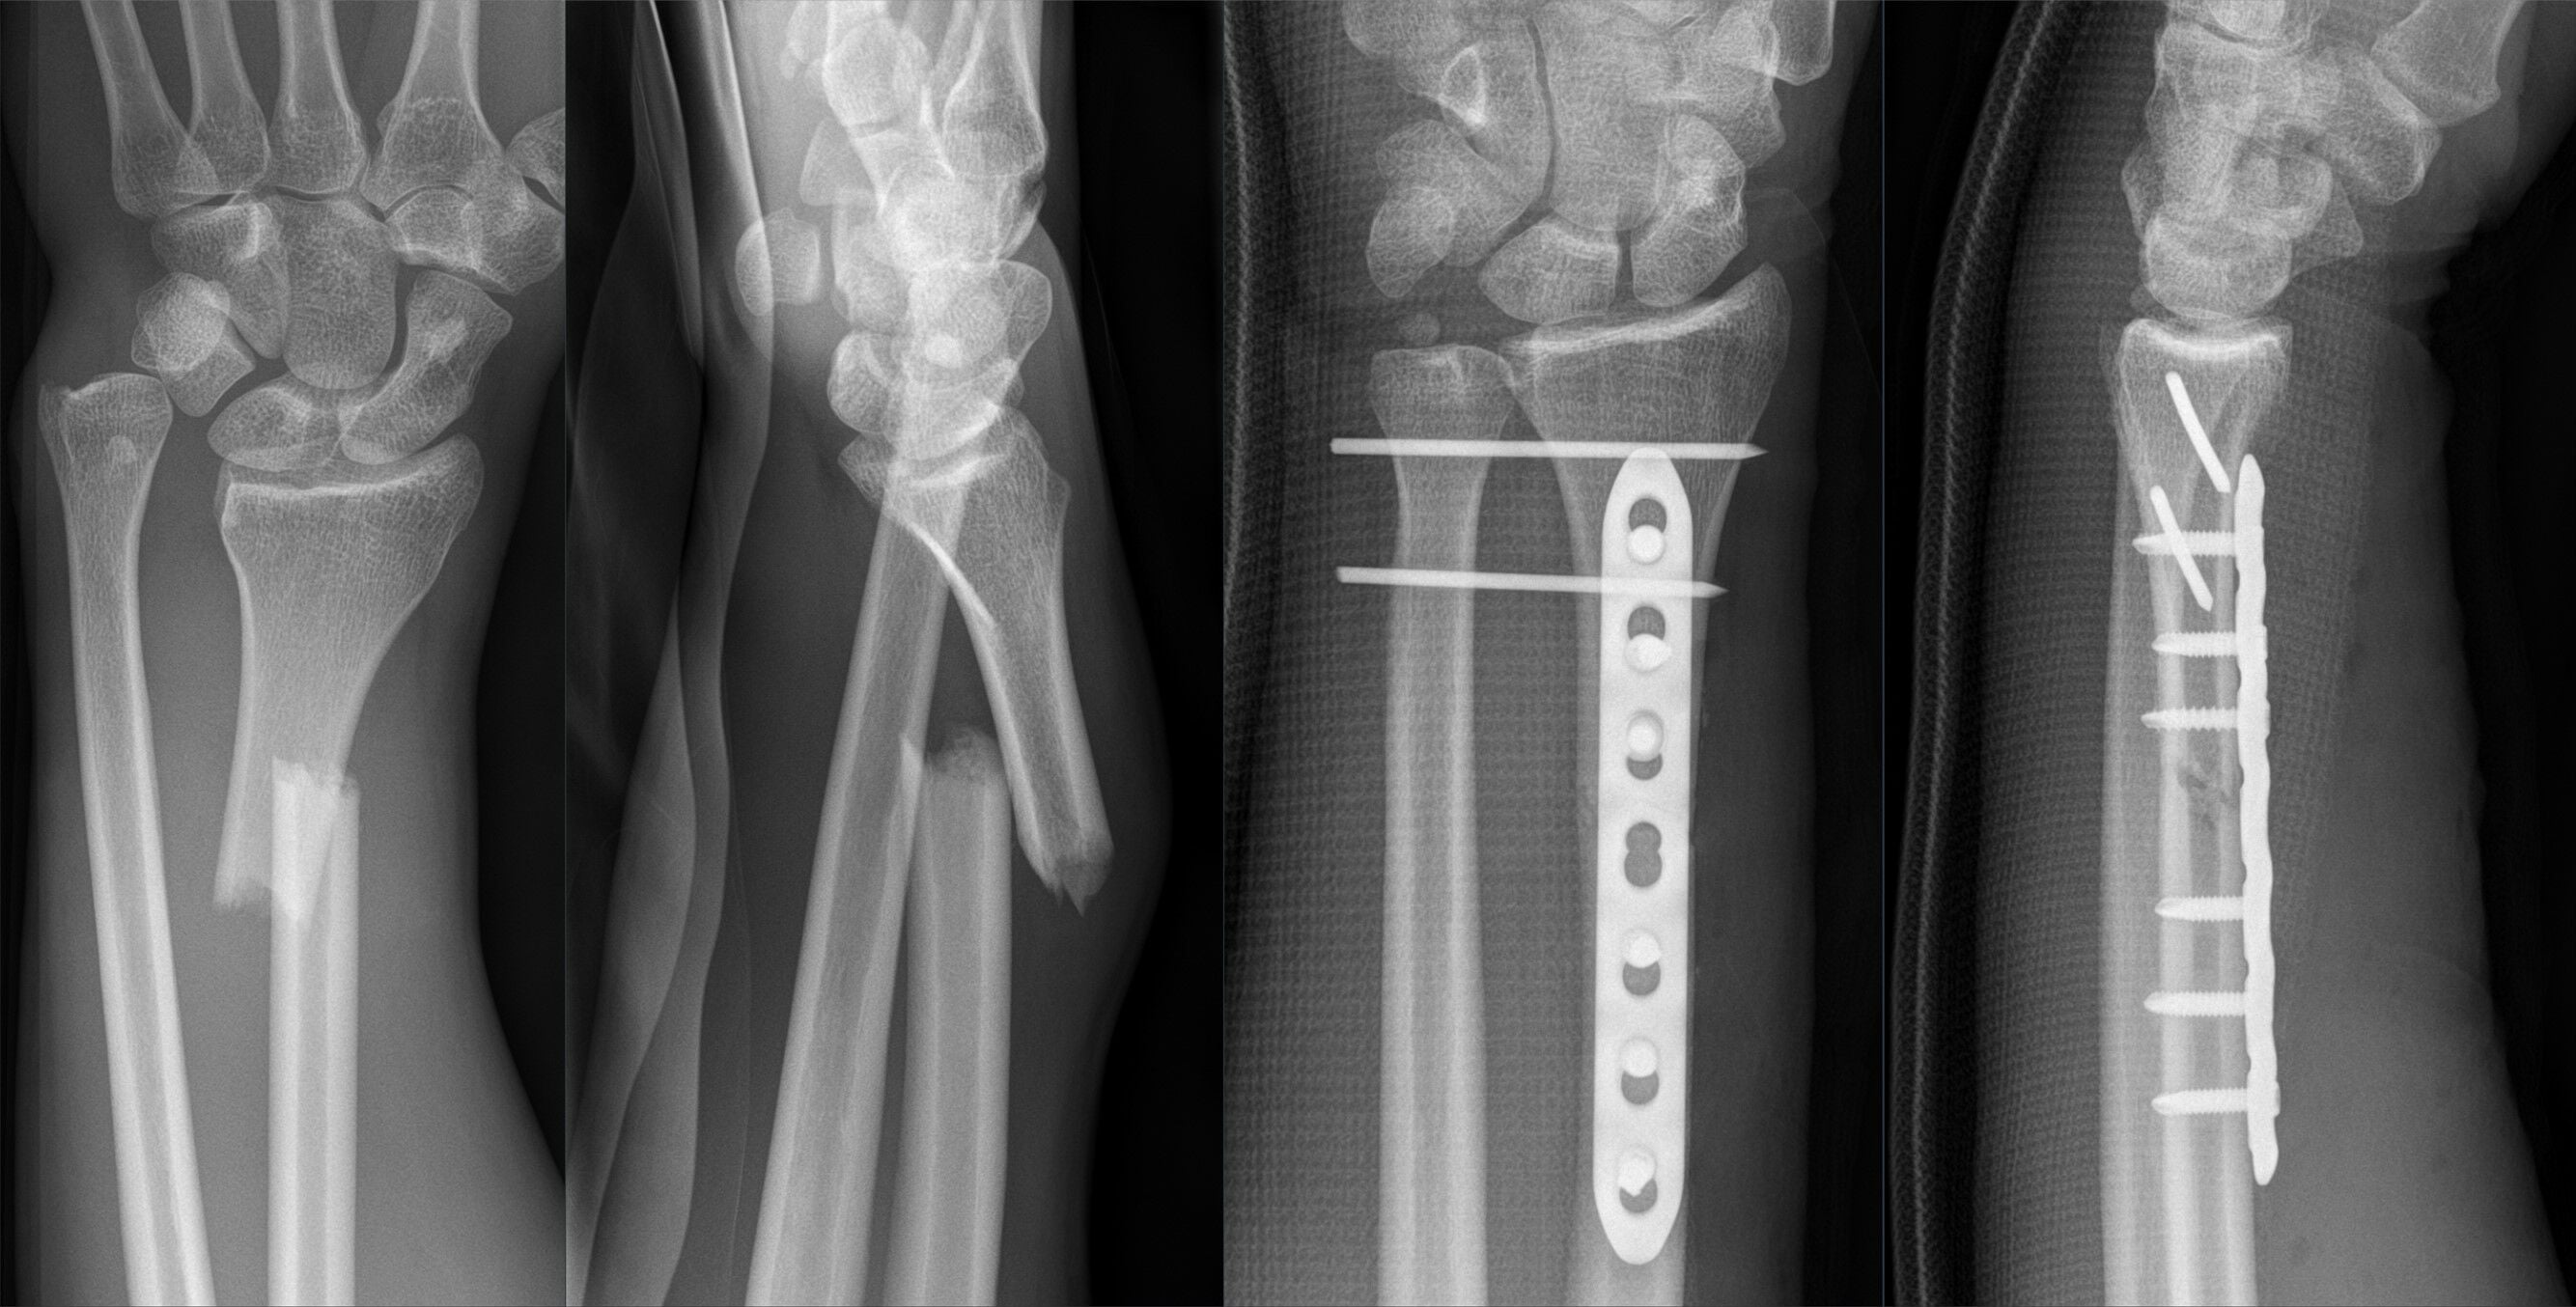
Galeazzi in adults. Almost always operative, because this is the fracture of necessity. The radius is fixed first, then the DRUJ is tested: a stable DRUJ needs no further treatment and moves early, and an unstable one is stabilised by one of the options under Surgical Technique.
Galeazzi in children. Closed reduction may be attempted, proceeding to ORIF of the radius if it is unstable.
FASGaleazzi Management
Hook:Be FASt to recognise and treat Galeazzi - Fix, Assess, Stabilise
Surgical Technique
Set-up and approach. Supine, with an arm table and a tourniquet. The proximal ulna is approached along its posterior subcutaneous border, adding the lateral Kocher interval (anconeus / ECU) if the radial head must be explored.
Ulna fixation. A 3.5mm DCP or LCP, with compression plating for simple patterns and bridge plating if comminuted. Restore length and correct angulation precisely: this is what reduces the radial head.
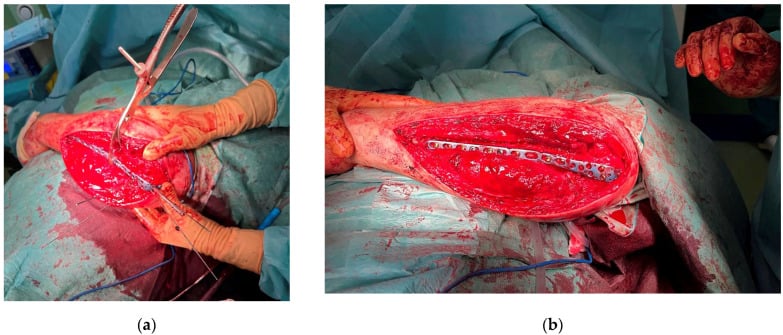
Radial head assessment. After fixing the ulna, take the elbow through full flexion-extension and pronation-supination. The reduction is concentric and stable in most cases, and needs no further action. If the head is unstable or irreducible, explore through the Kocher interval and address radial head and coronoid fractures in Bado II; the blocks to reduction, and their management, have their own section below.
Annular ligament reconstruction in the chronic Monteggia. A Bell-Tawse-type reconstruction uses triceps fascia or palmaris longus, looped around the radial neck and secured to the ulna. It is preceded by an ulnar osteotomy to correct the malunion.
Complications
Monteggia. Five complications need to be anticipated:
- Missed diagnosis - the most important and most preventable complication. Up to half are missed initially, leaving a chronic radial head dislocation that is difficult to reconstruct (see Controversies).
- Radial head instability - usually from inadequate ulnar reduction, occasionally from interposed annular ligament. Re-examine ulnar alignment first (see the irreducible joint, below).
- PIN palsy - classically Bado III; covered under nerve injuries below.
- Proximal radioulnar synostosis / heterotopic ossification - more frequent after high-energy Bado II and radial head fixation.
- Stiffness - mitigated by early mobilisation once fixation is stable.
Galeazzi. Four need to be anticipated:
- DRUJ instability - persistent if not recognised and addressed intraoperatively; may need delayed TFCC reconstruction.
- Malunion / radial shortening - causes ulnocarpal impaction and may require ulnar shortening osteotomy.
- Stiffness / loss of forearm rotation - early range of motion is critical once the construct, and the DRUJ, is stable.
- AIN / median nerve irritation - related to the volar approach and usually transient.
The chronic Monteggia. A missed radial head dislocation remodels the radiocapitellar joint and the ulna. Correcting ulnar alignment with an osteotomy can restore a stable radiocapitellar relationship, but a healed osteotomy does not guarantee joint stability.
Nerve Injuries in Forearm Fracture-Dislocations
Each injury carries a characteristic, and different, neurological risk. Document nerve function before and after any manipulation or surgery.
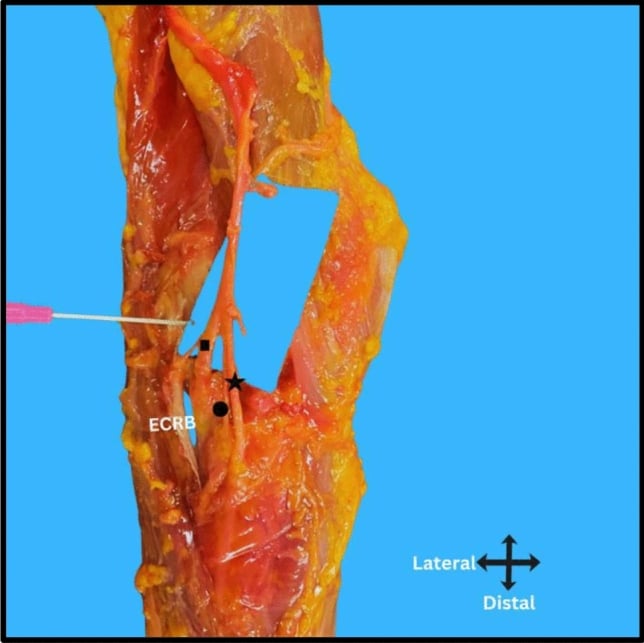
The PIN in Monteggia. The posterior interosseous nerve, the deep motor continuation of the radial nerve, winds around the radial neck and passes between the two heads of supinator, entering beneath its proximal fibrous edge, the arcade of Frohse. A displaced radial head therefore stretches or compresses it, and PIN palsy is the commonest nerve lesion in Monteggia. It is classically the Bado III association, because the lateral dislocation stretches the nerve round the radial neck, and it also occurs with anterior (Bado I) displacement, especially in children.
Examining the PIN. The deficit is purely motor, with no sensory loss. Test extension of the fingers and thumb at the MCP joints, and wrist extension: the wrist still extends but drifts into radial deviation, because ECRL (innervated proximal to the PIN) is spared while ECU is denervated.
Natural history. Most are a neurapraxia that recovers spontaneously once the radial head is reduced, typically over roughly 8 to 12 weeks. Observe after anatomic reduction, obtain nerve conduction studies if there is no recovery by about three months, and consider exploration then. Explore earlier if the nerve is suspected to be entrapped at open reduction. A radial head that will not reduce also raises the suspicion of entrapment, and is a reason to explore.
A patient who can extend the wrist but only into radial deviation, with preserved sensation, has a PIN palsy rather than a complete radial nerve injury. After a Monteggia reduction this is almost always a recovering neurapraxia - reduce the radial head, document the deficit, and observe rather than rush to explore.
The AIN and median nerve in Galeazzi. The anterior interosseous nerve, a motor branch of the median nerve, and the median nerve itself lie in the volar (Henry) territory used for radial fixation. A deficit is therefore usually an iatrogenic retraction neurapraxia rather than a primary injury, and recovery is the rule. Test the AIN with the "OK" sign (FPL and index FDP: flexion of the thumb IP and index DIP joints), and check median sensation over the volar radial three-and-a-half digits.
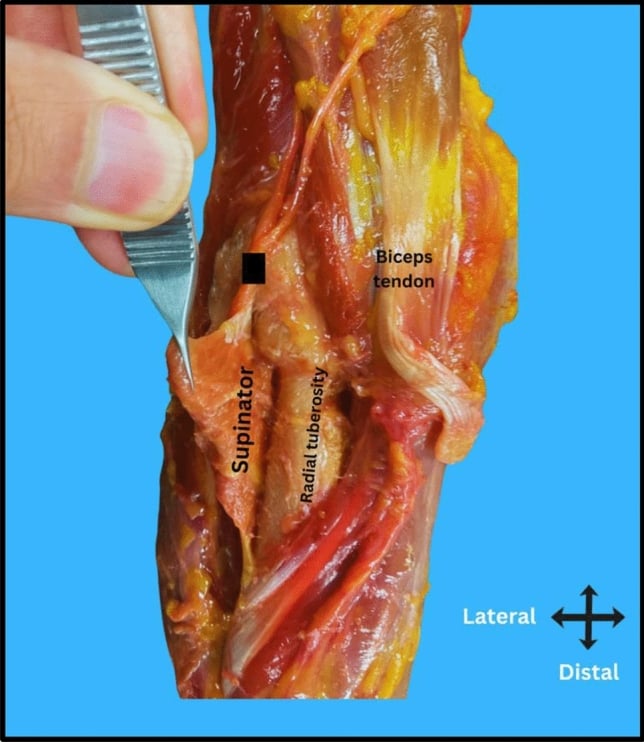
The Irreducible Joint: Blocks to Reduction
The governing rule, fix the fractured bone and the joint reduces, fails in a minority, and the reason differs at each end of the forearm. Distinguish a joint that is reducible but unstable, which is immobilised or transfixed, from one that is irreducible because a structure is mechanically blocking it, which mandates open reduction. Never transfix or cast a joint that is not concentrically reduced.
The radial head that will not reduce: re-check the ulna. The commonest reason a radial head stays dislocated after fixation is inadequate ulnar reduction, a residual loss of length or angulation. Revise the osteosynthesis before blaming soft tissue.
The radial head that will not reduce: the mechanical block. A true block is usually the torn or inverted annular ligament, interposed capsule, or an osteochondral or radial head fragment lying in the joint. It requires open reduction through the lateral (Kocher) interval to extract the interposed tissue and repair or reconstruct the annular ligament.
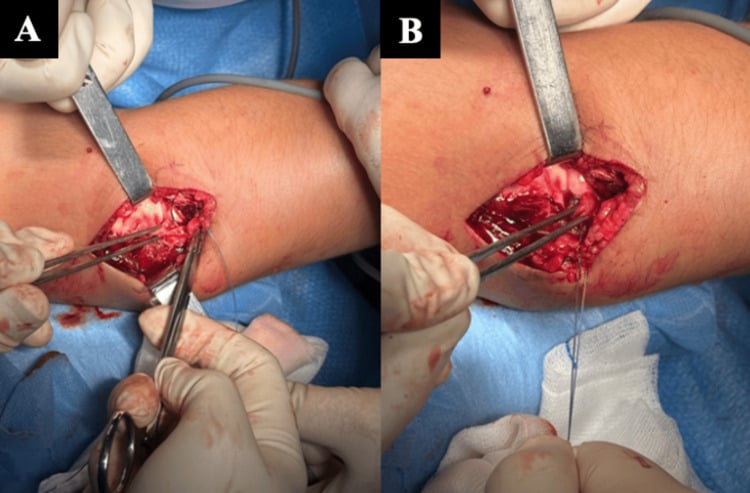
The DRUJ that will not reduce. After anatomic radial fixation most DRUJs reduce. If one remains frankly dislocated rather than merely lax, suspect an interposed structure. The classic culprit is the ECU tendon and its subsheath displaced into the joint, sometimes with the extensor digiti minimi or EDC tendons or an entrapped ulnar styloid fragment, or the volar capsule buttonholed by the ulnar head.
Open reduction of the DRUJ. An irreducible DRUJ needs open reduction, usually through a dorsal approach, to lift the interposed tendon out of the joint and repair the TFCC and subsheath. It cannot be solved by forcing supination or by transfixing an unreduced joint.
Confirm reduction on a true lateral wrist radiograph before the K-wire or supination cast. If the ulnar head remains dorsally or volarly displaced despite radial fixation, that is an irreducible DRUJ (think interposed ECU tendon) requiring open reduction - not more immobilisation.
Postoperative Care
Early motion. Early motion prevents stiffness, the main functional problem in both injuries.
Monteggia. A brief backslab, for about 2 weeks, rests the wound and soft tissues, followed by early elbow and rotation range of motion. Avoid forced rotation initially and extremes of pronation and supination for 4-6 weeks, aiming for full range by 8-12 weeks.
Galeazzi with a stable DRUJ. A removable splint for comfort for about 2 weeks, then early active range of motion, with progressive strengthening from about 6 weeks.
Galeazzi with an unstable DRUJ. A supination cast or K-wires for about 6 weeks, then range of motion. The start is delayed, but the aim is still full range.
Return to work and sport. Manual work at about 8-12 weeks (union); contact sport at about 12-16 weeks.
Outcomes and Prognosis
Acute Monteggia. Anatomic ulna fixation gives good or excellent results in the majority: in Ring's adult series 40 of 48 were excellent or good. Unsatisfactory outcomes cluster in Bado II with associated radial head or coronoid injury. Minor loss of terminal extension is common, and forearm rotation is usually preserved.
Acute Galeazzi. Anatomic radial fixation with a stable, or stabilised, DRUJ gives good results.
Chronic and missed injuries. Results are significantly poorer. Chronic Monteggia reconstruction in children gives meaningful but incomplete gains, and results are best when surgery is within one year (Chen 2018). Reconstruction for chronic DRUJ instability gives variable results.
Prognostic factors. Four carry prognostic weight:
- Anatomic reduction of the fractured bone is the dominant prognostic factor
- Early (acute) treatment beats delayed or chronic surgery
- Associated injuries worsen outcome: radial head and coronoid fractures in Bado II, open fracture, nerve injury
- Persistent radial shortening or DRUJ instability predicts poor Galeazzi results
Guidelines, Registries & Global Practice
OrthoVellum is a global resource - the principles below hold across training systems and examination boards worldwide.
Global epidemiology:
- Monteggia lesions: ~1-2% of forearm fractures; paediatric peak (Type I/III) and adult peak (Type II, higher-energy).
- Galeazzi: ~3-7% of forearm fractures; adults 30-50, often occupational/sport.
Side-by-side guidance and consensus (recommendations are broadly concordant):
- Position on these injuries
- Anatomic ORIF of the fractured bone with plate fixation; restore length/alignment so the joint reduces; assess and address the associated joint
- Position on these injuries
- Adult diaphyseal forearm and forearm fracture-dislocations managed operatively with timely imaging of the whole forearm including both joints
- Position on these injuries
- No injury-specific clinical practice guideline; teaching follows the ring-concept and anatomic fixation principles above
- Position on these injuries
- Endorses anatomic radial/ulnar fixation and intraoperative joint (radial head / DRUJ) assessment
Acute forearm fracture-dislocation fixation is not captured in arthroplasty registries (NJR, AJRR, AOANJRR), as these injuries are managed with osteosynthesis rather than implants; the evidence base is case series and classification studies rather than registry or RCT data.
- Well-resourced settings: routine CT for complex Bado II, locking plates, intraoperative fluoroscopic DRUJ stress testing, radial head arthroplasty available for Essex-Lopresti.
- Limited-resource settings: greater reliance on plain radiographs and contralateral comparison, conventional DCP fixation, K-wire DRUJ transfixation and supination casting; the same anatomic-reduction principles still govern outcome.
- Universal priority everywhere: image the whole forearm and both joints and check the radiocapitellar line - the diagnostic miss, not the implant, is the main cause of poor outcomes.
Controversies and Areas of Uncertainty
- Reconstruct vs accept the chronically dislocated radial head (paediatric Monteggia): Reconstruction (ulnar osteotomy +/- open reduction +/- annular ligament reconstruction) improves stability and pain but carries notable complication rates and unpredictable rotation, and outcomes deteriorate beyond one year. Some advocate observation in late/minimally symptomatic presentations. There is genuine debate over whether annular ligament reconstruction is necessary at all - Chen et al achieved maintained reduction in 18 of 20 children without it, relying on ulnar lengthening/angulation osteotomy.
- Need for trans-capitellar K-wires: Useful when radial head reduction is unstable, but they risk breakage and are avoided by some surgeons in favour of robust osteotomy correction.
- Bado II radial head and coronoid management: The decision to fix, replace or excise the radial head, and whether to fix small coronoid fragments, drives outcome in adult Monteggia and remains individualised.
- Galeazzi DRUJ: how to stabilise: Choice between K-wire transfixation, supination immobilisation, TFCC repair and ulnar styloid fixation is not standardised; the unifying principle is anatomic radial length restoration first, then test and treat residual instability.
- Ulnar styloid fixation: Whether to fix a styloid base fragment in an otherwise stable DRUJ is contested; isolated tip fractures generally do not need fixation.
MCQ Practice Points
Q: What is the Bado classification of Monteggia fractures?
A: Type I: anterior radial head dislocation, anterior ulna angulation (commonest overall). Type II: posterior dislocation, posterior angulation (commonest in adults; the radial head and coronoid fractures that drive outcome). Type III: lateral dislocation, metaphyseal ulna fracture (paediatric) - the type classically associated with PIN palsy, because a lateral dislocation stretches the nerve round the radial neck. Type IV: anterior dislocation with both-bone proximal-third fractures. All require radiocapitellar line assessment.
Q: What radiographic line must be checked to diagnose a Monteggia lesion?
A: The radiocapitellar line - drawn along the radial neck/shaft axis it should pass through the capitellum on all views (AP, lateral, oblique). Disruption indicates radial head dislocation. "Any isolated ulna fracture is a Monteggia until proven otherwise" - always obtain elbow views. Missed in up to 50% initially.
Q: What defines a Galeazzi fracture-dislocation?
A: Distal radius fracture with DRUJ disruption. Called the "fracture of necessity" - requires surgery in adults. DRUJ instability arises from a disrupted TFCC and loss of radial length. Signs: ulnar fovea tenderness, DRUJ widening on PA view, ulnar styloid base fracture, and instability on stress testing.
Q: What is the Essex-Lopresti injury?
A: Radial head fracture + interosseous membrane disruption + DRUJ instability (longitudinal radioulnar dissociation). If the radial head is excised, the radius migrates proximally causing wrist pain and weakness. Treat with radial head replacement (not excision) and protect/reconstruct the IOM.
Q: Why is anatomic ulna reduction critical in Monteggia treatment?
A: Anatomic ulna reduction restores length and IOM tension so the radial head usually reduces spontaneously. Persistent dislocation after ulna fixation suggests interposed tissue (annular ligament/capsule) requiring open reduction. In children, anatomic closed reduction is often sufficient; adults typically need ORIF of the ulna.
Related pages: Radial Head Fractures and Coronoid Fractures for the two injuries that decide the outcome of a Bado II, with Radial Head Arthroplasty when the head is unreconstructable; Radial Head Dislocations for the isolated dislocation and the congenital mimic; Forearm Shaft Fracture (Adult) and Both-Bone Forearm Fractures for the ring concept applied to the diaphysis, and Paediatric Forearm Fractures for the plastically deformed ulna that hides a Monteggia in children; Distal Radius Fractures and TFCC Injuries for the Galeazzi end of the forearm; and Radioulnar Synostosis for the complication both operations risk.
For each injury in full depth rather than in comparison, see Monteggia Fractures - which carries the Jupiter subclassification, the Bell Tawse and ulnar-osteotomy techniques for chronic cases, and the population-based complication data by Bado type - and Galeazzi Fractures.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 35-year-old man presents to the emergency department after falling from a ladder onto his outstretched dominant right arm. He has pain and deformity of the proximal forearm. X-rays show a fracture of the proximal ulna with anterior angulation. On the AP view, the radial head appears congruent with the capitellum, but on the lateral view, the radial head appears to be slightly anterior to the capitellum. What is your diagnosis and how do you manage this injury?”
“A 28-year-old professional gymnast falls on her outstretched hand during training. She has pain at the wrist and distal forearm. X-rays show a fracture of the distal radius at the junction of the middle and distal thirds with dorsal angulation. You also notice the DRUJ appears widened compared to the contralateral side (3mm vs 1mm), and there is a small ulnar styloid fracture. The emergency department doctor asks if this can be treated in a cast. What is your diagnosis and management plan?”
“You are asked to see a 12-year-old boy referred by his GP for a 'funny elbow'. He fell from monkey bars 8 months ago and was treated in a cast for an 'ulna fracture' at another hospital. Since the cast came off he has progressive elbow pain and cannot fully extend or supinate. Examination shows a prominent radial head laterally. X-rays show a healed ulna fracture with residual anterior angulation, and the radial head is dislocated anteriorly/laterally with a flattened, dome-shaped capitellum. What has happened and how do you manage this?”
Monteggia
- Proximal ulna fracture + radial head dislocation
- Bado I anterior (commonest overall); Type II posterior commonest in adults (radial head + coronoid); Type III lateral is the PIN palsy type
- Fix ulna anatomically and the radial head reduces
- Check radiocapitellar line on all views
Galeazzi
- Distal radius fracture + DRUJ disruption
- Fracture of necessity - operate in adults (~80% conservative failure)
- ORIF radius, restore length, then assess DRUJ stability
- Supination is the stable position for the DRUJ
Ring Concept
- Forearm = ring (PRUJ + IOM + DRUJ)
- If one bone fractured + displaced...
- ...there must be disruption elsewhere
- Always X-ray entire forearm + both joints
Key Complications
- Missed diagnosis (especially Monteggia)
- Persistent joint instability
- Malunion affecting rotation
- PIN palsy (classically Monteggia Type III)
Evidence Base and References
Monteggia Fractures in Adults (Bado II Predominance)
- 48 adult Monteggia fractures, mean follow-up 6.5 years
- Bado type II (posterior) was the commonest adult pattern (38 of 48)
- 26 of 38 type II had associated radial head fractures; coronoid fractures common
- Stable anatomic plate fixation of the ulna gave excellent/good results in 40 of 48; unsatisfactory outcomes clustered in type II with radial head/coronoid involvement
Galeazzi 'Fracture of Necessity'
- 125 patients with Galeazzi-type fracture-dislocations (86 adults with the classic lesion)
- Conservative (cast) treatment failed in ~80% of adults; succeeded only in children
- Operative fixation of both the radius and the DRUJ gave excellent results in over half
- Established the 'fracture of necessity' concept - radial shortening perpetuates DRUJ instability
Galeazzi: Treatment-Oriented Classification (7.5cm Rule)
- 40 Galeazzi fractures treated with ORIF of the radial shaft
- Type I (fracture within 7.5cm of the distal radius articular surface): 12 of 22 had intraoperative DRUJ instability
- Type II (fracture over 7.5cm from the joint, middle third): only 1 of 18 unstable
- Distance of the radial fracture from the DRUJ predicts the need for DRUJ stabilisation
Full reference list:
- Bado JL. The Monteggia lesion. Clin Orthop Relat Res. 1967;50:71-86.
- Ring D, Jupiter JB, Simpson NS. Monteggia fractures in adults. J Bone Joint Surg Am. 1998;80(12):1733-44. PMID 9875931.
- Mikic ZD. Galeazzi fracture-dislocations. J Bone Joint Surg Am. 1975;57(8):1071-80. PMID 1201989.
- Rettig ME, Raskin KB. Galeazzi fracture-dislocation: a new treatment-oriented classification. J Hand Surg Am. 2001;26(2):228-35. PMID 11279568.
- Chen HY, Wu KW, Dong ZR, et al. The treatment of chronic radial head dislocation in Monteggia fracture without annular ligament reconstruction. Int Orthop. 2018;42(9):2165-72. PMID 29713746.