Heterotopic Bone in Muscle | Zoning Phenomenon | Wait for Maturity | Surgical Excision
- Zoning phenomenon: Mature bone peripherally, immature centrally - characteristic, but absent in the early phase when MO mimics sarcoma
- Timing: conventionally 6-12 months before excision, but contested - see He 2018
- Maturity assessment: corticated margins on X-ray/CT, settled ALP, bone-scan uptake plateaued (not literally cold)
- Prophylaxis after excision: indomethacin or single-dose radiotherapy, the best-supported intervention here
- Early phase is the danger: imaging and histology can both mimic sarcoma before zoning appears - image at intervals, refer if unsure
- “Zoning phenomenon (mature periphery, immature centre) is highly characteristic but NOT pathognomonic, and is absent early
- “Judge maturity on corticated margins and a plateaued bone scan - mature heterotopic bone is never truly cold
- “Do not excise while actively forming; conventional wait 6-12 months, though early excision is now contested (He 2018)
- “Post-excision prophylaxis (indomethacin or single-dose radiotherapy) is standard; the 50% to 10-20% figures are conventional rather than measured on this page
Overview and Epidemiology
Myositis ossificans is heterotopic bone formation within muscle, typically after trauma or in association with neurological conditions. The name is a misnomer: there is no inflammation, and the bone forms in muscle, not from muscle.
History. First described in 1883, it was originally thought to be inflammatory and is now recognised as heterotopic ossification. The zoning phenomenon was once described as pathognomonic; it is characteristic, not pathognomonic, and it is absent early.
Who gets it. Young, active adults, with a peak at 20-40 years; the traumatic form predominates in athletes and trauma patients. There is a male predominance, reflecting higher exposure to contact-sport and trauma mechanisms.
Where. It is most common after quadriceps contusions, elbow trauma (especially in children) and hip trauma. In the West Point athlete series (Ryan et al. 1991) it developed in approximately 9% of significant quadriceps contusions.
Risk factors. The features that mark out the patient at risk after a contusion:
- Knee range of motion under 120 degrees
- Football or other contact injury
- Previous quadriceps injury
- Treatment delay over 3 days
- Ipsilateral knee effusion
- Early aggressive massage or stretching
Anatomy and Pathophysiology
How it forms. Muscle trauma, a contusion with its haematoma, starts a sequence that takes 6-12 months to complete:
- The haematoma organises into fibrous tissue
- Fibroblasts undergo metaplasia to osteoblasts
- Heterotopic bone forms within the muscle
- The bone matures
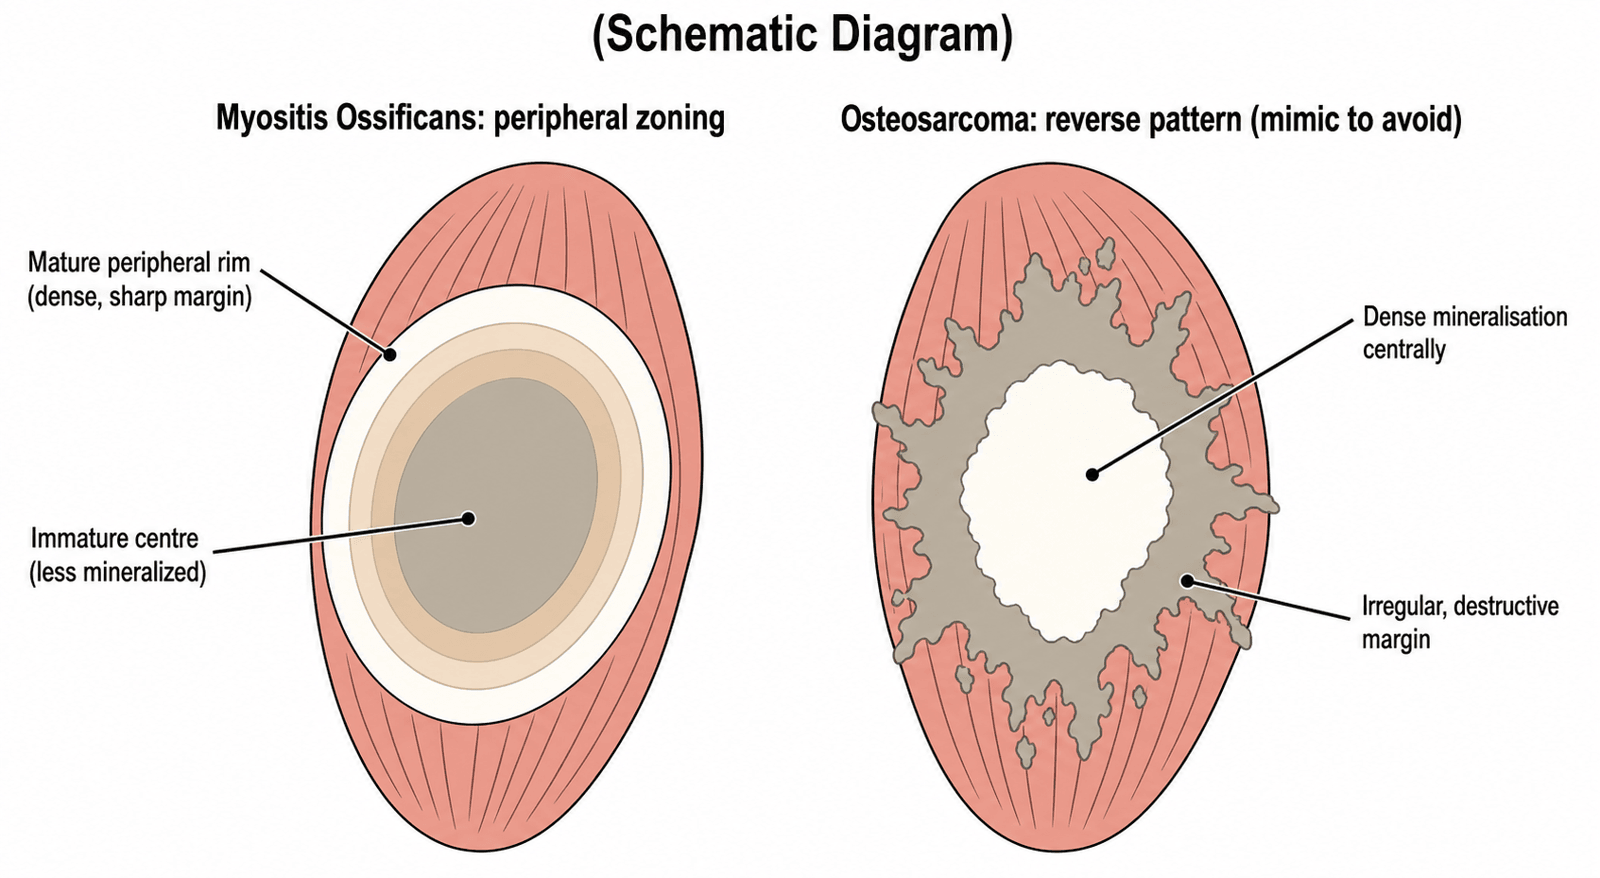
The zoning phenomenon. The bone forms from the outside in. The periphery forms first and matures to lamellar bone while the centre is still immature, so the radiograph shows mature bone peripherally and immature bone centrally. Osteosarcoma shows the reverse, mineralising most densely in the centre, and this is the feature on X-ray that separates the two.
Characteristic, not pathognomonic. Zoning develops as the lesion matures, and in the first weeks it is absent. In that early phase both imaging and histology can be non-characteristic and can mimic sarcoma (Savvidou 2021), which is exactly when the misdiagnosis happens. An early film that lacks zoning excludes neither myositis ossificans nor a sarcoma: interval imaging establishes the diagnosis, and a single early film does not.
Histopathology: The Zonal Architecture and the Sarcoma Trap
The radiographic zoning phenomenon has a microscopic counterpart, and it is what makes the sarcoma trap comprehensible. The lesion is organised into three concentric zones, and the diagnostic danger lies entirely in the centre:
- Central zone, the danger zone. Highly cellular, mitotically active proliferating fibroblasts and immature mesenchymal spindle cells in a myxoid or haemorrhagic background, with reactive but not truly malignant atypia. On a small or early biopsy this is the zone misread as osteosarcoma.
- Intermediate zone. Osteoblasts rimming trabeculae of immature woven bone (osteoid) within a fibrovascular stroma, an orderly transition rather than a permeative one.
- Peripheral zone. Well-organised mature lamellar or trabecular bone, cytologically bland and sharply demarcated from the surrounding muscle. This is the rim seen radiographically.
Why it maps onto imaging. Bone organises from the periphery inward over weeks, so the peripheral bone, the earliest to mature, forms the corticated rim. Extraskeletal osteosarcoma is the opposite: pleomorphic cells produce malignant osteoid throughout the mass, with the densest mineralisation centrally and destructive margins.
Telling it from osteosarcoma. The key exam distinction:
- Myositis ossificans is well-circumscribed with orderly zonal maturation, immature centre to mature periphery; osteosarcoma is disorganised and permeative, with no zonal gradient
- The peripheral bone of myositis ossificans is bland and lamellar, where osteosarcoma produces malignant osteoid from atypical cells throughout
- A subset of myositis ossificans carries a USP6 gene rearrangement, shared with nodular fasciitis and aneurysmal bone cyst and absent in osteosarcoma, which can support the diagnosis in genuinely difficult cases
The practical rule. A biopsy sampled from the immature centre in the first few weeks is the classic error that yields a false osteosarcoma report. If biopsy is truly unavoidable, sample the periphery, and have a musculoskeletal pathologist interpret it together with the trauma history and imaging, never in isolation.
Elbow (Brachialis) Myositis Ossificans and the Forced-Stretch Pitfall
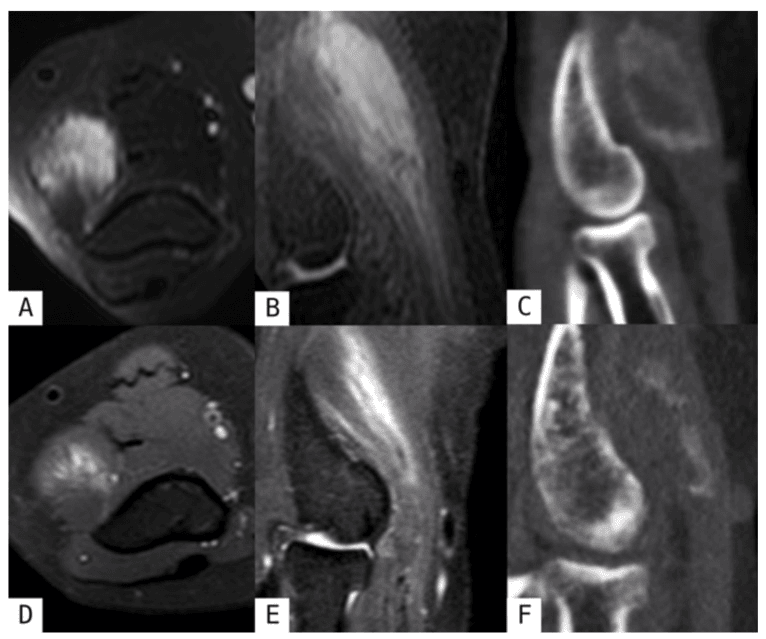
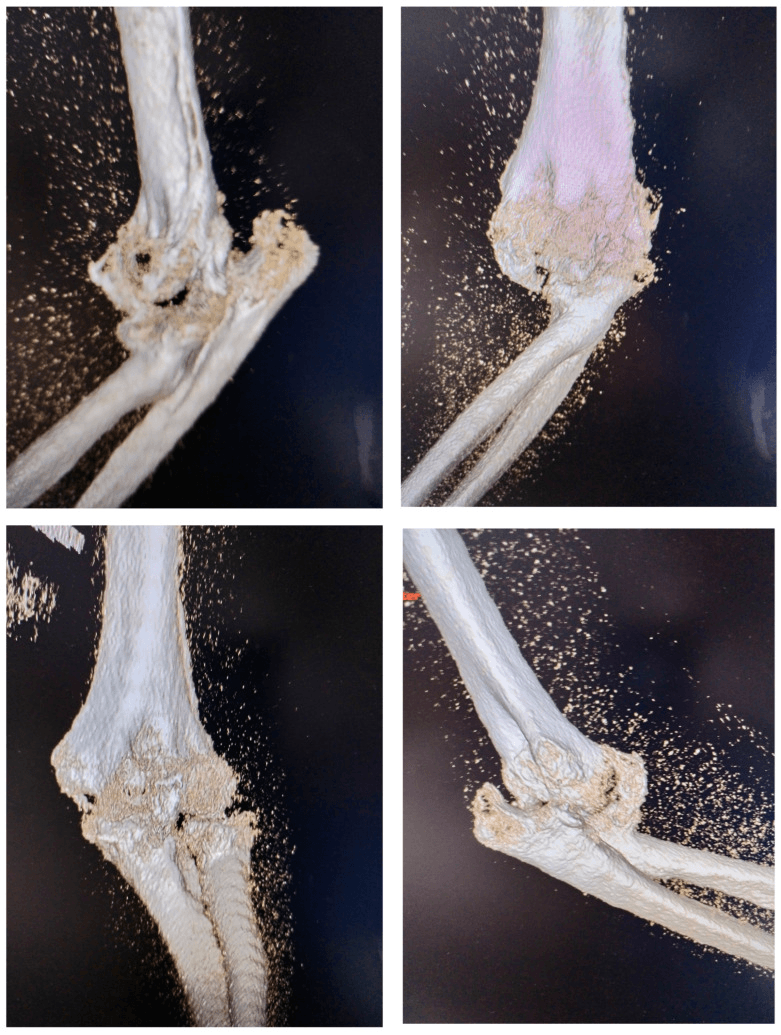
After the quadriceps, the elbow is the classic site, and it carries a distinct, heavily examinable iatrogenic risk. Elbow myositis ossificans follows posterior elbow dislocation, terrible-triad injuries and paediatric supracondylar or forearm fractures. It characteristically forms anteriorly within the brachialis, which lies directly on the anterior capsule and distal humerus, where haematoma from the injury organises, ossifies and blocks the flexion-extension arc.
The forced-stretch pitfall. The single greatest avoidable risk is forced passive stretching or manipulation of the stiff, freshly injured elbow. Vigorous passive mobilisation re-injures the muscle, enlarges the haematoma and converts it into heterotopic bone, which is why the old teaching of aggressive passive stretching of the stiff post-traumatic elbow, and of manipulation under anaesthesia in the acute or subacute phase, has been abandoned.
Principles at the elbow. The rules specific to this joint:
- Favour early active and active-assisted range of motion within a pain-free arc; avoid forced passive stretch and early manipulation under anaesthesia
- Consider NSAID or indomethacin prophylaxis after high-risk elbow trauma or surgery in at-risk patients
- Neurogenic elbow ossification (after head injury) matures more slowly and recurs more often than the traumatic form
- Once the lesion is stable (corticated margins, settled ALP, plateaued scan), a symptomatic anterior lesion restricting the arc can be excised under the same maturity rule and post-excision prophylaxis used elsewhere
Classification Systems
Myositis ossificans is classified by its cause and by its maturity.
By cause. Three types are described:
- Cause
- After trauma/contusion
- Features
- Most common; typically a single site; best prognosis
- Treatment
- Wait for maturity, excise if symptomatic
- Cause
- After head injury/SCI
- Features
- Multiple sites, often bilateral; longer maturation (12+ months)
- Treatment
- Higher recurrence risk
- Cause
- Genetic, rare
- Features
- Progressive, multiple sites
- Treatment
- Not surgical - a different entity; excision is contraindicated and worsens the condition
By maturity. Maturity is read from the radiograph, the bone scan and the alkaline phosphatase (ALP) together, and it decides whether excision is safe:
- Radiograph
- Appears on X-ray
- Bone Scan
- Hot (increased uptake)
- ALP
- Elevated
- Maturity
- Immature - do not excise
- Radiograph
- Zoning phenomenon
- Bone Scan
- Warm (decreasing)
- ALP
- Normalising
- Maturity
- Immature - do not excise
- Radiograph
- Corticated margins
- Bone Scan
- Uptake fallen to a stable plateau
- ALP
- Normal
- Maturity
- Mature - safe to excise if symptomatic
- Radiograph
- Well-corticated, stable size
- Bone Scan
- Stable plateau
- ALP
- Normal
- Maturity
- Fully mature - ideal for excision
Clinical Assessment
History. Ask about trauma or a contusion in the preceding weeks to months:
- Quadriceps contusion, the most common
- Elbow trauma
- Hip trauma
- Head injury or spinal cord injury, in the neurogenic form
Early, at 3-4 weeks. There is a palpable firm mass in the muscle, range of motion is decreased and activity is painful. Swelling may persist.
Established, at 3-6 months. The mass is firm and fixed within the muscle. Range of motion is limited out of proportion to the injury, passive stretch aggravates the pain, and the lesion may cause functional impairment. By this stage the X-ray shows the zoning phenomenon.
Persistent pain and ROM limitation beyond expected recovery after a muscle contusion should raise suspicion for myositis ossificans. An X-ray at 3-4 weeks will show the lesion, and the zoning phenomenon, once it appears, supports the diagnosis.
Investigations
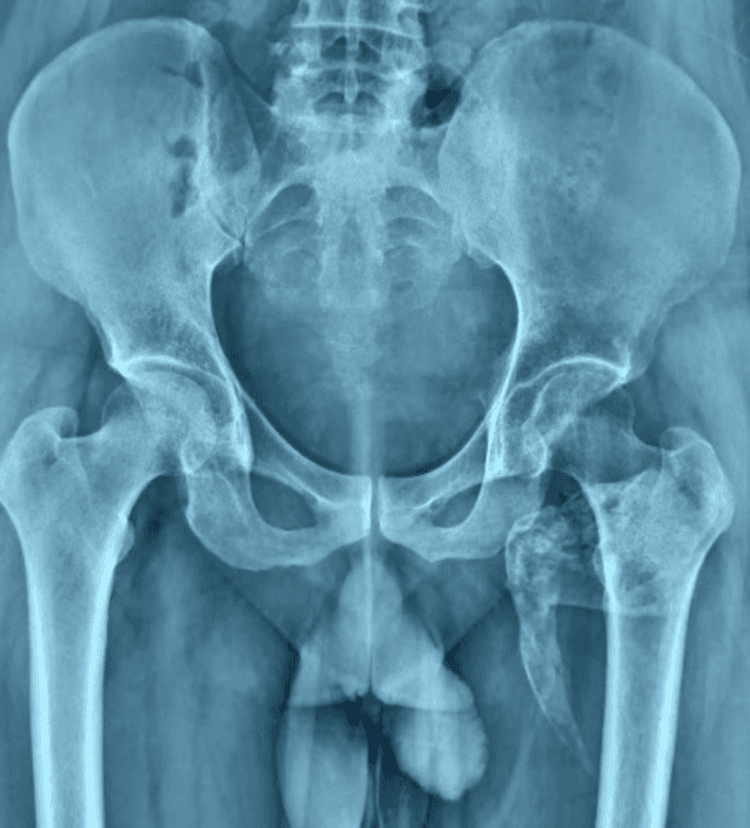
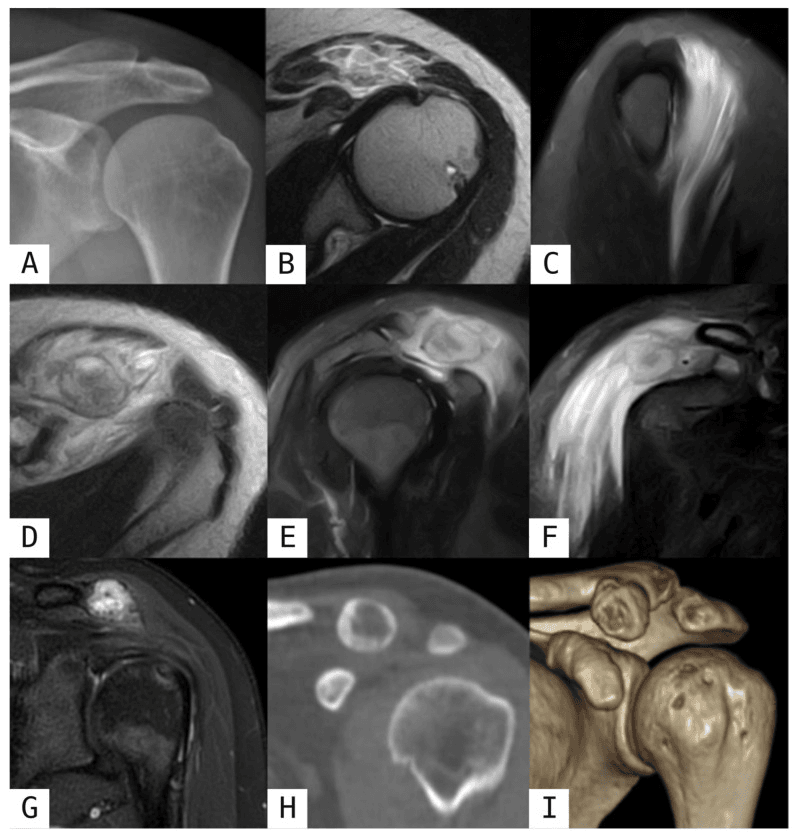
Radiographs. The lesion appears at 3-4 weeks after injury. While immature it has ill-defined margins without cortication; zoning follows, and corticated margins develop over 6-12 months. Corticated margins on X-ray or CT are the most accessible sign that the lesion has stopped changing.
Bone scan. A three-phase bone scan is hot while the lesion is immature, and uptake falls as it matures. Serial scans are the traditional indicator of maturity, and the traditional rule required the scan to be cold before excision. Mature heterotopic bone is bone and retains some uptake, so the practical criterion is uptake that has fallen to a stable plateau on serial scans rather than literal absence of activity. Waiting for a truly cold scan can mean never operating; a still-rising or still-hot scan means the lesion is active.
CT shows the zoning phenomenon clearly and is the planning study, showing the relationship to the neurovascular structures; 3D reconstruction helps.
MRI shows the soft-tissue involvement and shows muscle oedema early. It may help distinguish the lesion from a tumour, but it is supportive rather than diagnostic.
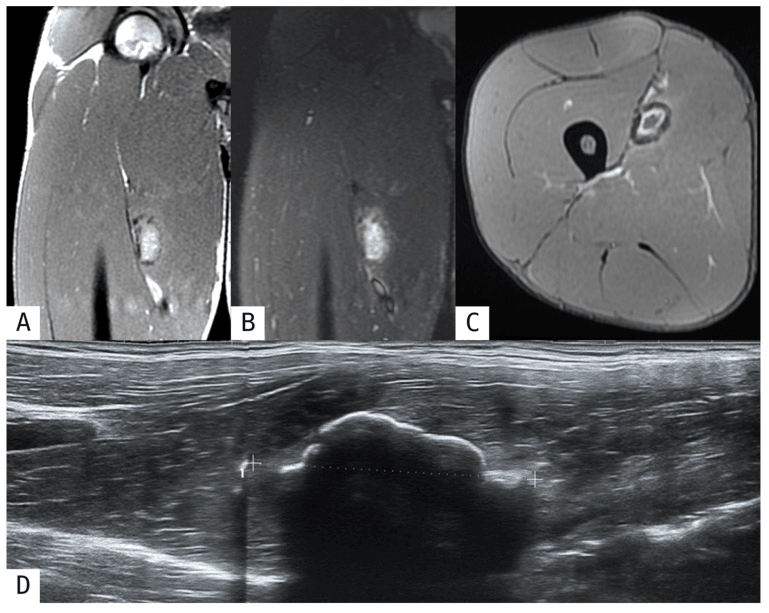
Alkaline phosphatase. Serum ALP rises with active ossification and settles as the lesion matures. It is non-specific, so a trend beats a single value: monitor it serially if maturity is uncertain, and read a normal value as support for maturity rather than proof of it.
CABMaturity Assessment
Hook:CAB: Corticated margins, ALP falling, Bone scan stable (not necessarily cold).
Differential diagnosis. The mimics, and the error each one invites:
- Discriminating Feature
- Trauma history; rapid evolution then maturation
- Imaging Clue
- Zoning - peripheral mature rim, immature centre; corticates by 6-12 months
- Pitfall to Avoid
- Biopsy of early lesion misread as sarcoma
- Discriminating Feature
- Older or no clear trauma; progressive growth
- Imaging Clue
- Reverse zoning - densest mineralisation centrally; cortical destruction
- Pitfall to Avoid
- Calling a malignant mass 'old contusion'
- Discriminating Feature
- Painless enlarging mass
- Imaging Clue
- Enhancing soft-tissue mass, little/no peripheral ossification
- Pitfall to Avoid
- Unplanned excision/whoops procedure
- Discriminating Feature
- Periarticular, often renal/metabolic
- Imaging Clue
- Lobulated amorphous calcification, no zoning or bone trabeculation
- Pitfall to Avoid
- Confusing calcification with ossification
- Discriminating Feature
- Continuity with parent bone cortex/marrow
- Imaging Clue
- Pedunculated, cortico-medullary continuity
- Pitfall to Avoid
- Missing the bony attachment
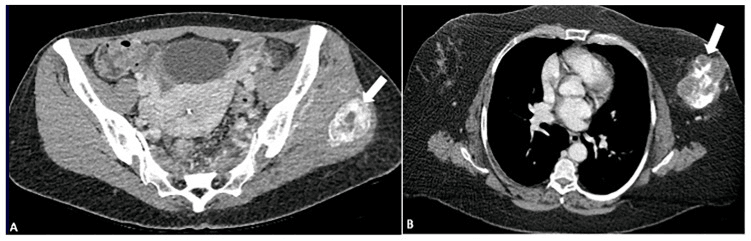
The most dangerous error is biopsying an early myositis ossificans: immature woven bone with hypercellular fibroblastic tissue can be histologically mistaken for osteosarcoma, leading to inappropriate radical surgery. With a clear trauma history and a peripheral maturing rim, follow with serial imaging rather than rushing to biopsy. If genuinely uncertain, refer to a sarcoma unit before any biopsy.
Management Algorithm
The early lesion. A lesion under 6 months old, with a hot bone scan and an elevated ALP, is managed conservatively and is not excised, because recurrence is high after excision of an immature lesion:
- NSAIDs may limit progression if caught early
- Physiotherapy for gentle range of motion, avoiding aggressive stretching
- Monitoring with serial X-rays, bone scan and ALP
When to excise. The conventional rule is to wait a minimum of 6 months and ideally 12, on the grounds that excision disrupts the maturation process and the lesion recurs. The widely quoted 50%+ recurrence after early excision is convention, and is not measured by any study cited on this page (see Controversies).
The case for earlier surgery. The rule is now contested. He 2018, the only direct comparison of timing cited on this page, studied the post-traumatic elbow: excision before 12 months (mean 7.4 months) gave better elbow function, in range of motion and Mayo scores, than later surgery, with no difference in recurrence. Judge the lesion by corticated margins and a settled clinical picture, and weigh a stiff, disabling joint against a number on a scan: a disabling joint may justify operating before the scan settles, and the decision increasingly rests on symptoms rather than on a scan.
Do not excise a lesion that is still actively forming. Early excision is the most common error.
Indications for excision. Excision is for a lesion that is:
- Stable: corticated margins, ALP settled, bone scan plateaued, size no longer growing
- Symptomatic: pain, ROM limitation or functional impairment
- Unresponsive to conservative management
An asymptomatic mature lesion is observed. It may resolve or remain stable, and is excised only if it becomes symptomatic.
Prophylaxis after excision. Prophylaxis is mandatory, and is planned before the operation. The two options:
- Indomethacin 75mg daily for 6 weeks, starting on the first postoperative day
- Radiation 700-800 cGy as a single fraction within 72 hours
The conventional figures are recurrence of 50%+ without prophylaxis and 10-20% with it. The trials comparing indomethacin with radiation found no significant difference between them; the Evidence Base sets out how firm that equivalence is.
Surgical Technique
Planning. CT with 3D reconstruction defines the extent of the lesion, its margins and its relationship to the neurovascular structures, and the approach is planned from it.
Excision. Complete excision with meticulous haemostasis is the aim:
- Use an extensile approach if needed, identify the lesion and protect the neurovascular structures
- Identify the margins, distinguishing the lesion from normal muscle
- Excise all the heterotopic bone, preserving viable muscle
- Achieve meticulous haemostasis, because haematoma promotes recurrence
- Consider a suction drain
- Repair muscle if needed and close in layers
Complications
- Cause
- Excision before maturity
- Prevention/Management
- Wait for maturity, confirm with bone scan
- Cause
- No post-excision prophylaxis
- Prevention/Management
- Mandatory prophylaxis (indomethacin or radiation)
- Cause
- During excision
- Prevention/Management
- Careful technique, identify nerves early
- Cause
- Surgical site
- Prevention/Management
- Antibiotics, meticulous technique
- Cause
- Inadequate haemostasis
- Prevention/Management
- Meticulous haemostasis, drain
- Cause
- ROM loss
- Prevention/Management
- Physiotherapy, early mobilisation
Nerve injury. The nerves are at risk during excision. Identify them early and dissect carefully; neurolysis may be required.
Recurrence is the most common complication. Operate on a stable lesion (corticated margins, plateaued bone scan) and use post-excision prophylaxis (indomethacin or single-dose radiotherapy), which is the intervention with actual randomised support.
Postoperative Care
Prophylaxis runs alongside rehabilitation:
Post-Excision Protocol
- Start prophylaxis (indomethacin day 1 OR radiation within 72 hours)
- Pain management
- Elevation if limb
- Monitor neurovascular status and for complications
- Continue prophylaxis
- Begin gentle ROM exercises
- Physiotherapy consultation
- Monitor wound healing
- Continue prophylaxis (total 6 weeks if indomethacin)
- Active ROM exercises
- Strengthening as tolerated
- Functional restoration
- Serial X-rays to assess for recurrence
- Clinical assessment
- ROM measurement
- Functional assessment
Outcomes and Prognosis
Recurrence. The rates below are the conventional figures rather than ones measured on this page:
- Prophylaxis
- Any
- Recurrence Rate
- 50%+
- Prophylaxis
- None
- Recurrence Rate
- 50%+
- Prophylaxis
- Prophylaxis
- Recurrence Rate
- 10-20%
Prognostic factors. Recurrence is influenced by:
- Maturity: mature lesions recur less
- Prophylaxis, which dramatically reduces recurrence
- Completeness of excision: incomplete excision increases recurrence
- Location: some sites have higher recurrence
Function. Most patients have a good functional recovery. Range of motion is expected to improve and pain relief is usually achieved, although a recurrence may require repeat surgery.
Guidelines, Registries & Global Practice
Global epidemiology:
- Traumatic myositis ossificans is the dominant form worldwide and is closely tied to contact-sport participation and high-energy trauma, so reported frequency tracks local sporting culture and trauma burden rather than geography.
- Significant quadriceps contusions carry roughly a 9% risk (athlete cohorts); the elbow is the next most common site, particularly after paediatric supracondylar/forearm injuries and forceful reduction.
- Neurogenic heterotopic ossification (after traumatic brain or spinal cord injury) is a distinct, related entity that is more common in regions with high road-trauma and conflict-injury volumes.
Side-by-side guideline themes:
- Diagnostic emphasis
- Sarcoma in differential of any soft-tissue mass; image before biopsy
- Prophylaxis / treatment stance
- NSAID or single-fraction radiotherapy for high-risk HO; excise mature symptomatic lesions
- Diagnostic emphasis
- Refer indeterminate masses to a sarcoma/MSK-oncology unit before intervention
- Prophylaxis / treatment stance
- Risk-stratified prophylaxis; conservative-first for early lesions
- Diagnostic emphasis
- Recognise HO as a complication of fracture surgery and head injury
- Prophylaxis / treatment stance
- Prophylaxis (NSAID/radiotherapy) in selected high-risk fixation, e.g. acetabular
- Diagnostic emphasis
- CT for maturation pattern and surgical planning
- Prophylaxis / treatment stance
- Operate only on mature lesions; NSAID widely used as first-line prophylaxis
- No dedicated myositis-ossificans registry exists; the strongest comparative data come from heterotopic-ossification prophylaxis RCTs in acetabular-fracture and hip-arthroplasty cohorts (see Evidence Base), which consistently show NSAID and single-fraction radiotherapy to be equivalent.
- Arthroplasty registries (NJR, AJRR, AOANJRR, SHAR) track heterotopic ossification only indirectly via revision/stiffness data, reinforcing that severe HO is uncommon when at-risk patients receive prophylaxis.
- Where bone scintigraphy, MRI/CT, and radiotherapy are readily available, maturity is confirmed objectively before excision and radiotherapy is an option for prophylaxis.
- In limited-resource settings, serial plain radiographs (corticated margins, stable size) plus normalising alkaline phosphatase guide maturity, and oral NSAID prophylaxis is preferred for cost, access, and simplicity.
Excising immature myositis ossificans leads to high recurrence (50%+). Regardless of healthcare setting, confirm maturity (cold bone scan where available, otherwise corticated margins on serial radiographs and normal ALP) before excision, and give post-excision prophylaxis. Avoid early biopsy of a suspicious mass that may be myositis ossificans - immature histology can mimic sarcoma.
Controversies & Areas of Uncertainty
The 50% figure. The "50% recurrence if excised immature" figure comes from older surgical case series, not modern controlled data. The principle of waiting for maturity is sound, but the precise recurrence rate is uncertain and likely site- and technique-dependent.
Bone scan or serial imaging. Historic teaching mandates a cold three-phase bone scan before excision, but many units now rely on stable, fully corticated lesions on serial radiographs or CT plus a normalised ALP. There is no high-level trial defining the single best maturity test.
Is excision necessary at all? Conservative series (e.g. Simon et al. 2016) show most athletes return to full activity despite persisting ossification, which challenges routine excision. Surgery is increasingly reserved for genuinely mechanical, function-limiting lesions.
Prophylaxis in traumatic myositis ossificans. The RCT evidence for NSAID and radiotherapy equivalence derives from acetabular-fracture and arthroplasty heterotopic ossification and is extrapolated to excision of myositis ossificans. Direct trial data in traumatic myositis ossificans are lacking.
NSAID or radiotherapy. The trials found no significant difference in efficacy, so the real debate is NSAID gastrointestinal and renal risk and the effect on fracture and soft-tissue healing, against radiotherapy's cost, access and theoretical malignancy concern in young patients. That balance favours NSAIDs in most healthy young trauma patients.
Related pages: Heterotopic Ossification for the broader entity, of which post-traumatic myositis ossificans is the intramuscular form and from which most of the prophylaxis evidence on this page is borrowed. For the malignancies this lesion is mistaken for — the reason an early biopsy is dangerous — see Extraskeletal Osteosarcoma, Parosteal Osteosarcoma, High-Grade Surface Osteosarcoma and Osteosarcoma. Fibrodysplasia Ossificans Progressiva is the genetic mimic in which biopsy and surgery actively provoke the disease, and Elbow Stiffness and Contracture covers the joint where excision timing matters most.
MCQ Practice Points
Q: What is the zoning phenomenon in myositis ossificans? A: Mature bone peripherally, immature bone centrally — highly characteristic on X-ray and the feature that distinguishes myositis ossificans from osteosarcoma, which mineralises most densely centrally. It is not pathognomonic, and it is absent in the early phase, when imaging and histology can both mimic sarcoma — which is when the diagnosis is actually difficult.
Q: How do you assess maturity of myositis ossificans before excision? A: Corticated margins on X-ray or CT, a settled ALP, and bone-scan uptake that has fallen to a stable plateau on serial scans — conventionally at a minimum of 6 months and ideally 12. Two caveats worth stating: mature heterotopic bone retains some uptake, so a literally cold scan is the wrong criterion, and the only direct timing comparison cited here (He 2018, elbow) found excision before 12 months gave better function with no increase in recurrence. The widely quoted 50%+ early-recurrence figure is convention, not a measured result from any study on this page.
Q: How do you prevent recurrence after excision of myositis ossificans? A: Post-excision prophylaxis is mandatory - indomethacin 75mg daily for 6 weeks OR radiation 700-800 cGy single fraction within 72 hours. This reduces recurrence from 50%+ to 10-20%. Both modalities equally effective. Never excise without prophylaxis.
Q: When is it safe to excise myositis ossificans? A: Conventionally a minimum of 6 months and ideally 12, judged on corticated margins, a settled ALP and bone-scan uptake that has plateaued. Note two qualifications: mature heterotopic bone retains some uptake so a literally cold scan is the wrong criterion, and He 2018 found earlier excision (mean 7.4 months) gave better elbow function with no increase in recurrence. The 50%+ figure for early recurrence is convention rather than a measured result.
Q: What is the recurrence rate after excision of mature myositis ossificans with prophylaxis? A: 10-20% with prophylaxis, 50%+ without prophylaxis - this is why prophylaxis is mandatory. Recurrence is also 50%+ if excised before maturity, regardless of prophylaxis.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old athlete presents 3 months after a severe quadriceps contusion. X-ray shows a lesion with zoning phenomenon (mature periphery, immature center). Bone scan is still hot. The patient wants it removed because it's causing pain and limiting ROM. How do you manage this?”
“A 30-year-old man has a mature myositis ossificans in the quadriceps (12 months old, bone scan cold, ALP normal, corticated margins). It's causing significant pain and limiting knee flexion to 90 degrees. Describe your surgical approach and post-operative management.”
“A 22-year-old footballer is referred with a firm, enlarging, painful mass in the thigh that appeared a few weeks after a tackle. The referring GP has arranged an MRI that the radiologist reports as a 'heterogeneous soft-tissue mass with surrounding oedema - cannot exclude sarcoma.' The patient and family are anxious and want it biopsied today. How do you proceed?”
Key Facts
- Heterotopic bone formation in muscle
- Zoning phenomenon characteristic but NOT pathognomonic; absent early
- Appears on X-ray at 3-4 weeks
- Matures over 6-12 months
Maturity Assessment (CAB)
- Bone scan uptake plateaued on serial scans (not necessarily cold)
- ALP normal (alkaline phosphatase)
- Bone scan confirms maturity
- Corticated margins on X-ray
- Minimum 6 months, ideally 12 months
Recurrence Prevention
- Do not excise while actively forming (50%+ recurrence is convention, contested by He 2018)
- Excise when stable (corticated margins, plateaued scan)
- Post-excision prophylaxis mandatory
- Indomethacin 75mg daily for 6 weeks OR radiation 700-800 cGy single fraction within 72 hours
- Recurrence: 10-20% with prophylaxis, 50%+ without
Zoning Phenomenon
- Mature bone peripherally, immature centrally
- Characteristic on X-ray, not pathognomonic
- Distinguishes from osteosarcoma (reverse pattern)
- Forms from outside in (periphery first)
Evidence Base
Quadriceps Contusions: West Point Update
- 117 quadriceps contusions in athletes; myositis ossificans developed in 9%
- Severity graded by knee ROM at 12-24h (mild over 90 degrees, moderate 45-90 degrees, severe under 45 degrees)
- Five risk factors: knee motion under 120 degrees, football injury, previous quadriceps injury, treatment delay over 3 days, ipsilateral knee effusion
- Resting the knee in flexion with early flexion exercises sped recovery (mean disability 13-21 days)
Myositis Ossificans Traumatica: Forms, Diagnosis and Treatment
- Heterotopic bone formation; 'myositis' is a misnomer (no true myositis)
- Reviews the distinct clinical entities grouped under the term
- Zoning phenomenon and centripetal maturation key to radiographic diagnosis
- Differentiation from soft-tissue sarcoma is the central diagnostic challenge
Indomethacin vs Localised Irradiation for HO Prophylaxis (Acetabular Fractures)
- Prospective RCT, 166 patients after surgical acetabular fracture fixation
- Indomethacin 25mg three times daily for 6 weeks vs single 800 cGy within 72h
- Clinically significant (Brooker III/IV) HO: 11% indomethacin vs 4% radiation - not significant (p=0.22)
- All 16 untreated patients developed HO; 38% Brooker III/IV