Functional Imaging for Bone, Infection & Tumour Assessment
Bone Scintigraphy (Tc-99m MDP): Whole-body skeletal survey — sensitive for metastases, infection, occult fracture
Three-Phase Bone Scan: Adds flow and blood pool phases — helps differentiate infection from other causes
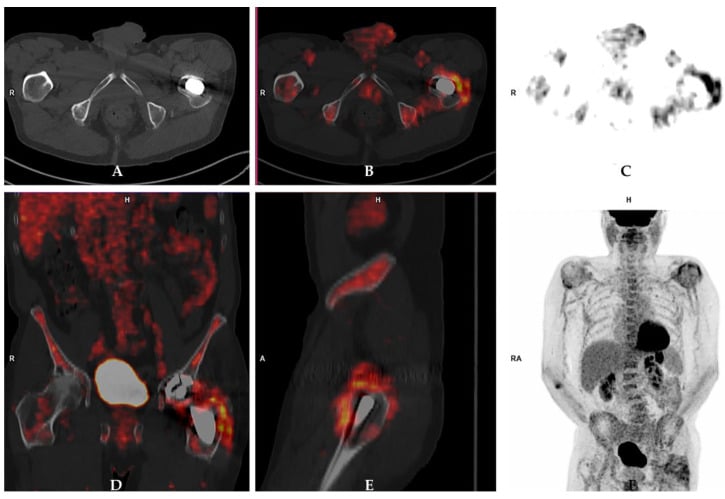
SPECT-CT: Combines SPECT (3D nuclear) with CT — better anatomical localisation
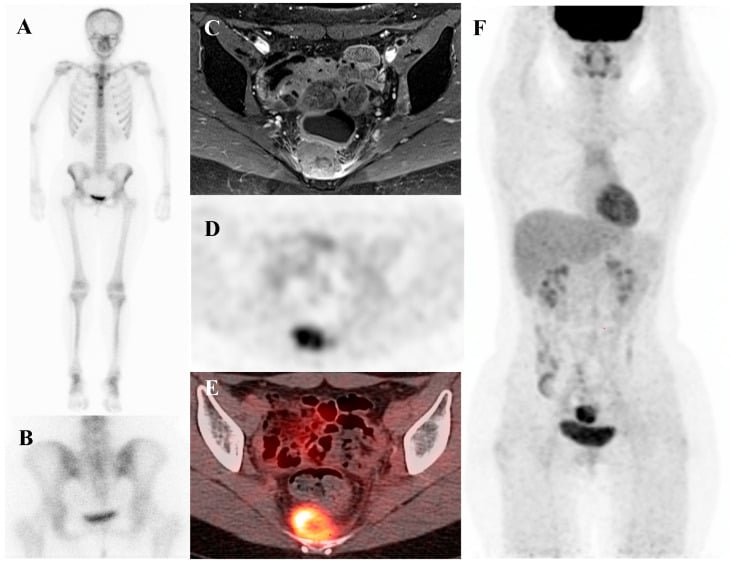
PET-CT (F-18 FDG): Detects metabolic activity — superior for tumour staging and infection localisation
Labelled WBC Scan: Gold standard for prosthetic joint infection — labels patient's own white cells
Key: Nuclear medicine provides FUNCTIONAL information about biological processes, complementing the ANATOMICAL information from radiography, CT, and MRI
- Bone scintigraphy with Tc-99m MDP detects areas of increased osteoblastic activity — it reflects bone TURNOVER, not a specific diagnosis.
- The three-phase bone scan adds vascular (flow and blood pool) phases to the standard bone phase, improving differentiation of infection from other causes of increased uptake.
- Bone scans are highly SENSITIVE (95%) but poorly SPECIFIC — virtually any process that increases bone turnover will cause uptake.
- PET-CT with F-18 FDG detects metabolically active tissue (infection, tumour) with better specificity and resolution than bone scintigraphy.
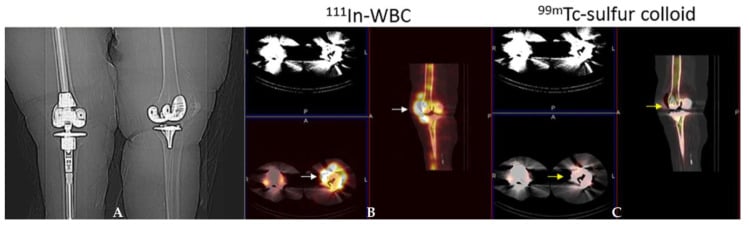
- Labelled white cell scans (In-111 or Tc-99m HMPAO) are the gold standard nuclear medicine test for prosthetic joint infection.
- “A 'cold' lesion on bone scan (photopenic/absent uptake) suggests: aggressive tumour outpacing bone response, myeloma, avascular necrosis, or early infection before osteoblastic response.
- “The three-phase bone scan: Phase 1 (flow) = arterial vascularity, Phase 2 (blood pool) = soft tissue hyperaemia, Phase 3 (delayed) = bone turnover. All three positive in infection.
- “PET-CT is increasingly replacing bone scan for metastatic workup due to superior sensitivity, specificity, and anatomical localisation.
- “Bone scan remains positive for 1-2 YEARS after joint replacement — normal postoperative uptake. A WBC scan helps differentiate infection from normal healing.
- “The 'superscan' pattern (diffuse intense skeletal uptake with faint/absent kidneys) indicates widespread metastatic disease or metabolic bone disease.
Overview
Function, not structure. Radiography, CT and MRI show what bone looks like; nuclear medicine shows what it is doing. The tracer reports physiological change, whether increased bone turnover, metabolic activity, white cell accumulation or blood flow, and it often does so before any structural abnormality is visible on anatomical imaging.
How the image is made. A radioactive tracer (a radiopharmaceutical) is given to the patient, typically intravenously, and is designed to accumulate at sites of a specific biological activity. A gamma camera detects the emitted radiation and produces an image of the tracer's distribution through the body. Areas of increased accumulation, the hot spots, mark increased biological activity; areas of decreased accumulation, the cold spots, may indicate avascularity, bone destruction or tissue death.
Why the functional view matters. Functional change precedes structural change, so a stress fracture appears on a bone scan 1-2 weeks before it is visible on a radiograph. A single functional study can survey the entire skeleton, which is what the whole-body bone scan for metastases does. And function can characterise lesions that look alike on anatomical imaging, separating infection from tumour. The trade-off is that nuclear medicine has lower spatial resolution and lower specificity than the anatomical modalities.
The tracers. The ones an orthopaedic surgeon meets:
- Tc-99m MDP (methylene diphosphonate): binds to hydroxyapatite at sites of osteoblastic activity; the workhorse of skeletal nuclear medicine, with a 6-hour half-life
- F-18 FDG (fluorodeoxyglucose): a glucose analogue taken up by metabolically active cells; used in PET-CT for tumour and infection
- Labelled white cells: the patient's own leucocytes, which migrate to sites of infection; used for prosthetic joint infection
- Ga-67 citrate: accumulates in infection and some tumours; largely replaced by FDG-PET and white cell scans
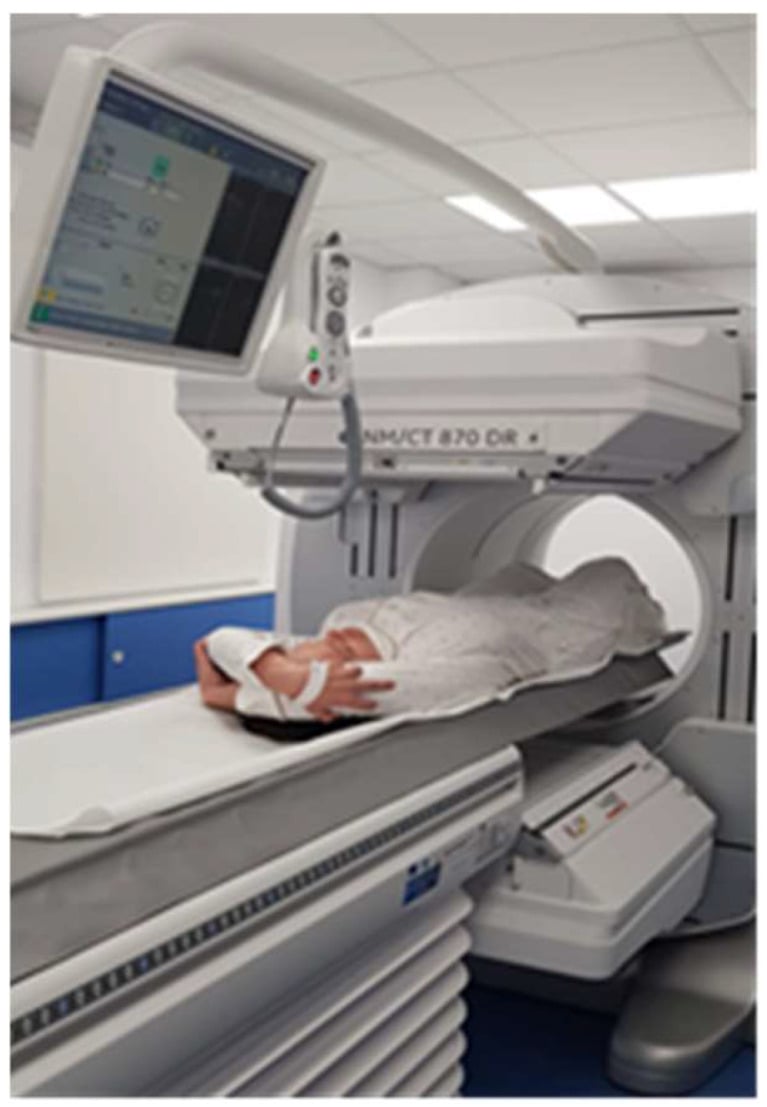
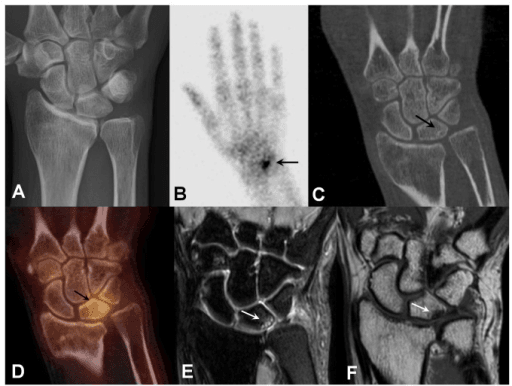
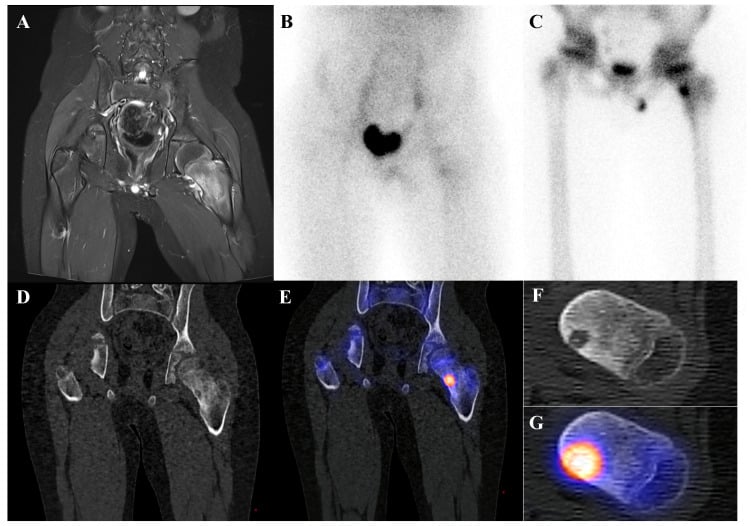
Hybrid SPECT-CT. SPECT gives the nuclear image in three dimensions, and the integrated low-dose CT adds anatomical localisation and attenuation correction. The fused image marries function to structure: a focus of tracer uptake can be assigned to a specific bone, joint or implant interface rather than being reported only as a planar hot spot.
Systematic Approach
Read a bone scan in the same order every time. The steps run from the technical to the anatomical, and the last of them, correlation with anatomical imaging, is what turns a hot spot into a diagnosis.
- Assessment
- Assess overall image quality, symmetry, and artefacts
- Key Considerations
- Check for injection site extravasation, urinary contamination, and patient motion artefacts
- Assessment
- Match findings across flow, blood pool, and delayed phases
- Key Considerations
- The phase pattern (all three positive, delayed only, or soft tissue only) is the discriminator, set out under Bone Scintigraphy below
- Assessment
- Identify areas of focally increased uptake
- Key Considerations
- Correlate with clinical history: single vs multiple, location (metaphysis = infection, vertebral body = metastasis), intensity
- Assessment
- Identify areas of decreased or absent uptake (cold spots)
- Key Considerations
- These are the false-negative patterns (MARL, under Bone Scintigraphy below)
- Assessment
- Assess the overall distribution pattern
- Key Considerations
- Superscan = diffuse uptake. Linear = fracture. Juxta-articular = arthritis. Random = metastases. Single = infection/tumour
- Assessment
- Relate findings to anatomical imaging (radiographs, CT, MRI)
- Key Considerations
- Always correlate nuclear medicine findings with anatomical imaging for definitive diagnosis
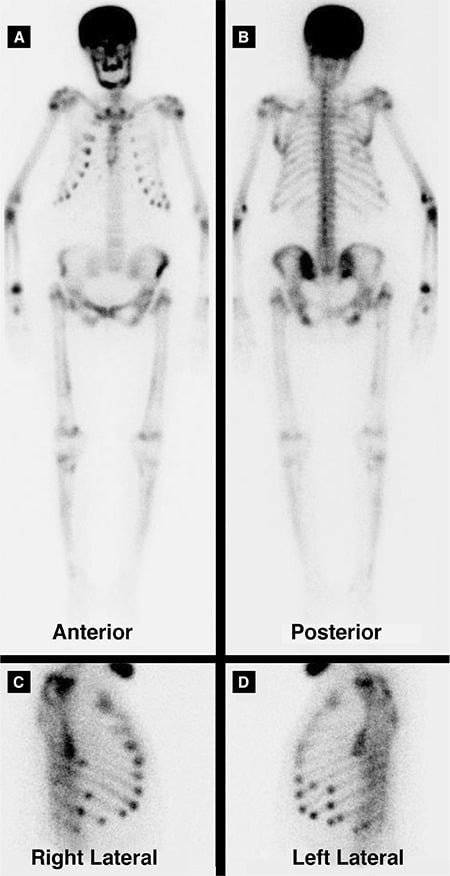
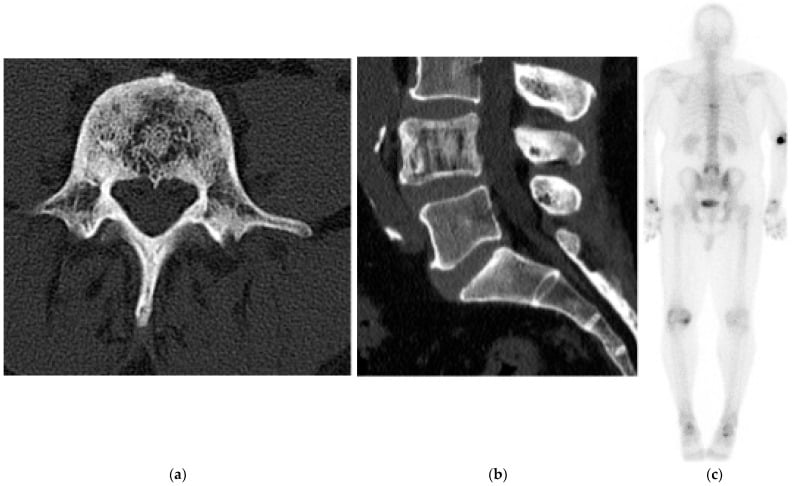
The superscan. Diffuse, intense, homogeneous uptake through the whole skeleton with faint or absent kidneys and almost no soft tissue background: the skeleton has extracted nearly all of the tracer. Despite the high-contrast appearance it is always pathological, and the differential is widespread osteoblastic metastases (prostate, breast) or metabolic bone disease.
Key Studies
Tc-99m MDP Bone Scintigraphy
Mechanism. Tc-99m MDP is injected intravenously and carried to the skeleton in the bloodstream, where it binds calcium hydroxyapatite by chemisorption. Uptake is proportional to two things: local blood flow, which delivers the tracer, and osteoblastic activity, which binds it. Any process that increases either produces increased uptake, which is why the scan is so sensitive and so unspecific.
The three-phase protocol. The phases move from seconds to hours after the injection:
- Phase 1, flow: dynamic images acquired immediately after injection, over the first 30-60 seconds, showing arterial blood flow to the region; increased flow means hypervascularity (infection, tumour, fracture)
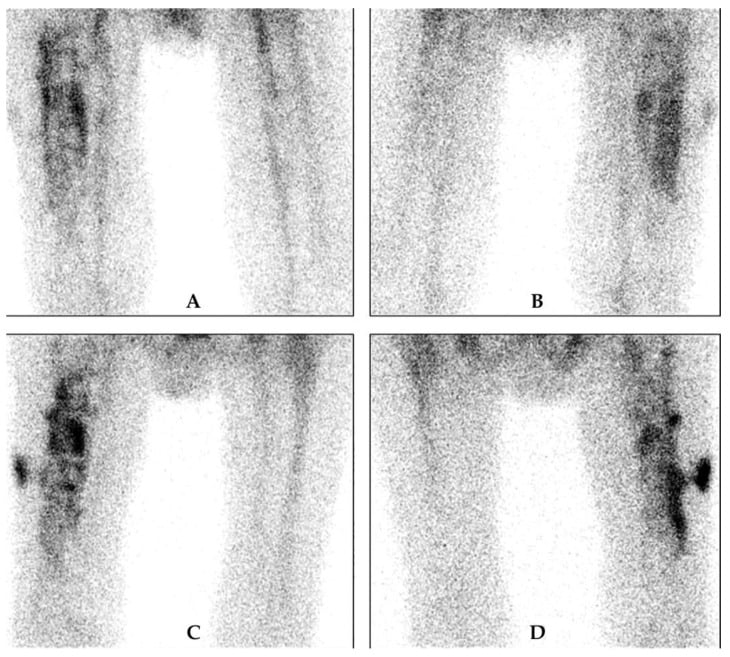
- Phase 2, blood pool: a static image at 5-10 minutes, showing soft tissue distribution and venous pooling; increased blood pool means soft tissue hyperaemia (infection, inflammation)
- Phase 3, delayed bone: static images at 2-4 hours, by which time approximately 50% of the tracer has been taken up by bone and background soft tissue activity has cleared; the MDP is now bound to hydroxyapatite at sites of active turnover, so focal uptake means osteoblastic activity
Reading the phases together. The pattern across the three phases is the discriminator:
- All three phases positive: osteomyelitis, acute fracture, active tumour, CRPS/RSD
- Phase 3 positive only: stress fracture (subacute), established metastasis, degenerative change
- Phases 1 and 2 positive with phase 3 negative: cellulitis, a soft tissue infection without bone involvement
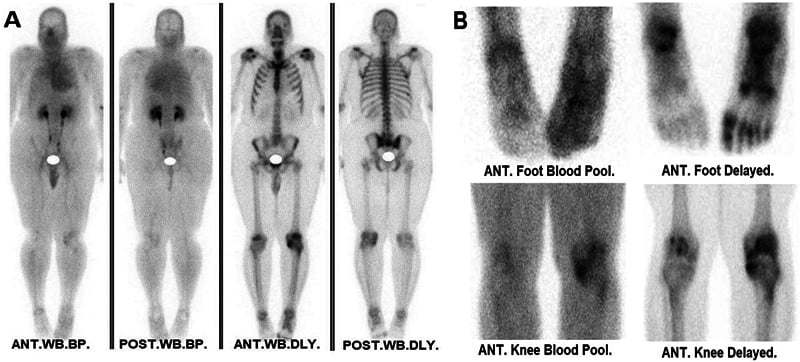
Applications in orthopaedics. The metastatic skeletal survey, with sensitivity of approximately 95% for blastic metastases; occult fracture detection; stress fracture diagnosis; the extent and activity of Paget disease; and complex regional pain syndrome, which gives diffuse periarticular uptake.
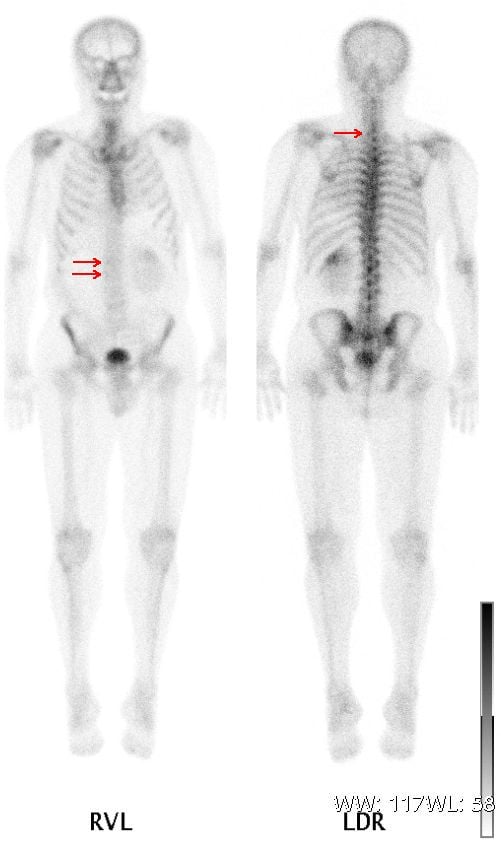
Read that 95% carefully. It is the figure for blastic lesions, and the denominator matters. Measured per patient rather than per blastic lesion, planar scintigraphy performs less well: in 131 breast and prostate patients at high risk of metastases, patient-level sensitivity was 75% for planar imaging, rising to 87% when SPECT/CT was added. Every patient found on planar imaging was also found on SPECT/CT, and SPECT/CT found three more, so SPECT/CT changes who gets diagnosed rather than merely refining the report, and reprojected SPECT/CT images can replace the separate planar acquisition altogether. The trade-off to state honestly is that specificity of the reprojected images was lower than planar, so correlation with cross-sectional imaging stays essential.
The tumour biology decides whether the test works at all. MDP uptake reflects the osteoblastic response, not the presence of tumour, so the scan is only as good as the bone's reaction to the tumour. In purely lytic disease it fails: compared against radiographs across 562 skeletal sites in 51 myeloma patients, scintigraphy missed or underestimated disease at 27% of sites. That is not a technique problem to be solved with better cameras; myeloma provokes little osteoblastic response, so there is nothing for the tracer to bind. Bone scan is therefore the wrong test to screen or monitor myeloma, and whole-body low-dose CT, MRI or FDG-PET-CT are the modern standards.
The same logic explains why FDG-PET-CT outperformed scintigraphy for skeletal staging in lung cancer (pooled 0.92 sensitivity / 0.98 specificity versus 0.86 / 0.88), while bone scintigraphy retains a strong role in predominantly blastic disease such as prostate cancer.
What makes a hot spot, and what makes a cold one. Anything that increases bone turnover produces a hot spot; the cold spots are the false negatives. Both lists are worth carrying verbatim.
FITMAPCauses of Increased Uptake (Hot Spots)
Hook:FITMAP: virtually any process causing increased bone turnover produces a hot spot. Bone scan is sensitive but NOT specific.
MARLCauses of Decreased Uptake (Cold Spots)
Hook:MARL cold spots: Myeloma, AVN, Rapidly destructive tumour, and irradiated Lesions — these are potential false negatives on bone scan.
Differential Diagnosis of a Focal Hot Spot
A single area of increased uptake is the commonest diagnostic dilemma in skeletal nuclear medicine. The bone scan itself rarely gives the answer; the discriminators are clinical context, the three-phase pattern, the anatomical location, and correlative imaging. The table frames the reasoning a candidate should articulate at the viva.
- Typical Location / Pattern
- Axial skeleton, vertebral body/pedicle, random
- Discriminating Feature
- Known primary; often multiple foci; lytic primaries (renal, myeloma) may be photopenic — confirm on CT/MRI
- Typical Location / Pattern
- Metaphysis (children), any bone
- Discriminating Feature
- All three phases positive; focal flow and blood-pool uptake; correlate with CRP/ESR and MRI
- Typical Location / Pattern
- Tibia, metatarsal, femoral neck, pars
- Discriminating Feature
- Fusiform or linear delayed uptake; positive before radiographic change; sport/load history
- Typical Location / Pattern
- Juxta-articular, facet joints, first CMC
- Discriminating Feature
- Delayed-phase only; bilateral and symmetric; matches osteophytes on radiograph
- Typical Location / Pattern
- Pelvis, femur, skull, vertebra
- Discriminating Feature
- Intense uptake of an entire bone with expansion; classic bone deformity; raised ALP
- Typical Location / Pattern
- Femur, tibia, posterior elements
- Discriminating Feature
- Focal intense uptake with central 'double-density'; night pain relieved by NSAIDs; lucent nidus on CT
- Typical Location / Pattern
- Femoral / humeral head, scaphoid
- Discriminating Feature
- Early photopenia, later 'doughnut' of surrounding uptake; correlate with MRI
Guidelines, Registries & Global Practice
Nuclear medicine in orthopaedics is governed by overlapping radiation-protection law and professional society guidance that converge on the same clinical principles worldwide. The unifying framework is the ICRP/IAEA "justification and optimisation" doctrine (ALARA): every study must be clinically justified and delivered at the lowest dose consistent with diagnostic quality. A standard Tc-99m MDP bone scan delivers an effective dose of roughly 3-6 mSv, and an FDG-PET-CT roughly 7-25 mSv (PET plus the CT component), figures that are broadly consistent across national reference-dose schemes.
Radiation Safety and Special Situations (patient precautions)
- Pregnancy: radionuclide studies use ionising radiation, so an elective bone scan is generally deferred in pregnancy; if a study is essential, it proceeds on a justified, ALARA basis with good hydration and frequent voiding (or bladder catheterisation) to clear tracer from the bladder and minimise fetal/gonadal dose. FDG and the CT component of PET-CT add dose and warrant particular caution.
- Breastfeeding: precautions depend on the tracer. For Tc-99m MDP, breast-milk excretion is very low and prolonged interruption is generally NOT required (brief expression/discard per local protocol). For F-18 FDG, milk is not the main issue but the mother should limit close contact with the infant for several hours because of the high-energy 511 keV annihilation photons. Labelled-leukocyte agents have their own schedules — follow the nuclear medicine department's tracer-specific advice.
- General precautions: hydrate and void frequently after any bone-seeking tracer to reduce bladder dose; paediatric studies use weight-adjusted (lowest diagnostic) activity; and brief distancing from young children and pregnant contacts is advised after higher-energy PET tracers. Every study must still pass the justification test (will it change management?) before the optimisation/ALARA step.
Global Epidemiology and Utilisation
- Skeletal metastases are the dominant indication: bone is the third most common metastatic site, and prostate, breast and lung cancers account for the majority of bone-scan referrals globally.
- Periprosthetic joint infection complicates approximately 1-2% of primary hip and knee arthroplasties — a rising absolute burden as arthroplasty volumes grow in every major joint registry.
- Access is highly uneven: PET-CT scanner density ranges from many per million population in high-income settings to near-zero in much of sub-Saharan Africa and South Asia, where planar bone scintigraphy (or radiography/MRI alone) remains the practical mainstay.
Side-by-Side Society Guidance
- Region/Scope
- Europe
- Position Relevant to Orthopaedics
- Publishes procedure guidelines for bone scintigraphy, SPECT/CT and FDG-PET; endorses leukocyte/marrow imaging and the EANM/SNMMI joint criteria for prosthetic-joint and bone infection
- Region/Scope
- North America
- Position Relevant to Orthopaedics
- Co-authors the joint EANM/SNMMI infection-imaging guidance; supports FDG-PET and labelled-leukocyte imaging for osteomyelitis and PJI
- Region/Scope
- USA
- Position Relevant to Orthopaedics
- Rates MRI highly for osteomyelitis/PJI workup; positions bone scan and labelled-WBC studies as adjuncts when MRI is contraindicated or equivocal (e.g. metal artefact)
- Region/Scope
- UK
- Position Relevant to Orthopaedics
- Prioritise MRI and aspiration for PJI; reserve nuclear imaging for problem-solving. NICE supports skeletal staging by the most accurate available modality (often PET in lytic disease)
- Region/Scope
- Oncology, global
- Position Relevant to Orthopaedics
- Bone-only metastatic disease is not RECIST-measurable; functional response on bone scan/PET informs treatment decisions in prostate and breast cancer
- Region/Scope
- PJI, global
- Position Relevant to Orthopaedics
- Defines PJI diagnostically; nuclear studies are a minor (adjunct) criterion behind aspiration, serology and histology
Registry and Resource-Setting Notes
- Arthroplasty registries (NJR for England/Wales, AJRR in the US, AOANJRR in Australia, the Swedish and Norwegian registries) track revision for infection rather than imaging modality, but they quantify the PJI burden that drives demand for leukocyte/marrow and FDG-PET studies.
- High-resource practice: hybrid SPECT/CT and FDG-PET-CT are increasingly first-line for problem-solving; F-18 NaF PET and PSMA-PET are displacing planar bone scans for prostate-cancer staging where reimbursed.
- Limited-resource practice: a single gamma camera may serve a large region; planar Tc-99m MDP remains the affordable workhorse, FDG/cyclotron access is the rate-limiting step, and MRI plus radiography often substitutes for advanced nuclear studies.
Controversies & Areas of Uncertainty
For prostate cancer, planar Tc-99m MDP bone scan is being displaced by PSMA-PET and F-18 NaF PET in centres where these are reimbursed, with higher sensitivity for early marrow disease. However, the bone scan remains the cheapest whole-body skeletal survey and underpins validated response criteria (PCWG3 "2+2" rule). The optimal first-line modality therefore depends as much on access and cost as on raw accuracy.
Combined leukocyte/marrow scintigraphy is the most specific nuclear study, but it is labour-intensive and increasingly challenged by FDG-PET, which is faster and comparably accurate (Verberne meta-analysis). No nuclear test is a stand-alone diagnostic — all major consensus definitions (MSIS/ICM) rank imaging below aspiration, serology and histology.
Paradoxical increase in bone-scan uptake 2-3 months after effective systemic therapy reflects osteoblastic healing, NOT progression. Misinterpreting flare as treatment failure is a classic trap; reassessment at 6 months or cross-sectional/biochemical correlation resolves it.
Hybrid SPECT/CT improves specificity and localisation and is becoming routine in high-resource settings, but adds dose and cost. Whether it should replace planar imaging universally — versus being reserved for equivocal foci — remains a pragmatic, resource-dependent question rather than a settled one.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 65-year-old man with prostate cancer presents with back pain. His PSA has risen. You request a bone scan which shows multiple focal areas of increased uptake in the thoracic and lumbar spine, ribs, and pelvis.”
“You are investigating a 60-year-old woman with a painful total knee replacement at 3 years post-operatively. A bone scan shows increased periarticular uptake. The three-phase study is positive in all three phases.”
“An examiner asks: 'A 45-year-old patient presents with widespread bone pain. You notice a bone scan showing diffusely increased skeletal uptake with virtually no renal or soft tissue activity. What is the diagnosis?'”
Three-Phase Bone Scan
- Phase 1 (Flow): arterial vascularity — first 30-60 seconds
- Phase 2 (Blood pool): soft tissue — 5-10 minutes
- Phase 3 (Delayed bone): osteoblastic activity — 2-4 hours
- All three positive: infection, acute fracture, active tumour
- Phase 3 only positive: stress fracture, degenerative, metastasis
Hot Spots (FITMAP)
- Fracture, Infection, Tumour, Metabolic, Arthritis, Post-surgical
- Sensitive (95%) but NOT specific — virtually any bone turnover shows up
Cold Spots (MARL — False Negatives)
- Myeloma (no osteoblastic response — bone scan NEGATIVE)
- AVN (early avascular phase before revascularisation)
- Rapidly destructive tumour (outpaces osteoblastic response)
- Lesion previously irradiated
Prosthetic Joint Infection
- Bone scan: sensitive but NOT specific for PJI (specificity 33%)
- Combined WBC/marrow scan: gold standard for PJI (sensitivity 83%, specificity 94%)
- Discordant WBC uptake (WBC+/marrow-) = infection
- Normal bone scan uptake after arthroplasty persists 1-2 years
PET-CT vs Bone Scan
- PET-CT: better specificity, detects lytic lesions, soft tissue disease
- Bone scan: better sensitivity for blastic metastases, cheaper, more available
- PET-CT increasingly preferred for comprehensive tumour staging
- Bone scan remains valid for prostate and breast cancer screening
Evidence Base
FDG-PET-CT vs Bone Scintigraphy for Skeletal Metastases (Lung Cancer)
- Pooled analysis of 17 studies (2940 patients) comparing FDG-PET-CT, FDG-PET, MRI and bone scintigraphy for bone metastases in lung cancer.
- FDG-PET-CT had pooled sensitivity 0.92 and specificity 0.98 — the highest diagnostic odds ratio of all modalities.
- Bone scintigraphy had sensitivity 0.86 and specificity 0.88, inferior to PET-CT on every metric.
Bone Scan False Negatives in Myeloma
- Radionuclide images and radiographs compared in 51 myeloma patients across 562 skeletal sites.
- Scintigraphy failed to show radiographically evident disease, or underestimated its extent, at 27% of sites — confirming relative insensitivity.
- The shortfall reflects the purely lytic nature of myeloma lesions: no osteoblastic response means little or no MDP uptake.
Bone SPECT/CT vs Planar Bone Scintigraphy for Metastases
- 131 breast and prostate cancer patients at high risk of bone metastases underwent Tc-99m HMDP planar scintigraphy plus whole-body SPECT/CT, with NaF/PSMA PET-CT and whole-body MRI as reference.
- Every metastatic patient detected by planar scintigraphy was also detected by SPECT/CT, and SPECT/CT additionally identified three patients missed on planar imaging.
- Patient-level sensitivity rose from 75% (planar) to 87% (SPECT/CT-derived images).
Bone scan sensitivity depends on the osteoblastic response of the underlying lesion, and SPECT/CT meaningfully augments planar imaging where anatomical localisation is needed.