Eccentric Load Injury | Bench Press Mechanism | Loss of Axillary Fold
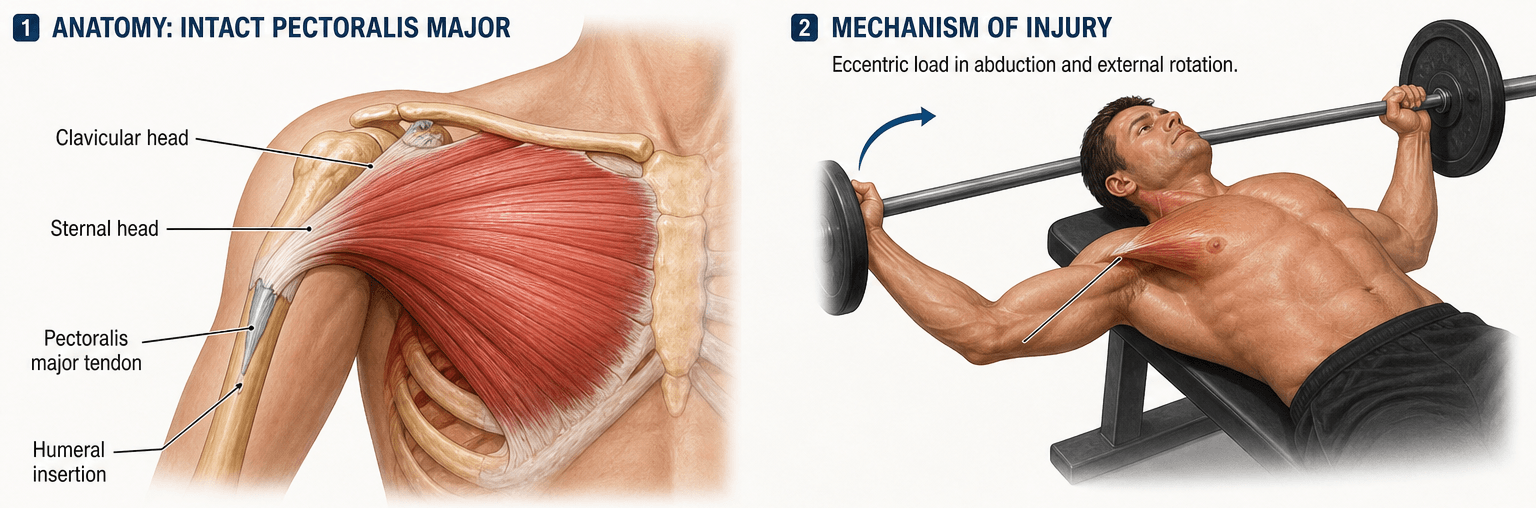
- Pectoralis major has two heads: clavicular (proximal) and sternocostal (distal), forming a bilaminar tendon inserting on the lateral lip of the bicipital groove
- Mechanism is eccentric loading during bench press, especially during the eccentric (lowering) phase with the arm abducted and externally rotated
- Classic exam finding: loss of the anterior axillary fold with webbing, ecchymosis over the chest wall, and weakness of adduction and internal rotation
- Acute surgical repair within 6 weeks yields significantly better outcomes than delayed repair or conservative management for complete tears
- MRI is the gold standard for confirming diagnosis, delineating tear location, and assessing retraction
- “Loss of anterior axillary fold is pathognomonic for pectoralis major rupture
- “Tietjen Type III (complete tendon avulsion from humerus) is the most common pattern in surgical series
- “Arm in abduction and external rotation during eccentric loading is the classic mechanism
- “Surgical repair within 6 weeks gives best results; chronic tears have inferior outcomes
Overview and Epidemiology
Pectoralis major rupture is an increasingly recognised injury, particularly among weightlifters and athletes. Its incidence has risen significantly over recent decades, in parallel with the growing popularity of resistance training and with anabolic steroid use.
Who. Predominantly men aged 20 to 40. The bench press accounts for approximately 90% of cases, and the dominant side is more commonly affected.
What it costs. Weakness of shoulder adduction, flexion and internal rotation, which significantly impairs pressing and throwing. The lost anterior axillary fold is disfiguring, and the psychological impact is important in young active patients and bodybuilders.
Why it is missed. In the emergency setting the ecchymosis and swelling obscure the clinical picture, so the diagnosis is frequently missed or delayed. Early recognition and timely surgical repair of a complete tear yield excellent functional outcomes; delayed diagnosis leads to retraction, scarring and inferior results.
Pathophysiology
The muscle. A large fan-shaped muscle with two heads, clavicular and sternocostal, which converge on a bilaminar tendon. The tendon twists 90 degrees before inserting on the lateral lip of the bicipital groove of the humerus, where its anterior and posterior layers have a U-shaped morphology.
- Origin
- Medial half of clavicle
- Insertion
- Lateral lip of bicipital groove (anterior layer, distal)
- Primary Action
- Shoulder flexion and adduction
- Origin
- Anterior sternum and costal cartilages 1-6
- Insertion
- Lateral lip of bicipital groove (posterior layer, proximal)
- Primary Action
- Shoulder adduction and internal rotation
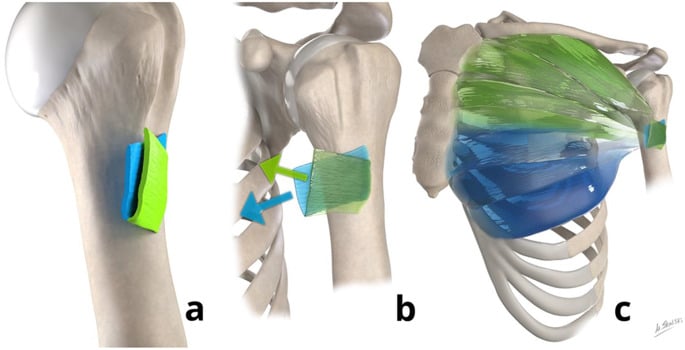
Why the inferior fibres fail. The layered, twisted arrangement puts the inferior (sternocostal) fibres under the greatest tension when the arm is abducted and externally rotated. In that position they are maximally stretched, at a mechanical disadvantage, and they are the most vulnerable during eccentric loading.
Mechanism. The arm is abducted 60 to 90 degrees and externally rotated, in the eccentric (lowering) phase of the bench press or a similar pressing movement. A maximal eccentric contraction against heavy load exceeds the tensile strength of the tendon. Inadequate warm-up, excessive load and anabolic steroid use all contribute.
Why the insertion. Failure is most commonly at the humeral insertion, as a tendinous avulsion. The twist of the bilaminar tendon concentrates stress there, and the insertion zone is a vascular watershed with a relatively poor blood supply.
Anabolic steroids are a recognised risk factor. They rapidly increase muscle mass and contractile force, but the tendon does not strengthen at the same rate, and they also cause collagen dysplasia: disorganised, stiffer, less elastic collagen fibrils with altered crimp. A powerful muscle pulling on an under-adapted, stiffer tendon fails under eccentric load, the classic steroid user rupturing mid bench press.
What steroid use changes. It has consequences for the examination, the operation and the counselling:
- The drugs act systemically, so the other pectoralis, and other tendons, are also at risk: examine and counsel about the contralateral side, and be alert to a history of prior tendon ruptures
- The tendon is often of poorer quality, which can compromise suture purchase and is cited among the poor-prognosis factors; assess it intra-operatively and choose fixation accordingly
- Counsel on cessation, realistic expectations and modification of maximal single-rep lifting, because the underlying tendon vulnerability persists
Classification and Types
Tietjen's classification, as modified by ElMaraghy, runs from a muscle belly strain to complete rupture of the tendon from the humerus; the modification adds subtypes for partial tears based on their extent. Which layer tears, and how far the tear runs proximally, is what the classification records. Type III is the most clinically significant and the most commonly reported in surgical series.
- Description
- Muscle belly strain or contusion, no tendon disruption
- Clinical Features
- Pain, minimal swelling, preserved axillary fold
- Treatment
- Conservative: rest, ice, progressive rehabilitation
- Description
- Partial tear at musculotendinous junction (parsimonious)
- Clinical Features
- Weakness, some deformity, palpable defect possible
- Treatment
- Conservative for low demand; surgical for athletes
- Description
- Partial tear at musculotendinous junction (extensive)
- Clinical Features
- Significant weakness, visible deformity, ecchymosis
- Treatment
- Surgical repair recommended for active patients
- Description
- Complete tendon rupture from humeral insertion
- Clinical Features
- Complete loss of axillary fold, marked weakness, ecchymosis
- Treatment
- Surgical repair indicated; best within 6 weeks
Clinical Assessment
History. A sudden audible or palpable pop, or a tearing sensation, during the eccentric phase of a bench press or similar pressing movement. Sharp pain in the anterior chest or proximal arm settles to a dull ache, and weakness of pressing, adduction and internal rotation is immediate. Swelling and bruising develop over the following hours to days.
Examination. Compare with the other side throughout.
- Inspection - loss of the anterior axillary fold, asymmetric with the other side; the fold looks flattened or concave, a web-like deformity (webbing)
- Ecchymosis - over the anterior chest wall, the axilla and the medial proximal arm
- Palpation - a defect along the lateral chest wall or proximal humerus; the retracted muscle belly may be palpable medially
- Resisted adduction and internal rotation - tested with the arm forward-elevated; weak, and reproduces the pain
The most reliable clinical sign is asymmetric loss of the anterior axillary fold. Stand the patient with the arms at the sides and look at the fold from the front, then ask them to press the hands together (isometric adduction): on the affected side the muscle contracts but the fold stays deficient, because the tendon is discontinuous, and the belly may bunch up proximally. With a history of eccentric loading this is highly suggestive of complete rupture, and it should prompt urgent MRI and surgical referral.
An intact-looking axillary fold does not exclude rupture. The fold has two contributors, because the tendon is bilaminar: when a tear spares the clavicular head, as an isolated sternocostal (sternal) head tear or a partial tear does, the upper, clavicular part of the fold stays intact. The fold can look deceptively preserved at rest, and the diagnosis is wrongly downgraded to a strain.
- Examine dynamically and inferiorly: on resisted adduction and internal rotation, look for a thinned, low or asymmetric inferior fold and a step-off, and compare the sides with the palms pressed together
- Palpate specifically for the inferior (sternal-head) defect along the lateral chest wall and humeral insertion, rather than just inspecting the gross contour
- Keep a low threshold for MRI even when the fold appears present: the sternal head carries most of the muscle's adduction and internal-rotation power, and a missed sternal-head tear still becomes a retracted chronic problem
- Key Feature
- Loss of axillary fold after bench press
- Discriminating Finding
- Ecchymosis, weakness of adduction and internal rotation
- Investigation
- MRI confirms tear location and extent
- Key Feature
- Anterior chest pain without axillary fold loss
- Discriminating Finding
- Pectoralis major intact on clinical exam
- Investigation
- MRI differentiates; rare compared to PM rupture
- Key Feature
- Popeye deformity, not axillary fold loss
- Discriminating Finding
- Ecchymosis anterior arm, not chest; biceps contour abnormal
- Investigation
- Clinical diagnosis confirmed with ultrasound or MRI
- Key Feature
- Global shoulder pain and instability
- Discriminating Finding
- Positive apprehension, not axillary fold deformity
- Investigation
- X-ray and MRI for labral injury
- Key Feature
- Pain without functional muscle deficit
- Discriminating Finding
- Intact axillary fold, normal adduction strength
- Investigation
- Chest X-ray if rib fracture suspected
Both present with anterior pain and ecchymosis after lifting. Pectoralis major rupture loses the anterior axillary fold and weakens adduction and internal rotation. Proximal biceps rupture gives the Popeye deformity of the biceps belly and weakens supination and elbow flexion, and the axillary fold is preserved.
Investigations
Radiographs. AP and axillary lateral views of the shoulder. Most ruptures are purely soft tissue and the films are normal, so their main job is to exclude other pathology. Look for a bony avulsion fragment from the lateral bicipital groove and for soft-tissue swelling; focal loss of the normal pectoralis major soft-tissue shadow on the AP view may suggest the diagnosis.
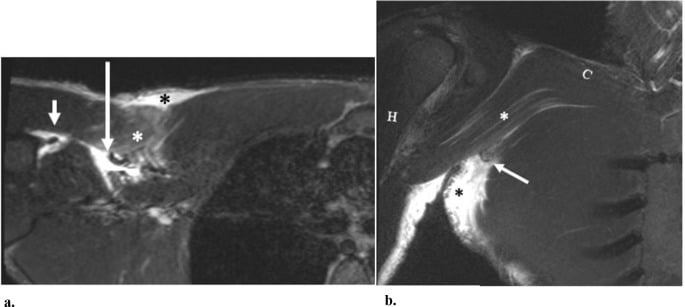
MRI is the gold standard and is indicated in all suspected ruptures. It shows discontinuity of the tendon at the humeral insertion, retraction of the muscle belly and the surrounding haemorrhage and oedema, and it places the tear as tendinous, musculotendinous or muscular.
- T1 and T2 weighted sequences in axial, coronal and sagittal planes
- T2 fat-suppressed sequences best demonstrate the tear and the fluid collection
- Axial T2-weighted images are the most useful for identifying the discontinuity at the humeral insertion
Why the detail matters. MRI accurately delineates the tear location, its extent and the degree of retraction, and that plans the operation: it determines whether direct repair is feasible or graft reconstruction will be needed. Tendinous avulsions are repaired directly to bone, while musculotendinous junction tears may require different reconstruction techniques. Do not delay MRI in a suspected complete tear, because the surgical window is time-sensitive.
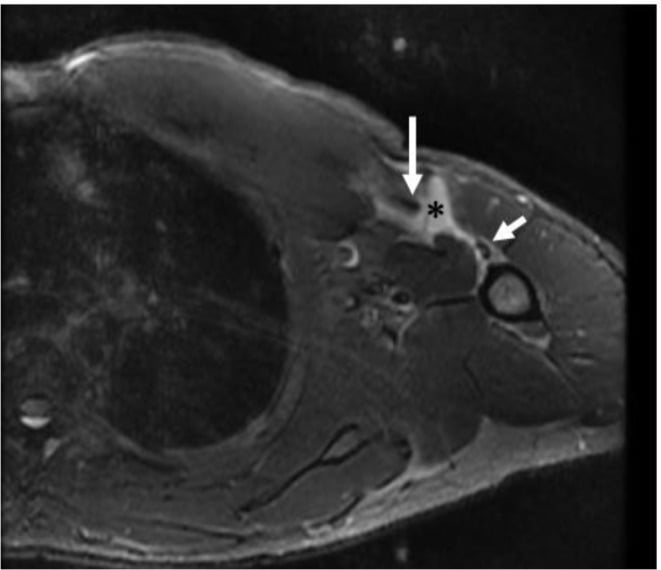
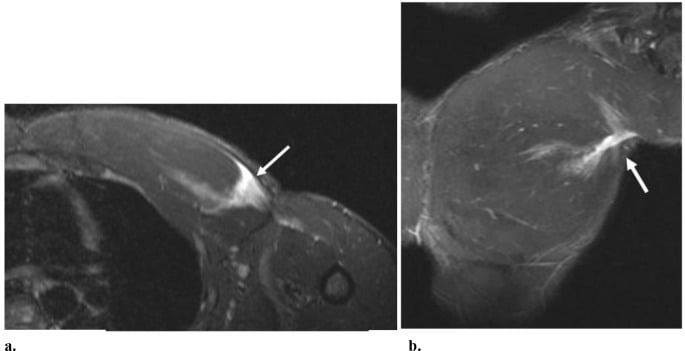
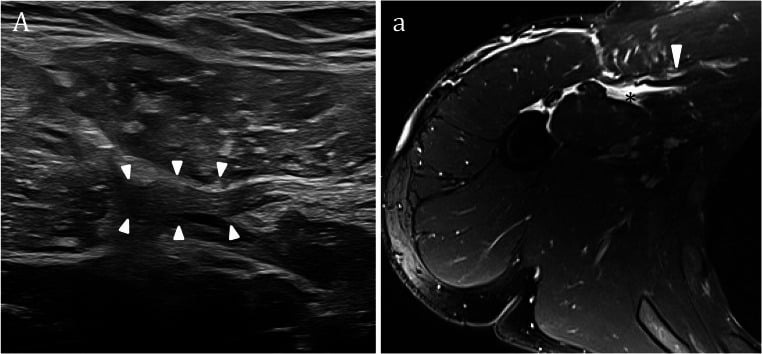
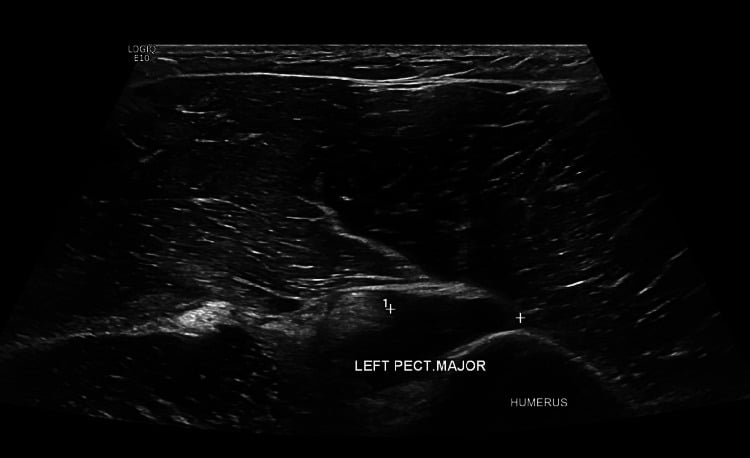
Ultrasound is the alternative for rapid bedside assessment when MRI is unavailable. It shows tendon discontinuity, haematoma and retraction, and it allows dynamic assessment, but it is operator-dependent and less accurate than MRI for tear extent and preoperative planning. The musculotendinous junction tear is the one that is easiest to miss on MRI and easiest to see on a targeted scan.
Management Algorithm
The decision. For a complete tear (Type III) in an active patient or athlete, surgical repair is the treatment of choice, because conservative management leaves persistent weakness of adduction and internal rotation and a permanent cosmetic deformity. Conservative management is appropriate for Type I strains and partial tears in low-demand patients. The decision must factor in age, activity level, occupation and sporting demands.
- Diagnosis
- Loss of axillary fold, MRI confirms tear
- Treatment
- Urgent surgical repair within 6 weeks
- Key Pearl
- Complete tears in active patients need surgery
- Diagnosis
- Some axillary fold preserved, MRI partial
- Treatment
- Conservative or surgical based on demand
- Key Pearl
- High-demand athletes may benefit from repair
- Diagnosis
- Retracted tendon, absent axillary fold
- Treatment
- Delayed repair or reconstruction with graft
- Key Pearl
- Outcomes inferior to acute repair
Timing. Refer complete tears for surgical consultation urgently. Repair is ideally within 2 to 3 weeks and acceptable up to 6 weeks, and 6 weeks is the key threshold: beyond it, tissue retraction and scarring make repair more difficult and significantly compromise repair quality and functional outcomes. A tear that presents later is a delayed repair (6 weeks to 3 months) or a chronic one (over 3 months).
Goal. Restore the anterior axillary fold and the power of adduction and internal rotation by anatomic repair of the tendon to its humeral insertion, through a deltopectoral approach (Surgical Technique).
Before surgery. MRI confirms the tear location and retraction. Consent covers infection, re-rupture, stiffness and residual weakness.
Surgical Technique
Positioning. Beach chair, or supine with a bump under the shoulder, with the head of the bed elevated 30-45 degrees and the arm free-draped so that it can be positioned during the repair.
Incision. The standard deltopectoral approach, along the interval from the clavicle to the deltoid insertion, typically 8-12 cm. It can be extended distally for better exposure of the humeral insertion.
Dissection. The cephalic vein marks the interval; it is usually taken laterally with the deltoid, and preserved or ligated if necessary. Retract the deltoid laterally and pectoralis major medially, and identify the torn tendon edge, retracted medially; it may be significantly retracted and need careful mobilisation. The approach gives excellent visualisation of the humeral insertion and allows the tendon to be mobilised.
Anatomy to respect. The coracoid is the landmark for orientation, and the long head of biceps lies medial to the surgical field. The axillary nerve is deep and inferior, and safe with proper retraction.
Complications
- Incidence
- Around 5 percent after repair
- Risk Factors
- Early return to heavy lifting, inadequate fixation
- Management
- Revision repair if tissue adequate; graft reconstruction if not
- Incidence
- Common after delayed repair
- Risk Factors
- Chronic tears, muscle atrophy, poor tissue quality
- Management
- Rehabilitation and activity modification
- Incidence
- Around 10 percent post-operative
- Risk Factors
- Prolonged immobilisation, poor rehabilitation compliance
- Management
- Physiotherapy, rarely manipulation under anaesthesia
- Incidence
- Around 1 to 2 percent
- Risk Factors
- Diabetes, smoking, prolonged tourniquet time
- Management
- Standard wound infection management; may require washout
- Incidence
- Near universal if untreated
- Risk Factors
- Complete tears managed conservatively
- Management
- Only addressed by surgical repair or reconstruction
Early diagnosis and timely surgical repair prevent the complications of chronic rupture. A missed or delayed diagnosis that results in a chronic retracted tear converts a straightforward primary repair into a complex reconstruction with inferior outcomes. Always examine the axillary fold in any patient presenting with anterior chest or shoulder pain after weightlifting.
Postoperative Care and Rehabilitation
Rehabilitation is critical to a successful outcome. The protocol balances early motion, to prevent stiffness, against protection of the repair while it heals.
The first 6 weeks are critical for tendon-to-bone healing. Aggressive early motion can lead to repair failure. Passive ROM is safe. Active motion begins at 4-6 weeks. Resistance is delayed until 6 weeks minimum.
- Sling with the arm in neutral rotation, worn for 4 to 6 weeks in all; removed for hygiene
- Pendular exercises and elbow, wrist and hand ROM only
- No active shoulder motion and no passive stretching
- Ice and elevation for swelling; educate the patient about the restrictions
- Passive ROM under therapist supervision: forward flexion to 90 degrees, external rotation to neutral, with gentle pendulum exercises
- Avoid terminal external rotation and abduction, which stress the repair
- Sling between exercises; still no active shoulder motion
- Pain-free scapular retraction exercises begin
- Discontinue the sling
- Progress passive ROM to full and begin active-assisted ROM in all planes, progressing to active ROM as tolerated
- Continue to avoid combined abduction and external rotation
- Light isometrics in adduction and internal rotation; no resistance exercises
- Active ROM and progressive resistance exercises, starting with gentle strengthening: rubber bands (therabands) and light dumbbells
- Focus on internal rotation and adduction strengthening, gradually increasing ROM and resistance
- Chest press with light weight, limited range at first
- Continue to avoid maximal external rotation
- Progressive resistance training and sport-specific exercises, with a gradual return to weightlifting
- Bench press with light to moderate weight (below); no heavy bench press yet
- Focus on proper form and controlled motion
- Most patients return to full activity by 6 months
- Gradual return to pre-injury activity levels; competitive sport may resume after 6 months
- Heavy weightlifting after 6-9 months
- Emphasise proper warm-up and technique
- Full strength recovery may take up to 12 months
Milestones. Full passive ROM is expected at 6 weeks, and full active ROM, with strength training beginning, at 12 weeks. By 6 months the patient returns to sport with near-normal strength, and at 12 months has full strength and unrestricted activity.
Return to bench press. Light bench press at 3 months (50% body weight), moderate at 6 months (80% body weight) and heavy after 9-12 months. Maximal single-rep attempts are avoided permanently.
Outcomes and Prognosis
- Timing
- Within 6 weeks
- Expected Outcome
- Over 90 percent good to excellent results
- Return to Sport
- 4 to 6 months, high rate of return
- Timing
- 6 weeks to 3 months
- Expected Outcome
- 70 to 80 percent good results
- Return to Sport
- 6 to 9 months, some residual weakness
- Timing
- Over 3 months
- Expected Outcome
- 50 to 70 percent functional improvement
- Return to Sport
- Variable, may not return to pre-injury level
- Timing
- N/A (non-operative)
- Expected Outcome
- Pain resolves, persistent weakness and deformity
- Return to Sport
- Return to modified activity at 3 to 4 months
Strength and return to sport. Over 90% return to sport after acute surgical repair. Strength recovery is 95-100% after acute repair against 70-85% after chronic reconstruction, which also carries a higher re-rupture risk.
The best prognosis follows acute repair within 2 to 3 weeks of a tendinous avulsion (Type III), anatomically repaired to bone and followed by a compliant rehabilitation programme. The prognosis is poor with repair delayed beyond 6 weeks, musculotendinous junction tears, significant retraction and muscle atrophy, and anabolic steroid-associated tendon dysplasia.
Guidelines, Registries & Global Practice
- Incidence rising worldwide in parallel with the popularity of resistance training and weightlifting
- Predominantly males aged 20 to 40, though female cases are increasingly reported
- Anabolic steroid use is a recognised risk factor, more prevalent in competitive bodybuilding communities globally
- Bench press is the most common mechanism across all regions and populations
- High-resource settings: Urgent MRI and surgical repair within 2 to 3 weeks is standard for complete tears; suture anchors widely available
- Limited-resource settings: Diagnosis may be clinical and ultrasound-based; transosseous bone tunnels are a low-cost alternative to anchors for repair
- Universal principle: Timing of repair is the most important modifiable factor regardless of setting
- Rehabilitation: Structured physiotherapy protocols are universally applicable regardless of fixation method
- Diagnosis Emphasis
- MRI gold standard; clinical exam sufficient to suspect diagnosis
- Acute Treatment
- Surgical repair for complete tears in active patients within 6 weeks
- Surgical Technique
- Suture anchors or bone tunnels to lateral bicipital groove
- Diagnosis Emphasis
- Clinical assessment of axillary fold + MRI to confirm
- Acute Treatment
- Surgical repair recommended for complete tears; conservative for partial tears in low-demand patients
- Surgical Technique
- Anatomical footprint restoration; anchors increasingly preferred
- Diagnosis Emphasis
- Imaging to define tear pattern for surgical planning
- Acute Treatment
- Early repair for complete tendon avulsions
- Surgical Technique
- Transosseous repair principles; anchors as equivalent alternative
There is no dedicated registry for pectoralis major ruptures. The evidence base consists of retrospective case series, a few prospective cohort studies, and one systematic review. No randomised controlled trial compares surgical to non-operative management, although the observational evidence strongly favours surgery for complete tears. The key exam message: the superiority of early surgical repair is supported by consistent observational evidence, and timing is the most important modifiable prognostic factor.
Controversies & Areas of Uncertainty
Both fixation methods have good published outcomes. No randomised trial has demonstrated superiority of one technique over the other. Suture anchors are more expensive but technically simpler. Bone tunnels are low-cost and equally effective. Choice is often dictated by surgeon preference and resource availability.
The optimal management of Tietjen Type II partial tears is debated. Low-demand patients may do well with conservative management, but high-demand athletes may benefit from surgical repair to maximise strength recovery. No high-quality evidence guides this decision, which must be individualised.
There are case reports of pectoralis major rupture following corticosteroid injection for shoulder pathology. The causal relationship is unproven, but caution is advised when injecting near the pectoralis major insertion in active weightlifters.
While most studies report high rates of return to sport after surgical repair, return to competitive-level bench press at pre-injury loads is less well documented. Athletes should be counselled that while the vast majority return to training, elite-level powerlifting performance may be affected.
MCQ Practice Points
Q: What is the most common mechanism of pectoralis major rupture? A: Eccentric contraction during bench press lowering phase (around 90% of cases). The shoulder is in abduction and external rotation, placing maximal tension on the sternal head which fails at the musculotendinous junction or tendinous insertion.
Q: Why is the sternal head of pectoralis major more commonly injured than the clavicular head? A: Because of the 90-degree bilaminar tendon twist, the inferior sternocostal fibres are placed under maximal tension when the arm is abducted and externally rotated, and the sternocostal head represents the larger share of muscle mass experiencing the force - so eccentric overload during the bench-press lowering phase fails the sternal head preferentially, typically at the tendinous insertion or musculotendinous junction.
Q: According to Tietjen classification, which type has the best surgical outcomes? A: Type III (tendon rupture) has best outcomes because healthy tendon tissue can be securely repaired to bone with anchors or tunnels. Type I (muscle belly) is difficult to repair and does better nonoperatively.
Q: What is the classic clinical triad of complete pectoralis major rupture? A: (1) Ecchymosis over anterior chest, (2) loss of anterior axillary fold (asymmetry), and (3) palpable defect at humeral insertion. This triad allows clinical diagnosis before imaging.
Q: What is the optimal timing for surgical repair of pectoralis major rupture? A: Within 6 weeks of injury, ideally 2-3 weeks. Acute (under 2 weeks) has tissue friability and edema. After 6 weeks, tissue retraction and scarring make direct repair difficult. This window provides best tissue quality for secure repair.
Q: What strength recovery can be expected with surgical repair versus nonoperative management? A: Surgical repair achieves 95-100% of contralateral strength, while nonoperative management achieves 60-70% of contralateral strength. This difference justifies surgery in active individuals with complete ruptures.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 32-year-old male weightlifter presents to the emergency department 3 days after feeling a pop in his right chest while performing a bench press. He describes a tearing sensation during the lowering phase with his arms wide. On examination, there is extensive ecchymosis over the anterior chest wall and medial proximal arm. The anterior axillary fold is absent on the right compared to the left. Resisted adduction and internal rotation are weak. X-rays are normal. What is the diagnosis and management?”
“A 40-year-old manual worker presents with a 4-month history of right shoulder weakness. He recalls a tearing sensation in his chest during a gym session 4 months ago but did not seek medical attention at the time. The anterior axillary fold is absent. MRI shows a complete pectoralis major tendon avulsion from the humerus with 5 cm of retraction and moderate muscle atrophy. How would you manage this?”
Key Anatomy
- Bilaminar tendon: clavicular head (anterior layer) and sternocostal head (posterior layer)
- Insertion: lateral lip of the bicipital groove of the humerus
- The tendon twists 90 degrees, concentrating stress on inferior fibres during eccentric loading
- Functions: shoulder adduction, flexion, and internal rotation
Diagnosis
- Classic triad: bench press mechanism, loss of anterior axillary fold, ecchymosis
- Weakness of resisted adduction and internal rotation
- MRI is gold standard for confirming tear location and extent
- Axial T2-weighted MRI best demonstrates the discontinuity at the humeral insertion
Classification
- Tietjen Type I: muscle belly strain (conservative)
- Tietjen Type II: partial tear at musculotendinous junction (conservative or surgical)
- Tietjen Type III: complete tendon avulsion from humerus (surgical)
- Most common pattern at surgery: tendinous avulsion from humeral insertion
Treatment
- Complete tears in active patients: surgical repair within 6 weeks (ideally 2 to 3 weeks)
- Surgical technique: deltopectoral approach, repair to lateral bicipital groove via anchors or bone tunnels
- Partial tears in low-demand patients: conservative (rest, progressive rehabilitation)
- Chronic tears: reconstruction with autograft or allograft if direct repair not feasible
Outcomes and Pitfalls
- Acute repair: over 90 percent good to excellent results, high return to sport
- Chronic repair: inferior outcomes, 50 to 70 percent functional improvement
- Most common missed diagnosis: dismissing as simple muscle strain without examining axillary fold
- Critical time threshold: 6 weeks from injury for optimal repair
Evidence Base and Key Trials
Rupture of the pectoralis major: a meta-analysis of 112 cases
- Meta-analysis of 112 cases demonstrating that surgical repair of pectoralis major ruptures yields superior outcomes compared to conservative management
- Patients treated with surgical repair achieved near-normal strength and returned to pre-injury activity levels
- Conservatively treated patients had persistent weakness of adduction and internal rotation
- Advocated early surgical repair for complete tears in active individuals
Ruptures of the pectoralis major muscle. An anatomic and clinical analysis.
- 12 patients with 14 ruptures, 9 of which occurred while weight lifting, combined with a cadaveric hemithorax study simulating the bench press
- Fibre excursion was measured at seven points along the muscle origin: the short, INFERIOR fibres lengthened disproportionately during the final 30 degrees of humeral extension
- The authors concluded that those inferior fibres are at a mechanical disadvantage at the end of the eccentric phase, and high load applied to maximally stretched fibres produces the rupture
- Five acute and two chronic ruptures were repaired; on Cybex isokinetic testing the operated patients had torque and work comparable with the other side, while conservatively treated patients had a marked deficit in both
Clinical considerations for the surgical treatment of pectoralis major muscle ruptures based on 60 cases: a prospective study and literature review
- Prospective study of 60 surgically treated pectoralis major ruptures demonstrating excellent functional outcomes after repair
- Surgical group demonstrated significant improvement in strength, cosmesis, and patient satisfaction
- The isokinetic strength deficit was markedly lower in the surgically treated group compared to historical conservative controls
- Recommended surgical repair for complete tears, especially in athletes and active individuals
A systematic review and comprehensive classification of pectoralis major tears
- Systematic review proposing a comprehensive classification system for pectoralis major tears based on tear location and extent
- Clarified the bilaminar tendon anatomy and its relevance to the pattern of injury and surgical repair
- Modified the Tietjen classification to include partial tear subtypes (ElMaraghy modification)
- Provided surgical guidance for anatomical footprint restoration during repair based on the classification
Treatment of Pectoralis Major Tendon Tears: A Systematic Review and Meta-analysis of Operative and Nonoperative Treatment
- 23 articles and 664 injuries met inclusion criteria; all patients were male, mean age 31.5 years, 63.2 per cent injured during weight training, mean follow-up 37 months
- Repair was significantly superior to non-operative treatment for functional outcome (23.3 per cent relative improvement, P = .027), isometric strength (77.1 per cent, P less than .001), isokinetic strength (28.9 per cent, P less than .001), cosmesis satisfaction (13.8 per cent, P = .037) and resting deformity (98.9 per cent, P less than .001)
- The overall complication rate after operative treatment was 14.2 per cent
- The rerupture rate was 3.1 per cent