The True Workhorse of Elbow Flexion
- Origin: distal half of the anterior humerus, embracing the deltoid insertion; insertion: ulnar tuberosity and coronoid process — NOT the radius, so it cannot supinate.
- Dual innervation: musculocutaneous nerve (C5, C6) to the bulk of the muscle, with a radial nerve branch (C7) to the inferolateral fibres of the deep head — present in every specimen in the defining cadaveric study, so expect it rather than rely on it.
- It has the largest physiological cross-sectional area of the elbow flexors and its moment arm is unaffected by forearm rotation, so it is the true prime flexor.
- The deep surface is intimately applied to the anterior elbow capsule; this is the plane developed in open anterior capsular release for elbow contracture.
- The brachialis is the muscle within which heterotopic bone forms after elbow dislocation, and the muscle split in Henry anterolateral and anterior approaches to the humerus.
- “Leonello and colleagues showed two heads in every specimen and a radial nerve branch to the deep head in all eleven — this is the internervous plane that makes the muscle splittable, though eleven specimens establish that it is usual rather than invariant.
- “Because brachialis inserts on the ulna it flexes with equal power whether the forearm is pronated or supinated — the basis of testing it in full pronation.
- “In elbow contracture the brachialis is short and scarred; elevating it off the capsule from lateral to medial protects the median nerve and brachial artery medially.
- “Radial nerve palsy weakens elbow flexion only slightly, because brachialis and biceps are musculocutaneous — the loss is brachioradialis, the paradoxical radial-innervated flexor.
Overview
The brachialis is the deep flexor of the anterior arm, lying directly on the anterior surface of the distal humerus and the anterior elbow capsule with the biceps brachii superficial to it. It shares the anterior compartment with biceps brachii, which takes the radial tuberosity and is both a flexor and a supinator, and with coracobrachialis, which runs to the mid-medial humerus and flexes and adducts the shoulder. All three are musculocutaneous muscles (C5, C6); brachialis alone has a second supply.
Its surgical importance is out of proportion to how it is taught. This is the muscle the trainee finds under the biceps in a Henry approach, the muscle stripped away in contracture release, and the muscle in which the ossifying haematoma of myositis ossificans forms after an elbow dislocation. Three features drive that importance: an insertion on the ulna alone, a dual nerve supply that puts an internervous plane inside a single muscle, and a deep surface adherent to the anterior joint capsule. Whatever you do to brachialis, you do next to the capsule, the radial nerve laterally, and the brachial artery and median nerve medially.
Companion muscle. The superficial, strap-like flexor that borders it laterally is the brachioradialis — the paradoxical radial-innervated flexor that is expendable as a tendon-transfer donor precisely because brachialis and biceps carry the flexion load.
Attachments, Innervation and Relations
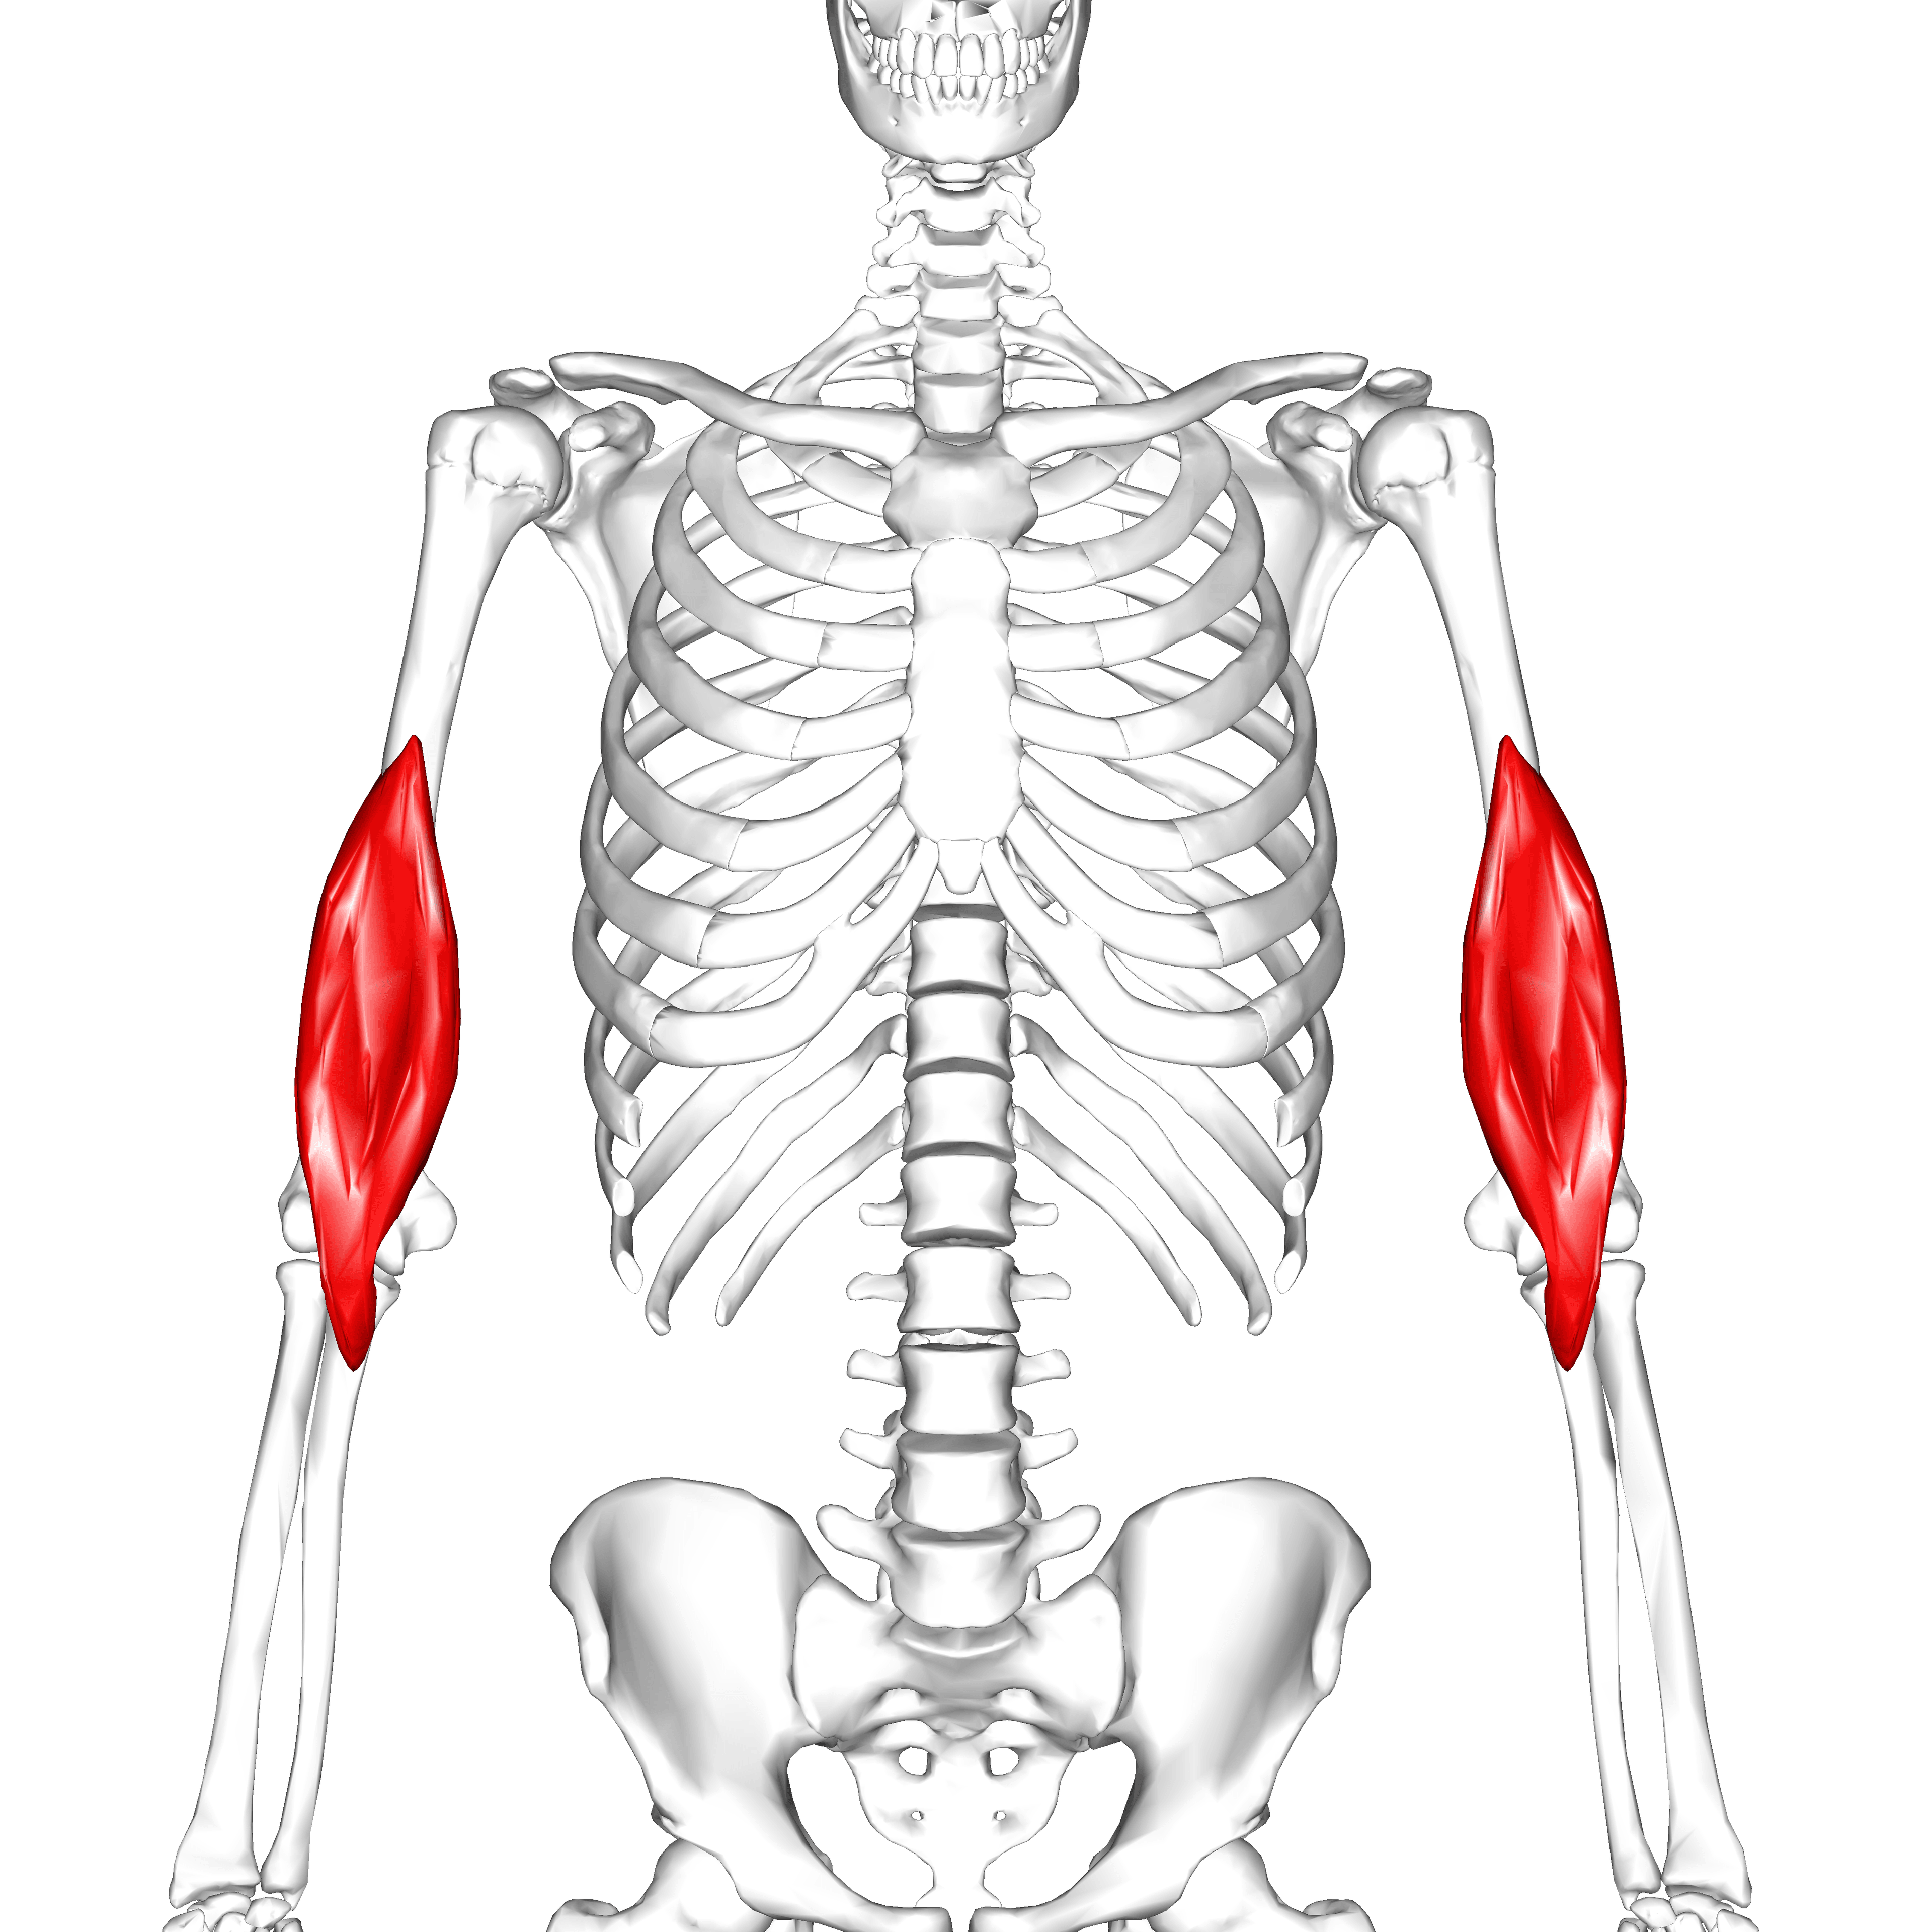
Origin. The distal half of the anterior surface of the humerus, from about the level of the deltoid insertion to within 2 cm of the joint line. The origin has two limbs that embrace the deltoid tuberosity in a V shape, a reliable landmark when working proximally in an anterior approach, and fibres arise from the medial and lateral intermuscular septa as well. The lateral septal origin is what brings the muscle into contact with the radial nerve where the nerve pierces that septum.
Two heads. Leonello and colleagues found two heads in every specimen they dissected, and the difference between them is mechanical rather than decorative.
- Superficial head — the larger. A more proximal origin on the anterolateral humerus, longitudinal fibres, and a thick round tendon onto the ulnar tuberosity. The long origin and distal insertion give it the bulk of flexion strength
- Deep head — smaller and fan-shaped, with oblique fibres converging into an aponeurosis onto the coronoid process, more anteriorly. Better placed to initiate flexion from full extension
- The two are separable by blunt dissection, which is what makes the superficial head tendon available as a local graft
Insertion. The tendon of the superficial head takes the ulnar tuberosity and the aponeurosis of the deep head the coronoid process, with the footprint 1 to 2 cm distal to the coronoid tip, immediately anterior to the anterior band of the medial collateral ligament complex. The insertion is entirely on the ulna: there is no radial attachment, so the muscle contributes nothing to supination or pronation.
Action and Biomechanics
Primary action. Flexion of the elbow in the sagittal plane, and nothing else: no supination, no pronation, and no shoulder action, since the muscle does not cross the shoulder. Brachialis is short-fibred, pennate and high in cross-sectional area — high force over limited excursion — and its flexion moment arm peaks near 90 to 100 degrees of flexion.
Why brachialis, not biceps, is the prime flexor. Maximum force follows physiological cross-sectional area (PCSA), and brachialis has the largest PCSA of the elbow flexors, exceeding biceps brachii. Biceps inserts on the radial tuberosity, so pronating the forearm winds its tendon around the radius, shortens its flexion moment arm and costs it roughly a third of its flexion contribution in full pronation. Brachialis inserts on the ulna, which does not rotate, so its moment arm is unchanged by forearm rotation; in full pronation it is doing nearly all the work, and that is the physiological basis of testing it with the forearm fully pronated.
Brachioradialis, the third flexor. It has the longest flexion moment arm of the three because it inserts far distally on the radial styloid, but its small PCSA means it generates modest force — a distant third by force and first by moment arm. It works best as a rapid, high-excursion flexor in the mid-prone position, and as a shunt muscle resisting distraction of the joint.
- Nerve
- Musculocutaneous (+ radial)
- Insertion
- Ulnar tuberosity / coronoid
- Role in flexion
- Prime mover — largest PCSA
- Behaviour in pronation
- Unchanged
- Nerve
- Musculocutaneous
- Insertion
- Radial tuberosity
- Role in flexion
- Powerful flexor AND main supinator
- Behaviour in pronation
- Contribution falls markedly
- Nerve
- Radial
- Insertion
- Radial styloid
- Role in flexion
- Longest moment arm, modest force; shunt muscle
- Behaviour in pronation
- Most efficient in mid-prone
- Nerve
- Median
- Insertion
- Lateral radius mid-shaft
- Role in flexion
- Weak accessory flexor
- Behaviour in pronation
- Primary pronator
- Nerve
- Radial
- Insertion
- Olecranon
- Role in flexion
- Antagonists
- Behaviour in pronation
- Not affected
What happens when it fails. Isolated brachialis loss is rare and functionally subtle, because biceps compensates in supination and brachioradialis in mid-prone. A musculocutaneous palsy takes biceps and brachialis together and leaves flexion to brachioradialis alone: roughly 30 per cent of normal power, or MRC grade 3 against gravity only, and weakest in full supination. Supination is weak as well, and the lateral forearm is numb. A distal biceps rupture is the reverse case — brachialis remains, so flexion power falls by about 30 per cent while supination power falls by around 40 to 50 per cent, which is why supination weakness rather than flexion weakness drives the decision to repair.
Contracture. The muscle is a common site of shortening after prolonged immobilisation, and that myostatic component contributes to a fixed flexion deformity that will not resolve with capsular release alone.
Leonello and colleagues noted that the radial-innervated inferolateral fibres of the deep brachialis head run in a direction similar to the anconeus, so that the two muscles together form a muscular sling around the ulnohumeral joint — brachialis anterolaterally and anconeus posterolaterally, both radial-innervated, both spanning the joint obliquely.
The proposal is that this complex acts as a dynamic stabiliser of the ulnohumeral joint, resisting varus and posterolateral rotatory displacement. It is the anterior counterpart of the argument made for anconeus in posterolateral rotatory instability, and it explains why an oblique, radial-innervated slip of an otherwise sagittal-plane flexor exists at all.
Surface Anatomy and Examination
Palpation. Flex the elbow to 90 degrees with the forearm fully pronated and resist further flexion. Full pronation slackens the biceps and removes it from the picture, so the contractile bulk that remains on either side of the biceps tendon, particularly along the lateral border of the distal biceps, is brachialis. The most reliable point to feel it is the lateral aspect of the distal arm, just medial to the brachioradialis, 3 to 5 cm proximal to the elbow crease.
Isolation tests. The tests differ in which muscle they silence, and each has its own way of misleading you.
- How to perform
- Elbow 90 degrees, forearm FULLY pronated, resist flexion
- Positive finding
- Weakness relative to the supinated position
- What it means
- Brachialis (and brachioradialis) deficit; biceps contribution minimised in pronation
- False positives
- Pain inhibition; shoulder external rotation substitution
- How to perform
- Elbow 90 degrees, forearm supinated, resist flexion
- Positive finding
- Weakness with preserved pronated power
- What it means
- Biceps-dominant loss, e.g. distal biceps rupture with intact brachialis
- False positives
- Lacertus fibrosus intact masks the deficit
- How to perform
- Elbow 90 degrees, thumb up, resist flexion
- Positive finding
- Absent visible brachioradialis cord
- What it means
- Radial nerve lesion proximal to the brachioradialis branch
- False positives
- Obesity obscures the cord; test the other side
- How to perform
- Hook an index finger laterally under the distal biceps tendon with the elbow at 90 degrees and forearm supinated
- Positive finding
- No cord to hook
- What it means
- Complete distal biceps rupture
- False positives
- Lacertus fibrosus mistaken for the tendon — hook from LATERAL, not anterior
- How to perform
- Light touch over the lateral forearm distal to the elbow crease
- Positive finding
- Reduced or absent
- What it means
- Musculocutaneous nerve involvement (lateral cutaneous nerve of forearm)
- False positives
- Overlap with radial sensory territory at the margins
Pitfalls. Patients cheat by externally rotating the shoulder and using gravity, so stabilise the elbow against the trunk before grading anything. An intact lacertus fibrosus after a distal biceps rupture leaves flexion power looking normal and the muscle belly only mildly retracted, which is how the diagnosis is missed; this is why the hook test is performed from the lateral side. In acute trauma pain inhibition makes formal grading unreliable, and documenting sensation in the lateral forearm is the more useful record.
Examining for contracture. A fixed flexion deformity with a hard end-point suggests a bony block or capsular contracture, while a soft, springy end-point that improves with slow sustained stretch suggests myostatic brachialis shortening. A palpable hard mass in the antecubital fossa in the weeks after an elbow dislocation is heterotopic bone within brachialis until proven otherwise.
Complications
Denervation and donor morbidity. Splitting the muscle along the internervous line causes no functional deficit, which is the whole point of the plane. Splitting it transversely or too far laterally cuts the entering musculocutaneous twigs and denervates the medial portion, and the resulting flexion weakness is real but usually masked by biceps. Harvesting the superficial head tendon leaves the deep head still flexing, and the reported penalty is loss of terminal flexion power rather than of arc.
Post-operative stiffness. The single most common complication of any anterior elbow procedure, because the brachialis scars readily to the capsule. Mitigation is early active motion within 24 to 48 hours, continuous nerve blockade or good multimodal analgesia to allow it, and static progressive splinting rather than forceful passive stretching.
Clinical Relevance
The mechanism. Myositis ossificans of brachialis is the classic post-traumatic sequel of a simple elbow dislocation, and the route to it is direct: the dislocating coronoid tears through the muscle, producing an intramuscular haematoma against a periosteally stripped humerus. That haematoma ossifies.
Risk factors.
- Elbow fracture-dislocation rather than simple dislocation — heterotopic ossification was seen in 30 per cent of surgically treated elbow fracture-dislocations in a recent randomised trial, most commonly around the radial head
- Associated head injury or burns
- Repeated forceful passive stretching and vigorous early manipulation
- Delayed surgery through an already inflamed field
Course. Pain and a firm mass in the antecubital fossa at 2 to 6 weeks, radiographic flocculent calcification from about 3 to 4 weeks, and maturation with a peripheral cortical rim by 6 to 12 months.
Telling it from a sarcoma. Heterotopic ossification matures from the periphery inward — the zonal phenomenon, a mature cortical rim outside an immature centre — whereas a parosteal or extraskeletal osteosarcoma ossifies centrally first. Never biopsy an immature-looking calcifying mass in the antecubital fossa in the weeks after trauma: the histology looks alarmingly cellular, and misdiagnosis as sarcoma is a documented disaster.
Management. Active and active-assisted motion only, with no forced passive stretching, and static progressive or turnbuckle splinting for a fixed deformity. Excision waits until the bone is mature and motion has plateaued, traditionally 6 to 12 months, though contemporary practice increasingly excises earlier when the arc is functionally limiting and the bone is radiographically defined. Prophylaxis with indometacin or single-dose radiotherapy is used in high-risk cases, principally after excision.
Surgical Relevance
The interval. Proximally between the deltoid and pectoralis major, then between biceps medially and brachialis in the middle of the arm.
The split. Distally the brachialis is divided longitudinally in the line of its fibres, and this is the manoeuvre the approach turns on. Keep the lateral third with the radial nerve and the medial two-thirds with the musculocutaneous nerve: because these are separate nerve territories, splitting the muscle denervates nothing.
Structures at risk.
- Radial nerve laterally, in the brachialis-brachioradialis interval
- Musculocutaneous nerve in the biceps-brachialis plane, and its continuation as the lateral cutaneous nerve of the forearm emerging lateral to the biceps tendon at the elbow — the commonest sensory casualty of an over-enthusiastic distal extension
- Brachial artery and median nerve medially; retract the biceps and the bundle together, medially, as one unit
What the exposure gives. The entire anterior humeral shaft down to within 2 cm of the joint. It does not give good access to the posterior column of the distal humerus, for which a posterior approach is required.
The anterolateral variant. The interval here is brachialis medially against brachioradialis laterally, a true internervous plane between musculocutaneous and radial territory, and it is preferred for the distal third of the humeral shaft when the surgeon wants direct control of the radial nerve. That nerve lies in the interval and is identified and protected first.
Guidelines, Registries & Global Practice
Anatomical Variation Across Populations
- The two-headed configuration described by Leonello and colleagues was present in 100 per cent of an Australian cadaveric series; subsequent dissection studies in other populations have consistently described a bilaminar arrangement, though the degree of separability between the heads varies.
- The radial contribution to the deep head is reported as constant in the studies that specifically looked for it. Older anatomy texts that describe brachialis as purely musculocutaneous predate this work and should not be quoted in a viva.
- Reports of a brachialis accessorius or an anomalous slip crossing the median nerve or brachial artery exist but are rare; they are occasionally implicated in high median nerve or brachial artery entrapment.
Differences in Described Technique
- Position on brachialis handling
- Describes the anterolateral approach with a longitudinal brachialis split, noting the lateral third as radial-innervated and instructing the surgeon to identify the radial nerve in the brachialis-brachioradialis interval before lateral retraction.
- Position on brachialis handling
- Splits the brachialis in its midline distally; contemporary teaching refines this by keeping the split medial to the lateral third to respect the internervous boundary.
- Position on brachialis handling
- Universal agreement that brachialis is elevated off the capsule rather than divided, and that capsular EXCISION rather than incision is required.
- Position on brachialis handling
- Emphasises joint insufflation before portal placement, elbow flexion during anterior work, retractor use rather than suction, and awareness that the radial nerve is the closest structure to the anterolateral capsule.
Heterotopic Ossification Prophylaxis: Global Variation
- Indometacin (typically 25 mg three times daily for 2 to 6 weeks) is the most widely used pharmacological prophylaxis, and is the default in most European and Australasian units.
- Single-dose radiotherapy (commonly 7 Gy) is used more frequently in North American practice, particularly after excision of established heterotopic bone or in patients with a contraindication to non-steroidal anti-inflammatories.
- Neither is routinely given after a simple elbow dislocation; both are reserved for high-risk cases — associated head injury or burns, elbow fracture-dislocation, or after excision of established heterotopic bone.
- In limited-resource settings, where delayed presentation and prolonged immobilisation are common, myostatic brachialis contracture and heterotopic ossification are both more prevalent, and early active mobilisation programmes rather than pharmacological prophylaxis are the highest-yield intervention.
Rehabilitation Consensus
- There is broad international agreement that forced passive stretching of the post-traumatic elbow is harmful and that active, active-assisted and static progressive splinting protocols are preferred.
- Continuous passive motion after elbow contracture surgery has not been shown to improve final arc over a well-supervised active programme and is not universally adopted.
Related pages: Musculocutaneous Nerve Anatomy and Radial Nerve Anatomy are the two supplies that meet inside this muscle and make the longitudinal split possible; Brachioradialis Anatomy is the lateral neighbour that forms the interval in which the radial nerve is found, and the muscle to raise when the anterior elbow needs cover. Distal Biceps Rupture is why brachialis matters clinically — flexion is largely preserved because brachialis is intact, and supination is what is lost, since only biceps reaches the radius. Elbow Stiffness and Contracture is the condition in which the scarred brachialis is elevated off the capsule, and Heterotopic Ossification is what forms in the muscle belly after injury. Elbow Dislocations, Coronoid Fractures and Supracondylar Humerus Fracture are the injuries that tear or contuse it, the last being the classic paediatric setting for brachialis interposition. Humeral Shaft Fractures and Distal Humerus Fractures are the operations in which the muscle is split, with Median Nerve Anatomy naming the structure protected medially and Anconeus Anatomy the muscle with which the deep head's fibres form a sling around the ulnohumeral joint.
MCQ Practice Points
Q: Where does brachialis insert, and what does this exclude? A: The ulnar tuberosity and coronoid process. Because it takes no radial attachment it contributes nothing to supination or pronation — it is a pure elbow flexor.
Q: Which nerve, apart from the musculocutaneous, supplies brachialis? A: The radial nerve (C7), supplying the inferolateral fibres of the deep head — present in every specimen in the Leonello cadaveric series.
Q: What distinguishes the two heads of brachialis? A: Superficial head — larger, longitudinal fibres, thick round tendon, inserts on the ulnar tuberosity. Deep head — smaller, fan-shaped, aponeurotic, inserts on the coronoid.
Q: Why is brachialis rather than biceps the prime elbow flexor? A: Largest physiological cross-sectional area, plus a flexion moment arm that is independent of forearm rotation because the ulna does not rotate.
Q: In which interval is the radial nerve found in the distal arm? A: Between brachialis (medial) and brachioradialis (lateral). It crosses the lateral intermuscular septum a mean of 12 cm proximal to the olecranon fossa.
Q: What lies immediately deep to the distal brachialis? A: The anterior capsule of the elbow joint. This adherence is why brachialis is elevated, not divided, in anterior capsular release.
Q: In which muscle does myositis ossificans classically form after elbow dislocation? A: Brachialis — the coronoid tears through it, producing the intramuscular haematoma that ossifies.
Q: How does heterotopic ossification differ radiographically from extraskeletal osteosarcoma? A: Heterotopic ossification matures from the periphery inward (mature rim, immature centre); osteosarcoma ossifies centrally first.
Q: How do you isolate brachialis clinically? A: Resisted elbow flexion with the forearm fully pronated, which minimises the biceps contribution.
Q: Why is brachialis a poor muscle flap donor around the elbow? A: Segmental (Mathes-Nahai type IV) blood supply with no dominant pedicle. Use brachioradialis anteriorly or anconeus posteriorly instead.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A candidate is shown a prosection of the anterior arm. The examiner points at the brachialis and asks: what is its nerve supply, and why does the answer matter to you as a surgeon?”
“A 24-year-old sustained a simple posterior elbow dislocation, reduced in the emergency department six weeks ago. He returns with a hard, tender mass in the antecubital fossa and a fixed flexion deformity of 45 degrees. What is your diagnosis and how do you manage him?”
“You are performing an open release for a post-traumatic elbow contracture with a 50 degree fixed flexion deformity. Describe how you handle the brachialis and what you are protecting.”
Anatomy
- Origin: distal half anterior humerus, embracing deltoid insertion
- Two heads: superficial (round tendon, ulnar tuberosity), deep (aponeurosis, coronoid)
- Insertion entirely on the ULNA - no supination role
- Deep surface adherent to the anterior elbow capsule
Innervation
- Musculocutaneous C5, C6 - medial two-thirds
- Radial C7 - inferolateral fibres of deep head (constant)
- Internervous plane runs INSIDE the muscle
- Split medial to the lateral third
Biomechanics
- Largest PCSA of the elbow flexors - true prime mover
- Moment arm independent of forearm rotation
- Test in FULL PRONATION to isolate
- Musculocutaneous palsy: flexion drops to about grade 3 (brachioradialis)
Surgical Numbers
- Radial nerve crosses lateral septum: mean 12 cm proximal to olecranon fossa
- Median nerve and brachial artery: within 1 cm medial to brachialis border at joint line
- Radial nerve crosses posterior humerus 14.2 cm proximal to lateral epicondyle
- HO after operated elbow fracture-dislocation: about 30 per cent
Pathology
- Myositis ossificans - coronoid tears through the muscle
- Zonal phenomenon: mature rim outside, immature centre
- Myostatic contracture contributes to fixed flexion deformity
- Poor flap donor - type IV segmental supply
Evidence Base
Brachialis Muscle Anatomy: A Study in Cadavers
- Eleven cadaveric upper limbs dissected under loupe magnification
- The brachialis had TWO heads in every specimen: a larger superficial head with longitudinal fibres inserting by a thick round tendon on the ulnar tuberosity, and a smaller fan-shaped deep head inserting by aponeurosis onto the coronoid
- In every specimen a branch of the RADIAL nerve supplied the inferolateral fibres of the deep head, confirmed histologically
- The superficial head has a more proximal origin and more distal insertion, giving it the mechanical advantage for bulk flexion strength; the deep head is better placed to initiate flexion from full extension
- The radial-innervated deep-head fibres run in a direction similar to anconeus, forming a muscular sling around the ulnohumeral joint that may act as a dynamic stabiliser
Radial and Axillary Nerves: Anatomic Considerations for Humeral Fixation
- Fifty fresh human cadaveric upper extremities dissected to localise the radial and axillary nerves against bony landmarks
- The radial nerve crossed the lateral intermuscular septum a mean of 17 plus or minus 2.3 cm (range 13 to 22 cm) distal to the proximal humerus
- It lay a mean of 12 plus or minus 2.3 cm (range 7.4 to 16.6 cm) proximal to the olecranon fossa, approximating the midpoint of the bone
- The axillary nerve lay as close as 0.7 cm from the surgical neck, directly over the posterior cortex
- The radial nerve crosses the septum more proximally than generally taught, placing it at risk during implant insertion in the distal half of the humerus
Alternative Operative Exposures of the Posterior Humeral Diaphysis with Reference to the Radial Nerve
- Ten cadaveric specimens dissected to map the radial nerve against posterior humeral exposures
- The nerve crossed the posterior humerus from a mean of 20.7 cm proximal to the medial epicondyle to 14.2 cm proximal to the lateral epicondyle
- The standard triceps-splitting approach exposed a mean of 15.4 cm of humerus from the lateral epicondyle to where the nerve crossed
- Mobilising the nerve proximally added a further 6 cm of accessible diaphysis
- A modified posterior approach reflecting both the lateral and medial triceps heads medially after distal identification of the nerve exposed 26.2 cm of diaphysis
Tranexamic Acid and Heterotopic Ossification Formation Following Elbow Surgery
- Prospective randomised controlled trial of 47 patients undergoing surgery for acute traumatic elbow fracture-dislocation
- Heterotopic ossification occurred in 30 per cent of the whole cohort, most commonly around the radial head (71 per cent of cases)
- Clinically relevant heterotopic ossification led to reoperation in 14.3 per cent of the cohort overall
- Heterotopic ossification developed in 43.5 per cent of the tranexamic acid group versus 16.7 per cent of controls (relative risk 2.6), a difference that did not reach statistical significance in this sample
- Mean follow-up 12.9 months
Brachioradialis Muscle Flap: Clinical Anatomy and Use in Soft-Tissue Reconstruction of the Elbow
- Fifty-three upper extremities dissected to define the muscular and vascular anatomy of brachioradialis
- A consistent major pedicle was found near the elbow, arising in descending order of frequency from the radial recurrent, radial and brachial arteries
- Proximally pedicled, the distal muscle covered the elbow both anteriorly and posteriorly in every specimen
- Arc of rotation encompassed the distal half of the arm and the proximal two-thirds of the forearm, covering defects up to 3 cm
- No loss of upper extremity function and no need to sacrifice a major vessel