Massive Cuff Tear | Superior Migration | Acetabularization
- Pathophysiology: Loss of 'The Spacer' (Supraspinatus) and 'The Fulcrum' (Force Couples).
- Acetabularization of the acromion is the hallmark radiographic sign.
- Pseudoparalysis (less than 90 deg active elevation with full passive) is a key indication for Reverse TSA.
- Hemiarthroplasty is largely historical/salvage (CTA Head).
- Reverse TSA requires a functioning Deltoid and Axillary Nerve.
- “Look for the 'Popeye' deformity (Biceps rupture is common precursor).
- “Anterior-Superior Escape: Head palpable subcutaneously.
- “Hornblower's Sign (Teres Minor) predicts External Rotation outcome.
- “Fluid sign (Geyser sign) on AC joint.
- “Subscapularis failure leads to Anterior Escape.
- “Teres Minor failure leads to External Rotation deficit.
Overview and Epidemiology
Definition. Cuff tear arthropathy (CTA) is the end stage of a chronic massive rotator cuff tear. Loss of the cuff force couples lets the humeral head migrate superiorly, where it erodes the acromion into a socket (acetabularisation), rounds off the greater tuberosity (femoralisation) and finally destroys the glenohumeral joint. Neer first characterised it in 1983; the rapidly destructive, crystal-driven variant is the Milwaukee shoulder.
Who and how often. Typically the elderly, over 70 years, with a female predominance. Only a minority of massive cuff tears progress to true arthropathy, with an estimated prevalence of around 4% in cohorts over 70. Most massive tears remain functional through "suspension-bridge" compensation and never develop arthritis.
Mechanism. Two hits. The first is mechanical: the force couple and the superior stabiliser are lost, concavity compression goes with them, and without a fulcrum the head translates superiorly. The second is nutritional and inflammatory, as decreased synovial fluid and the release of basic calcium phosphate crystals contribute to cartilage loss.
Natural history. Progression is slow, over years. Pain and pseudoparalysis, not the radiographic grade alone, drive the decision to operate.
Anatomy and Biomechanics
The coracoacromial arch. With the cuff gone, the acromion and the coracoacromial (CA) ligament become the new weight-bearing roof of the shoulder and the last passive restraint holding the head down. Debridement or decompression in suspected CTA must preserve the CA ligament, and it is often preserved at hemiarthroplasty. At reverse arthroplasty it is usually released.
The glenoid can erode superiorly, the E2 pattern of the Favard classification.
Subscapularis and teres minor. Subscapularis is often intact in the early stages, but if it tears the head escapes anteriorly. Teres minor is critical for external rotation, and its state predicts external rotation after a reverse (see Investigations).
Neurovascular relations. Know where these lie before operating:
- Axillary nerve - runs 5cm distal to the acromion, through the quadrangular space with the posterior circumflex humeral artery
- Suprascapular nerve - passes through the suprascapular notch (under the transverse ligament) and the spinoglenoid notch; at risk during posterior glenoid retraction
- Cephalic vein - the primary landmark for the deltopectoral approach; preserving it reduces venous congestion
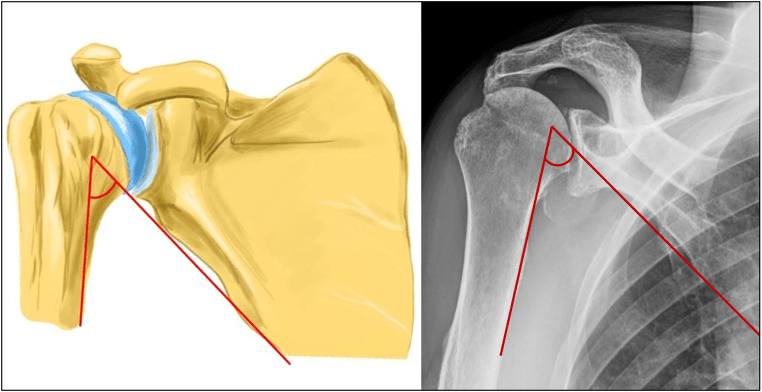
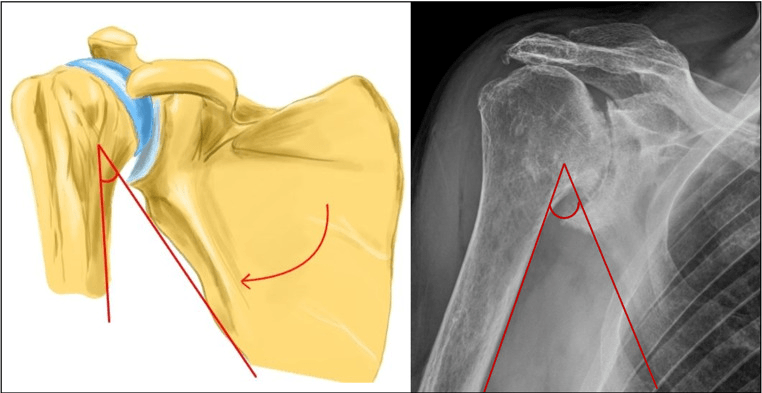
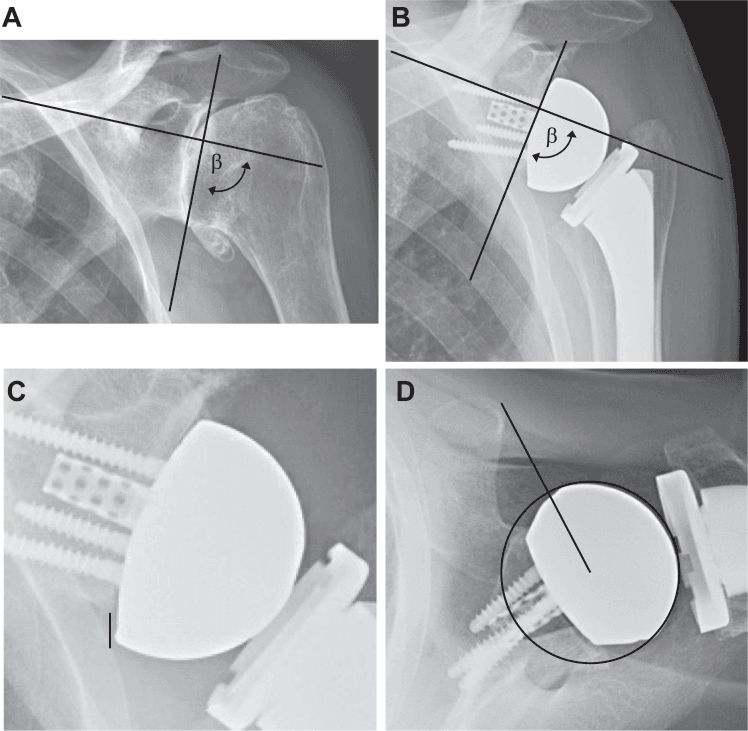
The scapulohumeral angle. The angle between the humeral shaft and the lateral border of the scapula. A centred head and a balanced cuff let the humerus elevate without excessive compensatory scapular rotation. In CTA, superior migration and loss of the glenohumeral fulcrum drive compensatory upward rotation of the scapula and the angle closes; after reverse arthroplasty the same geometry brings the humeral cup closer to the inferior scapular neck.
Classification Systems
Three systems, each answering a different question. Seebauer is functional, built on the centre of rotation and stability, and guides treatment. Hamada stages the radiographic progression of a massive cuff tear to CTA. Favard grades glenoid morphology in the cuff-deficient shoulder, and so dictates reaming strategy, the need for augments or bone graft, and baseplate seating.
- Features
- Head Centered, Minimal migration
- Stability
- Stable
- Treatment
- Hemi / Reverse
- Features
- Head Centered, Medialized glenoid
- Stability
- Stable
- Treatment
- Hemi / Reverse
- Features
- Head Migrated Superiorly
- Stability
- Stable (under arch)
- Treatment
- Reverse TSA
- Features
- Anterior-Superior Escape
- Stability
- Unstable
- Treatment
- Reverse TSA
Clinical Assessment
History. Night pain is prominent, and the patient cannot lift the arm. There is often a long history of shoulder trouble.
Examination. Look for supraspinatus and infraspinatus wasting and a "Popeye" muscle from biceps rupture. On movement, forward flexion is less than 90° (pseudoparalysis), and an anterolaterally escaped head shows as a palpable bulge. The lag signs map the cuff:
- External rotation lag sign - infraspinatus
- Hornblower's sign - teres minor
- Lift-off lag sign - subscapularis
The arm that will not lift. Three conditions share active elevation of less than 90°. Passive range separates stiffness from the other two, and the nerve separates cuff failure from paralysis:
- Pseudoparalysis - active elevation less than 90°, passive full, from cuff failure. Treated by reverse TSA.
- Pseudo-pseudoparalysis - active and passive both less than 90°, from stiffness or pain. Rehabilitation and conservative care first.
- True paralysis - active less than 90°, passive full, from nerve injury (axillary or suprascapular). Treated by tendon transfer.
Always document axillary nerve function (deltoid contraction). A reverse TSA relies entirely on the deltoid.
The high-riding head has a short differential:
- History
- Chronic pain, weakness
- Key Feature
- Arthritis + Cuff Tear
- Management
- Reverse TSA
- History
- Pain, preserved motion
- Key Feature
- Normal Joint Space
- Management
- Repair / SCR / Balloon
- History
- Trauma
- Key Feature
- No acromial wear
- Management
- Urgent Repair
- History
- Systemic disease
- Key Feature
- Central erosion
- Management
- Medical Mx / Arthroplasty
Anterosuperior Escape and the Escape Sign
Definition. Anterosuperior escape is dynamic anterosuperior subluxation of the humeral head out from under the CA arch during attempted elevation, so that the head becomes visible and palpable as a subcutaneous bulge beneath the anterolateral acromion. It reflects loss of the anterosuperior force couple, combined supraspinatus and subscapularis deficiency, together with an incompetent CA arch. It defines Seebauer 2B, and it changes management from optional to mandatory replacement.
The iatrogenic escape. Aggressive acromioplasty or division of the CA ligament in a shoulder with a massive tear can convert a contained, stable head into a fixed anterosuperior escape. That is the reason the CA ligament is preserved at debridement or decompression.
Once escape is established, hemiarthroplasty, arthroscopic debridement and isolated cuff procedures all fail because there is no stable fulcrum. Reverse TSA is the definitive solution: its semi-constrained, medialised and distalised design recreates a fixed fulcrum and lets the deltoid elevate a contained head.
Investigations
Radiographs. AP and axillary views. The changes progress systematically from early superior migration to late acetabularisation:
- Acromiohumeral interval (AHI) - less than 7mm suggests a massive tear; less than 5mm is diagnostic of an extensive tear
- Joint space - glenohumeral space is lost, superiorly first
- Femoralisation - rounding of the greater tuberosity
- Acetabularisation - concavity of the acromial undersurface
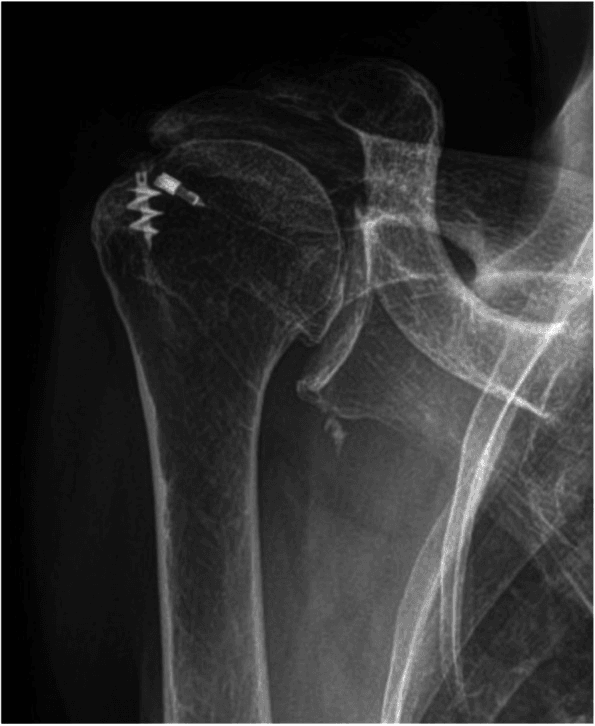
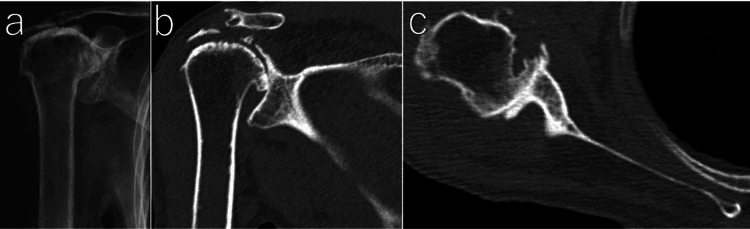
CT is the arthroplasty planning study. It shows glenoid bone stock, including screws or anchors left by previous surgery, and superior glenoid wear (the Favard E-types).
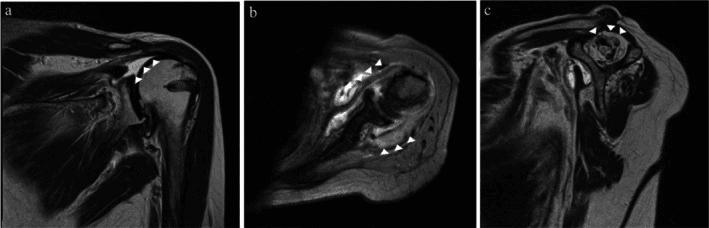
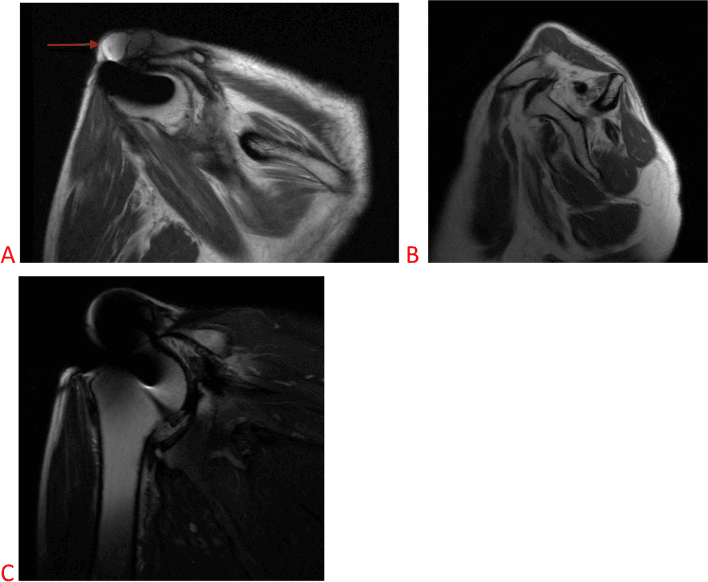
MRI is the gold standard for the engine of the shoulder, the muscles. Fatty infiltration is graded by Goutallier:
- Grade 0 - no fat
- Grade 1 - some fatty streaks
- Grade 2 - more muscle than fat (less than 50%)
- Grade 3 - equal muscle and fat (50%)
- Grade 4 - more fat than muscle (greater than 50%)
Grade 3 and 4 changes are irreversible. Repairing a cuff with grade 3 or 4 fat has a 90-100% failure rate.
Which scan the grade came from. Goutallier grading was devised and validated on CT, and Fuchs showed that agreement between CT and MRI grading is only fair to moderate. Record which modality a grade came from, and do not read an MRI grade against a CT-derived threshold. Grading is reproducible within a modality, which is why it remains usable.
Teres minor is the most critical structure to evaluate before a reverse TSA; look for it on the axial cuts. If it is absent, or fatty infiltrated to grade 3 or 4 (Hornblower's sign clinically), the patient will not have external rotation after a standard reverse. That is a specific indication for a latissimus dorsi transfer, which may be added.
Management
The decision. Always try a period of non-operative management first, unless there is anterior escape (Seebauer 2B), which is functionally debilitating.
Non-operative care suits the elderly, low-demand patient with a stable joint (Seebauer 1). Physiotherapy follows a deltoid re-education protocol that strengthens the anterior deltoid; rotator cuff strengthening is avoided, since the cuff is gone. Corticosteroid injection gives temporary pain relief. Many patients with Seebauer 1A or 1B do well with a low-demand adaptation.
Operative options.
- Indication
- Painful mild CTA, Good motion
- Pros
- Low morbidity
- Cons
- Unpredictable
- Indication
- Seebauer 1A (Historical)
- Pros
- Preserves bone
- Cons
- Unreliable pain relief
- Indication
- Pseudoparalysis, Seebauer 2, Failure of Non-op
- Pros
- Restores elevation
- Cons
- Complication risk
Hemiarthroplasty has no place with anterior escape (an incompetent coracoacromial arch), without static constraints, or in a high-demand patient who needs active elevation.
Reverse TSA Principles
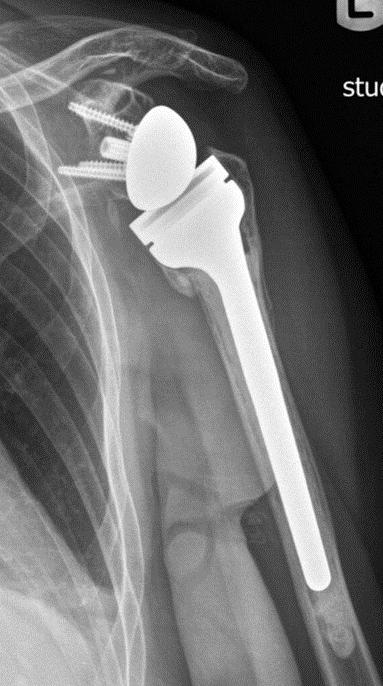
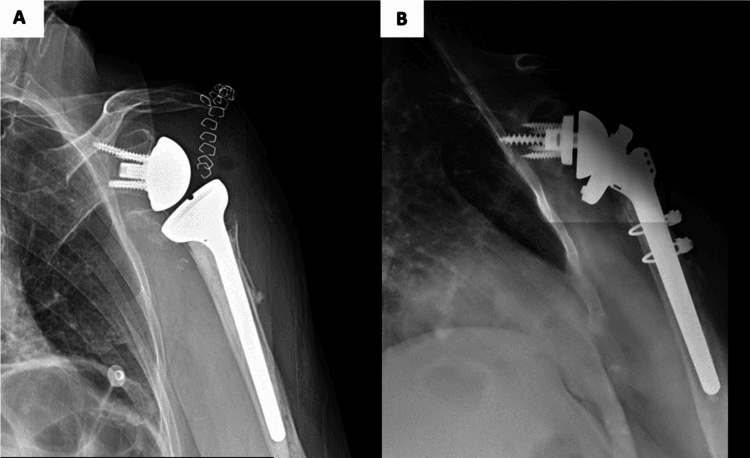
Reverse total shoulder arthroplasty (rTSA) is the workhorse for CTA. The Grammont-style reverse works through three changes:
- Medialisation of the centre of rotation increases the lever arm of the deltoid and recruits more fibres
- Distalisation of the centre of rotation retensions the deltoid
- Constraint - the semi-constrained design provides stability, replacing the function of the cuff
Indications
- CTA with pseudoparalysis
- Massive irreparable cuff tear
- Failed hemiarthroplasty or total arthroplasty
- Proximal humerus malunion or nonunion
Contraindications. The deltoid must work, its muscle quality must be adequate, and the glenoid must be able to support the baseplate:
- Deltoid paralysis (axillary nerve injury)
- Active infection
- Glenoid bone deficiency, unable to hold the baseplate screws
Surgical Technique
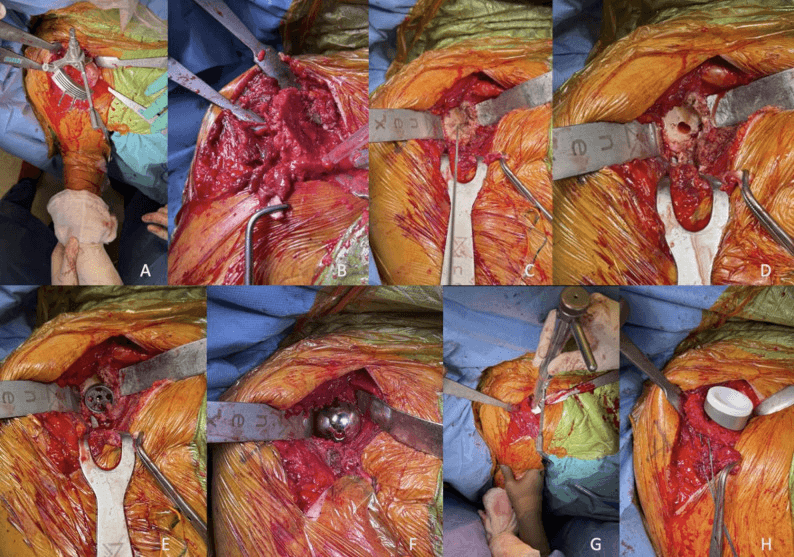
Deltopectoral approach. The standard. Preserve the deltoid insertion distally and protect the cephalic vein. The CA ligament is usually released (see Anatomy). Subscapularis is often contracted or torn, and is released or debrided; whether to repair it is discussed under Humerus and Trialling.

Complications
- Risk
- Common
- Mechanism
- Medial humeral cup hits scapula neck
- Prevention
- Lateralized glenosphere / Inverse graft
- Risk
- 1-3%
- Mechanism
- Overtensioning / Deltoid stress / Osteopenia
- Prevention
- Avoid lengthening arm too much
- Risk
- 3%
- Mechanism
- Undertensioning / Impingement
- Prevention
- Proper tensioning, larger glenosphere
- Risk
- Common
- Mechanism
- Arm lengthening traction
- Prevention
- Intra-op monitoring
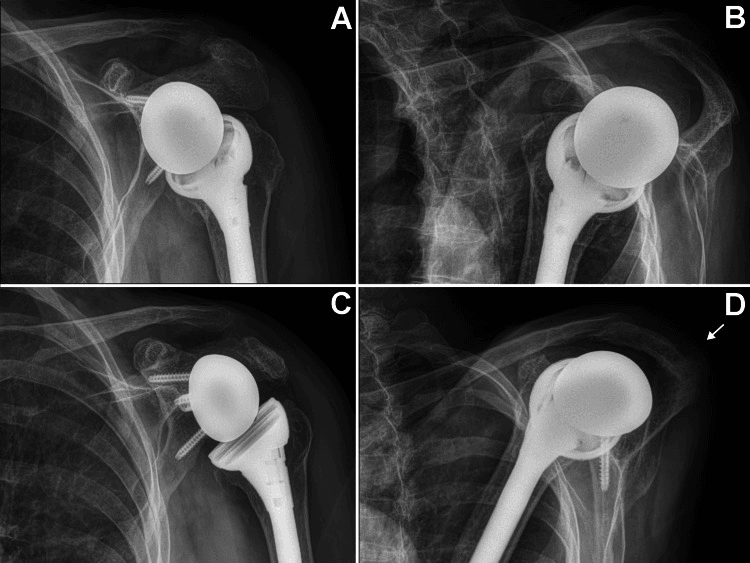
Scapular notching is unique to the reverse: the humeral cup abrades the inferior scapular neck during adduction. Sirveaux grades it by how far the defect has reached:
- Grade 1 - pillar only
- Grade 2 - contacting the lower screw
- Grade 3 - extending over the lower screw
- Grade 4 - extending to the central peg, threatening fixation
Preventing notching. Lateralisation is the most effective method, on the glenoid side (bony-metallic BIO-RSA, or metallic) or the humeral side (onlay or curved stems). Inferior overhang of the glenosphere prevents impingement in adduction, and inferior baseplate tilt reduces impingement. The neck-shaft angle matters too: the original Grammont 155° stem has a high rate of notching, and modern 135° inlay or onlay designs reduce it but increase shear force on the baseplate. No design has proven clearly superior in revision rates.
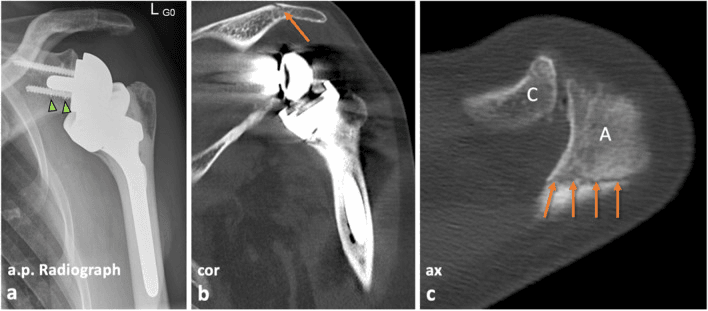
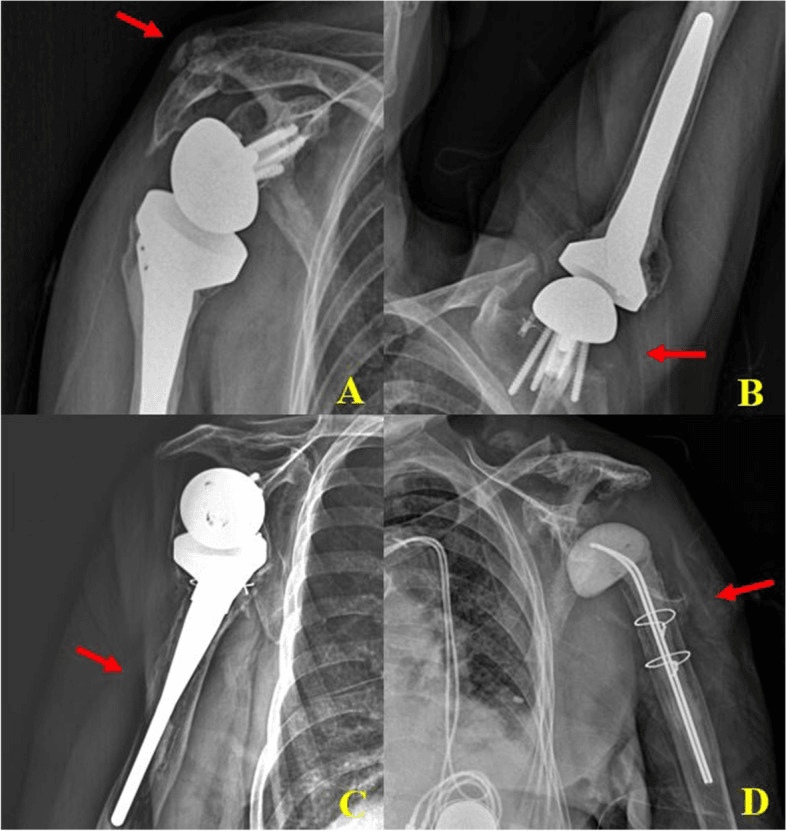
Acromial stress fracture. The deltoid is significantly tensioned, and in the elderly osteopenic patient that stress can fracture the acromion or scapular spine. The story is sudden pain after doing well for 3 months; radiographs might miss it, so scapular views or CT are needed. The consequence is catastrophic, because the deltoid origin becomes unstable and the reverse stops working. Treatment is conservative, with a high rate of nonunion; ORIF has a high failure rate.
Infection: the organism. Cutibacterium acnes is the causative organism in over 60% of shoulder periprosthetic joint infections. It is a slow-growing, Gram-positive, anaerobic bacillus, a skin commensal living in the sebaceous glands, which are dense in the shoulder region. Risk factors are male sex (more hair and sebum), younger age, prior surgery and topical steroids.
Presentation. Acute sepsis with fever and redness is rare. The typical picture is aggressive stiffness or unexplained pain after a period of doing well.
Diagnosis. ESR and CRP are often normal in C. acnes infection, and dry taps are common. Cultures must be held for a minimum of 14 days, up to 21. On frozen section, over 50 PMNs per high-power field is suggestive.
Management. DAIR (debridement) has a poor success rate for C. acnes and is considered only for acute haematogenous spread. Two-stage revision is the gold standard. Stage 1 is removal of all implants, thorough debridement and an antibiotic spacer (high-dose vancomycin/gentamicin), followed by six weeks of targeted antibiotics, often including rifampicin for biofilm. Stage 2 is reimplantation after an antibiotic holiday and a negative rescreen.
Neurological injury. The axillary nerve is most at risk, during the inferior capsular release or from traction, and injury presents as deltoid paralysis. Most are neurapraxias that resolve. Identify the nerve, and keep the arm adducted while releasing inferiorly.
Postoperative Care
Rehab Protocol
A sling for comfort and protection, usually for 4 weeks. Passive supine elevation to 90° is allowed immediately, and passive external rotation to neutral (0°). Hand-to-mouth activities such as eating and drinking are encouraged to prevent stiffness.
- No extension - extension coupled with adduction and internal rotation (reaching for the back pocket) is the position of dislocation
- No active elevation - protects the deltoid and any subscapularis repair
Wean the sling during the day and begin active assisted motion with pulleys and stick exercises. Deltoid recruitment starts with supine active forward elevation, gravity eliminated, and progresses to standing as deltoid control improves. Hydrotherapy is excellent for deltoid activation without gravity.
Progressive resistance bands (Therabands) for the deltoid, and strengthening of the scapular stabilisers (rhomboids and trapezius), with return to full activities of daily living. Golf and swimming (breaststroke) are often tolerated; overhead sports such as the tennis serve are generally discouraged.
Repetitive overhead lifting is generally restricted to under 5-10kg. Joint position sense is altered, because there is no cuff.
Outcomes and Prognosis
Across landmark series, reverse TSA reliably converts a painful pseudoparalytic shoulder into a functional, pain-free one, with Constant scores roughly doubling (Sirveaux 22.6 to 65.6; Wall 23 to 60).
Elevation is restored reliably, to over 130°; expect about 140°. Rapid fatigue with overhead activity is common, due to deltoid fatigue.
Rotation. External rotation is often not restored (0-10°) unless teres minor is intact or a latissimus dorsi transfer is done. Patients can feed themselves and reach the top of the head, but reaching up the back (internal rotation) is limited.
Guidelines, Registries & Global Practice
Global registry trends. National joint registries worldwide (AOANJRR in Australia, NJR in England/Wales, the New Zealand Joint Registry, and Nordic registries) document the same shift: reverse TSA has overtaken hemiarthroplasty and anatomic TSA for the cuff-deficient shoulder and now accounts for the majority of all shoulder replacements in most developed health systems. Hemiarthroplasty for cuff deficiency has been largely abandoned because of unreliable pain relief and superior migration.
- Position on CTA Management
- Reverse TSA recommended for CTA with pseudoparalysis; cuff repair not indicated once arthropathy is established.
- Position on CTA Management
- Reverse TSA is the procedure of choice for symptomatic CTA; emphasises deltoid/axillary nerve integrity.
- Position on CTA Management
- Reverse TSA the dominant implant for CTA; lower revision than hemiarthroplasty for the same diagnosis.
- Position on CTA Management
- Lateralized designs and inferior glenosphere placement to reduce notching; teres minor assessment before surgery.
Revision and survivorship (registry-level).
- Primary reverse TSA shows roughly 90-95% survivorship at 10 years across large registries.
- Leading reasons for revision: infection (often the commonest early cause), instability/dislocation, and periprosthetic/acromial fracture.
- For an elderly primary CTA patient the lifetime risk of revision is low, so the implant typically outlasts the patient.
Implant and fixation notes.
- Metal-backed (screw-fixed) baseplates are standard for the reverse glenoid, in contrast to the cemented all-polyethylene glenoid used in anatomic TSA (where metal-backed designs failed early).
- Registries show no consistent difference between cemented and uncemented humeral stems for reverse TSA; modern uncemented HA-coated stems perform well.
Surgeon volume. A consistent volume-outcome relationship exists across registries: low-volume surgeons (broadly fewer than ~10 shoulder arthroplasties/year) have higher revision rates. Shoulder arthroplasty is increasingly a subspecialty procedure.
High- vs limited-resource practice variation.
- High-resource settings: ready access to reverse implants, CT-based planning, navigation/patient-specific instrumentation (used in a substantial minority of cases to reduce glenoid-placement outliers), and stemless/short-stem options (faster uptake in Europe).
- Limited-resource settings: reverse implants may be unavailable or unaffordable; arthroscopic debridement, biceps tenotomy, partial cuff repair, or even glenohumeral arthrodesis remain pragmatic salvage options for pain in the cuff-deficient arthritic shoulder.
Related pages: Reverse Total Shoulder Arthroplasty is the operation this diagnosis leads to and carries the implant design, notching and survivorship detail in full - including the point that ten-year survival exceeds 90 percent for the IMPLANT and was 58 percent for FUNCTION in the same cohort; Massive Rotator Cuff Tears for the stage before arthropathy, where repair, debridement and transfer are still on the table; Rotator Cuff Tears for the tear patterns and the reparability judgement that decides whether a patient ever reaches this page; Subscapularis Tears for the anterior structure whose loss produces anterosuperior escape and contraindicates hemiarthroplasty; Total Shoulder Arthroplasty (Anatomic) for the alternative that requires a competent cuff and fails by rocking-horse glenoid loosening without one; Shoulder Arthroplasty Complications for instability, infection and the acromial fracture carded above; and Latissimus Dorsi Anatomy for the muscle transferred when a reverse cannot restore external rotation in the teres-minor-deficient shoulder.
Controversies and Areas of Uncertainty
Medialised or lateralised. Grammont medialisation limits rotation and raises notching; lateralisation improves rotation and contour at the cost of more baseplate torque when it is metallic. Boileau's BIO-RSA argues that bony lateralisation keeps the centre of rotation at the bone interface and so avoids that added torque, a biomechanical argument rather than a measured clinical comparison. The optimal degree of global lateralisation and distalisation is still debated.
The younger, active patient. Reverse TSA for the cuff-deficient shoulder under about 60 years remains contentious, given finite implant longevity and higher demand. Joint-preserving options are weighed first: debridement, partial repair, superior capsular reconstruction, and lower trapezius or latissimus dorsi transfer.
Pseudoparalysis or pseudoparesis. The literature inconsistently defines pseudoparalysis (truly less than 90°) against pseudoparesis (weak, but greater than 90°), which confounds comparison of joint-preserving and replacement outcomes.
Navigation and stemless stems. Whether navigation or patient-specific instrumentation reduces glenoid-placement outliers enough to lower long-term loosening, and how durable stemless reverse humeral components are, await mature registry data.
MCQ Practice Points
Q: What is the primary mechanical deficit in CTA? A: Loss of the Force Couple (Concavity Compression) and upward migration of the humeral head due to unopposed Deltoid pull.
Q: What distinguishes Seebauer 2A from 2B? A: Anterior instability. 2A is centered superiorly (stable under arch). 2B escapes antero-superiorly (unstable).
Q: How does a Reverse TSA improve elevation? A: It Medializes the center of rotation (recruiting more deltoid fibers) & Distalizes the humerus (tensioning the deltoid).
Q: What is the most common complication of Grammont style Reverse TSA? A: Scapular Notching. (Though modern lateralized designs have reduced this).
Q: Which nerve must be functioning for a Reverse TSA? A: Axillary Nerve (Deltoid function). Without deltoid, the prosthesis won't work.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 75F had a Hemiarthroplasty for a fracture 2 years ago. Now has pain and cannot lift arm above 40 degrees. X-ray shows superior escape of the prosthesis.”
“You perform a Reverse TSA on a 70M. Post-op, he has 140 elevation but cannot externally rotate (ER is -10). He is unhappy (cannot eat with fork, comb hair). Why?”
“Differentiate Pseudoparalysis from True Paralysis from Stiffness.”
Diagnosis
- Pseudoparalysis
- High riding head
- Acetabularization
- Fluid Sign
- Hornblower's Sign
Classification
- Hamada (X-ray severity)
- Seebauer Type 1 (Stable)
- Seebauer Type 2 (Unstable/Escape)
- Favard (E-type glenoid)
Management
- Non-op (Physio/Inject) for low demand
- Reverse TSA (Gold Standard)
- Hemi (Historical)
- Arthrodesis (Salvage)
Reverse Biomechanics
- Medialize COR
- Lengthen Deltoid Lever
- Distalize Humerus
- Semi-constrained
- Recruit ant/post deltoid
Complications
- Scapular Notching
- Acromial Fracture
- Dislocation
- Infection
- Neuroapraxia
Evidence Base
Grammont Reverse Principles
- Medializing the centre of rotation increases the deltoid lever arm and recruits more fibres.
- Distalizing the humerus tensions the deltoid.
- A fixed, semi-constrained fulcrum lets the deltoid substitute for the absent cuff.
Reverse TSA Results by Etiology
- Mean Constant score improved from 23 to 60 points; 173 of 186 patients satisfied or very satisfied.
- Best results in primary cuff tear arthropathy, OA with cuff tear, and massive cuff tear.
- Posttraumatic and revision cases had less improvement and higher complication rates.
Grammont Inverted Prosthesis for CTA (Landmark Series)
- Mean Constant score improved from 22.6 to 65.6; active forward elevation rose from 73 to 138 degrees.
- Integrity of teres minor was essential for recovery of external rotation and significantly influenced Constant score.
- Glenoid loosening/component dissociation noted; recommended for elderly low-demand patients.
BIO-RSA (Bony Increased-Offset Lateralization)
- Autologous humeral-head bone graft behind the baseplate incorporated in 98% of cases.
- Inferior scapular notching in only 19%; Constant score improved from 31 to 67.
- Bony lateralization keeps the centre of rotation at the bone interface, avoiding the added torque of metallic lateralization.
Hemiarthroplasty vs Reverse for CTA
- New Zealand Joint Registry pairs matched for age, sex and ASA.
- Mean 6-month Oxford Shoulder Score 37.5 (reverse) vs 31.1 (hemiarthroplasty).
- Fewer revisions in the reverse group (5 vs 9).
Goutallier Fatty Degeneration (CT vs MRI)
- Interobserver reproducibility of fatty-degeneration grading was good-to-excellent on both CT and MRI, taken separately
- BUT the correlation BETWEEN MRI and CT was only fair to moderate and, in the authors' words, remained UNSATISFACTORY
- Simplifying the original 5-grade scale to 3 grades did not rescue the agreement - it remained unsatisfactory
- Degree of fatty degeneration correlated significantly with muscle atrophy of the same muscle
Scapular/Acromial Fractures after RTSA
- Osteoporosis was a significant risk factor (odds ratio 1.97).
- Plain radiographs detected only 78.8% of fractures; advanced imaging often required.
- 14 of 16 scapular-spine fractures originated at a screw tip; the proposed (Crosby) classification had only moderate reliability.