Vitamin C Deficiency | Collagen Synthesis Failure | Paediatric Metabolic Bone Disease
- Scurvy = Vitamin C deficiency causing failure of collagen cross-linking (hydroxylation of proline and lysine)
- Subperiosteal haemorrhage is the hallmark orthopaedic manifestation - causes severe pain and pseudoparalysis
- Radiographic constellation: Frankel line, Trummerfeld zone, Wimberger ring - highly characteristic together, but no single sign is pathognomonic (dense metaphyseal bands also occur in lead poisoning, healing rickets, treated leukaemia and hypervitaminosis D)
- Corner sign and Pelkan spurs mimic metaphyseal fractures of NAI - CRITICAL differential diagnosis
- Treatment: Vitamin C 200-500 mg daily - dramatic improvement within 1-2 weeks
- “Scurvy causes failure of collagen TYPE I synthesis (requires vitamin C for proline/lysine hydroxylation)
- “Pseudoparalysis in scurvy = painful subperiosteal haemorrhage, NOT neurological deficit
- “Unlike rickets (growth plate disorder), scurvy affects OSTEOID formation and vessel integrity
- “Frankel line is DENSE (hypermineralised) because cartilage calcifies but cannot be resorbed - opposite to rachitic changes
Overview and Definition
Scurvy is a systemic disease caused by severe vitamin C (ascorbic acid) deficiency. Collagen synthesis fails, with widespread musculoskeletal, vascular and connective tissue manifestations. In children the orthopaedic picture is particularly striking: subperiosteal haemorrhage, pseudoparalysis and characteristic radiographic changes that must be distinguished from non-accidental injury.
History. James Lind described it in sailors in 1753 and found citrus fruit curative. Sir Thomas Barlow described the infantile form, Barlow disease, in 1883.
Incidence. Scurvy in developed countries is rare but not extinct, and no reliable incidence figure exists. It is diagnosed only when someone thinks to send an ascorbic acid level, so every published rate is a rate of diagnosis, not of disease, and the case-report literature is the literature. Treat any precise incidence quoted for scurvy with suspicion.
Case reports and series have increased over the last two decades. That reflects both genuine re-emergence in restrictive-eating children and increased awareness after the first autism-related series were published.
Who gets it. The high-risk groups:
- Autism spectrum disorder, with restrictive eating patterns and food texture aversions: the commonest setting in paediatric orthopaedic and rheumatology series
- Developmental delay with sensory processing disorders and limited food acceptance
- Neglected or abused children
- Prolonged exclusive breastfeeding without supplementation beyond 6 months, or prolonged exclusive milk feeding in a toddler whose diet has no fruit or vegetables
- Bottle-fed infants given boiled or pasteurised milk: vitamin C is heat-labile and is destroyed by prolonged boiling
- Gastrointestinal disorders: malabsorption, short gut syndrome
- Cerebral palsy on restricted diets, or tube feeds without vitamin C
- Food fad or junk food diets, and diets imposed by parents (alternative medicine, extreme veganism without supplementation)
- Transfusion-dependent iron overload in sickle cell disease or thalassaemia: iron overload consumes ascorbate
- Oncology and post-transplant children: chemotherapy, bone-marrow transplant, prolonged poor intake and mucositis
- Long-term parenteral nutrition or unsupplemented enteral feeds
Which cause is commonest depends on where you look. The evidence disagrees. Ma (Boston) and Perkins (Seattle) describe autism and developmental delay as the dominant setting, 8 of 10 in Perkins' rheumatology referrals. Golriz reviewed 32 biochemically confirmed cases at a large Texas children's hospital and found the commonest underlying condition was iron overload from repeated transfusion for sickle cell disease or thalassaemia (20 of 32), with neurological disorders in 4 and chemotherapy or bone-marrow transplant in 3. Golriz identified no cases at all from dietary deficiency in otherwise-well children.
The two findings are a lesson in referral filter more than a contradiction. A rheumatology or orthopaedic clinic sees the child who limps, and that child usually has a restrictive diet. A laboratory audit of everyone tested captures the transfusion-dependent and oncology populations, who are tested for other reasons. Both lists matter, and the transfusion and oncology group is the one most often missing from teaching.
How long it takes. Symptoms require sustained near-total deprivation, conventionally at least 1 to 3 months of a vitamin C-free diet, since the body pool must fall substantially before collagen synthesis fails. Fatigue and malaise come at 4-12 weeks of deficiency and full clinical scurvy at 12-20 weeks. Symptoms develop faster in children than in adults.
Pathophysiology
Collagen synthesis. Vitamin C acts at the two hydroxylation steps:
- Procollagen synthesis in the ribosome: pro-alpha chains containing proline and lysine
- Hydroxylation of proline to hydroxyproline, by prolyl hydroxylase
- Hydroxylation of lysine to hydroxylysine, by lysyl hydroxylase
- Triple helix formation, stabilised by hydrogen bonds involving hydroxyproline
- Secretion and cleavage of the propeptides
- Cross-linking by lysyl oxidase, which is copper-dependent, not vitamin C-dependent
What vitamin C does. It is an essential cofactor for prolyl hydroxylase and lysyl hydroxylase, keeping iron in the ferrous (Fe2+) state at the enzyme's active site. Without it the iron oxidises to Fe3+ and the enzymes become inactive. The result is underhydroxylated collagen that cannot form stable triple helices, and weak, defective connective tissue.
What fails. Type I collagen is the most affected: bone matrix, where it makes up 90% of the organic bone, tendons and ligaments, the dermis, blood vessel walls and dentin. That accounts for both halves of the disease, musculoskeletal and vascular:
- Osteoid matrix defects: impaired bone formation
- Vascular fragility: weakness of the capillary basement membrane
- Impaired wound healing: fibroblasts cannot produce functional collagen
- Connective tissue weakness in tendons, ligaments and gingiva
Iron. Vitamin C also enhances absorption of non-haem iron (reducing Fe3+ to Fe2+) and mobilises iron from stores. Scurvy therefore causes iron deficiency, which explains the concurrent anaemia.
Bone. Rickets is a failure of mineralisation; scurvy is a failure of osteoid production itself. Osteoblasts cannot synthesise stable type I collagen, so the osteoid matrix is deficient and structurally weak. Remodelling is impaired because old bone cannot be replaced, and generalised osteopenia develops.
The growth plate. Here scurvy differs fundamentally from rickets, and the radiographic signs follow step by step:
- Cartilage proliferation and calcification proceed normally, because they do not need vitamin C
- The zone of provisional calcification becomes hyperdense: the Frankel line
- Resorption of the calcified cartilage fails, since it requires functional osteoclasts with vascular invasion
- Primary spongiosa does not form properly, for want of functional osteoid
- Microfractures occur in the transition zone: the Trümmerfeld zone
- The metaphyseal corners weaken and fracture: the corner sign and Pelkan spurs
The vessels. Capillary fragility is central to the orthopaedic manifestations:
- Subperiosteal haemorrhage: blood accumulates beneath the periosteum
- Metaphyseal haemorrhage at the bone-cartilage junction
- Muscle haematomas, with painful swelling of the limbs
- Periosteal elevation, where massive haemorrhage lifts the periosteum from the cortex
Clinical Presentation
Subperiosteal haemorrhage. The hallmark orthopaedic finding, most common in the lower limbs at the distal femur and proximal tibia. It presents as painful swelling with exquisite tenderness: a firm, warm swelling over the metaphysis that may be mistaken for cellulitis. It mimics infection (osteomyelitis), malignancy (neuroblastoma metastases) and trauma.
Pain and pseudoparalysis. The bone pain is severe and diffuse, especially in the lower limbs. The child screams when handled (the "scorbutic cry") and is reluctant to walk or crawl. Pseudoparalysis is the refusal to move a painful limb, and the child may lie in the frog-leg position, hips flexed and externally rotated.
Pseudoparalysis in scurvy is due to pain avoidance, not neurological deficit. The child has full motor function but refuses to move due to severe pain from subperiosteal haemorrhage. Deep tendon reflexes are preserved. This distinguishes scurvy from polio, Guillain-Barre, and spinal pathology.
Fractures. These occur with minimal or no trauma:
- Metaphyseal corner fractures (the corner sign)
- Epiphyseal separation through the weakened zone
- Rib fractures, from fragility of the costochondral junction
Joints and muscle. Bleeding into the joint produces haemarthrosis, and the muscles weaken and atrophy.
Gums. Swollen, spongy, bluish-red gums that bleed spontaneously or with brushing, and teeth that loosen with loss of alveolar bone. Gingival changes are present only once teeth have erupted, so they are absent in infants.
Skin. The capillary weakness shows as:
- Petechiae, especially on the lower limbs, and purpura
- Ecchymoses, bruising with minimal trauma
- Perifollicular haemorrhages
- Corkscrew hairs: coiled, brittle hairs from abnormal keratin, pathognomonic
- Hyperkeratosis with follicular plugging, and dry, rough skin
Wounds heal poorly, old scars dehisce and recovery from injury is slow. Conjunctival haemorrhage and epistaxis also occur.
Constitutional features. Malaise and fatigue are often the first symptoms. Irritability is marked in children, and anorexia brings poor appetite and failure to thrive. A low-grade fever may suggest infection.
Blood and circulation. The anaemia is usually normocytic and may be macrocytic, with iron deficiency from impaired absorption and folate deficiency, since vitamin C protects folate. It brings pallor and tachycardia. Dyspnoea on exertion, cardiac enlargement (rare in children) and hypotension in severe cases complete the picture.
Age. Presentation peaks at 6-24 months, and the picture changes with age:
- Infants (6-12 months), Barlow disease: the historical peak, in the weaning period. Irritability, failure to thrive, the frog-leg posture ("pithed frog" position), lower limb swelling from subperiosteal haemorrhage, pseudoparalysis with refusal to move the legs, and a costochondral rosary similar to that of rickets
- Toddlers (1-3 years): refusal to walk in a child who was previously walking, limping or refusing to bear weight, leg pain and swelling, easy bruising, and gingival changes once teeth have erupted
- Older children: a presentation similar to adults, with joint pain and swelling, gingival bleeding and poor wound healing; there may be an underlying restrictive eating disorder
Investigations
Blood tests. A serum ascorbic acid below 11 micromol/L (0.2 mg/dL) confirms deficiency. Leukocyte vitamin C reflects tissue stores better but is rarely available. The bone biochemistry is what separates scurvy from rickets:
- Scurvy
- Very low
- Rickets
- Normal
- NAI
- Normal
- Scurvy
- Normal
- Rickets
- Low
- NAI
- Normal
- Scurvy
- Normal
- Rickets
- Low-normal
- NAI
- Normal
- Scurvy
- Normal
- Rickets
- Low
- NAI
- Normal
- Scurvy
- Normal or mildly elevated
- Rickets
- Very high
- NAI
- Normal
- Scurvy
- Normal
- Rickets
- Elevated
- NAI
- Normal
- Scurvy
- Anaemia (normocytic or macrocytic)
- Rickets
- May have anaemia
- NAI
- Normal
Inflammatory markers (CRP and ESR) may be elevated. That does not exclude scurvy, and it can mislead towards sepsis or rheumatic disease. In a restricted diet, screen for concurrent deficiencies of iron and folate.
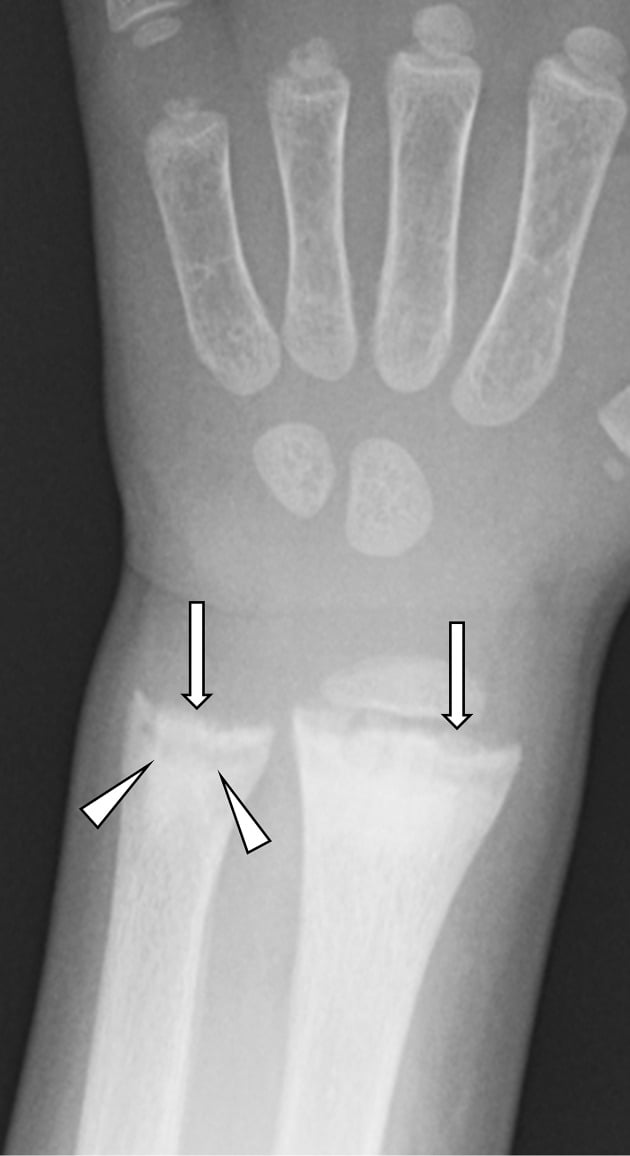
Radiographs. Knee films (AP and lateral) are the most sensitive, with the wrists (distal radius and ulna) and chest (costochondral junctions) as useful adjuncts. The constellation is highly characteristic, but no single sign is pathognomonic: dense metaphyseal bands also occur in lead poisoning, healing rickets, treated leukaemia and hypervitaminosis D.
- Appearance
- Dense white transverse metaphyseal line (hyperdense ZPC)
- Significance
- Characteristic, though a dense band alone is not specific; the opposite of the rachitic metaphysis
- Appearance
- Lucent "rubble" band beneath the Frankel line
- Significance
- Microfractures/debris - site of epiphyseal separation
- Appearance
- Dense epiphyseal rim with osteopenic centre
- Significance
- Not the Wimberger sign of congenital syphilis (see Differential Diagnosis)
- Appearance
- Lateral metaphyseal corner defects or spurs
- Significance
- Mimic the classic metaphyseal lesions of NAI - but bilateral and symmetric in scurvy
- Appearance
- Ground-glass bone, pencil-thin cortices
- Significance
- Defective osteoid throughout the skeleton
- Appearance
- Calcified subperiosteal haematoma
- Significance
- Healing-phase finding; can look alarming but resolves
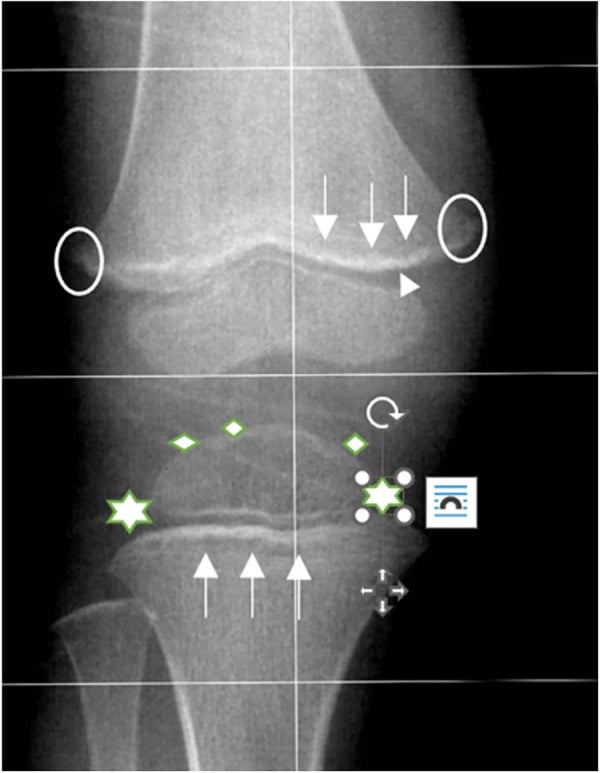
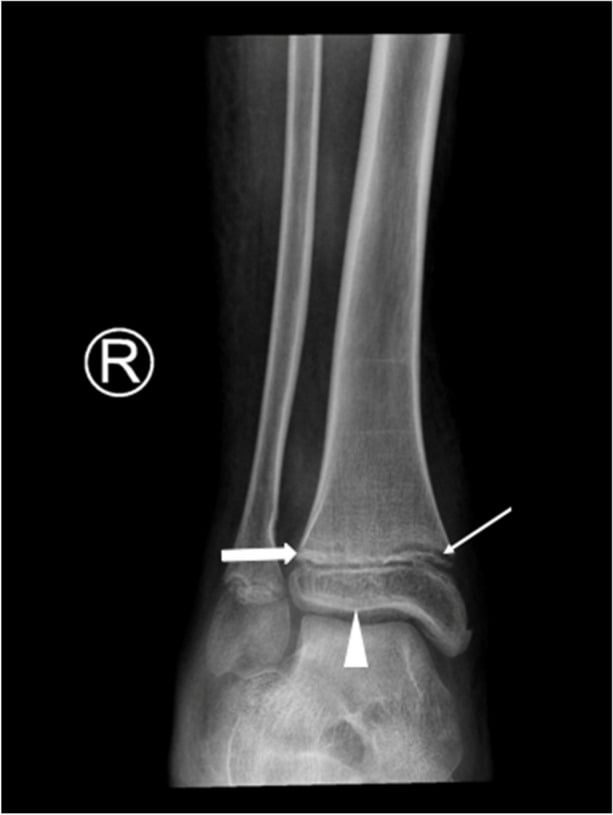
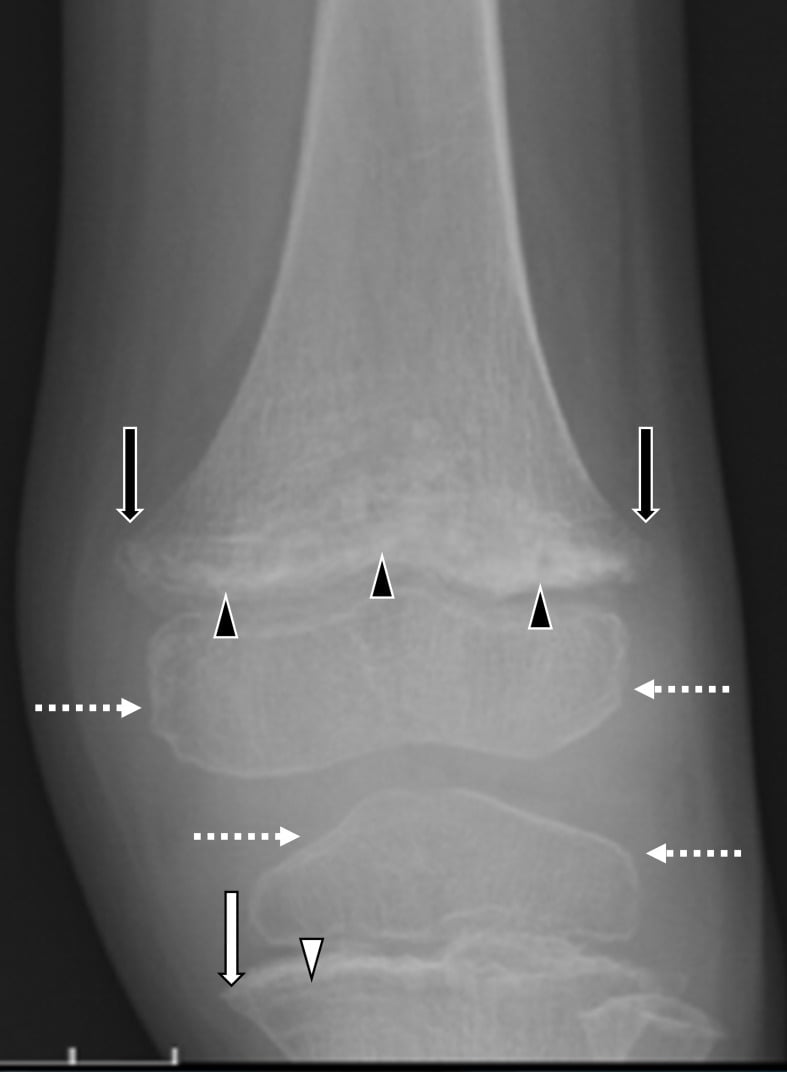
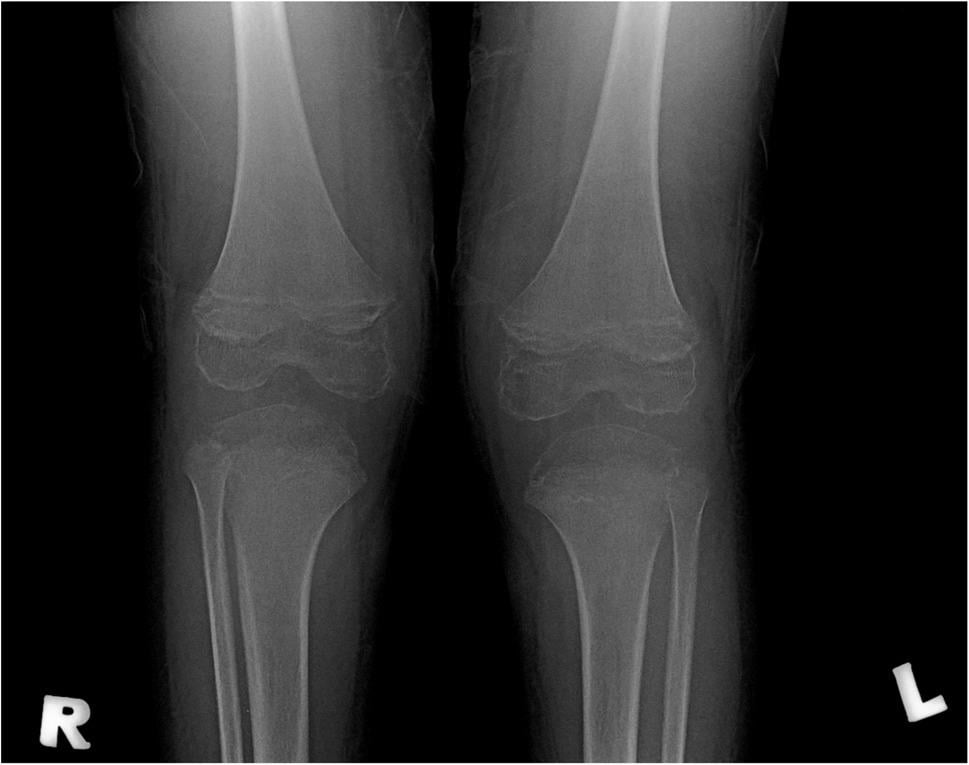
Early disease. Plain films can look normal in a symptomatic child, or show only faint bands.
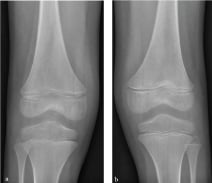
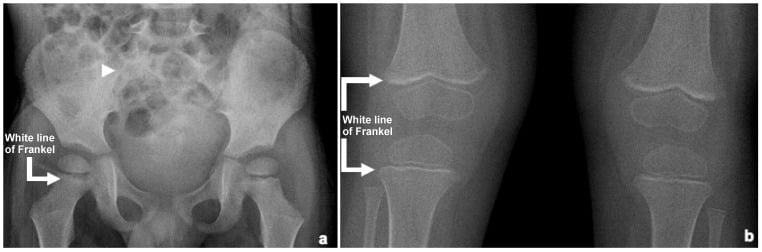
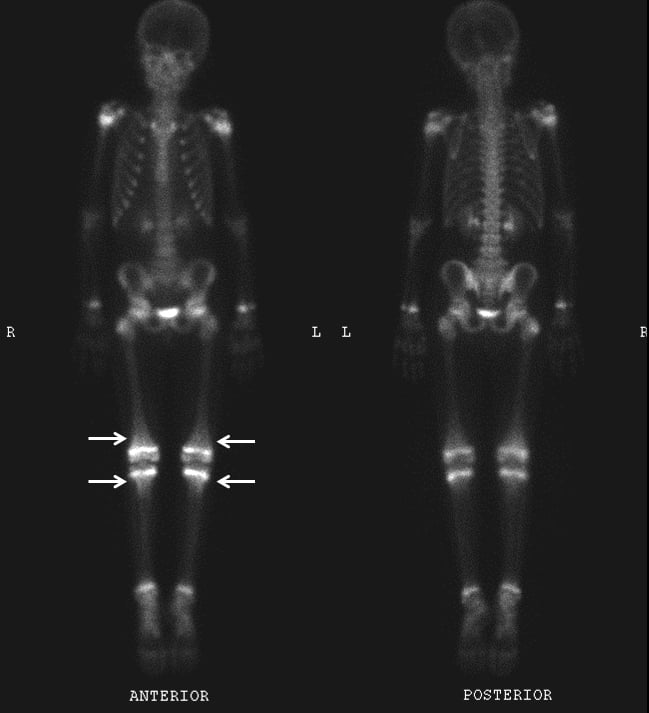
Bone scintigraphy. Uptake is symmetric and periarticular.
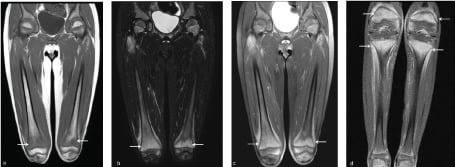
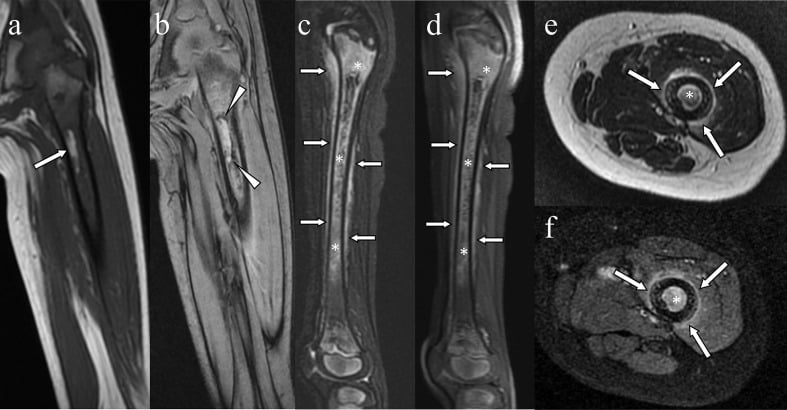
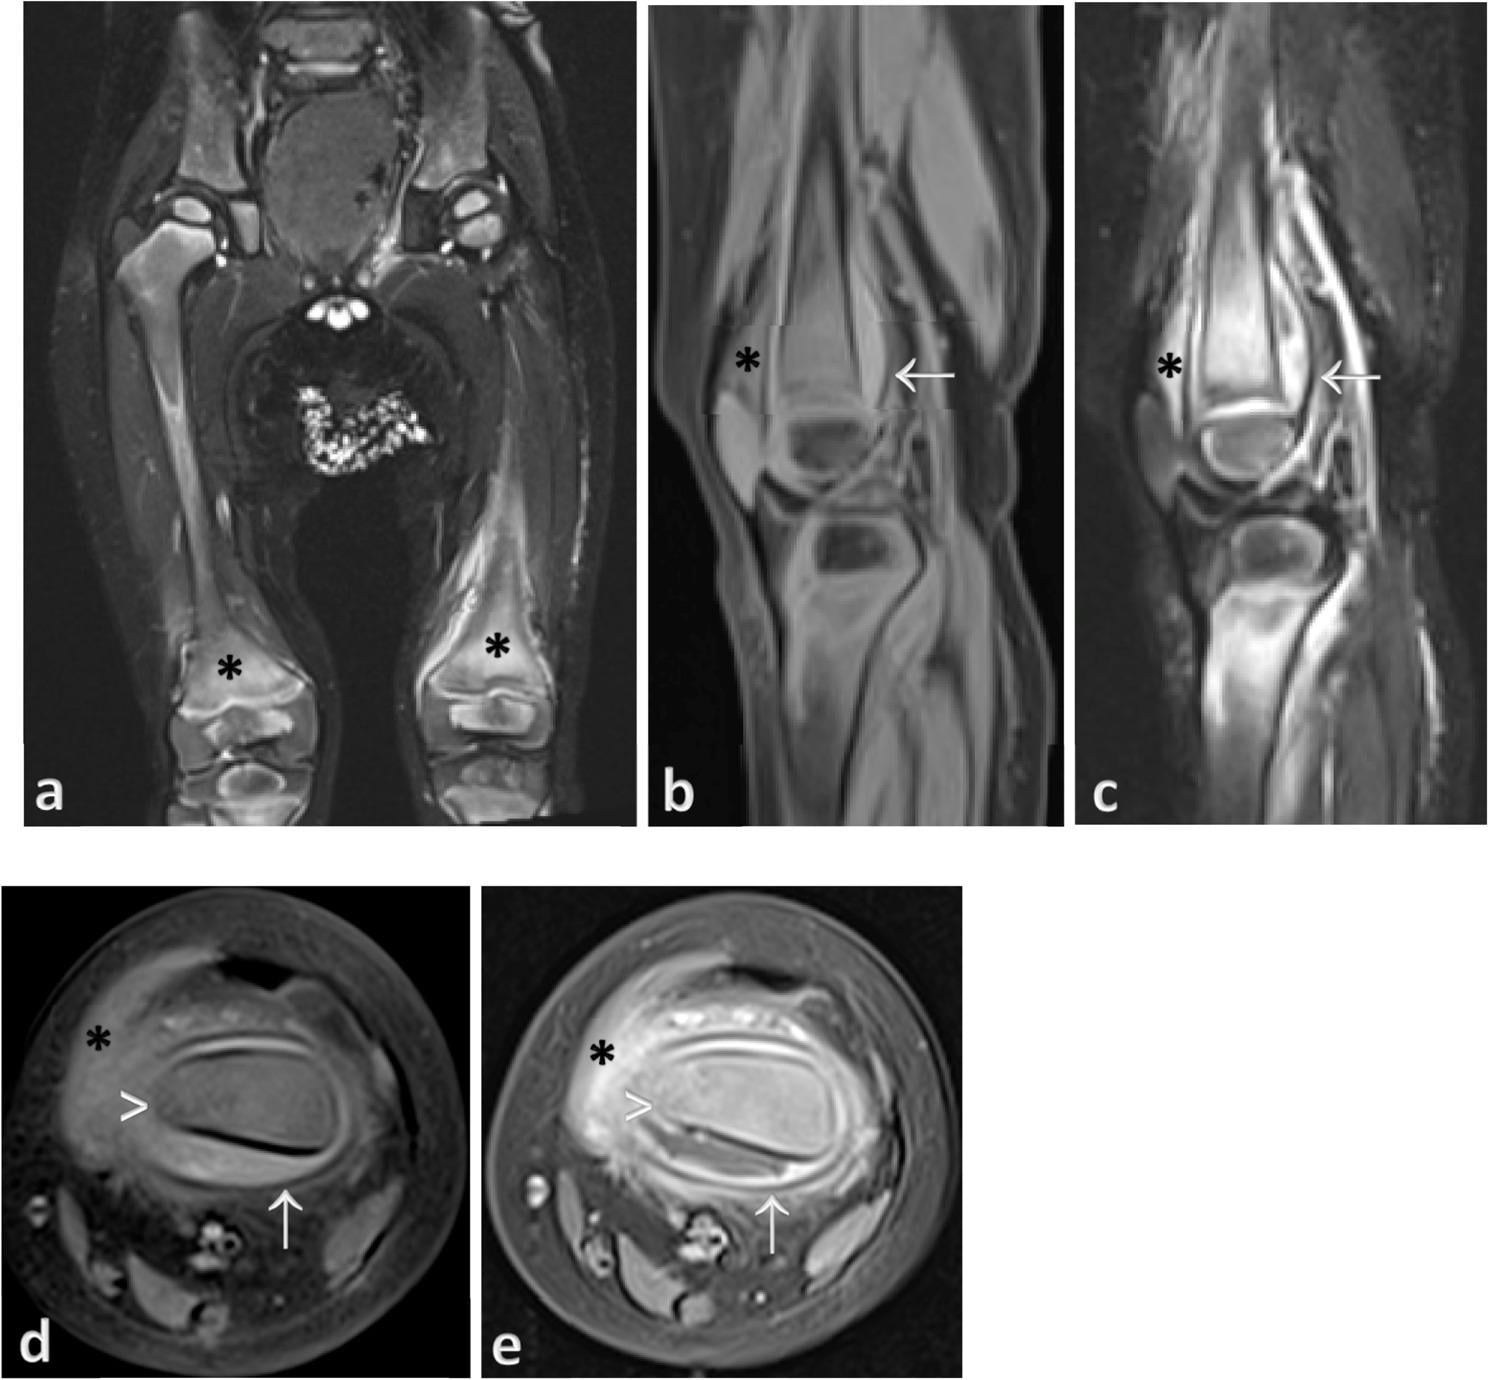
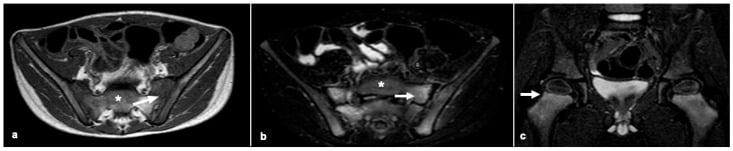
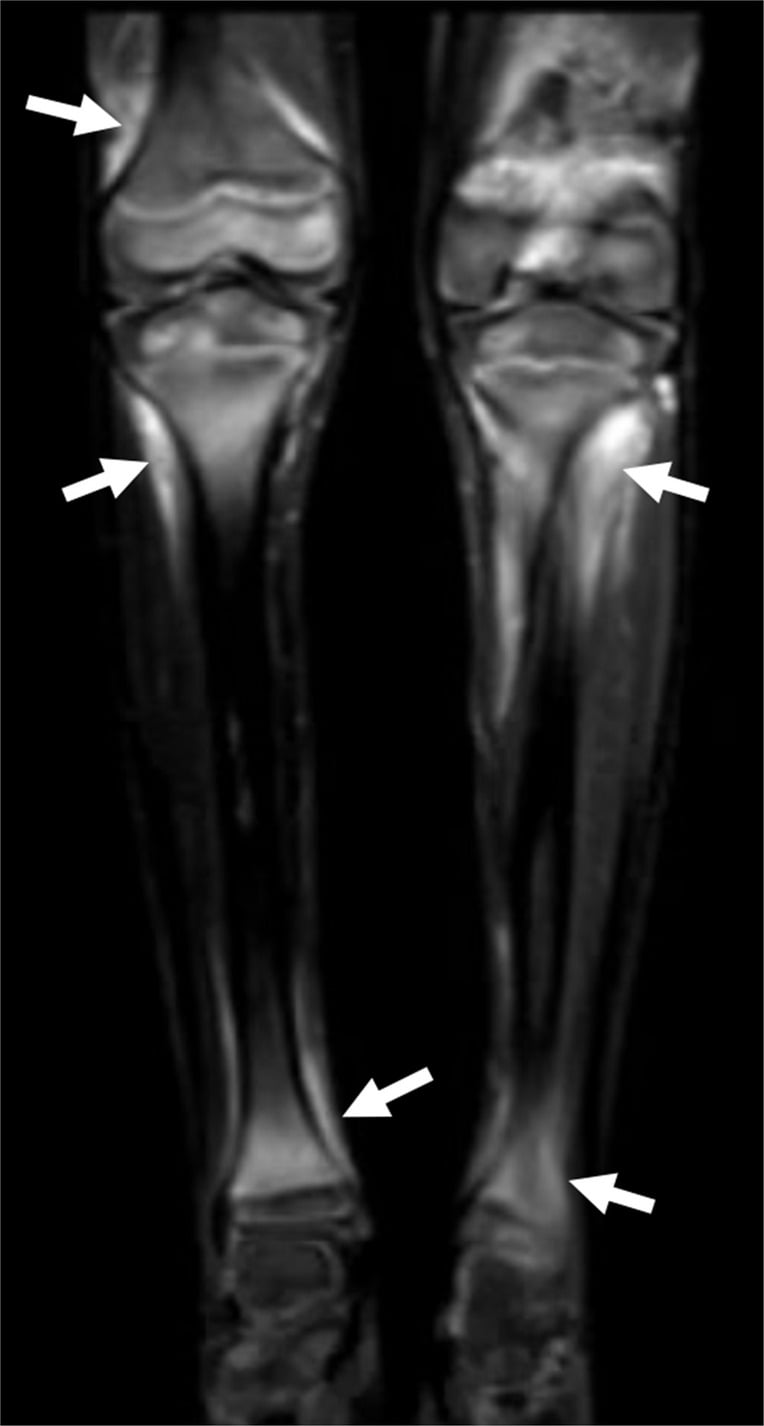
MRI. Scurvy produces diffuse metaphyseal marrow oedema (T2/STIR hyperintensity), most marked at the knee in the distal femur and proximal tibia. With it come a periosteal reaction, subperiosteal fluid or haematoma collections (T2-bright, with peripheral enhancement) and oedema of the surrounding soft tissue and muscle.
Why MRI misleads. MRI is usually what triggers the invasive workup. Marrow oedema, periosteal reaction and enhancing subperiosteal collections closely mimic osteomyelitis, leukaemia or metastatic neuroblastoma, and chronic non-bacterial osteomyelitis (CNO/CRMO), which is exactly why children are taken to biopsy, marrow sampling or empirical antibiotics before scurvy is considered. In an at-risk child, symmetric, bilateral knee-metaphyseal oedema with subperiosteal collections should prompt a serum ascorbic acid level and dietary history before an invasive test (Golriz); the plain films then confirm the classic signs.
Differential Diagnosis
Scurvy can mimic child abuse and vice versa. Failure to diagnose scurvy may lead to wrongful accusation of parents. Failure to diagnose NAI may leave a child in danger. Key differentiating features:
Favours scurvy
- Symmetric bilateral involvement
- Dietary history of restrictive eating
- Systemic signs (gingival bleeding, petechiae, corkscrew hairs)
- Low serum vitamin C
- Rapid response to vitamin C treatment
Favours NAI
- Asymmetric injuries of varying ages
- Inconsistent or changing history
- Delay in seeking care
- Retinal haemorrhages, subdural haematoma
- Normal vitamin C levels
- Soft tissue injuries (bruising in unusual locations)
When in doubt, test vitamin C levels, involve the child protection team, and treat with vitamin C while investigation proceeds. The two conditions can coexist.
Scurvy, rickets and NAI. Scurvy is a failure of collagen and vessels, rickets a failure of mineralisation, and NAI is mechanical injury. The metaphysis, the epiphysis and the distribution show the difference:
- Scurvy
- Vitamin C deficiency - collagen synthesis failure
- Rickets
- Vitamin D/calcium deficiency - mineralisation failure
- Non-Accidental Injury
- Trauma from abuse
- Scurvy
- Osteoid/collagen production, vessel fragility
- Rickets
- Cartilage mineralisation at growth plate
- Non-Accidental Injury
- Mechanical injury
- Scurvy
- Dense Frankel line, corner sign/spurs
- Rickets
- Widened, frayed, cupped metaphyses; widened growth plates
- Non-Accidental Injury
- Classic metaphyseal lesions, bucket handle
- Scurvy
- Wimberger ring (calcified rim, osteopenic centre)
- Rickets
- Delayed ossification, irregular
- Non-Accidental Injury
- Usually normal
- Scurvy
- Symmetric, bilateral, lower limb predominant
- Rickets
- Symmetric, bilateral at all growth plates
- Non-Accidental Injury
- Asymmetric, variable, often multiple ages; skeletal survey shows multiple fractures
- Scurvy
- Gingival bleeding, petechiae, poor wound healing
- Rickets
- Rachitic rosary, frontal bossing, delayed fontanelle, widened wrists and ankles, bowing
- Non-Accidental Injury
- Bruising, burns, retinal haemorrhages, inconsistent history
The rosary. Both diseases bead the costochondral junctions, but the beads feel different. The scorbutic rosary is sharp and angular, often with a step or depression of the sternum, because the weakened junctions let the sternum sink inward: haemorrhage and subluxation at a weakened junction, a collagen and vessel problem. The rachitic rosary is rounded, broad and knobbly, from overgrowth of uncalcified cartilage and osteoid at the growth zone: cartilage hypertrophy, a mineralisation problem.
This is a classic bedside discriminator. A sharp, angular rosary, with the other scorbutic signs and a low vitamin C, points to scurvy; a rounded, broad one, with a high alkaline phosphatase and low vitamin D, points to rickets.
Other causes of a swollen, unmoving limb. Infection and malignancy are the diagnoses that drive the invasive workup:
- Key Features
- Fever, single bone involvement, elevated inflammatory markers
- Investigations
- Raised CRP/ESR, blood culture positive, MRI shows abscess
- Key Features
- Abdominal mass, periorbital ecchymoses, systemic illness
- Investigations
- Elevated catecholamines, bone marrow involvement, MIBG scan positive
- Key Features
- Pallor, hepatosplenomegaly, lymphadenopathy, bleeding
- Investigations
- Abnormal blood film, bone marrow confirms diagnosis
Two Wimbergers. This is the trap that catches candidates: two different signs share one name.
- Wimberger ring - scurvy. A dense sclerotic ring encircling an osteopenic epiphysis. The peripheral zone of provisional calcification keeps calcifying while the centre demineralises: defective central osteoid with normal peripheral mineralisation. It is a ring around the whole epiphysis.
- Wimberger sign (Wimberger corner sign) - congenital syphilis. Focal destruction and erosion of the medial aspect of the proximal tibial metaphysis, bilateral and symmetric, from syphilitic metaphysitis. It is a localised bite out of one corner, not a ring, and in a different bone location entirely.
Both appear in the same clinical situation: an infant or young child who will not move a limb, with metaphyseal changes on the film and non-accidental injury on the differential. The names collide exactly where the confusion is most costly. Read the description, not the eponym: a ring around an epiphysis is scurvy; erosion of the medial proximal tibial metaphysis is syphilis.
Congenital syphilis. It shares the wider picture: pseudoparalysis of Parrot (the infant stops moving a painful limb, exactly as in scurvy), symmetric bilateral long-bone changes with metaphyseal erosions, periosteal reaction and irritability. The discriminators:
- The maternal and antenatal history, and maternal and infant treponemal serology
- The age: congenital syphilis presents in the first months of life, scurvy typically after 6 months of a vitamin C-free diet and usually in the second year
- The other stigmata: rhinitis (snuffles), rash, hepatosplenomegaly and the Wegner sign of metaphyseal serration
Management
The dose. Vitamin C 200-500 mg daily, oral or IV, until clinical and biochemical resolution, usually 1-3 months. Oral ascorbic acid tablets or liquid are preferred if tolerated; IV is for severe cases, vomiting or malabsorption. No loading dose is needed, as standard doses are effective. Adequate dietary vitamin C must then be ensured long-term.
The response. The expected course:
- Pain relief within 24-48 hours
- Bleeding stops within 1 week
- Bone tenderness improves over 1-2 weeks
- Radiographic healing at 2-4 weeks, with subperiosteal calcification visible
- Complete bone remodelling over 3-6 months
Dramatic improvement after vitamin C is virtually diagnostic of scurvy, and pain relief comes before any radiographic change. If there is no improvement by 1 week, reconsider the diagnosis.
Nutrition. Other deficiencies are common in restrictive diets and are corrected alongside: iron for anaemia or concurrent iron deficiency, folate if the anaemia is macrocytic. Dietitian involvement is essential, and the underlying eating disorder (autism, sensory issues) needs addressing.
Complications
Scurvy is highly reversible, so most complications stem from delayed or missed diagnosis rather than from the deficiency itself. With timely vitamin C the orthopaedic outcome is excellent.
From the disease. The deficiency itself can cause:
- Epiphyseal separation or displacement through the weakened Trümmerfeld zone, which usually heals without deformity once treated
- Growth disturbance: rare, and possible after significant physeal injury or very prolonged untreated disease
- Severe anaemia from capillary bleeding and impaired handling of iron and folate
- Persistent pain and immobility, with disuse muscle atrophy, during the untreated phase
From the diagnosis. The harms of getting it wrong:
- Invasive workup: biopsy, bone-marrow sampling, prolonged antibiotics or empiric chemotherapy after misdiagnosis as infection, malignancy, JIA or vasculitis
- Wrongful safeguarding action if scorbutic corner lesions are misread as non-accidental injury
- Missed coexisting pathology if an empiric vitamin C trial is relied on alone
- Recurrence if the underlying restrictive diet is not addressed
The most consequential "complication" of scurvy in modern practice is the harm and cost of an extensive, invasive diagnostic workup before a simple ascorbic acid level is checked. Diagnose early and the skeletal complications largely vanish.
Guidelines, Registries & Global Practice
Global Epidemiology
Scurvy persists worldwide across both high- and low-resource settings, and is best understood as a disease of dietary pattern rather than geography.
- Typical at-risk group
- Children with autism / developmental delay, restrictive eaters, transfusion-dependent iron overload, post-chemotherapy/BMT
- Driver
- Sensory food selectivity; processed diets; impaired absorption
- Typical at-risk group
- Refugees, famine and conflict populations, the institutionalised elderly
- Driver
- Restricted access to fresh fruit and vegetables
- Typical at-risk group
- Exclusive boiled/over-processed milk feeding, food-fad diets, alcohol dependence, isolated/elderly poor
- Driver
- Ascorbic acid is heat-labile and not stored long-term
US NHANES population data confirm measurable vitamin C deficiency even in food-abundant countries, concentrated in low-income, smoking and restricted-diet groups. Pooled paediatric series consistently identify autism spectrum disorder and developmental delay as the dominant modern risk factors, with diagnosis frequently delayed because scurvy is "off the radar."
Side-by-Side Guidance
There is no high-level interventional trial base for scurvy; management rests on consistent nutritional and paediatric guidance rather than competing society protocols.
- Position
- Defines deficiency thresholds and emphasises dietary adequacy / fortification in at-risk populations; treatment-dose ascorbic acid restores stores rapidly
- Position
- Therapeutic vitamin C for established deficiency, then maintenance via diet/supplement
- Position
- Define RDA and the intake gap that precedes clinical scurvy
- Position
- Screen restrictive eaters and tube-fed/neurodisabled children; supplement and involve dietetics
The practical message is uniform across bodies: confirm with serum ascorbic acid where available, give therapeutic vitamin C, correct the underlying dietary cause, and expect rapid response.
Registry and Resource Notes
Scurvy is not tracked in arthroplasty/implant registries; surveillance comes from paediatric and nutrition reporting networks and published case series. In high-resource settings, serum ascorbic acid and MRI are available to confirm the diagnosis and avoid invasive workup. In limited-resource settings, diagnosis is necessarily clinical and therapeutic (a trial of vitamin C with documented rapid response), and prevention via fresh produce, fortification, or supplementation is the priority.
Safeguarding Considerations (Global Principle)
When scurvy is suspected, clinicians must weigh both nutritional neglect and the possibility of the picture mimicking (or coexisting with) non-accidental injury. Most jurisdictions mandate reporting of suspected child abuse or neglect. Scurvy in a child with a known developmental disorder and restricted eating usually reflects family difficulty rather than neglect; a collaborative, supportive approach is appropriate alongside appropriate safeguards. Check vitamin C levels before escalating safeguarding concerns - the rapid response to treatment helps clarify the diagnosis.
Related pages: Non-Accidental Injury is the diagnosis this page exists to be distinguished from, in both directions - a scorbutic corner lesion misread as abuse, and abuse missed because a nutritional explanation was accepted too readily. Rickets is the other metaphyseal deficiency disease and the classic paired question: a mineralisation failure with frayed cupped metaphyses against a collagen failure with a dense metaphyseal line. The Limping Child is the presentation, and Paediatric Acute Osteomyelitis, Chronic Recurrent Multifocal Osteomyelitis and Leukaemic Bone Involvement are the three diagnoses whose MRI appearance scurvy imitates closely enough to send children to biopsy. Periosteal Reaction Patterns is the framework for reading the subperiosteal new bone that appears dramatically during treatment and can itself be mistaken for tumour. Calcium Homeostasis and Metabolic Bone Disease and Metabolic Bone Imaging place scurvy among the metabolic bone diseases and supply the biochemical panel that separates them - normal calcium, phosphate and alkaline phosphatase being the scorbutic signature. Osteogenesis Imperfecta is the inherited collagen disorder that sits beside this acquired one in the fragile-bone differential.
Controversies and Areas of Uncertainty
- Diagnostic threshold and assay reliability. Reported "deficiency" cut-offs vary between series (commonly under 11 micromol/L, but some cohorts use under 23 micromol/L). Plasma ascorbic acid reflects recent intake and is degraded by sample handling; leukocyte vitamin C better reflects tissue stores but is rarely available. A normal-borderline plasma level after recent dietary change can therefore mask true tissue depletion.
- Diagnosis versus child abuse. Metaphyseal corner changes overlap with the classic metaphyseal lesions of non-accidental injury, and the two can coexist. There is no validated radiographic scoring system to separate them with certainty, so practice relies on bilateral symmetry, systemic scorbutic signs, dietary history and treatment response rather than imaging alone.
- Empirical vitamin C trial as a diagnostic test. Rapid response (24-48 h) to vitamin C is widely cited as confirmatory, but a therapeutic trial is not a controlled test and can delay recognition of coexisting pathology if relied on in isolation.
- Optimal dose and route. Reported regimens range widely (roughly 100-500 mg daily, oral or IV). No comparative trials define an optimal paediatric dose, duration, or route; recovery appears rapid across the range used.
- True incidence is unknown. Scurvy is not registry-tracked; published figures derive from case series and are likely underestimates given frequent misdiagnosis as infection, malignancy, vasculitis or arthritis.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 2-year-old boy is referred with a 2-week history of refusing to walk. He was previously walking independently. He cries when his legs are touched. There is no history of trauma. He is an extremely selective eater, accepting only white bread and milk. On examination, he is irritable, has swelling over both distal thighs, and assumes a frog-leg position. His gums appear swollen and bleed when touched.”
“A 15-month-old girl presents with irritability and leg swelling. The parents report she has been refusing to eat anything except formula for months. X-rays show bilateral metaphyseal corner lesions at the knees and calcified subperiosteal elevation along the femurs. The treating team is concerned about non-accidental injury.”
“An 8-year-old boy with autism spectrum disorder is referred for severe bilateral leg pain. His parents report he has an extremely restricted diet, eating only chicken nuggets and chips for the past 2 years. He has stopped walking over the past month. Examination shows painful swelling over both tibias, petechiae on his legs, and bleeding from his gums when he opens his mouth. His pediatrician has checked basic bloods showing normocytic anemia but normal calcium, phosphate, and alkaline phosphatase.”
Pathophysiology - One Liner
- Vitamin C deficiency → failure of proline/lysine hydroxylation → defective collagen triple helix → weak osteoid + capillary fragility
- Affects Type I collagen (bone, vessels, tendons) - NOT cartilage (so growth plate calcifies normally)
- Frankel line = dense because cartilage calcifies but cannot be resorbed (opposite to rickets which has widened/frayed metaphysis)
Clinical Presentation - Key Features
- Subperiosteal hemorrhage → painful swelling, pseudoparalysis, frog-leg position
- Gingival bleeding and swelling (only if teeth erupted)
- Petechiae, ecchymoses, corkscrew hairs
- Peak age: 6-24 months (historical) or older in autism/restricted eating (modern)
Radiographic Signs - The Classic Triad Plus
- FRANKEL LINE - dense white line at metaphysis (hypermineralized ZPC)
- TRUMMERFELD ZONE - lucent debris band beneath Frankel line
- WIMBERGER RING - dense epiphyseal rim with osteoporotic centre
- CORNER SIGN / PELKAN SPURS - lateral metaphyseal corner defects (mimics NAI!)
- Generalized osteopenia with ground-glass appearance
Differential from NAI - Critical Points
- SCURVY: Bilateral symmetric, dietary history, gingival/skin bleeding, low vitamin C, rapid response to treatment
- NAI: Asymmetric, inconsistent history, varying fracture ages, soft tissue injury, normal vitamin C
- Both can coexist - nutritional neglect may accompany physical abuse
Biochemistry Pattern
- Vitamin C: VERY LOW (less than 11 micromol/L)
- Calcium, phosphate, vitamin D: NORMAL
- ALP: NORMAL or slightly elevated (vs very high in rickets)
- FBC: Normocytic or macrocytic anemia
Treatment - Exam Answer
- Vitamin C 200-500 mg daily (oral or IV)
- Pain relief within 24-48 hours (diagnostic!)
- Radiographic healing by 2-4 weeks
- Complete remodeling by 3-6 months
- No surgery needed - fractures heal with medical treatment
Modern Risk Factors
- Autism spectrum disorder with restrictive eating (MOST COMMON modern cause)
- Developmental delay with sensory food aversions
- Neglect or extreme parental dietary beliefs
- Prolonged formula without supplementation
- Processed food diet (nuggets, chips, white bread = no vitamin C)
Evidence Base
Musculoskeletal Manifestations of Scurvy
- Musculoskeletal symptoms occur in approximately 80% of cases - arthralgia, myalgia, hemarthrosis, muscular hematoma
- Vitamin C depletion causes defective osteoid matrix formation and increased bone resorption
- Imaging may show osteopenia, periosteal proliferation, osteolysis and osteonecrosis; children develop lower-limb pain from subperiosteal bleeding
- Serum ascorbic acid below 2.5 mg/L confirms diagnosis; supplementation gives prompt resolution
Scurvy in the Paediatric Age Group - A Disease Often Forgotten
- Children with abnormal dietary habits, mental illness or physical disability are most at risk
- Common radiological findings: subperiosteal haematoma, ring epiphysis, dense metaphyseal (Frankel) white line and the lucent rarefaction zone, with epiphyseal slips
- Rarity means scurvy is seldom suspected, frequently causing delayed recognition
- High index of suspicion plus bilateral limb radiographs aid diagnosis of this 'eternal masquerader'
Modern American Scurvy - Vitamin C Deficiency at a Children's Hospital
- At-risk groups were iron overload from transfusion (sickle cell/thalassaemia), neurologic disorders, and chemotherapy/bone-marrow transplant - NOT dietary deficiency in otherwise-well children
- Deficiency is frequently missed on clinical evaluation and imaging despite extensive workup
- Radiographs showed ill-defined sclerotic and lucent metaphyseal bands, mainly at the knee
- MRI showed diffuse T2 hyperintensity in lower-limb metaphyses, periosteal reaction and soft-tissue oedema
Scurvy as a Manifestation of Food Selectivity in Children with Autism
- All children had a developmental disorder, most commonly autism, with long-standing food selectivity (diets devoid of fruit and vegetables)
- None had been receiving a multivitamin supplement
- All presented with limp, prompting an elaborate panel of tests and procedures before scurvy was recognised
- Vitamin C led to rapid recovery, underscoring nutritional causes of musculoskeletal symptoms in autism
References
-
Fain O. Musculoskeletal manifestations of scurvy. Joint Bone Spine. 2005;72(2):124-128. doi:10.1016/j.jbspin.2004.01.007
-
Golriz F, Donnelly LF, Devaraj S, Krishnamurthy R. Modern American scurvy - experience with vitamin C deficiency at a large children's hospital. Pediatr Radiol. 2017;47(2):214-220. doi:10.1007/s00247-016-3726-4
-
Agarwal A, Shaharyar A, Kumar A, Bhat MS, Mishra M. Scurvy in pediatric age group - A disease often forgotten? J Clin Orthop Trauma. 2015;6(2):101-107. doi:10.1016/j.jcot.2014.12.003
-
Harknett KM, Hussain SK, Rogers MK, Inclima MP. Scurvy mimicking osteomyelitis: a case report and review of the literature. Clin Pediatr. 2014;53(10):995-997. doi:10.1177/0009922813515847
-
Léger D. Scurvy: reemergence of nutritional deficiencies. Can Fam Physician. 2008;54(10):1403-1406.
-
Weinstein M, Babyn P, Zlotkin S. An orange a day keeps the doctor away: scurvy in the year 2000. Pediatrics. 2001;108(3):E55. doi:10.1542/peds.108.3.e55
-
Popovich D, McAlhany A, Adewumi AO, Barnes MM. Scurvy: forgotten but definitely not gone. J Pediatr Health Care. 2009;23(6):405-415. doi:10.1016/j.pedhc.2008.10.008
-
Karthiga S, Geetha S, Maheshkumar P. Scorbutic rosary: A case report of scurvy in a child. Indian J Radiol Imaging. 2019;29(3):333-336. doi:10.4103/ijri.IJRI_45_19
-
Ma NS, Thompson C, Weston S. Brief report: Scurvy as a manifestation of food selectivity in children with autism. J Autism Dev Disord. 2016;46(4):1464-1470. doi:10.1007/s10803-015-2660-x
-
Ratanachu-Ek S, Sukswai P, Jeerathanyasakun Y, Wongtapradit L. Scurvy in pediatric patients: a review of 28 cases. J Med Assoc Thai. 2003;86(Suppl 3):S734-740.
-
Olmedo JM, Yiannias JA, Windgassen EB, Gornet MK. Scurvy: a disease almost forgotten. Int J Dermatol. 2006;45(8):909-913. doi:10.1111/j.1365-4632.2006.02844.x
-
Schleicher RL, Carroll MD, Ford ES, Lacher DA. Serum vitamin C and the prevalence of vitamin C deficiency in the United States: 2003-2004 National Health and Nutrition Examination Survey (NHANES). Am J Clin Nutr. 2009;90(5):1252-1263. doi:10.3945/ajcn.2008.27016