Comprehensive exam-focused review of wheelchair seating and positioning principles including pelvic positioning, pressure management, postural supports, and interface with orthopaedic surgery for patients with neurological conditions
- Neutral pelvic positioning is fundamental to proximal stability
- Posterior pelvic tilt leads to sacral sitting and kyphosis
- Pressure mapping compares cushions and positions; it does not measure tissue risk and cannot clear a patient as safe
- Hip surveillance protocols essential in non-ambulatory CP
- Spinal fusion timing considers seating and sitting balance
- “ASIS alignment determines pelvic position assessment
- “Windswept deformity: combined hip abduction and contralateral adduction
- “Obliquity creates asymmetric weight distribution
- “There is no validated interface-pressure threshold for safe sitting - the '32 mmHg capillary closure' figure is from finger nailfold capillaries, not loaded tissue, and is not achievable under the ischia
- “Multidisciplinary team essential: OT, PT, orthotist, surgeon
Wheelchair Seating and Positioning
Overview
Wheelchair seating and positioning is a critical component of care for patients with neurological conditions who are non-ambulatory or have limited mobility. Proper seating reduces the risk of secondary complications: pressure ulcers, scoliosis progression, hip subluxation and respiratory compromise.
The pelvis comes first. The pelvis is the foundation of the seating system, and neutral pelvic positioning is essential for proximal stability and distal function. Always assess pelvic position before anything else.
The team. A multidisciplinary approach involving occupational therapists, physiotherapists, orthotists and orthopaedic surgeons is essential for optimal outcomes. The surgeon's share is the hip, the spine and the contractures, and surgical decisions on each of them affect seating requirements.
Pathophysiology and Biomechanical Principles
The pelvic foundation. The pelvis is the key to proximal stability: proper pelvic positioning enables optimal trunk alignment, head control and upper limb function. In neutral the ASIS landmarks are level, the pelvis is tilted neither excessively anteriorly nor posteriorly, and the ASIS and pubic symphysis lie in the same vertical plane. Weight is distributed evenly on the ischial tuberosities, lumbar lordosis is preserved and the thighs lie parallel to the seat surface. [1]
Neutral is optimal for pressure distribution and is the goal for most seating interventions.
Posterior pelvic tilt. When the pelvis rolls back the patient sits on the sacrum, and the spine above compensates. The consequences run up the chain:
- Sacral sitting, with increased pressure on the sacrum and coccyx
- Loss of lumbar lordosis, with compensatory thoracic kyphosis
- Cervical hyperextension to keep the visual field
- Increased risk of pressure injuries
- Compromised respiratory function
The kinetic chain. The seated posture is a kinetic chain from the pelvis through the spine to the head, and each dimension of the chair acts on it. [2]
- Seat depth - thigh support and popliteal pressure
- Seat width - how much lateral trunk support is available
- Seat-to-back angle - posture and pressure distribution
- Footrest height - thigh loading and pelvic position
- Armrest height - shoulder positioning and transfers
The goals of seating. Seating intervention has four goals:
- Posture and alignment - maintain a neutral pelvic position, preserve or improve spinal alignment, support the head for function, and prevent or accommodate deformity
- Pressure management - distribute forces over the maximal area, reduce peak pressures at bony prominences, enable regular pressure relief and prevent tissue breakdown
- Function - facilitate upper limb reach and manipulation, safe swallowing and breathing, communication and vision, and mobility and access to the environment
- Comfort and tolerance - maximise sitting duration, reduce pain and fatigue, and improve quality of life and participation in activities
PPFCGoals of Seating
Hook:Think PPFC like Performance, Protection, Function, Comfort for the seated patient
Clinical Assessment and Pelvic Positioning
Technique. Pelvic position is assessed by palpating bony landmarks with the patient seated. The ASIS are the primary reference points for tilt and obliquity. [3]
- Seat the patient on a firm surface
- Palpate both ASIS
- Judge their position relative to the pubic symphysis to assess tilt
- Compare the ASIS heights to assess obliquity
- Compare the ASIS and PSIS planes to assess rotation
- Decide whether any deformity is fixed or flexible
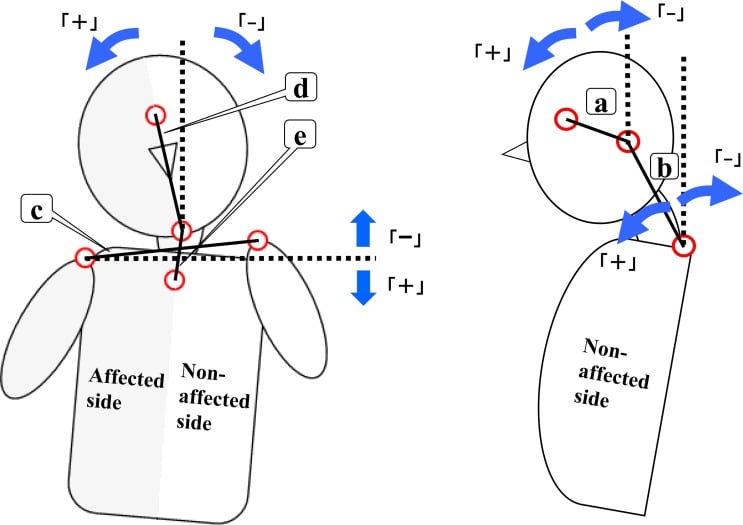
Tilt. Posterior tilt places the ASIS behind the pubic symphysis. It is common in hypotonic patients, causes sacral sitting with increased sacral and coccygeal pressure, and may be fixed or flexible. Anterior tilt places the ASIS in front of the symphysis; it is less common in wheelchair users, may occur with a hip flexion contracture and can increase lumbar lordosis.
Establish tilt first and in isolation, because obliquity and rotation are measured against a pelvis whose sagittal position is already known.
Investigations and Pressure Management
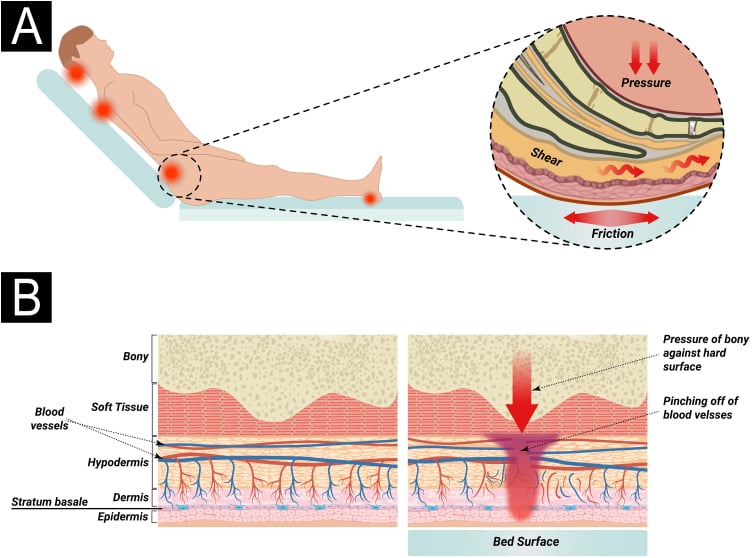
How pressure injury happens. Pressure injury is a time-dependent failure caused by sustained tissue deformation, ischaemia-reperfusion, shear, friction and adverse microclimate. Interface pressure contributes to load, but no validated universal pressure threshold predicts tissue injury: individual anatomy, perfusion, muscle bulk and exposure duration change tolerance. [5]
Who is at risk. The risk factors for pressure injury:
- Impaired sensation (SCI, neuropathy)
- Impaired mobility
- Incontinence
- Malnutrition
- Cognitive impairment
- Previous pressure injury
- Bony prominences
- Muscle atrophy
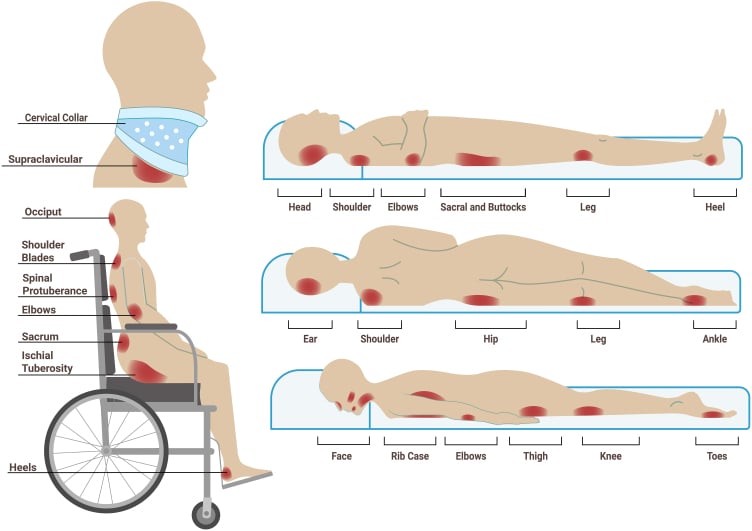
Where. When seated, the ischial tuberosities carry the highest risk. The other sites depend on posture and build:
- Sacrum and coccyx, especially with posterior pelvic tilt
- Greater trochanters, with lateral positioning
- Spinous processes, in kyphotic patients
- Scapulae, in thin patients with high backrests
Pressure Mapping
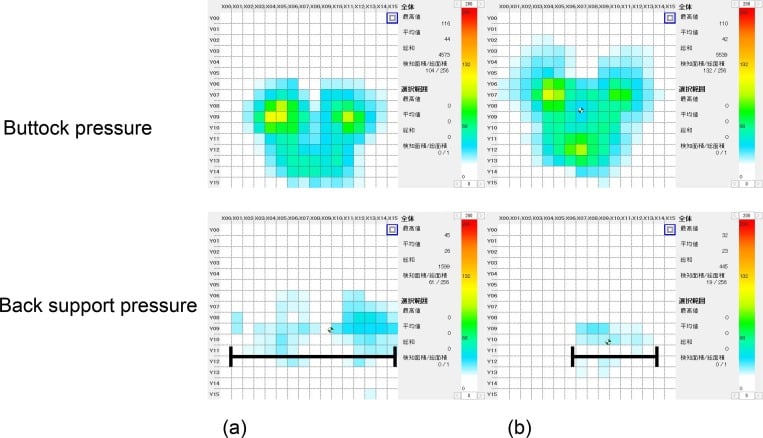
What it measures. Interface pressure mapping gives an objective measurement of pressure distribution between the patient and the seating surface. Sensor arrays quantify pressure at multiple points and display the result as a colour-coded map. [6]
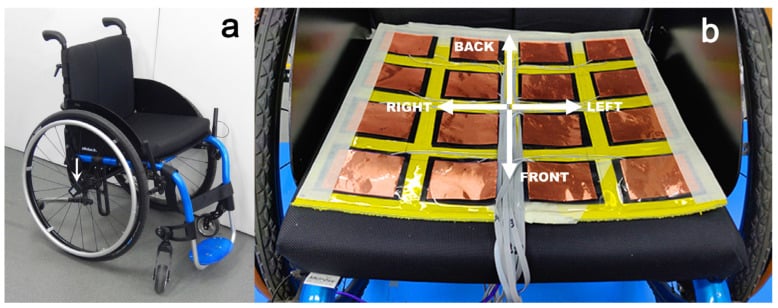
Clinical uses. Mapping earns its place in:
- Cushion selection and comparison
- Optimising positioning adjustments
- Identifying high-pressure areas
- Documentation for funding justification
- Patient and caregiver education
- Outcome measurement
The parameters reported. A map yields:
- Peak pressure, the maximum value at a single point
- Average pressure across the contact area
- Pressure gradient, the rate of change
- Contact area, the distribution of load
- Pressure time integral, the duration factor
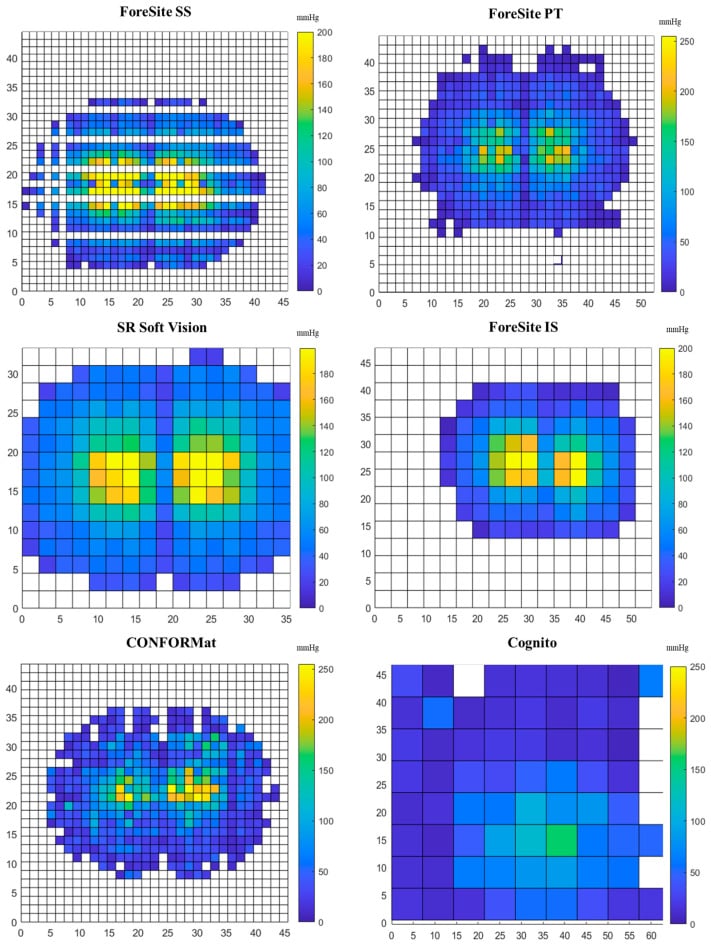
What Pressure Mapping Cannot Do - and the 32 mmHg Trap
A map is a measure of interface pressure: the load at the skin-cushion boundary. It is not tissue pressure, and it is not a risk score.
The "32 mmHg capillary closure pressure" is not a seating target. The figure descends from Landis's 1930 measurements of nailfold capillary pressure in the fingers of seated healthy adults. It is a physiological measurement of pressure inside a capillary, not a threshold at which tissue dies, and it was never derived from loaded soft tissue over a bony prominence. No cushion brings ischial interface pressure under 32 mmHg in a seated adult, so an unachievable target is worse than no target: it either paralyses cushion selection or invites the conclusion that every cushion has failed.
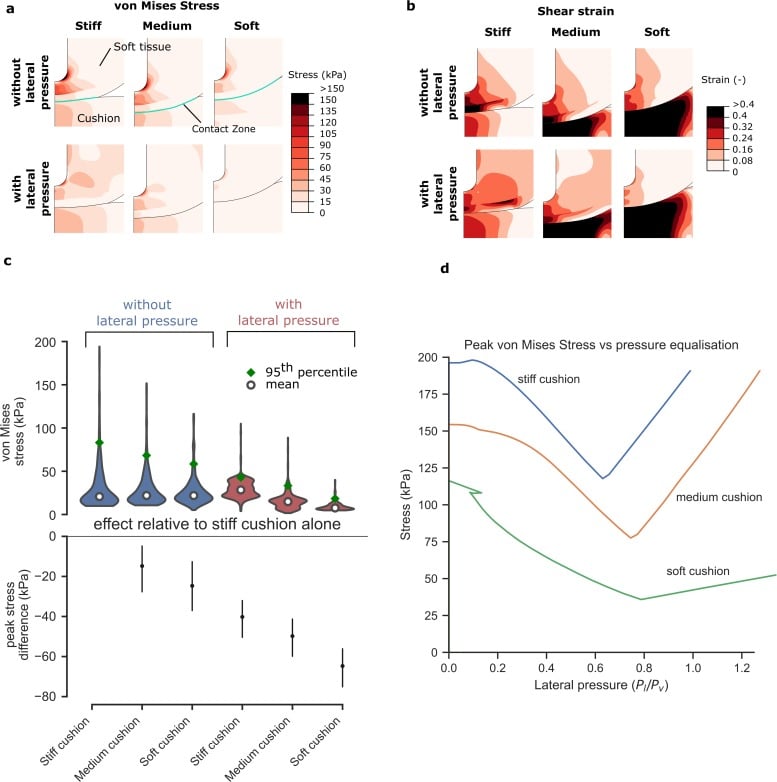
Deep tissue injury is caused by sustained deformation. The severe pressure injury forms in muscle overlying the bony prominence and becomes visible at the skin only later. Internal strains at the ischium are several times the interface value, and the tolerable strain falls steeply with time: cells tolerate roughly 65% engineering strain for about an hour but only about 40% over five hours (Gefen, carded below). Two patients with identical maps can have very different internal loading depending on muscle bulk, atrophy, body habitus and bone shape.
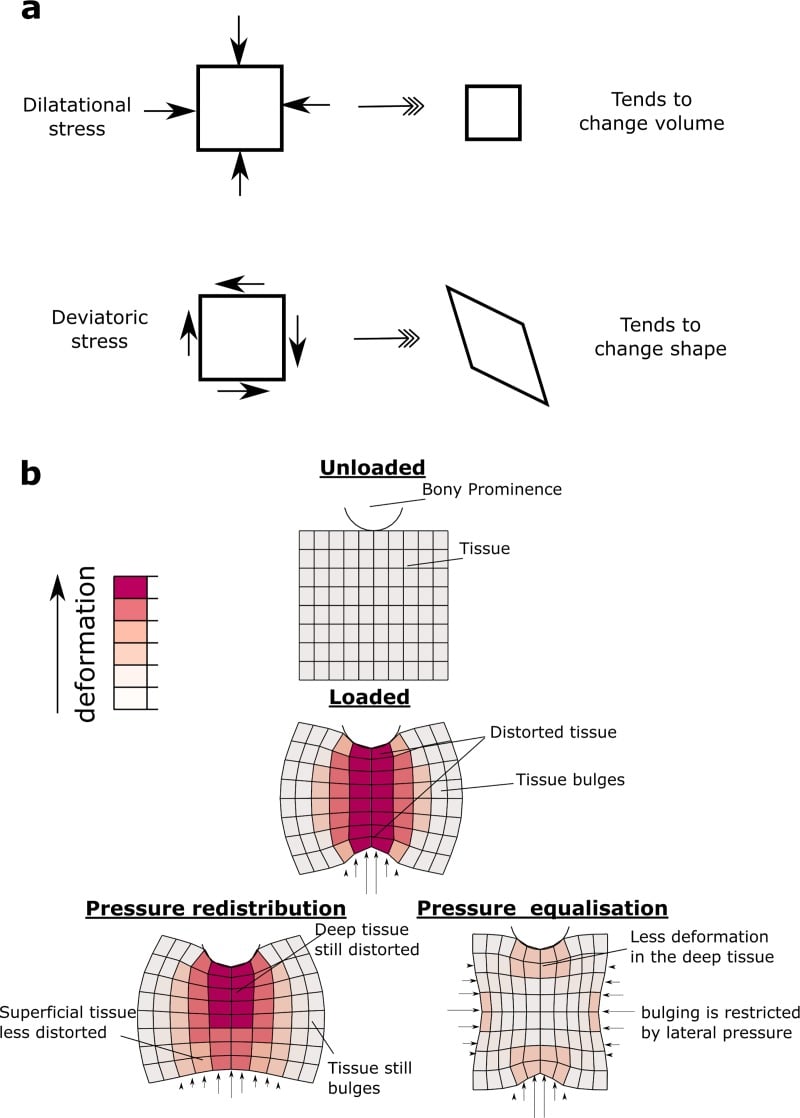
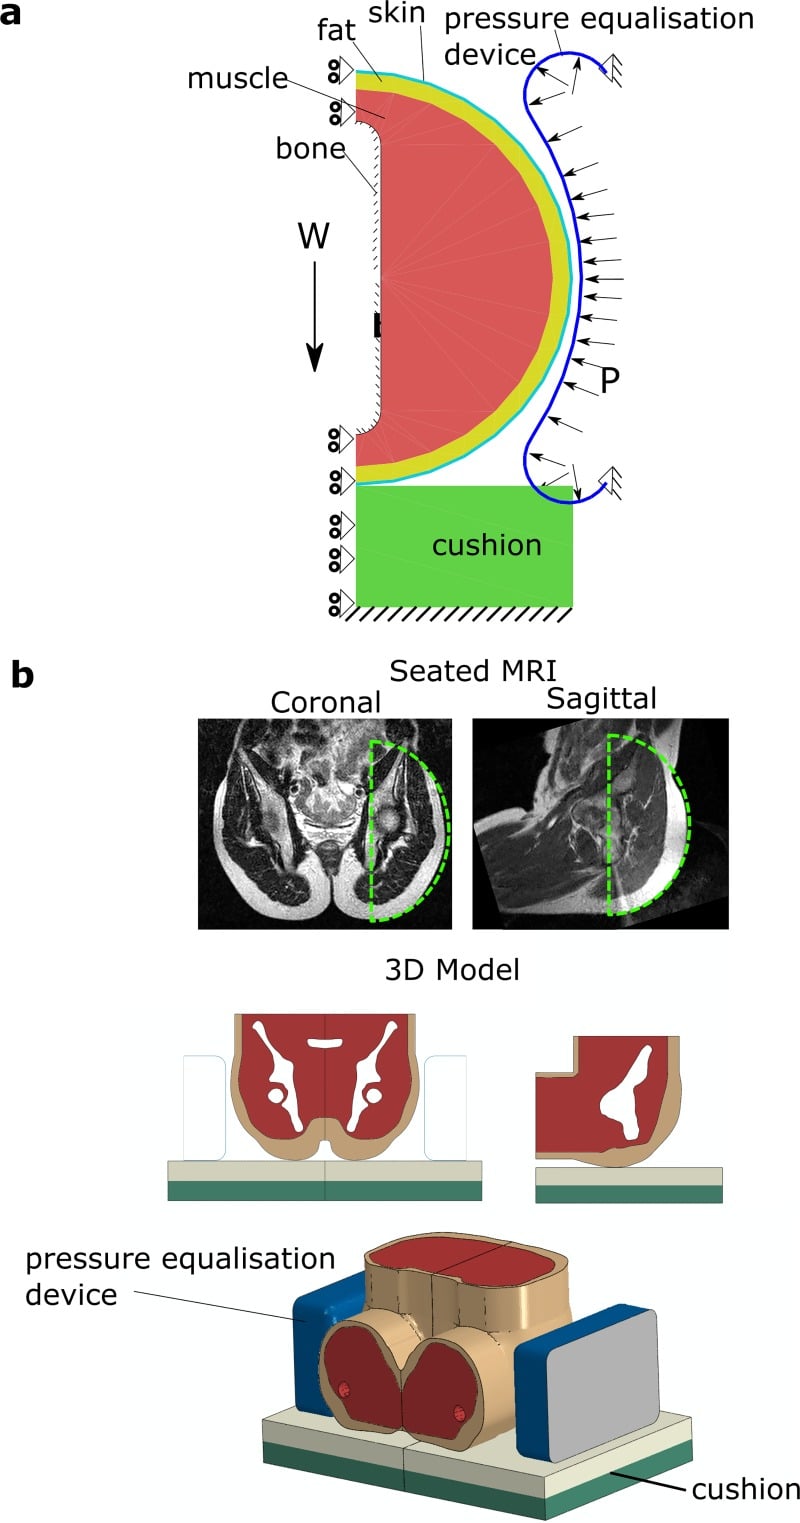
Shear and microclimate are invisible on the map. A pressure map records normal force only. Shear from a reclined backrest or a sling seat, and heat and moisture at the interface, all lower tissue tolerance, and none of them register.
What mapping is for. Pressure mapping is defensible for comparing cushions and positions in the same patient at the same sitting, and for education and funding documentation. It is not a test that clears a patient as safe, and a good-looking map does not permit longer sitting without pressure relief. Regular weight shifts remain essential.
Cushion Selection
The choice. Cushion selection depends on pressure injury risk level, positioning needs, transfer ability, lifestyle factors and budget constraints. [7] In practice that means weighing:
- Risk level (low, moderate, high, very high)
- Postural stability requirements
- Transfer method and frequency
- Weight and build of the patient
- Continence status
- Maintenance capacity
- Environmental factors (temperature, moisture)
- Description
- Polyurethane or viscoelastic foam layers
- Advantages
- Lightweight, low cost, good stability
- Disadvantages
- Limited pressure relief, degrades over time, heat retention
- Best For
- Low risk patients, backup cushions
- Description
- Viscous gel in flexible container
- Advantages
- Excellent pressure distribution, good stability, durable
- Disadvantages
- Heavy, may leak, temperature sensitive
- Best For
- Moderate risk, stable posture
- Description
- Interconnected air cells (e.g., ROHO)
- Advantages
- Best pressure envelopment, adjustable, lightweight
- Disadvantages
- Requires maintenance, unstable base, puncture risk
- Best For
- High risk SCI, bony prominences
- Description
- Combination of foam, gel, and/or air
- Advantages
- Balances pressure relief and stability
- Disadvantages
- More complex, higher cost
- Best For
- Mixed needs, moderate-high risk
- Description
- Moulded to patient anatomy
- Advantages
- Optimal positioning, maximum control
- Disadvantages
- Expensive, difficult to adjust, accommodates growth poorly
- Best For
- Complex deformity, fixed postures
Management and Postural Support
Seating Systems
Linear (planar) systems are flat surfaces set at various angles, such as a solid seat insert or a flat back support. They are adjustable, versatile and lower in cost, and suit flexible postures.
Contoured (custom-moulded) systems are shaped to the patient's anatomy, such as a custom-moulded back or a system made from a seating simulator cast. They give maximum contact and support and are optimal for fixed deformities, at higher cost and complexity.

Trunk and Pelvic Support
Lateral trunk supports provide coronal-plane stability and prevent or accommodate scoliosis. Their position varies with the curve pattern, they may be fixed or swing-away, and they must not impede respiration.
Back supports. A solid insert replaces the sling upholstery and provides consistent postural support; it may be flat, contoured or custom-moulded. Its height affects head control and comfort, and its angle affects pelvic position.
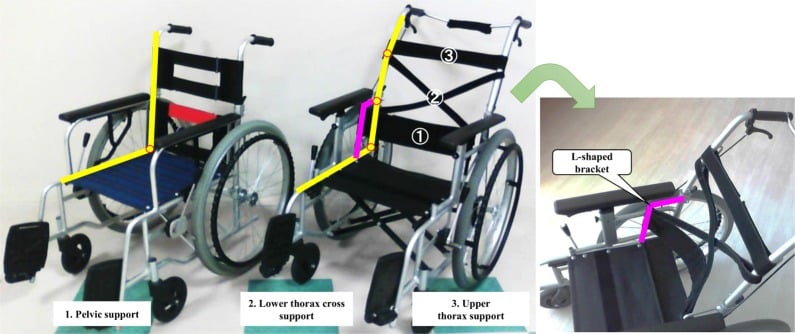
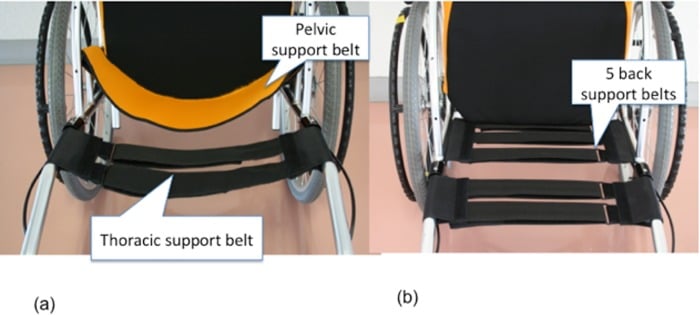
Pelvic positioning devices. Three groups of device position the pelvis and hips:
- Pelvic guides (laterals) position the pelvis in the midline, prevent lateral migration, and may accommodate or correct obliquity
- Anterior pelvic supports prevent forward sliding: a seat belt, positioned at an optimal 45-degree angle, a subasis bar (a padded bar below the ASIS) or a positioning belt system
- Hip positioning aids - a pommel or medial thigh support prevents adduction, abductor wedges position the hips, and thigh guides control rotation
Head support. A headrest is indicated for poor active head control, fatigue with prolonged sitting, transportation safety and posterior head positioning. The types are flat posterior support, contoured occipital support, circumferential support for complex needs, and dynamic headrests that allow movement.
Condition-Specific Seating
Cerebral palsy is the most common cause of childhood physical disability, and 25-35% of affected individuals require a wheelchair for primary mobility. Seating needs vary with motor type (spastic, dyskinetic, ataxic, mixed) and functional level (GMFCS I-V). [8]
By GMFCS level. Support needs rise with the level:
- Level III may walk with assistive devices and uses a wheelchair for longer distances. Sitting balance is usually maintained, linear seating is often sufficient, and the focus is positioning for function.
- Level IV has limited self-mobility and requires a wheelchair in the community. There may be some sitting balance, moderate postural support may be needed, and progressive scoliosis is a risk.
- Level V is dependent for all mobility, with limited head and trunk control. Maximum postural support is required, the risk of hip displacement is high, and complex contoured seating is often needed.
What the chair cannot do. Seating cannot prevent hip displacement; it accommodates the deformity once present. It can support a scoliosis, which affects sitting balance and function, but not correct it. Hip surveillance and spinal fusion are covered under the surgical interface below. Seating in CP needs ongoing review because of growth, changing tone and progressive deformity.
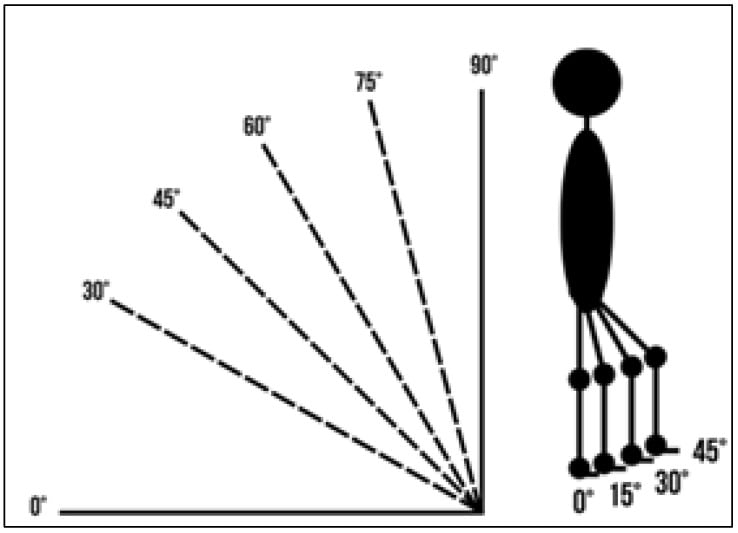
24-Hour Postural Management
Twenty-four-hour postural management treats seating, supported lying and supported standing as one continuous programme rather than three unrelated devices.
Every posture counts. A dependent child spends the day sitting, the night lying (often the single longest posture, up to 10 to 12 hours), and ideally some time standing. A destructive or asymmetric posture in any of these, especially in the many hours spent lying, drives the development of windswept hips, pelvic obliquity, scoliosis and hip subluxation.
The three arms. Each covers a different part of the day:
- Supportive seating by day
- Night-time (sleep-system) positioning to hold symmetrical, supported lying
- Standing in a stander, for weight-bearing, hip development, bone density and stretch
The chair alone cannot protect body shape if the child lies windswept for half the day.
The evidence. The preferred lying posture is associated with the direction of scoliosis and windsweeping (Agustsson), so managing lying and standing, and not seating in isolation, is what plausibly preserves body shape. The supporting evidence is largely low-level, but this is the accepted framework.

Complications and Surgical Interface
Hip Surveillance and Management
The risk. Non-ambulatory children with cerebral palsy are at high risk of hip displacement, with a prevalence of 60-90% in GMFCS levels IV and V. Orthopaedic surveillance every 6-12 months is essential. [11]
- Clinical hip examination every 6 months
- Anteroposterior pelvis radiograph at least annually
- Migration percentage calculation
- Acetabular index measurement
- Assessment of hip pain and function
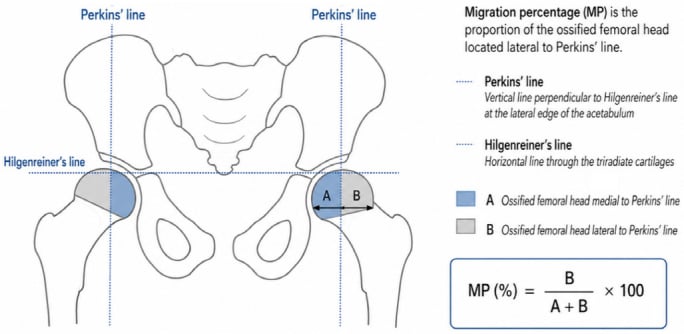
Migration percentage thresholds. The migration percentage sets the response:
- Less than 30%: observation, continue surveillance
- 30-50%: increased surveillance, consider soft tissue surgery
- More than 50%: high risk for dislocation, consider reconstruction
- Dislocated: salvage procedures may be needed
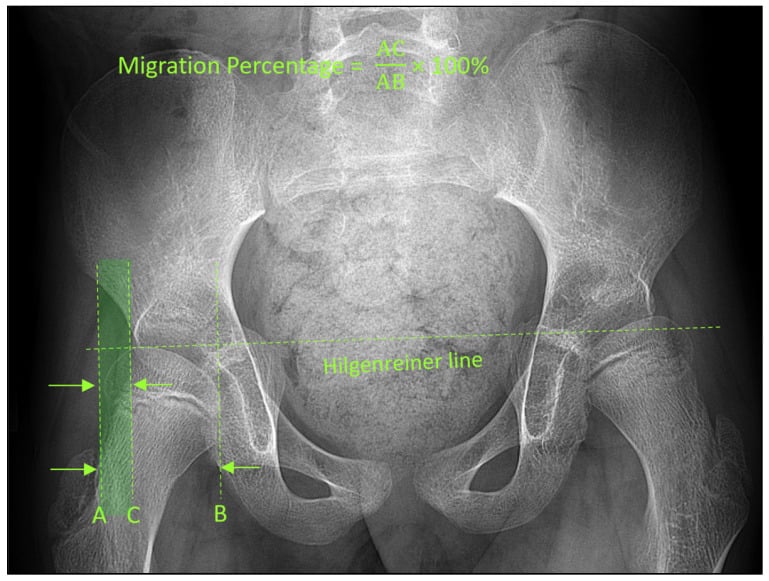
After hip surgery. Soft tissue releases may improve positioning, whereas bony procedures require healing before seating. Post-operative seating assessment is needed, and it weighs an accommodating against a corrective approach.
Spinal Surgery
The problem. Neuromuscular scoliosis is progressive in non-ambulatory patients and frequently requires surgical intervention, and spinal fusion significantly changes seated posture and function. [12]
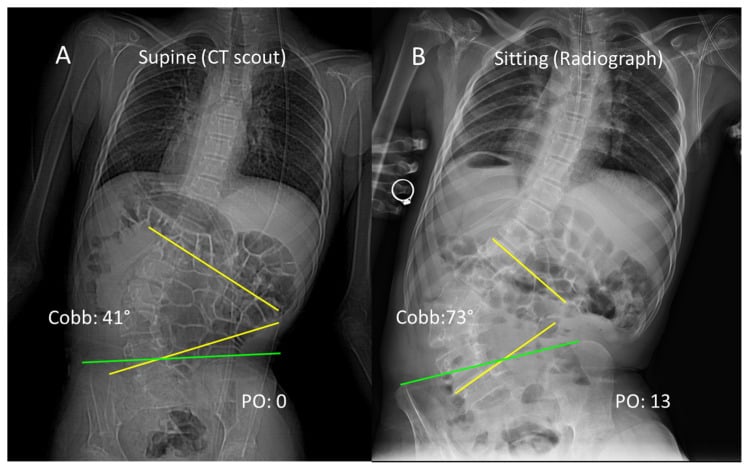
Indications for fusion. Fusion is considered for:
- Progressive curve despite bracing
- Curve magnitude affecting function
- Pelvic obliquity causing sitting imbalance
- Respiratory compromise from the curve
- Pain related to the deformity
Extent and timing. The upper level depends on the curve pattern. In neuromuscular scoliosis the lower level typically extends to the pelvis, with L5/S1 or iliac fixation common. Whether lumbar motion is preserved or sacrificed is part of the decision, and sitting balance goals influence the levels. Timing balances curve progression against growth and considers skeletal maturity.
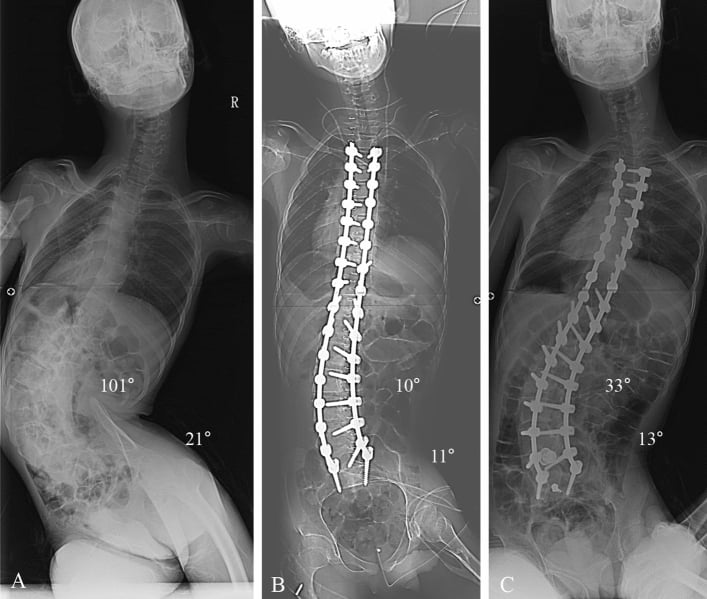
After fusion. Sitting balance changes significantly, and seating reassessment is mandatory:
- Compensatory spinal motion is lost
- The fixed spine requires the seat angle to match it
- Pelvic alignment is often improved
- A new seating system may be needed
- Function may improve or decline
- In neuromuscular disorders, respiratory function may improve
Limb Procedures
Lower limb. Orthopaedic procedures on the limbs affect positioning requirements and seating prescription. Hip flexion contracture release may improve the sitting angle, a knee flexion contracture affects footrest positioning, foot deformity correction improves footplate placement, and limb length discrepancy affects pelvic position.
Upper limb. The seating concerns are elbow and wrist positioning for function, hand support at armrest level, and integrating splints with the seating system.
Multidisciplinary Team
Core team. Each member brings a distinct part of the assessment:
- Occupational therapist - seating and positioning assessment, functional upper limb evaluation, equipment prescription, home and school environment assessment, and activities of daily living training
- Physiotherapist - physical assessment and mobility, postural management programmes, respiratory physiotherapy, strengthening and stretching, and gait training when applicable
- Orthotist - fabrication of custom seating components and positioning orthoses, technical expertise in materials, fitting and adjustments, maintenance and repairs
- Rehabilitation engineer - complex seating solutions, power mobility systems, electronic access devices, environmental controls and technical problem-solving
- Orthopaedic surgeon - hip surveillance and surgery, spinal deformity management, contracture correction, bone health management and coordination with the seating team
- Rehabilitation physician - medical oversight of rehabilitation, spasticity and pain management, coordination of care and prescription authority
The assessment. The initial assessment covers the medical history and diagnosis, physical examination (range of motion, tone, posture), evaluation of current equipment, functional assessment, goals identified with the patient and family, and environmental considerations.
Seating simulation. Simulation trials positioning options, angle adjustments, cushions and components, with pressure mapping and photographic documentation.
Tilt-in-Space versus Recline
Tilt-in-space keeps the angles. It tilts the whole seat and back as a fixed unit around a pivot, so the hip and knee angles are preserved while the person's orientation to gravity changes. It is the workhorse for pressure relief, shifting load off the ischial tuberosities onto the back and posterior thigh, and for rest, fatigue and gravity-assisted head and trunk control. Because the body and supports move together, it generally produces less shear than recline.
Recline opens the hip angle. The backrest reclines relative to the seat, extending the trunk on the thighs. It is useful for intermittent hip-angle change, toileting and catheterisation, and comfort. The relative movement can increase sacral shear as the back slides, and in some patients opening the hip angle triggers an extensor thrust that pushes them forward out of the chair.
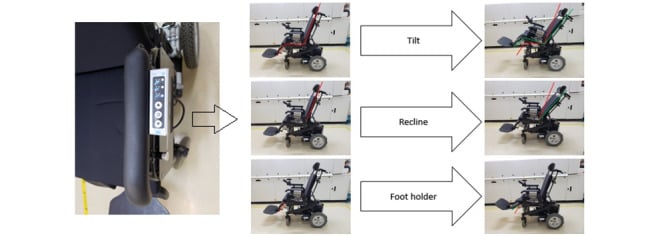
They are not interchangeable. For routine pressure relief in a patient at skin risk, tilt is preferred because it preserves joint angles and limits relative movement. Recline is added for specific needs, often combined with tilt to reduce shear.
Guidelines, Registries & Global Practice
Wheelchair seating need is driven by the global burden of cerebral palsy (roughly 2-3 per 1000 live births, the commonest cause of childhood physical disability), traumatic and non-traumatic spinal cord injury (global incidence on the order of 250,000-500,000 new cases per year), and progressive neuromuscular disease (Duchenne muscular dystrophy ~1 in 3500-5000 male births). Access to appropriate seating varies enormously between high-resource and limited-resource settings.
Side-by-Side Guidance
- Focus
- Wheelchair provision
- Core Recommendation
- 8-step service-delivery model (assess, prescribe, fit, train, follow-up); appropriate manual wheelchairs for less-resourced settings
- Focus
- CP hip displacement
- Core Recommendation
- GMFCS-stratified clinical and radiographic surveillance using migration percentage; refer when migration percentage rises or exceeds ~30-40%
- Focus
- Pressure injury
- Core Recommendation
- Risk assessment, individualised support surface, repositioning/weight-shift, skin inspection, nutrition
- Focus
- Neuromuscular
- Core Recommendation
- Anticipatory powered mobility with tilt/recline, scoliosis and respiratory surveillance
- Focus
- Seating standards
- Core Recommendation
- Clinician-led assessment, trial, pressure mapping and documentation before complex prescription
Registry and Surveillance Evidence
Population registers, rather than implant registries, drive practice here. The Swedish CPUP and the Victorian (Australian) CP registers generated the GMFCS-stratified hip-displacement data (Soo et al.) and the surveillance-reduces-surgery evidence (Hägglund et al.) that underpin worldwide hip surveillance programmes now adopted in the UK, Scandinavia, Australia and beyond.
High- vs Limited-Resource Practice
- High-resource settings: multidisciplinary seating clinics, pressure mapping, custom-moulded and powered tilt/recline systems, formal hip surveillance programmes, and third-party funding for complex assistive technology.
- Limited-resource settings: emphasis on appropriate, durable, locally maintainable manual wheelchairs (WHO model), simpler postural supports, and caregiver training; custom seating, pressure mapping and powered mobility are frequently unavailable, raising pressure injury and deformity risk. The clinical principles (neutral pelvis, pressure distribution, regular repositioning) remain universal even where the technology does not.
Related pages: Cerebral Palsy is the condition most of this page's evidence comes from, and Cerebral Palsy Hip Surveillance is the programme the Soo and Hagglund data built - migration percentage is the number that decides whether a seated child needs a hip operation rather than a better cushion. Windswept Deformity is the specific pattern that defeats a symmetrical seating system, and Neuromuscular Scoliosis is where pelvic obliquity stops being a seating problem and becomes a surgical one. Spinal Cord Injury is the other population sitting all day, with a different tissue-tolerance profile and a different pressure-injury pattern from the elderly nursing-home residents in the carded cushion trial. Duchenne Muscular Dystrophy and Spina Bifida are the progressive and congenital settings where seating must be planned against a known trajectory - and in spina bifida against insensate skin. Early-Onset Scoliosis and VEPTR and Growing Rods matter because a growing construct changes the seated trunk repeatedly, so the chair must be re-prescribed at each lengthening. Gastrocnemius Equinus Contracture is the commonest reason a footplate cannot be reached, which pushes the pelvis forward into the sacral sitting this page is largely about.
Controversies and Areas of Uncertainty
Wheelchair seating is an area where strong physiological rationale often outruns high-level trial evidence. Examiners reward candidates who can state what is genuinely established versus what is consensus or extrapolation.
- Does seating prevent hip displacement in CP? No. Postural management and abduction positioning are widely used, but evidence that day seating prevents hip migration is weak; the Soo cohort and current surveillance practice treat hip displacement as a natural-history problem managed by radiographic surveillance and surgery, not by the chair. Seating accommodates, it does not protect the hip.
- The 32 mmHg "capillary closure" misconception. The figure derives from Landis's 1930 nailfold capillary measurements and is widely quoted, but real interface pressures over the ischium routinely exceed it without ulceration, and tissue tolerance varies with shear, time, perfusion and individual factors. It is neither a treatment target nor a safety benchmark; interpret pressure maps comparatively, and remember that deep-tissue injury may begin at the muscle-bone interface independent of surface pressure.
- Air versus gel versus foam. The Brienza RCT shows specified skin-protection cushions beat plain foam, but it does not establish superiority of any one skin-protection technology. Cushion choice remains individualised to risk, posture, transfer technique and maintenance capacity rather than dictated by trial data.
- Standing programmes and 24-hour postural management. Biologically plausible for bone density, contracture and comfort, but supporting evidence is largely low-level; intensity and dosing remain uncertain.
- Timing of neuromuscular spinal fusion. Tension between operating early (better pulmonary reserve, more flexible curve) and delaying for skeletal growth; no consensus threshold, decisions are individualised around curve magnitude, FVC trajectory and pelvic obliquity.
- Powered versus manual mobility in young children. Early powered mobility may aid development and participation, but concerns about cost, safety and deconditioning mean practice varies widely.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 10-year-old child with spastic quadriplegic cerebral palsy (GMFCS level V) is referred for wheelchair seating assessment. The parents report increasing difficulty with positioning and skin redness over the sacrum. On examination, there is a posterior pelvic tilt when seated, thoracolumbar scoliosis, and bilateral hip flexion contractures of 30 degrees. How would you approach this patient?”
“A 25-year-old male with T6 complete spinal cord injury from a motorcycle accident 6 months ago is transitioning from rehabilitation to community living. He has had no pressure injuries during rehabilitation but you are asked to optimise his seating for community use. What are the key considerations and how would you prescribe an appropriate cushion?”
“A 14-year-old boy with Duchenne muscular dystrophy has progressive scoliosis now measuring 55 degrees. He has been wheelchair-dependent for 2 years. His respiratory function is declining with FVC of 60% predicted. The spinal surgeon is considering posterior spinal fusion. How does seating assessment inform surgical planning, and what changes do you anticipate post-operatively?”
Goals of Seating (PPFC)
- Posture: maintain alignment, prevent deformity
- Pressure: distribute load, prevent injury
- Function: optimise upper limb use, mobility
- Comfort: ensure tolerance, quality of life
Pelvic Position
- Pelvis is foundation of seating system
- ASIS landmarks determine tilt and obliquity
- Neutral: ASIS and pubic symphysis vertical
- Posterior tilt: sacral sitting, kyphosis, increased pressure
- Obliquity: unequal ASIS heights, asymmetric loading
Pressure Management
- No validated safe interface-pressure threshold; compare maps within the same patient and system
- High-risk areas: ischial tuberosities, sacrum, trochanters
- Pressure mapping: objective cushion comparison
- Weight shifts every 15-30 minutes in SCI
- Cushion types: foam, gel, air, hybrid, custom
Cushion Selection
- Foam: low cost, limited relief, good stability
- Gel: good pressure relief, heavy, stable
- Air: best envelopment, maintenance required, unstable
- Hybrid: balances pressure relief and stability
- Match to risk level and functional needs
Seating System Types
- Linear (planar): flat surfaces, adjustable, versatile
- Contoured (custom): shaped to anatomy, maximum support
- Solid seat insert replaces sling upholstery
- Lateral trunk supports for scoliosis
- Pelvic guides and positioning belts for control
Condition-Specific Considerations
- CP: hip surveillance, scoliosis management, GMFCS level
- SCI: pressure prevention paramount, sensation absent
- DMD: progressive weakness, respiratory needs, scoliosis
- All: ongoing review essential
Orthopaedic Interface
- Hip displacement: 60-90% in non-ambulatory CP
- Seating accommodates but cannot prevent displacement
- Spinal fusion changes sitting balance significantly
- Post-surgical seating reassessment mandatory
- Hip flexion contractures require opened seat-to-back angle
Multidisciplinary Team
- OT: seating assessment, prescription, function
- PT: physical assessment, mobility, respiratory
- Orthotist: custom fabrication, fitting, repairs
- Orthopaedic surgeon: hip and spine surgery
- Rehabilitation physician: coordination, spasticity
Evidence Base
Hip Displacement in Cerebral Palsy (Victorian Cohort)
- Overall hip displacement incidence 35% across the birth cohort
- 0% at GMFCS I versus 90% at GMFCS V (linear gradient)
- Relative risk versus GMFCS II: III 2.7, IV 4.6, V 5.9
- Justifies GMFCS-based surveillance and resource allocation
Skin-Protection Cushions Prevent Pressure Ulcers (RCT)
- N = 232; 6-month follow-up across 12 nursing homes
- Ischial ulcers 0.9% (skin-protection) vs 6.7% (foam), P = 0.04
- Combined ischial plus sacral ulcers 10.6% vs 17.6% (NS)
- Cushion type and correct fit both matter for prevention
Reliability of Interface Pressure Map Interpretation
- Visual pressure-map ranking agreed with ranking by numerical data
- Significant intra- and inter-rater agreement (P less than 0.001)
- Agreement held across operator experience levels and surfaces
- Establishes RELIABILITY of map interpretation - it does not test whether mapping predicts tissue injury
Why Interface Pressure Thresholds Fail: Deformation-Based Injury Thresholds
- Deep tissue injury is defined by sustained DEFORMATION of muscle over bone, not by interface pressure
- The classical pressure-time curves used to set seating targets have serious methodological flaws
- Tolerable strain falls steeply with duration - roughly 65% engineering strain for about an hour, but only about 40% over five hours (companion experimental work)
- Thresholds must be individualised: muscle atrophy, obesity and bone shape change internal strain for the same external load
Fusion to the Pelvis for Cerebral Palsy Scoliosis
- N = 287; scoliosis 76 to 25 degrees (68% correction)
- Pelvic obliquity 17 to 5 degrees (71% correction)
- Deep infection ~6%, 3 perioperative deaths
- 96% caretaker-reported satisfaction
GMFCS Predicts Sitting and Standing Performance
- N = 562 (total population, ages 3-18)
- Adaptive seating use 42% overall, rising with GMFCS
- 99% could sit and 96% could stand with supports
- GMFCS strongly predicts seating/positioning needs
Population Surveillance Reduces CP Orthopaedic Surgery
- Surgery for contracture/torsion fell 40% to 15% (P = 0.0019)
- Range of motion improved in non-ambulant children
- Severe contractures largely prevented
- Surveillance plus early tone/posture management is effective
Standards of Care in Duchenne Muscular Dystrophy
- Multidisciplinary, anticipatory model alters natural history
- Powered mobility with tilt/recline after loss of ambulation
- Scoliosis and respiratory surveillance integral to seating
- Coordinated care improves function and longevity
References
-
Letts M, Rang M. Seating and positioning for children with cerebral palsy. In: Pediatric Orthopaedics. 3rd ed. Saunders; 1997:1112-1145.
-
Hobson DA, Tooms RE. Seated lumbar/pelvic alignment. A comparison between spinal cord-injured and noninjured groups. Spine. 1992;17(3):293-298.
-
Holmes KJ, Michael SM, Thorpe SL, Solomonidis SE. Management of scoliosis with special seating for the non-ambulant spastic cerebral palsy population. Clin Biomech. 2003;18(6):480-487.
-
Ágústsson A, Sveinsson Þ, Pope P, Rodby-Bousquet E. Preferred posture in lying and its association with scoliosis and windswept hips in adults with cerebral palsy. Disabil Rehabil. 2019;41(26):3198-3202.
-
National Pressure Ulcer Advisory Panel and European Pressure Ulcer Advisory Panel. Prevention and Treatment of Pressure Ulcers: Clinical Practice Guideline. National Pressure Ulcer Advisory Panel; 2014.
-
Stinson MD, Porter-Armstrong AP, Eakin PA. Pressure mapping systems: reliability of pressure map interpretation. Clin Rehabil. 2003;17(5):504-511.
-
Brienza D, Kelsey S, Karg P, et al. A randomized clinical trial on preventing pressure ulcers with wheelchair seat cushions. J Am Geriatr Soc. 2010;58(12):2308-2314.
-
Rodby-Bousquet E, Hägglund G. Sitting and standing performance in a total population of children with cerebral palsy: a cross-sectional study. BMC Musculoskelet Disord. 2010;11:131.
-
Consortium for Spinal Cord Medicine. Pressure ulcer prevention and treatment following spinal cord injury: a clinical practice guideline for health-care professionals. J Spinal Cord Med. 2001;24(Suppl 1):S40-101.
-
Bushby K, Finkel R, Birnkrant DJ, et al. Diagnosis and management of Duchenne muscular dystrophy, part 2: implementation of multidisciplinary care. Lancet Neurol. 2010;9(2):177-189.
-
Soo B, Howard JJ, Boyd RN, et al. Hip displacement in cerebral palsy. J Bone Joint Surg Am. 2006;88(1):121-129.
-
Tsirikos AI, Lipton G, Chang WN, Dabney KW, Miller F. Surgical correction of scoliosis in pediatric patients with cerebral palsy using the unit rod instrumentation. Spine. 2008;33(10):1133-1140.
-
Hägglund G, Andersson S, Düppe H, Lauge-Pedersen H, Nordmark E, Westbom L. Prevention of severe contractures might replace multilevel surgery in cerebral palsy: results of a population-based health care programme and new techniques to reduce spasticity. J Pediatr Orthop B. 2005;14(4):269-273.
-
Rodby-Bousquet E, Hägglund G. Sitting and standing performance in a total population of children with cerebral palsy: a cross-sectional study. BMC Musculoskelet Disord. 2010;11:131.
-
World Health Organization. Guidelines on the Provision of Manual Wheelchairs in Less-Resourced Settings. Geneva: WHO; 2008.