Post-Fusion Degeneration | Radiographic vs Symptomatic | Motion Preservation vs Fusion Extension
- Define your terms - radiographic degeneration (ASDeg) far exceeds symptomatic disease (ASDis); only about a quarter to a third of radiographic change becomes symptomatic
- Symptomatic ASD is roughly 2.5-3% per year - cervical 2.9%/yr (Hilibrand), lumbar reaching ~36% needing surgery by 10 years (Ghiselli)
- PI-LL mismatch and loss of lumbar lordosis are the key MODIFIABLE risk factors; pre-existing adjacent degeneration is the key non-modifiable one
- Facet joint violation during screw placement and adjacent-level laminectomy are technique-dependent risks the surgeon controls
- Motion preservation (TDR) has NOT clearly reduced adjacent-level reoperation in mid-term RCTs/reviews (Radcliff lumbar; Harrod cervical) - the one counter-signal is the 7-year two-level Mobi-C IDE (adjacent-level surgery 4.4% vs 11.3% with ACDF), industry-run in highly selected patients. It is not a guaranteed solution
- “Hilibrand 1999 (cervical): single-level fusion had HIGHER adjacent-level risk than multilevel - supports natural-history contribution
- “Ghiselli 2004 (lumbar): found NO correlation between fusion length and ASD - a classic exam trap
- “PI-LL mismatch of 10 degrees or more and SVA of 50 mm or more are associated with ASD even after single-level PLIF
- “Radcliff RCT: most 'extra' reoperations after fusion were instrumentation removal, not adjacent-level surgery
Overview and Epidemiology
Adjacent segment disease (ASD) is the development of degenerative change at the spinal levels immediately adjacent to a previous fusion.
Define the terms. The distinction that runs through the whole topic is between what the imaging shows and what the patient feels:
- Radiographic ASD, used interchangeably with adjacent segment degeneration (ASDeg): imaging evidence of degeneration at an adjacent level (disc space narrowing, osteophytes, facet hypertrophy)
- Symptomatic ASD (ASDis): pain or neurological symptoms arising from adjacent level degeneration
- Adjacent segment pathology: symptomatic disease requiring treatment
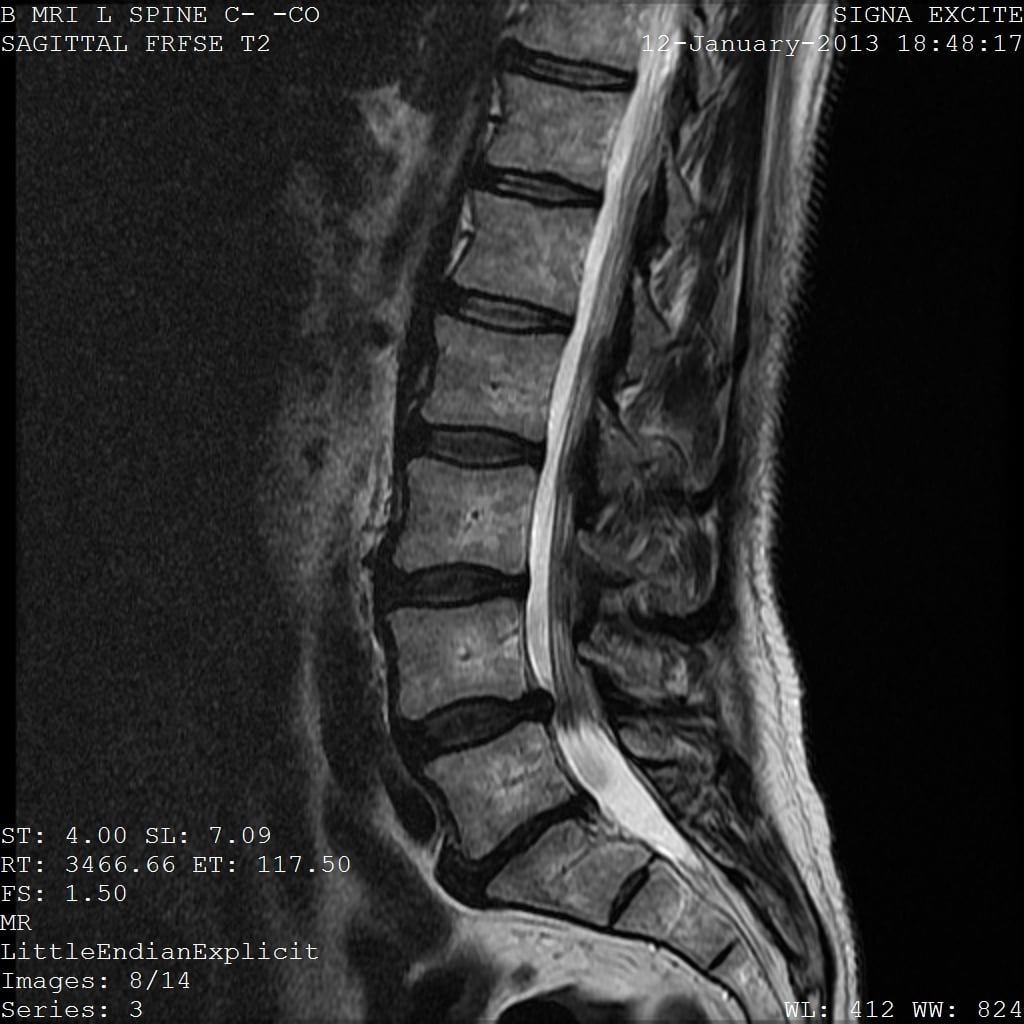
How common radiographic change is. Pooled radiographic degeneration is 26.6% in the lumbar spine and 32.8% in the cervical spine (Hashimoto 2018 systematic review), up to 30% at 10 years. Only about one-quarter to one-third of that radiographic degeneration becomes symptomatic; radiographic change may not progress, and not every change on imaging requires intervention.
How common symptomatic disease is. Symptomatic ASD develops at roughly 2.5-3% per year. In the cervical spine the rate is 2.9% per year (Hilibrand 1999). In the lumbar spine, disease-free survival is 83.5% at 5 years and 63.9% at 10 years, with symptomatic degeneration warranting surgery predicted at 16.5% by 5 years and up to about 36% by 10 years (Ghiselli 2004).
Convert the annual rate before quoting it. A constant 2.9% per year is not a small number over the life of a fusion. Kaplan-Meier survivorship in the same cervical cohort (374 patients, 409 arthrodeses, followed up to 21 years) predicted that 25.6%, roughly one in four, would develop new adjacent-level disease within 10 years (95% CI 20-32%), and two-thirds of those affected, about 17% of all patients, ultimately required further surgery. An annual rate sounds reassuring and a decade of it does not; consent should use the compounded figure, because that is the one that matters to a patient.
Where it happens. L4-5 is the most common lumbar level: it is the most mobile lumbar segment, and it is the level left next to a fusion that ends at L5 rather than S1. In the cervical spine C5-6 and C6-7 are the most common levels.
Risk Factors
Pre-existing degeneration at the adjacent level is the strongest non-modifiable predictor of ASD. PI-LL mismatch with loss of lordosis, and facet joint violation, are the most important modifiable, technique-dependent factors, and they are the ones the surgeon controls.
- Factor
- Age over 60
- Impact
- Higher baseline degeneration
- Factor
- Pre-existing adjacent degeneration
- Impact
- Most significant risk factor
- Factor
- Obesity
- Impact
- Increased spinal loading
- Factor
- Osteoporosis
- Impact
- Altered load transfer
- Factor
- PI-LL mismatch / lost lordosis
- Impact
- Strongest modifiable risk (Lau 2021)
- Factor
- Sagittal imbalance (SVA over 50 mm)
- Impact
- Abnormal load distribution
- Factor
- Facet joint violation
- Impact
- Iatrogenic destabilisation of adjacent level
- Factor
- Adjacent-level laminectomy
- Impact
- Destabilises the next segment
- Factor
- Fusion length
- Impact
- Disputed - Ghiselli found NO correlation
- Factor
- Stiff instrumentation
- Impact
- Greater load transfer (biomechanical)
Sagittal alignment. Loss of lumbar lordosis and PI-LL mismatch are the strongest modifiable risk (Lau 2021). A PI-LL mismatch of 10 degrees or more and an SVA of 50 mm or more are associated with ASD even after a single-level PLIF, as is high pelvic tilt, and a fusion in kyphosis accelerates ASD. Restoring sagittal balance at the index operation is protective: lumbar lordosis should match pelvic incidence, with a PI-LL mismatch under 10 degrees.
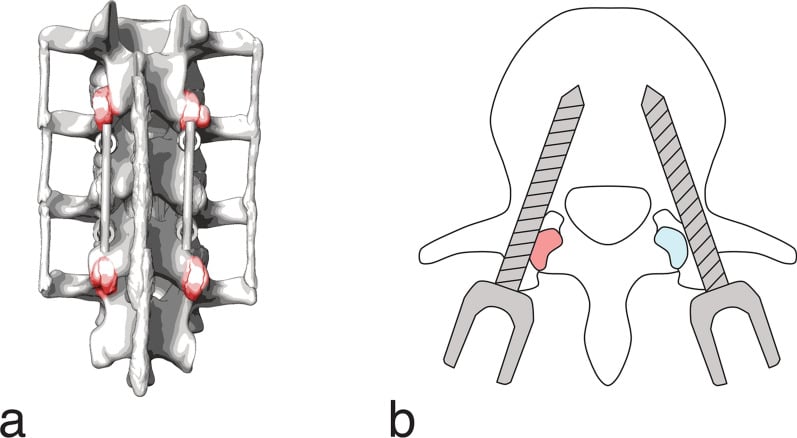
Facet joint violation. Of all the risk factors, this is the one most directly in the surgeon's hands, and examiners reward candidates who can explain it. When the cranial-most pedicle screw is placed, a starting point that is too superior or lateral, or a trajectory that is too cephalad, breaches the facet joint of the segment above the construct, the UIV+1 mobile level, destabilising and degenerating the very level the construct was meant to protect. The risk is higher with freehand or open placement and a cephalad-angled cranial screw, and it is reported in a meaningful fraction of cranial screws.
Avoid it with a more caudal, medial starting point and a non-cephalad trajectory for the UIV screw, keep instruments and the screw head off the unfused facet capsule, and confirm on fluoroscopy or navigation that the cranial screw has not entered the joint above.
Decompression at the next level. An adjacent-level laminectomy, or a wide decompression with extensive facet removal, destabilises the segment next to the construct.
It is intuitive that longer fusions cause more ASD, and the biomechanics say so, but the landmark studies are nuanced. Ghiselli (2004) found no correlation between lumbar fusion length and ASD, and Hilibrand (1999) found single-level cervical fusion carried a higher adjacent-level risk than multilevel fusion. These findings are frequently used to argue that natural-history progression of spondylosis, not just biomechanical stress, drives ASD. "Shortest necessary fusion" remains sensible practice, stated as principle rather than as proven prevention.
Prevention at the index operation. The levers the surgeon holds follow directly from the modifiable factors:
- Restore sagittal alignment: match lumbar lordosis to pelvic incidence, with adequate lordosis
- Preserve the facet joints: avoid unnecessary facet removal and keep the cranial screw out of the UIV+1 facet
- Preserve the posterior musculoligamentous complex, and do not extend a decompression into the adjacent facet or lamina
- Choose a sensible construct endpoint: end at a stable level rather than a mobile segment
- Fuse no more than necessary
- Treat the comorbidities: BMI, smoking, bone health
Prophylactic hardware. Surgeons have also tried to prevent ASD at the index operation with motion-sparing hardware, the so-called "topping-off" construct: a semi-rigid or dynamic rod, an interspinous process device or a pedicle-based dynamic stabiliser at the level immediately above the fusion to soften the stress transition, or a hybrid of fusion with an adjacent disc replacement. The evidence has been disappointing. Randomised and comparative studies of dynamic stabilisation, interspinous spacers and topping-off constructs have not reliably shown a reduction in clinically important ASD, and the devices bring their own problems: screw loosening, device failure, interspinous fracture and cost.
That dovetails with the natural-history argument: if much of ASD is the patient's own progressive spondylosis, a gadget at one extra level cannot prevent it. Cervical disc arthroplasty is the one motion-preserving strategy with the best, though still debated, ASD-reduction data, and that is a different setting. Topping-off and hybrid constructs remain investigational and should not be presented as standard care; the prevention that matters is technique, not implants.
Pathophysiology and Biomechanics
Load transfer. Fusion eliminates motion at the treated segments, so load and motion transfer to the adjacent levels. Stress on the adjacent disc and facets rises, and degeneration at those levels accelerates. That is the load transfer hypothesis, and it is the biomechanical basis of ASD.
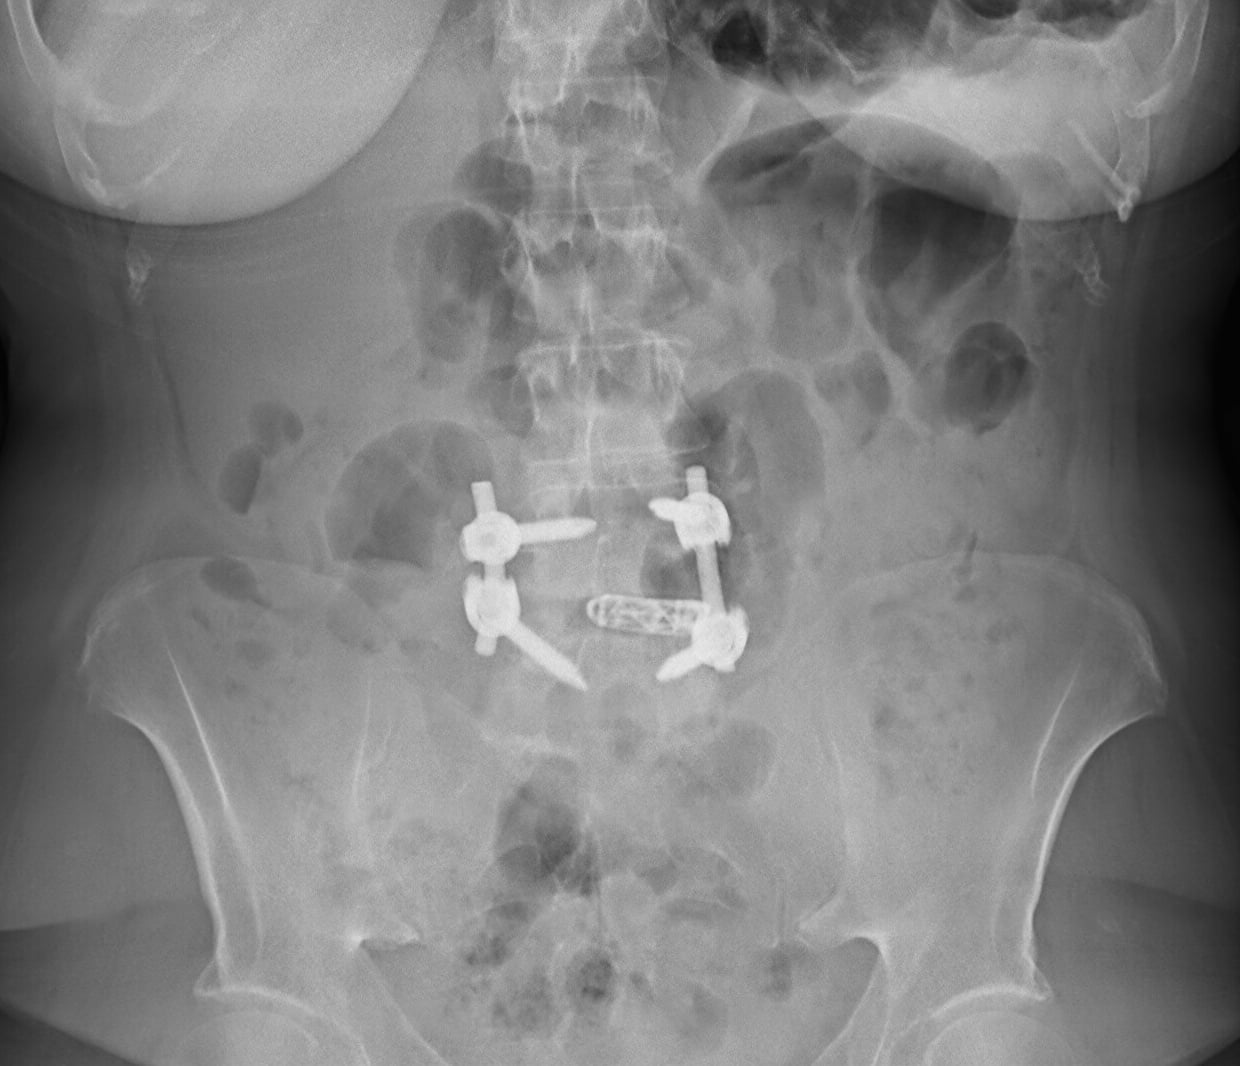
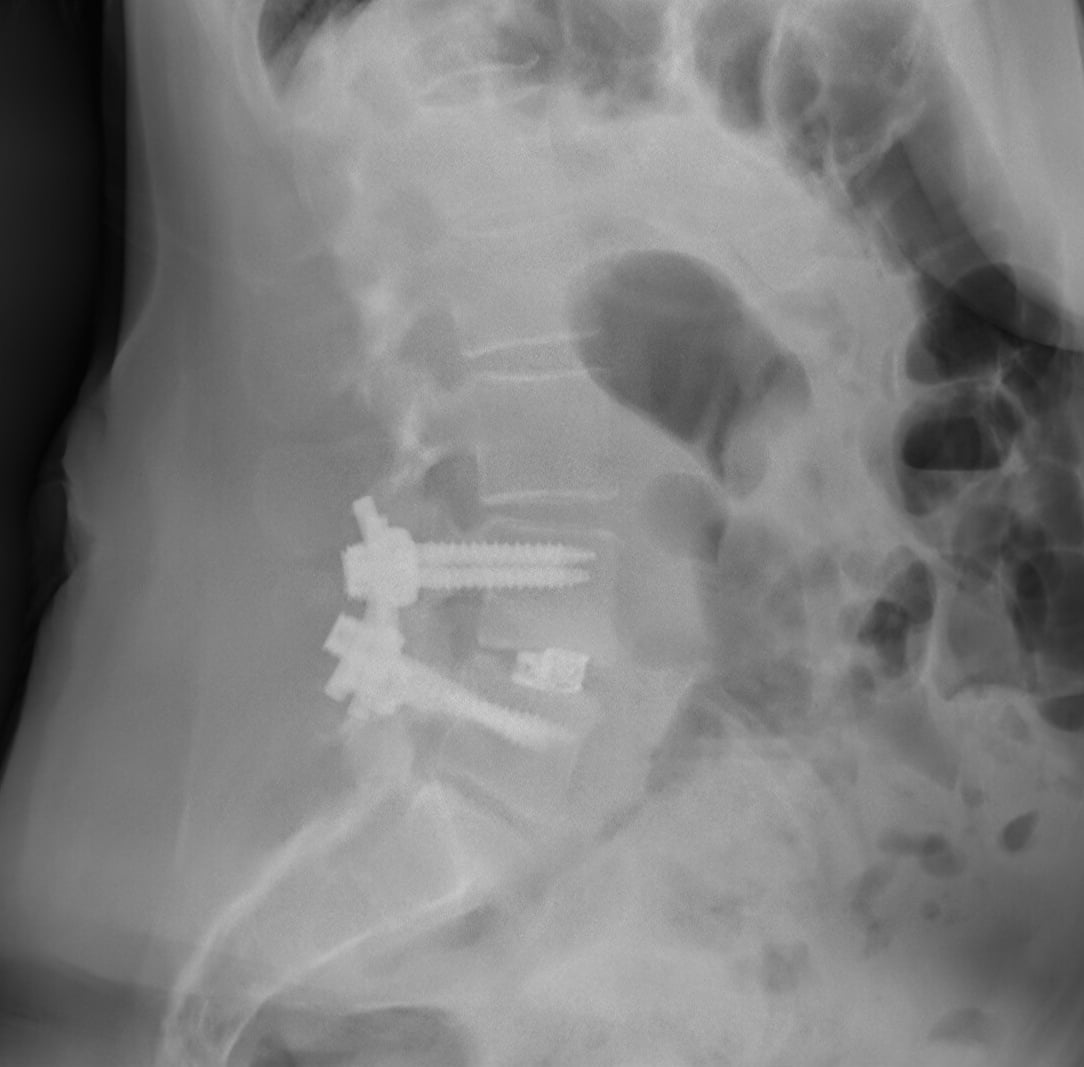
What the laboratory shows. Cadaveric studies show increased intradiscal pressure at the adjacent levels after fusion, increased facet joint loading above the fusion, and greater motion at the adjacent segments to compensate for the fused levels. Finite-element models show the same, and show that longer constructs raise stress at the transition zones.
What changes the load. The stress an adjacent level sees depends on the construct and on the level itself:
- Fusion length: a longer fusion places greater stress on the adjacent levels
- Fusion position: sagittal balance affects how the load is distributed
- Adjacent segment quality: a segment with pre-existing degeneration is the vulnerable one
- Construct rigidity: stiff pedicle screw constructs transfer more load than cables or wires
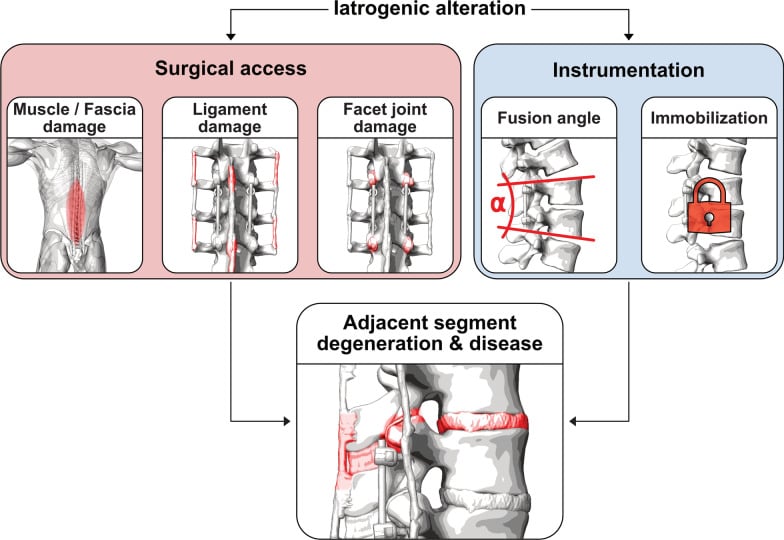
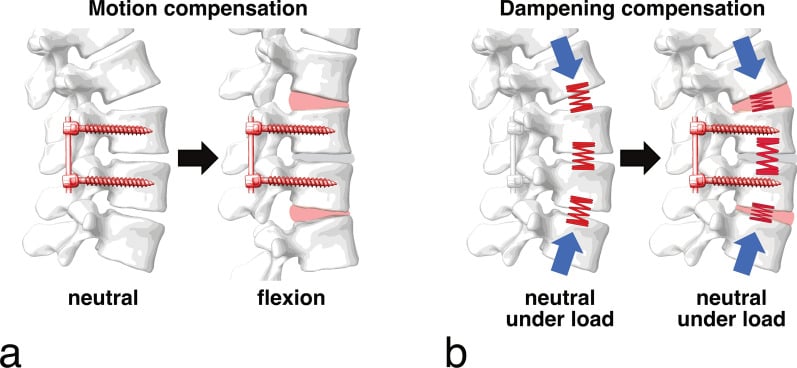
The natural history argument. Patients who need a fusion already have degenerative disease, and their adjacent segments may have subclinical degeneration at the time of surgery. Some ASD is therefore natural progression of that disease, and age-matched controls develop degeneration too. The high rate of imaging change set against the much lower rate of clinical disease supports natural history playing a major role.
The laboratory signal does not translate cleanly into clinical ASD. Cadaveric and finite-element models predict more adjacent stress with longer constructs, yet the landmark clinical series found no such fusion-length effect (the trap under Risk Factors). Biomechanics is necessary but not sufficient to explain ASD; the truth involves both biomechanical factors and natural history, and both contribute.
Classification Systems
By location. ASD is described by where it sits relative to the construct.
- Location
- Above fusion
- Frequency
- More common (2:1)
- Clinical Features
- Stenosis, instability, radiculopathy
- Location
- Below fusion
- Frequency
- Less common
- Clinical Features
- Disc herniation, stenosis
- Location
- Proximal junction
- Frequency
- Long fusions
- Clinical Features
- Kyphotic collapse at UIV
By severity. Radiographic change at the adjacent segment is graded by what the imaging shows.
- Radiographic Findings
- No changes
- Clinical Significance
- Normal adjacent segment
- Radiographic Findings
- Mild disc space narrowing or osteophytes
- Clinical Significance
- Usually asymptomatic
- Radiographic Findings
- Moderate narrowing with facet changes
- Clinical Significance
- May be symptomatic
- Radiographic Findings
- Severe stenosis, instability, or spondylolisthesis
- Clinical Significance
- Often symptomatic
Clinical Assessment
History. The pattern to elicit is a symptom-free interval after the index surgery, months to years, followed by new pain in a location or pattern different from the original complaint: axial back pain, radicular symptoms, or both. It may mimic the original presentation. Ask about functional impact (walking distance, activities of daily living) and the details of the previous surgery: the levels fused, the approach and any complications.
Presentation patterns. The pathology at the adjacent level decides the symptoms:
- Stenosis: neurogenic claudication, radiculopathy
- Disc herniation: radicular pain, dermatomal sensory changes
- Instability: mechanical back pain, worse with motion
- Spondylolisthesis: back pain, radicular symptoms, gait changes
Examination. The findings point towards the pathology and towards the operation it will need.
- Suggests
- Nerve root compression at adjacent level
- Management Implication
- May need decompression
- Suggests
- Central stenosis above fusion
- Management Implication
- Extension of fusion likely
- Suggests
- Failed to restore lordosis at index
- Management Implication
- Major reconstruction needed
- Suggests
- Instability at adjacent level
- Management Implication
- Fusion extension required
- Suggests
- May be discogenic/facetogenic
- Management Implication
- Consider less invasive options
Progressive neurological deficit, cauda equina symptoms or severe instability require urgent assessment and likely intervention. Most ASD presents insidiously, with gradual symptom development.
Differential diagnosis. New or recurrent symptoms after a fusion are not automatically ASD. Exclude the mimics systematically before attributing symptoms to the adjacent level; several require entirely different management.
- Distinguishing Features
- Symptom-free interval then new pain at NEW level/dermatome
- Key Investigation
- MRI shows degeneration at level next to fusion
- Management Difference
- Decompression or fusion extension
- Distinguishing Features
- Persistent/recurrent axial pain at SAME level, no symptom-free interval
- Key Investigation
- CT (lucency, hardware halo), flexion-extension motion
- Management Difference
- Revision of original fusion, not extension
- Distinguishing Features
- Mechanical pain, screw haloing or rod fracture
- Key Investigation
- CT and radiographs
- Management Difference
- Hardware revision
- Distinguishing Features
- Symptoms localise to operated level
- Key Investigation
- MRI/CT at index level
- Management Difference
- Targeted re-decompression
- Distinguishing Features
- Constitutional symptoms, raised CRP/ESR
- Key Investigation
- Inflammatory markers, MRI, aspiration
- Management Difference
- Debridement, antibiotics
- Distinguishing Features
- Acute pain, osteoporosis, often at UIV
- Key Investigation
- CT/MRI (STIR oedema)
- Management Difference
- Bracing, cement, or extension
- Distinguishing Features
- Groin or buttock pain, positive provocation tests
- Key Investigation
- Hip/SI exam, diagnostic injection
- Management Difference
- Hip or SI-directed treatment
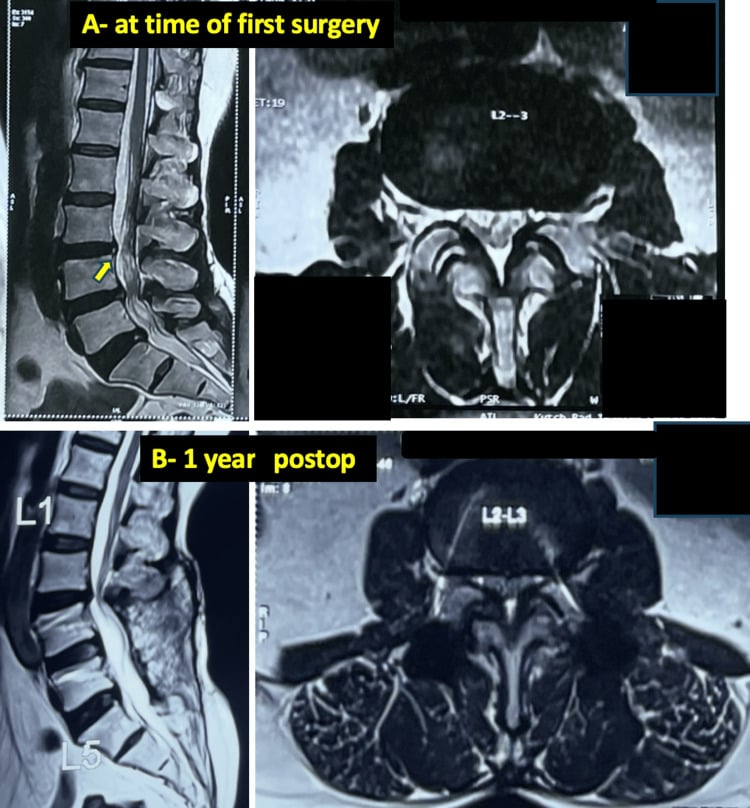
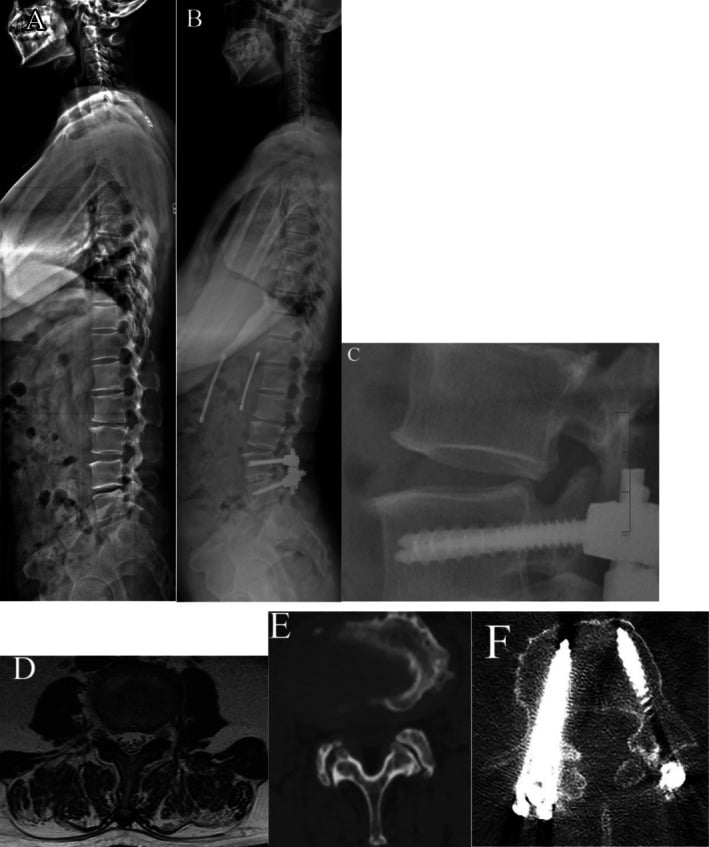
The single most important distinction is ASD versus pseudarthrosis. A solid fusion must be confirmed, ideally on CT, before fusion extension is considered: extending a fusion onto a non-united segment will fail.
Investigations
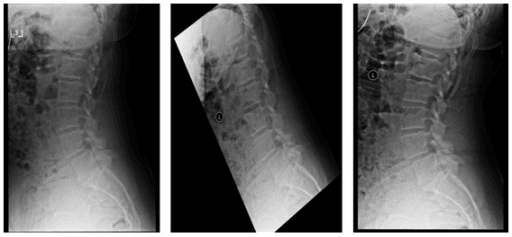
Radiographs. Standing views are the first-line study and are essential, because they reveal functional alignment and dynamic change:
- AP and lateral lumbar spine
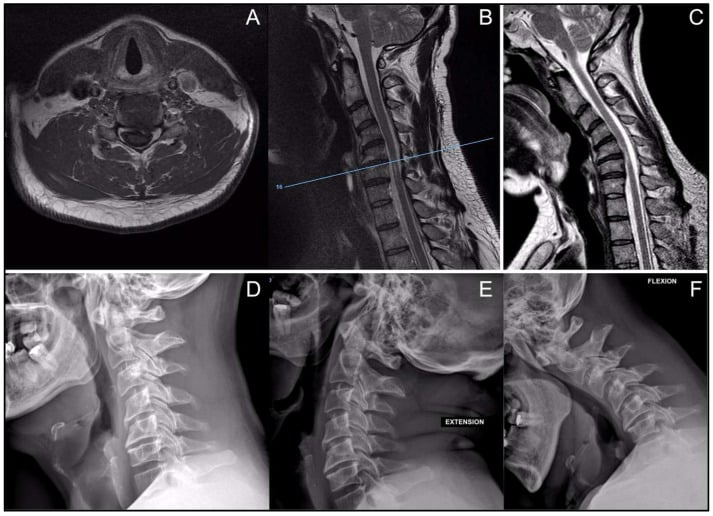
- Flexion-extension views for dynamic instability
- Long-cassette scoliosis views if there is deformity
Look for disc space narrowing at the adjacent levels, osteophyte formation, endplate sclerosis, a new spondylolisthesis, loss of disc height compared with the preoperative films, and change in sagittal alignment. Dynamic instability is translation greater than 4 mm or angulation greater than 10 degrees on flexion-extension.
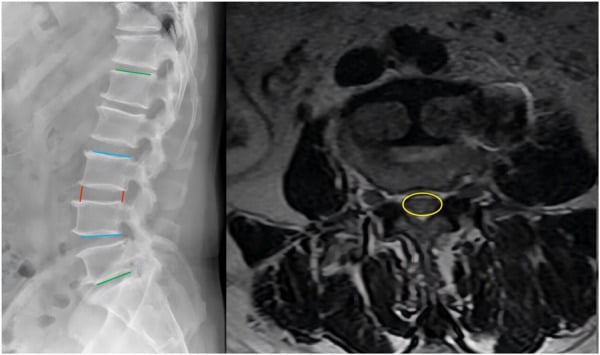
MRI. The study for soft tissue and neural assessment, indicated for radicular symptoms, neurogenic claudication or progressive symptoms, and essential for assessing neural compression and planning surgery. It shows disc degeneration or herniation, central or foraminal stenosis, ligamentum flavum hypertrophy, facet joint effusion or cyst, and nerve root compression. Metal artefact from the hardware is the limitation, and titanium-compatible sequences may be needed.
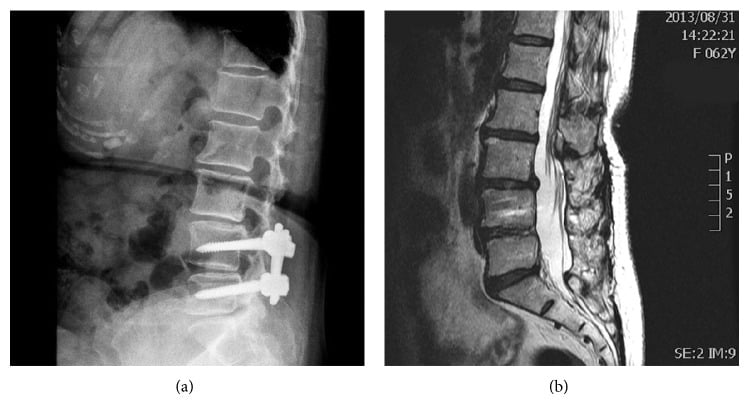
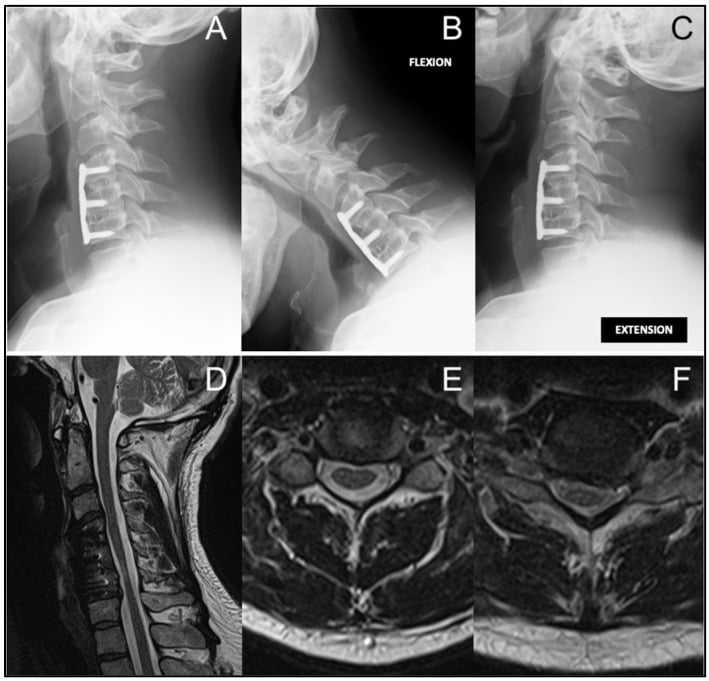
CT. The study for bone detail and fusion status: whether the fusion is solid or a pseudarthrosis, bone quality, the detail of facet arthropathy, and preoperative planning. CT myelography is the alternative when MRI is contraindicated or inadequate, and it allows dynamic assessment.
Diagnostic injections. Selective nerve root blocks, facet joint injections, medial branch blocks and adjacent-level discography (controversial) localise the pain source. They confirm the pain generator, help distinguish ASD from pseudarthrosis and guide surgical planning, and they earn their place when the clinical and imaging findings are discordant.
Management Algorithm
- 1Diagnosis
Confirm ASD vs pseudarthrosis, hardware failure, other pathology
Accurate diagnosis guides treatment
- 2Conservative Trial
PT, medications, injections for 3-6 months
50% may improve with conservative care
- 3Surgical Planning
Assess instability, neural compression, sagittal balance
Determines surgical approach
- 4Surgery
Decompression alone vs extension of fusion vs motion preservation
Based on pathology and patient factors
Conservative first. Symptomatic ASD is treated non-operatively for 3-6 months before surgery is considered, and approximately 50% of patients may improve with conservative treatment. The programme:
- Physiotherapy: core strengthening, flexibility exercises, posture optimisation, activity modification
- Medication: NSAIDs, neuropathic agents (gabapentin, pregabalin), short-term oral steroids for an acute exacerbation, muscle relaxants
- Injections: epidural steroid injections, facet joint injections, medial branch blocks, selective nerve root blocks
- Bracing: a limited role in the lumbar spine; it may provide short-term relief
When conservative treatment fails. The choice of operation depends on the pathology, the stability of the segment, the alignment and the patient.
Decompression alone. For isolated stenosis without instability, with preserved disc height and no significant spondylolisthesis. It preserves motion; the risk is that it destabilises the segment and a fusion is needed later.
Extension of fusion. For instability, spondylolisthesis, or sagittal imbalance requiring correction. It is the most common surgical approach, and most symptomatic ASD that comes to surgery is treated this way. The disadvantage is further load transfer to the next level.
Motion preservation and hybrid constructs. Total disc replacement adjacent to the fusion, or dynamic stabilisation, may reduce load transfer, but both are investigational with limited long-term data. A hybrid construct, fusion at the index level with motion preservation at the adjacent level, has the theoretical advantage of reduced ASD and is technically demanding.
- Favours Decompression Alone
- Stable segment
- Favours Fusion Extension
- Instability present
- Favours Decompression Alone
- Preserved
- Favours Fusion Extension
- Collapsed
- Favours Decompression Alone
- Absent
- Favours Fusion Extension
- Present
- Favours Decompression Alone
- Maintained
- Favours Fusion Extension
- Imbalanced
- Favours Decompression Alone
- Minimal
- Favours Fusion Extension
- Significant
- Favours Decompression Alone
- Single level, focal
- Favours Fusion Extension
- Multiple levels
Surgical Technique
Fusion extension. Planning covers how many levels to add, whether sagittal balance needs correcting, where the upper instrumented vertebra (UIV) will be, and the quality of the bone. Extending to the sacrum and pelvis may be needed if fusing below L4.
Fusion Extension Steps
Posterior approach extending above or below the previous incision. Identify the previous hardware. Assess for loosening or pseudarthrosis at the original levels.
Evaluate the stability of the existing instrumentation. It may need revising if loose. Connect the new segments to the existing construct if it is stable.
Decompress the neural elements at the affected level or levels. Perform an adequate foraminotomy if there are radicular symptoms.
Place pedicle screws at the new levels. Connect to the existing construct with rods or rod-to-rod connectors. Consider an interbody fusion for stability.
Address sagittal balance if needed. Restore appropriate lordosis. Confirm alignment on imaging.
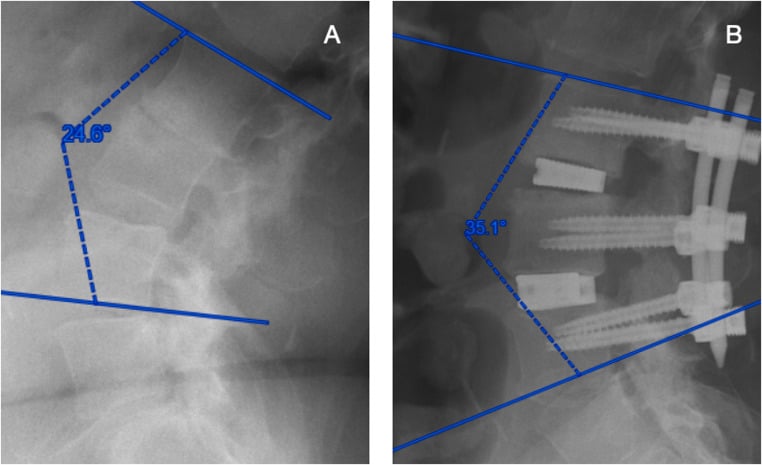
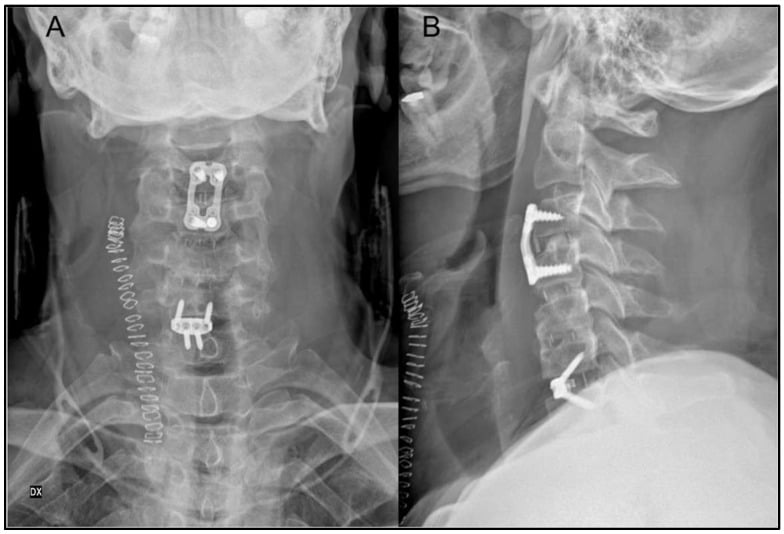
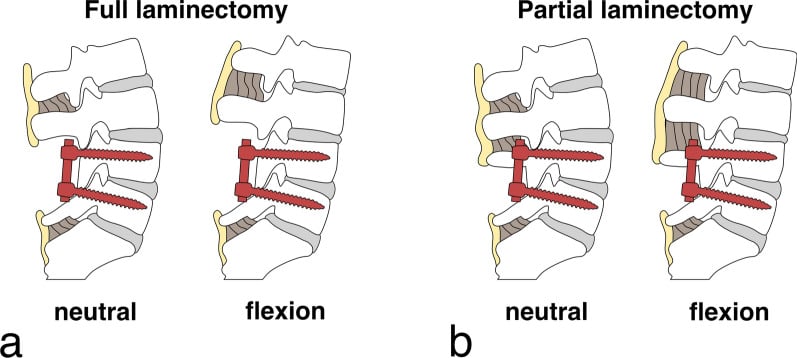
Adjacent-level decompression. For the patient who meets the criteria for decompression alone and has focal neural compression. A laminotomy or laminectomy at the adjacent level, preserving as much facet as possible (greater than 50%), with a foraminotomy for radicular symptoms, taking care not to destabilise the segment. It carries less morbidity than a fusion and preserves motion at that level; against that is a 10-20% risk of subsequent instability, which may need a fusion later. Patient selection is critical.
Motion preservation. The options are total disc replacement at the adjacent level, dynamic stabilisation devices and interspinous process devices. Total disc replacement replaces the disc at the level adjacent to the fusion and theoretically reduces load transfer; it requires intact posterior elements and has limited application for extension to a fusion. Dynamic stabilisation uses pedicle screw-based systems with a flexible connection that allow some motion while providing stability, with mixed outcomes in the literature.
Long-term data are limited, patient selection is critical, and motion preservation may reduce but not eliminate ASD. It remains investigational for treating or preventing ASD.
Complications
Revision surgery. Revision surgery for ASD has higher complication rates than primary surgery. The complications, by timing:
- Intraoperative: dural tear (more common in revision), nerve root injury, vascular injury with an anterior approach, hardware malposition
- Early postoperative: wound infection (higher in revision surgery), hardware failure, adjacent-level injury from retraction, medical complications
- Late: pseudarthrosis at the new fusion, hardware loosening, recurrent ASD at the next level, persistent symptoms
The cascade. Each extension creates a new transition zone and puts the next adjacent level at risk; after a fusion extension, symptomatic ASD continues at 2.5% per year. The end result may be multiple revisions and a long fusion. The possibility of a cascade is what makes prevention at the index operation, and attention to the modifiable risk factors, matter.
Postoperative Care
After fusion extension. Recovery follows the phases below, with bone healing assessed at 3-6 months on standing radiographs.
Recovery Phases
Mobilisation with physiotherapy. DVT prophylaxis. Wound monitoring. Pain management.
Limited bending, twisting and lifting. Walking programme. Wound healing. Brace if prescribed.
Gradual increase in activity. Physiotherapy for core strengthening. Fusion assessment on X-ray.
Progressive return to normal activities. Impact activities when the fusion is solid. Long-term follow-up for the next adjacent level.
Protecting the next level. Prevention of ASD at the newly adjacent levels is an important component of care, and much of it is the patient's: smoking cessation, weight management, bone health optimisation, activity modification, core strengthening and regular follow-up surveillance.
Outcomes and Prognosis
Surgical treatment of ASD is generally effective but carries the risk of further ASD at the next levels.
- Success Rate
- 50%
- Recurrent ASD Risk
- N/A
- Notes
- Initial trial for all
- Success Rate
- 60-70%
- Recurrent ASD Risk
- 10-20% need later fusion
- Notes
- Select patients only
- Success Rate
- 70-80%
- Recurrent ASD Risk
- Continues at 2.5%/yr
- Notes
- Most common approach
- Success Rate
- Variable
- Recurrent ASD Risk
- May be reduced
- Notes
- Limited long-term data
- Better Prognosis
- Short (less than 6 months)
- Worse Prognosis
- Prolonged (greater than 2 years)
- Better Prognosis
- Single level
- Worse Prognosis
- Multiple levels
- Better Prognosis
- Balanced
- Worse Prognosis
- Fixed imbalance
- Better Prognosis
- Normal
- Worse Prognosis
- Osteoporotic
- Better Prognosis
- Non-smoker
- Worse Prognosis
- Current smoker
- Better Prognosis
- None
- Worse Prognosis
- Multiple prior surgeries
Guidelines, Registries & Global Practice
Global epidemiology
- Symptomatic ASD requiring surgery is a leading cause of lumbar fusion revision worldwide; pooled radiographic degeneration is ~26.6% (lumbar) and ~32.8% (cervical) (Hashimoto 2018).
- A systematic review reported a higher prevalence of lumbar ASDeg in Western than in Eastern populations (Cannizzaro 2022), likely reflecting differences in surgical indications, BMI distribution and follow-up imaging practice rather than a single biological cause.
- As global life expectancy and fusion volumes rise, the absolute burden of ASD is increasing, making prevention at the index operation a worldwide priority.
Side-by-side guidance (recommendations converge more than they differ)
- Region
- US / international
- Position relevant to ASD
- Decompression with fusion for instability; emphasises restoring alignment and shortest appropriate construct
- Region
- UK
- Position relevant to ASD
- Exhaust non-surgical care before revision; no routine prophylactic extension of fusion
- Region
- International (AO Foundation)
- Position relevant to ASD
- Standardising ASD definitions (ASDeg vs ASDis); restore sagittal balance and avoid facet violation
- Region
- Europe
- Position relevant to ASD
- Spinopelvic alignment central to deformity and ASD prevention; PI-LL matching emphasised
- Region
- International
- Position relevant to ASD
- Age-adjusted PI-LL and SVA targets to reduce mechanical complications and ASD
All major societies agree on three points: (1) confirm the diagnosis and exclude pseudarthrosis/infection before surgery, (2) treat conservatively first, and (3) restore sagittal alignment and avoid iatrogenic destabilization at the index operation. Genuine differences are minor and largely about thresholds rather than principles.
Registry evidence
- Large national spine registries (e.g. the Swedish Spine Register (Swespine), the British Spine Registry, and Norwegian (NORspine) datasets) capture reoperation as a proxy for symptomatic ASD and consistently identify revision for adjacent-level pathology as a major late reoperation cause.
- Registry reoperation data underpin patient counselling on long-term revision risk and are increasingly used to benchmark alignment-restoring techniques.
High- vs limited-resource practice variation
- Well-resourced settings: routine long-cassette standing radiographs for spinopelvic parameters, MRI with metal-artifact-reduction sequences, navigation/robotics to reduce facet violation, and access to revision deformity surgery and arthroplasty.
- Limited-resource settings: sagittal alignment may be judged on standard radiographs without full spinopelvic measurement; metal-artifact MRI and revision deformity capacity may be scarce, so prevention at the index operation and prolonged non-operative management carry even greater weight.
- Bone-health optimization (vitamin D, osteoporosis treatment) and smoking cessation are universally relevant, low-cost, modifiable measures that improve both prevention and revision outcomes regardless of setting.
Controversies and Areas of Uncertainty
ASD is one of the most debated topics in spine surgery, and examiners use it to test whether a candidate can reason with uncertain evidence rather than recite dogma.
Does motion preservation help? Total disc replacement reduces overall reoperation in some trials but has not consistently reduced adjacent-level surgery versus fusion at mid-term (Radcliff lumbar RCT; Harrod/Hilibrand cervical review). The counter-signal is the 7-year two-level Mobi-C IDE, with adjacent-level secondary surgery of 4.4% against 11.3% with ACDF, an industry-sponsored trial in highly selected patients. Whether arthroplasty truly prevents ASD, rather than avoiding fusion-specific reoperations, remains unproven.
Prophylactic extension. Should a mildly degenerate adjacent level be included in the index fusion? Hilibrand argued that symptomatic degenerate segments should be fused, but prophylactically extending onto an asymptomatic level lengthens the construct, creates a new transition zone and is not evidence-supported. Most surgeons fuse only symptomatic levels.
Do not commit dogmatically to "fusion causes ASD". A strong answer states that ASD is multifactorial, part iatrogenic (sagittal malalignment, facet violation) and part natural history (pre-existing spondylosis), cites Hilibrand and Ghiselli, and emphasises that the surgeon's controllable levers are restoring lordosis, preserving facets and selecting the shortest appropriate construct.
MCQ Practice Points
- Symptomatic ASD rate: roughly 2.5-3% per year (cervical 2.9%/yr - Hilibrand)
- Radiographic ASD at 10 years: approximately 30% (pooled 26.6% lumbar, 32.8% cervical)
- Surgery for ASD: lumbar 16.5% by 5 years, predicted 36% by 10 years (Ghiselli); cervical ~17% of all patients by 10 years
- L4-5 is most common ASD level (when fusion ends at L5)
- PI-LL mismatch increases ASD risk
- Pre-existing adjacent degeneration is strongest risk factor
- Radiographic vs symptomatic ASD distinction
- Risk factors for ASD
- Role of sagittal balance
- Treatment options for symptomatic ASD
- When to decompress alone vs extend fusion
- Prevention strategies
- Fusion length effect on ASD
- Fusion length is a TRAP, not a fact: biomechanics predicts more ASD with longer fusions, but Ghiselli found NO correlation and Hilibrand found single-level fusion carried HIGHER adjacent-level risk
- Fusion to L5 (vs S1) has higher ASD at L4-5
- Motion preservation may reduce but not eliminate ASD
- Both iatrogenic and natural history factors contribute
Q: What is the symptomatic ASD rate after lumbar fusion? A: Roughly 2.5-3% per year - but quote the compounded figures, which are what the patient hears: Ghiselli's lumbar series predicted 16.5% needing surgery by 5 years and 36.1% by 10 years. Radiographic ASD is far more common (~30% at 10 years) and only a quarter to a third becomes symptomatic.
Q: What is the single strongest risk factor for developing ASD? A: Pre-existing degeneration at adjacent levels at the time of index surgery is the strongest predictor.
Q: What sagittal parameter mismatch increases ASD risk? A: PI-LL mismatch greater than 10 degrees. Restoring appropriate lumbar lordosis is protective against ASD.
Q: How does fusion length affect ASD risk? A: This is the trap - do not answer "longer fusion, more ASD." Biomechanically longer constructs raise adjacent stress, but the landmark clinical studies refute the simple dogma: Ghiselli found NO correlation between lumbar fusion length and adjacent-segment surgery, and Hilibrand found single-level cervical fusion carried HIGHER adjacent-level risk than multilevel - the argument that natural-history spondylosis, not construct length alone, drives ASD. "Shortest necessary fusion" remains sensible practice, but state it as principle, not as proven ASD prevention.
Q: When can decompression alone be performed for ASD? A: When there is stable stenosis without spondylolisthesis and preserved disc height. Instability requires fusion extension.
Exam Cheat Sheet
Key Numbers
- Symptomatic ASD: 2.5-3% per year (cervical 2.9%/yr)
- Radiographic ASD at 10yr: ~30% (26.6% lumbar / 32.8% cervical)
- Surgery for ASD: lumbar 16.5% at 5yr, ~36% predicted at 10yr (Ghiselli)
- PI-LL mismatch: less than 10 degrees target
Risk Factors
- Pre-existing adjacent degeneration (strongest)
- Fusion length: DISPUTED - Ghiselli found no correlation; Hilibrand found single-level worse
- Sagittal imbalance/loss of lordosis
- Fusion ending at L5 (vs S1)
- Wide decompression destabilizing facets
Treatment Approach
- Conservative first: PT, NSAIDs, injections
- Decompression alone: stable, preserved disc
- Fusion extension: instability, spondylolisthesis
- Address sagittal imbalance when present
Prevention Strategies
- Shortest necessary fusion length
- Restore appropriate sagittal balance
- Preserve adjacent facet joints
- Smoking cessation, weight management
Exam Traps
- Confusing radiographic and symptomatic ASD
- Decompression alone with instability
- Ignoring sagittal balance
- Not discussing ASD with fusion patients
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 60-year-old woman who had L4-S1 fusion 5 years ago presents with new-onset bilateral leg pain and back pain. She has difficulty walking more than 100 meters. Examination reveals reduced ankle reflexes and sensory changes in the L3 distribution. Her previous surgery was uneventful with good relief of symptoms for the first 4 years.”
“You are planning a L4-L5 fusion for a 55-year-old man with spondylolisthesis. He asks about the risk of needing more surgery in the future because of problems at other levels. How would you counsel him?”
“A 58-year-old woman had L5-S1 fusion 8 years ago and now has symptomatic stenosis at L4-5. MRI shows severe stenosis with a 5mm spondylolisthesis at L4-5. Her standing X-rays show positive sagittal balance with loss of lumbar lordosis. How would you approach this?”
Evidence Base
Landmark Cervical ASD Natural History (Hilibrand)
- 374 patients, 409 anterior cervical arthrodeses, followed up to 21 years
- Symptomatic adjacent-segment disease occurred at a relatively constant 2.9% per year over the first 10 years
- Survivorship predicted 25.6% of patients (95% CI 20-32%) would develop new adjacent-level disease within 10 years
- Highest-risk levels were C5-6 and C6-7; risk was HIGHER after single-level than multilevel arthrodesis
- Authors concluded all symptomatic degenerated segments should be included in the index fusion
Lumbar Adjacent-Segment Survivorship (Ghiselli)
- 215 patients after posterior lumbar arthrodesis, mean follow-up 6.7 years
- Symptomatic degeneration warranting decompression or fusion predicted at 16.5% at 5 years and 36.1% at 10 years
- Disease-free survival 83.5% at 5 years and 63.9% at 10 years (Kaplan-Meier)
- No significant correlation between fusion length and adjacent-segment disease
- No significant correlation between preoperative adjacent-level arthritic grade and need for further surgery
Pooled Incidence of ASDeg and ASDis (Systematic Review)
- Pooled incidence of radiographic adjacent-segment degeneration: 26.6% (lumbar) and 32.8% (cervical)
- Approximately one-quarter to one-third of radiographic degeneration progresses to symptomatic disease
- Lumbar risk factors: age, high BMI, pre-existing adjacent degeneration, adjacent-level laminectomy, insufficient lumbar lordosis, multilevel fixation, osteoporosis
- Cervical risk factors: young age, pre-existing degeneration, short fusion, high T1 slope, plate placed close to adjacent disc
- Motion-preserving surgery appeared to carry lower ASD risk than conventional fusion
Risk Factors for Symptomatic Lumbar ASD (Meta-analysis)
- 16 studies, 3,553 patients pooled for symptomatic ASD after lumbar fusion
- High BMI and facet joint violation during screw insertion were significant surgical/patient risk factors
- Decreased pre- and post-operative lumbar lordosis and increased postoperative PI-LL mismatch significantly increased ASD risk
- Pre-existing adjacent disc degeneration and decreased adjacent disc height predicted ASD
- Anterior shift of the sagittal plumb line and higher postoperative pelvic tilt were also associated with ASD
Spinopelvic Imbalance and ASD After PLIF (Matsumoto/Okuda)
- 1:5 matched case-control study: 20 revision-for-ASD patients vs 100 controls after L4-5 single-level PLIF
- PI-LL mismatch of 10 degrees or more was present in 75% of ASD patients vs 43% of controls (p less than 0.01)
- Sagittal vertical axis of 50 mm or more was seen in 50% of ASD patients vs 21% of controls (p less than 0.01)
- ASD patients had significantly lower lumbar lordosis and higher pelvic tilt
- Even after single-level fusion, restoring segmental and lumbar lordosis appeared protective against ASD
Sagittal Alignment as an ASD Risk Factor (Djurasovic)
- Case-control study: 51 patients with adjacent-segment degeneration matched to controls
- ASD patients had significantly less lordosis through the fusion and across the lumbar spine after the index operation
- No significant difference in pre-existing adjacent-level degeneration between ASD and control groups
- No significant difference in smoking rates between groups
- Concluded fusion in abnormal sagittal alignment - not merely progression of pre-existing degeneration - predisposes to ASD
Lumbar TDR vs Fusion - 2-Level Reoperation (Radcliff RCT)
- Prospective RCT: 229 patients, 2-level degenerative disc disease, TDR (n=161) vs circumferential fusion (n=68)
- Overall adjacent-segment disease rate was only 3.5% (8/229) at 5 years
- Adjacent-level reoperation did not differ significantly between TDR (2.5%) and fusion (5.9%)
- Overall secondary surgery was lower with TDR (5.6%) than fusion (19.1%), but most fusion reoperations were instrumentation removal
- Excluding instrumentation removal, reoperation rates were similar - TDR was non-inferior to fusion
Cervical Motion Preservation vs Fusion for ASD (Systematic Review)
- Systematic review of 14 studies comparing cervical TDR with anterior cervical decompression and fusion (ACDF)
- Reoperation for clinical adjacent-segment pathology ranged 1.0% to 4.8%, with no statistically significant difference between TDR and ACDF
- No significant difference in radiographic or clinical ASP between cervical TDR and ACDF at short- to mid-term follow-up
- Insufficient evidence to recommend non-arthroplasty motion-preserving devices over fusion
- Highlighted lack of consistent ASD definitions across the literature