The Pure Motor Branch
- AIN is a purely motor nerve (except for sensory branches to the wrist joint).
- It supplies 3 muscles: FPL, FDP (Index/Middle), and Pronator Quadratus.
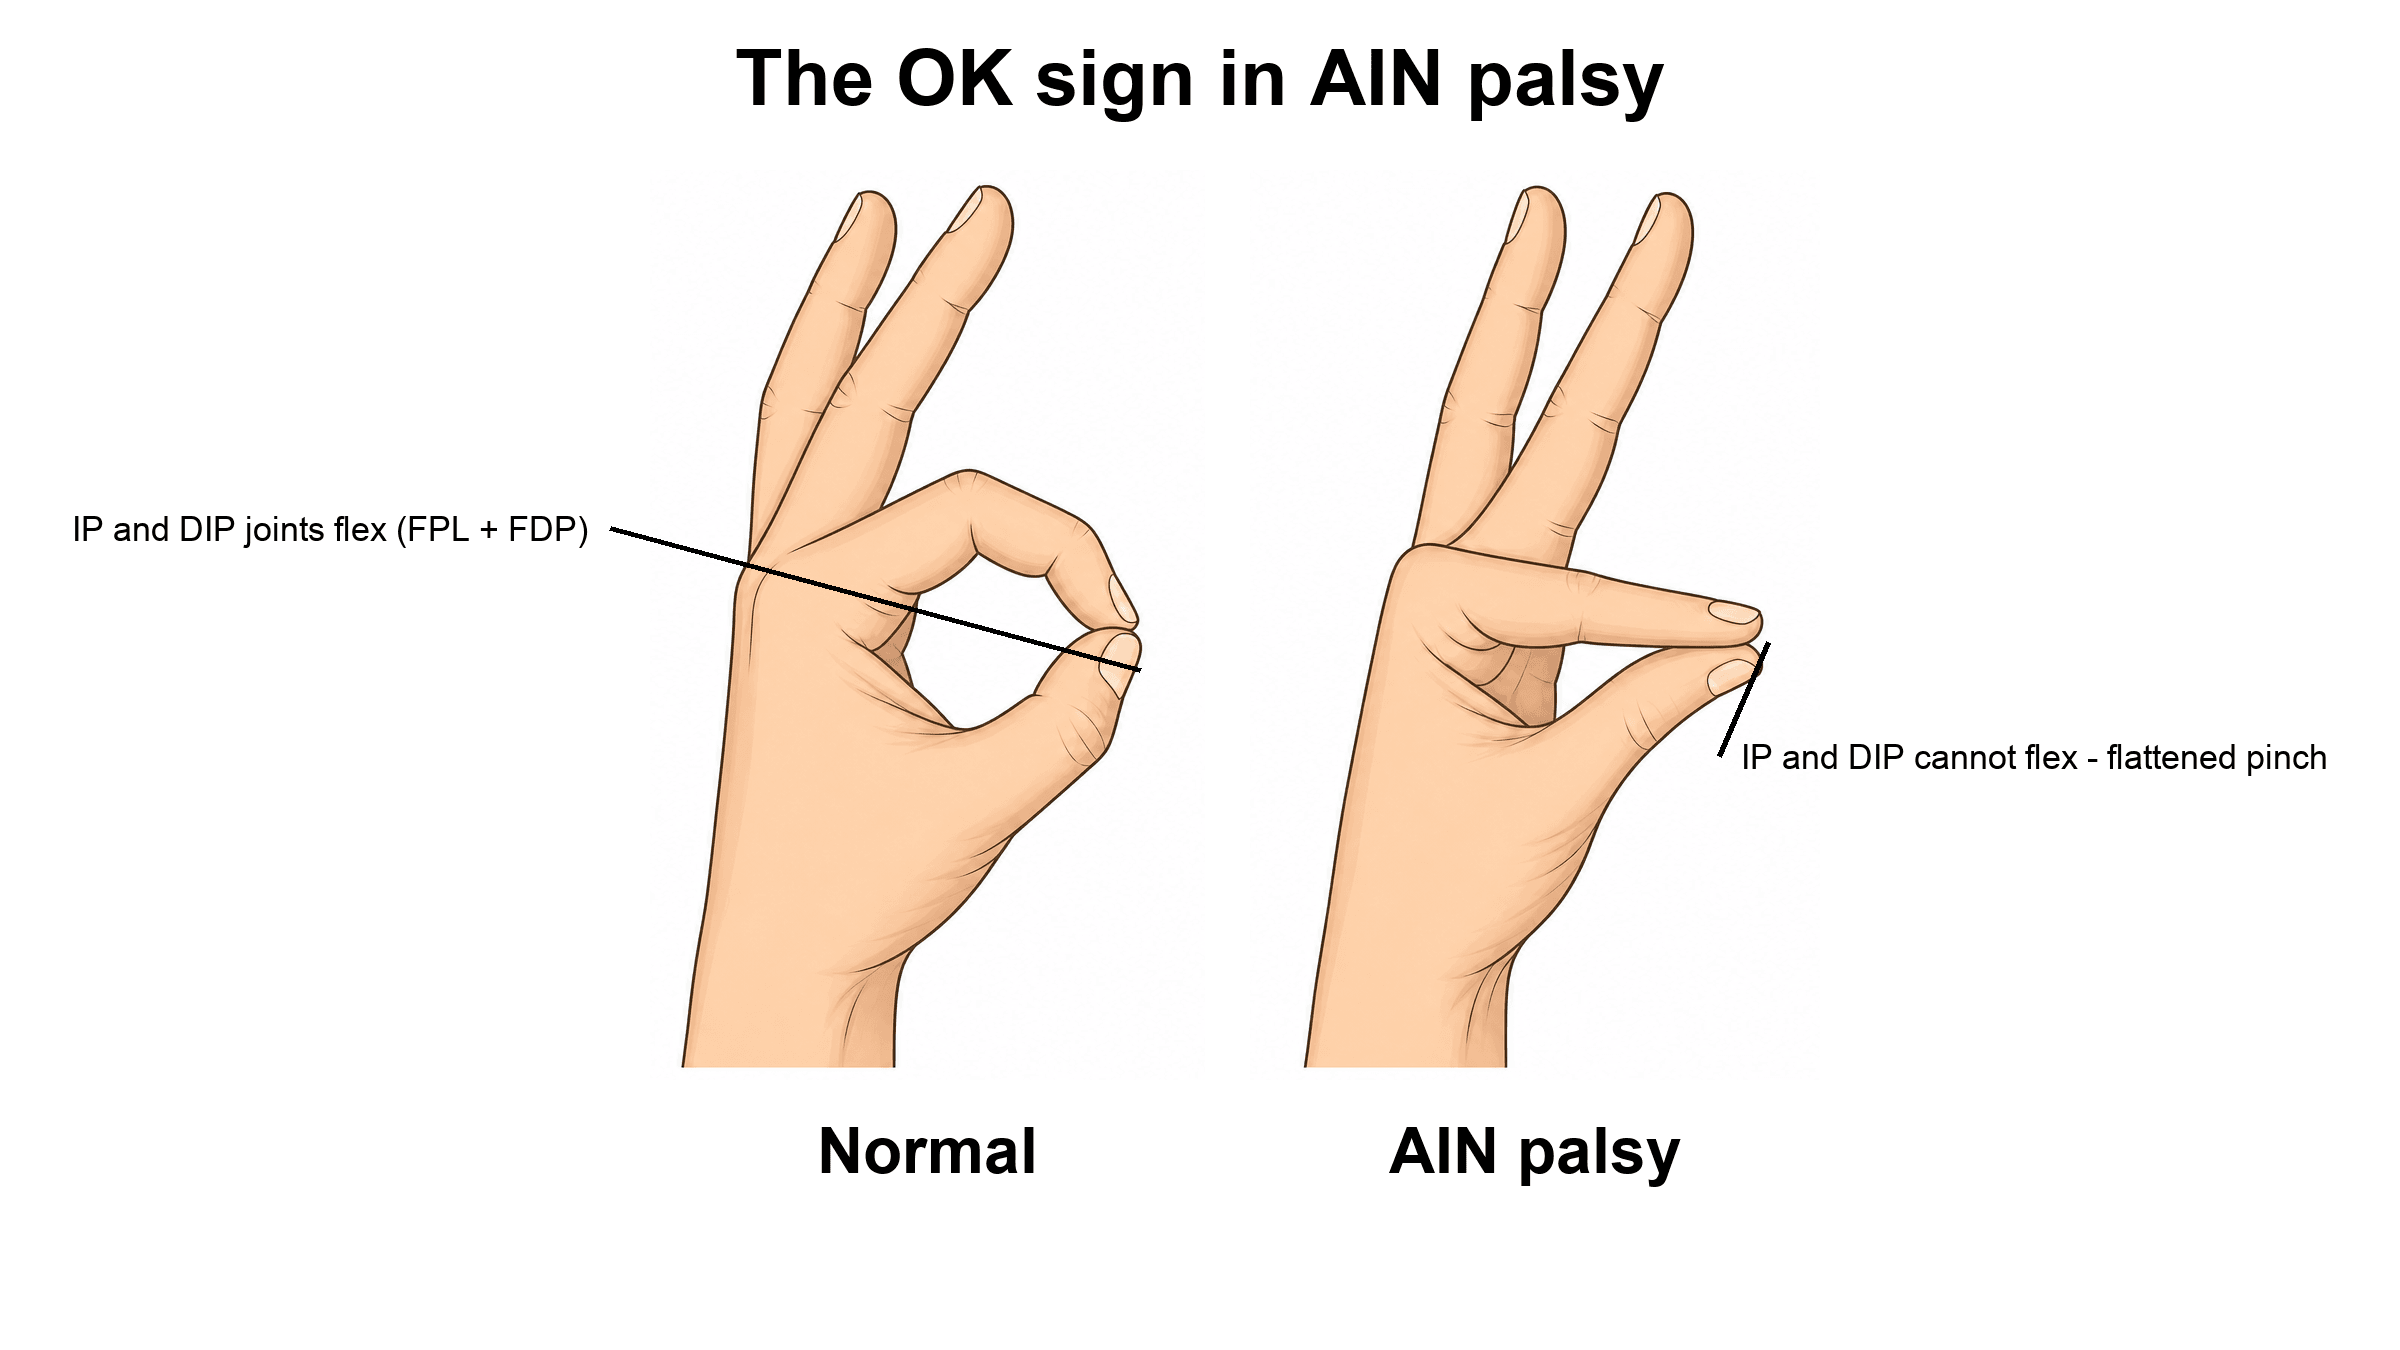
- Compression causes AIN Syndrome (Kiloh-Nevin): Inability to make the 'OK' sign.
- No cutaneous sensory loss in AIN syndrome (unlike Median nerve compression).
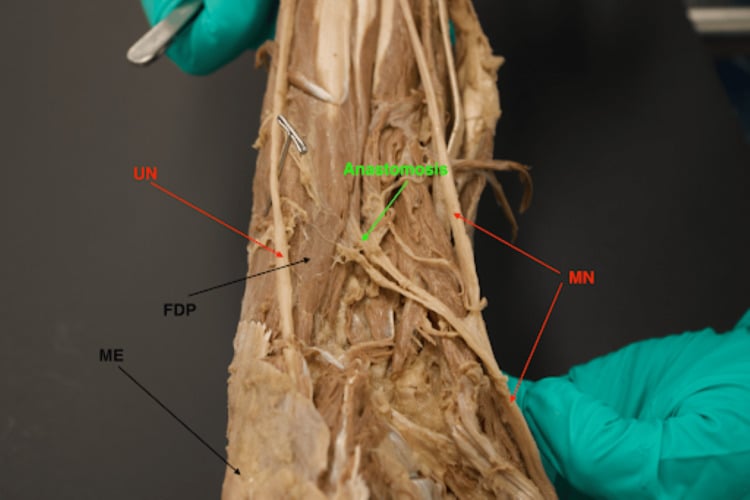
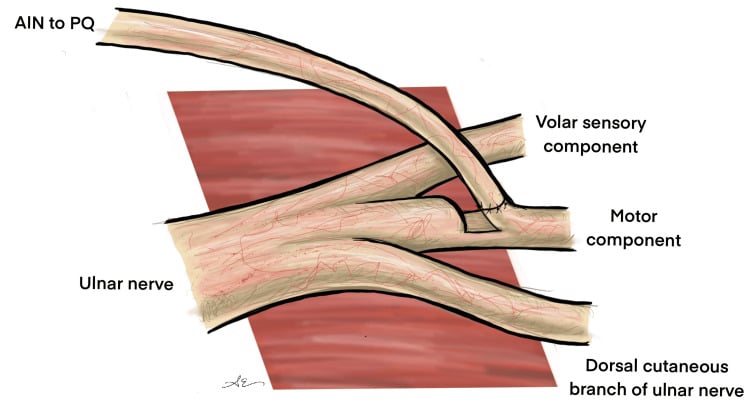
- Martin-Gruber Anastomosis is a crossover from AIN/Median to Ulnar nerve in the forearm.
- Parsonage-Turner Syndrome (Neuralgic Amyotrophy) can mimic AIN palsy.
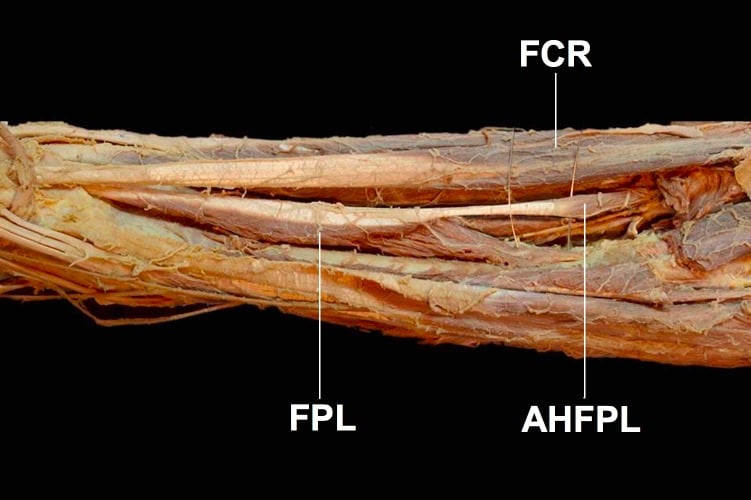
- “Gantzer's Muscle (Accessory FPL head) is the most common cause of compression.
- “In MGA, intrinsic hand muscles (normally ulnar) are innervated by the Median nerve.
- “The 'Spinner's Bands' (of FDS) can also compress the AIN.
Overview
The anterior interosseous nerve (AIN) is the largest branch of the median nerve in the forearm. It arises approximately 5-8 cm distal to the lateral epicondyle and courses deep on the interosseous membrane to supply the deep volar compartment.
"Pure motor", with a caveat. The AIN is classically described as a pure motor nerve, but it provides articular mechanoreceptor fibres to the wrist joint, composed of Pacinian corpuscles and Ruffini endings. Those afferents are what make it a target for wrist denervation, set out under Neurovascular.
Scope note. This page covers the nerve's surgical anatomy, variants and relations. For the AIN syndrome as a clinical entity — presentation, differential diagnosis (including Parsonage-Turner) and management — see anterior interosseous nerve syndrome.
Neurovascular
Origin. The AIN leaves the median nerve 5-8 cm distal to the lateral epicondyle, as it passes between the two heads of pronator teres. Its root value is C8-T1. It travels initially parallel to the median nerve, then dives deep.
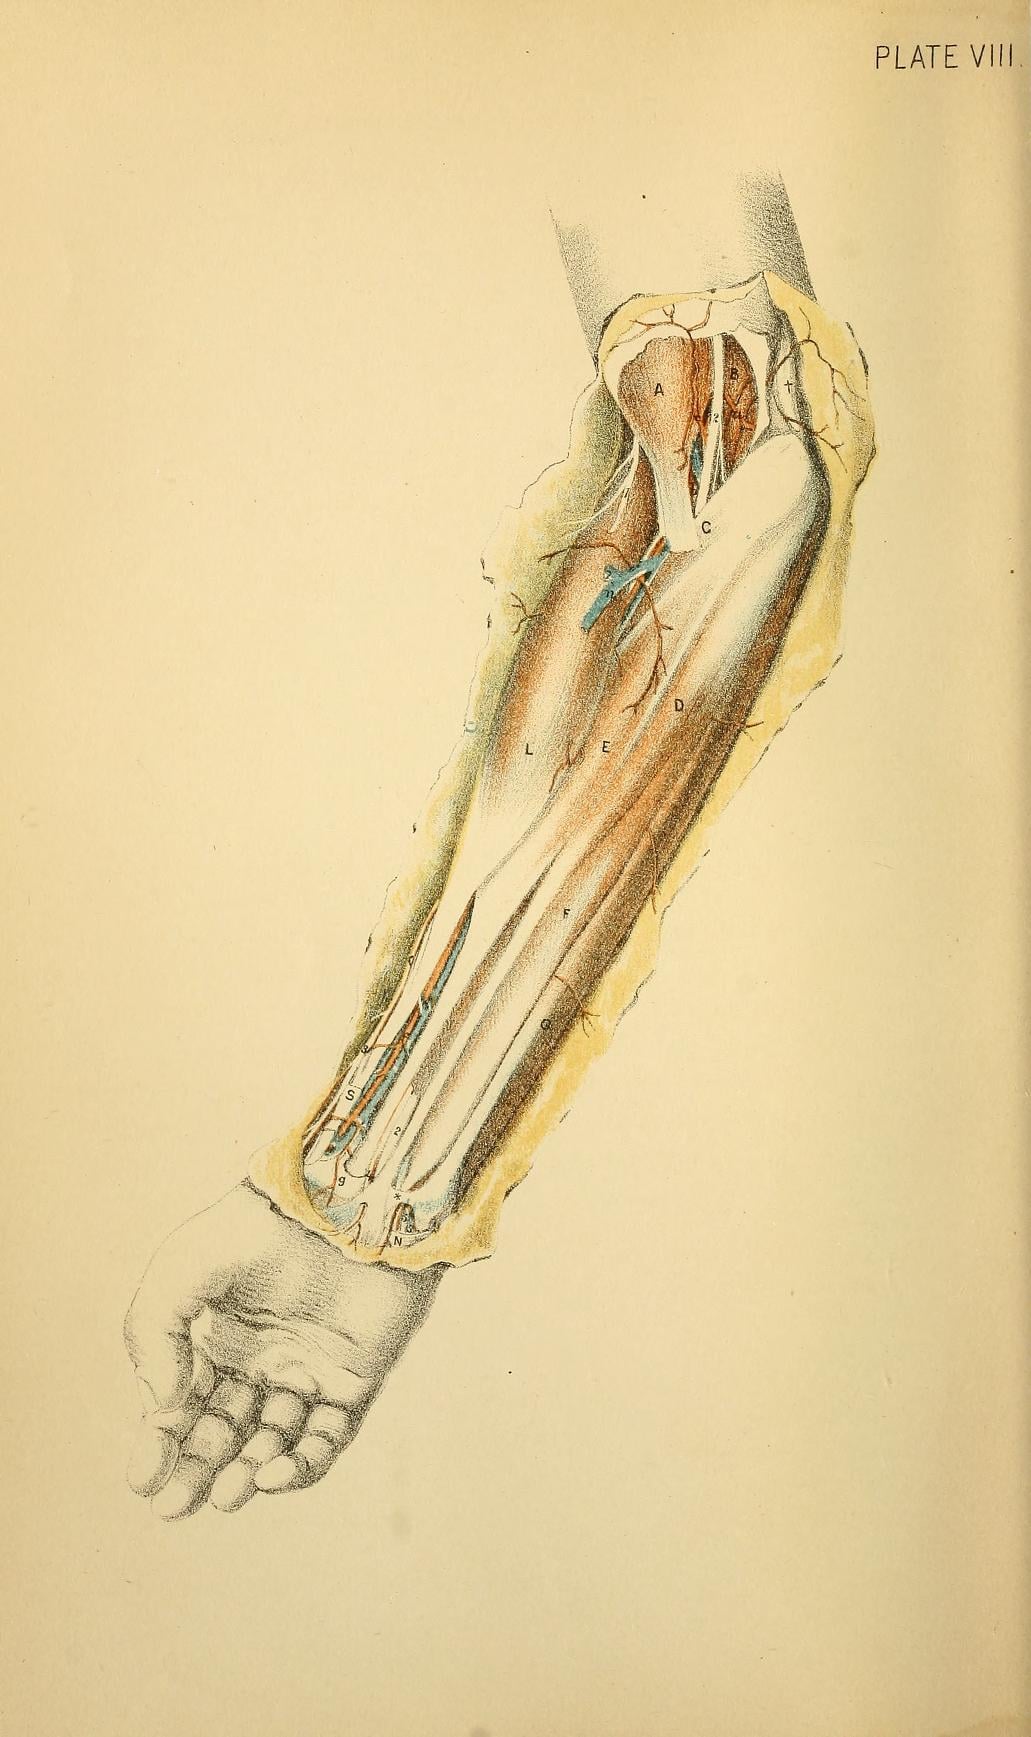
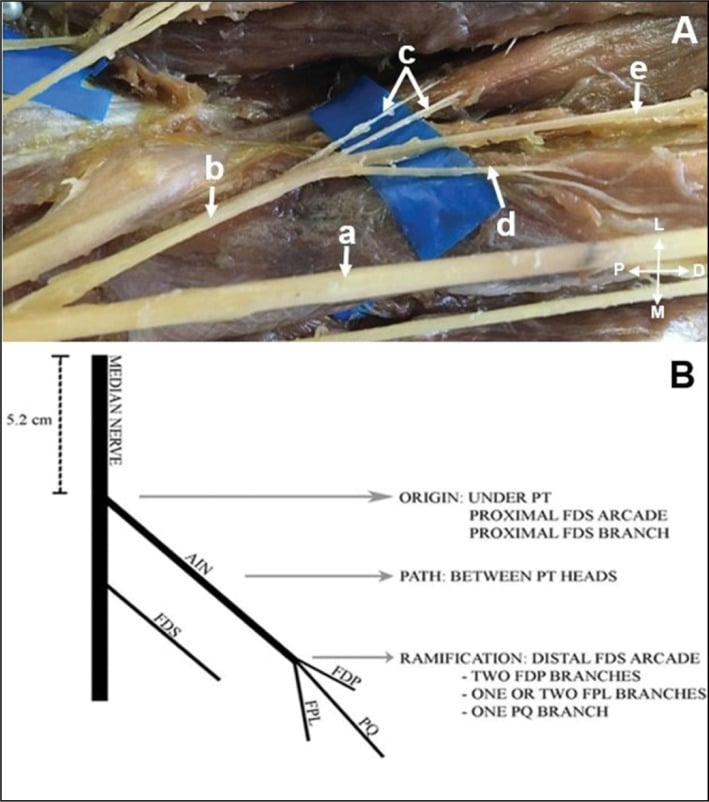
Relations. The nerve runs between FPL radially and FDP ulnarly, on the anterior surface of the interosseous membrane, and it lies strictly on that membrane. It is accompanied by the anterior interosseous artery, a branch of the common interosseous artery.
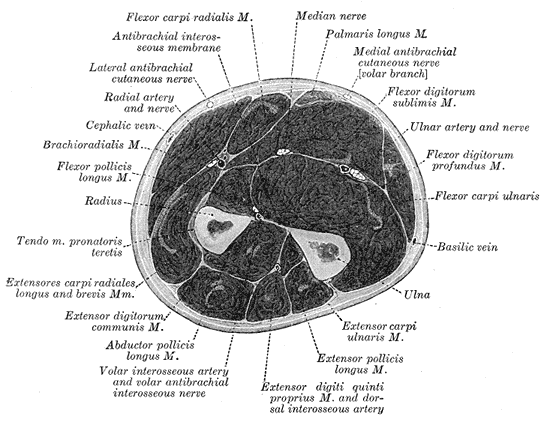
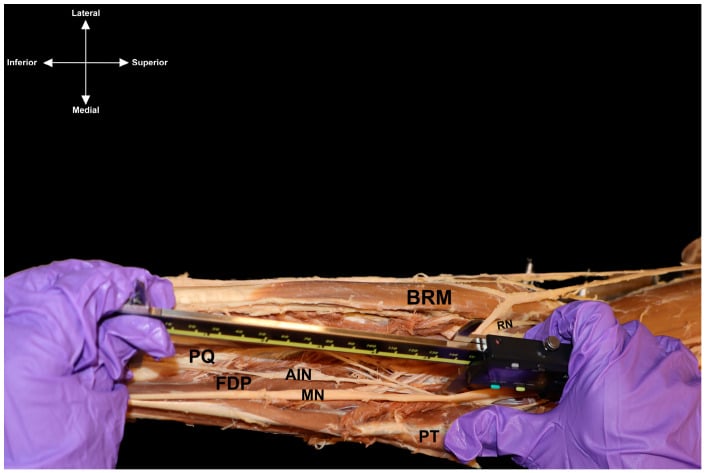
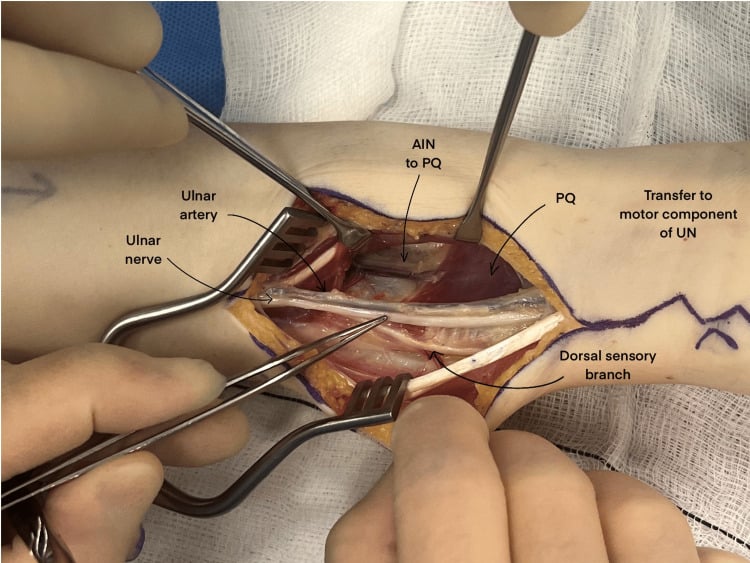
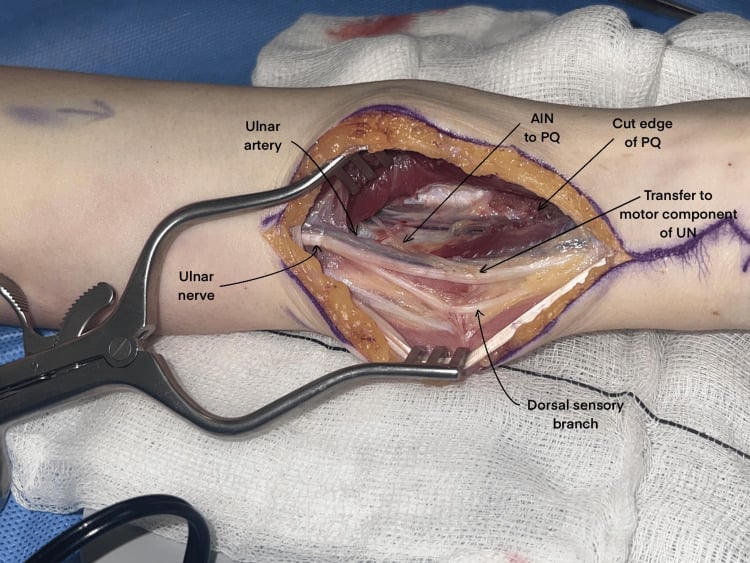
Termination. The AIN passes deep to pronator quadratus, supplies it, and its terminal continuation pierces the muscle to end as articular (sensory) branches to the wrist: the volar radiocarpal, midcarpal, intercarpal, distal radioulnar and CMC joints.
Articular branches and wrist denervation. The terminal articular twigs are the anatomical basis of total (or partial) wrist denervation, the Wilhelm procedure, in which the wrist's articular nerve supply is divided to relieve degenerative wrist pain while preserving motion. The two principal targets are the AIN and the posterior interosseous nerve (PIN); their terminal articular twigs are resected on the volar and dorsal wrist respectively, and a limited AIN-plus-PIN neurectomy is the most commonly performed version.
Why it costs no function. The twigs are sensory-only and lie distal to the last motor branch, the one to pronator quadratus, so denervation does not weaken pronation, finger flexion or grip. A diagnostic local-anaesthetic block of the AIN and PIN that abolishes the pain predicts a good response before committing to neurectomy.
Anatomical Variants and Anastomoses
Martin-Gruber anastomosis (MGA). A crossover of motor fibres from the median nerve (AIN) to the ulnar nerve in the forearm, present in about 15% of the population. It is typed by where the crossing fibres end up:
- Type I to the thenar muscles
- Type II to the first dorsal interosseous (FDI)
- Type III to the hypothenar muscles
The significance runs in both directions, and that is the examinable part. A proximal ulnar lesion may spare the intrinsics, because the fibres destined for them have already left the median nerve and cross over distal to the injury, so the ulnar palsy looks unexpectedly mild. A proximal median (or AIN) lesion can weaken ulnar-innervated intrinsics, because those crossing fibres are cut before they reach the ulnar nerve, so a median-territory injury mimics an ulnar palsy.
Sensation is not affected. MGA is a purely motor crossover, so any sensory finding must be explained by something else. Always check for an MGA when EMG findings conflict.

Clinical Assessment
Kiloh-Nevin syndrome (AIN palsy). The patient loses FPL (thumb IP flexion) and FDP to the index (DIP flexion), and pronation is weak when it is tested with the elbow fully flexed, the position in which pronator quadratus is the primary pronator and pronator teres is relaxed. Sensation is normal.
The OK sign. Ask the patient to pinch pad-to-pad, forming a circle. In AIN palsy the thumb IP and index DIP joints cannot flex, so the rounded "O" becomes a flattened teardrop pinch.
Examination. Isolate each muscle, then screen for the mimics, and always compare with the contralateral side:
- Isolated FPL test: stabilise the thumb proximal phalanx and ask for active IP joint flexion; it is absent in AIN palsy
- Isolated FDP-index test: hold the index PIP joint extended and ask for active DIP flexion; it is absent in AIN palsy
- Pronator quadratus test: resist pronation with the elbow fully flexed, which relaxes pronator teres and isolates PQ; it is weak in AIN palsy
- Tenodesis effect: passive wrist extension should produce passive finger and thumb flexion; an intact tenodesis arc helps exclude tendon rupture (an FPL rupture, the Mannerfelt lesion)
- Sensory screen: confirm normal sensation in the median territory; any numbness points away from isolated AIN palsy toward pronator syndrome or a higher median lesion, and if numbness is present it is not an isolated AIN palsy
Where the AIN sits among the forearm nerve palsies. Each has a motor pattern, a sensory territory, a bedside test and a named sign:
- Motor
- FPL, FDP(I/M), PQ
- Sensory (Skin)
- None
- Test
- OK Sign
- Sign
- Teardrop
- Motor
- All flexors (exc FCU)
- Sensory (Skin)
- Radial 3.5 digits
- Test
- Fist
- Sign
- Hand of Benediction
- Motor
- Thenar (LOAF)
- Sensory (Skin)
- Radial 3.5 digits
- Test
- Opposition
- Sign
- Ape Hand
- Motor
- Intrinsics, FCU
- Sensory (Skin)
- Ulnar 1.5 digits
- Test
- Cross fingers
- Sign
- Claw Hand
Imaging and Electrodiagnostics
Electromyography is the gold standard. It shows active denervation (fibrillations, positive sharp waves) in FPL, FDP to the index and middle fingers, and pronator quadratus. The changes appear 3-4 weeks after onset.
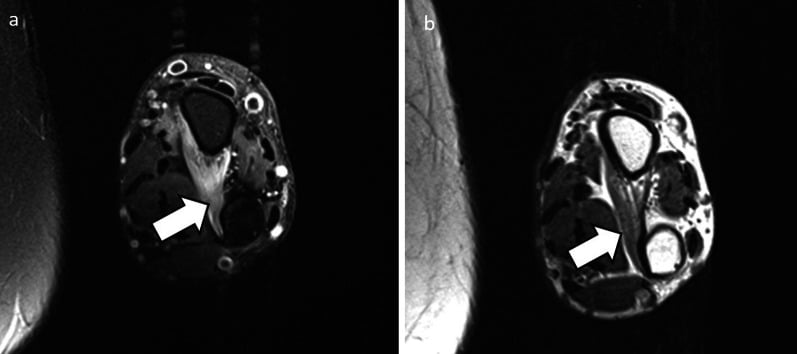
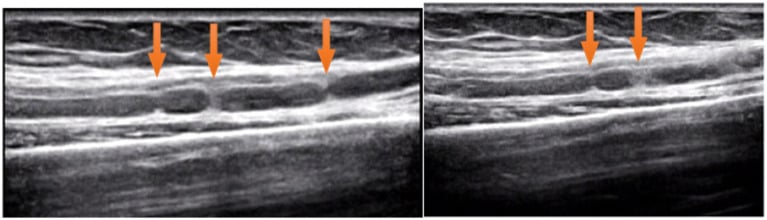
Separating neuritis from a focal lesion. Brachial plexitis (Parsonage-Turner) shows patchy involvement of other nerves, for example the suprascapular or the long thoracic. If the EMG is equivocal, look for denervation oedema on MRI.
Differential Diagnosis
The acute, painless loss of thumb-and-index pinch has a short but high-stakes differential. The two errors that fail vivas are operating on a neuritis and missing a tendon rupture.
- Sensory loss
- None
- Pronator quadratus
- Weak (denervated)
- Key discriminator
- Pure motor loss of FPL + FDP-index, normal sensation
- Sensory loss
- Usually none in AIN form
- Pronator quadratus
- Weak
- Key discriminator
- Severe prodromal shoulder/arm pain then weakness; often multifocal on EMG
- Sensory loss
- Present (palmar median + radial 3.5 digits)
- Pronator quadratus
- Variable
- Key discriminator
- Numbness AND volar forearm aching; positive provocative tests
- Sensory loss
- Present (radial 3.5 digits)
- Pronator quadratus
- Weak
- Key discriminator
- Adds thenar and FCR/PL/FDS weakness plus sensory loss
- Sensory loss
- None
- Pronator quadratus
- Normal
- Key discriminator
- Lost tenodesis arc; normal EMG; mechanical cause
- Sensory loss
- None
- Pronator quadratus
- Weak
- Key discriminator
- Conduction block on EDX; responds to IVIg, not surgery
AIN palsy is often viral or inflammatory, an immune-mediated neuritis (Parsonage-Turner, neuralgic amyotrophy), rather than compressive. The history is a viral illness and severe shoulder or arm pain, followed by weakness and then wasting. Decompression does not help Parsonage-Turner and may make it worse, so always order an EMG to confirm denervation and rule out brachial plexitis.
Surgical Technique
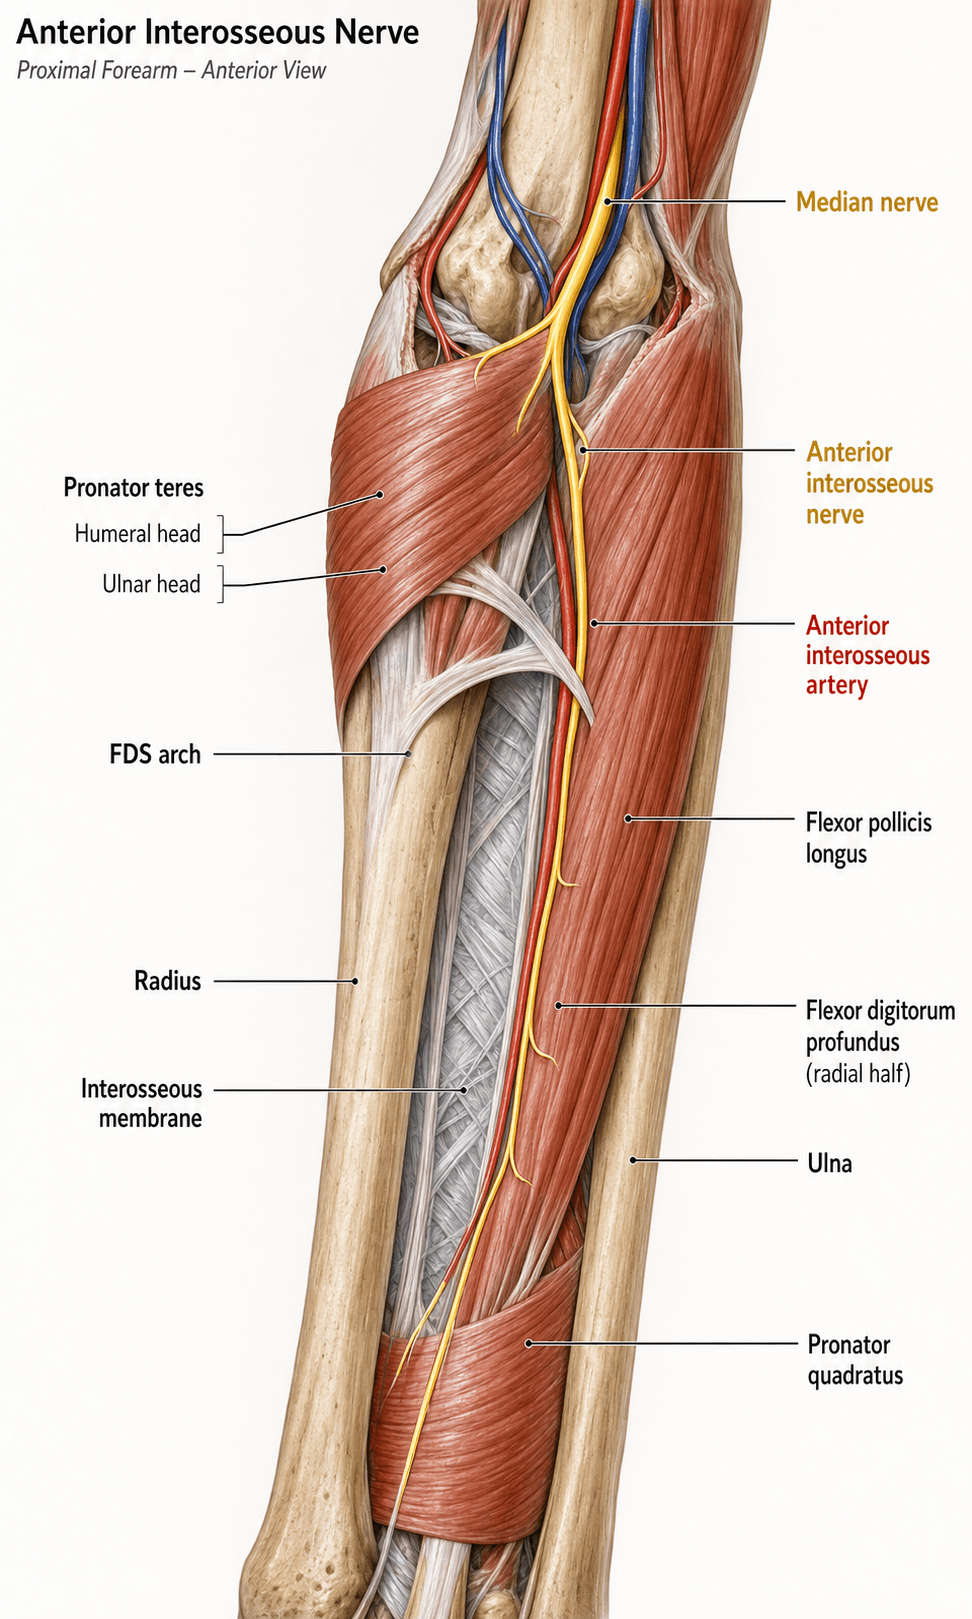
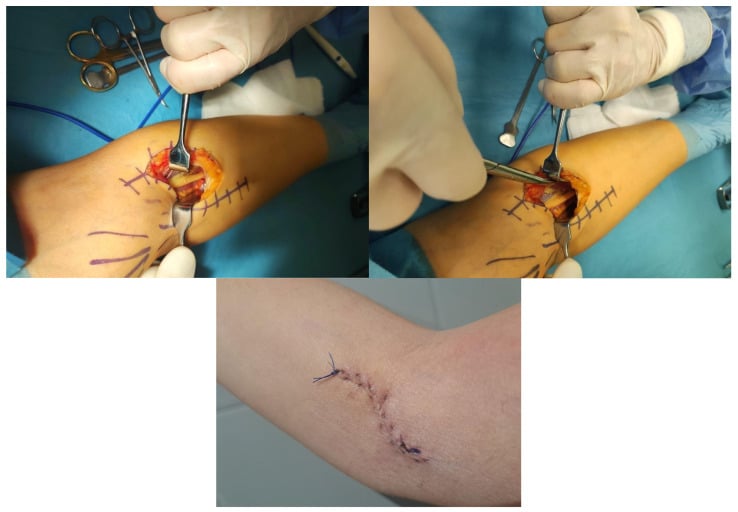
Henry's approach. A curvilinear incision crossing the elbow crease obliquely, lateral to medial. The interval is between pronator teres (median nerve) and brachioradialis (radial nerve). Superficially, protect the lateral cutaneous nerve of the forearm (musculocutaneous nerve), which is often at risk during the incision.
Complications
Of the exploration itself. Iatrogenic injury to the median nerve or the radial artery; haematoma, from the rich vascular supply; hypertrophic scarring at the antecubital fossa, and hypersensitivity in the scar; and a neuroma of the lateral antebrachial cutaneous nerve. CRPS is always a risk.
Of the decision. Failure to improve, when the diagnosis was incorrect, and recurrence after an incomplete release, for example a missed Gantzer's muscle.
Rehabilitation
No splint is usually required unless the hand is weak. Maintain full passive range of motion to prevent contractures.
Strengthening begins once signs of reinnervation appear. Sensory rehabilitation is not needed, because there is no sensory loss.
Prognosis
Neuritis. 80-90% recover within 1 year. Recovery continues for up to 18 months, but the plateau occurs earlier.
Compression. Excellent recovery if decompressed early, provided it was a true compression.
Trauma. A poor outcome if the nerve is transected; it requires grafting.
Clinical Relevance
The standard treatment. A spontaneous palsy, neuritis or viral, without a mass is observed. Observation runs for 3-12 months, and most resolve spontaneously within 6-12 months. Surgical release is avoided in the acute inflammatory phase. NSAIDs cover the pain if it is neuralgic amyotrophy; the therapy programme is set out under Rehabilitation.
Guidelines, Registries & Global Practice
Global Epidemiology
- Isolated AIN palsy is rare, accounting for well under 1% of all upper-limb mononeuropathies in electrodiagnostic referral series.
- The majority of spontaneous (non-traumatic) cases are now regarded as a forme fruste of neuralgic amyotrophy (Parsonage-Turner syndrome) rather than mechanical entrapment.
- Neuralgic amyotrophy itself has a reported incidence of roughly 1 per 1,000 person-years when actively sought, far higher than older estimates of about 2-3 per 100,000 - the AIN/median territory is among the most frequently affected.
- Male predominance and a frequent antecedent trigger (viral illness, vaccination, surgery, strenuous exertion) are described across populations.
Side-by-Side Guidance (no single national framework)
- Position on spontaneous AIN palsy
- Electrodiagnosis to confirm and exclude broader plexopathy; observe spontaneous cases; reserve surgery for a defined mass or documented compression
- Position on spontaneous AIN palsy
- Distinguish neuritis from entrapment before any decompression; expectant management for idiopathic palsy
- Position on spontaneous AIN palsy
- Anatomical decompression only where a structural compressor is demonstrated; growing role for MRI/ultrasound to detect hourglass constrictions in non-recovering cases
- Position on spontaneous AIN palsy
- Oral corticosteroids may shorten the painful phase if started early; nerve imaging and selective interfascicular neurolysis for hourglass constrictions that fail to recover
There is broad international agreement: confirm with electrodiagnosis, observe idiopathic palsy for 12 or more months, and operate only for a structural lesion or a demonstrated fascicular constriction.
Registry & Imaging Notes
- There is no implant registry relevant to AIN palsy (a soft-tissue, non-arthroplasty condition); the evidence base is built on case series and electrodiagnostic/imaging cohorts.
- High-resolution 3T MR neurography and high-frequency ultrasound have shifted practice in well-resourced centres, enabling pre-operative localisation of hourglass constrictions (see Sneag et al.).
High- vs Limited-Resource Practice Variation
- Well-resourced settings: ready access to nerve conduction studies, MR neurography and microsurgical neurolysis; earlier, more selective surgery for imaging-proven constrictions.
- Limited-resource settings: diagnosis is predominantly clinical (the "OK sign"/teardrop pinch and preserved sensation), electrodiagnosis and advanced imaging may be unavailable, and management is necessarily conservative with longer observation; tendon transfers remain the universally available salvage for persistent paralysis.
Controversies & Areas of Uncertainty
Neuritis or entrapment. The dominant modern view (Miller-Breslow, Seror) is that most spontaneous AIN palsies are a neuritis, not mechanical entrapment; a minority remain genuinely compressive. There is no reliable bedside test to separate them at presentation, so electrodiagnosis and time are used as the discriminator.
Does Gantzer's muscle actually compress the AIN? Anatomically the accessory FPL head usually lies posterior to both the median nerve and the AIN (al-Qattan), which argues against it being a frequent true compressor despite its traditional billing as "the most common cause".
Role and timing of surgery. Whether and when to decompress an idiopathic palsy is unsettled. Most authors observe for 12 or more months, because surgery has not shortened recovery in comparison series; others explore earlier when a discrete compressor is suspected.
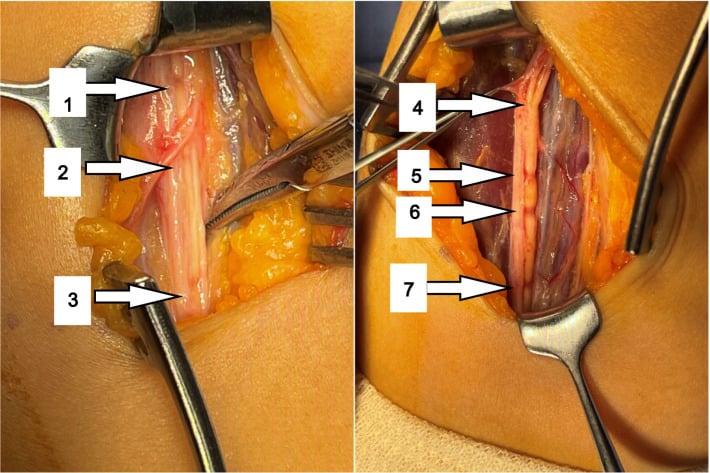
Hourglass constrictions. High-resolution MRI and ultrasound increasingly reveal fascicular hourglass constrictions or torsion in non-recovering "neuritis" (Sneag). Whether these are best treated by interfascicular neurolysis, resection and graft, or continued observation is an active question.
Corticosteroids in neuralgic amyotrophy. Early oral steroids may shorten the painful phase, but high-quality evidence for improved long-term motor recovery is limited.
MCQ Practice Points
Q: Which muscle is the most common cause of mechanical AIN compression? A: Gantzer's Muscle (Accessory head of FPL).
Q: What is the sensory deficit in a pure AIN palsy? A: None (it is a pure motor nerve to muscles). Articular branches only.
Q: A Martin-Gruber anastomosis typically involves fibers moving from where to where? A: Median to Ulnar.
Q: What condition typically mimics AIN palsy with a prodrome of pain? A: Parsonage-Turner Syndrome (Neuralgic Amyotrophy).
Q: When should EMG be performed in suspected AIN palsy? A: Wait 3-4 weeks after symptom onset. Earlier EMG may be falsely negative as denervation changes take time to develop. Pronator Quadratus testing is pathognomonic.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old wakes up with inability to bend the tip of his thumb. No pain. No trauma. Sensation normal.”
“A patient has a complete transection of the Ulnar nerve at the elbow. But he still has strong First Dorsal Interosseous function. Explain.”
“You decompressed an AIN palsy 6 months ago. No recovery. Patient is upset.”
Anatomy
- Origin: Median N (5-8cm distal to lateral epicondyle)
- Muscles: FPL, FDP (Index/Middle), Pronator Quadratus
- No Cutaneous Sensation (pure motor)
- Runs on anterior surface of interosseous membrane
- C8-T1 nerve root origin
Clinical
- Sign: Teardrop pinch (Cannot make OK sign)
- Syndrome: Kiloh-Nevin (AIN palsy)
- Mimic: Parsonage-Turner (Neuralgic Amyotrophy)
- Test: Pronation with elbow flexed (isolates PQ)
- No numbness - distinguishes from Pronator Syndrome
Variants & Compression
- Martin-Gruber Anastomosis (Median to Ulnar crossover)
- Gantzer's Muscle (accessory FPL head) - most common cause
- Pronator Teres deep head compression
- FDS arch (Spinner's bands) compression
- Lacertus fibrosus compression
Management
- Conservative: Observation 6-12 months (most recover)
- Surgical: Reserved for mass lesions or failure after 12 months
- Salvage: Tendon transfers (BR to FPL, FDP side-to-side)
- EMG: Confirm denervation 4 weeks post-onset
- DO NOT operate on Parsonage-Turner
Evidence Base
Nonoperative Treatment of AIN Paralysis (Foundational Natural-History Series)
- 10 patients with spontaneous partial AIN paralysis followed prospectively; all presented with a typical history of pain
- 7 of 10 had signs of involvement of nerves beyond the AIN on examination or EMG, supporting a neuritis rather than focal compression
- 8 patients treated by observation showed recovery by 6 months and full recovery within 1 year
- Surgical decompression did not shorten recovery time compared with observation
Gantzer's Muscle - Anatomical Study of the Accessory Head of FPL
- 25 cadaver limbs dissected; Gantzer's muscle present in 13 of 25 (52%)
- The accessory head was supplied by the anterior interosseous nerve in every specimen in which it was present
- It arose from the medial humeral epicondyle in 85%, with a dual epicondyle-plus-coronoid origin in the remainder
- It always lay POSTERIOR to BOTH the median nerve and the anterior interosseous nerve
Proximal Martin-Gruber Anastomosis at the Elbow (Largest EDX Series)
- Prospective 4-year electrodiagnostic detection of a proximal (elbow-level) Martin-Gruber anastomosis - the largest such series reported
- 16 cases identified, all with crossover fibres reaching an ulnar-innervated branch
- Detection via the first dorsal interosseous was more sensitive than via abductor digiti minimi
- A proximal MGA can mimic ulnar neuropathy at the elbow and create a discrepancy between clinical and electrodiagnostic findings
AAEM Case Report #25 - Electrodiagnosis of AIN Syndrome
- Illustrative case (57-year-old woman) with weakness of FPL and FDP to the index finger and no sensory deficit
- Median motor and sensory conduction studies were normal; needle EMG abnormalities were confined to FPL, FDP-index and pronator quadratus
- Reviews the literature distinguishing idiopathic AIN syndrome (part of neuralgic amyotrophy) from anatomic causes such as a fibrous band or anomalous muscle
- Establishes the role of electrodiagnosis - especially pronator quadratus sampling - in localising the lesion to the AIN
AIN Lesions - Clinical and Electrophysiological Features
- Consecutive series of 13 patients with AIN lesions referred for electrodiagnosis
- Only 3 had a correct initial clinical diagnosis and 3 were wrongly labelled tendon ruptures - highlighting frequent misdiagnosis
- 5 lesions were of mechanical origin and 7 were attributed to neuritis; all showed EDX abnormalities, most commonly in the pronator quadratus
- Late spontaneous recovery was common and only one patient underwent surgical exploration
MRI Bullseye Sign for Hourglass Constrictions in Parsonage-Turner Syndrome
- 6 patients with Parsonage-Turner syndrome and absent or minimal recovery underwent high-resolution MRI followed by surgical exploration
- Involved nerves included the anterior interosseous and pronator teres fascicles of the median nerve, plus suprascapular, axillary and radial nerves
- 23 constriction sites across 10 nerves were identified on MRI; a peripheral-bright, central-dark 'bullseye sign' lay immediately proximal to 21 of 23 sites
- All MRI-identified constrictions were confirmed at operation