Intercalated Segment Concept | SL vs LT Injury | Static vs Dynamic | SLAC Progression
- Intercalated segment = proximal carpal row (no tendon attachments), controlled by ligaments
- DISI = SL tear, lunate follows triquetrum dorsally (extended), SL angle over 70°
- VISI = LT tear, lunate follows scaphoid palmarly (flexed), SL angle under 30°
- Watson scaphoid shift test is suggestive, NOT pathognomonic - generalised laxity gives false positives, so always compare the contralateral wrist and weight a PAINFUL clunk over a clunk alone
- Static vs dynamic - static shows on plain films, dynamic needs stress views
- “True lateral X-ray essential - measure SL angle from scaphoid axis to lunate perpendicular
- “SL gap over 3mm on PA = Terry Thomas sign (compare to other side)
- “Capitolunate angle over 15 degrees confirms carpal malalignment
- “DISI progresses to SLAC wrist, VISI to ulnocarpal/midcarpal arthritis
Overview
Carpal instability is a spectrum of wrist pathology in which normal carpal kinematics are disrupted by ligamentous injury. DISI and VISI are the two named patterns of that disruption, and both are read off the position of a single bone on a true lateral radiograph: the lunate.
The intercalated segment. The proximal row — scaphoid, lunate and triquetrum — is called the intercalated segment because no tendon inserts on it. Its movement is passive, set by the bones and ligaments around it, and it lies between the radius and the distal row as a link transmitting force across the wrist. The distal row (trapezium, trapezoid, capitate, hamate) is rigidly interconnected, has minimal motion between its members, and keeps a fixed relationship with the metacarpals.
The balance the ligaments keep. The scaphoid naturally flexes and the triquetrum naturally extends: the row is pulled into flexion under axial load by scaphoid geometry and into extension under compression at the capitate articulation. The intrinsic intercarpal ligaments, scapholunate and lunotriquetral, hold those opposing forces against each other, and while they are intact the row moves as a unit. The lunate has no tendon of its own and follows whichever bone it remains attached to — which is the whole of DISI and VISI.
Why DISI happens. Tear the scapholunate ligament and the scaphoid is no longer tethered to the lunate, so it flexes palmarly under load as its shape inclines it to. The lunate, now attached only to the triquetrum, is carried with the triquetrum into extension and tilts dorsally — dorsal intercalated segment instability.
Why VISI happens. Tear the lunotriquetral ligament and the triquetrum no longer tethers the lunate, which loses the stabilising effect of the helicoid triquetrum. Still attached to the scaphoid, the lunate follows it into flexion and tilts palmarly — volar intercalated segment instability.
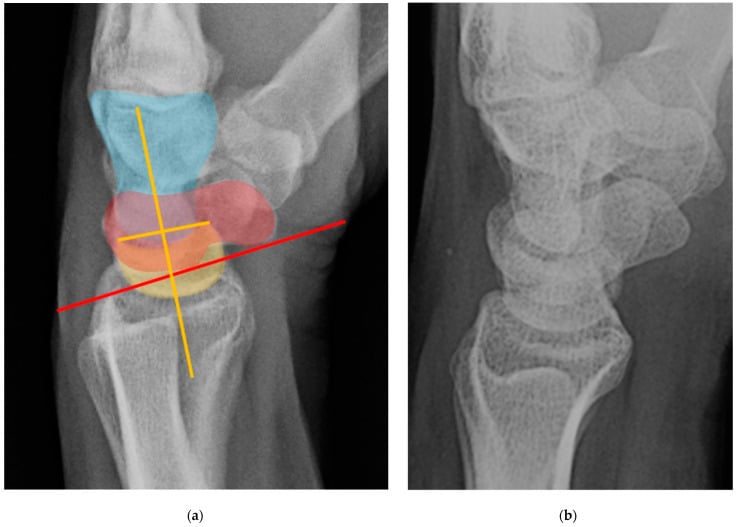
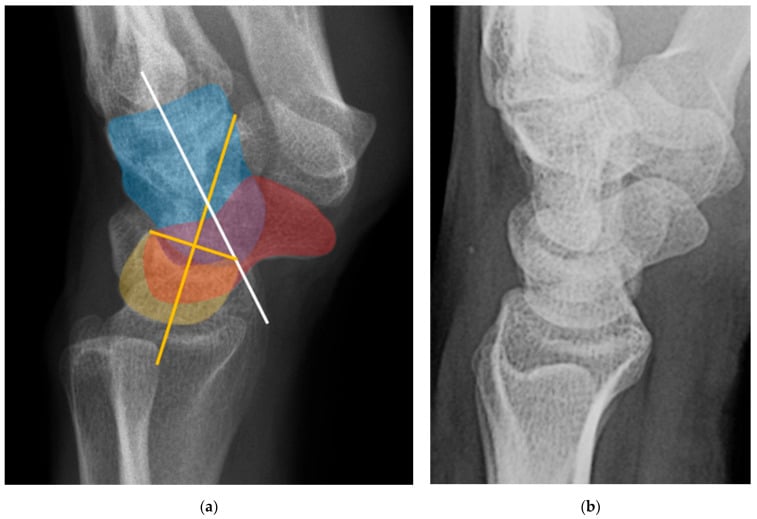
- DISI
- Over 70°
- VISI
- Under 30°
- Normal
- 30-60° (avg 47°)
- DISI
- Extended (dorsal tilt)
- VISI
- Flexed (volar tilt)
- Normal
- Neutral
- DISI
- Scapholunate
- VISI
- Lunotriquetral
- Normal
- Intact
- DISI
- Watson scaphoid shift
- VISI
- Reagan LT ballottement
- Normal
- Negative
- DISI
- SLAC wrist
- VISI
- Ulnocarpal/midcarpal
- Normal
- None
- DISI
- Common (90%)
- VISI
- Rare (10%)
- Normal
- N/A
Pathophysiology and Mechanisms
The two intrinsic ligaments do not fail in the same way, and the difference decides which fibres a repair must restore.
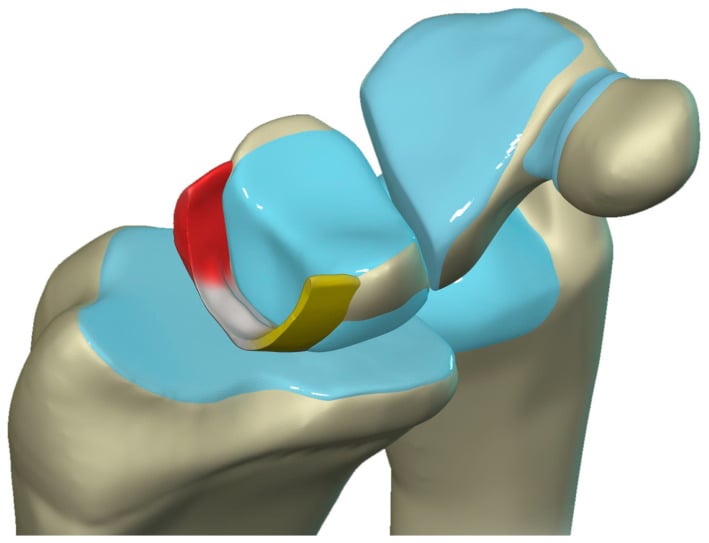
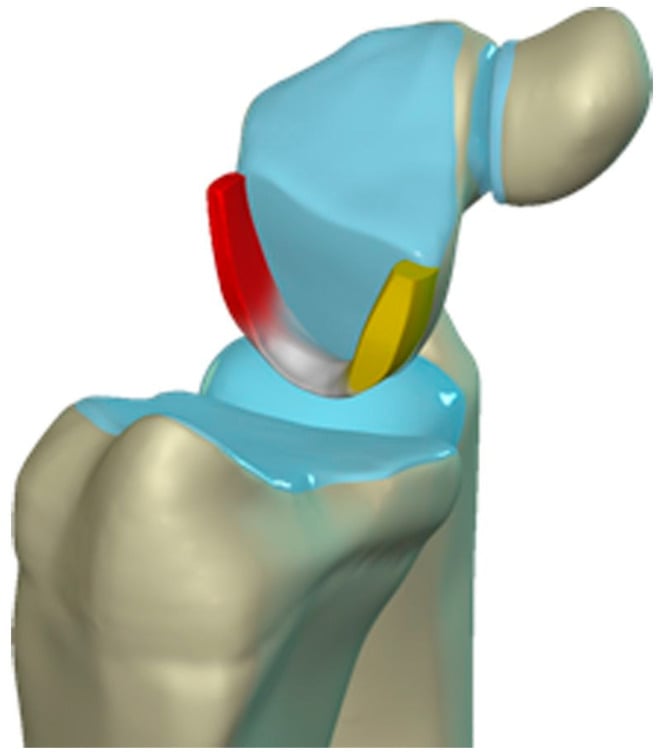
The scapholunate ligament. Three portions of unequal strength. The dorsal portion is the thickest and strongest at 2-3mm and is the primary restraint to scaphoid flexion and pronation; the palmar portion is of intermediate strength; the proximal portion is membranous, the weakest, and has no structural role. Rupture runs palmar, then proximal, then dorsal, so the dorsal fibres are the last to go and the ones the surgeon comes back for.
The lunotriquetral ligament. The mirror image. Its palmar portion is the strongest component and the primary restraint to triquetral extension, the dorsal portion is intermediate and the proximal portion membranous. It is injured less often than the scapholunate.
The extrinsic ligaments. The palmar extrinsics matter more than the dorsal:
- Radioscaphocapitate (RSC) - the primary palmar stabiliser
- Long radiolunate (LRL) - lunate stabilisation
- Short radiolunate (SRL) - palmar constraint
- Radioscapholunate (RSL) - a neurovascular conduit with minimal structural role
- Dorsal radiocarpal (DRC) - dorsal constraint
- Dorsal intercarpal (DIC) - the scaphoid-triquetrum link
Dart thrower's motion. From radial deviation with extension to ulnar deviation with flexion. It is predominantly midcarpal motion and puts least stress on the intercarpal ligaments, which is why it is preserved after some injuries.
Blood supply. The scapholunate ligament is fed by the dorsal branch of the radial artery and the anterior interosseous artery, with limited vascularity in its central portion. The lunotriquetral ligament takes branches of the ulnar artery and the anterior interosseous artery and is slightly better vascularised than the scapholunate.
Innervation. The posterior interosseous nerve supplies the dorsal ligaments, the anterior interosseous nerve the palmar ones. Their proprioceptive function matters to carpal kinematics, which is the case against denervation: it may address the pain, but it sacrifices the proprioception.
Classification Systems
Mayfield described progressive perilunar instability: sequential ligament failure around the lunate in a hyperextension injury. Each stage includes all the previous ones, so by Stage IV the ligamentous ring around the lunate is completely disrupted.
Stage I. The scapholunate ligament ruptures and the scaphoid separates from the lunate, giving SL dissociation.
Stage II. The capitolunate joint fails and the capitate dislocates dorsally around the lunate - the perilunate dislocation.
Stage III. The lunotriquetral ligament ruptures, isolating the lunate from the carpal bones on both sides while it stays in the lunate fossa.
Stage IV. The dorsal radiocarpal ligament ruptures and the lunate dislocates into the carpal tunnel.
SCLLMayfield Stages
Hook:SCLL like SKULL - injury progresses around the lunate like drawing a skull, ending with lunate dislocation
Clinical Assessment
History. A fall on the outstretched hand is the usual mechanism, and the direction of the load points to the ligament: hyperextension with ulnar deviation injures the scapholunate, extension with radial deviation the lunotriquetral. High-energy trauma produces the perilunate dislocations.
Symptoms. Wrist pain, dorsal for a scapholunate injury and ulnar for a lunotriquetral one, with weakness of grip, clunking or clicking on movement, and pain on weight-bearing through the hand. Swelling is often minimal in chronic cases, so a normal-looking wrist proves nothing.
Red flags. Three findings change the urgency:
- Acute severe deformity, meaning a perilunate dislocation
- Median nerve symptoms, meaning acute carpal tunnel syndrome from the dislocation
- Associated fractures of the scaphoid or radial styloid
Inspection and palpation. Look for swelling (dorsal with scapholunate injury, ulnar with lunotriquetral), prominence of the ulnar head in LT injury, and loss of carpal height in chronic instability. Then localise the tenderness: the SL interval lies 1cm distal to Lister's tubercle, the LT interval just ulnar to the lunate, and scaphoid tubercle tenderness accompanies SL injury.
The Watson scaphoid shift test is the examination for scapholunate instability:
- Patient's forearm in neutral rotation
- Examiner's thumb on the scaphoid tubercle, fingers dorsally
- Apply pressure while moving the wrist from ulnar to radial deviation
- Positive: a painful clunk as the scaphoid subluxes dorsally
- Compare with the contralateral side - it may be positive bilaterally in lax individuals
The test is suggestive, not pathognomonic — and the distinction protects patients from unnecessary surgery. A sign is pathognomonic only if its presence proves the disease, and a positive scaphoid shift does not: dorsal subluxation can be produced by generalised ligamentous laxity in a wrist whose scapholunate ligament is intact. That is precisely why every description of the test insists on the contralateral comparison. A documented case makes the point starkly (DOI) — a woman six weeks postpartum had a positive Watson test with a frankly subluxable scaphoid and radiographic scapholunate subluxation, all from pregnancy and lactation-related laxity; it resolved completely once lactation ceased, with no recurrence over five years.
The direction of the error is over-diagnosis, and the real risk is an operation on a lax but structurally intact wrist. Examine both wrists, treat a painful clunk as far more meaningful than a painless one, ask about generalised hypermobility and, in a woman of childbearing age, about pregnancy or lactation, and confirm a suspected tear with MR arthrography or arthroscopy before committing to surgery.
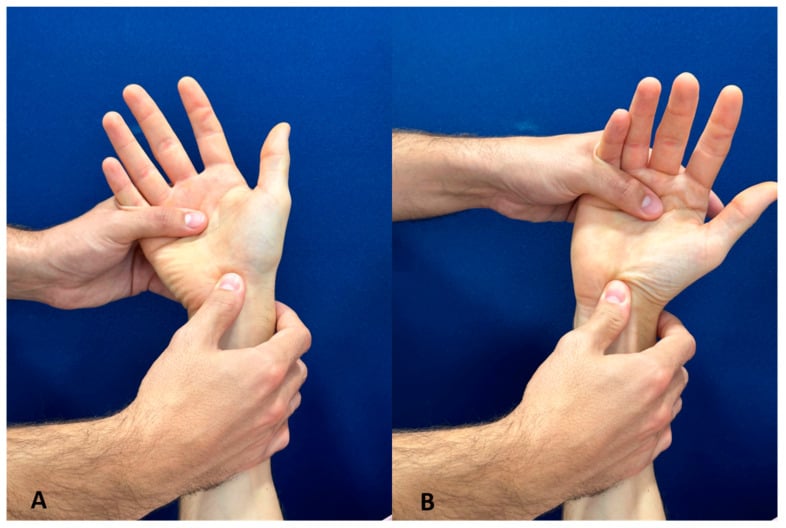
Two further scapholunate tests. The scaphoid compression test loads the thumb metacarpal axially and is positive when it reproduces pain at the SL interval, testing the ligament under compression. The finger extension test resists active finger extension and is positive when dorsal wrist pain increases, which indicates scapholunate pathology.
Lunotriquetral tests. All three are compared with the other wrist:
- LT ballottement (Reagan's test) - stabilise the lunate with one hand and translate the triquetrum dorsally and palmarly; pain, crepitus or increased motion is positive
- LT compression test - ulnar-deviate the wrist and load axially through the ring and small finger metacarpals; pain at the LT interval is positive
- Shuck test - the pisiform is used as a lever to load the LT joint; pain or clicking is positive
The four instability patterns are sorted by which interface has failed, and the label matters because two of them are not treated with the SL/LT algorithm at all.
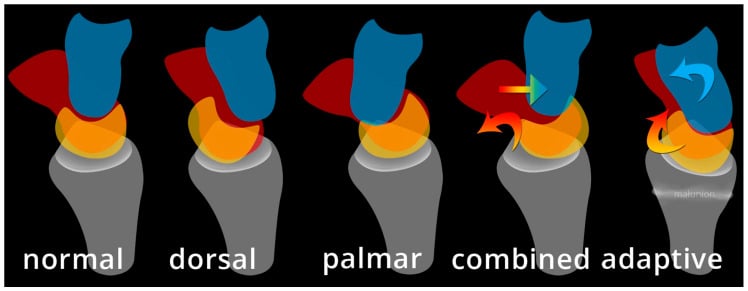
Carpal instability dissociative (CID) is disruption within a carpal row and the commonest pattern: SL dissociation giving DISI, LT dissociation giving VISI. Carpal instability combined (CIC) is both dissociative and non-dissociative failure together, which is what a perilunate injury after severe trauma amounts to.
Carpal instability non-dissociative (CIND) is disruption between the rows rather than within one, radiocarpal or midcarpal, and usually involves the extrinsic ligaments. Palmar midcarpal instability is the commonest type: the proximal row sits abnormally flexed, VISI-like, at rest and then snaps suddenly into extension as the wrist moves into ulnar deviation, the painful or painless catch-up clunk. Dorsal and combined types also exist. The mechanism is laxity or incompetence of the extrinsic ulnar arcuate and triquetrohamate-capitate ligaments, which allows a delayed, jerky proximal-row transition rather than a smooth one; it is strongly associated with generalised ligamentous laxity and is often atraumatic and bilateral. Because it is non-dissociative the static films and the SL and LT intervals are normal, so the diagnosis is made on dynamic fluoroscopy or video showing the abrupt midcarpal shift, not on a single radiograph. There is no ligament tear to repair, so proprioceptive and neuromuscular retraining with splinting is first-line and often sufficient, and refractory cases are treated by soft-tissue reconstruction or a limited midcarpal fusion.
A painful catch-up clunk on ulnar deviation with normal SL and LT intervals is midcarpal, non-dissociative instability. Diagnose it dynamically, treat it first with proprioceptive rehabilitation, and do not apply the SL/LT repair algorithm to it.
Carpal instability adaptive (CIA) is a carpus that has adapted to a malunited distal radius, most often the dorsally angulated Colles-type malunion, and it is the pattern most often got the wrong way round. A dorsal malunion with loss of volar tilt produces an adaptive DISI: the lunate follows the dorsally tilted lunate fossa into extension. Taleisnik and Watson put it exactly - loss of the normal palmar tilt "prepositions the carpus in a dorsal collapse alignment" (PMID 6725893) - and Park's cadaver dorsal closing-wedge model produced "a spectrum from dorsal subluxation of the entire carpus to adaptive dorsal carpal instability (DISI deformity)" (PMID 11901381). A volar, Smith-type malunion produces the mirror image, an adaptive VISI, and is much less common because volar malunion itself is much less common.
The discriminator, and the fix. The SL and LT intervals are normal, the malalignment is passively correctable, and there is a distal radius malunion with abnormal radial tilt and length on imaging: this is extrinsic, not a ligament tear. Treat the radius, not the carpus. A corrective distal radius osteotomy that restores radial inclination, volar tilt and length corrects the adaptive carpal alignment with it, and operating on the carpal ligaments here is the error.
Dorsal malunion gives DISI. Volar malunion gives VISI. The deformity follows the articular surface: tilt the lunate fossa dorsally and the lunate extends with it.
The reason the opposite is so often written is a real phenomenon reported at a different joint. In severe dorsal malunion the distal row must flex to keep the hand aligned, so the midcarpal joint can adopt a flexed, VISI-like posture even while the radiolunate relationship is frankly DISI - this is Taleisnik and Watson's midcarpal instability, and it is why some texts speak of a "compensatory VISI" after dorsal malunion. Always say which joint you are measuring. The radiocarpal answer, and the one an examiner wants, is DISI.
Doarn's series quantifies both patterns: of 27 dorsally angulated malunions, 16 adapted at the midcarpal joint and 11 at the radiocarpal joint - and the radiocarpal group corrected less completely after osteotomy (radiolunate, radioscaphoid and capitolunate angles all failed to normalise) and had worse range of motion. Severity and delay predicted failure to correct, especially beyond 40 weeks (PMID 38106951), which is the argument for early osteotomy.
- Key distinguishing features
- Dorsoradial pain, weak grip, painful clunk on radial deviation
- Discriminating test / investigation
- SL angle greater than 70 degrees on lateral; Terry Thomas sign; positive Watson shift
- Key distinguishing features
- Ulnar-sided pain, clicking on ulnar deviation
- Discriminating test / investigation
- SL angle less than 30 degrees; positive Reagan ballottement; MR arthrogram
- Key distinguishing features
- Painless or painful catch-up clunk with ulnar deviation, ligamentous laxity
- Discriminating test / investigation
- Normal SL/LT intervals; dynamic fluoroscopy shows sudden midcarpal shift
- Key distinguishing features
- Ulnar pain, painful forearm rotation, click on pronosupination
- Discriminating test / investigation
- Positive fovea sign and TFCC stress test; MR arthrogram; DRUJ ballottement
- Key distinguishing features
- Acute radial pain, anatomical snuffbox tenderness after FOOSH
- Discriminating test / investigation
- Repeat radiographs/CT/MRI; intact SL interval distinguishes from SL injury
- Key distinguishing features
- Insidious central dorsal wrist pain, stiffness, no clear trauma
- Discriminating test / investigation
- Lunate sclerosis/collapse on radiograph; MRI marrow change; normal SL angle early
Investigations
Radiographs. A true lateral is essential, because the carpal angles are measured on it and it is the film the DISI/VISI diagnosis turns on. The set is four:
- PA - carpal spacing and the arcs of Gilula
- True lateral - the carpal angles
- Scaphoid view - scaphoid pathology
- The contralateral wrist - essential in borderline cases
The scapholunate angle is drawn between the long axis of the scaphoid and a line perpendicular to the distal articular surface of the lunate. Normal is 30-60 degrees, averaging 47 degrees; over 70 degrees is DISI and under 30 degrees is VISI.
The capitolunate angle runs from the long axis of the capitate to the perpendicular to the lunate. Normal is under 15 degrees, and more than that confirms carpal malalignment. The radiolunate angle, radial axis to lunate, is normally neutral (0 degrees plus or minus 10) and is abnormal in both patterns.
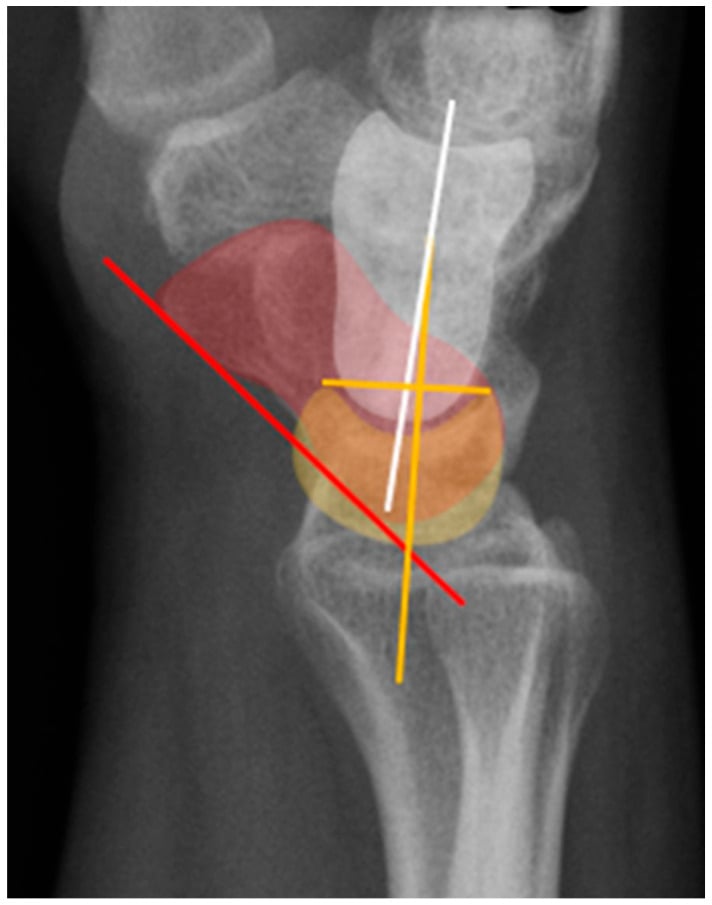
Three signs on the PA film. All of them are compared with the other wrist before they are believed:
- Terry Thomas sign - an SL interval over 3mm suggests SL injury (normal is under 3mm); over 5mm means a complete tear
- Gilula's arcs - arc I along the proximal surfaces of the proximal row, arc II along their distal surfaces, arc III along the proximal surfaces of capitate and hamate; disruption of any arc indicates intercarpal pathology
- Scaphoid ring sign - the cortical ring of a flexed scaphoid, that is rotatory subluxation, seen in SL dissociation and DISI
Stress radiographs are how a dynamic instability is caught. A clenched-fist AP view loads the scapholunate interval and may reveal widening that the resting film does not show; maximum radial and ulnar deviation views assess scaphoid motion, and a dynamic DISI may appear only in radial deviation. Fluoroscopy adds real-time assessment of carpal motion, the dart thrower's arc, and provocative manoeuvres under imaging.
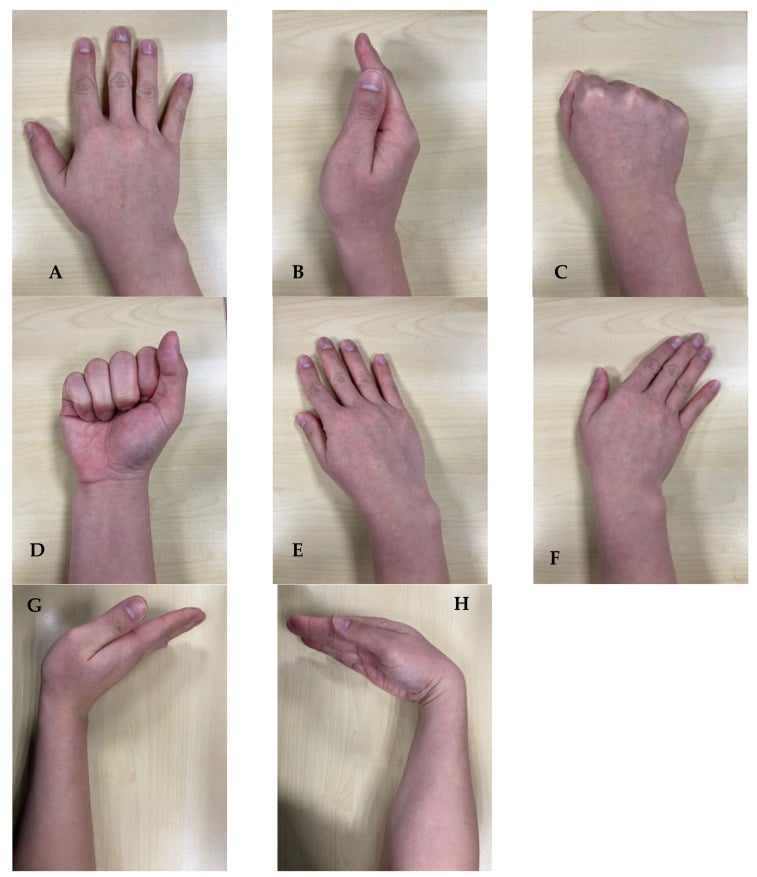
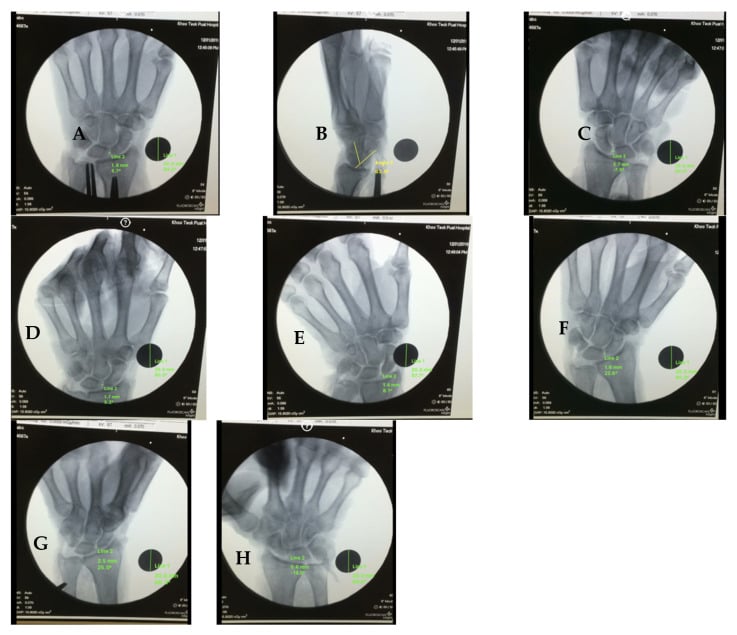
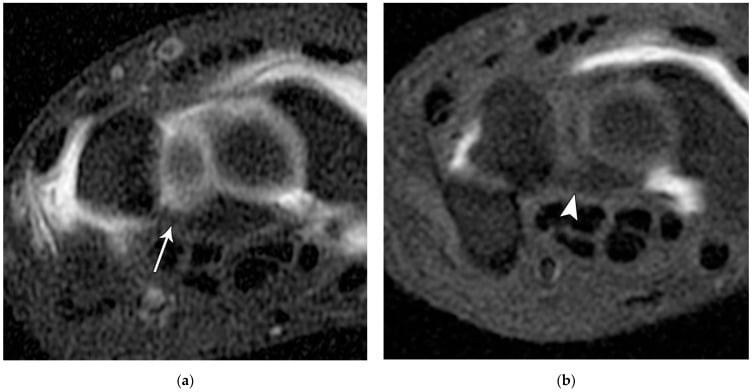
MRI shows the soft tissues: the integrity of the scapholunate and lunotriquetral ligaments, associated TFCC pathology, and the pattern of bone marrow oedema.
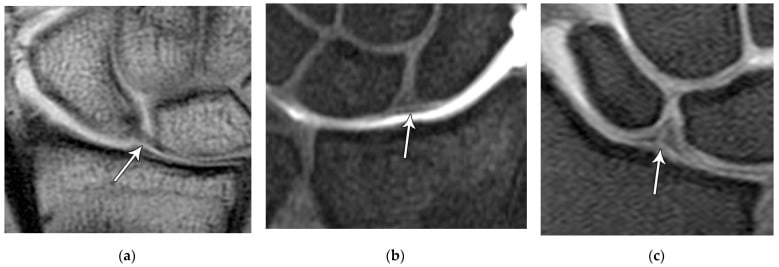
MR arthrography is the most accurate imaging test for a ligament tear, with about 90% sensitivity and specificity for scapholunate tears, and the direction of contrast leak names the injury: radiocarpal into midcarpal is an SL tear, midcarpal into radiocarpal an LT tear.
CT gives bone detail, identifies fractures and provides three-dimensional reconstructions for surgical planning.
Arthroscopy is the diagnostic reference standard. It allows dynamic assessment under direct vision, grades the ligament tear by the Geissler classification, and can treat what it finds.
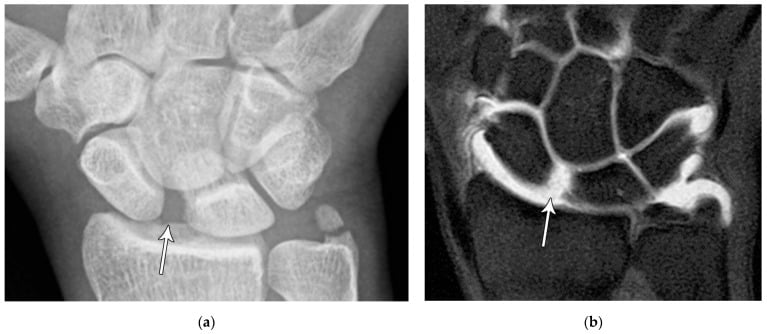
The Geissler grades are read with a probe from the midcarpal joint, and the step from grade II to grade III is whether the probe passes between the bones:
- Arthroscopic findings
- Attenuation or haemorrhage of the interosseous ligament; no instability on probing
- Arthroscopic findings
- Attenuation with incongruity and a visible step-off; the probe cannot be passed between the bones
- Arthroscopic findings
- Incongruity and step-off with the probe passing between the bones from the midcarpal side; volar ligament intact
- Arthroscopic findings
- Complete ligament disruption with gross instability; a 2.7mm arthroscope passes through the gap
Management
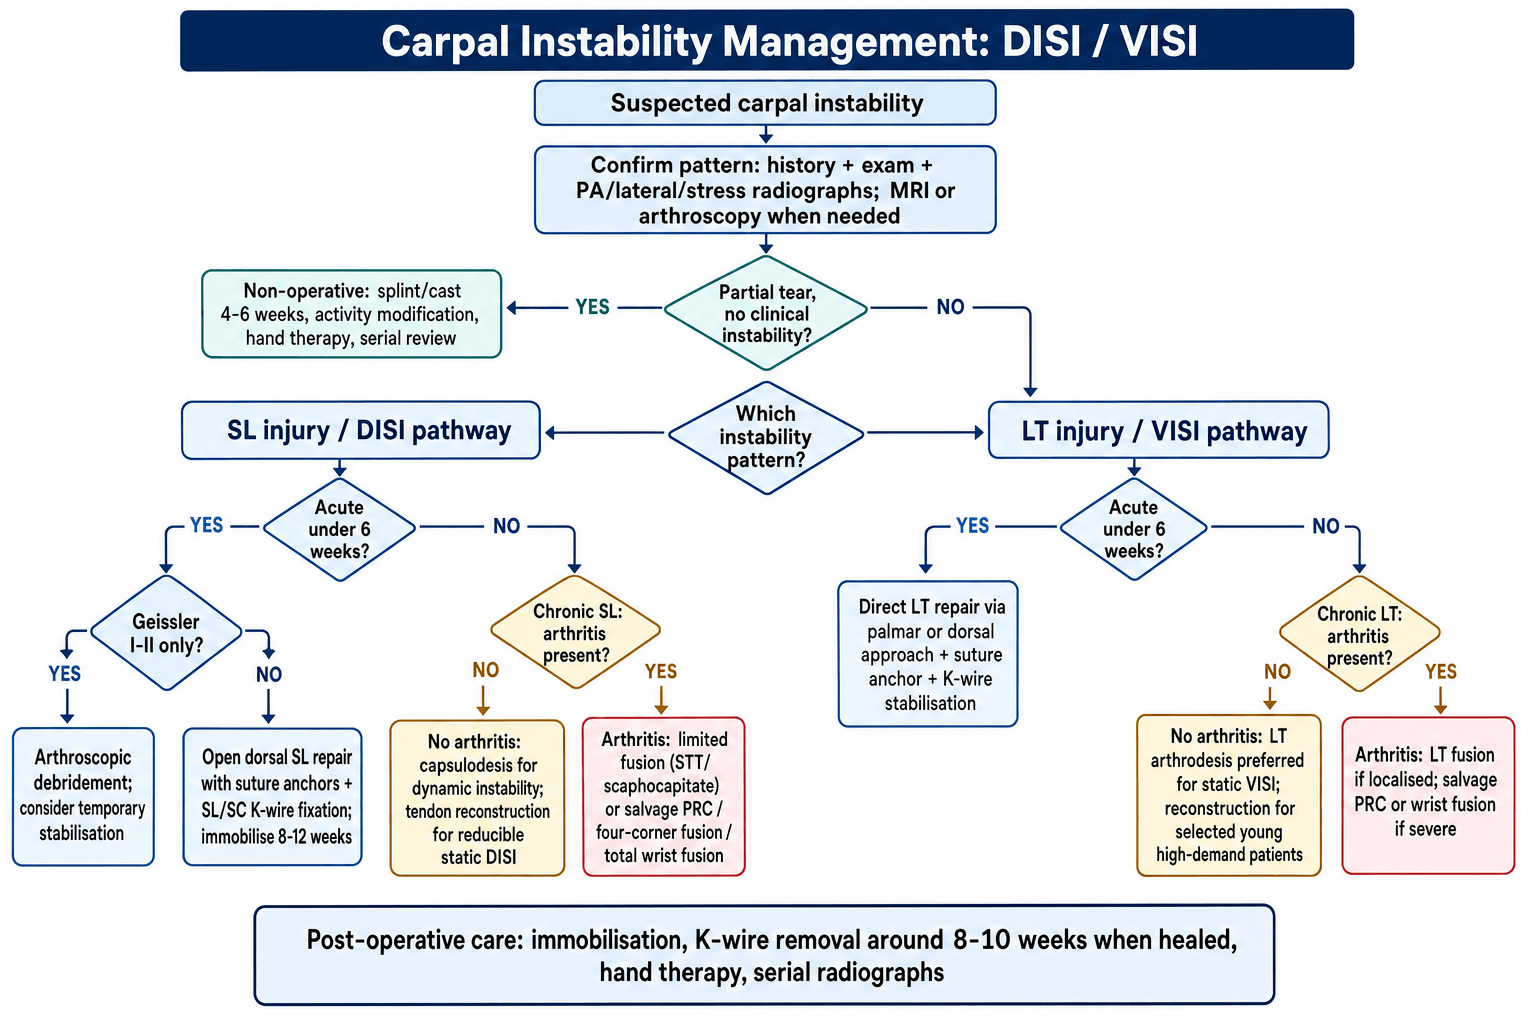
Who. Pre-dynamic instability, meaning a partial ligament tear with no instability on examination; the patient whose comorbidities preclude surgery; and temporary stabilisation before definitive surgery.
What. Immobilisation in slight flexion and ulnar deviation for 4-6 weeks in a cast or splint, physiotherapy for proprioception and grip strengthening, and activity modification to avoid the provocative movements. Serial examination monitors for progression.
Surgical Technique
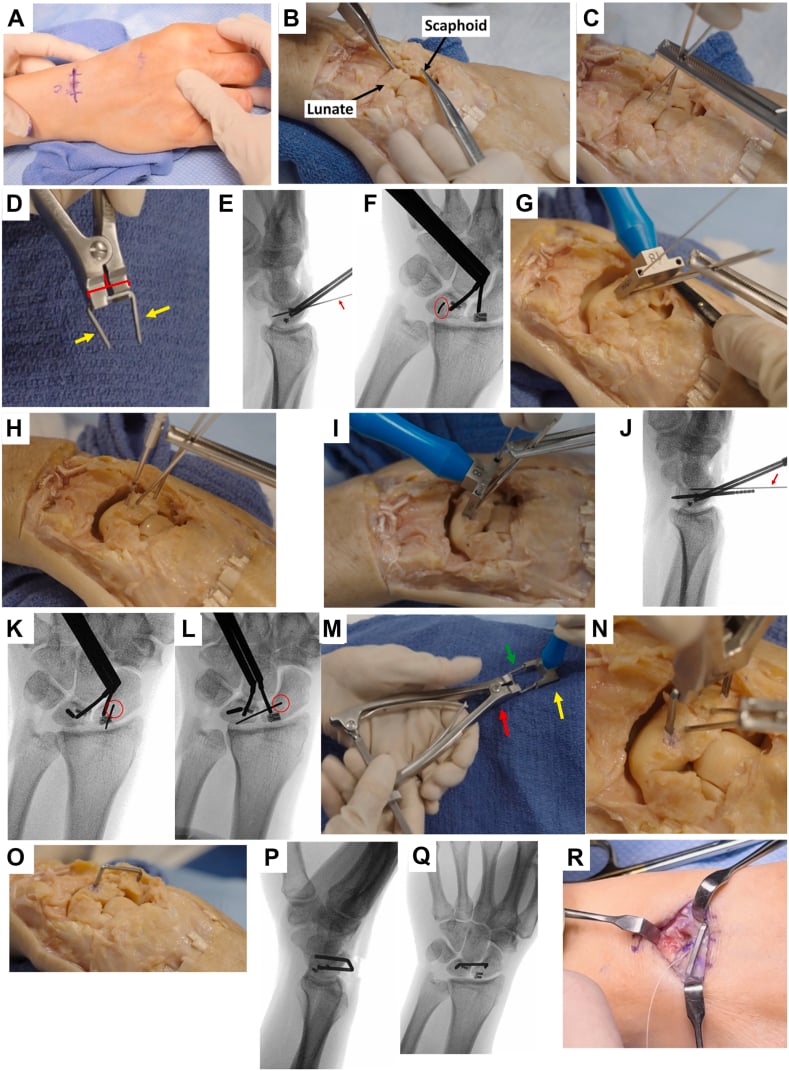
Setup and approach. Supine with an arm table and an upper-arm tourniquet. A dorsal longitudinal incision 4-5cm long centred over Lister's tubercle, the interval developed between the third and fourth extensor compartments, the extensor tendons protected, and a dorsal capsulotomy made - ligament-sparing or traditional.
Direct repair. Identify the torn ligament remnants and debride non-viable tissue, place suture anchors in the scaphoid and lunate, and repair the dorsal scapholunate ligament with non-absorbable sutures. The repair may be augmented with a dorsal capsulodesis.
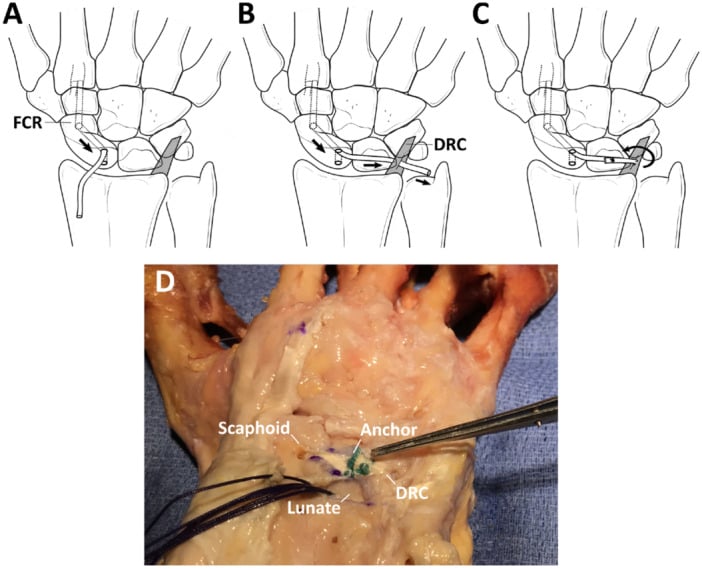
Reconstruction (modified Brunelli). Harvest a strip of FCR tendon 10cm long and half the tendon's width. Drill a 3.2mm tunnel through the scaphoid from the distal pole to the SL interval, pass the graft through it, and anchor it to the lunate with a suture anchor or bone tunnel, tensioning with the wrist in neutral or slight extension.
K-wire fixation. Two 1.1-1.4mm wires across the SL joint and one or two across the scaphocapitate joint, with the reduction checked fluoroscopically.
Complications
The untreated DISI wrist develops progressive radioscaphoid arthritis in the SLAC pattern, stage I to II to III, which is similar to the SNAC wrist progression; 30-50% develop arthritis within 10 years. An untreated VISI progresses less predictably and generally more slowly: ulnocarpal impaction may develop and midcarpal arthritis is possible.
Early complications of surgery. Superficial infection runs at 2-5% and deep infection at under 1%, treated with antibiotics and debridement if needed. Nerve injury - the superficial radial nerve or the DBRCU on the dorsal approach, or the posterior interosseous nerve - is usually a neuropraxia and resolves. Hardware problems include K-wire migration or breakage and screw prominence, and removal is often required.
Late complications. Persistent instability from incomplete ligament healing or a stretched repair may need revision or salvage. Stiffness is common after prolonged immobilisation and needs intensive physiotherapy, occasionally tenolysis or capsular release. A recurrent DISI or VISI, from progressive stretching of the reconstruction, has limited revision options and may progress to salvage. Secondary arthritis follows altered joint loading and progressive cartilage degeneration, and its ultimate outcome resembles untreated instability, with salvage fusion sometimes required.
Procedure-specific complications. Limited fusions (STT, scaphocapitate) carry 5-15% non-union along with hardware prominence, adjacent joint arthritis and residual instability. Proximal row carpectomy may develop radiocapitate arthritis with progressive pain and come to total wrist fusion. Total wrist fusion costs all wrist motion and risks hardware failure, adjacent joint stress and a non-union rate of under 5%.
The failed reconstruction. Work out what was done, when, and with what result, then examine the wrist, obtain a CT to assess any fusion and an MRI for the soft tissues, and consider diagnostic arthroscopy. Early failure may be re-repaired or reconstructed; otherwise the options are conversion to a limited fusion or a salvage procedure. Counsel honestly: each operation reduces the options that remain, wrist fusion is the end of the line, and realistic expectations are part of the consent.
Postoperative Care
Immobilisation. A long-arm cast or splint for the first 2-4 weeks to control forearm rotation, then a short-arm cast or splint for the remaining 4-6 weeks, with the wrist in slight extension and ulnar deviation.
Monitoring. Wound check at 10-14 days and suture or staple removal at 2 weeks, watching for infection and neurovascular compromise. Radiographs at 2 and 6 weeks assess the hardware and the reduction.
Early exercises. Active finger range of motion from day one prevents stiffness, shoulder and elbow motion is maintained, and oedema is controlled with elevation and compression.
Outcomes and Prognosis
Scapholunate instability. Direct repair of an acute injury gives 80-90% good or excellent results when performed within 3 weeks,, and results deteriorate significantly after 6 weeks. Capsulodesis gives 70% satisfaction at 5 years but 30% recurrent DISI, and suits dynamic instability as a bridge procedure. Tendon reconstruction with a modified Brunelli gives 78% good or excellent results at 3 years, declining to 56% at 10 years as the reconstruction progressively stretches. Limited fusions (STT, scaphocapitate) give 75-85% pain relief with about 50% of motion preserved.
Lunotriquetral instability. Acute direct repair gives 80% good results and does better than repair of a chronic tear. LT arthrodesis is the most predictable option for chronic LT instability.
Salvage. Proximal row carpectomy gives 80% good or excellent results at 5-10 years and preserves a functional range of motion, though it may deteriorate over time with radiocapitate arthritis. Four-corner fusion performs similarly and may be preferred for heavy manual labourers. Total wrist fusion gives reliable pain relief at the cost of all wrist motion, and is the last resort.
What predicts the outcome. Favourable: an acute injury under 6 weeks, dynamic rather than static instability, young age, no arthritis and a compliant patient. Unfavourable: a chronic injury, static instability, established arthritis, heavy manual occupation and bilateral disease.
Guidelines, Registries & Global Practice
Global Epidemiology
Scapholunate (SL) interosseous ligament injury is the commonest form of carpal instability and is frequently occult at first presentation. Arthroscopic studies of displaced intra-articular distal radius fractures found intracarpal soft-tissue injury in 68% of wrists, with SL tears in around one-third (Geissler 1996, PMID 8613442). High-energy AO type B (shearing) distal radius fractures carry an especially high SL injury burden - 14 of 15 wrists in one series (Yoshida 2015, PMID 26388007). DISI substantially outnumbers VISI in clinical practice, and the untreated SL-dissociation natural history is a predictable SLAC arthritis pattern present in roughly 57% of degenerative wrists reviewed radiographically (Watson & Ballet 1984, PMID 6725894).
Guideline & Society Positions (Side-by-Side)
There is no single high-level clinical practice guideline dedicated to DISI/VISI; recommendations are derived from hand-surgery society consensus and systematic reviews. Evidence underpinning operative choices is uniformly low (Level III-IV).
- Position
- Hand-surgeon-led care; arthroscopy is the diagnostic reference standard; early repair for acute reparable SL tears
- Evidence level
- Consensus / Level IV
- Position
- Staged management by Garcia-Elias algorithm; reconstruction for reducible static DISI without arthritis
- Evidence level
- Consensus / Level IV
- Position
- Acute repair preferred where feasible; 3-ligament tenodesis as reference reconstruction
- Evidence level
- Consensus / Level IV
- Position
- No technique proven superior for chronic SL instability; prospective trials needed
- Evidence level
- Level III (heterogeneous)
Registry Evidence
No national joint registry (AOANJRR, NJR, AJRR) collects carpal-ligament reconstruction as a discrete, tracked procedure, so registry-grade survivorship data do not exist for DISI/VISI surgery. The best available pooled evidence comes from systematic reviews rather than registries.
- Chronic non-arthritic SL dissociation: pain fell from 6.0 to 2.8 at 2 years with capsulodesis and tenodesis performing similarly; complication rate 20%, CRPS 3.8% (Naqui 2017, PMID 29022774).
- Capsulodesis versus reconstruction: no significant difference in motion or radiographic correction across 308 patients (Wang 2016, PMID 28690470).
- Acute perilunate injuries: pooled complications include arthritis 30%, carpal instability 15%, lunate avascular necrosis 12% (Lee 2023, PMID 36708152).
Practice Variation
- Diagnosis. Wrist arthroscopy is the diagnostic reference standard internationally, but access varies; MRI and MR arthrography (around 90% sensitivity/specificity for SL tears) are first-line where arthroscopy is rationed.
- Timing. Universal agreement that acute reparable SL tears (within ~6 weeks) do best with early repair; the threshold for reconstruction versus salvage in chronic disease varies by surgeon and resource setting.
- Reconstruction choice. Three-ligament tenodesis (Garcia-Elias) predominates in Europe/UK; RASL, internal-brace augmentation and capsulodesis remain in use across North America, reflecting absence of comparative superiority data.
- Rehabilitation. Specialist hand therapy and custom thermoplastic splinting are standard of care in high-income settings but are less consistently available in lower-resourced settings.
Viva Scenarios
Examination Practice
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old man presents 3 months after a fall on his outstretched hand. He has persistent dorsal wrist pain and weakness. X-rays show widened SL interval and increased SL angle. How would you assess and manage this patient?”
“You are shown a lateral wrist X-ray with SL angle of 25 degrees and capitolunate angle of 20 degrees. What is the diagnosis and how does this differ from DISI?”
“Describe the Mayfield classification of perilunate instability and explain the anatomical basis for this progression.”
MCQ Practice Points
Q: What SL angle confirms DISI pattern on lateral wrist radiograph?
A: Greater than 70 degrees confirms DISI pattern. Normal SL angle is 30-60 degrees (average 47 degrees). VISI pattern shows SL angle less than 30 degrees.
Q: A patient with perilunate dislocation has disruption of SL and LT ligaments with the lunate still in the lunate fossa. What Mayfield stage is this?
A: Stage III - includes SL disruption (Stage I), capitolunate disruption (Stage II), and LT disruption (Stage III). Stage IV would show lunate dislocation into carpal tunnel.
Q: Which clinical test is most specific for scapholunate ligament injury?
A: Watson scaphoid shift test - pressure on scaphoid tubercle while moving wrist from ulnar to radial deviation produces painful dorsal subluxation clunk. Must compare to contralateral side as may be positive bilaterally in lax individuals.
Q: What is the preferred treatment for chronic LT instability with static VISI deformity?
A: LT arthrodesis - provides 90% union rate with minimal motion loss since LT joint contributes little to overall wrist motion. More predictable than ligament reconstruction.
Q: What is the natural history of untreated chronic SL dissociation?
A: SLAC wrist (scapholunate advanced collapse) - predictable arthritis pattern progressing from radial styloid to scaphoid fossa to capitolunate joint. Radiolunate joint typically spared. 30-50% develop arthritis within 10 years.
Radiographic Criteria
- Normal SL angle: 30-60° (average 47°)
- DISI: SL angle over 70°, lunate extended dorsally
- VISI: SL angle under 30°, lunate flexed palmarly
- Normal CL angle: under 15°
- SL gap over 3mm = Terry Thomas sign
- Scaphoid ring sign = rotatory subluxation
Clinical Tests
- Watson scaphoid shift: SL instability (DISI)
- LT ballottement (Reagan's): LT instability (VISI)
- Compare all tests to contralateral side
- Dynamic instability = positive stress tests only
- Static instability = abnormal standard X-rays
Mayfield Stages
- Stage I: SL ligament
- Stage II: + Capitolunate (perilunate dislocation)
- Stage III: + LT ligament
- Stage IV: + Dorsal radiocarpal (lunate dislocation)
Treatment Algorithm
- Acute SL (under 6 weeks): Direct repair + K-wires
- Chronic SL (no arthritis): Tendon reconstruction
- SL + arthritis: Limited fusion or salvage
- LT instability: Arthrodesis preferred (90% union)
- Salvage: PRC, 4-corner fusion, wrist fusion
Key Biomechanics
- Scaphoid flexes; triquetrum extends
- Lunate follows attached bone
- SL tear leads to lunate follows triquetrum leads to DISI
- LT tear leads to lunate follows scaphoid leads to VISI
- DISI 10× more common than VISI
Exam Tips
- Always compare to contralateral wrist
- Explain intercalated segment concept
- Know Mayfield stages for viva
- Understand why reconstructions fail over time
- Be able to interpret lateral wrist X-rays
Evidence Base
Current Evidence
Mayfield Classification - Progressive Perilunar Instability
- Cadaveric loading of 32 wrists to failure (mechanism: extension, ulnar deviation, intercarpal supination) produced 13 perilunate and 2 lunate dislocations in a sequential, predictable fashion. Defined the four-stage perilunar instability (PLI) scale: Stage I (scapholunate diastasis, least instability) through Stage IV (lunate dislocation, greatest instability). Reduction was achieved by reversing the injury mechanism.
Geissler Arthroscopic Classification (Original Description)
- Arthroscopy of 60 displaced intra-articular distal radius fractures found intracarpal soft-tissue injury in 41 patients (68%): TFCC tears (26), scapholunate interosseous tears (19) and lunotriquetral tears (9). This is the source describing the arthroscopic grading of interosseous ligament injury (probing from the midcarpal joint) now known as the Geissler classification.
Dorsal Capsulodesis - Intermediate Outcomes
- 31 patients with chronic SL dissociation (18 dynamic, 13 static) treated by dorsal capsulodesis (Blatt or Mayo technique), mean follow-up 54 months. Wrist motion fell ~20% and grip strength did not improve. Pain improved but only 2 patients were pain-free. Radiographically the SL gap increased (2.7 to 3.9 mm) and the SL angle increased (56 to 62 degrees) - capsulodesis did not maintain carpal alignment.
Dorsal Intercarpal Ligament Capsulodesis - Long-Term
- 59 patients followed a mean of 8.25 years after capsulodesis for static SL instability. Mean DASH 28 and Mayo wrist score 61. After early improvement, mean SL and radiolunate angles deteriorated back toward pre-operative values and carpal height index fell; 78% had radiographic degenerative arthritis. Capsulodesis did not maintain carpal reduction over time, although most patients retained acceptable function.
Lunotriquetral Arthrodesis - Technique and Union
- 22 patients undergoing LT arthrodesis. Herbert screw supplemented with a K-wire, combined with immobilisation longer than 6 weeks, achieved union in all patients - including revision of prior failed arthrodesis. Pain improved in all and all previously-working patients returned to work. Routine PA/lateral films frequently failed to profile the fusion; fluoroscopy or tomography is recommended to confirm union.
LT Arthrodesis - High Failure Rate Caution
- 29 patients with chronic LT ligament tears treated by LT arthrodesis. Fusion was achieved in only 16 cases with non-union persisting in 13; 17 wrists remained painful and 19 patients required on average two additional procedures, three progressing to total wrist arthrodesis. The authors questioned the procedure relative to ligamentoplasty and extended (four-corner) arthrodesis.
Garcia-Elias Three-Ligament Tenodesis (Reference Reconstruction)
- Describes a prognostic six-stage treatment algorithm for SL instability and the three-ligament tenodesis (3LT) for non-repairable complete SL rupture causing reducible carpal malalignment without secondary osteoarthritis. Reports promising early results for restoring carpal alignment, combining features of three earlier techniques.
SLAC Wrist - Natural History of Untreated SL Dissociation
- Review of 4000 wrist radiographs identified 210 cases of degenerative arthritis. The commonest pattern (57%) was radioscaphoid-to-scaphocapitate degeneration (SLAC), 27% was scapho-trapezio-trapezoid, and 15% combined. The radiolunate joint is characteristically spared, defining the predictable SLAC progression.
Capsulodesis vs Reconstruction - Pooled Evidence
- Systematic review of 308 patients across 11 studies (chronic SL tears, mean 11 months to surgery). No significant difference between capsulodesis and ligament reconstruction in wrist flexion or extension. Pooled post-operative SL angle/gap were 60.3 degrees / 3.44 mm after capsulodesis and 56.5 degrees / 2.72 mm after reconstruction. Studies were heterogeneous, precluding a definitive recommendation.