Contrast-Enhanced Joint Imaging for Intra-articular Pathology
Direct MR Arthrography: Joint injection (Gd-DTPA diluted) + MRI. Best for labral tears, partial cuff tears, capsular pathology
Indirect MR Arthrography: IV gadolinium + exercise + MRI. Non-invasive but inferior to direct
CT Arthrography: Joint injection (iodinated contrast) + CT. For bony detail, MRI contraindication
Conventional Arthrography: Joint injection + fluoroscopic radiographs. Largely replaced by MRA/CTA
Key: Direct MRA is the gold standard for intra-articular soft tissue pathology; CT arthrography excels at bony assessment
- Direct MR arthrography (MRA): gadolinium is INJECTED directly into the joint under fluoroscopic or ultrasound guidance, then MRI is performed.
- Indirect MR arthrography: gadolinium is given INTRAVENOUSLY, then the patient exercises to promote diffusion of contrast into the joint.
- Direct MRA is the gold standard for labral pathology — distension of the joint with contrast separates labral tissue from the glenoid, improving tear detection.
- CT arthrography uses iodinated contrast injected into the joint, followed by CT — excellent for bony detail (glenoid bone loss, Hill-Sachs) and in patients with MRI contraindications.
- The key indication for arthrography over non-contrast MRI is the improved detection of partial-thickness tears, labral tears, and capsular pathology.
- “Direct MRA pooled sensitivity for labral tears (about 88%) is significantly higher than non-contrast MRI (about 76%); MRA also has higher specificity (93% vs 87%).
- “Gadolinium for MRA is diluted to approximately 1:200 (2mmol/L). The relationship is BIPHASIC - gadolinium shortens T1 (brightening) and T2 (darkening), and past the peak the T2 effect dominates, so an undiluted agent produces signal LOSS. Adding iodinated contrast to confirm needle position lowers T1 signal by about 26% and shifts the peak lower still, so that mixture needs more dilution.
- “Images must be acquired within 30-60 minutes of injection — contrast absorption reduces diagnostic quality rapidly.
- “CT arthrography is the preferred alternative when MRI is contraindicated (pacemaker, metal) and is superior for assessing glenoid bone loss.
- “The sublabral recess and sublabral foramen are NORMAL VARIANTS that mimic labral tears — knowing these prevents surgical over-treatment.
Overview
Arthrography is the introduction of contrast material into a joint to improve the imaging of intra-articular structures. It is one of the most valuable diagnostic techniques for labral pathology, partial-thickness rotator cuff tears, cartilage lesions, loose bodies and capsular abnormalities.
The principle. Contrast fills the joint, outlining the intra-articular structures and separating them from one another. A tear that is invisible on non-contrast MRI becomes conspicuous once contrast insinuates into the defect and creates a high-contrast interface with the adjacent tissue.
What distension adds. The distended capsule mechanically separates the labrum from the glenoid, the capsule from bone and one tendon layer from the next, and the contrast finds its way into partial-thickness tears (undersurface cuff tears, labral tears) that non-contrast MRI can miss. The distended capsule is itself informative: capsular redundancy in multidirectional instability, HAGL lesions, the capsular adhesions of adhesive capsulitis and loose bodies are all shown.
Direct and indirect. Direct arthrography is percutaneous injection of contrast into the joint under image guidance, fluoroscopy or ultrasound, which gives consistent, controlled distension and a high intra-articular contrast concentration. Indirect arthrography gives gadolinium intravenously and then has the patient exercise gently for 10-15 minutes so that contrast diffuses across the synovial membrane into the joint. It is non-invasive, but distension is less reliable and the intra-articular concentration lower, so direct arthrography is the technique of choice whenever arthrography is indicated.
MR and CT. MR arthrography uses dilute gadolinium, bright on T1, and its soft tissue contrast suits labral tears, partial cuff tears, cartilage defects and capsular pathology. CT arthrography uses dilute iodinated contrast and gives superior bony detail: quantification of glenoid bone loss, measurement of a Hill-Sachs lesion, and osteochondral defects. When each is chosen is set out under the joint-specific applications below.
Direct Arthrography Technique
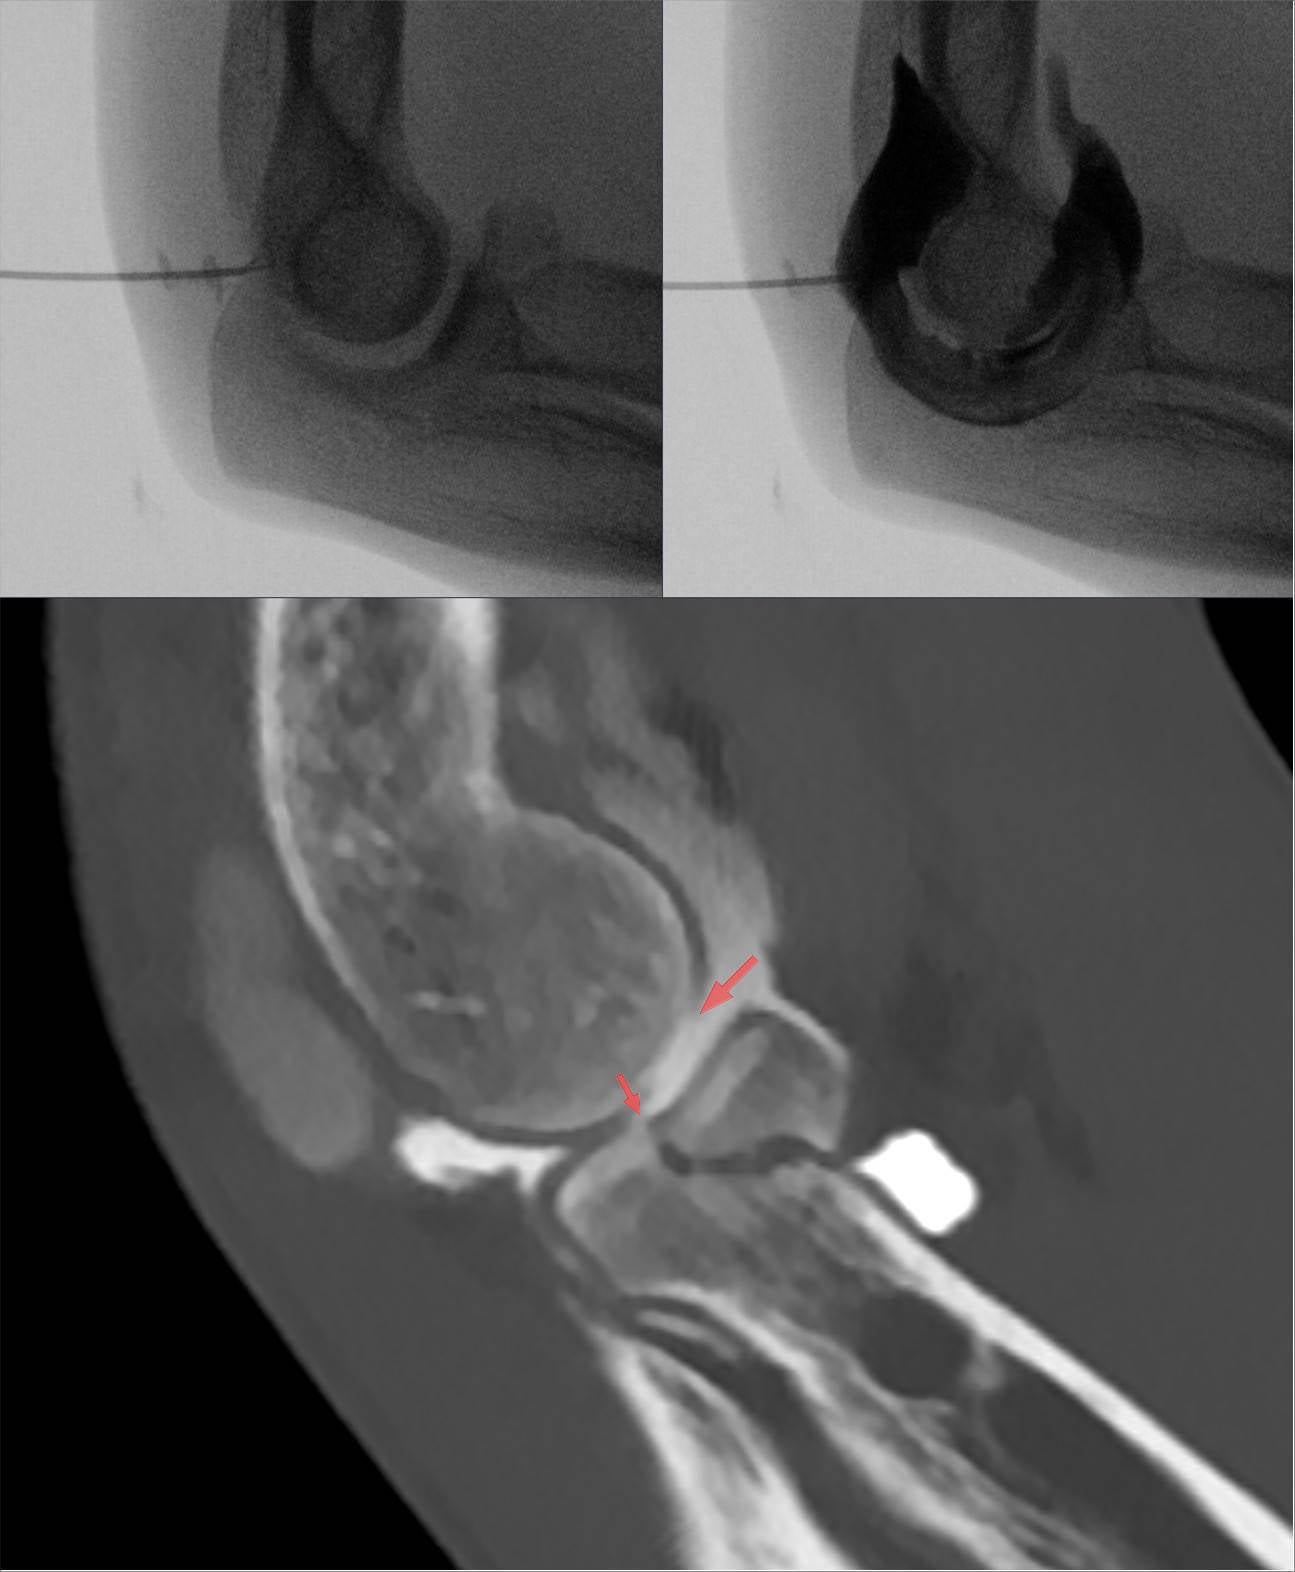
Needle placement. A 22-gauge spinal needle is advanced into the joint under fluoroscopic or ultrasound guidance, and a small test injection of iodinated contrast confirms the intra-articular position on fluoroscopy before the diagnostic contrast goes in.
Why gadolinium is diluted. For MR arthrography the gadolinium is diluted to about 1:200 in saline, which is 2 mmol/L. Its effect on signal is biphasic, not paradoxical: gadolinium shortens both T1, which raises signal, and T2*, which lowers it, and above the peak concentration the T2* effect wins, so an undiluted agent goes dark. The test injection sets a trap here. Iodinated contrast mixed with gadolinium cuts T1 signal by about 26% at 2 mmol/L and shifts the peak to a lower gadolinium concentration, so a gadolinium-iodine mixture needs more dilution, not the standard recipe.
Volume. Enough is injected to distend the capsule and separate the intra-articular structures. The same volumes serve MR and CT arthrography:
- Shoulder: 10-20 mL
- Hip: 10-15 mL
- Elbow: 7-10 mL
- Ankle: 5-8 mL
- Wrist: 3-5 mL
Timing. Image within 30-60 minutes of the injection. The synovium absorbs contrast progressively, and diagnostic quality degrades with it.
Sequences. T1-weighted fat-suppressed images are the mainstay. Gadolinium is bright on T1, so a contrast-filled tear stands out against the dark background of fat-suppressed tendon and labrum. T2-weighted sequences complement them by showing effusion and oedema.
Contraindications, Complications & Technical Pitfalls
Arthrography is an invasive procedure, and the examiner expects you to be able to consent a patient for it and to recognise its complications and technical pitfalls.
- Reason / action
- Absolute — risk of seeding the joint; choose another approach or defer until resolved
- Reason / action
- Do a diagnostic ASPIRATION (and culture), not a contrast study — and never inject contrast/steroid into a potentially infected joint
- Reason / action
- Gadolinium reactions are rare; for iodinated CT arthrography use premedication or switch to a gadolinium/MR study; document the reaction history
- Reason / action
- Relative — correct or check coagulation before deep injections (e.g. hip); small-joint injections carry lower risk
- Reason / action
- Avoid fluoroscopic guidance (ionising radiation) — use ultrasound guidance instead; weigh the need for the study
- Reason / action
- May preclude a safe injection or diagnostic-quality imaging
Complications. Most are minor and self-limiting:
- Post-arthrography pain and transient chemical synovitis, common over the 24-48 hours after injection: a mild inflammatory response to contrast and distension, managed with rest, ice, simple analgesia or NSAIDs, and reassurance
- Vasovagal reaction during the injection: lie the patient flat, elevate the legs and observe
- Infection and septic arthritis: rare with strict aseptic technique, but the most feared complication. Suspect it with disproportionate pain, swelling, fever and erythema in the days after the procedure, and treat as septic arthritis: aspirate, culture, antibiotics
- Contrast reaction, allergic or physiological, to gadolinium or iodinated contrast, managed by the standard contrast-reaction protocols
- Bleeding and haematoma, especially in anticoagulated patients or after deep injections
- Needle injury to adjacent neurovascular structures, the concern at the hip, where the femoral bundle lies medial to the head-neck target
The air-bubble pitfall. Air injected inadvertently with the contrast appears as one or more rounded intra-articular filling defects that can be mistaken for chondral or osteochondral loose bodies. An air bubble is perfectly round and smooth, has no internal trabeculation or ossification, and moves to the non-dependent, uppermost part of the joint when the patient is repositioned, whereas a true loose body falls to the dependent recess. Minimise injected air so that the artefact is not created in the first place.
Pitfalls: Normal Variant vs True Tear
The interpretive skill that matters most in shoulder arthrography is telling a normal anterosuperior labral variant from a true tear. Mislabelling a sublabral foramen or a Buford complex as a Bankart lesion can lead to inappropriate surgery.
The variants. Each is a normal finding that mimics a tear:
- Sublabral foramen: an opening between the anterosuperior labrum and the glenoid, present in about 12-18% of shoulders. A normal variant, not a Bankart lesion
- Sublabral recess: the superior labrum may have a normal recess beneath a meniscoid attachment, deepest at 11-1 o'clock, which can mimic a SLAP tear
- Buford complex: complete absence of the anterosuperior labrum with a thick, cord-like middle glenohumeral ligament. Not pathological and needs no treatment; never report the cord-like ligament as a displaced labral fragment
Labral morphology also varies normally, triangular, rounded, flat or cleaved, and variation alone does not indicate pathology. The normal synovial recesses, the axillary pouch and the subscapularis bursa, should likewise not be read as pathological collections.
- Normal variant (do NOT treat)
- Anterosuperior labrum, 1–3 o'clock (sublabral foramen); superior recess 11–1 o'clock
- True labral tear (treat)
- Anteroinferior (Bankart, 3–6 o'clock) or extending below the equator
- Normal variant (do NOT treat)
- Smooth, well-corticated, regular contrast cleft
- True labral tear (treat)
- Irregular, frayed or displaced labral fragment with contrast tracking into substance
- Normal variant (do NOT treat)
- Smoothly contoured, parallel to glenoid rim (sublabral recess medially angled, smooth)
- True labral tear (treat)
- Laterally extending, irregular, full-thickness separation
- Normal variant (do NOT treat)
- No paralabral cyst, no bone oedema, intact periosteum
- True labral tear (treat)
- Paralabral cyst, glenoid rim fracture/oedema, capsular stripping (Perthes/ALPSA)
Systematic Approach
Read an arthrogram structure by structure: the labrum, the rotator cuff, the biceps tendon, the capsule and ligaments, the articular cartilage, and then any filling defect within the contrast.
- Normal Appearance
- Triangular or rounded, firmly attached to glenoid rim, smooth margins
- Pathological Findings
- Tear: contrast extending into or beneath the labrum. Bankart: inferior labral detachment. SLAP: superior labral tear with or without biceps anchor involvement
- Normal Appearance
- Intact tendon without contrast extension into the tendon substance
- Pathological Findings
- Full-thickness tear: contrast extends from joint into subacromial space. Partial tear (articular surface): contrast insinuates into undersurface of tendon without full extension through
- Normal Appearance
- Located in the bicipital groove, intimately associated with the rotator interval
- Pathological Findings
- Biceps subluxation: tendon displaces medially over the lesser tuberosity. Sheath tear: contrast extends into the bicipital sheath
- Normal Appearance
- Capsule smoothly lines the joint. Glenohumeral ligaments visible as thickenings
- Pathological Findings
- HAGL: contrast extending beyond the humeral attachment site. Capsular redundancy: excessive volume in inferior pouch (MDI)
- Normal Appearance
- Smooth, uniform thickness articular surface without contrast undercutting
- Pathological Findings
- Chondral defect: contrast replaces or undercuts the cartilage surface. Grading by depth and area
- Normal Appearance
- No filling defects within the contrast-filled joint
- Pathological Findings
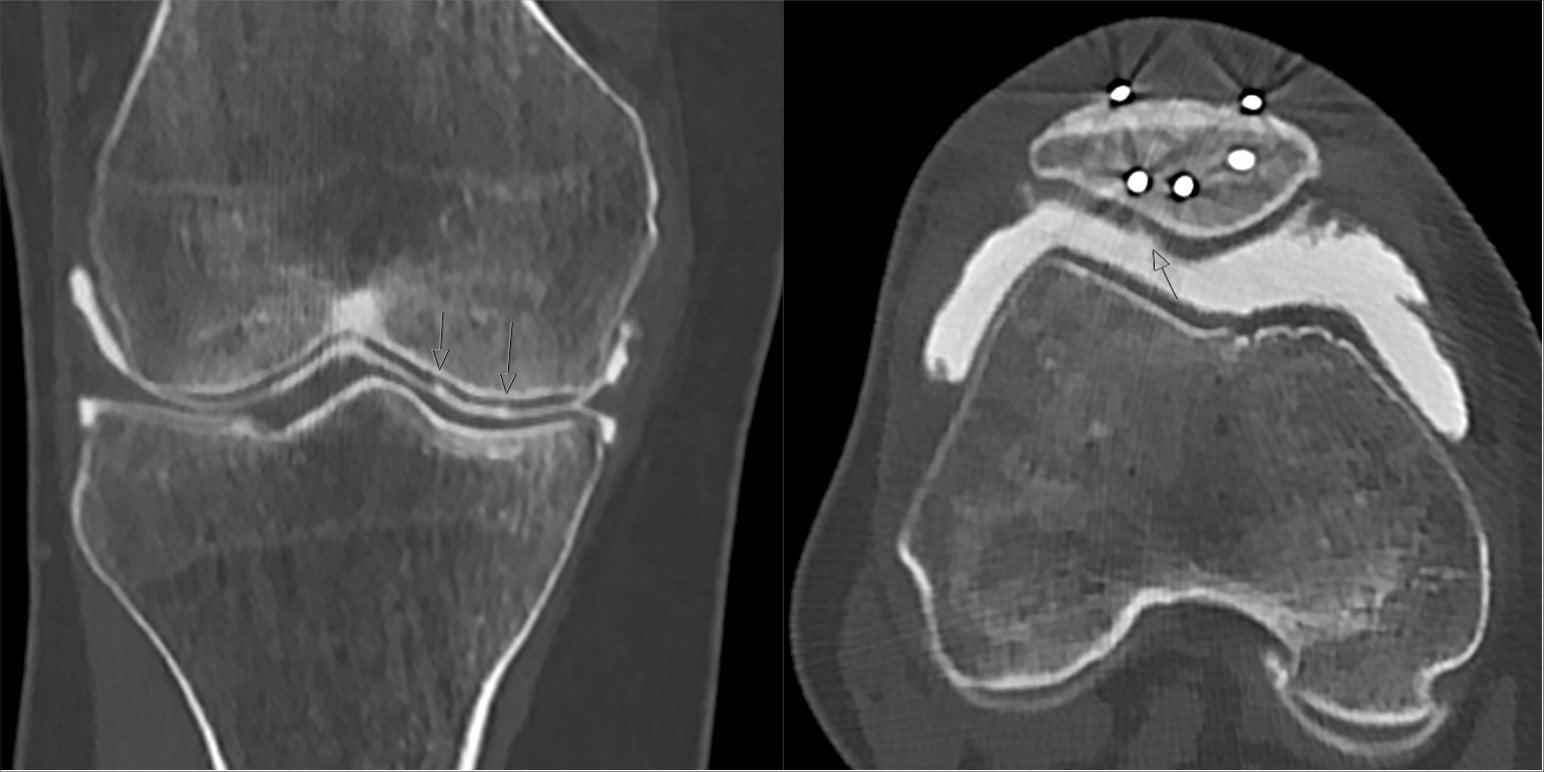
- Filling defect: contrast surrounds a dense rounded opacity (chondral or osteochondral loose body). Best seen on CT arthrography
Joint-Specific Applications
The shoulder is the most common joint for arthrography and the one most often examined. Direct MR arthrography of the shoulder is the gold standard for:
- Labral tears: Bankart (anterior-inferior), reverse Bankart (posterior), SLAP (superior) and HAGL lesions
- Partial-thickness rotator cuff tears, particularly articular-surface tears (Ellman classification)
- Capsular pathology, read from the capsular volume: increased in multidirectional instability, decreased in adhesive capsulitis
- Loose bodies
Injection. An anterior approach under fluoroscopy or ultrasound, the needle aimed at the junction of the middle and lower thirds of the glenoid; once the test injection confirms position, the joint is distended with dilute gadolinium.
Sequences. T1-weighted fat-suppressed images in three planes: axial, coronal oblique and sagittal oblique. The ABER position (abduction and external rotation), acquired in the axial plane, improves visualisation of the anterior-inferior labrum, the anterior band of the inferior glenohumeral ligament and undersurface cuff tears.
Accuracy. In a meta-analysis of 4,667 shoulders, direct MR arthrography reached a pooled sensitivity of 88% and specificity of 93% for glenoid labral lesions, against 76% and 87% for non-contrast MRI.
Guidelines, Registries & Global Practice
Arthrography is performed worldwide by radiologists or musculoskeletal subspecialty radiologists on referral from orthopaedic surgeons and sports physicians. Direct MR arthrography is the internationally accepted standard for glenohumeral labral assessment and acetabular labral evaluation. The injection is performed under fluoroscopic or ultrasound guidance; a gadolinium-based contrast agent (commonly gadopentetate dimeglumine or an equivalent macrocyclic agent) is diluted to approximately 2 mmol/L (about 1:200) in saline, and imaging is completed within 30–60 minutes before synovial absorption degrades joint distension.
- Position relevant to arthrography
- MR arthrography rated 'usually appropriate' for chronic shoulder instability/labral assessment and for suspected hip labral tear/FAI; ultrasound and non-contrast MRI prioritised for many cuff questions
- Practical implication
- Reserve invasive arthrography for labral and partial-cuff questions, not routine full-thickness cuff or first-line screening
- Position relevant to arthrography
- Imaging is adjunctive; advanced imaging (including arthrography) is directed by the specific surgical question rather than performed routinely
- Practical implication
- Order the arthrogram when it will change the operative plan (e.g. repair vs reconstruction)
- Position relevant to arthrography
- MR arthrography or high-quality non-contrast 3T MRI accepted for labral work-up; resource and access drive local choice
- Practical implication
- Either route acceptable where 3T MRI is available and reported by MSK radiologists
- Position relevant to arthrography
- Consensus/technical guidelines describe direct MRA injection technique, contrast dilution and ABER positioning as standard MSK practice
- Practical implication
- Standardised injection volumes and dilution improve reproducibility across centres
- Position relevant to arthrography
- Use macrocyclic (lower-risk) GBCAs; caution in severe renal impairment; document consent for intra-articular off-label use where required
- Practical implication
- Contrast-agent choice and consent are governed by general GBCA safety policy, not arthrography-specific rules
Registry & outcome context. There is no dedicated arthrography registry; the downstream procedures that arthrography informs are tracked instead. Shoulder-instability and labral-repair outcomes feed into arthroplasty/soft-tissue datasets and instability cohorts, and glenoid bone-loss thresholds (the Sugaya en-face method and the glenoid track concept) drive the registry-relevant choice between Bankart repair and bony reconstruction (Latarjet/bone block). Accurate preoperative bone-loss quantification on CT (with or without intra-articular contrast) is therefore the key audited determinant of which instability procedure is performed.
High- vs limited-resource practice variation. In well-resourced settings, 3T MRI and dual fluoroscopic/US-guided injection allow routine direct MRA and 3D CT with en-face glenoid reconstruction for preoperative planning. Where MRI access is constrained, CT arthrography becomes the primary cross-sectional arthrogram because CT is faster, cheaper and more widely available, and still answers bony and many labral questions; conventional fluoroscopic arthrography remains a legitimate fallback for confirming intra-articular position or gross capsular leak. Where advanced imaging is unavailable, diagnostic arthroscopy assumes a larger role. This variation reflects equipment access and cost, not differing biology, and examiners expect candidates to justify the chosen modality by the clinical question and the local resource context.
Controversies & Areas of Uncertainty
Direct MRA against high-field non-contrast MRI. As 3T scanners and high-resolution sequences have improved, the incremental benefit of an invasive arthrogram over modern non-contrast 3T MRI for labral pathology is debated. Meta-analytic data still favour MRA for sensitivity, but some centres reserve arthrography for equivocal 3T studies, which reduces the number of injections. The optimal threshold for proceeding to MRA is not standardised.
Measuring bone loss. 3D CT with the Sugaya en-face view is the traditional reference for glenoid bone loss, but MRI-based and glenoid-track methods are increasingly used, to avoid radiation and to assess bipolar loss, glenoid plus Hill-Sachs, together. The percentage that mandates bony reconstruction is a continuum modified by the glenoid track concept rather than a single fixed cut-off.
Gadolinium in the joint. Intra-articular gadolinium is an off-label use of gadolinium-based contrast agents. Concern about tissue deposition has driven a shift towards macrocyclic agents, and some groups use saline-only arthrography or dilute iodinated CT arthrography to avoid intra-articular gadolinium altogether. Local consent and contrast-safety policy govern practice.
The place of indirect MRA. Its role is contested. Most experts limit it to patients in whom direct injection is refused or unavailable, and many musculoskeletal radiologists do not offer it at all.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old man has recurrent anterior shoulder dislocations. His non-contrast MRI shows an equivocal anterior labral finding. You are considering further imaging.”
“A 30-year-old woman presents with deep groin pain and mechanical catching in her hip. You suspect a labral tear. Her plain radiographs show cam morphology.”
“An examiner asks you to compare direct MR arthrography, indirect MR arthrography, and CT arthrography. When would you choose each?”
Direct MR Arthrography (Gold Standard)
- Joint injection of dilute gadolinium (1:200 = 2mmol/L) under fluoroscopy/US
- Image within 30-60 minutes (contrast absorbs progressively)
- Pooled sensitivity for labral tears: ~88% (vs 76% non-contrast MRI); specificity 93% vs 87%
- Best for: labral tears, partial cuff tears, capsular pathology
- ABER position improves anterior labral visualisation
CT Arthrography
- Joint injection of dilute iodinated contrast + CT scanning
- Superior bony detail (0.3-0.5mm resolution)
- Gold standard for glenoid bone loss quantification (3D en-face views)
- Alternative when MRI is contraindicated (pacemaker, MRI-unsafe implants)
- More than 20-25% glenoid bone loss = Latarjet rather than Bankart repair
Injection Volumes
- Shoulder: 10-20mL (largest orthopaedic joint injection)
- Hip: 10-15mL (anterior approach, avoid neurovascular bundle)
- Ankle: 5-8mL
- Wrist: 3-5mL (smallest — risk of capsular rupture with overfilling)
Normal Variants (Do NOT Treat)
- Sublabral foramen: opening at 1-3 o'clock (12-18% of shoulders)
- Buford complex: absent anterosuperior labrum + thick cord-like MGHL
- Sublabral recess: superior labral recess at 11-1 o'clock (mimics SLAP tear)
- Key: smooth margins, consistent location, no paralabral cysts
Hip MRA Specifics
- Hip: sensitivity 87% vs 66%, BUT specificity 64% vs 79% - MRA finds more tears and calls more that are not there
- Alpha angle on radial sequences: more than 55-60 degrees = cam morphology
- Wave sign: chondral delamination (contrast undercuts cartilage)
- Anterior/anterosuperior tears most common in cam-type FAI
Evidence Base
MR Arthrography vs MRI for Glenoid Labral Injury
- Sixty studies pooling 4,667 shoulders from 4,574 patients, verified against arthroscopy or open surgery.
- MR arthrography pooled sensitivity 88% and specificity 93% for glenoid labral lesions, versus non-contrast MRI sensitivity 76% and specificity 87%.
- On summary ROC analysis MRA was marginally but consistently superior to MRI for detecting glenohumeral labral lesions (Level 2a evidence).
MRA vs Non-Contrast MRI for Rotator Cuff
- Meta-analysis of 65 studies with surgical (open or arthroscopic) reference standard comparing MRI, MR arthrography and ultrasound.
- MR arthrography was significantly more sensitive AND more specific than either MRI or ultrasound for both full- and partial-thickness rotator cuff tears.
- Area under the summary ROC curve was greatest for MRA (0.935), then ultrasound (0.889), then MRI (0.878); MRI and ultrasound did not differ significantly.
Why Gadolinium Is Diluted — Concentration & Iodine Effect
- Phantom study of gadopentetate diluted across 0.625–40 mmol/L in saline, albumin and iodinated contrast, scanned at 1.5T and 0.2T.
- Gadolinium signal is biphasic: signal rises to a peak then falls at higher concentrations — confirming that undiluted (highly concentrated) gadolinium loses T1 signal.
- Mixing gadolinium with iodinated contrast reduced T1 signal by ~26% at 2 mmol/L and shifted the signal peak to a LOWER gadolinium concentration.
MRA is most valuable for partial tears and labral lesions, and the dilute-gadolinium technique is grounded in the biphasic signal physics above.