Subtrochanteric/Diaphyseal | Transverse or Short Oblique | Associated with Prolonged Antiresorptive Therapy
- ASBMR criteria define atypical fractures - learn the 5 major features
- Bisphosphonate use greater than 5 years significantly increases risk
- Check contralateral femur - 28% bilateral, may be prodromal
- Drug holiday consideration after complete fracture
- IM nail preferred - allows prophylactic fixation of contralateral
- “Prodromal thigh pain in 70% - often for weeks/months before fracture
- “Lateral cortex stress reaction is pathognomonic on X-ray
- “Risk-benefit still favors bisphosphonates in most osteoporotic patients
- “Glucocorticoid use and Asian ethnicity increase risk
Overview and Epidemiology
Atypical femoral fractures (AFFs) are stress fractures of the femoral shaft associated with prolonged antiresorptive therapy, particularly bisphosphonates, and they have distinct clinical and radiographic features. The first reports emerged in 2005-2007; the ASBMR Task Force criteria were established in 2010 and revised in 2013, and the problem led to the "drug holiday" concept for long-term bisphosphonate users.
How common. The absolute incidence is 0.3-5 per 10,000 patient-years (Shane task force: 3.2-50 per 100,000; Schilcher: an absolute increase of about 5 per 10,000), rising to about 10 per 10,000 (about 100 per 100,000) with long-term use. Women predominate, which reflects bisphosphonate use patterns, and the mean age is 65-75 years.
Duration. Duration of bisphosphonate use is the most important risk factor, and the relationship is steep rather than a simple doubling: in Black's analysis the hazard ratio was 8.86 at 3-5 years and 43.51 at 8 or more years versus under 3 months. Asian ethnicity carries a higher risk (HR 4.84, Black; 8-fold, Lo).
Other risk factors.
- Increased age
- Glucocorticoid use
- Femoral bowing (varus geometry)
- Rheumatoid arthritis
- Prior contralateral AFF
- Vitamin D deficiency
- Proton pump inhibitors (may increase risk)
- Osteoporosis severity (underlying bone quality)
- Oestrogen receptor status (hormonal factors)
Despite concerns about AFFs, bisphosphonates prevent far more fractures than they cause. Black's 196,129-woman analysis found 149 hip fractures prevented for every 2 bisphosphonate-associated AFFs in White women (about 75:1), versus 91 prevented for 8 AFFs in Asian women (about 11:1). The risk-benefit still strongly favours treatment in most osteoporotic patients; net benefit is large but markedly attenuated in Asian patients, which is why duration and ethnicity are individualised. The drug class, its mechanism and the duration data behind the drug holiday are set out in bisphosphonates, the disease being treated in osteoporosis, and the fracture pattern this must be distinguished from in subtrochanteric fractures.
Anatomy and Pathophysiology
Where they occur. AFFs occur in the subtrochanteric region, 5cm distal to the lesser trochanter, and in the femoral shaft down to the supracondylar flare. These are the areas of maximum tensile stress on the lateral cortex during gait.
Why the lateral cortex. During normal gait the femur experiences bending moments: the lateral cortex is under tension and the medial cortex under compression. Tension causes the stress fracture to initiate laterally and propagate medially, which explains the characteristic radiographic appearance. Varus alignment increases lateral cortex stress, femoral bowing increases the bending moment, and Asian patients often have more varus and bowing, contributing to their higher incidence.
How bisphosphonates contribute. Bisphosphonates inhibit osteoclast activity and suppress bone remodelling, so microdamage accumulates without repair. Over time mineralisation increases and the matrix becomes more homogeneous, with a reduced ability to absorb energy: the bone is more brittle. Microcracks develop in the lateral cortex, cannot heal because turnover is suppressed, and progress to a complete fracture.
- Normal Bone
- Variable
- Long-term Bisphosphonate
- Increased, homogeneous
- Normal Bone
- Normal
- Long-term Bisphosphonate
- Altered
- Normal Bone
- Repaired
- Long-term Bisphosphonate
- Accumulated
- Normal Bone
- Higher
- Long-term Bisphosphonate
- Lower (brittle)
- Normal Bone
- Higher
- Long-term Bisphosphonate
- Reduced
Bisphosphonates improve bone density and reduce vertebral and hip fracture risk. Long-term use, however, may alter bone quality in ways that increase brittleness, which is why drug holidays are considered after 5 or more years.
Classification - ASBMR Criteria
Under the revised (2013) definition of the American Society for Bone and Mineral Research (ASBMR), 4 of 5 major criteria must be present to diagnose an atypical femoral fracture:
- Description
- Subtrochanteric or diaphyseal
- Key Points
- Distal to lesser trochanter to supracondylar
- Description
- Transverse or short oblique
- Key Points
- Less than 30 degrees from horizontal
- Description
- Minimal or no trauma
- Key Points
- Fall from standing or less, no trauma
- Description
- Non-comminuted or minimal
- Key Points
- Simple fracture pattern
- Description
- Localised periosteal/endosteal reaction
- Key Points
- Cortical thickening, beaking
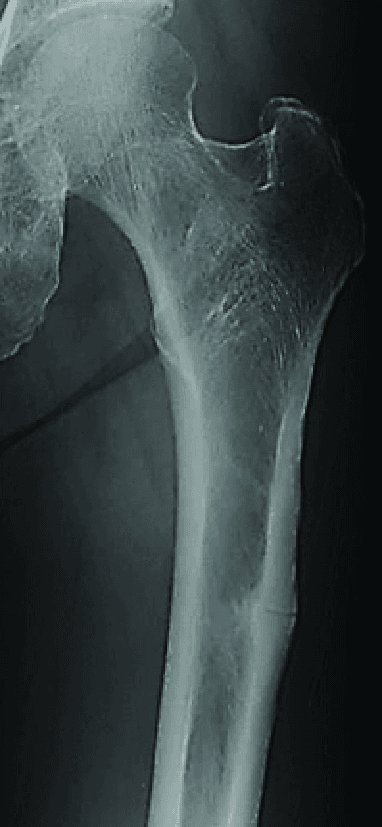
Lateral cortex beaking is the pathognomonic feature. It represents the stress reaction where the fracture initiates. On the radiograph, look for localised cortical thickening with a transverse lucent line.
Clinical Presentation and Assessment
History. Ask about the duration and type of bisphosphonate or antiresorptive therapy, the mechanism of the fracture (usually minimal trauma), any previous contralateral symptoms or fracture, the osteoporosis treatment history and glucocorticoid use.
Prodromal pain. 70% of patients with a complete AFF report prodromal thigh or groin pain for weeks to months beforehand. It is felt in the anterior or lateral thigh and is worse with weight bearing, which is typical stress fracture behaviour; a dull ache at rest, perhaps with night pain, indicates a progressive stress reaction. This is a missed opportunity for intervention: any patient on long-term bisphosphonates with thigh pain should have imaging to rule out a stress fracture. Symptoms may be bilateral, and 28% of patients have bilateral involvement.
Examination of the complete fracture. A shortened, externally rotated limb with thigh swelling and deformity, unable to bear weight. The neurovascular examination is usually intact; assess the skin for an open injury.
Examination of the incomplete fracture. The limb may look normal. Look for point tenderness over the lateral thigh and pain on weight bearing; the full range of hip motion is usually preserved.
Investigations
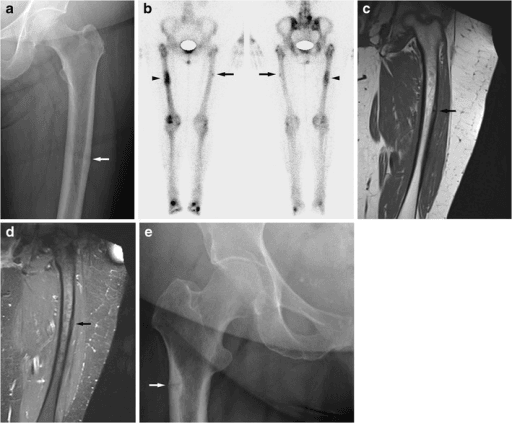
Radiographs. AP and lateral views of the full-length femur are essential: they show the entire femur for stress reactions and allow the fixation to be planned (nail length, starting point). Imaging of both femora is mandatory, to check for contralateral changes. Look for:
- Lateral cortex beaking or thickening: localised cortical thickening, the stress reaction
- A transverse lucency, a crack in the lateral cortex: an incomplete fracture
- A complete fracture with a transverse pattern and minimal comminution, meeting the ASBMR criteria
- A medial spike, a beak on the medial cortex of a complete fracture, which is a common finding
MRI is the test when the radiograph is inconclusive. It shows bone marrow oedema at the stress reaction site, and the fracture line may be visible before any radiographic change, which makes it useful for early and incomplete fractures.
Bone scan shows a hot spot at the stress fracture site. It is less specific than MRI but can assess bilateral involvement.
CT gives better cortical detail than the radiograph, can show early cortical changes, and helps with surgical planning.
Laboratory investigations.
- Vitamin D level: deficiency is common and affects healing
- Calcium and phosphate
- Alkaline phosphatase: low in hypophosphatasia
- PTH if secondary hyperparathyroidism is suspected
- Bone turnover markers: research interest
Management
- Key Action
- Confirm ASBMR criteria, image contralateral
- Treatment
- IM nail fixation, consider drug holiday
- Key Action
- Protected weight bearing, serial imaging
- Treatment
- Prophylactic IM nail if progression or persistent pain
- Key Action
- X-ray and MRI if X-ray negative
- Treatment
- Stop bisphosphonate, calcium/vitamin D, monitor
- Key Action
- Stage surgery or fix both at same session
- Treatment
- IM nail both femurs
- Key Action
- Drug holiday vs alternative agent
- Treatment
- Endocrinology referral, fracture liaison service
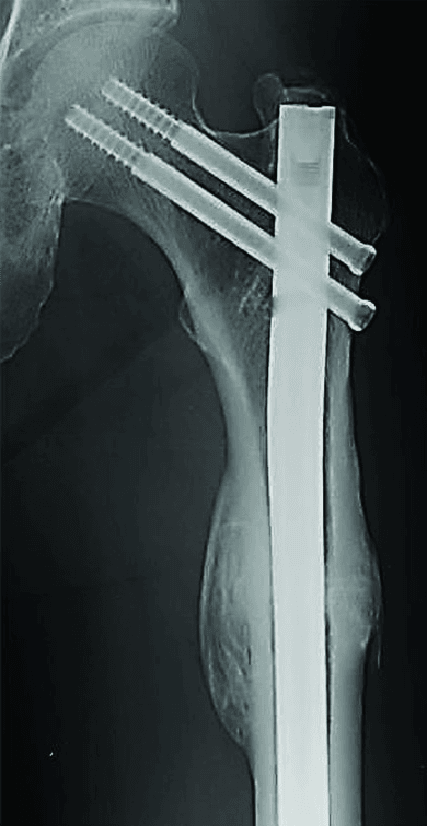
Surgical fixation is required for all complete AFFs, and the preferred implant is an intramedullary nail: a cephalomedullary nail (e.g., gamma nail, PFNA). It provides load-sharing fixation, protects the entire femur, allows immediate weight bearing (depending on the fixation), and enables bilateral fixation at the same sitting.
Surgical considerations. The entry point, piriformis or trochanteric, depends on the nail design. Ensure good distal locking, consider supplementary fixation if the fracture is comminuted, and assess and address the contralateral femur.
Lateral plate fixation alone should be avoided for atypical fractures. The plate creates a stress riser at its ends, and the abnormal bone quality may predispose to failure. If a plate is used, protect the entire femur.
Surgical Technique
Positioning. Supine on a radiolucent fracture table with the boot attached and traction applied, the contralateral leg in lithotomy or extended, and C-arm access for AP and lateral views.
Reduction. Traction and internal rotation typically reduce the fracture; external reduction aids may be needed for shortening or rotation. A varus tendency is common, so ensure proper alignment and confirm the reduction on fluoroscopy before nailing. Atypical fractures often have sharp transverse edges, and the fracture may need to be opened and reduced if closed reduction fails; avoid excessive manipulation, because the bone quality is poor.
A favourite operative-pitfall question: the same patients prone to AFF (older, often Asian, with femoral varus/bowing) have femora that do not accept a standard straight intramedullary nail, and the mismatch causes intra-operative disasters.
The problem. A Western straight (or standard-radius) nail in a markedly bowed, hard, brittle diaphysis impinges on the anterior and/or lateral cortex, risking iatrogenic cortical perforation/fracture, malreduction into the bow (apex-anterior/varus), and inability to fully seat the nail. The dense, low-turnover bone is unforgiving.
Planning. Template the radius of curvature against the implant on full-length films. In a very bowed femur choose a nail whose curvature matches the bone (smaller radius of curvature), a shorter nail that stops before the distal bow, or accept a more distal starting point, and have a contingency for opening the fracture.
Intra-operative. Ream carefully (brittle bone), advance the nail slowly watching the cortices on orthogonal fluoroscopy, and use blocking (Poller) screws or an open reduction to steer the nail and prevent the malalignment the bow tends to impose. For a severe deformity a corrective osteotomy at the apex may be needed to pass the nail and restore alignment.
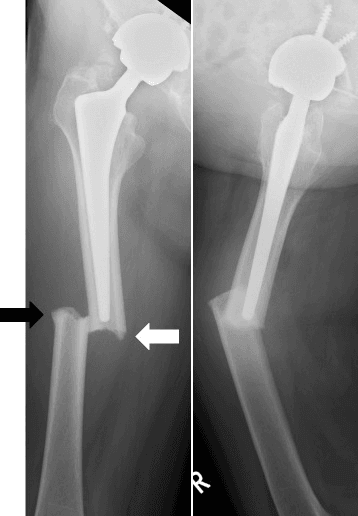
Special case: peri-implant. An AFF can occur at the tip of a hip stem or below a sliding hip screw plate; here a nail may not be possible and a plate (or revision arthroplasty) spanning the whole bone is used instead.
Complications
- Incidence
- 20-30%
- Prevention/Management
- Teriparatide, revision surgery, bone graft
- Incidence
- 28% overall
- Prevention/Management
- Prophylactic fixation, imaging surveillance
- Incidence
- 5-10%
- Prevention/Management
- Long nail, protect entire femur
- Incidence
- Variable
- Prevention/Management
- Adequate fixation, consider bone quality
- Incidence
- Common
- Prevention/Management
- May relate to implant, bone healing, or new stress reaction
- Incidence
- Variable
- Prevention/Management
- Careful intraoperative assessment, long nail
Delayed union and nonunion. The rate is higher than in typical femoral shaft fractures, at 20-30%, and is related to the suppressed bone turnover from bisphosphonate use. Consider teriparatide to stimulate healing, involve endocrinology for optimisation, and be prepared to revise with bone grafting.
Contralateral fracture. Bilateral involvement may present simultaneously or sequentially, which is the reason for contralateral imaging and for prophylactic fixation when an incomplete fracture is identified.
The high nonunion rate is not only from suppressed bone turnover: a large part is surgeon-modifiable, and this is the point examiners want beyond "the bone is slow to heal".
Varus malreduction is the enemy. AFFs are transverse fractures of a bowed, varus femur, so a nail naturally tends to leave the fracture in varus and apex-anterior, and malalignment (especially varus) is independently associated with delayed/failed union (the Egol data). Aim for an anatomic, slightly valgus-not-varus reduction.
Close the gap, achieve cortical contact. A transverse fracture must be well-apposed and compressed, not distracted. A residual fracture gap in low-turnover bone will not bridge: "fit-and-fill" the canal, back-slap or compress to close the gap, and open the fracture if a closed reduction leaves a gap or malalignment (open reduction does not preclude union, and lets you remove interposed tissue and apply a reduction clamp).
Mechanical environment. Avoid both excessive rigidity with a gap (no callus stimulus) and instability; a load-sharing full-length nail with good cortical apposition is the goal, with supplementary plating reserved for refractory cases.
Biology in parallel. Stop the antiresorptive, optimise vitamin D and calcium, and consider teriparatide, but biology will not rescue a malaligned, gapped construct. Most AFF nonunions are predictable, and a well-aligned, apposed nail is the single best determinant of union.
Postoperative Care and Rehabilitation
- Weight bearing as tolerated (typically)
- DVT prophylaxis
- Pain management
- Early mobilisation with physiotherapy
- Wound care
- Progressive ambulation
- Discharge home when safe
- Outpatient physiotherapy
- Monitor wound healing
- X-ray at 6 weeks
- Continued strengthening
- Serial X-rays to monitor healing
- Watch for delayed union
- May require extended time to unite
- Consider teriparatide if delayed
- Ongoing healing assessment
- May take 6-12 months to fully unite
- Address bone health
- Endocrinology referral for osteoporosis management
- Drug holiday discussion
Rehabilitation. Early weight bearing with the nail is balanced against monitoring of healing, and an extended healing time is expected. Address falls risk alongside comprehensive bone health management.
Bone health. The drug holiday, endocrinology referral and teriparatide are set out under Management. The practical adjuncts are calcium 1000-1200mg/day, vitamin D to normalise levels (target greater than 50nmol/L), and involvement of the fracture liaison service.
Outcomes and Prognosis
What decides healing.
- Impact on Outcome
- Longer duration associated with slower healing
- Impact on Outcome
- Nail has better outcomes, fewer complications
- Impact on Outcome
- May accelerate healing
- Impact on Outcome
- Deficiency delays healing
- Impact on Outcome
- Delays healing
- Impact on Outcome
- Increases morbidity
Function. Most patients return to their pre-injury function, although some persistent thigh discomfort is common. Hardware removal is rarely needed. Falls prevention matters, to prevent a contralateral fracture.
Guidelines, Registries & Global Practice
Global epidemiology: The absolute risk of atypical femoral fracture (AFF) in patients on bisphosphonates is consistently low across registries, while the relative risk is high and strongly duration-dependent. Asian ethnicity is a striking, duration-independent risk factor reported across multiple health systems.
- AFF incidence or risk
- Absolute increase 5 per 10,000 patient-years; RR 47.3
- Notes
- Risk falls ~70% per year after withdrawal
- AFF incidence or risk
- 1.78 → 113.1 per 100,000/yr (0–2 vs 8–10 yr use)
- Notes
- Incidence rises sharply with duration
- AFF incidence or risk
- HR 8.86 at 3–5 yr → 43.51 at greater than 8 yr
- Notes
- Asian vs White HR 4.84
- AFF incidence or risk
- Asian 64.2 vs White 7.6 per 100,000/yr (8-fold)
- Notes
- Adjusted HR 8.5
Side-by-side guidance from major bodies:
- Core guidance on AFF / long-term antiresorptives
- 5 major / 4 minor criteria; reassess after 5 yr oral or 3 yr IV; drug holiday 2–3 yr if no longer high-risk; continue to 10 yr (oral)/6 yr (IV) if high-risk
- Evidence level
- Expert consensus on cohort data
- Core guidance on AFF / long-term antiresorptives
- IM nailing preferred for complete AFF; image and consider prophylactic fixation of contralateral femur; multidisciplinary bone-health pathway
- Evidence level
- Consensus / cohort
- Core guidance on AFF / long-term antiresorptives
- Review bisphosphonate need after 5 years (3 yr for IV zoledronate); reassess fracture risk; consider holiday in lower-risk patients
- Evidence level
- Guideline
- Core guidance on AFF / long-term antiresorptives
- Investigate thigh/groin pain in long-term users with full-length femoral imaging; stop antiresorptive if AFF confirmed
- Evidence level
- Guideline
The dominant data come from integrated-care cohorts (Kaiser Permanente) and national registries (Sweden) rather than arthroplasty-style implant registries, because AFF is a pharmacovigilance rather than a device outcome. These consistently show the same message: net benefit of treatment is large in lower-risk (often White) populations and attenuated, though usually still favourable, in Asian patients.
Concern about AFF has been associated with a substantial fall in bisphosphonate prescribing and a possible rise in hip-fracture incidence in some health systems (Black 2020). Drug-holiday thresholds, the weight given to Asian ethnicity, and the threshold for prophylactic contralateral nailing all vary between centres.
Availability of anabolic therapy (e.g. teriparatide for severe osteoporosis or high fracture risk) varies between health systems and influences the choice of post-fracture agent. In populations where patients of Asian ancestry make up a larger share of those treated, ethnicity-specific counselling on duration and risk-benefit carries particular weight. Fracture liaison services remain central to secondary prevention across all settings.
In the Orthopaedic exam, be prepared to discuss the ASBMR criteria (know all 5 major criteria, with lateral cortex beaking now a MAJOR feature), the importance of full-length imaging of both femora, and the rationale for IM nail fixation. Understand drug-holiday concepts (reassess after 5 yr oral / 3 yr IV) and the role of teriparatide in delayed healing.
MCQ Practice Points
Q: How many of the ASBMR major criteria must be present to diagnose an atypical femoral fracture? A: 4 of 5 major criteria must be present: subtrochanteric/diaphyseal location, transverse or short oblique pattern, minimal/no trauma, non-comminuted or minimal comminution, lateral cortex beaking.
Q: What is the most important risk factor for atypical femoral fractures? A: Duration of bisphosphonate use. The relationship is steep and duration-dependent, not a simple doubling: the adjusted hazard ratio is 8.86 at 3-5 years and 43.51 at 8 or more years versus under 3 months (Black 2020). Risk falls rapidly on stopping (about 70% per year, Schilcher).
Q: What percentage of patients have prodromal symptoms before a complete atypical femoral fracture? A: 70% of patients report thigh or groin pain for weeks to months before the complete fracture. This represents an opportunity for early detection and prophylactic treatment.
Q: What is the preferred fixation for atypical femoral fractures and why? A: Intramedullary nail is preferred because it is load-sharing (protects abnormal bone), protects the entire femur, and allows prophylactic fixation of the contralateral femur. Lateral plate alone is associated with higher failure rates.
Q: What percentage of patients with atypical femoral fracture have bilateral involvement? A: 28% have bilateral involvement. This is why imaging of the contralateral femur is mandatory, and prophylactic fixation should be considered if incomplete fracture is identified.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 72-year-old woman on alendronate for 8 years presents after a fall from standing. X-rays show a transverse subtrochanteric fracture with minimal comminution and lateral cortex thickening. What is your diagnosis and management?”
“A 68-year-old woman on denosumab for 4 years presents with 3 months of left thigh pain. X-rays show localized lateral cortex thickening in the subtrochanteric region with a faint transverse lucency. She can walk with a limp. What is your management?”
“A patient had IM nailing of an atypical femoral fracture 9 months ago. She has persistent thigh pain. X-rays show no callus bridging and a persistent fracture line. What is your approach?”
ASBMR MAJOR CRITERIA (4 of 5 Required)
- 1. Location: Subtrochanteric or femoral shaft
- 2. Pattern: Transverse or short oblique (less than 30 degrees)
- 3. Trauma: Minimal or no trauma
- 4. Comminution: Non-comminuted or minimal
- 5. Lateral cortex: Localized periosteal/endosteal reaction (beaking)
KEY RISK FACTORS
- Bisphosphonate duration greater than 5 years (most important)
- Glucocorticoid use
- Asian ethnicity
- Femoral varus/bowing
- Prior contralateral AFF
SURGICAL MANAGEMENT
- IM nail preferred (load-sharing, protects whole femur)
- Avoid lateral plate alone (stress riser)
- Always image contralateral (28% bilateral)
- Prophylactic nail if incomplete fracture
- Consider bilateral fixation at same sitting
POST-FRACTURE BONE HEALTH
- Stop bisphosphonate (drug holiday)
- Optimize vitamin D (target greater than 50nmol/L)
- Calcium supplementation
- Consider teriparatide if delayed union
- Endocrinology referral
COMPLICATIONS
- Delayed union/nonunion (20-30%)
- Contralateral fracture (28%)
- Refracture
- Prolonged healing time
TRAPS AND PEARLS
- 70% have prodromal thigh pain - investigate!
- Risk-benefit still favors bisphosphonates overall
- Lateral beaking is pathognomonic
- Peritrochanteric fractures are NOT atypical
- Expect longer healing than typical fractures
Evidence Base
Shane et al. ASBMR Task Force Second Report (Defining Classification)
- Revised case definition: 5 major and 4 minor features, with 4 of 5 major features required for diagnosis. The periosteal/endosteal lateral cortex stress reaction was upgraded from a minor to a major feature, and disease/drug associations were removed from the case definition. AFFs are characterised as stress or insufficiency fractures. Absolute risk on bisphosphonates is low (3.2 to 50 per 100,000 person-years), rising to approximately 100 per 100,000 person-years with long-term use.
Black et al. AFF Risk vs Fragility-Fracture Prevention (Kaiser, 196,129 women)
- Adjusted hazard ratio for AFF rose with bisphosphonate duration: 8.86 at 3 to less than 5 years and 43.51 at 8 or more years (versus less than 3 months). Risk fell rapidly after discontinuation. Asian women had higher risk than White women (HR 4.84). After 3 years of treatment in White women, 149 hip fractures were prevented for every 2 bisphosphonate-associated AFFs, versus 91 hip fractures prevented for 8 AFFs in Asian women.
Dell et al. Incidence by Bisphosphonate Duration (Kaiser Southern California)
- In 1.8 million patients, age-adjusted AFF incidence rose from 1.78 per 100,000 person-years at 0.1 to 1.9 years of bisphosphonate exposure to 113.1 per 100,000 person-years at 8 to 9.9 years. Of 142 atypical fractures, 128 had bisphosphonate exposure (mean 5.5 years).
Schilcher, Michaelsson & Aspenberg - Swedish National Registry
- Nationwide cohort: age-adjusted relative risk of AFF with bisphosphonate use was 47.3, but the absolute increase was only 5 cases per 10,000 patient-years. Risk diminished by approximately 70% per year after drug withdrawal.
Lo et al. Race/Ethnicity and AFF Risk (Kaiser Northern California)
- Among 48,390 women starting oral bisphosphonates, AFF rate was 8-fold higher in Asian than White women (64.2 versus 7.6 per 100,000 person-years; age-adjusted HR 8.5, reduced to 6.6 after adjusting for bisphosphonate duration).
Adler et al. ASBMR Long-Term Bisphosphonate / Drug-Holiday Task Force
- After 5 years of oral or 3 years of intravenous bisphosphonate, reassess fracture risk. High-risk patients (low hip T-score, prior fracture, fracture on therapy) may continue to 10 years oral or 6 years IV. For patients no longer at high risk, a drug holiday of 2 to 3 years can be considered. AFF risk clearly rises with treatment duration but is outweighed by vertebral fracture reduction in high-risk patients.
Egol et al. Healing After IM Nailing of Complete AFFs
- In 33 patients (41 complete AFFs, mean 8.8 years of bisphosphonate use) treated with intramedullary nailing, 98% were radiographically healed by 12 months although healing was delayed, particularly when malaligned. Patients reported a mean of 6 months of prodromal pain; 64% returned to baseline function within 1 year.