MTP Extension + PIP/DIP Flexion
- Claw toe: MTP hyperextension + PIP flexion + DIP flexion - all three joints involved.
- Hammer toe: only PIP flexion with neutral MTP and DIP - single joint deformity.
- Intrinsic weakness: Loss of lumbricals/interossei → extrinsic muscles unopposed.
- Flexibility test: Passively correct with MTP flexed - if corrects, intrinsics still work.
- Neurological cause: Always consider CMT, diabetes, spinal cord pathology - bilateral distribution.
- “All 3 joints affected in claw (vs 1 in hammer/mallet)
- “Flex MTP to test flexibility (relaxes extrinsics)
- “Neurological cause in majority (CMT, diabetes)
- “Girdlestone-Taylor = FDL to EDL transfer
- “Rigid needs PIP/DIP fusion, adding a Weil osteotomy for transfer metatarsalgia
Overview and Epidemiology
Claw toe is a triplanar deformity of a lesser toe: the MTP joint hyperextends while both the PIP and DIP joints flex. Hammer toe flexes the PIP alone and mallet toe the DIP alone; claw toe affects all three joints at once. MTP hyperextension is pathognomonic for claw toe and suggests intrinsic muscle dysfunction.
Epidemiology. Claw toes are reported in 2-20% of adults, the figure varying with age, and can occur at any age depending on the cause. There is no significant sex predominance, unlike hammer toe. Between 60 and 80% are bilateral, which suggests a systemic cause, and 80% have an underlying neurological condition or cavus foot.
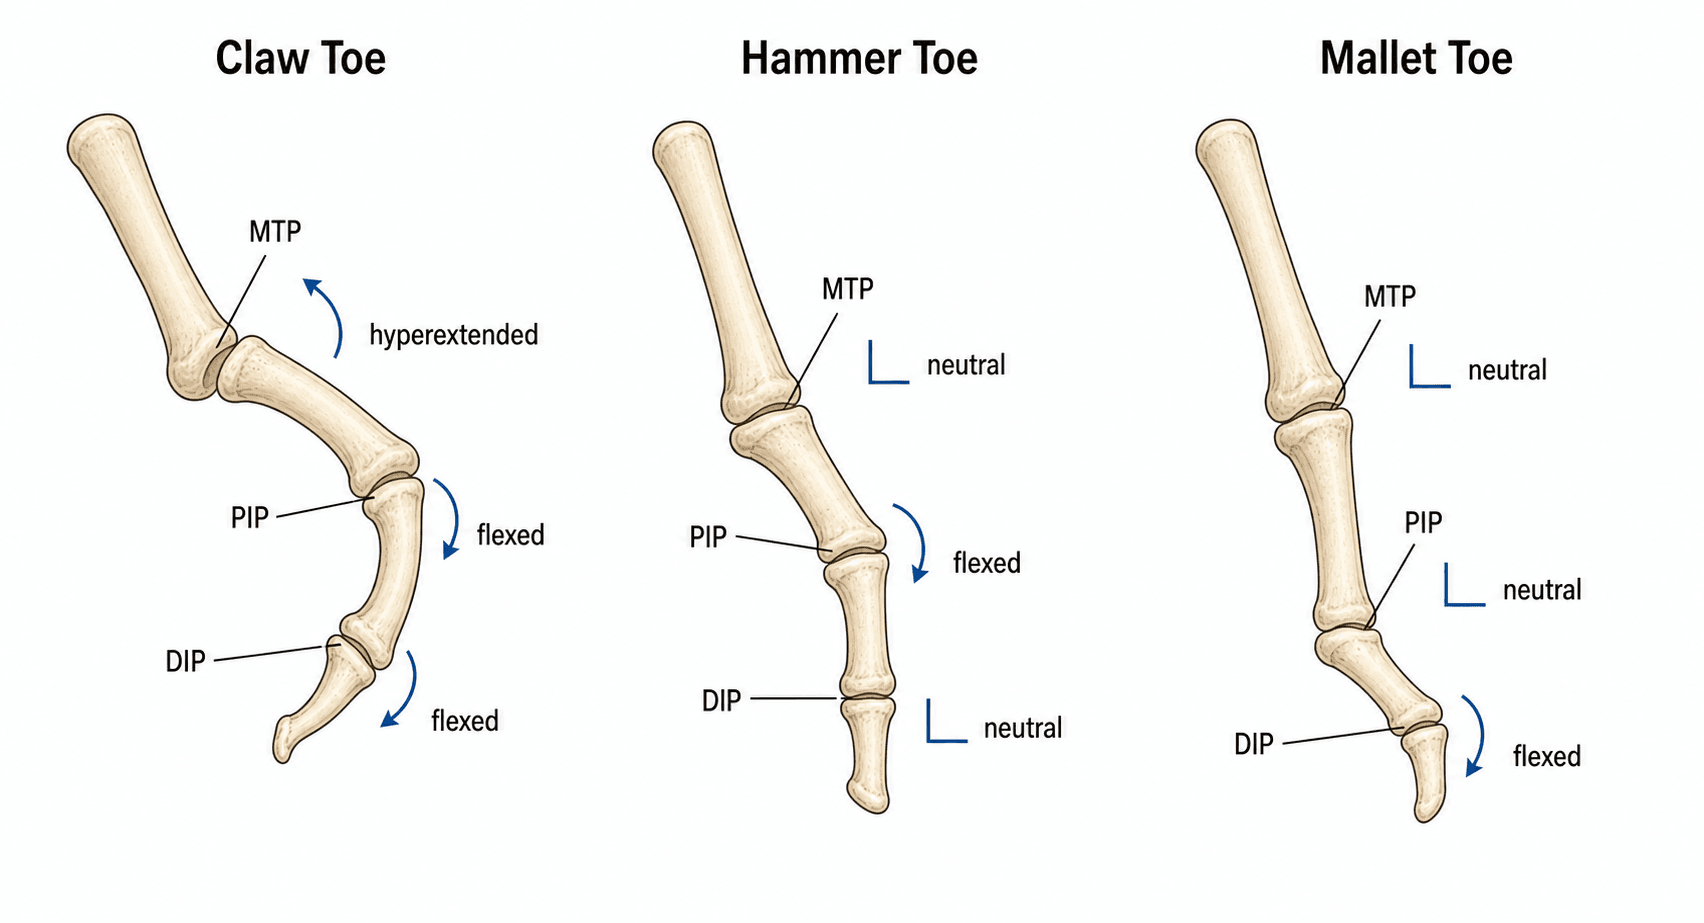
- Claw Toe
- Hyperextended
- Hammer Toe
- Neutral/Extended
- Mallet Toe
- Neutral
- Claw Toe
- Flexed
- Hammer Toe
- Flexed
- Mallet Toe
- Neutral
- Claw Toe
- Flexed
- Hammer Toe
- Neutral/Extended
- Mallet Toe
- Flexed
- Claw Toe
- All 3 joints
- Hammer Toe
- 1 joint (PIP)
- Mallet Toe
- 1 joint (DIP)
- Claw Toe
- Neurological/intrinsic weakness
- Hammer Toe
- Mechanical/footwear
- Mallet Toe
- FDP/long toe
- Claw Toe
- 60-80% (systemic)
- Hammer Toe
- 40% (mechanical)
- Mallet Toe
- 20% (local)
- Claw Toe
- CMT, cavus foot, diabetes
- Hammer Toe
- Hallux valgus, tight shoes
- Mallet Toe
- Long 2nd toe
- Claw Toe
- Flex MTP to test
- Hammer Toe
- Plantarflex ankle to test
- Mallet Toe
- Assess DIP alone
- Claw Toe
- FDL-to-EDL transfer
- Hammer Toe
- FDL tenotomy/transfer
- Mallet Toe
- FDP tenotomy
- Claw Toe
- PIP+DIP fusion + Weil
- Hammer Toe
- PIP arthroplasty/fusion
- Mallet Toe
- DIP fusion
Pathophysiology
The intrinsic muscles. The lumbricals and interossei are the balancing muscles of the lesser toe. Both flex the MTP joint and extend the PIP and DIP joints, and the interossei also abduct and adduct the toes.
- Lumbricals (4) - arise from the FDL tendons and insert into the medial aspect of the extensor hood. The first is supplied by the medial plantar nerve, the second to fourth by the lateral plantar nerve
- Interossei (7: 3 plantar, 4 dorsal) - arise from the metatarsals and insert into the base of the proximal phalanx and the extensor hood. All are supplied by the lateral plantar nerve
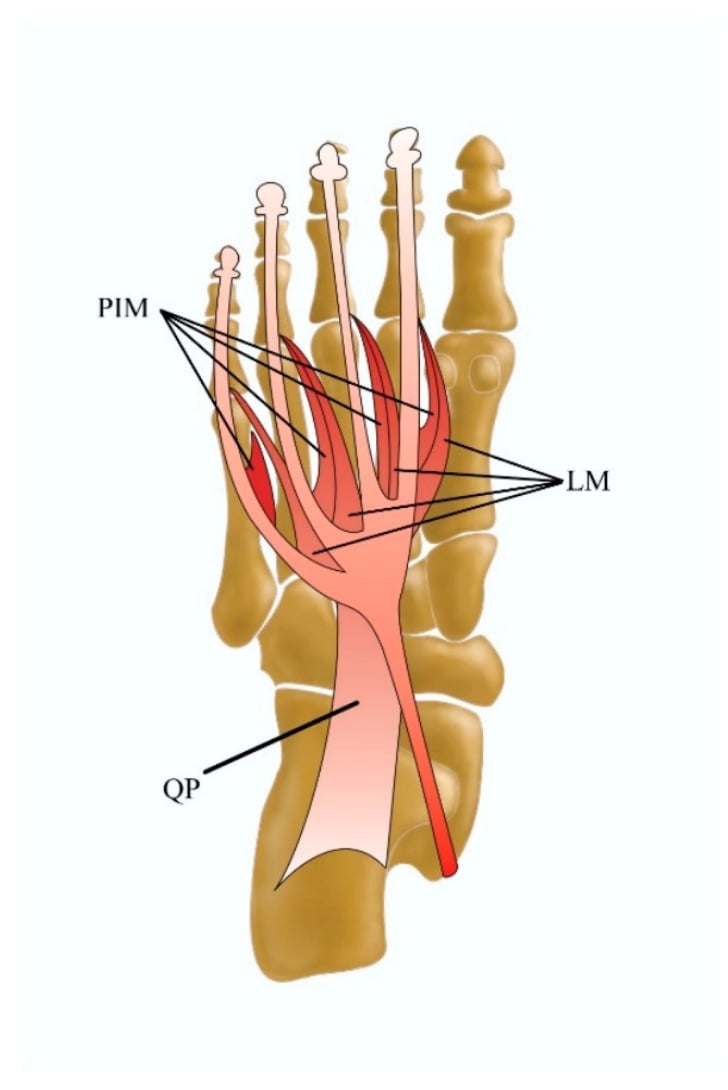
The balance. In the normal toe the intrinsics flex the MTP and extend the IP joints, the extrinsic flexors (FDL and FDB) flex the PIP and DIP, and the extrinsic extensors (EDL and EDB) extend the MTP. Together they hold the toe in a neutral position.
When the intrinsics fail. Weak or paralysed intrinsics leave the extrinsic muscles to dominate:
- EDL unopposed → MTP hyperextension
- FDL and FDB unopposed → PIP and DIP flexion
- Loss of stabilisation → progressive deformity
- Weight-bearing forces drive the MTP into further extension
LIFEIntrinsic Muscle Function - LIFE
Hook:LIFE - Lumbricals and Interossei Flex MTP and Extend IP joints. Loss = claw toe.
Transfer metatarsalgia. MTP hyperextension shifts weight onto the metatarsal heads, and the result is plantar callus and pain.
Causes. Neurological causes are the most common. Neurological claw toes are bilateral and progressive, and the disease affects the intrinsic muscles first.
- Neurological - Charcot-Marie-Tooth disease (CMT), the most common neurological cause; diabetic neuropathy, through a motor component affecting the intrinsics; spinal cord pathology such as syringomyelia or tethered cord; cerebral palsy, with spasticity and muscle imbalance; peripheral nerve injury (sciatic or tibial nerve lesions)
- Biomechanical - cavus foot; gastrocnemius contracture, which increases forefoot loading; a long toe or metatarsal, a mechanical disadvantage; chronic MTP joint instability from plantar plate insufficiency
- Inflammatory - rheumatoid arthritis (synovitis → joint destruction); seronegative arthropathies (psoriatic, reactive arthritis); crystal arthropathies (gout, CPPD), less commonly
- Traumatic - compartment syndrome, with intrinsic muscle necrosis and fibrosis; crush injury
- Iatrogenic - previous forefoot surgery disrupting muscle and tendon balance; overcorrection of flatfoot by excessive plantar fascial release
The cavus foot. Hindfoot varus drives forefoot pronation, peroneus longus overpull plantarflexes the first ray, and the intrinsics are weakened by stretching.
Primary claw toe. When no cause can be identified the deformity is primary (idiopathic). It is often associated with cavus foot and progresses over time. Secondary claw toe is neurological (CMT, diabetes, spinal pathology), inflammatory (RA, seronegative arthritis), traumatic (compartment syndrome, crush injury) or iatrogenic (a post-surgical complication).
Classification and Staging
Flexibility is the classification that matters, because it determines treatment. It is graded on the flexibility test described under examination.
- With the MTP flexed
- Corrects completely
- Findings
- Intrinsics weak but functional; no fixed joint contractures
- Treatment
- Soft-tissue procedures (FDL transfer)
- With the MTP flexed
- Partial correction
- Findings
- Early fixed contractures developing; some intrinsic function preserved
- Treatment
- Soft tissue + limited bone procedure (PIP arthroplasty)
- With the MTP flexed
- No correction
- Findings
- Fixed PIP/DIP contractures; intrinsics absent or fibrosed
- Treatment
- Bone procedures (PIP/DIP arthrodesis)
- With the MTP flexed
- No correction
- Findings
- Rigid deformity plus MTP dislocation; complete plantar plate rupture; severe transfer metatarsalgia
- Treatment
- Arthrodesis + Weil osteotomy
Clinical Presentation
Symptoms. The pain maps onto the deformity:
- Dorsal toe pain - shoe pressure over the PIP and DIP joints
- Plantar forefoot pain - transfer metatarsalgia from MTP hyperextension
- Tip-of-toe pain - DIP callus and ground contact
- Interdigital pain - impingement against the adjacent toe
Function. Patients have difficulty finding comfortable footwear and cannot wear dress or athletic shoes. Walking hurts, especially barefoot; cosmetic concerns and progressive worsening over time complete the history.
Clues to the cause. Ask about weakness or numbness in the feet and legs (neurological), lateral ankle instability and chronic sprains (cavus foot), and morning stiffness with multiple joint involvement (inflammatory).
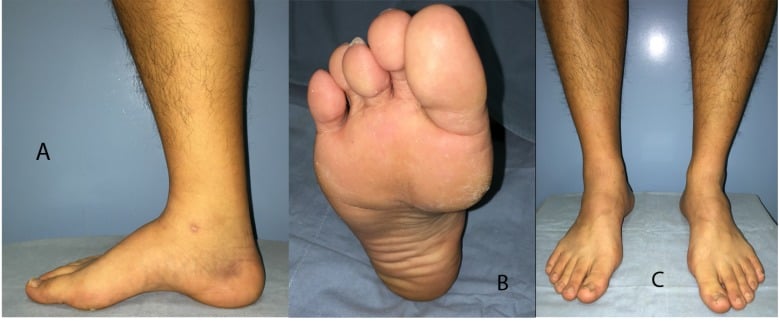
Standing. Observe the toes weight-bearing, the hindfoot alignment (varus suggests cavus) and the height of the medial arch. Look for callus over the dorsal PIP and DIP joints and beneath the metatarsal heads.
The flexibility test. This is the critical examination, because it chooses the operation.
- Passively flex the MTP joint to 90°, which relaxes the extrinsic tendons (FDL and EDL)
- Attempt to passively extend the PIP and DIP joints
- Assess the degree of correction
Complete correction with the MTP flexed means a flexible deformity: the intrinsics are present but weak, and the toe is a candidate for Girdlestone-Taylor transfer. Partial correction means semi-rigid, with an intrinsic contracture developing. No correction means rigid, a fixed contracture with joint changes that needs bone surgery.
The Kelikian push-up test. Examiners ask for it by name. The flexibility test relaxes the extrinsics by flexing the MTP; the push-up test asks a different question by pushing up on the plantar aspect of the metatarsal head to simulate weight-bearing.
- The toe corrects - the deformity is driven by MTP position, and correcting the MTP (soft-tissue release, plantar plate repair, Weil shortening) may straighten the toe without an IP procedure
- The toe stays clawed - there is a fixed IP contracture that must be addressed in its own right
Use both. Flexing the MTP tells you whether the extrinsics are the problem; pushing up the metatarsal head tells you whether the MTP is. They can disagree, and when they do the disagreement is the operative plan: a toe that corrects on push-up but not on MTP flexion needs the metatarsal addressed, not the toe.
The MTP joint. The drawer test displaces the proximal phalanx dorsally, and a positive test indicates plantar plate insufficiency. Check the MTP range of motion (extension is often limited by the capsule) and palpate for synovitis and tenderness.
Neurovascular examination.
- Sensation - light touch, two-point discrimination
- Motor - intrinsic strength (toe spread, toe grip)
- Reflexes - ankle jerk, plantar response
- Gait - high-stepping (foot drop), lateral instability
- Pulses - dorsalis pedis, posterior tibial
Associated deformities.
- Cavus foot - Coleman block test for hindfoot flexibility
- Hallux valgus - often coexists with lesser-toe pathology
- Ankle instability - chronic lateral ligament laxity
- Gastrocnemius contracture - Silfverskiöld test
Investigations
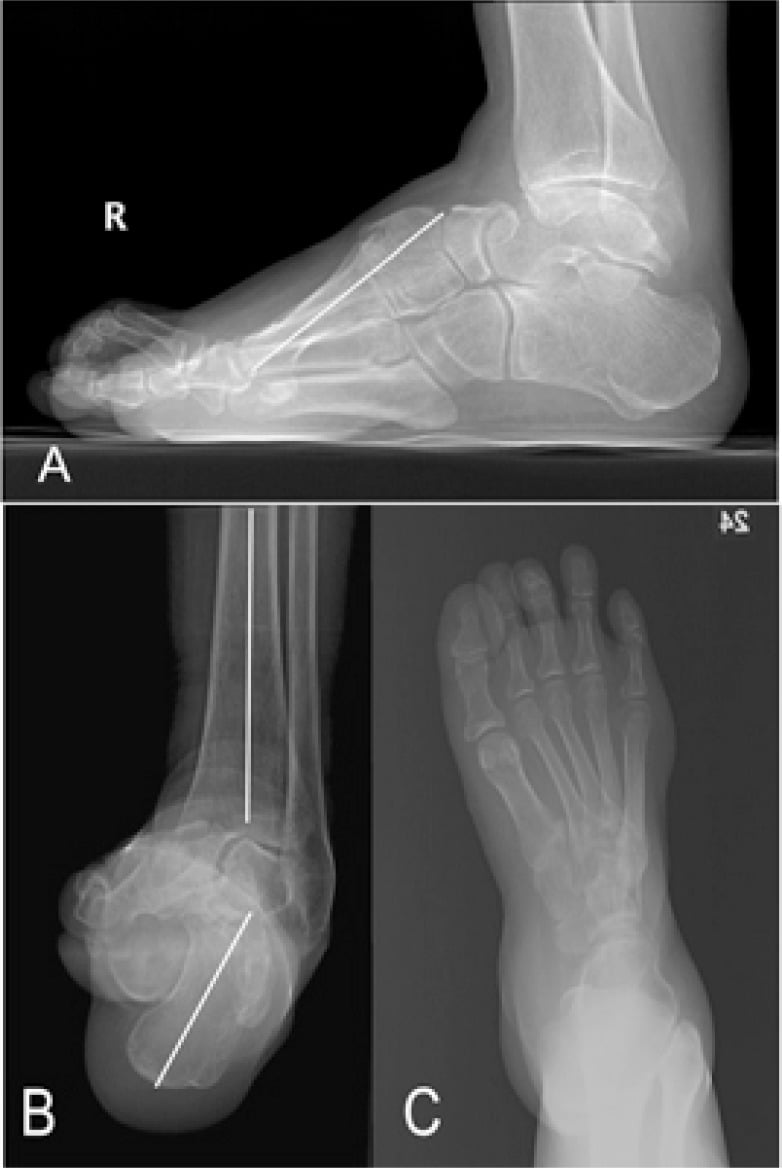
Radiographs. Weight-bearing views of the foot:
- AP - MTP joint alignment, metatarsal declination angle, joint space, erosive changes (inflammatory arthritis), metatarsal length pattern
- Lateral - MTP hyperextension angle, PIP and DIP flexion angles, calcaneal pitch (cavus assessment), metatarsal declination, forefoot-hindfoot relationship
- Oblique - MTP joint congruity, PIP and DIP joint anatomy, osteophyte formation
Always obtain weight-bearing radiographs. Non-weight-bearing images miss the true extent of MTP hyperextension and underestimate the deformity severity.
Measurements. A claw toe shows increased PIP and DIP flexion angles and plantar subluxation of the proximal phalanx, and the angles below separate normal from abnormal:
- Normal
- 0-10° extension
- Claw toe
- Hyperextension over 20°
- Normal
- 20-30°
- Claw toe
- Over 30° if cavus
- Normal
- 15-25°
- Claw toe
- -
Neurological work-up. Bilateral or progressive claw toes are investigated for a cause:
- EMG/NCS - identifies a peripheral neuropathy pattern
- MRI spine - if upper motor neuron signs are present
- Genetic testing - CMT panel if there is a family history
- HbA1c - screens for diabetes
- Vitamin B12 - deficiency neuropathy
Inflammatory work-up. If inflammatory arthritis is suspected: ESR and CRP, rheumatoid factor and anti-CCP, HLA-B27 for a seronegative arthropathy, and uric acid for gout.
Management
Non-operative care. It controls symptoms but does not correct the deformity; progressive worsening is expected and surgery is often eventually required. It suits:
- Mild, asymptomatic deformity
- A flexible deformity with minimal symptoms
- A patient medically unfit for surgery
- Patient preference after counselling
Non-operative options.
- Footwear - wide, deep toe box; soft uppers to reduce pressure; cushioned insoles; custom shoes if the deformity is severe
- Orthoses - night-time toe-straightening splints; metatarsal pads to offload the metatarsal heads; custom insoles for cavus foot correction; crest pads to support the PIP joint
- Symptomatic treatment - callus debridement (podiatry); corn pads and toe sleeves; NSAIDs for inflammatory pain; physiotherapy for intrinsic strengthening
Treat the cause. Optimise diabetic control, treat rheumatoid arthritis, manage the neurological condition, and follow a gastrocnemius stretching protocol.
Absolute indications for surgery.
- Intractable pain despite conservative measures
- Skin breakdown or ulceration
- Functional limitation affecting quality of life
- Progressive deformity with a risk of skin compromise
Relative indications.
- Cosmetic concerns (patient-driven)
- Difficulty with footwear
- Recurrent callus formation
- Mild pain with activity
Patient selection. The patient should be medically fit for surgery, with realistic expectations, able to comply with postoperative restrictions, and with an adequate vascular supply and no active infection. The flexibility grade then chooses the operation.
Surgical Techniques
Girdlestone-Taylor Procedure (FDL-to-EDL Transfer)
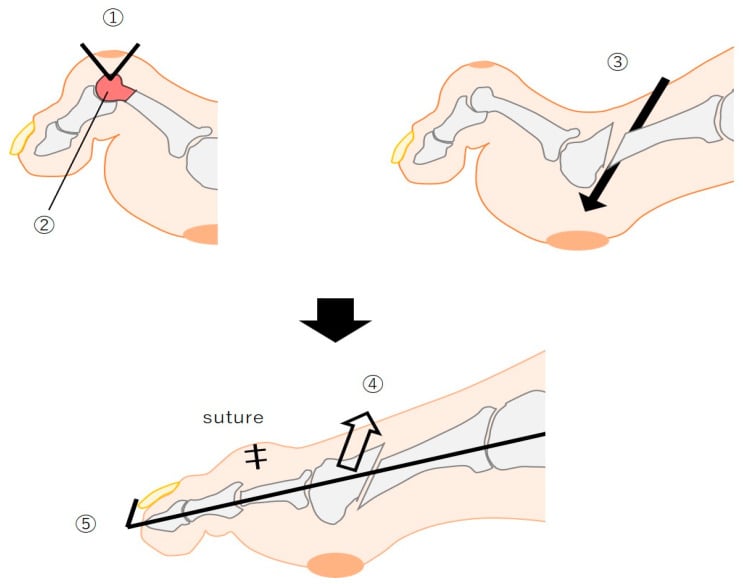
Principle. The transfer converts the extrinsic flexor, FDL, into an extensor and restores the balance the intrinsics have lost: the MTP is held out of hyperextension and the IP joints extend.
Indications. A flexible claw toe that corrects with the MTP flexed, with preserved intrinsic function (weak but present), no fixed PIP or DIP contracture and no significant MTP joint pathology.
Set-up. Supine, with a thigh tourniquet and the foot in neutral.
Steps.
- FDL harvest - plantar incision at the base of the toe; identify and isolate FDL, transect it distally and retrieve it proximally into the wound
- Dorsal approach - longitudinal dorsal incision over the PIP joint; identify EDL and the extensor hood and split the hood longitudinally
- Transfer - pass FDL through the interosseous space plantar to the deep transverse metatarsal ligament, bring it dorsal to the proximal phalanx and weave it into EDL or the extensor hood, tensioned to hold the toe in neutral with the ankle at 90°
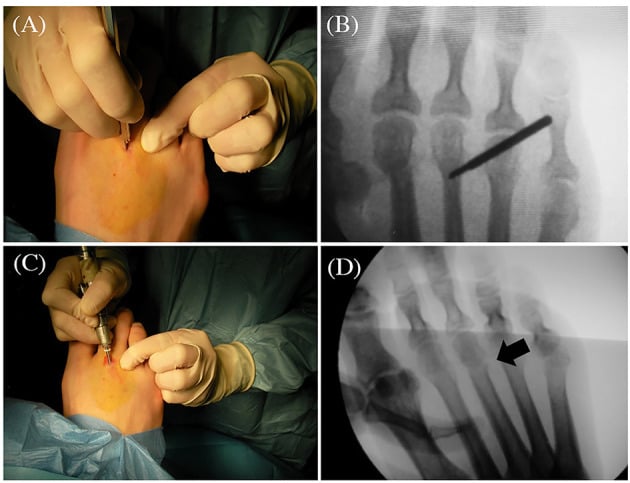
- Additional procedures if needed - MTP capsulotomy for an MTP extension contracture, PIP capsulotomy for a mild PIP flexion contracture, and optional temporary K-wire stabilisation
- Closure - extensor hood with absorbable sutures, skin with non-absorbable sutures, compression dressing with the toe in neutral
Aftercare. A stiff-soled shoe or walking boot for 4-6 weeks, weight-bearing as tolerated, with toe taping to maintain the correction. Sutures come out at 2 weeks and active range-of-motion exercises start at 4 weeks.
Results. Good to excellent results in 80-90%, patient satisfaction in 80-90%, pain relief in 85-95% and correction maintained in 75-85%. The complications are floating toe (10-15%) and recurrence (5-10%); the Boyer and DeOrio series in the Evidence Base, using a modified technique, reported no floating toes.
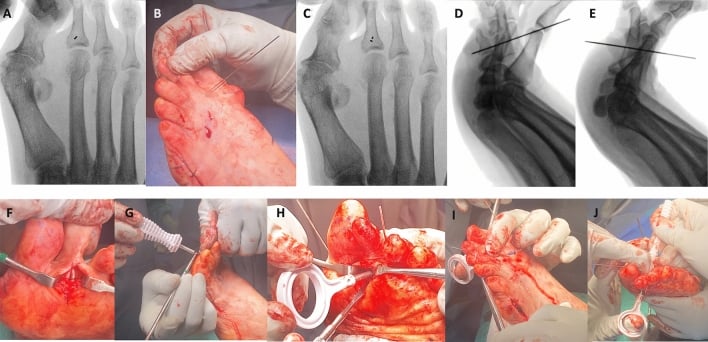
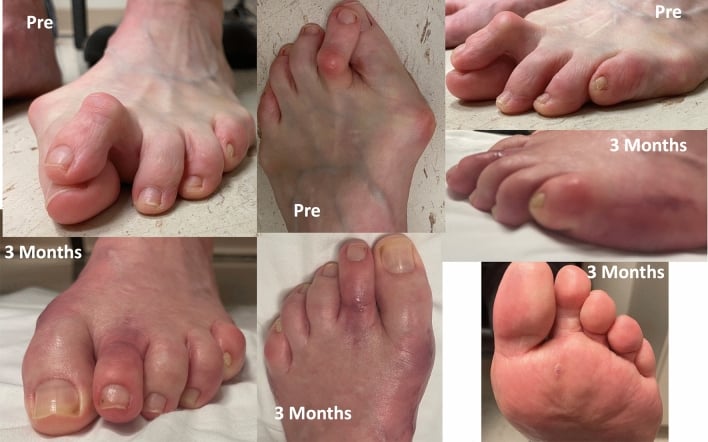
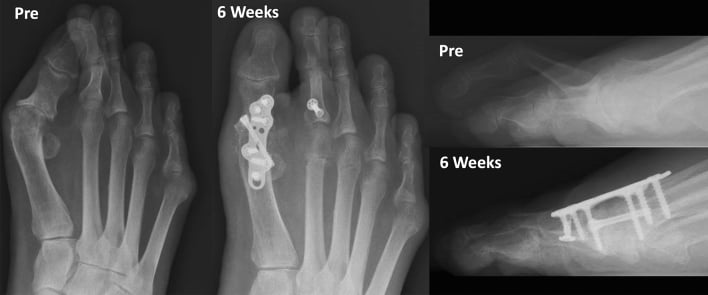
Complications
Intraoperative
Neurovascular injury. Digital nerves or arteries can be injured during dissection, more commonly in scarred or inflamed tissue. Prevention is careful dissection with identification of the structures; repair primarily if the injury is identified, and observe if it is minor.
Inadequate correction. Residual deformity after the procedure; undercorrection is more common than overcorrection. Prevention is intraoperative assessment and adequate release. Accept mild residual deformity and revise significant deformity.
K-wire problems. Pin migration and breakage, as well as pin-tract infection (below). Prevention is proper technique and pin care.
Early (less than 6 weeks)
Wound complications. Superficial infection in 2-5%, delayed healing in 5-10% and wound breakdown in less than 5%, managed with local wound care, antibiotics and debridement.
Pin-tract infection. Occurs in 5-10% with percutaneous K-wires and presents as erythema and drainage around the pin. Pin care and oral antibiotics treat it, with early removal of the wire if it is severe.
Swelling. Expected, and it can be significant, typically lasting 2-3 months. Elevation, compression and ice manage it.
Late (more than 6 weeks)
Floating toe. The most common complication, in 10-20% after PIP arthroplasty: the toe sits elevated off the ground and lacks purchase. Excessive bone resection or a tight transfer causes it. It is usually asymptomatic but cosmetically concerning; most are observed, and a symptomatic toe is revised to an arthrodesis.
Recurrence. 5-15%, depending on the procedure. It is more common if the underlying cause has not been addressed and more likely after flexible procedures than after arthrodesis. Treat it conservatively first and revise if needed.
Stiffness. Expected, and intended, after arthrodesis. It can affect the adjacent joints and may limit footwear options; shoe modifications and stretching help.
Nonunion and malunion. Nonunion occurs in 5-10% at the PIP and in less than 5% at the DIP; malunion (rotational or angular deformity) in 5%. Smoking, diabetes and poor fixation are the risk factors, and revision arthrodesis is for the symptomatic toe.
Transfer metatarsalgia. Pain under the adjacent metatarsal heads from the altered biomechanics after surgery. Prevention is addressing metatarsal length discrepancies; metatarsal pads, and possibly a Weil osteotomy, treat it.
Vascular compromise. Rare but serious, and more common in smokers, diabetics and patients with peripheral vascular disease; it can lead to toe ischaemia and necrosis. Prevention is careful patient selection and preserving the vascular supply. A viable toe is observed; a necrotic one is amputated.
In diabetic patients, always assess vascular supply before surgery. Transcutaneous oxygen measurement (TcPO2) greater than 30mmHg required for healing. Consider vascular surgery consult if borderline.
Floating Toe: the Commonest Complication
- Why it happens. The toe floats when its plantar-flexing / ground-purchase force at the MTP is lost or overpowered by a dorsal force:
- PIP resection arthroplasty shortens the toe and disrupts the flexor and plantar-plate purchase, so the toe loses the plantarflexion that holds the pulp down.
- An over-tight FDL-to-EDL transfer pulls the toe into too much MTP flexion-correction and dorsiflexion, lifting the tip.
- A Weil osteotomy translates the metatarsal head plantarward and proximally, which shifts the intrinsic (interosseous/lumbrical) tendons dorsal to the MTP axis of rotation - the intrinsics then act as MTP extensors instead of flexors, producing a dorsal contracture and a floating toe (the classic Weil pitfall).
- How to prevent it. Resect minimal bone, tension the transfer so the toe rests plantigrade with the ankle neutral (not over-corrected), preserve or repair the plantar plate, limit Weil shortening and avoid excessive plantar translation, and stabilise the MTP (temporary K-wire) while it heals.
- How to treat a symptomatic floating toe. Most are asymptomatic and observed. A symptomatic one is addressed by flexor tenodesis / FDL transfer to restore plantar pull, plantar plate reefing, MTP capsular release of the dorsal contracture, or, if a Weil has malpositioned the head, a corrective (e.g. more proximal / less plantar) revision.
Q: What is a floating toe and why does a Weil osteotomy cause it? A: A floating toe sits dorsiflexed off the ground with no pulp purchase - the commonest complication of lesser-toe surgery. It arises when the toe loses its plantar-flexing force: after PIP resection (loss of flexor/plantar-plate purchase), an over-tight FDL transfer, or a Weil osteotomy - the Weil moves the metatarsal head plantar/proximal so the intrinsic tendons pass dorsal to the MTP axis and act as extensors rather than flexors. Prevent it by minimal resection, correct transfer tension, plantar-plate preservation and limited Weil shortening; treat a symptomatic one with flexor tenodesis, plantar-plate reefing, dorsal release or Weil revision.
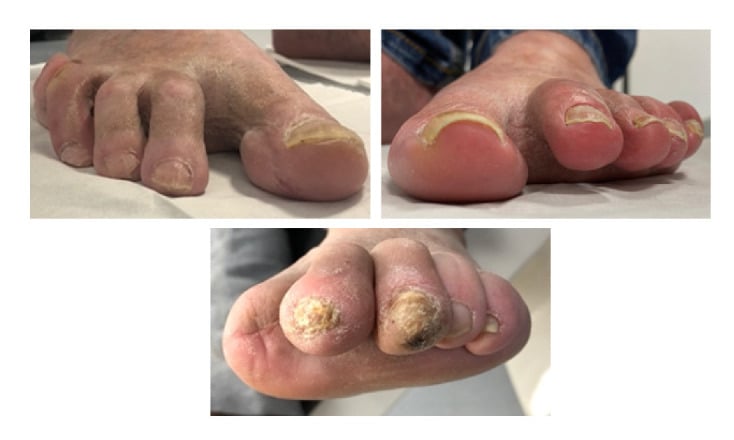
Percutaneous Flexor Tenotomy for the Flexible (Diabetic) Claw Toe
- The indication. A flexible claw or hammer toe with a tip-of-toe (apex) ulcer or impending ulcer, classically in a diabetic neuropathic (or neuroischaemic) foot - the setting where a formal open reconstruction or arthrodesis carries unacceptable wound and vascular risk.
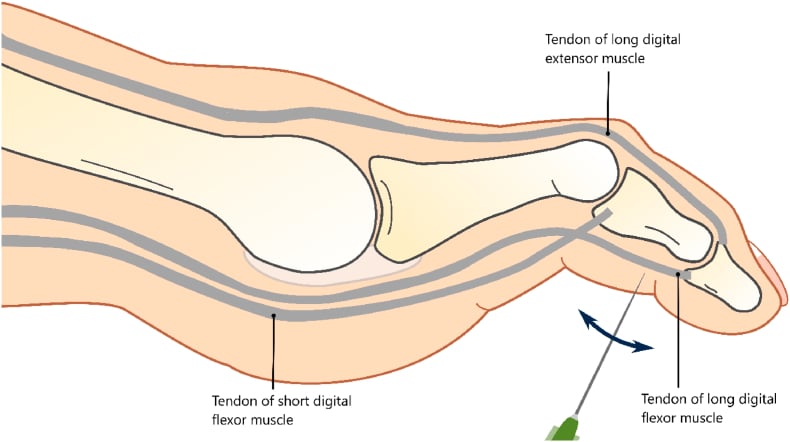
- The procedure. A percutaneous stab on the plantar surface just proximal to the flexion crease divides the FDL and FDB tendons; the flexible toe then straightens and the tip lifts off the ground, offloading the apex. It is done under local anaesthetic, needs no fixation, and the incision heals by itself.
- Why it works and its evidence. Releasing the deforming flexor pull lets the neuropathic toe sit plantigrade so the ulcer offloads and heals (Rasmussen: 93% healed, median 21 days, no infections or amputations), and prophylactic tenotomy of an at-risk toe prevents ulceration. It is explicitly a limb-sparing alternative to amputation in the poorly-vascularised foot.
- The limits. It only works while the toe is flexible - a rigid contracture will not correct with tenotomy alone and needs PIP arthrodesis (or resection) as elsewhere in this topic; and dividing the flexors can leave a small floating-toe tendency, usually well tolerated in this population.
Q: A diabetic has a flexible claw toe with a tip ulcer and poor vasculature - what is the least invasive surgical option? A: A percutaneous flexor tenotomy - a plantar stab just proximal to the flexion crease divides FDL and FDB, letting the flexible toe straighten and lifting the tip so the apex ulcer offloads and heals (Rasmussen: 93% healed, median 21 days, no infections/amputations; also prevents ulceration prophylactically). It needs only local anaesthetic and no fixation, making it a limb-sparing alternative to amputation. It works only while the toe is flexible - a rigid toe needs arthrodesis.
Postoperative Care and Rehabilitation
Weeks 0-2. Keep the compression dressing clean and dry, elevate the foot above heart level to reduce swelling, and weight-bear as tolerated in a stiff-soled shoe or boot. Ice for 20 minutes every 2-3 hours, give oral analgesics as needed, and clean any K-wire daily with an alcohol wipe.
First review at 10-14 days. Remove the sutures, assess wound healing and check the alignment for rotation. Change to a lighter dressing or toe sleeve and continue weight-bearing in the protective shoe.
Weeks 2-6. Protected weight-bearing continues with any K-wire left in place. Buddy-tape the toe to its neighbour, start gentle passive motion of the unfused joints, control swelling with compression and elevation, and watch for pin-tract infection.
Review at 6 weeks. The K-wire comes out in the office under local anaesthetic and radiographs assess alignment and early fusion. The patient moves into a regular supportive shoe and begins active motion, with a physiotherapy referral if the toe is stiff.
Weeks 6-12. Progress weight-bearing to normal, with active and passive motion, intrinsic strengthening exercises and scar massage. Return to regular activities gradually, and assess shoe fitting.
Review at 12 weeks. Final radiographs confirm fusion, the functional outcome is assessed, residual swelling or stiffness is addressed, and the patient is cleared for full activities if healed.
3-12 months. Swelling may persist for 3-6 months, and numbness around the surgical site gradually improves. Modify shoes as needed, monitor for recurrence or adjacent toe deformity, and review annually if there is a neurological condition.
Prevention and Prognosis
Primary prevention in at-risk groups.
- Neurological conditions (CMT, diabetes) - regular foot examinations, early intrinsic strengthening, custom orthotics for cavus foot, proper diabetic foot care and optimised glucose control
- Cavus foot - early identification and treatment, lateral column lengthening if progressive, a gastrocnemius stretching programme and appropriate footwear
- Inflammatory arthritis - DMARD therapy to control disease, early soft-tissue procedures if deformity is developing, and regular rheumatology and podiatry follow-up
Preventing recurrence after surgery. Address the underlying neurological or biomechanical cause, keep to proper footwear long term, continue intrinsic strengthening, and monitor the adjacent toes, with revision surgery if the deformity recurs.
Prognosis. Young age, a single toe, a flexible deformity and no systemic disease are favourable. A progressive neurological condition, multiple toes, rigid deformity, diabetes and smoking are unfavourable.
The long view. Patients with a progressive neurological condition are likely to develop deformities of the adjacent toes, and a cavus foot carries a high recurrence risk if it is not addressed. The isolated idiopathic claw toe has good long-term outcomes with appropriate surgery.
Guidelines, Registries & Global Practice
Global Epidemiology
- Diabetes burden: ~537 million adults live with diabetes worldwide (IDF, 2021); distal symmetrical polyneuropathy develops in roughly 30-50% over time and is a leading driver of acquired claw toe and plantar pressure redistribution.
- Charcot-Marie-Tooth disease: prevalence ~1 in 2,500 globally - the commonest inherited neuropathy and the classic cause of bilateral, progressive claw toes with cavovarus feet.
- Lesser-toe deformity: prevalence rises steeply with age; population foot studies report clawing/hammering in a substantial minority of older adults, more in women (footwear and hallux valgus association) but with no sex bias in neurological claw toe.
- Resource-setting variation: in high-resource settings deformity is often elective/cosmetic-driven; in limited-resource settings the same deformity more often presents late with ulceration, infection or osteomyelitis because of delayed access and barefoot/ill-fitting footwear.
Side-by-Side Guidance
- Focus
- Diabetic foot
- Key recommendation
- Annual risk stratification; offload high-pressure deformities; flexor tenotomy for ulcerating/at-risk flexible claw toes
- Focus
- Diabetic foot, foot surgery
- Key recommendation
- Multidisciplinary foot service for active ulcers; correct deformity to remove pressure source rather than repeated debridement alone
- Focus
- Lesser-toe deformity
- Key recommendation
- Match procedure to flexibility - soft-tissue balancing for flexible, arthrodesis for rigid; address forefoot/MTPJ driver
- Focus
- Fixation principles
- Key recommendation
- Stable IP arthrodesis (K-wire or intramedullary implant); preserve digital vascularity
- Focus
- Neurological foot
- Key recommendation
- Treat claw toes as part of global cavovarus correction, not in isolation, to limit recurrence
There is no implant registry specific to lesser-toe surgery; outcome data derive from case series (see Evidence Base) rather than national arthroplasty registries such as NJR/AJRR/AOANJRR. Intramedullary IP fusion implants are tracked only through device-surveillance schemes, not joint registries.
Practice Variation
- High-resource: day-case surgery, intramedullary headless implants, MRI-confirmed plantar plate repair, formal gait/neuromuscular work-up.
- Limited-resource: emphasis on footwear, callus care and simple K-wire arthrodesis or percutaneous flexor tenotomy; earlier resort to amputation when ulceration is neglected or vascular supply is poor.
Controversies and Areas of Uncertainty
- Arthroplasty vs arthrodesis for rigid PIP deformity: arthrodesis gives more reliable alignment and lower recurrence but at the cost of a stiff toe and a small nonunion rate; resection arthroplasty is quicker and easier to revise but has a higher floating-toe and recurrence rate. Robust comparative (Level I) data are lacking.
- K-wire vs intramedullary implant for IP fusion: newer buried intramedullary devices avoid pin-tract infection and external wires, but high-quality evidence of superior fusion or function over the cheap, familiar K-wire remains limited, and implants add cost.
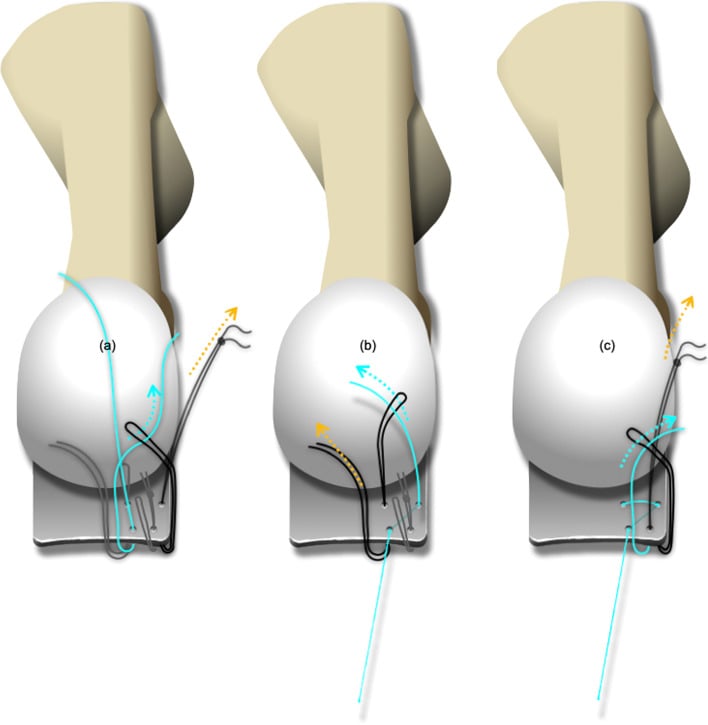
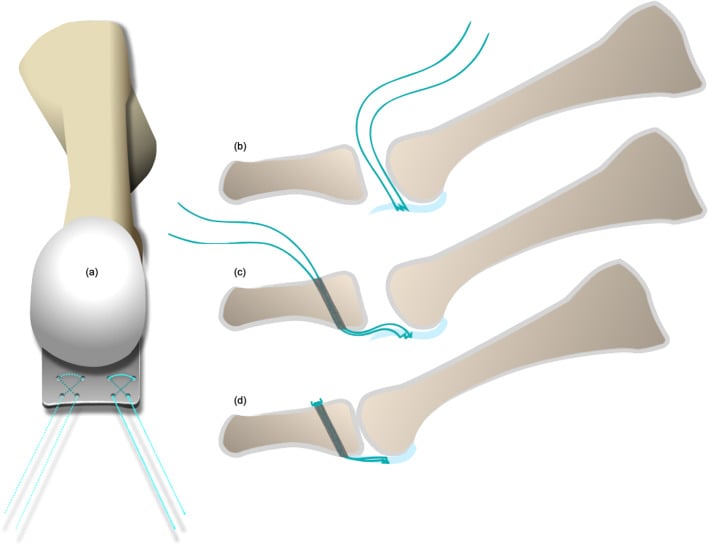
- Does the plantar plate always need formal repair? For MTPJ instability driving a claw/crossover toe, some advocate anatomic dorsal plantar plate repair with Weil osteotomy, while others argue a Weil osteotomy plus flexor transfer alone restores enough stability - the marginal benefit of suturing an often-attenuated plate is debated.
- Prophylactic surgery in the neuropathic foot: percutaneous flexor tenotomy can heal and prevent tip-of-toe ulcers, but how widely to apply prophylactic tenotomy in asymptomatic at-risk diabetic claw toes is unsettled.
- Extent of cavus correction: how aggressively to correct the hindfoot at the index operation (osteotomy/tendon transfer) versus staging it remains a judgement call, balanced against recurrence risk if the cavus driver is left untreated.
MCQ Practice Points
Q: What distinguishes a claw toe from a hammer toe?
A: Claw toe = MTP hyperextension + PIP flexion + DIP flexion (ALL 3 joints involved) Hammer toe = PIP flexion only (MTP and DIP neutral/extended)
This is the most commonly tested distinction. Claw toe involves intrinsic weakness with extrinsic dominance, affecting all three joints. Hammer toe is mechanical, primarily affecting PIP.
Q: How do you perform the flexibility test for claw toe, and what does it determine?
A: Passively flex the MTP joint to 90° (relaxes extrinsic tendons), then attempt to extend the PIP/DIP joints.
- Flexible: Toe corrects → intrinsics weak but present → soft tissue surgery (FDL transfer)
- Rigid: No correction → fixed contracture → bone procedures (arthrodesis)
This test directly determines surgical approach.
Q: A patient presents with bilateral claw toes affecting multiple lesser toes. What does this suggest?
A: Systemic or neurological etiology - bilateral involvement in 60-80% of claw toe cases suggests underlying condition. Must investigate for:
- CMT (most common hereditary cause)
- Diabetic neuropathy
- Spinal cord pathology (syrinx, disc)
- Inflammatory arthritis
Always perform full neurological examination when bilateral.
Q: What is the most common complication after PIP arthroplasty for claw toe?
A: Floating toe (10-20%) - toe sits elevated and doesn't touch ground. Occurs due to disruption of flexor mechanism and scarring. Other complications: recurrence (5-15%), nonunion (5-10% after arthrodesis), pin tract infection (5-10%).
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 32-year-old woman presents with bilateral claw toe deformities affecting 2nd and 3rd toes. She reports increasing pain over the past 2 years, difficulty with footwear, and her father had similar foot problems. On examination, she has cavus foot deformity bilaterally, and the claw toes are flexible when you flex the MTP joints. There is no MTPJ instability.”
“A 58-year-old man with type 2 diabetes presents with rigid claw toe deformity of the 2nd toe. He has a 1cm ulcer over the PIP joint that has been present for 3 months despite conservative care. The toe is rigid with no correction when you flex the MTP joint. He has palpable pedal pulses, and sensation is reduced in a stocking distribution. HbA1c is 8.2%.”
“A 45-year-old woman had hammer toe surgery (PIP arthroplasty) on her 2nd toe 2 years ago. She now has recurrent deformity, but it now appears as a claw toe with MTP hyperextension. Additionally, her 3rd and 4th toes have developed claw deformities. She has high arched feet. Previous surgery notes indicate isolated PIP arthroplasty was performed without addressing forefoot or hindfoot.”
“A 52-year-old woman presents with painful 2nd toe claw deformity. The toe crosses slightly over the hallux. She has bunion deformity. On examination, the 2nd toe has MTP hyperextension, but when you perform a drawer test, the toe subluxes dorsally very easily. The PIP flexion deformity is semi-rigid. No other toes are affected, and her hindfoot is normal.”
Definition - All 3 Joints
- MTP: Hyperextension (dorsiflexed)
- PIP: Flexion (plantarflexed)
- DIP: Flexion (plantarflexed)
- vs Hammer (PIP only) vs Mallet (DIP only)
Pathophysiology
- Intrinsic weakness (lumbricals, interossei)
- Extrinsics unopposed: EDL→MTP extension, FDL→IP flexion
- Normal: intrinsics flex MTP, extend IP
- Loss of balance = claw deformity
Etiology - Think Neurological
- CMT (most common neurological)
- Diabetic neuropathy (motor)
- Cavus foot (intrinsic stretch)
- Spinal cord (syringomyelia)
- Inflammatory (RA)
Flexibility Test - CRITICAL
- Flex MTP to 90° (relaxes extrinsics)
- Attempt to extend PIP/DIP
- Flexible = corrects (intrinsics weak but present)
- Rigid = fixed (intrinsics absent)
- Determines surgery type
Examination Sequence
- 1. Standing: Cavus, calluses, adjacent toes
- 2. Flexibility: Flex MTP, assess correction
- 3. MTPJ: Drawer test (plantar plate)
- 4. Neurovascular: Sensation, strength, pulses
- 5. Coleman block: Hindfoot flexibility if cavus
Imaging
- Weight-bearing AP/Lat/Oblique foot
- MTP hyperextension angle (over 20 degrees abnormal)
- Calcaneal pitch (over 30 degrees = cavus)
- EMG/NCS if neurological suspected
Surgical Decision
- Flexible: FDL-to-EDL transfer (Girdlestone-Taylor)
- Semi-rigid: Transfer + PIP arthroplasty
- Rigid: PIP+DIP arthrodesis
- Transfer metatarsalgia: Add Weil osteotomy
- Cavus foot: MUST address to prevent recurrence
Girdlestone-Taylor
- Converts FDL (flexor) to extensor
- Harvest FDL plantarly, route dorsal
- Weave into EDL/extensor hood
- Restores MTP flexion, IP extension
- 80-90% good results if flexible
Arthrodesis Technique
- Resect PIP joint surfaces (congruent)
- Resect DIP joint surfaces
- K-wire fixation 6 weeks
- If metatarsalgia: Weil (shorten MT 3-5mm)
- Fusion rate 85-95%
Complications
- Floating toe (10-20%) - most common
- Recurrence (5-15%, higher in CMT)
- Nonunion (5-10%)
- Pin infection (5-10%)
- Transfer metatarsalgia if not addressed
Key Numbers
- Bilateral: 60-80% (systemic cause)
- CMT: 60-80% develop by age 40
- Flexible surgery: 80-90% pain relief
- Rigid fusion: 85-95% fusion rate
- Recurrence in CMT: 15-20%
Viva Red Flags
- Don't miss bilateral = neurological cause
- Don't treat toe without addressing cavus
- Don't do soft tissue on rigid toe
- Don't forget diabetic vascular assessment
- Don't ignore hallux valgus driving crossover
Evidence Base
Statistics, sample sizes and conclusions below reflect the source papers, not idealised figures.
Flexor-to-Extensor (Girdlestone-Taylor) Transfer for Lesser-Toe Deformity
- Retrospective review of 38 patients (79 toes, 46 feet), mean follow-up 33 months
- 89% of toes - patients satisfied and would undergo the procedure again
- Modified flexor-to-extensor technique produced few complications and NO floating toes
- Supports FDL transfer as the workhorse for flexible lesser-toe deformity
FDL Transfer for Second MTPJ Instability and Crossover Toe
- 64 feet (59 patients), crossover second-toe deformity in 87%, mean follow-up 45 months
- Mean AOFAS score 82; toe stable to stress in 78% of feet
- 37% retained a residual MTPJ dorsiflexion contracture and stiffness drove dissatisfaction
- Weil osteotomy added in 45% - tendon transfer alone often insufficient for fixed deformity
Plantar Plate Repair with Weil Osteotomy (Dorsal Approach)
- Prospective series: 97 feet, 138 plantar plate tears repaired dorsally with Weil osteotomy
- 80% good-to-excellent satisfaction at 12 months; mean VAS pain fell 5.4 to 1.5
- Mean AOFAS rose 49 to 81; paper pull-out test passed in 42% pre-op vs 54% post-op
- Anatomic plantar plate restoration is feasible from a dorsal approach with Weil shortening
Rheumatoid Forefoot Reconstruction - Long-Term Follow-up
- Forty-three consecutive patients (58 feet) were operated; after six deaths and five subtotal procedures the study reports 32 patients (47 feet) at a mean six years, with NO PATIENT LOST TO FOLLOW-UP, after first-MTP fusion plus lesser-metatarsal-head resection and PIP arthrodesis for fixed hammer toes
- Lesser-MTP dislocation fell from 70% pre-op to 7% post-op; all first-MTP fusions united
- A stable first ray protected lateral rays from later subluxation
- Demonstrates principle - correct the whole forefoot, not the deformed toe alone
Percutaneous Flexor Tenotomy for Diabetic Toe Ulcers
- 38 diabetic patients, 65 claw/hammer toes treated by percutaneous flexor tenotomy
- 93% of ulcerated toes healed (median 21 days); no infections or amputations
- No toe treated prophylactically went on to ulcerate during follow-up
- Effective even in neuroischaemic ulcers - a minimal, limb-sparing option
Surgical Correction of CMT Cavovarus Foot with Claw Toes
- Stepwise algorithm for severe Charcot-Marie-Tooth cavovarus deformity
- Soft-tissue balancing (split posterior tibial tendon transfer) plus adjunctive bony correction by deformity severity
- Flexible clawed hallux managed with modified Jones; fixed plantarflexed first ray needs dorsal closing-wedge osteotomy
- Lesser claw toes addressed with flexor tenotomy as part of global foot correction
References
-
Coughlin MJ, Mann RA. Lesser toe deformities. J Am Acad Orthop Surg. 2007;15(9):567-576.
-
Myerson MS, Jung HG. The role of toe flexor-to-extensor transfer in correcting metatarsophalangeal joint instability of the second toe. Foot Ankle Int. 2005;26(9):675-679.
-
Nix SE, Vicenzino BT, Collins NJ, Smith MD. Characteristics of foot structure and footwear associated with hallux valgus: a systematic review. Osteoarthritis Cartilage. 2012;20(10):1059-1074.
-
Burns J, Crosbie J, Hunt A, Ouvrier R. The effect of pes cavus on foot pain and plantar pressure. Clin Biomech. 2005;20(9):877-882.
-
Highlander P, VonHerbulis E, Gonzalez A. Complications of the Weil osteotomy. Foot Ankle Spec. 2011;4(3):165-170.
-
Hicks JH. The mechanics of the foot: II. The plantar aponeurosis and the arch. J Anat. 1954;88(1):25-30.
-
Coughlin MJ, Schutt SA, Hirose CB. Metatarsophalangeal joint pathology in crossover second toe deformity. Foot Ankle Int. 2012;33(6):463-470.
-
Barbari SG, Brevig K. Correction of clawtoes by the Girdlestone-Taylor flexor-extensor transfer procedure. Foot Ankle. 1984;5(2):67-73.
-
Caterini R, Farsetti P, Ippolito E. Long-term follow-up of toe flexor-extensor transfer in adolescent and adult patients with pes cavus. Foot Ankle Int. 1994;15(6):295-298.
-
Gallentine JW, DeOrio JK. Removal of the second toe for severe hammertoe deformity in elderly patients. Foot Ankle Int. 2005;26(5):353-358.
-
Hamer AJ, Stanley D, Smith TW. Surgery for curly toe deformity: a double-blind, randomised, prospective trial. J Bone Joint Surg Br. 1993;75(4):662-663.
-
Coughlin MJ, Dorris J, Polk E. Operative repair of the fixed hammertoe deformity. Foot Ankle Int. 2000;21(2):94-104.
-
Wetmore RS, Drennan JC. Long-term results of triple arthrodesis in Charcot-Marie-Tooth disease. J Bone Joint Surg Am. 1989;71(3):417-422.