Tailbone Injury | Coccydynia
- Mechanism: Direct fall onto buttocks (sitting position). Childbirth. Repetitive trauma.
- Diagnosis: Clinical history and examination. X-ray confirms fracture/dislocation.
- Treatment: Conservative in vast majority. Cushion, NSAIDs, PT.
- Coccydynia: Persistent coccygeal pain. May require injections or, rarely, coccygectomy.
- Prognosis: Most resolve in 4-12 weeks. Small subset develop chronic pain.
- “Most coccyx fractures are managed conservatively.
- “5F: Female, Fat, Forty, Fall, Fracture (risk factors for coccyx injury/coccydynia).
- “Dynamic lateral X-ray (Sitting vs Standing) can assess mobility.
- “Coccygectomy is reserved for refractory coccydynia.
Overview and Epidemiology
Coccyx fractures and coccydynia, pain in the coccyx, result from trauma to the tailbone, the terminal segment of the spine.
Who. Coccyx injury is five times more common in women, whose coccyx is shorter and more curved, and the peak age is 40-50 years. The risk factors are obesity, female sex, direct trauma and childbirth.
Mechanism. The most common is a direct fall onto the buttocks in the sitting position. The others:
- Childbirth, where a traumatic delivery can sublux or fracture the coccyx
- Repetitive trauma, such as cycling or rowing
- Idiopathic coccydynia, pain without clear trauma, often postural or degenerative
5F5 F's of Coccydynia
Hook:Risk factors for coccyx problems.
Anatomy and Pathophysiology
The coccyx. The coccyx is three to five fused vertebral segments, articulating with the sacrum at the sacrococcygeal joint. Gluteus maximus, coccygeus, levator ani and the anococcygeal ligament attach to it.
The sacrococcygeal joint. It is a symphysis, a fibrocartilaginous disc between S5 and the first coccygeal segment. It normally allows a small range of passive flexion and extension, roughly 5 to 25 degrees, as the coccyx moves with sitting and defaecation. It commonly ankyloses with age, and the intercoccygeal joints are usually fused.
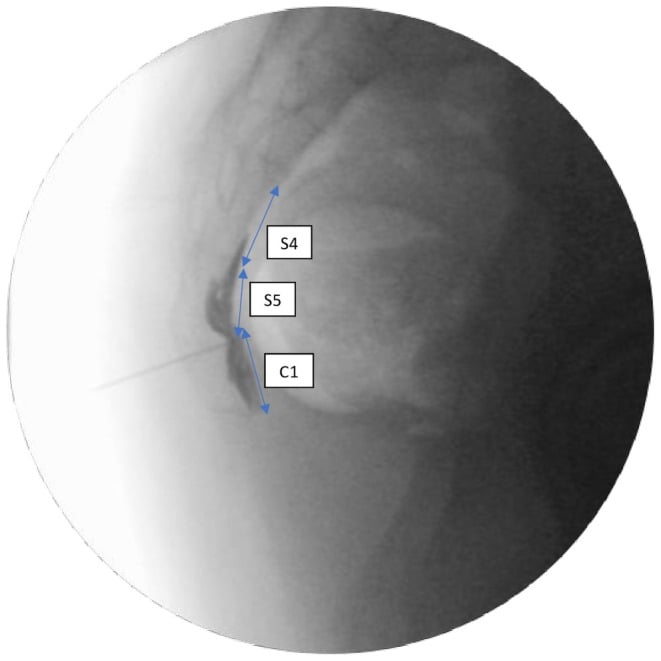
The ganglion impar. The ganglion impar (ganglion of Walther) is the solitary, midline, most caudal ganglion of the sympathetic chain, formed where the two paired paravertebral sympathetic trunks converge and fuse. It lies retroperitoneally, anterior to the sacrococcygeal junction, in front of the coccyx and behind the rectum. It relays sympathetic and nociceptive afferents from the perineum, distal rectum and anus, distal urethra, genitalia and coccyx, which is why it is a target for coccygeal and perineal pain.
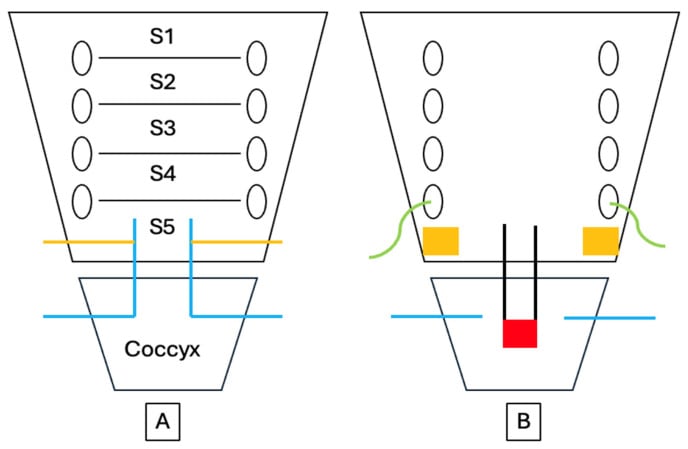
From injury to chronic pain. Direct impact fractures or dislocates the coccyx, and local inflammation brings swelling and pain. Most injuries heal with fibrous union over weeks to months. When the pain persists as chronic coccydynia, the causes are:
- Malunion with abnormal angulation
- Hypermobility or instability at the sacrococcygeal joint
- Degenerative changes
- Referred pain from L5/S1 or the sacroiliac joint
Classification
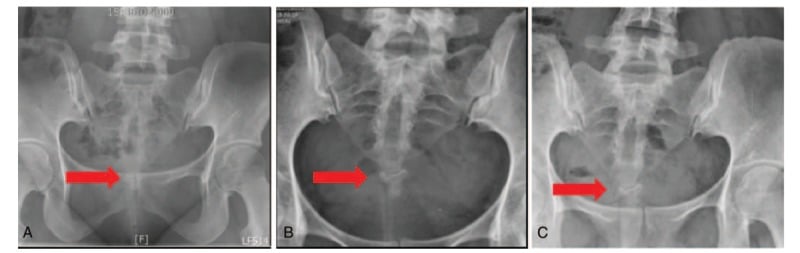
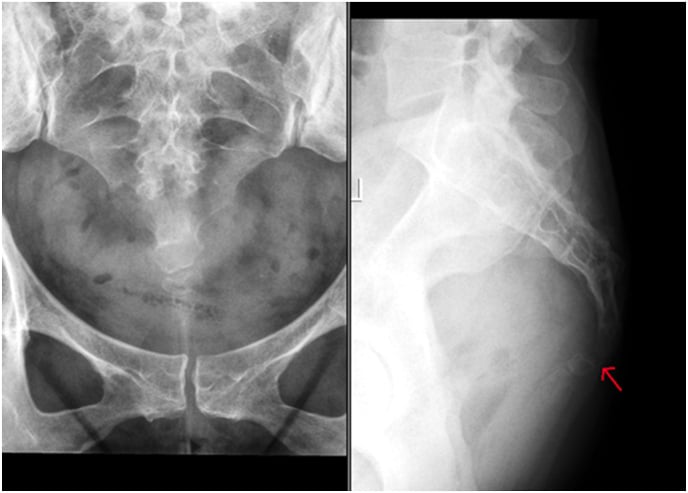
Injury type. A fracture is a break in a coccygeal segment, a dislocation is displacement at the sacrococcygeal or an intercoccygeal joint, and a fracture-dislocation combines the two. The distinction rarely changes management.
Coccydynia. Dynamic X-rays help assign the type:
- Type I, trauma: acute injury, a fracture or dislocation
- Type II, instability: hypermobility greater than 25 degrees on dynamic X-ray
- Type III, rigid spur: fixed anterior angulation, with a spur that causes pain on sitting
- Type IV, subluxation: posterior subluxation of the coccyx
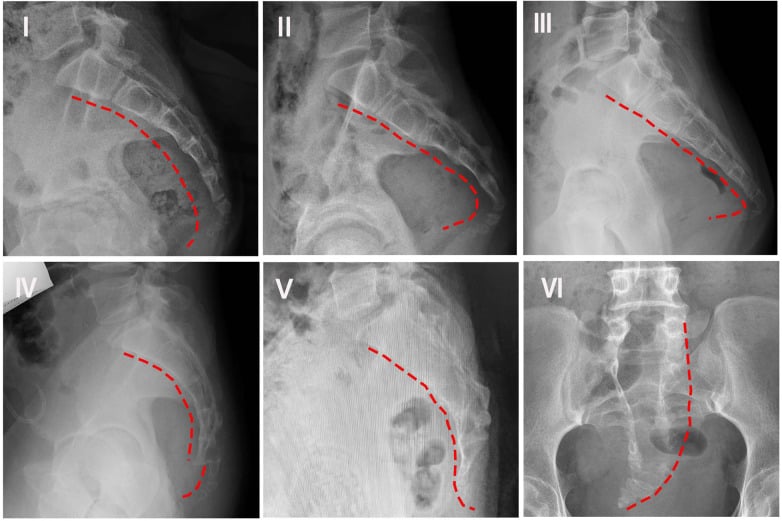
Morphology (Postacchini). On a lateral radiograph the coccyx is classified by its curvature. The forward-angulated and subluxated types, II to IV, are more often associated with coccydynia than type I. This morphology classification is distinct from the Maigne dynamic-radiograph lesion classification.
- Type I curves slightly forward with the apex pointing caudally; it is the commonest and the least symptomatic
- Type II has a more marked forward curve
- Type III is sharply angulated forward
- Type IV is subluxated at the sacrococcygeal or first intercoccygeal joint
Clinical Assessment
History. Establish the mechanism (a fall, childbirth or gradual onset) and whether the pain is acute or chronic. The pain sits at the tailbone, over the sacrococcygeal junction, and is worse with sitting, especially on hard surfaces, with leaning back and with defaecation.
Examination. The findings to seek:
- Inspection: bruising over the sacrococcygeal area
- Palpation: point tenderness over the coccyx externally, and tenderness on bimanual palpation, a rectal or vaginal finger combined with external pressure
- Coccygeal mobility: assessed on rectal examination, noting whether manipulation is painful
- Neurological examination: usually normal, as the coccyx does not contain the cord
- Rectal examination: excludes rectal pathology
Look beyond the coccyx. A fall onto the buttocks can also cause sacral fractures and vertebral compression fractures, so complete the assessment, and rule out a sacral fracture when the trauma was significant.
Investigations
Is imaging needed? The diagnosis is clinical. When the history is clear, a fall and tailbone pain, imaging may not change management and a routine X-ray is often not needed.
When imaging is done. The options:
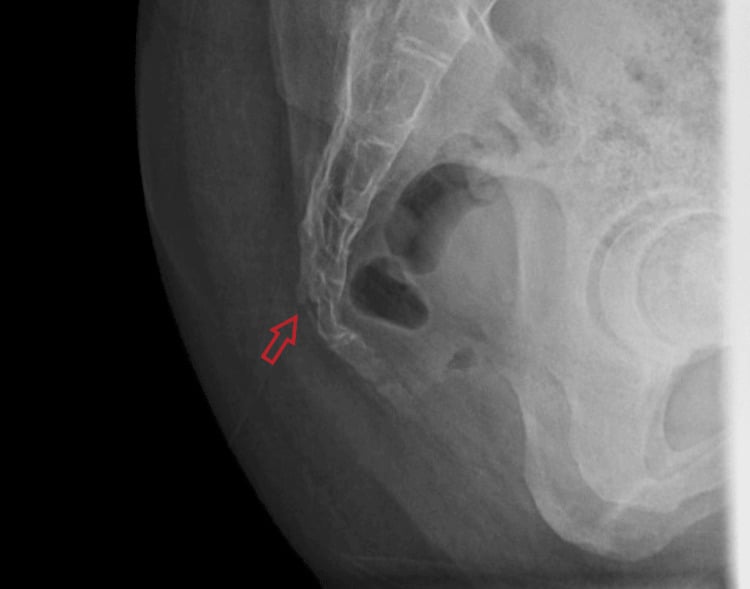
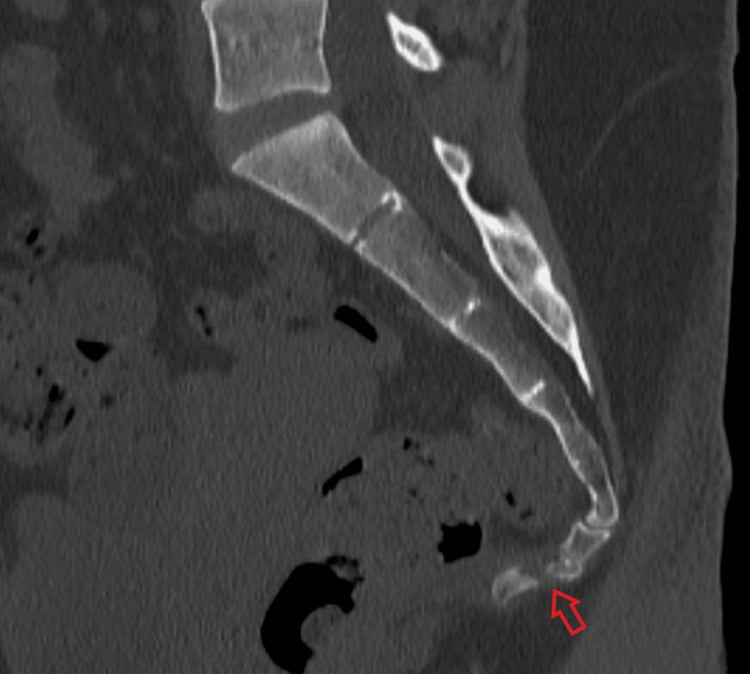
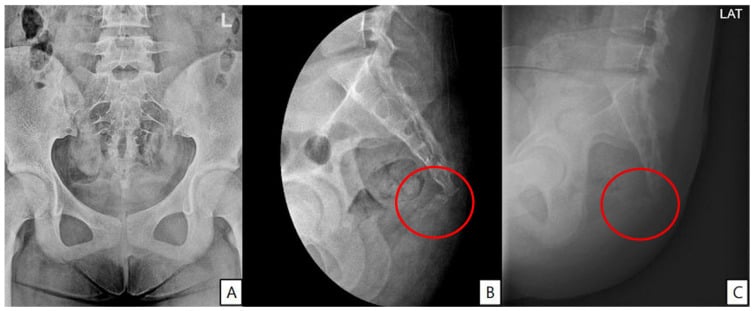
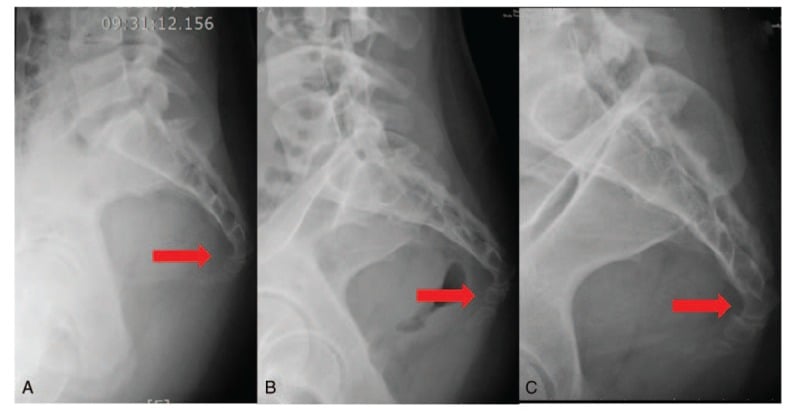
- Lateral coccyx radiograph: shows fracture, dislocation and angulation
- Dynamic lateral radiographs, sitting and standing: assess mobility, with movement greater than 25 degrees indicating hypermobility
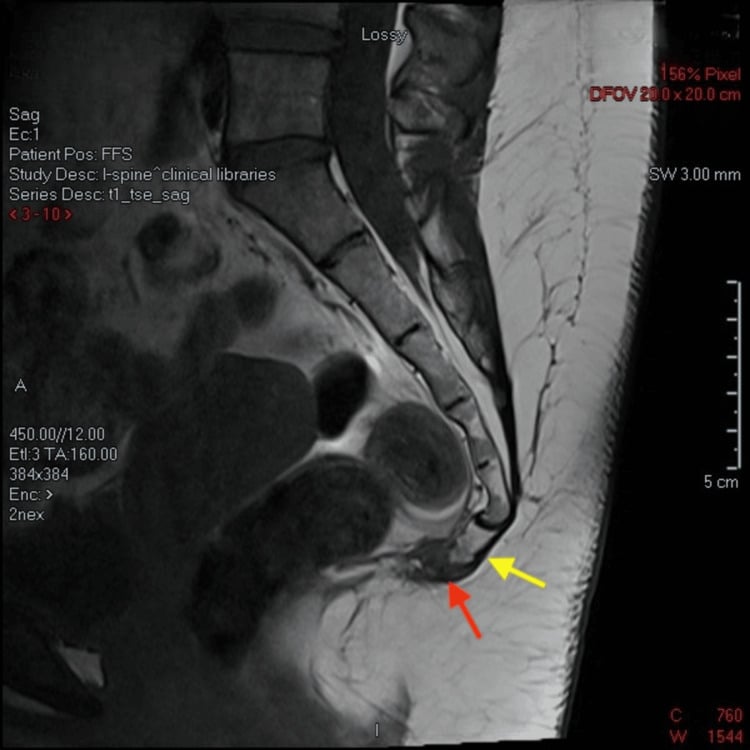
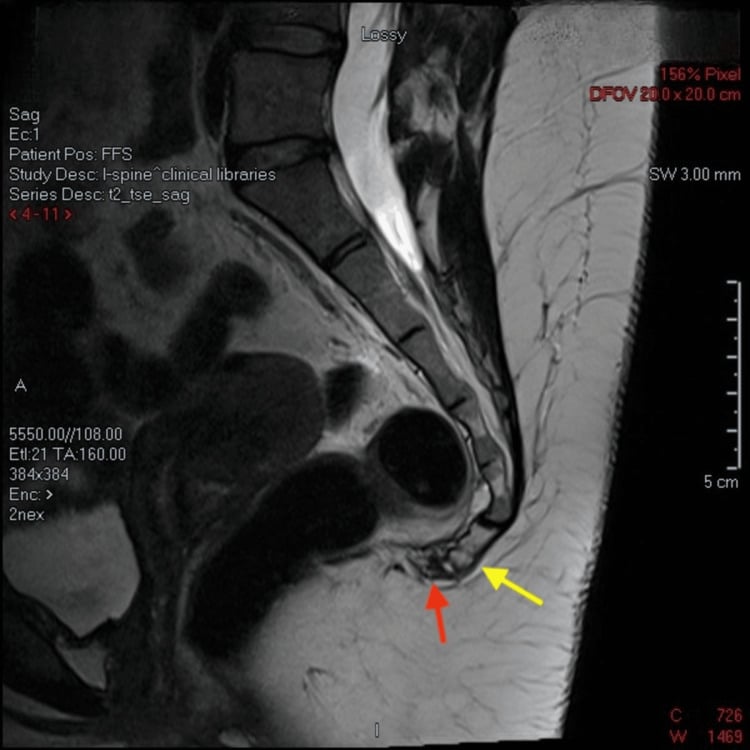
- MRI: rarely needed, but used for persistent pain to exclude tumour or infection
Differential Diagnosis
Pain localised to the tailbone is not always coccygeal in origin. The most important task is to separate true coccydynia from referred or sinister pathology before committing to long-term coccyx-directed treatment.
- Distinguishing Features
- Pain worse sitting and on standing up; point tenderness over coccyx; trauma or childbirth history
- Key Discriminator
- Reproduced by direct coccygeal palpation +/- dynamic radiograph lesion
- Distinguishing Features
- Older osteoporotic patient or athlete; tenderness over sacrum not coccyx
- Key Discriminator
- MRI marrow oedema; H-shaped uptake on bone scan (Honda sign)
- Distinguishing Features
- Midline natal-cleft sinus/pits, discharge, abscess; soft-tissue not bony pain
- Key Discriminator
- Visible sinus openings and induration in natal cleft
- Distinguishing Features
- Abscess, fissure, proctalgia fugax; pain with defaecation, anal not coccygeal tenderness
- Key Discriminator
- PR exam and anoscopy; no bony coccygeal tenderness
- Distinguishing Features
- Radicular leg symptoms, positive SIJ provocation; coccyx non-tender
- Key Discriminator
- Normal coccygeal palpation; positive root/SIJ tests
- Distinguishing Features
- Insidious unrelenting pain, night pain, neurological signs, mass on PR
- Key Discriminator
- MRI mass; do not attribute persistent atypical pain to benign coccydynia
Persistent atypical coccygeal pain without clear trauma, night pain, a palpable presacral mass on rectal examination, or neurological signs mandate MRI to exclude chordoma or other sacrococcygeal tumour before labelling pain as benign coccydynia.
Management Algorithm
Treatment is a ladder: conservative care first, injections when pain persists beyond 2-3 months, and coccygectomy only after 6-12 months of failed conservative treatment and injections.
Conservative care is the standard. It combines:
- Cushion: a donut or wedge cushion reduces pressure on the coccyx when sitting
- Analgesia: NSAIDs first line, and paracetamol; opioids are rarely needed
- Stool softeners: reduce straining at defaecation
- Activity modification: avoid prolonged sitting on hard surfaces, but keep gently active and avoid bed rest
- Physiotherapy: pelvic floor exercises and manual therapy
- Time: most resolve in 4-12 weeks
Set modest expectations for the manual therapy: in the randomised pilot carded in the Evidence Base, about one patient in four had a satisfactory result.
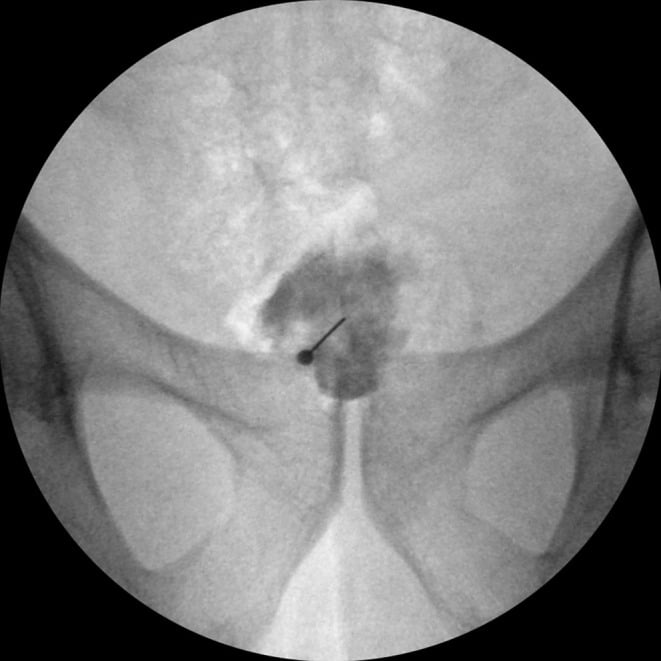
Ganglion impar block. Local anaesthetic, with or without steroid, is injected at the sympathetic ganglion impar, usually through a trans-sacrococcygeal needle (through the sacrococcygeal disc) under fluoroscopy or ultrasound. It provides temporary or prolonged relief. Neurolysis with phenol or alcohol, or radiofrequency, is used for malignant perineal pain.
Coccygeal injection. Steroid is injected around the sacrococcygeal joint. Repeated injections may be needed, and success is variable.
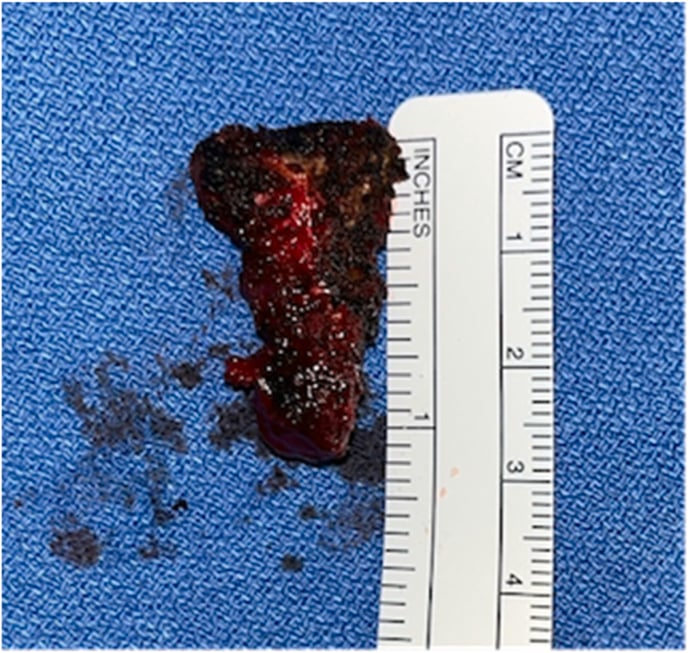
Coccygectomy for the refractory few. Surgery is rare. It is reserved for severe, debilitating coccydynia in which conservative treatment and injections have failed.
Surgical Technique
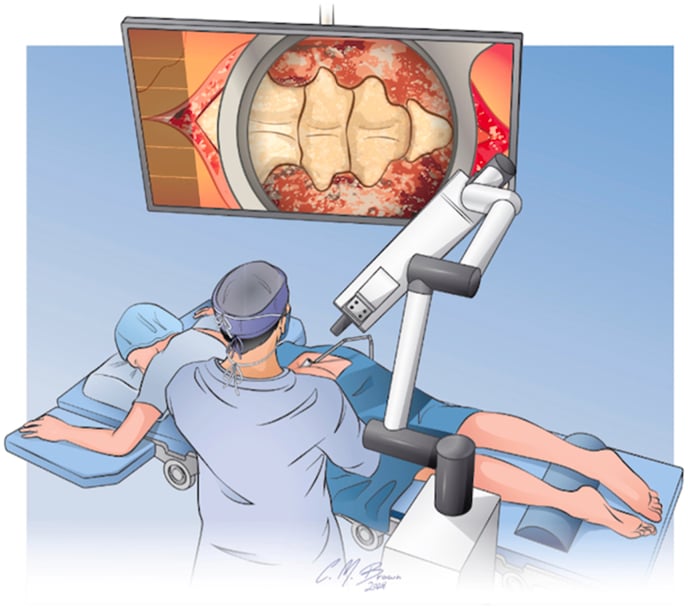
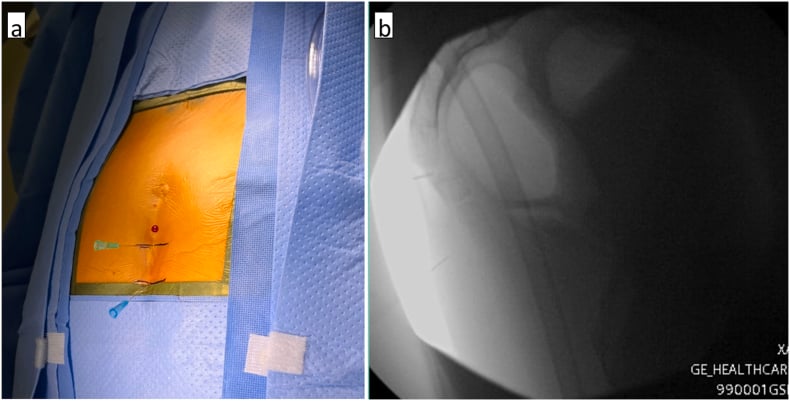
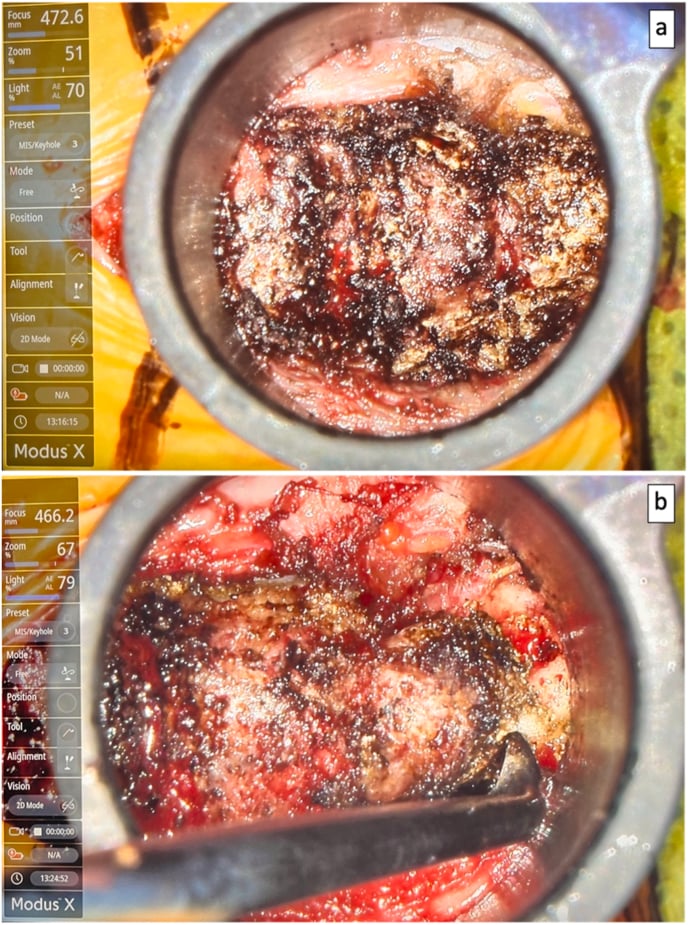
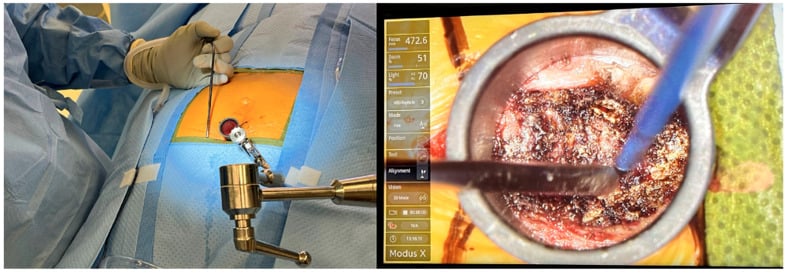
Coccygectomy is a standard midline approach with careful subperiosteal dissection. Meticulous technique reduces its high wound complication rate.
The procedure. In sequence:
- Position: prone, jack-knife or flat
- Prophylaxis: antibiotics (see Postoperative Care); bowel preparation is not usually needed
- Incision: midline longitudinal over the coccyx
- Dissection: incise the periosteum, dissect subperiosteally down to the coccyx while protecting the rectum, and identify the sacrococcygeal joint
- Excision: divide at the sacrococcygeal joint and remove the coccyx, or leave the most proximal segment
- Closure: close the periosteum if possible, then in layers, avoiding dead space
Pearls. Points of technique:
- The rectum lies very close, in front of the coccyx: keep a finger in it to guide the dissection
- Meticulous haemostasis matters because a haematoma this close to the anus leads to infection
- Some surgeons leave the most proximal coccygeal segment to maintain soft-tissue attachments
- Consider a drain if there is a large dead space or concern about haemostasis
Complications
Patient selection is the key to a good outcome. Dehiscence is managed by keeping the wound clean, and may need secondary closure.
- Risk Factor
- Severe injury, malunion
- Management
- Injections, coccygectomy
- Risk Factor
- Proximity to the anus
- Management
- Antibiotics, drainage or washout
- Risk Factor
- Dissection error
- Management
- Primary repair if recognised
- Risk Factor
- Inadequate haemostasis
- Management
- Drainage if significant
- Risk Factor
- Nerve irritation
- Management
- Reassurance, injections
Postoperative Care
After coccygectomy. The wound sits a few centimetres from the anus in a thin posterior soft-tissue envelope, so the whole protocol is built around keeping it clean, keeping stool soft and keeping direct pressure off it.
Prone or lateral positioning; no direct sitting on the wound. Occlusive dressing changed after any bowel action. Perioperative antibiotics per local protocol, continued for 24-48 hours after surgery, given the proximity to the anal verge.
Regular stool softeners and adequate fluid from day one. Straining loads the wound directly and a constipated first bowel action is the commonest cause of early wound breakdown.
Avoid direct sitting on the wound for 2-4 weeks; use a wedge or ring cushion that offloads the midline and sit forward on the thighs. Inspect the wound at each dressing change - deep infection close to the anus is the complication that determines the result.
Wound reviewed and healed; graduated return to sitting tolerance, driving and work. Counsel that pain relief may continue to improve over months rather than being complete at wound healing.
Outcomes
Conservative care. It succeeds in 90%, with resolution over weeks to months. A minority, 10-20%, develop chronic coccydynia, and patients should be warned.
Coccygectomy. In refractory cases 70-90% achieve significant improvement.
Guidelines, Registries & Global Practice
Global epidemiology
- Coccydynia accounts for under 1% of all back-pain presentations; true incidence is unknown because most cases never reach secondary care.
- Female predominance roughly 5:1, attributed to a shorter, more posteriorly angled coccyx and obstetric trauma; peak age 40-50 years (per Maigne and Wray cohorts).
- Obesity and very low BMI are both risk factors via altered sitting mechanics (Maigne 2000).
Guideline & society positions (side-by-side)
- Imaging Stance
- Isolated coccyx fracture is a clinical diagnosis; image to exclude sacral or pelvic-ring injury if mechanism warrants
- Treatment Emphasis
- Non-operative; coccyx fractures essentially never need acute fixation
- Imaging Stance
- Avoid routine radiographs for non-specific tailbone pain; reserve imaging/MRI for red flags
- Treatment Emphasis
- Conservative stepwise care; refer refractory pain to spine/pain services
- Imaging Stance
- Dynamic sit-stand radiographs to classify chronic cases
- Treatment Emphasis
- Stepwise ladder: conservative then injection/RFT/ESWT then coccygectomy
- Imaging Stance
- Fluoroscopy/US-guided block of the ganglion impar
- Treatment Emphasis
- Non-neurodestructive ganglion impar block before surgery (very-low-certainty evidence)
Registry note
- There is no dedicated coccyx implant/arthroplasty registry (no implant involved). The largest pooled outcome dataset comes from spine registries and systematic reviews (e.g. DaneSpine data within the Global Spine J review) rather than a single national registry.
High- vs limited-resource practice variation
- Well-resourced settings: ready access to MRI for red-flag exclusion, fluoroscopy/ultrasound-guided ganglion impar blocks, radiofrequency and shockwave therapy, and specialist coccygectomy in selected centres.
- Limited-resource settings: diagnosis is clinical; treatment centres on cushioning, NSAIDs, stool softeners, activity modification and physiotherapy. Injections and surgery are reserved for the rare refractory case referred to a regional centre. The good prognosis of conservative care makes this entirely appropriate for most patients worldwide.
Related pages: Sacral Fractures is the injury immediately above and the one that must not be missed when a fall on the buttock produces low sacrococcygeal pain - a transverse sacral fracture can present exactly as a "coccyx injury" and carries neurological risk that the coccyx never does. Sacral Insufficiency Fracture is the diagnosis in an older or osteoporotic patient whose pain began without a fall, and it is the commonest reason a plain film is inadequate. Pelvic Ring Injuries covers the higher-energy end of the same mechanism. Sacroiliac Joint Dysfunction and Lumbar Disc Herniation are the two referred sources most often mistaken for coccydynia, and the 1991 trial carded above is the reason a lumbar MRI is not needed to explain coccygeal pain - disc prolapse is not a significant cause. Low Back Pain Assessment supplies the red-flag screen that must precede any of this. Chordoma is the sinister diagnosis of the sacrococcygeal region and the single reason night pain, a palpable presacral mass or progressive symptoms mandate cross-sectional imaging rather than another injection. Systematic Approach to Spine Imaging with Systematic Approach to Pelvis and Hip Imaging cover the views and the sit-versus-stand technique this diagnosis depends on. Complex Regional Pain Syndrome is worth reading alongside the interventional evidence here, because both fields share the problem this page's ranking illustrates - uncontrolled before-and-after data in a condition with a large natural-history and placebo component.
Controversies & Areas of Uncertainty
Coccydynia is a low-evidence field: most data are retrospective, outcome measures are inconsistent, and no high-quality RCT compares the modern treatment ladder head-to-head.
Whether plain films change acute management is debated. In a clear traumatic history with isolated coccygeal tenderness, radiographs rarely alter conservative care; imaging is most useful for chronic or atypical pain to classify the lesion or exclude tumour.
The "greater than 25 degrees" cut-off for hypermobility (and posterior subluxation) derives from a small number of cohorts; normal mobility varies widely and the threshold is not universally validated. Use as a guide, not an absolute rule.
Ganglion impar block and corticosteroid injection have only very-low-certainty evidence, yet are routinely used before coccygectomy. Whether interventions meaningfully delay or prevent surgery, versus simply postponing definitive treatment, is unresolved.
Whether to excise the whole coccyx or leave the proximal segment, and the role of newer non-destructive techniques (radiofrequency, shockwave), lacks comparative trial data; practice is surgeon-dependent.
Viva Scenarios
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is your diagnosis and management?”
MCQ Practice Points
Q: What is the most common mechanism for coccyx fractures? A: Direct fall onto buttocks (sitting position).
Q: What is the first-line treatment for acute coccyx fractures? A: Conservative - Cushion (donut or wedge), NSAIDs, Activity modification, Stool softeners.
Q: What percentage of coccyx injuries develop chronic coccydynia? A: 10-20%.
Q: What does dynamic lateral X-ray assess? A: Coccygeal mobility. Greater than 25 degrees movement between sitting and standing indicates hypermobility.
Q: What is the surgical treatment for refractory coccydynia? A: Coccygectomy - Excision of the coccyx. Reserved for failures of 6-12 months of conservative treatment and injections.
5 F's
- Female (5x more common)
- Fat (obesity is risk factor)
- Forty (peak age 40-50)
- Fall (direct trauma mechanism)
- Fracture/Dislocation pattern
Treatment
- Cushion (Donut/Wedge) for sitting
- NSAIDs for pain control
- Stool Softeners to reduce straining
- Activity modification (avoid hard chairs)
- Time heals most (4-12 weeks)
Chronic Coccydynia
- Dynamic X-ray (sitting vs standing)
- Hypermobility: greater than 25° movement
- Ganglion Impar block first-line
- Coccygectomy for failures after 6-12 months
- 70-90% success with coccygectomy
Key Numbers
- 90% conservative success rate
- 70-90% surgery success rate
- 10-20% develop chronic coccydynia
- 10-15% wound infection post-op
- 4-12 weeks typical recovery
Evidence Base
Dynamic Radiographs Define Coccydynia Lesions
- 208 consecutive coccydynia patients imaged standing then in the painful sitting position.
- Two culprit lesions on dynamic films: posterior luxation and hypermobility; BMI determined lesion type (posterior luxation 51% in obese vs 3.7% in thin patients).
- Recent trauma (under 1 month) raised the instability rate from 55.6% to 77.1%; protocol identified the culprit lesion in 69.2% of cases.
Treatment Manipulation Outcomes by Coccyx Mobility
- Randomised pilot of three manual treatments (levator ani massage, joint mobilisation, levator stretch) in coccydynia.
- Overall satisfactory results in only 25.7% at 6 months and 24.3% at 2 years.
- Patients with a normally mobile coccyx fared best; an immobile coccyx had the poorest results.
Coccydynia: Aetiology and Conservative Treatment
- Five-year prospective trial of 120 patients; cause is a localised musculoskeletal abnormality, not lumbosacral disc prolapse.
- Physiotherapy of little help; local corticosteroid plus anaesthetic injection helped 60%.
- Injection combined with manipulation cured about 85%; coccygectomy needed in almost 20% with over 90% success.
How to read the treatment ranking
The systematic review orders treatments by mean VAS reduction - radiofrequency 5.11, shockwave 5.06, coccygectomy 4.86, injection 4.22, ganglion impar block 2.98, manual therapy 2.19, conservative care 1.69
- and that ordering must not be read as a ranking of efficacy. Three things about it are load-bearing:
- The top of the list is the least-studied part of it. Only five of 64 studies were randomised and 45 were retrospective. Radiofrequency and shockwave head the table on small, new, uncontrolled series, while the authors state that coccygectomy is by far the most thoroughly investigated option. A new technique reported by its enthusiasts reliably produces the largest before-and-after difference.
- The bottom of the list calibrates the top. Conservative care improved VAS by 1.69 without an intervention. That is the best available estimate of natural history plus regression to the mean in this condition, and it is contained inside every number above it before any specific effect begins.
- The comparisons are between studies, not within them. Patients reaching coccygectomy have failed everything else and usually have a positive diagnostic block, so they are a filtered population; the conservative-care patients are not. No trial has compared these options head to head.
The defensible conclusion is the one the ladder already encodes - escalate from cheap and safe to invasive and irreversible - and not that radiofrequency outperforms surgery.