Budapest Criteria | Vitamin C Prevention | Multidisciplinary Management | Early Treatment Critical
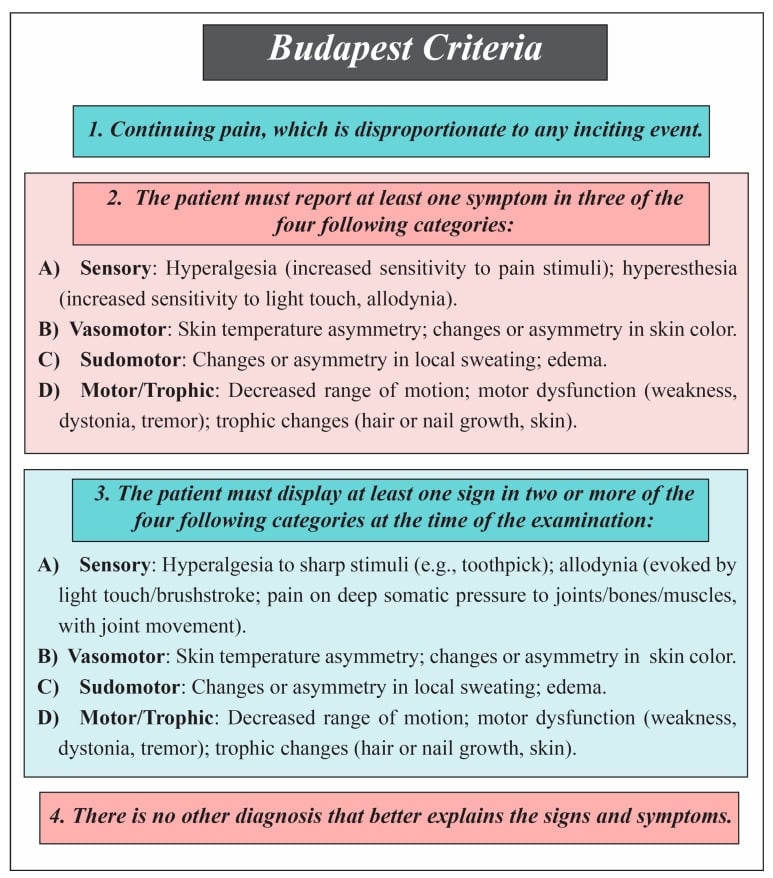
- Budapest criteria: continuing disproportionate pain plus symptoms in ≥3 of 4 categories (sensory, vasomotor, sudomotor/oedema, motor/trophic) AND signs in ≥2, with no better diagnosis
- Vitamin C prophylaxis: 500mg daily for 50 days cut CRPS after wrist fracture from ~10% to ~2.4% in the Zollinger RCT (later evidence mixed)
- Function-focused rehabilitation is the foundation - graded motor imagery, mirror therapy, desensitisation; escalate by response
- Multidisciplinary care: rehabilitation and self-management first; add pharmacological, psychological and interventional options selectively by phenotype and response
- Diagnosis of exclusion: actively rule out infection, DVT, compartment syndrome and nerve injury before diagnosing CRPS
- “Budapest criteria: disproportionate pain plus symptoms in ≥3 of 4 categories and signs in ≥2, with no better explanation
- “Vitamin C 500mg daily for 50 days reduced CRPS after wrist fracture (~10% to ~2.4%); the RCT was in wrist, not foot/ankle, and later data are mixed
- “Rehabilitation (graded motor imagery, desensitisation, mirror therapy) is the foundation of treatment
- “The classic 3-stage model is traditional but not validated - do not quote it as prognosis
Overview and Epidemiology
Complex regional pain syndrome (CRPS) is a chronic pain condition that typically develops after trauma or surgery, though it can arise spontaneously. It combines regional pain out of proportion to the injury with sensory, vasomotor, sudomotor/oedema and motor/trophic features. It was formerly known as reflex sympathetic dystrophy (RSD) or Sudeck's atrophy, and it remains one of the most contested diagnoses in orthopaedics.
The names. Silas Weir Mitchell described causalgia in 1864, and Sudeck described the atrophy in 1900. Reflex sympathetic dystrophy was the term in use until 1994, when the IASP adopted CRPS. The Budapest criteria, established in 2003, are the current diagnostic standard.
How common. Population incidence runs from 5.5 to 26 per 100,000 person-years, the lower figure from Olmsted County and the higher from Dutch primary-care data. Estimates vary several-fold with the case-finding method, so no single figure should be quoted as settled.
Who. Women are affected 3-4 times as often as men, and incidence is highest in postmenopausal women aged 61-70. The median age at onset is about 46, and the upper limb is affected more often than the lower.
What sets it off. Fracture is the commonest trigger, in 44-46% of cases, especially fracture of the distal radius. Surgery and sprains are other triggers, and onset can be spontaneous. The recognised risk factors are:
- Female sex
- Fracture and immobilisation, and cast-related complaints
- Smoking
- Possibly anxiety or depression
- Previous CRPS, which carries a 10-30% recurrence risk
Anatomy and Pathophysiology
Mechanism. The exact mechanism is unclear, and no single theory explains CRPS. Peripheral and central sensitisation, neurogenic inflammation, altered sympathetic function, cortical reorganisation and possible autoimmune contributions all have supporting evidence, but none is fully proven. The condition is best viewed as multi-mechanistic.
- Mechanism
- Release of neuropeptides (substance P, CGRP)
- Evidence
- Elevated levels in CRPS
- Mechanism
- Altered pain processing in CNS
- Evidence
- Functional MRI changes
- Mechanism
- Abnormal sympathetic activity
- Evidence
- Response to sympathetic blocks
- Mechanism
- Autoantibodies against nervous system
- Evidence
- Some evidence
What the signs mean. Allodynia, pain from a non-painful stimulus such as light touch, indicates central sensitisation. Hyperalgesia, exaggerated pain from a painful stimulus, indicates peripheral and central sensitisation. Temperature and colour asymmetry indicate autonomic dysfunction, and trophic changes (hair loss, nail changes, skin atrophy) indicate chronic change.
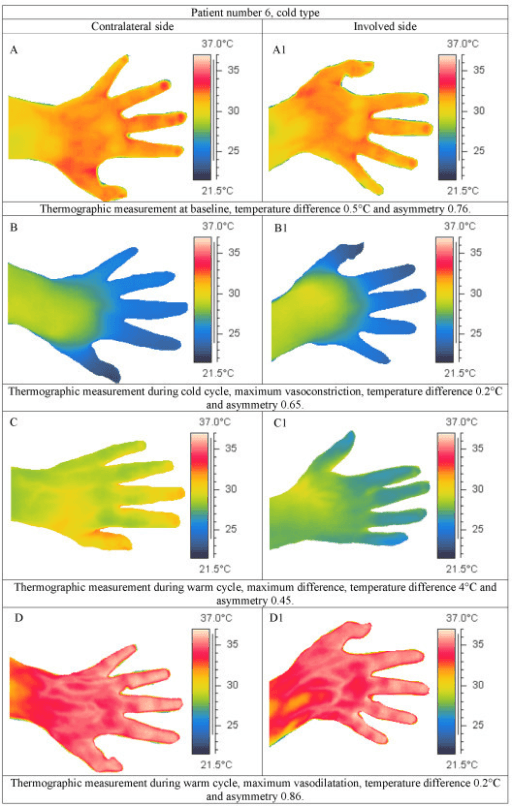
Phenotypes, not stages. The classic acute, dystrophic and atrophic sequence is traditional and not validated by prospective data, and many patients do not progress through it in order. Cluster analysis supports sub-types instead, a warm inflammatory form and a cold central form. The stage names are useful descriptive vocabulary but not a prognostic model.
- Timing
- Often earlier, but not time-defined
- Features
- Pain, swelling, warmth, erythema, sweating change, limited ROM
- Note
- Inflammatory features may fluctuate
- Timing
- Can occur early or late
- Features
- Coolness, cyanotic or mottled colour, trophic change, motor dysfunction
- Note
- Not an inevitable second stage
- Timing
- Variable duration
- Features
- Disuse, weakness, movement fear, dystonia, contracture or fixed functional loss
- Note
- Can become dominant in either phenotype; reflects phenotype and behaviour, not a validated stage 3
The phenotypes can occur at different durations and may change over time. Fixed changes are not automatically irreversible, and duration alone does not define prognosis. Treatment remains function-directed while alternative diagnoses are continually reconsidered.
Classification Systems
Budapest Diagnostic Criteria (Current Standard)
All four requirements must be met:
- Continuing pain disproportionate to the inciting event
- Symptoms in ≥3 of 4 categories:
- Sensory: allodynia (pain from light touch), hyperalgesia (exaggerated pain)
- Vasomotor: temperature asymmetry (greater than 1°C), skin colour changes (blotchy, purple, red, pale)
- Sudomotor/Oedema: swelling, sweating changes (hyperhidrosis or anhidrosis)
- Motor/Trophic: decreased ROM, motor dysfunction (weakness, tremor), trophic changes (hair loss, nail changes, skin atrophy)
- Signs in ≥2 of 4 categories (same categories)
- No other diagnosis that better explains the symptoms
A clinical diagnosis. No definitive test confirms CRPS; the diagnosis is made clinically on these criteria, and early diagnosis improves outcomes. The clinical criteria have a sensitivity of 0.99 and a specificity of 0.68.
Clinical Assessment
History. The story is of recent trauma or surgery, weeks to months earlier, followed by pain out of proportion to the injury and symptoms that progress. Ask about previous CRPS and the risk factors above.
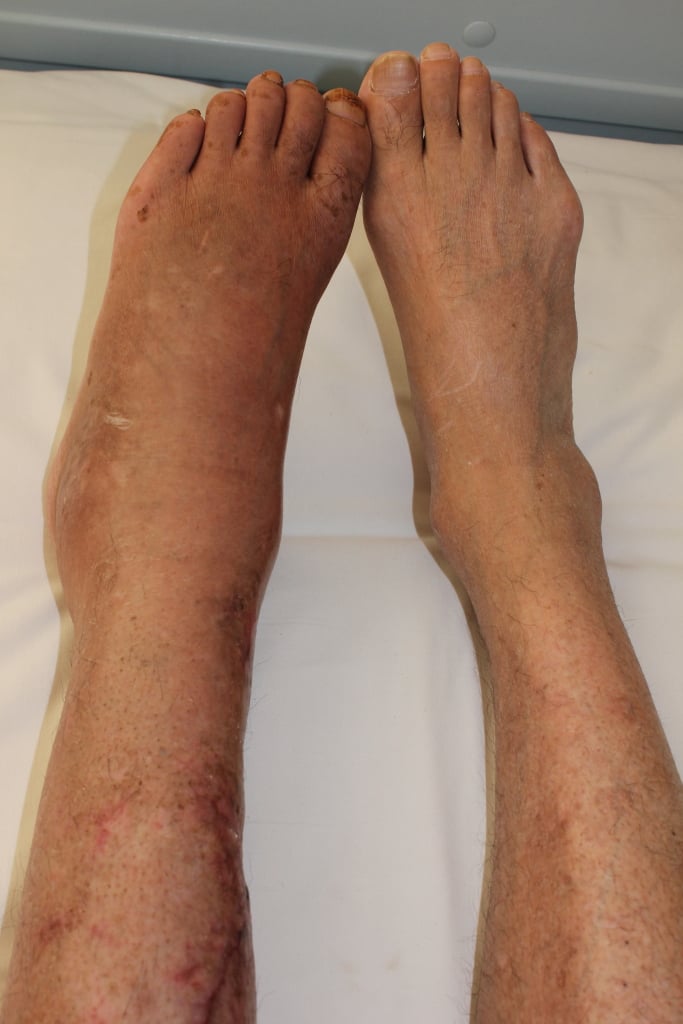
Examination. Examine both limbs side by side, compare with the contralateral limb and document how the findings vary. Test for allodynia with light touch and hyperalgesia with pinprick, measure temperature asymmetry objectively where possible, and look for colour change, sweating change and persistent oedema.
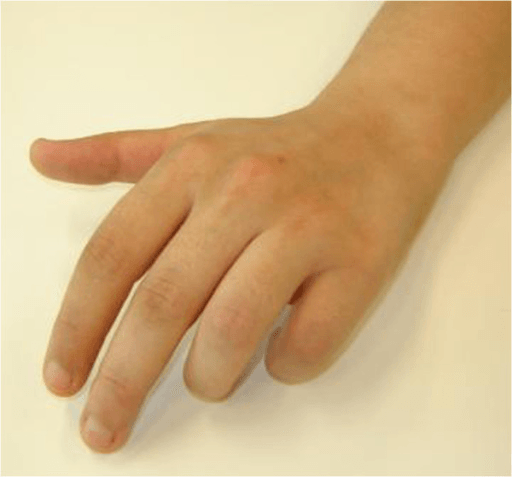
Motor and trophic signs. Range of motion is reduced out of proportion to the injury. Look for weakness, tremor and dystonia, and for trophic change in the hair, nails and skin.
Allodynia supports CRPS when it occurs within the full regional Budapest pattern, but it is not specific: nerve injury, entrapment and other neuropathic pain disorders can also cause pain from light touch. Apply every Budapest requirement and exclude a better diagnosis.
Investigations
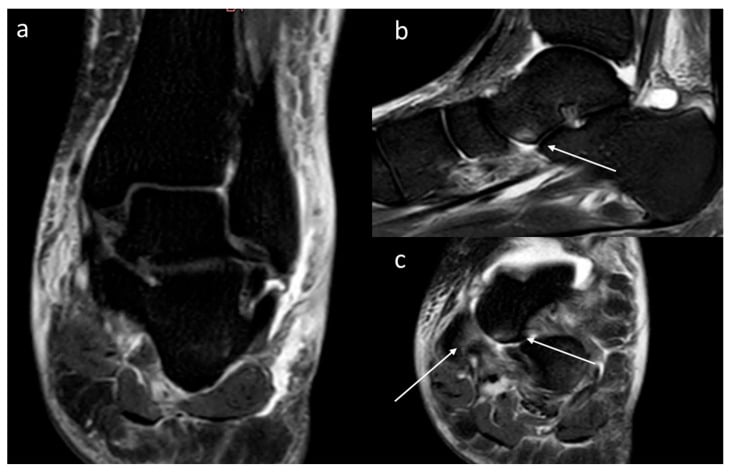
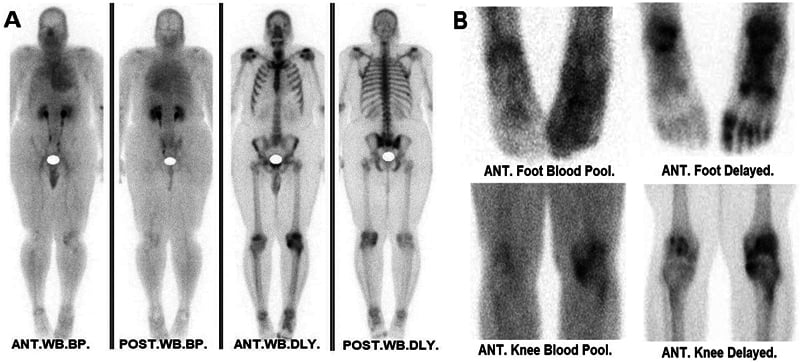
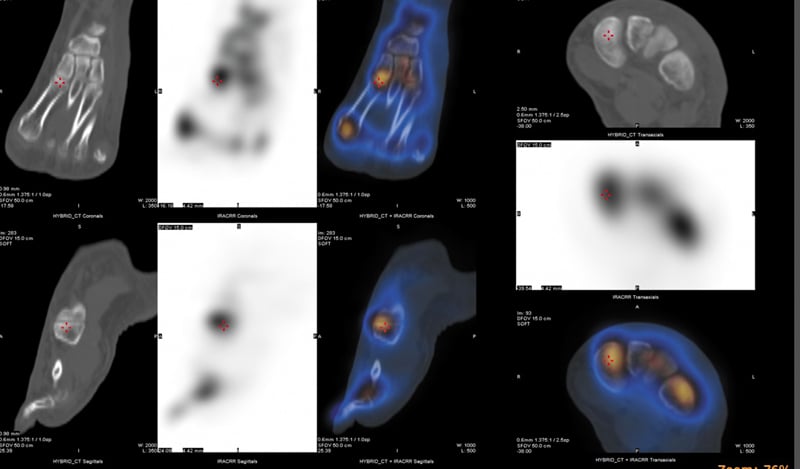
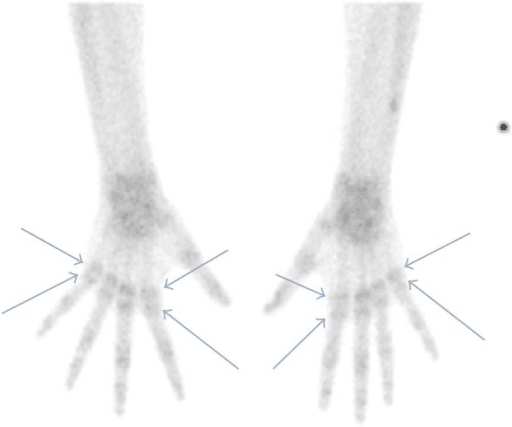
Tests support the diagnosis but do not make it. Three-phase bone scan and MRI are supportive but not required.
- Finding
- Increased uptake in affected limb
- Significance
- Supportive but not diagnostic
- Finding
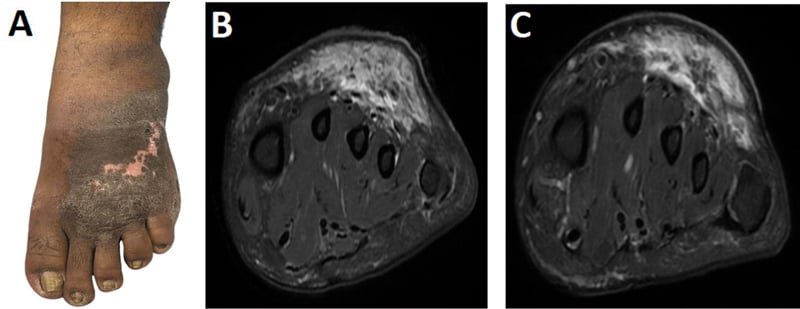
- Patchy bone marrow oedema, soft tissue oedema
- Significance
- Supportive but not diagnostic
- Finding
- Patchy osteopenia (late)
- Significance
- Late finding, not early
- Finding
- Temperature asymmetry
- Significance
- Supportive but not diagnostic
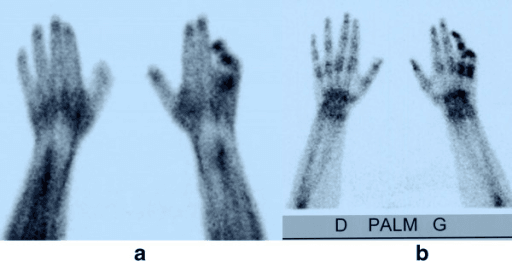
Three-phase bone scan. Each phase shows an increase in the affected limb:
- Phase 1 (blood flow): increased perfusion
- Phase 2 (blood pool): increased pooling
- Phase 3 (delayed): increased uptake
Sensitivity is 50-80%, so a normal scan does not exclude CRPS, and specificity is moderate.
MRI. Patchy bone-marrow oedema and soft-tissue oedema support the diagnosis without making it. MRI may also help exclude other diagnoses.
Sympathetically Maintained vs Sympathetically Independent Pain
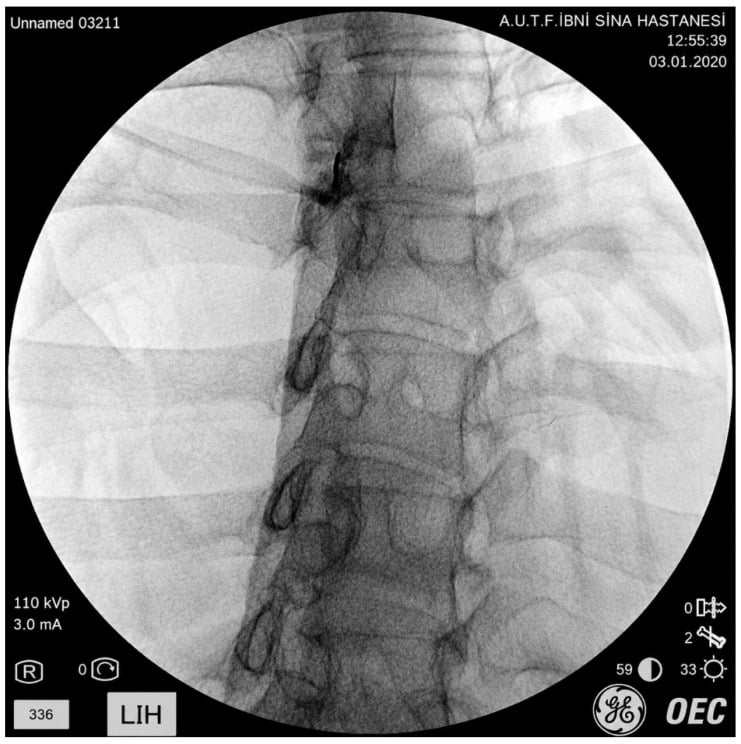
Sympathetic contribution to the pain varies within and between patients. Sympathetically maintained pain is a component that appears to improve after sympathetic interruption; sympathetically independent pain persists despite an adequate block. The two can coexist and change.
What a block tells you. A technically successful local-anaesthetic block may temporarily reduce pain and create a rehabilitation window, but the response is influenced by spread, placebo, sedation and measurement method. Block response is not a definitive diagnostic test for CRPS, does not prove a permanent mechanism and does not justify destructive sympathectomy.
Differential Diagnosis
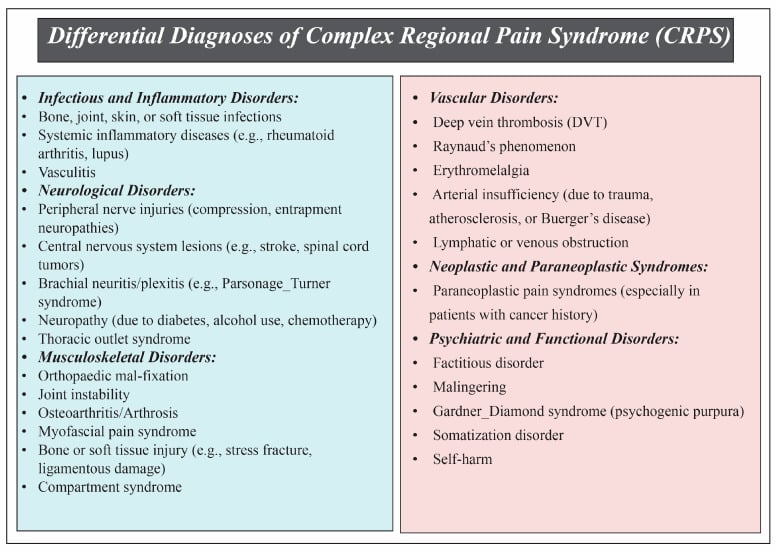
CRPS is a clinical diagnosis of exclusion: Budapest criterion 4 requires that no other diagnosis better explains the findings. The key mimics after limb trauma or surgery must be actively excluded before a patient is labelled with CRPS.
- Discriminating features
- Disproportionate pain plus vasomotor, sudomotor/oedema and motor/trophic signs in one region
- Excluded by
- Meets Budapest criteria; no better explanation
- Discriminating features
- Fever, raised CRP/WCC, localised collection, systemic upset
- Excluded by
- Bloods, aspiration, MRI/imaging
- Discriminating features
- Unilateral swelling, calf tenderness, risk factors
- Excluded by
- Doppler ultrasound, D-dimer
- Discriminating features
- Pain on passive stretch, tense compartment, early post-injury
- Excluded by
- Clinical exam, compartment pressures
- Discriminating features
- Pain in defined nerve territory, sensory/motor map fits a nerve
- Excluded by
- Examination, nerve conduction studies
- Discriminating features
- Focal bony tenderness, mechanical pain, implant prominence
- Excluded by
- Radiographs, CT
- Discriminating features
- Joint-centred swelling, polyarticular pattern, raised inflammatory markers
- Excluded by
- Bloods, joint aspiration, serology
Never diagnose CRPS until infection, DVT, compartment syndrome and nerve injury have been considered and excluded. Vasomotor change plus disproportionate pain can be the presentation of all four. Budapest criterion 4 ("no other diagnosis") is not optional.
Management Algorithm
The evidence is thin. The 4th-edition guidelines explicitly note a paucity of level 1-2 evidence, and function-focused rehabilitation has the most consistent support. Rehabilitation, education and pacing are the foundation. Graded motor imagery, mirror therapy, medicines, psychology, blocks and neuromodulation have variable evidence, and are selected to help a patient progress rather than applied as a fixed ladder.
Measuring progress. Track function, sleep, participation and adverse effects rather than relying on pain intensity alone. Pain medicine, rehabilitation, orthopaedics and the relevant medical specialties coordinate when function stalls or the diagnosis is uncertain.
Prevention
Vitamin C. In the Zollinger dose-response RCT in wrist fractures, CRPS developed in about 10% of placebo patients against 2.4% of those given vitamin C. The recommended dose was 500 mg daily for 50 days, with no added benefit from higher doses.
How far it travels. The Zollinger wrist-fracture RCTs are positive, but later wrist trials and meta-analyses have produced mixed results, and the effect was not reproduced in some surgical and foot/ankle cohorts, so applicability outside distal-radius fracture is uncertain. Its low cost and safety mean many guidelines still recommend it, and it is widely recommended for high-risk fractures, but the certainty of benefit is lower than once thought.
Using it. Present vitamin C as optional prophylaxis after wrist fracture, not a universal or mandatory peri-operative standard. Consider it only after checking renal/stone risk, interactions and local guidance.
General principles. These apply to every injury and operation:
- Avoid unnecessary immobilisation while respecting fracture or repair stability; early mobilisation reduces risk and prolonged immobilisation increases it
- Provide adequate multimodal analgesia, NSAIDs included, to prevent central sensitisation, with clear activity guidance
- Recognise cast pressure, infection, vascular compromise and nerve injury early
- Educate about expected recovery without catastrophising normal post-traumatic symptoms
Prevention evidence is limited, and early recognition of a concerning trajectory is more defensible than a universal drug pathway.
Bisphosphonates in CRPS
Where they stand. Bisphosphonates are the best-evidenced pharmacological disease-modifier in early CRPS, although the supporting data remain limited.
Rationale. Early CRPS shows accelerated regional bone turnover. The patchy periarticular osteopenia on late radiographs, the increased delayed-phase uptake on three-phase bone scan and the bone-marrow oedema on MRI all reflect osteoclast-driven bone resorption. Bisphosphonates inhibit osteoclastic resorption and damp this heightened turnover, and may also reduce the local acidic and inflammatory microenvironment and the associated nociceptor sensitisation.
Who benefits. Benefit is greatest in the early, warm, high-turnover phase with increased bone-scan uptake, the subgroup most likely to respond, and little in long-standing cold disease. Randomised trials support several agents (oral alendronate, intravenous pamidronate, intravenous neridronate), and the neridronate multicentre RCT is the most cited and most positive.
How to use them. Choice of agent and regimen require specialist assessment. They are a reasonable adjunct to function-focused rehabilitation in early CRPS, especially with imaging evidence of increased bone turnover, and not a substitute for it.
Neridronate for Early CRPS-I (Randomised Controlled Trial)
- Multicentre double-blind RCT, 82 patients with acute CRPS-I of the hand or foot: IV neridronate 100mg four times over 10 days vs placebo
- VAS pain fell significantly more with neridronate (further reduction 46.5mm vs 22.6mm over days 20-40; p less than 0.0001)
- Significant gains across other pain and quality-of-life indices; formerly-placebo patients matched the active group after open-label crossover
- At one year no patient reported CRPS-related symptoms
Surgical Technique
CRPS itself is not a surgical condition, but the underlying injury may need surgery, and some operations are done with CRPS present or at risk.
Operating on a limb at risk. Minimise surgical trauma: handle tissue gently, secure meticulous haemostasis, avoid excessive retraction and minimise tourniquet time if possible. The peri-operative pathway follows the prevention principles in the management section.
Hardware removal. Removing hardware does not reliably improve CRPS and may worsen symptoms if the CRPS is active. Remove it only if the hardware itself is causing problems, and treat the CRPS first.
Timing. Wait for the CRPS to stabilise or improve, which may take months to years. The decision is individualised.
Complications
- Timing
- Persistent
- Management
- Multidisciplinary pain management
- Timing
- Persistent
- Management
- Physiotherapy, occupational therapy
- Timing
- Late
- Management
- Surgical release if severe
- Timing
- Common
- Management
- Psychological support, CBT
- Timing
- Ongoing
- Management
- Monitor and adjust
Chronic CRPS. Between 10% and 20% develop chronic CRPS with permanent disability. The prognosis is poor if treatment is delayed, long-term pain management may be required, and functional impairment may be permanent.
Contractures. Fixed contractures are a late complication and may need surgical release. Early recognition and active, function-focused rehabilitation, with physiotherapy throughout, reduce the risk of contractures and chronic disability.
Postoperative Care
Where CRPS is a risk after surgery, the postoperative course applies the prevention principles in sequence. Vitamin C is included only where it is being used, as optional prophylaxis after wrist fracture.
CRPS Prevention Protocol
- If vitamin C is used, start 500mg daily (continue for 50 days)
- Multimodal analgesia
- Gentle tissue handling
- Minimise immobilisation
- Continue vitamin C if used
- Adequate pain control
- Early mobilisation if fracture stable
- Monitor for CRPS signs
- Continue vitamin C if used (total 50 days)
- Physiotherapy (ROM exercises)
- Functional restoration
- Monitor for CRPS
- Continue monitoring
- Early recognition if CRPS develops
- Multidisciplinary treatment if needed
If CRPS develops. Refer immediately to the multidisciplinary team and the pain clinic. Physiotherapy is the cornerstone, supported by psychological support, sympathetic blocks if needed and medication, where a neuropathic agent such as gabapentin may be trialled.
Outcomes and Prognosis
What the evidence shows. In the Olmsted County population study, about 74% of CRPS-I cases resolved, often spontaneously (Sandroni 2003). That estimate used older, less-specific IASP criteria, and outcomes are heterogeneous and hard to predict. Counselling that most cases resolve while a minority become chronic is more defensible than the older claim of fixed, stage-linked recovery rates.
Worse outcome. The associations are clinical and not precisely quantified:
- Longer symptom duration and delayed recognition
- The cold/central phenotype
- Marked motor/trophic changes and established contractures
- Psychological distress (anxiety/depression) as a comorbidity
- Previous CRPS (recurrence risk)
Guidelines, Registries & Global Practice
Global epidemiology:
- Population incidence varies several-fold by case-finding: 5.5 per 100,000 person-years (Olmsted County, USA) to 26.2 per 100,000 (Dutch primary care)
- Consistently female-predominant (3-4:1), peaking in postmenopausal women; fracture is the commonest trigger worldwide (44-46%)
- The diagnosis is clinical and standardised internationally by the Budapest criteria, so cross-country comparison is more consistent than for many pain conditions
Side-by-side guideline comparison:
- Diagnostic standard
- Budapest criteria
- Emphasis / notable position
- Function-focused interdisciplinary rehabilitation as the foundation; pragmatic recommendations given limited high-grade evidence
- Diagnostic standard
- Budapest criteria
- Emphasis / notable position
- Early diagnosis and the '4 pillars' (education, pain relief, physical/vocational rehab, psychology); GP-level recognition
- Diagnostic standard
- Clinical signs/symptoms
- Emphasis / notable position
- Free-radical scavengers (DMSO/N-acetylcysteine) for inflammatory CRPS; vitamin C to prevent CRPS after wrist fracture
- Diagnostic standard
- Budapest criteria
- Emphasis / notable position
- Stepwise, multidisciplinary care; SCS reserved for refractory disease in specialist centres
- CRPS is not tracked in joint registries, but registry-level evidence informs prevention: minimising re-operation, immobilisation and repeated cast complaints reduces risk
- Spinal cord stimulation outcomes are followed in device/pain registries; real-world data echo the trial finding of pain (not function) benefit with a meaningful revision rate
- High-resource settings: ready access to multidisciplinary pain services, graded motor imagery programmes, interventional blocks and SCS
- Limited-resource settings: emphasis shifts to early recognition, low-cost interventions (active rehabilitation, simple analgesics, amitriptyline, vitamin C prophylaxis after wrist fracture) and avoidance of prolonged immobilisation, since advanced interventional and neuromodulation options may be unavailable
Across all major guidance the message is the same: diagnose with the Budapest criteria, exclude mimics, and make function-focused rehabilitation the foundation, escalating to pharmacology, psychology and interventional procedures by response. Differences are mainly in adjuncts (e.g. Dutch free-radical scavengers) and in access to neuromodulation.
MCQ Practice Points
Q: What are the Budapest diagnostic criteria for CRPS? A: Need symptoms in ≥3 of 4 categories (Sensory, Vasomotor, Sudomotor/Edema, Motor/Trophic) plus continuing pain disproportionate to injury. This is the current diagnostic standard. No definitive test confirms CRPS.
Q: What is the best-evidenced prophylaxis for CRPS after fracture? A: Vitamin C 500mg daily for 50 days starting peri-operatively - in the Zollinger dose-response RCT this cut CRPS after distal radius fracture from ~10% to ~2.4%, with no extra benefit from higher doses. The strongest evidence is in wrist fractures; later/foot-ankle data are mixed, but it is cheap and safe.
Q: What is the natural history and prognosis of CRPS-I? A: Most cases (~74% in population data) resolve, often spontaneously, while a minority become chronic and disabling. The classic three-stage model is not validated and should not be quoted as fixed prognosis. Early recognition and function-focused rehabilitation remain the priority.
Q: What is the cornerstone of CRPS treatment? A: Physiotherapy - graded motor imagery, desensitization, mirror therapy, active ROM exercises. This is the cornerstone and must be started early. Medications, sympathetic blocks, and psychological support are also essential.
Q: What is allodynia in CRPS? A: Pain from a normally non-painful stimulus, such as light touch. It contributes to the sensory Budapest category but is not specific to CRPS; neuropathy and nerve injury can also produce allodynia.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 45-year-old woman presents 6 weeks after ankle fracture fixation. She has severe pain out of proportion, allodynia (pain from light touch), temperature asymmetry (2°C difference), and persistent swelling. How do you diagnose and manage this?”
“You are planning ankle fracture fixation in a 50-year-old woman with a history of anxiety. How do you prevent CRPS?”
“A 55-year-old man is referred 9 months after distal radius fixation with persistent burning pain, a cold mottled hand, fixed wrist stiffness and patchy osteopenia on radiographs. He has failed gabapentin and physiotherapy. How do you approach this, and how confident are you in the diagnosis?”
Key Facts
- Population incidence: 5-26 per 100,000 person-years
- Female:Male ratio: 3-4:1; fracture is commonest trigger
- Budapest criteria: symptoms in ≥3 of 4 categories plus signs in ≥2
- Vitamin C 500mg/50 days reduces post-wrist-fracture CRPS
Budapest Criteria
- Sensory: Allodynia, hyperalgesia
- Vasomotor: Temperature/color asymmetry
- Sudomotor/Edema: Swelling, sweating changes
- Motor/Trophic: Decreased ROM, trophic changes
- Need ≥3 of 4 categories plus continuing pain
Prevention
- Vitamin C 500mg daily for 50 days (CRPS ~10% to ~2.4% after wrist #)
- Early mobilization (avoid prolonged immobilization)
- Adequate multimodal analgesia
- Gentle tissue handling
- Start vitamin C peri-operatively
Treatment
- Rehabilitation: graded active use, desensitisation and exposure matched to irritability
- Medications: evidence-limited, phenotype-directed adjuncts with functional targets
- Psychological support: education, coping, pacing and treatment of comorbidity
- Blocks or neuromodulation: selected refractory cases after multidisciplinary review
Prognosis & Staging
- Most CRPS-I cases improve, often spontaneously (~74% in population data)
- Classic acute/dystrophic/atrophic staging is descriptive, NOT validated prognosis
- Cluster analysis supports warm vs cold sub-types, not fixed sequential stages
- Worse outlook: long duration, cold phenotype, established contractures, psychological distress
- Refractory disease - manage in a multidisciplinary pain service; consider SCS trial
Evidence Base
Incidence of CRPS: Dutch Population-Based Study
- Population-based cohort, 600,000 patients in Dutch primary care
- Overall CRPS incidence 26.2 per 100,000 person-years (95% CI 23.0-29.7)
- Females affected at least 3.4 times more often; highest incidence in women aged 61-70
- Upper limb more affected than lower limb; fracture the commonest trigger (44%)
Incidence, Prevalence and Outcome of CRPS-I: Olmsted County
- US population-based study, 74 CRPS-I cases over 1989-1999
- Incidence 5.46 per 100,000 person-years; period prevalence 20.57 per 100,000
- Female:male 4:1, median onset age 46; fracture the commonest trigger (46%)
- 74% of patients underwent resolution, often spontaneously
Vitamin C Prevention of CRPS after Wrist Fracture (Dose-Response RCT)
- Double-blind multicentre RCT, 416 patients with 427 wrist fractures (placebo vs 200, 500 or 1500mg vitamin C daily for 50 days)
- CRPS prevalence 2.4% with vitamin C vs 10.1% with placebo (p=0.002)
- 500mg dose: relative risk 0.17 (95% CI 0.04-0.77); no added benefit from 1500mg
- A daily dose of 500mg for 50 days is recommended
Validation of the Budapest Diagnostic Criteria
- Validation study in 113 CRPS-I and 47 non-CRPS neuropathic pain patients
- Budapest clinical criteria: sensitivity 0.99, specificity 0.68 (vs IASP specificity 0.41)
- Budapest research criteria: highest specificity 0.79
- Four-component structure (sensory, vasomotor, sudomotor/oedema, motor/trophic) drives improved specificity
CRPS: Practical Diagnostic and Treatment Guidelines, 4th Edition
- Interdisciplinary consensus guideline endorsing function-focused rehabilitation as the foundation of care
- Recommends a coordinated rehabilitation-pharmacology-psychology-interventional pathway, escalated by response
- Notes paucity of level 1-2 evidence; most modalities rest on lower-grade evidence and clinical experience
- Emphasises early, function-directed therapy rather than rest/immobilisation
Does Evidence Support Physiotherapy for Adult CRPS-I? Systematic Review
- Systematic review of 11 studies (5 RCTs) on physiotherapy for adult CRPS-I
- Good-to-very-good quality level II evidence that graded motor imagery reduces pain
- No evidence found to support commonly recommended treatments such as stress loading
- Heterogeneity prevented meta-analysis; physiotherapy often combined with medical management
Spinal Cord Stimulation for Chronic Refractory CRPS (RCT)
- RCT: 36 patients SCS plus physiotherapy vs 18 physiotherapy alone (CRPS over 6 months)
- Mean pain fell 2.4cm on a 10cm VAS at 6 months vs +0.2cm in controls (p less than 0.001)
- 39% of SCS patients much improved vs 6% of controls; no significant functional gain
- Complications requiring further procedures in 6 of 24 implanted patients