Benign Intramedullary Cartilage Tumour | Most Common Hand Tumour | Malignant Transformation Risk
- Most common tumour of hand bones - 90% in phalanges and metacarpals
- Lobulated hyaline cartilage with calcifications creating rings-and-arcs pattern on X-ray
- Solitary lesions 1-2% malignant transformation; in enchondromatosis it is 40% overall - and location decides: 15% if confined to hands and feet, 43-46% once long bones or pelvis are involved
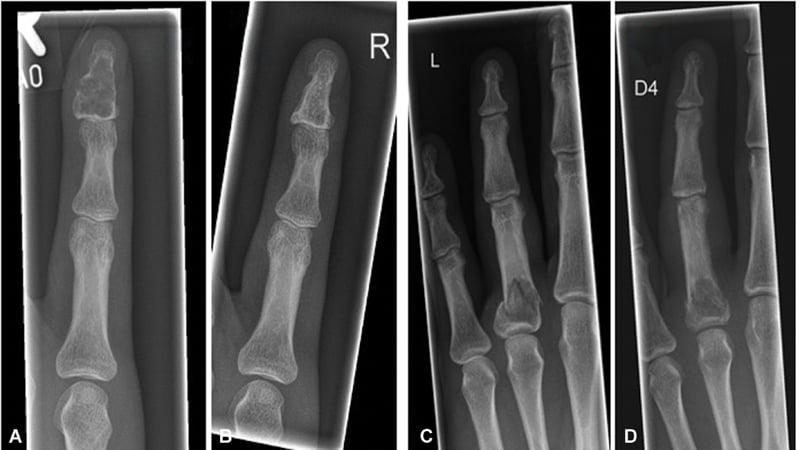
- Pathological fracture through enchondroma is common presentation in hand
- Pain in absence of fracture suggests malignant transformation to chondrosarcoma
- “Key differentiator: asymptomatic enchondroma vs painful chondrosarcoma
- “Rings-and-arcs calcification pattern pathognomonic for cartilage tumours
- “Ollier disease shows unilateral distribution; if bilateral consider Maffucci syndrome
- “Treatment of hand enchondroma: curettage and bone grafting after pathological fracture
Overview and Epidemiology
Enchondroma is a benign intramedullary tumour of hyaline cartilage and the most common tumour of hand bones, making up 50% of them. Most are silent, turning up on a radiograph taken for something else or announcing themselves as a low-energy fracture through a thinned cortex. The clinical work lies with the minority that are not benign, or not benign any longer.
Who. Peak incidence is 20-40 years, with a range of 10 to 60 and equal numbers of men and women.
Where. 90% arise in the tubular bones of the hands and feet. The proximal phalanx is the commonest site, then the metacarpal, then the middle phalanx.
How many. 90% of patients have a single sporadic lesion. The rest have multiple enchondromas, which is a different disease with a different risk and is classified separately.
Pathophysiology and Pathology
Origin. Enchondromas arise from persistent rests of growth plate cartilage that fail to undergo normal enchondral ossification. The islands stay in the medullary cavity and may slowly enlarge. The exact molecular mechanism is unclear, but mutations in isocitrate dehydrogenase (IDH1 and IDH2) have been identified in enchondromas and in secondary chondrosarcomas alike, so the mutation marks the lineage rather than the behaviour: other genetic changes drive malignant transformation.
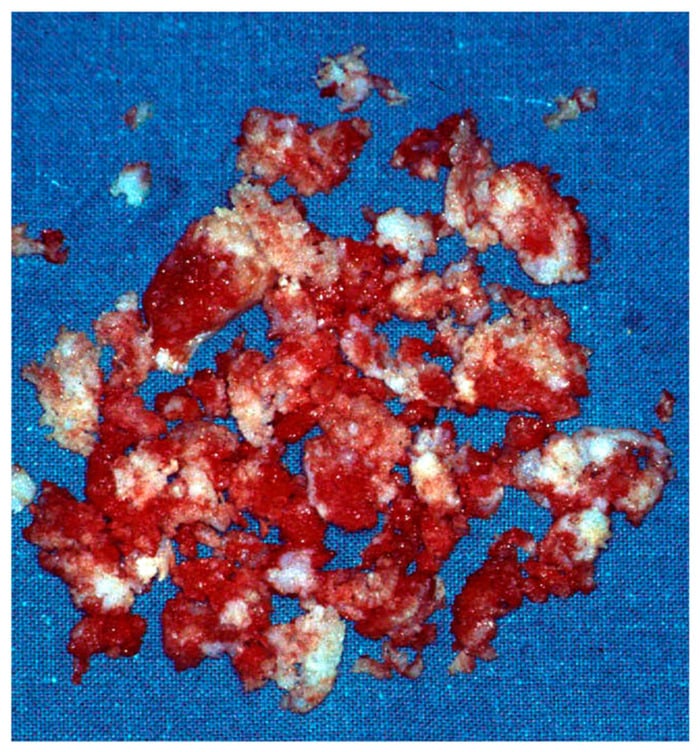
Macroscopically the lesion is lobulated, translucent blue-grey, firm hyaline cartilage in the central medullary cavity, with punctate white calcifications throughout. In hand bones it is typically 1-5cm.
Down the microscope it is hypocellular hyaline cartilage. Small, uniform chondrocytes sit in lacunae with small, regular, single nuclei in abundant matrix, and dystrophic calcification is common. Low cellularity is the reassuring feature.
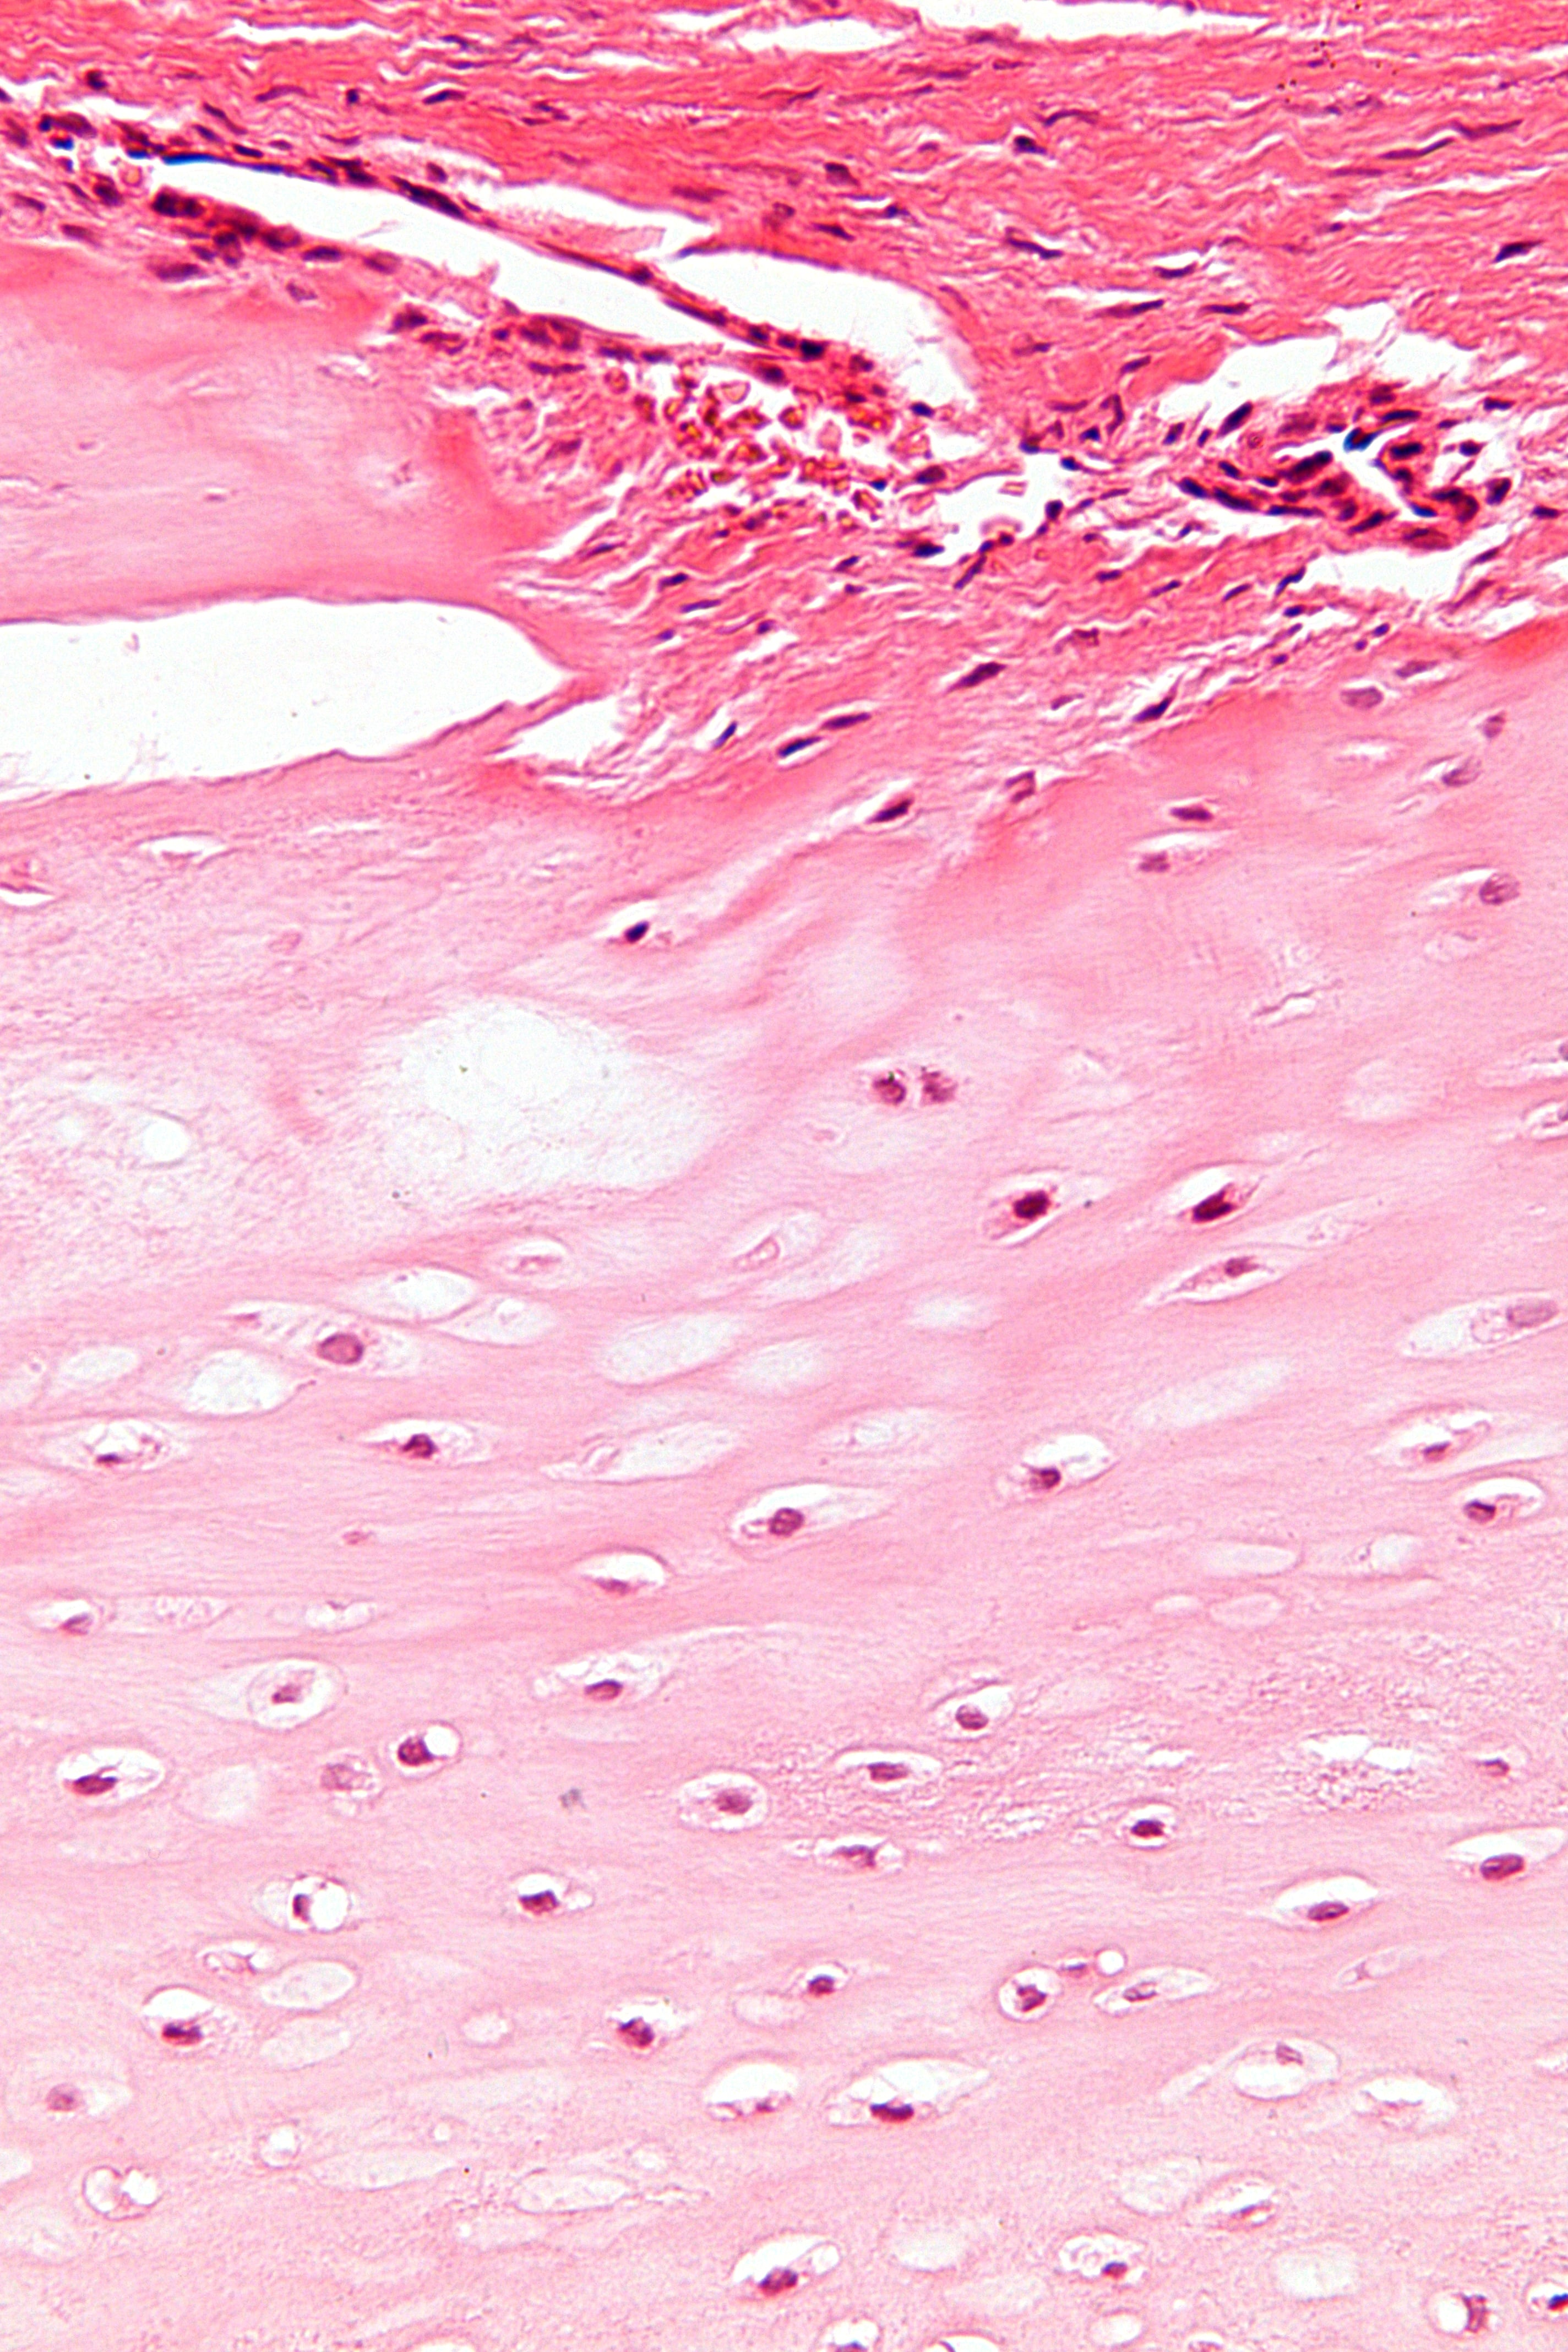
Telling it from low-grade chondrosarcoma on histology is difficult. The features that favour malignancy are increased cellularity, nuclear atypia with enlarged hyperchromatic nuclei, binucleate cells, myxoid degeneration and permeation into surrounding bone. None of them settles the question alone, and clinical and radiological correlation is essential: pain, axial location and a soft-tissue mass are more reliable indicators of malignancy than subtle histological change.
The same histology means different things in different bones, and the hand is the great exception.
- Acral (hand and foot) enchondromas frequently look "atypical" - increased cellularity, plump and binucleate chondrocytes, occasional myxoid change - yet they behave entirely benignly. True chondrosarcoma of the hand is rare.
- A pathologist reading the slide without knowing it is a phalanx may over-call chondrosarcoma, and a benign lesion is then treated with unnecessarily radical surgery, even amputation. The identical cellularity and atypia in a pelvic or proximal-femoral cartilage tumour would genuinely indicate malignancy.
- Always tell the pathologist the exact location, diagnose hand cartilage tumours by clinico-radiological correlation rather than histology alone, and remember the converse: in the axial skeleton and long bones, even subtle atypia with a permeative growth pattern is concerning.
- The same forgiveness applies to the giant ("Takigawa") and protuberant hand variants, which remain benign despite a worrying size or appearance.
A bimorphic ("two-component") tumour in which a low-grade cartilage lesion (enchondroma, atypical cartilaginous tumour or grade 1 chondrosarcoma) develops an abrupt, distinct high-grade non-cartilaginous sarcoma component - typically osteosarcoma-like, fibrosarcoma-like or undifferentiated pleomorphic sarcoma-like. It accounts for roughly 10 percent of chondrosarcomas and occurs in older patients (sixth to eighth decade).
The radiographic clue is a "two-tone" appearance: a calcified, rings-and-arcs low-grade cartilage area sitting next to an aggressive, purely lytic, destructive area with cortical breakthrough and a soft-tissue mass. Seeing those two zones together should immediately raise dedifferentiation, and it dictates the biopsy - sampling only the calcified cartilage under-grades the tumour, so the needle must go into the aggressive lytic zone.
Prognosis is dismal, with 5-year survival roughly 10 to 25 percent. Conventional chondrosarcoma is chemo- and radio-resistant and treated by surgery alone; dedifferentiated chondrosarcoma is managed like a high-grade sarcoma, with wide or radical excision and consideration of chemotherapy, although the survival benefit of chemotherapy remains limited.
Classification
Where it sits. Enchondroma is classified under benign chondrogenic tumours in the WHO Classification of Tumours of Soft Tissue and Bone. The rest of the cartilage family is worth holding in mind, and so is where each member sits: in the medulla, on the surface or in the epiphysis.
- Tumour Type
- Enchondroma
- Behaviour
- Benign, no metastatic potential
- Location
- Medullary cavity
- Tumour Type
- Osteochondroma
- Behaviour
- Benign, 1% malignant transformation
- Location
- Surface (metaphysis)
- Tumour Type
- Chondroblastoma
- Behaviour
- Locally aggressive, rare metastasis
- Location
- Epiphysis
- Tumour Type
- Chondromyxoid fibroma
- Behaviour
- Locally aggressive
- Location
- Metaphysis
- Tumour Type
- Chondrosarcoma Grade 1
- Behaviour
- Low-grade malignant
- Location
- Central medullary
- Tumour Type
- Chondrosarcoma Grade 2-3
- Behaviour
- High-grade malignant
- Location
- Central or periosteal
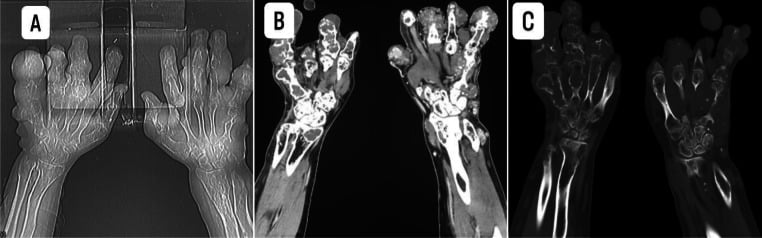
One lesion or many. Ollier disease is multiple enchondromas with a unilateral predominance. Maffucci syndrome is multiple enchondromas plus spindle cell haemangiomas. Neither is inherited: both follow somatic mosaic IDH1/IDH2 mutation. Metachondromatosis is rare and pairs enchondromas with osteochondromas.
How much risk, and driven by what. A solitary lesion carries a 1-2% lifetime risk of malignant transformation. In enchondromatosis the observed figure is 40% overall in Verdegaal's 161-patient series, and site decides it: 15% where disease is confined to the hands and feet, against 43-46% once long bones or the pelvis are involved, with a pelvic odds ratio of 3.8. The older 25-30% figure predates that series. Maffucci syndrome is conventionally held to carry a higher risk still, but the "approaching 100%" figure is not derived in any primary study - Verdegaal's series contained only 17 Maffucci patients and reported no separate rate - so it should not be quoted.
- Definition
- Single isolated lesion
- Malignancy Risk
- 1-2% lifetime
- Surveillance
- Minimal - patient education only
- Definition
- Multiple enchondromas, unilateral predominance
- Malignancy Risk
- 40% overall; 15% hands/feet only, 43-46% if long bones or pelvis involved (pelvic OR 3.8)
- Surveillance
- Stratify surveillance by SITE: hand/foot-only disease needs clinical review; axial or pelvic lesions need lifelong imaging screening
- Definition
- Multiple enchondromas plus spindle cell haemangiomas
- Malignancy Risk
- Conventionally above Ollier's but never separately quantified - do not quote 'nearly 100%'
- Surveillance
- Aggressive surveillance, low threshold for biopsy
Clinical Presentation
How it presents. Half of enchondromas are incidental, found on a film taken for another reason. The commonest symptomatic presentation in the hand is a pathological fracture; otherwise a slow-growing, painless firm swelling of the affected bone. In Ollier disease the presentation may instead be angular deformity or limb length discrepancy.
What you find. The bone is diffusely expanded and the overlying skin is normal, with no erythema or warmth. The mass is firm, fixed to bone and not tender unless the bone has fractured, and movement is limited only by a fracture or a large lesion, with no mechanical block on passive motion.
Systematic Hand Examination
- Diffuse expansion of the affected bone
- Angular deformity if the lesion is large
- Normal overlying skin
- Compare with the contralateral hand
- Firm mass, fixed to bone, non-tender
- Tenderness only if a fracture is present
- Normal temperature
- Radial and ulnar pulses, sensation
- Active range: may be limited by fracture or a large lesion
- Passive range: similar to active, no mechanical block
- Strength reduced if the bone has fractured
- Assess pinch and grip
The red flags. New pain in the absence of trauma is the single most important clinical discriminator between a benign enchondroma and malignant transformation, and it earns an urgent MRI with biopsy considered. The others are progressive enlargement on serial imaging, a palpable soft-tissue extension, an axial or proximal location, age over 40 years at new diagnosis, and the rare systemic symptoms of weight loss and fatigue.
PAINSRed Flags for Malignant Transformation
Hook:If patient has PAINS, think malignant transformation to chondrosarcoma!
Investigations and Imaging
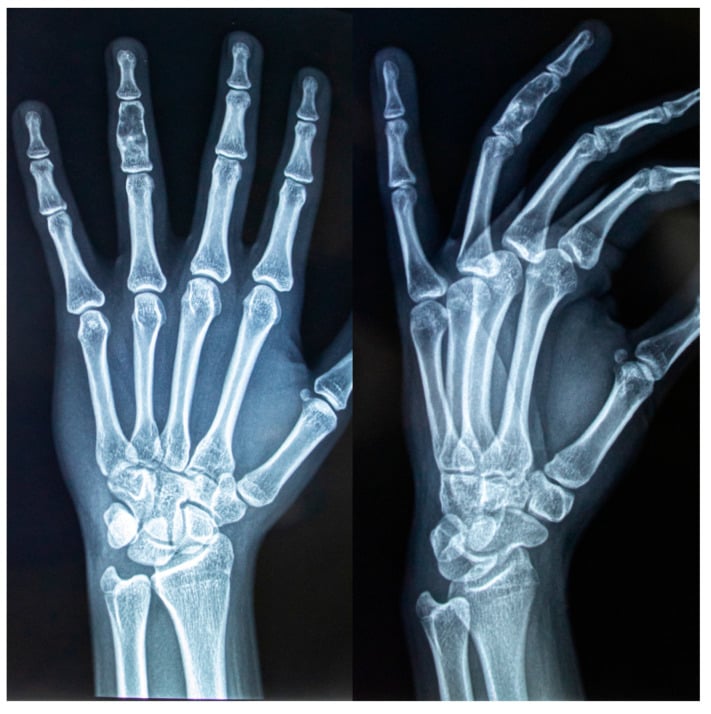
Plain radiography is the diagnostic gold standard. The lesion is an intramedullary lytic defect with punctate calcifications in a rings-and-arcs or popcorn pattern. Four things are read off the film in turn, and each of them is a question about malignancy.
Location. The lesion arises in the centre of the medullary cavity and expands radially. That separates it from a periosteal chondroma, which sits on the surface, and from a bone infarct, whose serpiginous rim follows the dead-bone interface rather than a lobulated tumour edge.
Matrix. Rings-and-arcs, popcorn or stippled calcification reflects mineralisation at the periphery of avascular cartilage lobules: calcified lobules make the rings and the intervening uncalcified fibrous septa make the arcs. It tells you the lesion is cartilage and nothing more - enchondroma, chondrosarcoma and chondroblastoma all show it, so the pattern is pathognomonic of cartilage, not of benignity.
Endosteal scalloping. Benign lesions scallop less than two thirds of cortical thickness. Scalloping beyond two thirds, or frank cortical breakthrough, points to chondrosarcoma, which is why the useful question at the cortex is how deep, not merely is it scalloped.
Periosteal reaction. An uncomplicated enchondroma provokes none. If you see one, something has changed: either a pathological fracture or malignant transformation. In a long bone, new pain without fracture carries the same warning.
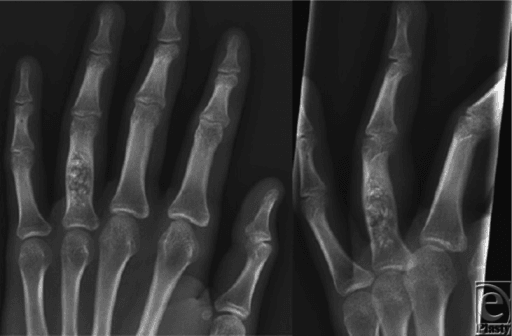
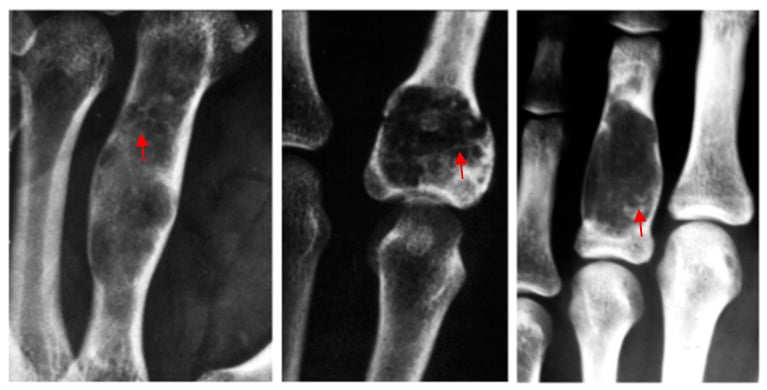
CT quantifies cortical destruction and measures the depth of scalloping in equivocal cases, particularly in axial or proximal long bone lesions.
- Percentage
- Under 1/3 thickness
- Interpretation
- Benign enchondroma
- Management
- Observation if asymptomatic
- Percentage
- 1/3 to 2/3 thickness
- Interpretation
- Likely benign, observe
- Management
- Close surveillance, MRI if symptoms
- Percentage
- Over 2/3 thickness
- Interpretation
- Concerning for malignancy
- Management
- MRI and biopsy required
- Percentage
- 100% (through cortex)
- Interpretation
- Highly suspicious for chondrosarcoma
- Management
- Wide excision with margins
MRI is mandatory for all symptomatic enchondromas and for those in axial or proximal long bone locations, to assess soft-tissue extension and marrow involvement. The features that carry weight are deep endosteal scalloping, cortical breach, a soft-tissue mass and interval growth - and not a cartilage cap, which an intramedullary lesion cannot have and which belongs to osteochondroma.
- Benign enchondroma
- Low to intermediate (cartilage)
- Suspicious for chondrosarcoma
- Heterogeneous with areas of low signal
- Benign enchondroma
- Very high (hyaline cartilage)
- Suspicious for chondrosarcoma
- Heterogeneous (myxoid degeneration)
- Benign enchondroma
- Peripheral enhancement of lobules only
- Suspicious for chondrosarcoma
- Intense irregular enhancement
- Benign enchondroma
- No soft tissue component
- Suspicious for chondrosarcoma
- Soft tissue mass present
- Benign enchondroma
- Typically under 5cm
- Suspicious for chondrosarcoma
- Typically over 5cm
- Benign enchondroma
- Well-defined lobulated contour
- Suspicious for chondrosarcoma
- Ill-defined infiltrative pattern
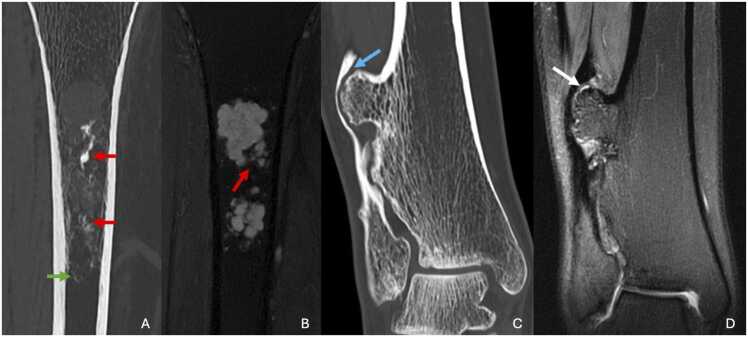
Even with MRI, distinguishing enchondroma from low-grade chondrosarcoma can be impossible on imaging alone. Biopsy is often required but carries the risk of upgrading tumour grade through sampling error, so clinical correlation - pain, patient age, lesion location - is paramount. In equivocal cases, serial imaging over 6 months to assess stability may be safer than biopsy.
Biopsy belongs to the symptomatic lesion, meaning pain without fracture, and to the radiologically suspicious one: axial location, soft-tissue mass or cortical breakthrough. A classic hand lesion needs neither.
- Biopsy Indication
- No biopsy needed
- Technique
- Diagnosis by imaging alone
- Risk
- None
- Biopsy Indication
- Curettage at surgery
- Technique
- Send curettings for histology
- Risk
- Low risk
- Biopsy Indication
- Biopsy required
- Technique
- CT-guided core needle
- Risk
- Tumour seeding, upgrade risk
- Biopsy Indication
- Biopsy before resection
- Technique
- Excisable trajectory, multiple cores
- Risk
- Tumour seeding, sampling error
Differential Diagnosis
The company it keeps. Age, site, the presence or absence of pain and the pattern of calcification separate the intramedullary cartilage lesions from each other and from their mimics.
- Age
- 20-40y
- Location
- Hand, foot (90%)
- Pain
- Painless unless fracture
- X-ray Features
- Rings-and-arcs, under 2/3 scalloping
- Age
- Any age
- Location
- Metaphysis/diaphysis
- Pain
- Painless
- X-ray Features
- Serpiginous calcification, sclerotic rim
- Age
- Under 20y
- Location
- Epiphysis
- Pain
- Painful
- X-ray Features
- Eccentric lytic, thin sclerotic rim
- Age
- 10-30y
- Location
- Metaphysis tibia
- Pain
- Mild pain
- X-ray Features
- Eccentric lytic, scalloped, sclerotic rim
Enchondroma against bone infarct is the pairing that catches candidates, because both are central and both calcify. Enchondroma calcifies in the organised lobular rings-and-arcs pattern, expands the bone and may scallop the cortex. An infarct calcifies serpiginously, following the vascular distribution, is ringed by dense peripheral sclerosis, is often one of several, and neither expands nor scallops the bone. The answer to give is that both show central calcification, but the pattern and the behaviour at the cortex are different.
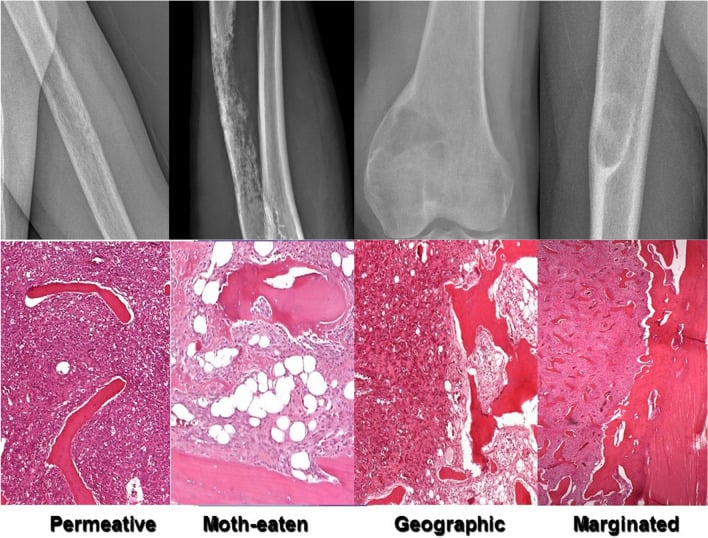
Fibrous dysplasia is the commonest mimic. It gives a ground-glass, sclerotic-rimmed lesion that lacks the discrete punctate and ring-and-arc calcification of cartilage, and it stays low signal on T2 rather than lobular and bright.
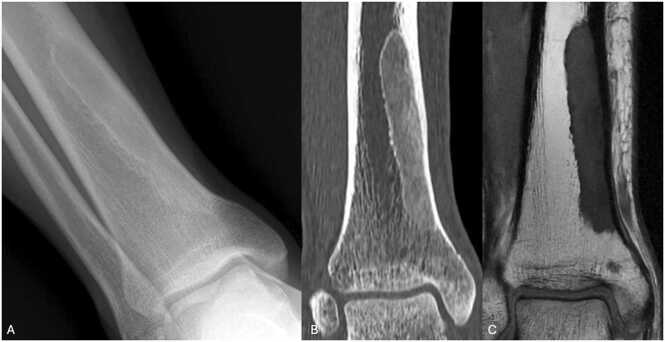
Enchondroma against low-grade chondrosarcoma is the decision the rest of the page turns on, and Murphey's criteria are how it is made. Read them together rather than hunting for one discriminator, and read them in the right bone: they were derived proximal to the metacarpals and metatarsals. In the hand, scalloping and expansion are expected and chondrosarcoma is rare, so applying the criteria there overcalls malignancy.
- Enchondroma (Benign)
- Painless or only with fracture
- Low-Grade Chondrosarcoma
- Pain without trauma
- Management
- Symptom assessment critical
- Enchondroma (Benign)
- Hand, foot (90% in hand)
- Low-Grade Chondrosarcoma
- Pelvis, femur, humerus (axial)
- Management
- Location guides suspicion
- Enchondroma (Benign)
- Under 2/3 scalloping
- Low-Grade Chondrosarcoma
- Over 2/3 or breakthrough
- Management
- Measure on CT
- Enchondroma (Benign)
- Absent
- Low-Grade Chondrosarcoma
- Present on MRI
- Management
- MRI essential for axial lesions
- Enchondroma (Benign)
- Uptake at or below the anterior iliac crest
- Low-Grade Chondrosarcoma
- Marked uptake GREATER than the anterior iliac crest
- Management
- Murphey's sixth criterion - the iliac crest is the internal reference, so read the two together on the same image
- Enchondroma (Benign)
- Hand or foot
- Low-Grade Chondrosarcoma
- Pelvis, scapula, proximal femur or proximal humerus
- Management
- Murphey derived these criteria PROXIMAL to the metacarpals and metatarsals. In the hand, scalloping and expansion are expected and chondrosarcoma is rare, so applying them there overcalls malignancy
Management Algorithm
The fork. A solitary hand lesion with classic benign features is a problem of reassurance and, if it has fractured, of timing. Anything axial or proximal, painful, over 5cm, breaching cortex or arising over the age of 40 is a problem of diagnosis, and it belongs in the imaging-biopsy-pathology pathway before anyone operates. Multiple enchondromatosis is a third path: lifelong surveillance rather than a single decision.
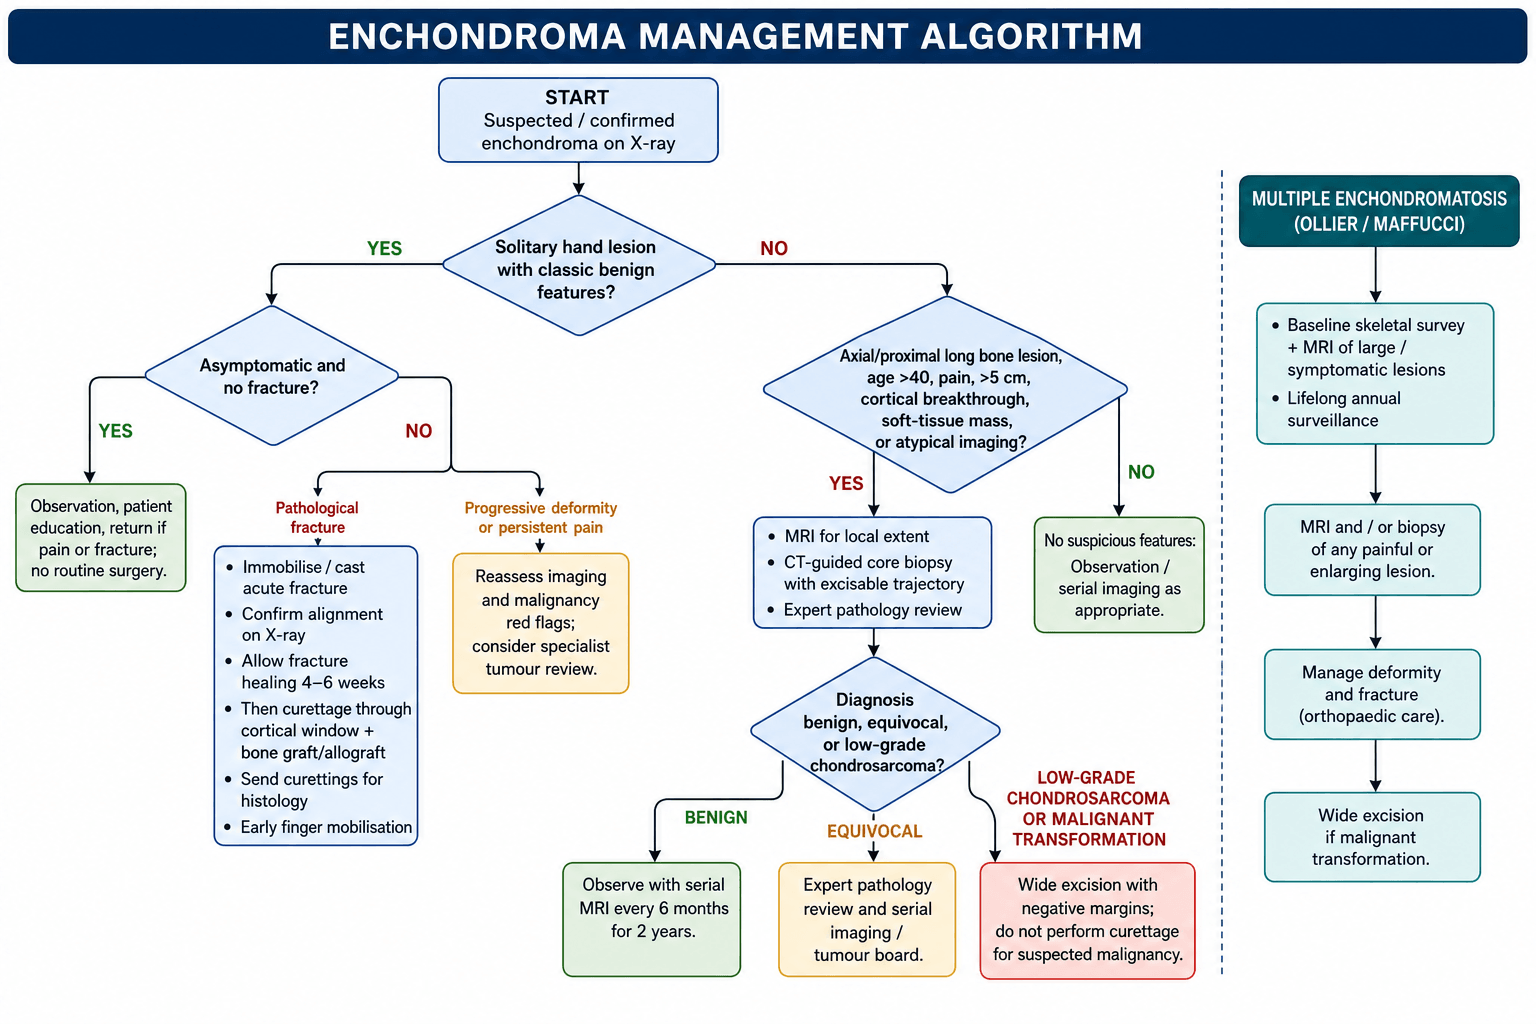
The asymptomatic lesion is observed. An incidentally discovered hand enchondroma with a classic appearance needs no surgery and no further imaging. Confirm the diagnosis on plain films, explain the benign nature, warn about the risk of a pathological fracture, and let the patient come back if anything changes.
Asymptomatic hand enchondromas should NOT be prophylactically excised. Their malignant potential is extremely low (under 1%) and surgery carries risks of stiffness, infection and neurovascular injury, so observation is safe and appropriate. Operate only for (1) pathological fracture, (2) progressive deformity, or (3) the rare development of pain suggesting malignancy.
The fractured lesion is treated in two stages. Treat the fracture first - splint or cast, radiograph to confirm alignment - and let it unite over 4-6 weeks. Curettage and grafting follow once the bone has healed, which is what keeps the re-fracture rate down, and the curettings go to histology to confirm the diagnosis.
Fracture Treatment Algorithm
- Immobilise in splint or cast
- Radiograph to confirm the fracture and assess alignment
- Conservative fracture treatment
- Allow the fracture to heal (4-6 weeks)
- Curettage of the lesion through a cortical window
- Thorough removal of all cartilage
- Bone grafting (autograft or allograft)
- Send curettings for histology
- Early mobilisation, finger exercises from day 1
- Progressive strengthening
- Return to function by 3 months
Surgical Technique
Curettage and bone grafting for hand enchondroma. The operation turns on four things: get to every recess of the cavity, take out all the cartilage, fill the defect so that a recurrence can be seen on a follow-up film, and send everything you remove to the pathologist.
Curettage Technique Steps
Regional or local anaesthesia with an arm tourniquet. Position the hand on a hand table. Mark the cortical window away from any previous fracture site.
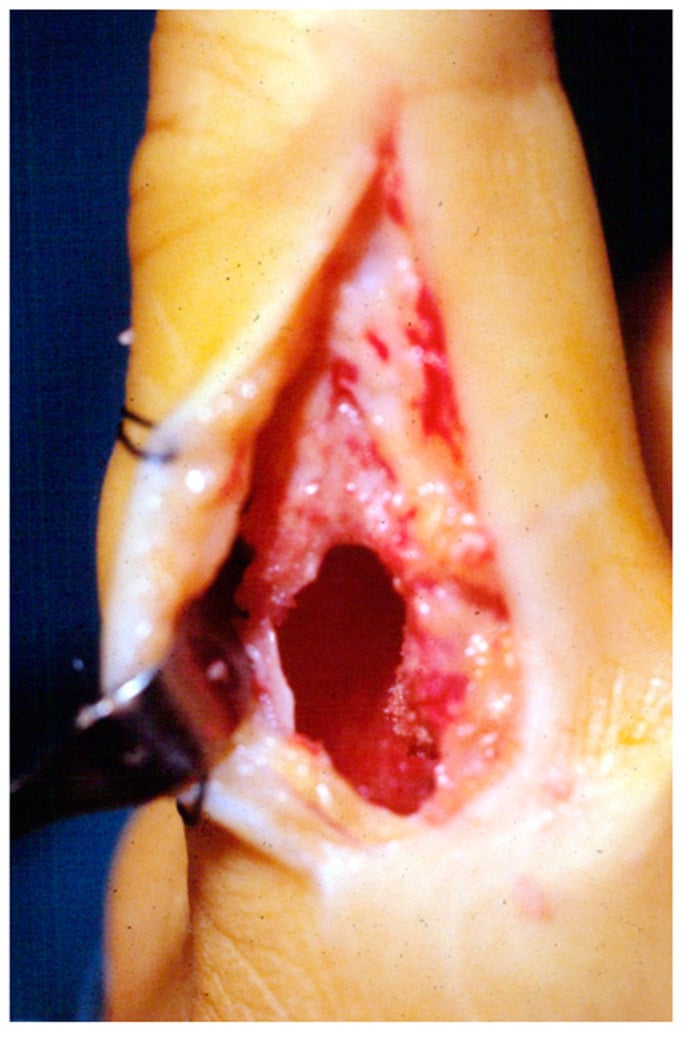
Dorsal longitudinal incision over the affected phalanx or metacarpal. Protect the extensor mechanism by splitting between the central slip and lateral band. Create a cortical window with an oscillating saw (5-8mm).
Thorough curettage of all cartilage with curettes of various sizes, deliberately breaking down the loculi of the lesion. Inspect the cavity to ensure no residual cartilage remains. Optionally take a further 1mm of cavity wall with a high-speed burr.
Pack the cavity with autograft (distal radius preferred) or allograft chips, filling the defect completely so that radiographic surveillance for recurrence is meaningful.
The cortical window needs no closure. Repair the extensor mechanism if split. Skin closure with interrupted nylon, bulky dressing and a finger extension splint.
- Wait for a pathological fracture to heal before curettage: it reduces the re-fracture risk
- Place the window on the dorsal surface, away from the flexor tendons
- Use curettes rather than a high-speed burr alone, which smears cartilage rather than removing it
- Inspect the cavity for residual cartilage fragments before grafting
- Send all curettings for histology
- Fill the defect completely, so that recurrence declares itself on a follow-up radiograph
Autograft: distal radius (Lister's tubercle), or iliac crest for larger defects. Best biological properties, at the cost of donor site morbidity.
Allograft: cancellous chips, no donor morbidity, readily available, with outcomes equivalent to autograft for hand enchondromas.
Synthetic: calcium phosphate or calcium sulfate, an option for small defects, but it may obscure the detection of recurrence.
Complications
What goes wrong after curettage. Recurrence comes from cartilage left behind, and everything else follows from the window, the graft and the time spent immobilised.
- Incidence
- Under 5% (hand), 10-20% (axial)
- Risk Factors
- Incomplete curettage, residual cartilage
- Management
- Revision curettage or wide excision
- Incidence
- 2-5%
- Risk Factors
- Large defect, inadequate bone graft
- Management
- Immobilisation, consider internal fixation
- Incidence
- 10-15%
- Risk Factors
- Prolonged immobilisation, adhesions
- Management
- Aggressive physiotherapy, tenolysis if needed
- Incidence
- 2-3%
- Risk Factors
- Contamination, poor vascularity
- Management
- Antibiotics, debridement if needed
- Incidence
- Under 1%
- Risk Factors
- Iatrogenic during dissection
- Management
- Primary repair if identified
Pathological fracture is a complication of the disease, not of the surgery. Cortical thinning weakens the bone, and 38% of hand enchondromas present with a fracture through it, the proximal phalanx accounting for 40%. There is no way to prevent it; immobilise, let the fracture heal and curette afterwards, and tell the patient at diagnosis that this is what the lesion may do.
If the lesion is suspicious, curettage is inadequate treatment. MRI first to assess soft-tissue extent, then a CT-guided biopsy along an excisable trajectory, then wide excision with negative margins if chondrosarcoma is confirmed.
Postoperative Care
The hand is mobilised early, with finger exercises from day 1 and full activity by 3 months.
Postoperative Rehabilitation Protocol
Bulky dressing with a finger extension splint. Elevate the hand above heart level. Active motion of the uninvolved fingers. Ice for swelling.
Reduce the dressing to a light compressive bandage. Begin active motion of the involved finger within pain tolerance. Buddy tape to the adjacent finger for support.
Gentle active and passive motion, working for full extension and flexion. Refer to hand therapy if stiffness is developing.
Progressive strengthening with putty and grip exercises. Light functional activities permitted. Radiograph at 6 weeks to assess graft incorporation.
Full activity including manual work by 3 months, with no long-term restrictions. Final radiograph to confirm healing and no recurrence.
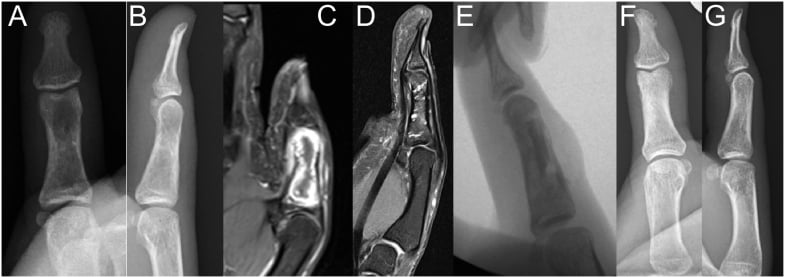
Read the early films with patience. Cancellous bone reconstitutes within about two months, but restoration of normal bone morphology takes up to a year, so a follow-up film that still looks mottled does not mean the operation has failed.
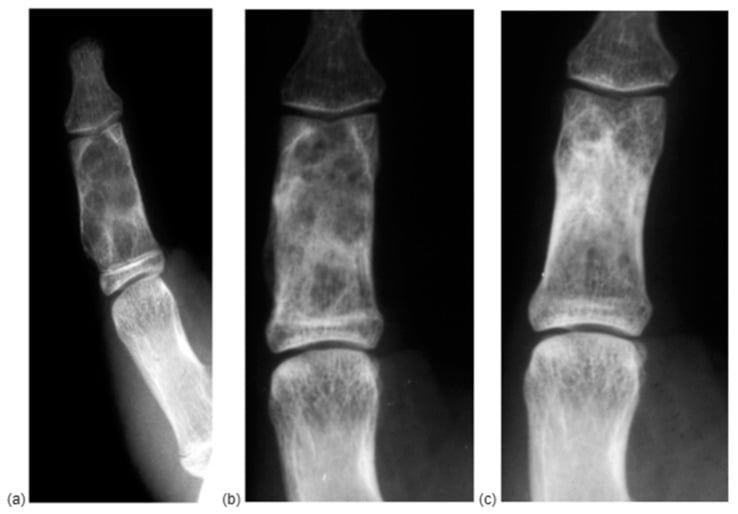
Hand enchondroma after curettage
- Radiographs at 6 weeks and 3 months to confirm graft incorporation
- No routine long-term follow-up needed
- Patient education: return if new pain develops
Axial lesions after curettage
- Serial imaging every 6 months for 2 years
- Annual imaging thereafter for 5 years
- MRI if there is concern about recurrence
Outcomes and Prognosis
Hand lesions do well. Curettage of a hand enchondroma has a low recurrence rate, minimal functional cost and return to full function by 3 months, and a curetted phalangeal lesion can still look durable at six years. Axial and proximal lesions recur more often, because complete removal through a difficult approach is harder to achieve.
Solitary lesions stay benign. The lifetime malignant transformation risk is 1-2%, the hand behaves best of all, and cure is the expectation after curettage. Axial lesions carry the higher risk and need surveillance. Where wide excision is performed for a grade 1 chondrosarcoma, 5-year survival is 90%.
Multiple enchondromatosis is a lifelong condition rather than an episode. Surveillance is lifelong and imaging repeated, and quality of life is impaired by the deformities and the operations they require.
Guidelines, Registries & Global Practice
Global Epidemiology
Enchondroma is among the commonest bone tumours worldwide, but its true frequency is far higher than symptomatic series suggest. Population imaging studies repeatedly find incidental cartilage lesions in roughly 3% of adults, and modern terminology now separates benign enchondroma from atypical cartilaginous tumour (ACT) / grade 1 chondrosarcoma in long bones.
- Figure
- 2.9% (distal femur 2.0%)
- Source / Cohort
- Walden 2008, AJR (PMID 18492914)
- Figure
- 2.8% (some proved ACT/CS1)
- Source / Cohort
- Stomp/Bovée 2015, Eur Radiol (PMID 25994192)
- Figure
- ~0.2%
- Source / Cohort
- Cited in Walden 2008 (PMID 18492914)
- Figure
- 40% (lifelong risk higher)
- Source / Cohort
- Verdegaal 2011, Oncologist (PMID 22147000)
- Figure
- 15%
- Source / Cohort
- Verdegaal 2011 (PMID 22147000)
- Figure
- Odds ratio 3.8
- Source / Cohort
- Verdegaal 2011 (PMID 22147000)
Side-by-Side Guidance: Diagnosis and Surveillance of Long-Bone Cartilage Tumours
There is no single randomised-trial-based guideline; international practice rests on bone-tumour society consensus and large referral-centre series. The major bodies converge on active surveillance for asymptomatic, imaging-benign lesions and referral of any red-flag lesion to a sarcoma unit.
- Core Position on Solitary Cartilage Tumours
- Refer suspected bone sarcoma to a specialist sarcoma centre before biopsy; biopsy through an excisable track; MDT decision-making
- Evidence Level
- Consensus guideline (expert)
- Core Position on Solitary Cartilage Tumours
- Asymptomatic, imaging-typical enchondroma needs no biopsy; suspicious long-bone lesions referred to a bone-tumour unit
- Evidence Level
- Consensus / national pathway
- Core Position on Solitary Cartilage Tumours
- Active surveillance acceptable for ACT/grade 1 lesions of long bones; intralesional curettage preferred over wide resection for low-grade central tumours
- Evidence Level
- Consensus + observational evidence
- Core Position on Solitary Cartilage Tumours
- Clinico-radiological correlation; biopsy reserved for symptomatic or atypical lesions; emphasises pain and deep scalloping as triggers
- Evidence Level
- Consensus / appropriate-use
- Core Position on Solitary Cartilage Tumours
- Defines enchondroma (benign) vs ACT/CS1 (locally aggressive, long bones) - terminology standard underpinning all guidance
- Evidence Level
- Reference standard
Across AAOS, BOOS, ESMO and EMSOS the message is identical: an asymptomatic enchondroma with classic imaging needs reassurance, not biopsy, while any painful, enlarging, deeply scalloping or axial cartilage lesion must be referred to a sarcoma multidisciplinary team before intervention. The shift toward active surveillance for ACT/grade 1 long-bone lesions is the main recent change in practice.
Registries and Practice Variation
There is no dedicated international enchondroma registry. Outcome data derive from sarcoma-unit cohorts and national bone-tumour referral databanks (e.g. the European Musculoskeletal Oncology Society network underpinning Verdegaal 2011). Practice still varies:
- Bone-void management after hand curettage (autograft vs allograft vs cement vs nothing) shows no proven difference in recurrence or complications (Bachoura 2015, PMID 26330779) - choice is surgeon-dependent.
- Long-bone ACT/grade 1: increasing international move from wide resection toward active surveillance or intralesional curettage, but thresholds differ between centres.
- IDH1/IDH2 mutation testing is available in tertiary molecular pathology laboratories and supports diagnosis in difficult cases but is not yet a routine global standard.
- Record a clear pain assessment - the single most important malignancy discriminator.
- Document endosteal scalloping depth (proportion of cortex) on the imaging report.
- Obtain MRI for any symptomatic or axial/proximal lesion before intervention.
- Ensure any biopsy track is excisable at definitive surgery and ideally performed at the treating sarcoma unit.
- Reassure patients with classic hand enchondroma about benign behaviour; advise return if new pain develops.
MCQ Practice Points
Q: What is the most common location for enchondroma and what are its characteristic imaging features?
A: Most common in small bones of the hands and feet (50%), followed by proximal humerus and femur. Imaging: Well-defined lytic lesion in medullary cavity; Chondroid matrix calcification ("rings and arcs," "popcorn" pattern); Endosteal scalloping (less than 2/3 cortical thickness); No periosteal reaction or cortical destruction; Size usually less than 5cm. In long bones, located in metaphysis or metadiaphysis.
Q: How do you differentiate benign enchondroma from low-grade chondrosarcoma?
A: Features favoring malignancy: Size greater than 5cm; Location in axial skeleton or proximal limb girdle; Endosteal scalloping greater than 2/3 cortical thickness; Cortical destruction or soft tissue mass; Pain at rest (not related to pathological fracture); Interval growth on serial imaging; Periosteal reaction. MRI: Enchondroma has peripheral/septal enhancement only; Chondrosarcoma shows diffuse enhancement. When uncertain, biopsy may not differentiate - close surveillance or wide excision based on clinical concern.
Q: What is Ollier disease and Maffucci syndrome, and what is the malignancy risk?
A: Ollier disease: Multiple enchondromas (enchondromatosis), non-hereditary, asymmetric distribution. Maffucci syndrome: Multiple enchondromas + soft tissue spindle cell haemangiomas. Malignancy risk: Ollier - use the measured figure, 40% overall in Verdegaal's 161-patient multicentre cohort, stratified by site (15% confined to hands and feet, 43-46% with long-bone or pelvic disease); the older "25-30%" predates it. Maffucci - conventionally held to be higher, with additional non-skeletal malignancies (mesenchymal ovarian tumours, gliomas), but the "approaching 100%" figure is not derived in any primary study and Verdegaal contained only 17 Maffucci patients with no separate rate reported. Both are driven by somatic mosaic IDH1/IDH2 mutations. Surveillance: clinical review with imaging of any new or symptomatic lesion; any pain or growth warrants investigation for malignant transformation.
Q: What is the standard treatment for solitary enchondroma in the hand?
A: Asymptomatic enchondroma: Observation with serial radiographs. Symptomatic (pain, pathological fracture risk) or post-fracture: Curettage and bone grafting. Technique: Allow fracture to heal first (4-6 weeks), then curettage through cortical window, thorough removal of cartilage, bone graft or cement. Recurrence rate: Less than 5%. Pathological fracture: May treat fracture first, then staged curettage, or combined if stable fixation achievable.
Q: What histological features differentiate enchondroma from chondrosarcoma?
A: Enchondroma: Hypocellular with small, uniform nuclei; Cells in lacunae with minimal atypia; No mitoses; Minimal myxoid change; Lobular architecture with peripheral enchondral ossification. Chondrosarcoma: Hypercellularity; Nuclear atypia, pleomorphism, binucleation; Mitotic figures (in higher grades); Myxoid matrix change; Permeation of surrounding bone trabeculae. Important: Histology alone may not differentiate Grade 1 chondrosarcoma from enchondroma - requires clinico-radiological correlation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old office worker presents with an incidentally discovered 2cm lytic lesion with rings-and-arcs calcification in the proximal phalanx of the middle finger on X-ray taken after minor trauma. The lesion is asymptomatic with no fracture. What is your diagnosis and management?”
“A 30-year-old manual laborer presents with acute pain and swelling of the right ring finger after lifting a heavy box. X-ray shows a displaced fracture through a 2.5cm lytic lesion with rings-and-arcs calcification in the proximal phalanx. How do you manage this patient?”
“A 45-year-old woman presents with 3 months of progressive thigh pain with no trauma. X-ray shows a 6cm intramedullary lytic lesion with rings-and-arcs calcification in the proximal femur with cortical scalloping over 2/3 thickness. MRI shows high T2 signal with some soft tissue component. How do you proceed?”
Key Facts
- Most common hand bone tumor (50%), benign intramedullary cartilage
- Peak age 20-40 years, equal male-female
- 90% in tubular bones of hands and feet (phalanges, metacarpals)
- Rings-and-arcs calcification pathognomonic on X-ray
Diagnosis
- X-ray: central medullary lytic with rings-and-arcs calcification
- Endosteal scalloping under 2/3 cortical thickness is benign
- MRI for symptomatic/axial lesions: high T2 signal cartilage
- Biopsy only if pain, axial location, or suspicious features
Red Flags for Malignancy
- Pain without trauma (key clinical red flag)
- Axial or proximal long bone location (pelvis, femur, humerus)
- Cortical scalloping greater than 2/3 or breakthrough
- Soft tissue mass on MRI, size over 5cm
Management
- Asymptomatic hand: observation only, no surgery
- Pathological fracture: immobilize, delayed curettage after healing
- Curettage technique: cortical window, thorough curettage, bone graft
- Suspected chondrosarcoma: wide excision with 5-10mm margins
Multiple Enchondromatosis
- Ollier disease: multiple unilateral; 40% overall malignancy risk (Verdegaal), site-stratified 15% to 46%
- Maffucci syndrome: enchondromas plus spindle cell haemangiomas; high risk, conventionally above Ollier's, but not separately quantified - avoid 'nearly 100%'
- Lifelong surveillance required for both syndromes
- IDH1/IDH2 mutations in 87% of enchondromas and chondrosarcomas
Key Outcomes
- Hand curettage: under 5% recurrence, excellent function
- Solitary enchondroma: 1-2% lifetime malignant transformation
- Low-grade chondrosarcoma: 90% 5-year survival with wide excision
- Chondrosarcoma does NOT respond to chemotherapy or radiation
Evidence Base and Key Studies
Chondrosarcoma Risk in Ollier Disease and Maffucci Syndrome (Landmark Multicentre Cohort)
- International multicentre study of 161 patients (144 Ollier disease, 17 Maffucci syndrome) from 13 European centres
- Overall observed incidence of secondary chondrosarcoma was 40% (age-dependent, rising as a lifelong risk)
- Disease confined to hands and feet only (18% of patients) carried the lowest risk - chondrosarcoma in just 15%
- Pelvic enchondromas markedly increased malignant risk (odds ratio 3.8) - patients with long-bone or axial lesions need regular screening
- Maffucci syndrome patients carry additional risk of vascular malignancy alongside chondrosarcoma
Enchondroma vs Chondrosarcoma in the Appendicular Skeleton: Differentiating Features
- Large series of 187 appendicular lesions (92 enchondromas, 95 chondrosarcomas) with multimodality imaging review
- Lesion-related pain, deep endosteal scalloping (greater than two-thirds cortical thickness), cortical destruction and soft-tissue mass all strongly favoured chondrosarcoma
- Periosteal reaction on radiographs and marked radionuclide uptake (greater than anterior iliac crest) also discriminated malignancy
- Combined clinical and imaging criteria distinguished appendicular enchondroma from chondrosarcoma in at least 90% of cases
Somatic Mosaic IDH1/IDH2 Mutations in Enchondromatosis (Defining Molecular Study)
- Somatic heterozygous IDH1 (predominant) or IDH2 mutations found in 87% of enchondromas and 70% of spindle cell haemangiomas
- Mutations were somatic mosaic, not germline - explaining the non-hereditary, mosaic pattern of Ollier disease and Maffucci syndrome
- 81% of Ollier and 77% of Maffucci patients carried IDH1/IDH2 mutations; identical mutations were present across separate lesions in the same patient
- IDH mutation drove DNA hypermethylation and gene downregulation; the same mutations also occurred in 40% of solitary central cartilage tumours and chondrosarcoma cell lines
Curettage and Allograft for Hand Enchondroma: Range of Motion and Recurrence
- Retrospective series of 111 hand enchondromas in 104 patients treated by curettage and cancellous allograft without internal fixation or adjuvant
- 81% of patients achieved full range of motion; preoperative pathological fracture predicted worse postoperative extension (reduced ROM in 28% vs 15%)
- Local recurrence developed in 5 of 50 (10%) patients with at least 2 years follow-up
- Recurrence was concentrated in giant-form (Takigawa) lesions (43%) and Ollier disease (23%); 16% of the cohort had Ollier disease
Hand Enchondroma Curettage Without Void Augmentation: Series and Systematic Review
- Systematic review of 22 studies (591 patients, 609 lesions) plus an institutional series of 26 lesions
- Complication rates were low and did not differ significantly between curettage alone, autograft, osteoconductive substitute, or cement augmentation (0.7% to 3.5%)
- Recurrence rates were not significantly different across void-management strategies
- Curettage alone is an effective, inexpensive option for most hand enchondromas
Incidental Enchondromas on Knee MRI: Population Prevalence
- Incidental enchondromas were present on 2.9% of 449 consecutive routine knee MRI examinations
- Most common in the distal femur (2.0%), then proximal tibia (0.7%) and proximal fibula (0.2%)
- Average lesion size 1.9 cm; 57% were under 1 cm and 92% lay in the metaphysis or diaphysis
- MRI prevalence far exceeded the historical autopsy figure (0.2%), reflecting greater MRI sensitivity; no aggressive features suggesting chondrosarcoma were seen