Malignant Spindle Cell Tumour | No Matrix Production | Diagnosis of Exclusion
- Fibrosarcoma is a malignant spindle cell tumour producing collagen but NO osteoid or chondroid matrix
- Diagnosis of exclusion requiring extensive immunohistochemistry to rule out other spindle cell tumours
- Herringbone pattern of spindle cells in fascicles is the classic histological appearance
- Secondary fibrosarcoma arises in Paget's disease (most common), post-radiation, bone infarct, or chronic osteomyelitis
- Treatment is wide surgical resection; chemotherapy role limited compared to osteosarcoma
- “Incidence has decreased as immunohistochemistry improves - many cases reclassified as UPS or other entities
- “Must exclude dedifferentiated osteosarcoma (look for focal osteoid), synovial sarcoma (SS18-SSX fusion), and metastatic carcinoma
- “Post-radiation sarcoma requires latency period of at least 3-5 years and arises in previously irradiated field
- “Prognosis is grade-dependent, but be careful with the numbers: the two largest series (Huvos, 130 patients; Papagelopoulos, 92) report 5-year survival of only 34% and 33.4%, and both span decades in which many cases would now be reclassified. No cited study on this page reports a modern survival figure for true fibrosarcoma of bone
Overview and Epidemiology
Fibrosarcoma of bone is a rare primary malignant spindle cell tumour that produces collagen but no osteoid or chondroid matrix. It makes up less than 5% of primary bone sarcomas, and it is a diagnosis of exclusion: it has no specific positive marker, so every other spindle cell tumour has to be ruled out first.
A shrinking diagnosis. Incidence has fallen dramatically over the past 30 years as immunohistochemistry and molecular testing have improved, which suggests that many historical cases were misclassified. Many tumours once called fibrosarcoma are now reclassified as undifferentiated pleomorphic sarcoma (UPS), synovial sarcoma, leiomyosarcoma or dedifferentiated chondrosarcoma, and the WHO trend is toward "undifferentiated/spindle cell sarcoma NOS". Whether true fibrosarcoma is a distinct biological entity or a diagnostic residuum remains debated.
Why it still matters. The diagnosis demands an extensive work-up to rule out other spindle cell tumours, a secondary fibrosarcoma signals malignant transformation of pre-existing bone pathology, and treatment differs from osteosarcoma, with a limited role for chemotherapy.
Who. Peak incidence is at 30-50 years, with a range of 10-80 years, and there is no significant sex predilection (1:1).
Where. The femur and tibia are the most common sites, and any bone can be affected:
- Femur 30%, tibia 25%, humerus 15%
- Axial sites (pelvis, mandible, spine) are uncommon
- Metaphyseal most often, sometimes diaphyseal
- Central (medullary) tumours are more common than surface (periosteal) ones
Primary and secondary. A primary fibrosarcoma arises de novo in normal bone. A secondary one arises in abnormal bone, and secondary tumours have a worse prognosis than primary ones. The substrates are:
- Paget's disease, the most common secondary cause, with a 1% sarcomatous degeneration rate
- Radiation, after a latency of 3-20 years, in the irradiated field
- Bone infarct, a rare substrate
- Chronic osteomyelitis (very rare), and fibrous dysplasia
- Primary Fibrosarcoma
- None (de novo in normal bone)
- Secondary Fibrosarcoma
- Paget's, radiation, infarct, osteomyelitis
- Primary Fibrosarcoma
- 30-50 years typically
- Secondary Fibrosarcoma
- Older (over 50 years for Paget's, radiation)
- Primary Fibrosarcoma
- Not applicable
- Secondary Fibrosarcoma
- 3-20 years for radiation, variable for Paget's
- Primary Fibrosarcoma
- Grade-dependent
- Secondary Fibrosarcoma
- Worse; no cited series on this page quantifies it separately for fibrosarcoma
PRICSecondary Fibrosarcoma Causes
Hook:PRIC causes: Paget's most common, Radiation with latency, Infarct chronic, Chronic infection!
Infantile Fibrosarcoma: A Different Disease With the Same Name
The single most important distinction on this page. Infantile (congenital) fibrosarcoma shares a name and a herringbone architecture with adult fibrosarcoma, and differs from it in genetics, behaviour, treatment and, above all, prognosis. Confusing the two is a serious error in both directions: it either terrifies the parents of a child who will almost certainly do well, or produces dangerous complacency about an adult tumour.
- Infantile fibrosarcoma
- Under 2 years; often congenital or in the first months of life
- Adult fibrosarcoma
- Fourth to sixth decade
- Infantile fibrosarcoma
- Soft tissue of the distal extremities; bone involvement is secondary
- Adult fibrosarcoma
- Bone (this page) or deep soft tissue
- Infantile fibrosarcoma
- ETV6-NTRK3 fusion from t(12;15)(p13;q25) in the large majority; some carry other kinase fusions
- Adult fibrosarcoma
- No defining fusion - it is a diagnosis of exclusion once every other spindle-cell sarcoma has been excluded
- Infantile fibrosarcoma
- Locally aggressive; metastasis is uncommon
- Adult fibrosarcoma
- Pulmonary metastasis in 30-40% of high-grade tumours; metastases in 68% of stage I-II patients in the Mayo series
- Infantile fibrosarcoma
- Complete surgical excision where it can be achieved without mutilation
- Adult fibrosarcoma
- Wide en-bloc resection
- Infantile fibrosarcoma
- Chemotherapy for unresectable disease, and TRK inhibitors (larotrectinib, entrectinib) for NTRK-fusion tumours - often used to shrink a tumour to make limb-preserving surgery possible
- Adult fibrosarcoma
- Chemotherapy is of modest and unproven benefit; no targeted agent
- Infantile fibrosarcoma
- Excellent - the great majority survive long term
- Adult fibrosarcoma
- Poor: 34% and 33.4% at five years in the two largest series
Why the genetics change the operation. An ETV6-NTRK3-positive tumour responds to a TRK inhibitor. In an infant, then, the fusion is confirmed first, and if the tumour cannot be removed without amputating or sacrificing a critical structure, it is treated first and the surgeon operates into a smaller tumour. Fusion testing therefore has to happen before the operation is planned, not once the specimen comes back. The same logic now applies to any adult spindle-cell sarcoma found to carry an NTRK fusion, which is rare but actionable and is a reason to test when the histology is unclassifiable.
A herringbone spindle-cell sarcoma in a neonate and one in a fifty-year-old are different diseases. The question that separates them at the bench is the fusion, and the question that separates them at the bedside is the age. If a page, a viva answer or a parent conversation quotes a five-year survival figure, it must first say which of the two it is describing.
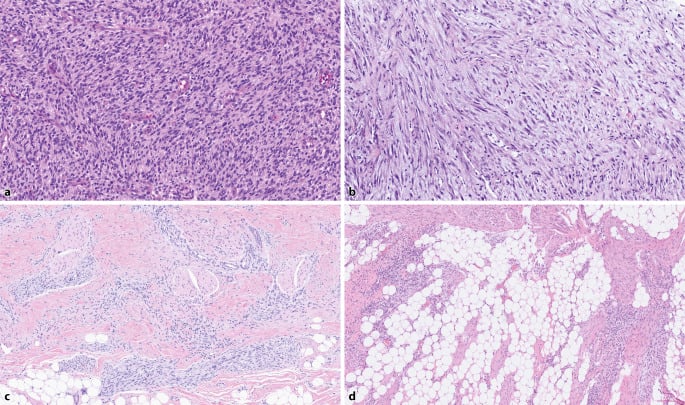
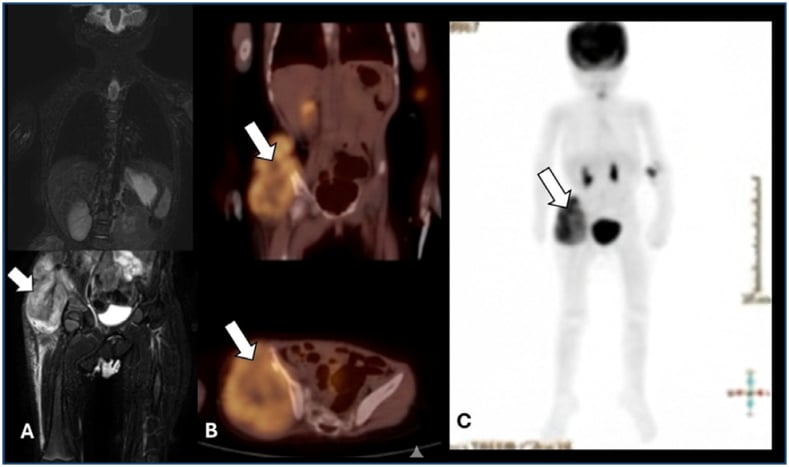
Pathology and Grading
Pathogenesis. Fibrosarcoma arises from primitive mesenchymal cells that differentiate along a fibroblastic lineage, producing collagen but no bone or cartilage matrix. The molecular pathogenesis is incompletely understood. Complex karyotypes are typical but non-specific, and there is no consistent chromosomal translocation, unlike synovial sarcoma or Ewing sarcoma, and that absence of a genetic signature contributes to the diagnostic difficulty.
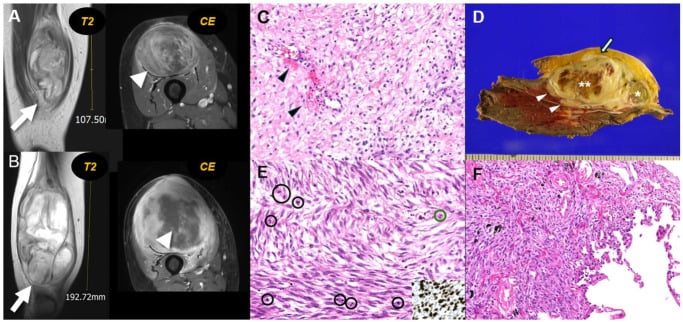
What the microscope shows. Spindle cells, elongated fibroblasts with tapered nuclei, are arranged in fascicles that intersect at acute angles, the herringbone pattern. Collagen production varies, vascularity is variable without a specific pattern, and there is no osteoid or chondroid matrix. That absence is the defining feature: even focal osteoid excludes the diagnosis and suggests osteosarcoma, so extensive sampling is mandatory.
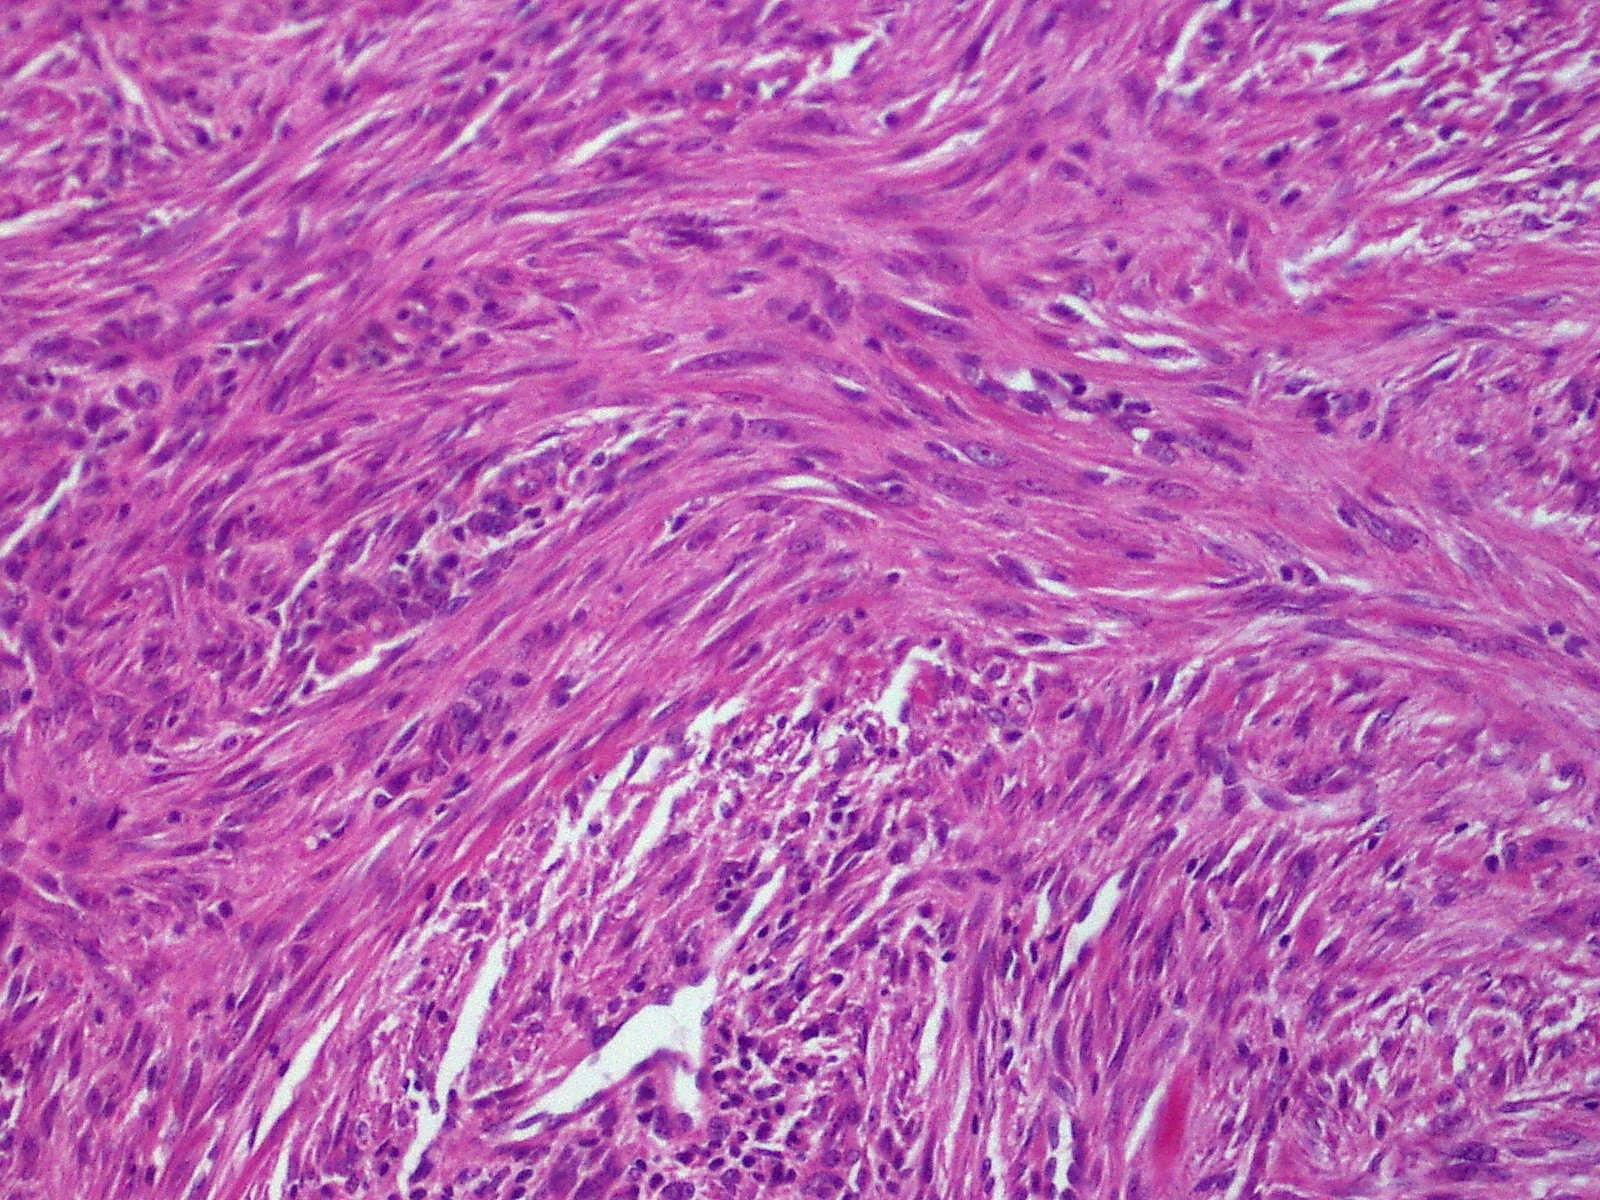
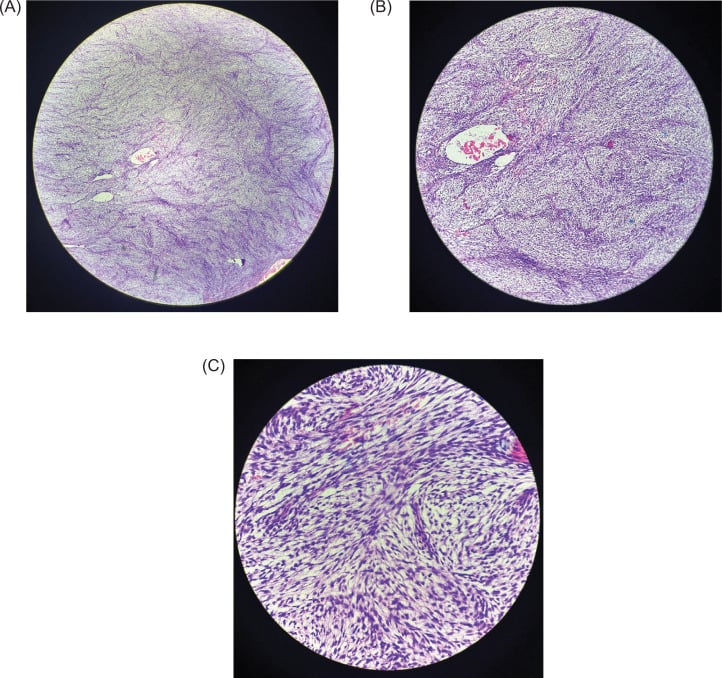
A diagnosis of exclusion. Fibrosarcoma has no specific positive immunohistochemical marker. The diagnosis requires:
- Spindle cell morphology with collagen production
- Absence of osteoid or chondroid matrix on extensive sampling
- Negative immunostains for other entities
- Absence of specific genetic translocations
Immunohistochemistry and molecular testing are therefore used to exclude, and many historical cases have been reclassified as UPS or other specific entities this way.
- Result in fibrosarcoma
- Positive
- What it excludes
- Nothing - a nonspecific mesenchymal marker
- Result in fibrosarcoma
- Negative
- What it excludes
- Nerve sheath tumour
- Result in fibrosarcoma
- Negative
- What it excludes
- Carcinoma, synovial sarcoma
- Result in fibrosarcoma
- Negative
- What it excludes
- Muscle tumours
- Result in fibrosarcoma
- Negative
- What it excludes
- Ewing sarcoma
- Result in fibrosarcoma
- Negative / absent
- What it excludes
- Dedifferentiated liposarcoma
- Result in fibrosarcoma
- Absent
- What it excludes
- Synovial sarcoma
- Result in fibrosarcoma
- Absent
- What it excludes
- Low-grade fibromyxoid sarcoma
Grade. Grade is the strongest prognostic factor, and it is read from cellularity, the organisation of the herringbone, nuclear atypia, mitoses, collagen and necrosis. Low-grade tumours carry the best outlook and high-grade the worst.
- Low-Grade
- Moderate, uniform distribution
- Intermediate-Grade
- Increased, variable
- High-Grade
- High, densely packed cells
- Low-Grade
- Well-organised fascicles
- Intermediate-Grade
- Less organised, focal disruption
- High-Grade
- Disorganised, sheet-like areas
- Low-Grade
- Mild, uniform nuclei
- Intermediate-Grade
- Moderate pleomorphism
- High-Grade
- Marked pleomorphism, variation
- Low-Grade
- Less than 5 per 10 HPF
- Intermediate-Grade
- 5-10 per 10 HPF
- High-Grade
- Greater than 10 per 10 HPF
- Low-Grade
- Abundant, dense
- Intermediate-Grade
- Variable amount
- High-Grade
- Sparse, immature
- Low-Grade
- Absent
- Intermediate-Grade
- Focal (less than 10%)
- High-Grade
- Extensive (over 10%)
The FNCLCC grade. The Fédération Nationale des Centres de Lutte Contre le Cancer grade is the standard, reproducible sarcoma grade. It scores three parameters and adds them:
- Tumour differentiation, 1-3: 1 closely resembles normal adult mesenchymal tissue (well differentiated), through to 3 for undifferentiated, embryonal or uncertain-lineage sarcomas
- Mitotic count, 1-3: 1 = 0-9, 2 = 10-19, 3 = 20 or more mitoses per 10 high-power fields
- Necrosis, 0-2: 0 = none, 1 = under 50%, 2 = 50% or more
- Total: 2-3 = grade 1 (low), 4-5 = grade 2 (intermediate), 6-8 = grade 3 (high)
How the two fit together. The descriptive table above covers the features the FNCLCC formalises, and it is usually the mitotic count and necrosis that push a fibrosarcoma into the high-grade group. Several schemes are in use (FNCLCC, three-tier and older Broders-type systems), and the threshold for calling a tumour high grade and escalating treatment is not standardised. The grade feeds the Enneking stage (G1 versus G2) and the decision whether to consider adjuvant chemotherapy.
The limits of grading. The FNCLCC was derived largely for soft-tissue sarcoma and applied to bone by extension, interobserver variability in the differentiation score is real, and it performs less well for some translocation-associated sarcomas. Grade is therefore combined with the full histological and molecular assessment, not a substitute for it.
Investigations and Staging
Radiographs. The plain radiograph is the initial assessment and contributes to surgical planning. It shows a destructive lytic lesion, geographic in low-grade tumours through moth-eaten to permeative in high-grade ones; the higher the grade, the more aggressive it looks. There is no matrix calcification or ossification, which would suggest osteosarcoma or chondrosarcoma. Periosteal reaction is variable and may include a Codman triangle in aggressive cases, and a soft-tissue mass is often visible once the cortex is breached.
Through a pathological fracture. The fracture is transverse or oblique through the lesion, with variable displacement. It may force a staged procedure, stabilisation and then resection, and whether it worsens the prognosis is unclear.
CT. Superior bone detail makes local CT essential for surgical planning. Acquire thin slices (1mm or less) with bone and soft-tissue windows and multiplanar reconstruction, and assess:
- The medullary destruction pattern
- Cortical breakthrough, its location and extent
- The size and margins of the soft-tissue mass
- The relationship to the neurovascular bundle
- Skip lesions, rare but important to detect
CT chest is mandatory for staging, because the lung is the most common metastatic site for bone sarcomas. Nodules over 5mm are suspicious, and the scan is the baseline for follow-up comparison.
MRI is the modality of choice for local staging, surgical planning and intramedullary extent. Its soft-tissue contrast shows involvement of muscle, nerve and vessels.
- Signal Intensity
- Low to intermediate signal (isointense to muscle)
- Clinical Significance
- Defines anatomical extent, marrow involvement
- Signal Intensity
- High signal (heterogeneous)
- Clinical Significance
- Soft tissue extent, oedema pattern
- Signal Intensity
- Heterogeneous enhancement
- Clinical Significance
- Viable tumour (enhances), necrosis (does not enhance)
- Signal Intensity
- High signal
- Clinical Significance
- Sensitive for marrow oedema, extent beyond gross tumour
- Signal Intensity
- High signal in tumour
- Clinical Significance
- Differentiates oedema from tumour, soft tissue extent
Whole-body staging and bloods. Whole-body imaging, PET-CT or a bone scan, looks for skip lesions and bone metastases, and PET-CT is an alternative route to whole-body staging. Blood tests (alkaline phosphatase and LDH) give a baseline and help exclude other pathology; alkaline phosphatase is usually normal unless there is Paget's disease.
Biopsy. Histological confirmation is mandatory before definitive treatment. The biopsy is performed by the treating surgeon, or in coordination with the surgical team, so that its trajectory can be excised at the definitive operation.
- Core needle preferred, CT- or fluoroscopy-guided (11-14 gauge): less contamination than open biopsy
- 3-5 cores minimum, from different areas
- Trajectory excisable at definitive resection: longitudinal in the extremity
- Avoid transarticular or transneural trajectories
- Avoid haematoma and contamination: meticulous haemostasis, and avoid a drain if possible
- Send fresh tissue for molecular studies if available, and for culture if infection is suspected
The pathology. Review by an expert musculoskeletal pathologist is mandatory. The specimen needs multiple sections to exclude osteoid, the immunohistochemistry panel, molecular studies if the diagnosis is uncertain, and a grade (low, intermediate or high).
Enneking (MSTS) surgical staging. The Enneking / Musculoskeletal Tumor Society staging of a malignant bone or soft-tissue sarcoma combines three axes. It is distinct from the AJCC TNM system, but it is the framework orthopaedic examiners expect for bone sarcoma.
- Grade (G): G1 low grade, G2 high grade (histological and biological aggressiveness)
- Site (T): T1 intracompartmental, confined within the bone or compartment of origin; T2 extracompartmental, through the cortex or compartment into surrounding tissue
- Metastasis (M): M0 none, M1 regional or distant metastasis
The axes combine into stages:
- Stage I (low grade, M0): IA = G1 T1 M0, IB = G1 T2 M0
- Stage II (high grade, M0): IIA = G2 T1 M0, IIB = G2 T2 M0
- Stage III: any G, any T, M1
Why the stage matters here. Most fibrosarcomas present as stage IIB, high grade with cortical breakthrough into a soft-tissue mass and no metastases. That is the dominant group in the Papagelopoulos series and the reason the standard operation is a wide en-bloc resection. A low-grade intracompartmental tumour (IA or IB) carries a much better outlook, while stage III disease shifts the goal toward systemic control.
Clinical Presentation
Pain. The presentation is non-specific, like that of other primary bone malignancies. Progressive pain is the most common initial symptom, often present for weeks to months before diagnosis. Unlike the pain of benign lesions it is typically progressive and not related to activity. It is constant, moderate to severe, may be present at rest and may worsen at night, and responds poorly to NSAIDs; if a nerve is compressed, it may follow that nerve's distribution.
Other presentations. Systemic features (fever, weight loss) are usually absent, and neurological symptoms are rare unless a nerve is compressed.
- Pathological fracture in 10-20%
- Swelling or a palpable mass when there is soft-tissue extension
- Limited motion when the tumour is near a joint
Examination. Look for swelling, which is visible when the soft-tissue component is large, skin that is usually normal but may show venous prominence, an antalgic gait if the lower limb is affected, and possibly angular deformity after a pathological fracture. Feel for localised bony tenderness and a firm mass, fixed to bone if large or through the cortex; the temperature is normal, not warm as in infection. Assess distal pulses, sensation and motor function.
Movement and the regional examination. Range of motion may be limited by pain if the lesion is juxta-articular, strength is reduced if muscle is involved or by pain, and the limb is checked for a pathological fracture. Lymph nodes are usually not enlarged, because bone sarcomas rarely spread by lymphatics. Examine the chest for metastases, though these are rarely found on examination.
Any of these needs immediate evaluation.
- Progressive neurological deficit suggesting spinal cord or nerve compression
- Acute onset pain with deformity suggesting pathological fracture
- Rapid increase in swelling suggesting aggressive growth or haemorrhage
- Systemic symptoms (fever, weight loss) suggesting infection or disseminated disease
Suspecting a secondary tumour. The clues lie in the history of the bone.
- Clinical Clue
- Known Paget's with sudden pain increase
- Typical Presentation
- Elderly patient, alkaline phosphatase elevated, rapid progression
- Clinical Clue
- Prior radiation therapy 3-20 years ago
- Typical Presentation
- Lesion arises in previously irradiated field, latency period essential
- Clinical Clue
- Known chronic infarct with new symptoms
- Typical Presentation
- Sickle cell disease, steroid use, expanding infarct on imaging
- Clinical Clue
- Long-standing draining sinus, new mass
- Typical Presentation
- Years of infection, sudden change in character, biopsy needed
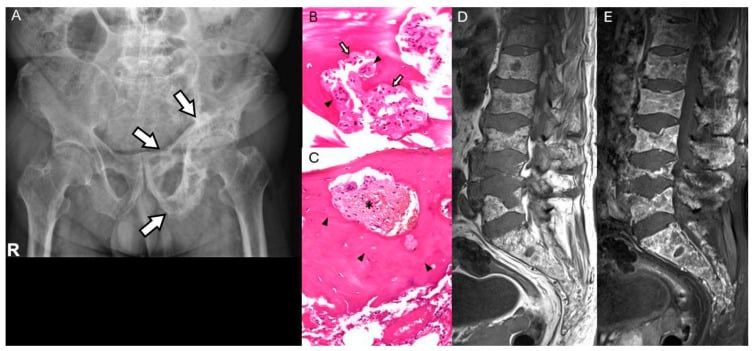

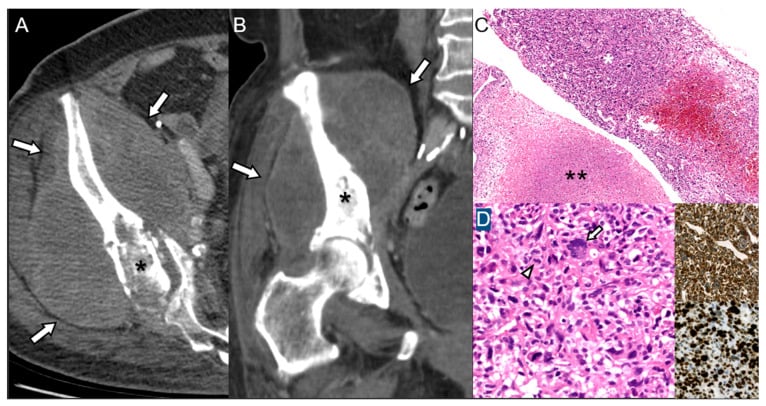
Differential Diagnosis
Osteoid decides it. The differential that matters most is dedifferentiated osteosarcoma. Osteosarcoma produces osteoid by definition, from malignant osteoblasts; it is more pleomorphic and its alkaline phosphatase is often elevated. It can contain dedifferentiated areas that mimic fibrosarcoma, which is why thorough sampling of multiple areas is essential.
- Histology
- Herringbone spindle cells, no osteoid
- Immunohistochemistry
- Vimentin+, all others negative
- Molecular
- No specific translocation
- Key Distinguishing Feature
- Diagnosis of exclusion
- Histology
- Spindle cells WITH osteoid (even focal)
- Immunohistochemistry
- Variable
- Molecular
- Complex karyotype
- Key Distinguishing Feature
- ANY osteoid production excludes fibrosarcoma
- Histology
- Monophasic (spindle) or biphasic
- Immunohistochemistry
- Cytokeratin+, EMA+, CD99+
- Molecular
- SS18-SSX fusion
- Key Distinguishing Feature
- Cytokeratin positivity, fusion gene
- Histology
- Pleomorphic, storiform pattern
- Immunohistochemistry
- Vimentin+, variable others
- Molecular
- Complex karyotype
- Key Distinguishing Feature
- Storiform pattern, marked pleomorphism
- Histology
- Spindle cells with cigar-shaped nuclei
- Immunohistochemistry
- SMA+, desmin+, h-caldesmon+
- Molecular
- Variable
- Key Distinguishing Feature
- Smooth muscle markers positive
- Histology
- Spindle cell variant (sarcomatoid)
- Immunohistochemistry
- Cytokeratin+, epithelial markers+
- Molecular
- Primary site specific
- Key Distinguishing Feature
- Epithelial markers, known primary
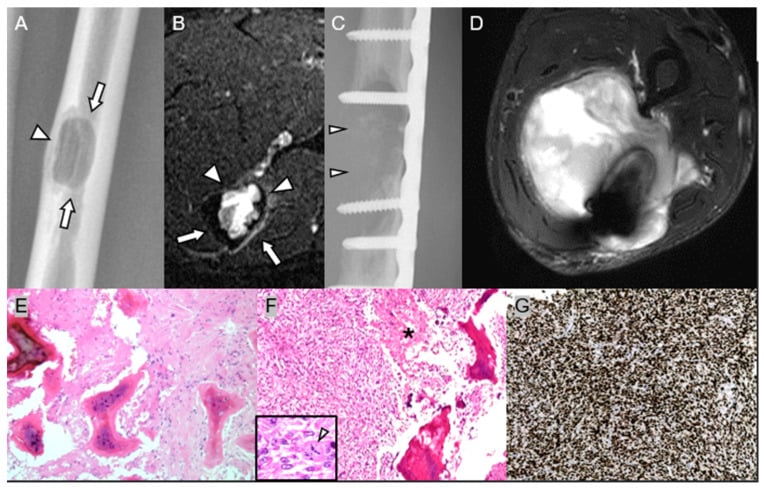
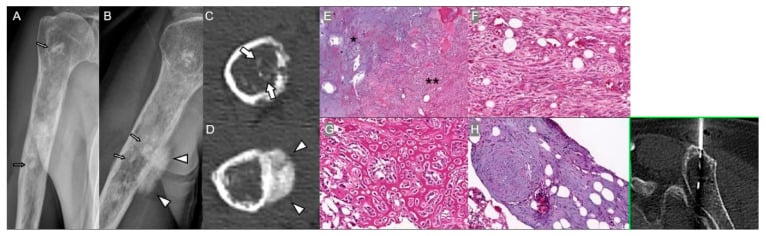
Management
The goal. Complete resection with wide oncological margins, preserving limb function when feasible. Planning begins at a multidisciplinary tumour board (surgeon, radiologist, pathologist, oncologist) that reviews all the imaging, MRI for extent and CT for bone detail, and plans the margins and the reconstruction. The patient is counselled about risks, alternatives and functional outcomes.
The resection. An en-bloc resection with 1-2cm margins in all directions, or a fascial barrier, taking the biopsy tract with the specimen. Neurovascular structures are preserved if it is oncologically safe, margins are sent for frozen section, and any structural defect is reconstructed.
Enneking margins. The target for fibrosarcoma is wide:
- Intralesional: tumour violated, gross disease left behind; not acceptable
- Marginal: through the reactive zone, microscopic disease likely; inadequate, with high recurrence
- Wide: through normal tissue, 1-2cm or an anatomical barrier such as fascia, joint capsule or the periosteum of uninvolved bone; skip lesions may be left if the margin is insufficient
- Radical: the entire compartment; rarely necessary for bone sarcomas
Reconstruction. A megaprosthesis is the most common reconstruction for the long bones. Allograft may be intercalary or osteoarticular, a vascularised fibular autograft is used less often, and arthrodesis is an option if the joint must be sacrificed and an endoprosthesis is not suitable.
- Advantages
- Immediate stability, early mobilisation, predictable
- Disadvantages
- Infection risk, loosening, limited lifespan
- Best Use
- Older patients, large defects, poor bone quality
- Advantages
- Biological, potential for remodelling, no foreign material
- Disadvantages
- Fracture risk, nonunion, disease transmission risk, slow incorporation
- Best Use
- Young patients, moderate defects
- Advantages
- Combines stability with biology, soft tissue attachment
- Disadvantages
- Both allograft and prosthesis complications possible
- Best Use
- Juxta-articular resections, need for soft tissue reattachment
- Advantages
- Biological, living bone, remodels, low infection
- Disadvantages
- Donor site morbidity, stress fracture, technically demanding, slow hypertrophy
- Best Use
- Young patients, smaller defects, high-demand patients
How wide is wide. The exact margin in millimetres that constitutes "wide", and the value of adjuvant radiotherapy for close or positive margins, are extrapolated from soft-tissue sarcoma and mixed bone-sarcoma data rather than from fibrosarcoma-specific randomised evidence.
Complications and Outcomes
- Incidence
- 10-30% depending on grade and margins
- Risk Factors
- Inadequate margins, high-grade, contaminated biopsy tract
- Management
- Re-excision with wider margins, consider radiation
- Incidence
- 30-40% for high-grade
- Risk Factors
- High-grade, tumour size over 8cm, elevated LDH
- Management
- Pulmonary metastasectomy if resectable, chemotherapy
- Incidence
- 5-15%
- Risk Factors
- Megaprosthetic reconstruction, long operative time, poor soft tissue coverage
- Management
- Debridement, antibiotics, may require prosthesis removal
- Incidence
- 10-20%
- Risk Factors
- Allograft reconstruction, delayed union, stress riser
- Management
- Protected weight-bearing, may require revision
- Incidence
- 2-5%
- Risk Factors
- Tumour proximity to vessels/nerves, extensive dissection
- Management
- Immediate repair if recognised, consultation
- Incidence
- Variable
- Risk Factors
- Muscle resection, nerve sacrifice, stiffness
- Management
- Rehabilitation, physiotherapy, functional bracing
Survival. Grade is the strongest prognostic factor, but no cited study reports a modern grade-stratified figure for true fibrosarcoma of bone. The two largest series report 34% and 33.4% at five years overall, both drawn from cohorts spanning most of the twentieth century in which many cases would now be reclassified, and the only contemporary multimodal series (EURO-B.O.S.S.) contained just three fibrosarcomas among 113 patients.
Secondary tumours. Secondary fibrosarcoma does worse than primary, but the figures in the management table do not allow a like-for-like comparison: the Paget figure comes from a series that was 88% osteosarcoma, and the post-radiation figure covers every histology.
- Favourable
- Low grade, well differentiated
- Poor
- High grade: poorly differentiated, high mitotic rate, necrosis
- Favourable
- Wide, greater than 1cm in all planes
- Poor
- Marginal or inadequate: less than 1cm or positive
- Favourable
- Less than 5cm diameter
- Poor
- Greater than 8cm
- Favourable
- Primary, de novo in normal bone
- Poor
- Secondary: Paget's, radiation field, infarct
- Favourable
- Distal, with better salvage options if recurrence
- Poor
- Axial (pelvis, spine), where wide margins are difficult
- Favourable
- None at presentation or during treatment
- Poor
- At presentation or early development
Surveillance. Recurrence and metastasis come early: 80% of local recurrences occur within the first 2 years and 90% within 5, and most metastases appear within the first 3 years, the lung being the most common site. Surveillance is more intensive for high-grade tumours and less so for low-grade ones.
- First 2 years: clinical examination and local imaging (X-ray or MRI) every 3 months, CT chest every 3 months
- Years 3-5: clinical examination and local imaging every 4-6 months, CT chest every 6 months
- After 5 years: annual follow-up with CT chest
Guidelines, Registries & Global Practice
Global Epidemiology
Fibrosarcoma of bone accounts for less than 5% of primary bone sarcomas worldwide, and reported incidence has fallen markedly over recent decades as immunohistochemistry and molecular testing reclassify many historical cases as undifferentiated pleomorphic sarcoma, leiomyosarcoma or dedifferentiated chondrosarcoma. It is best regarded as one of the rare primary malignant bone sarcomas (RPMBS), which collectively make up 5-10% of high-grade bone tumours (EURO-B.O.S.S.). Peak age is 30-50 years for primary disease, shifting older for secondary tumours arising in Paget disease or irradiated bone.
Society Guidance, Side by Side
- Diagnostic stance
- Fibrosarcoma is a diagnosis of exclusion after IHC/molecular workup; many spindle cell sarcomas of bone now coded as 'undifferentiated/spindle cell sarcoma NOS'
- Treatment emphasis
- Grade-based risk stratification; defines the entity rather than therapy
- Diagnostic stance
- Mandatory expert sarcoma pathology review; central reference panels encouraged
- Treatment emphasis
- Wide resection at a reference centre; perioperative chemo for high-grade per RPMBS data
- Diagnostic stance
- Referral to a designated bone sarcoma diagnostic and treatment centre (network model)
- Treatment emphasis
- MDT-directed wide excision and limb salvage; chemo decided case-by-case at the network MDT
- Diagnostic stance
- Treats non-osteosarcoma high-grade spindle/pleomorphic bone sarcoma broadly on the osteosarcoma pathway
- Treatment emphasis
- Wide resection; consider osteosarcoma-type chemotherapy for high-grade disease
- Diagnostic stance
- Pre-treatment biopsy along an excisable tract, planned with the resecting surgeon
- Treatment emphasis
- Reconstruction (endoprosthesis, allograft, APC) and stable fixation after wide resection
Registries and Evidence Networks
- Reference-centre registries (e.g. Rizzoli/EMSOS in Europe, Mayo and Memorial Sloan-Kettering historical series) supply almost all outcome data, because population numbers are tiny at any single unit.
- Cooperative trial groups (EURO-B.O.S.S., COSS, Euro-EWING networks) pool rare bone sarcomas to generate prospective chemotherapy evidence — the basis for offering osteosarcoma-type regimens in fit high-grade patients.
- There is no implant survivorship registry endpoint specific to fibrosarcoma; reconstruction outcomes are extrapolated from limb-salvage endoprosthesis and allograft series.
High- versus Limited-Resource Practice
- Specialist MSK pathology with full IHC and molecular panels
- MRI, CT chest and PET-CT staging routinely available
- Limb salvage with custom endoprostheses or allografts
- Multidisciplinary tumour board and prospective trial enrolment
- Restricted IHC may force a descriptive "spindle cell sarcoma" diagnosis
- Late presentation with large tumours and pathological fracture is common
- Amputation more often the realistic margin-achieving option than complex reconstruction
- Chemotherapy access and supportive-care capacity constrain osteosarcoma-type regimens
MCQ Practice Points
Q: What is the critical histological feature that distinguishes fibrosarcoma from osteosarcoma? A: Absence of osteoid or chondroid matrix production. Fibrosarcoma produces collagen only. Even focal osteoid on extensive sampling excludes fibrosarcoma and indicates osteosarcoma (or dedifferentiated osteosarcoma). This is why thorough sampling of multiple tumor areas is essential.
Q: Why is fibrosarcoma considered a diagnosis of exclusion? A: Fibrosarcoma has no specific positive immunohistochemical markers or genetic translocations. Diagnosis requires: (1) spindle cell morphology with herringbone pattern, (2) collagen production without osteoid/chondroid, (3) negative immunostains for other entities (S100, cytokeratin, muscle markers, CD99, MDM2), (4) absence of specific fusions (SS18-SSX, FUS). Many historical fibrosarcomas have been reclassified as UPS or other specific entities with modern diagnostics.
Q: What are the causes of secondary fibrosarcoma of bone, and which is most common? A: PRIC mnemonic: (1) Paget's disease (most common secondary cause, 1% degeneration rate), (2) Radiation therapy (3-20 year latency), (3) Infarct (chronic bone infarct), (4) Chronic osteomyelitis (very rare, also fibrous dysplasia). Secondary fibrosarcomas do worse still: Paget sarcoma ~10% at five years (Deyrup 2007) and post-radiation sarcoma 45% across all histologies (Mavrogenis 2012). For primary fibrosarcoma, resist quoting a grade-stratified figure - the two largest series report 34% and 33.4% overall, from cohorts many of whose cases would now be reclassified.
Q: What is the role of chemotherapy in fibrosarcoma of bone, and how does it differ from osteosarcoma? A: Unlike osteosarcoma where neoadjuvant and adjuvant chemotherapy is standard, fibrosarcoma has no proven benefit from chemotherapy. Fibrosarcoma is less chemosensitive than osteosarcoma. Some centers may use chemotherapy for high-grade tumors based on soft tissue sarcoma protocols (doxorubicin, ifosfamide), but evidence is limited and not routine standard of care. Decision should be individualized at multidisciplinary tumor board.
Q: What are the 5-year survival rates for fibrosarcoma based on grade and primary versus secondary? A: Grade is the strongest prognostic factor, but resist quoting a grade-stratified percentage - no study cited on this page reports one for true fibrosarcoma of bone. What can be said: the two largest series (Huvos, 130 patients; Papagelopoulos, 92) report overall five-year survival of 34% and 33.4%, both spanning decades in which many cases would now be reclassified by immunohistochemistry; and the only contemporary multimodal series contained just three fibrosarcomas among 113 patients. Secondary fibrosarcoma (Paget's, post-radiation, infarct) does worse. Post-radiation sarcoma specifically: Mavrogenis reported 45% five-year survival across 52 post-radiation sarcomas of all histologies, at a mean latency of 15 years. Paget sarcoma: Deyrup reported 10% five-year survival across 70 cases, of which 88% were osteosarcoma rather than fibrosarcoma.
Q: What are the diagnostic criteria for post-radiation sarcoma (Cahan criteria)? A: Modified Cahan criteria: (1) Tumor arises in previously irradiated field, (2) Latency period of at least 3-5 years after radiation, (3) Histologically different from original tumor (if radiation for malignancy), (4) Histologically confirmed sarcoma. These criteria distinguish radiation-induced sarcoma from recurrent original tumor or coincidental new tumor.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 40-year-old male presents with 3 months of progressive thigh pain. X-ray shows a 6cm lytic destructive lesion in the mid-femoral diaphysis with no matrix calcification. CT-guided biopsy reports spindle cells in herringbone pattern with no osteoid production. Immunohistochemistry shows vimentin positive, all other stains negative. How would you manage this patient?”
“A 72-year-old female with known polyostotic Paget's disease presents with sudden increase in pain in her proximal femur over 2 months. She has had Paget's for 20 years managed with bisphosphonates. X-ray shows a destructive lytic lesion in the proximal femur with cortical breakthrough in an area previously affected by Paget's. Alkaline phosphatase is markedly elevated at 950 (previously 400). What is your differential diagnosis and management approach?”
“A 55-year-old male was treated with radiation therapy 12 years ago for Ewing sarcoma of the proximal tibia (limb salvage with resection and allograft). He now presents with progressive pain and a new destructive lesion at the proximal tibia in the previously irradiated field. Biopsy confirms high-grade fibrosarcoma. CT chest shows no metastases. How would you counsel and manage this patient?”
Key Features
- Malignant spindle cell tumor producing collagen, NO osteoid or chondroid matrix
- Less than 5% of primary bone sarcomas, incidence decreasing (reclassification)
- Peak age 30-50 years, equal gender distribution
- Femur (30%) and tibia (25%) most common, metaphyseal predominant
- Diagnosis of exclusion - no specific positive markers or translocations
Histology and Diagnosis
- Herringbone pattern of spindle cells in fascicles
- Collagen production, NO osteoid (critical - excludes osteosarcoma)
- Graded by cellularity, atypia, mitotic rate, necrosis (low/intermediate/high)
- Vimentin positive, all other immunostains negative (S100, cytokeratin, desmin, CD99 all negative)
- Must exclude: osteosarcoma (osteoid), synovial sarcoma (SS18-SSX), UPS, carcinoma
Secondary Fibrosarcoma (PRIC)
- Paget's disease - most common secondary cause, 1% degeneration rate
- Radiation - 3-20 year latency, Cahan criteria (field, latency over 3 years, different histology)
- Infarct - chronic bone infarct, sickle cell or steroid history
- Chronic osteomyelitis - very rare, also fibrous dysplasia
- Secondary does worse: Paget sarcoma ~10% (Deyrup); post-radiation 45% all-histology (Mavrogenis); primary 34%/33.4% in the two largest historical series
Imaging and Staging
- X-ray: Lytic destructive lesion, NO matrix calcification/ossification
- MRI: Soft tissue extent, neurovascular relationship (T1 low, T2 high, heterogeneous enhancement)
- CT chest: Mandatory for staging (lung most common metastatic site)
- Biopsy: Core needle preferred, excisable trajectory, multiple samples to exclude osteoid
- PET-CT: Whole-body staging, assess for skip lesions
Treatment
- Wide surgical resection - primary treatment (1-2cm margins or fascial barrier)
- Reconstruction: Endoprosthesis, allograft, allograft-prosthetic composite, vascularized fibula
- Chemotherapy: Limited role (NOT standard like osteosarcoma), may consider for high-grade
- Radiation: Positive margins, unresectable, dose 60-66 Gy
- Amputation: If wide margins not achievable or unresectable with limb salvage
Prognosis and Surveillance
- Grade is the strongest prognostic factor; no cited series gives grade-stratified survival
- Two largest series: 34% and 33.4% overall five-year survival, both historical cohorts
- Secondary (Paget's, radiation, infarct) does worse: Mavrogenis 45% at five years across all post-radiation histologies; Deyrup 10% in Paget sarcoma, 88% of which were osteosarcoma
- Grade is the most important prognostic factor, alongside size, margins, and primary versus secondary
- Surveillance: Every 3 months for 2 years (clinical, local imaging, CT chest), then every 6 months to 5 years
Differential Diagnosis (Spindle Cell Tumors)
- Osteosarcoma (dedifferentiated) - ANY osteoid production excludes fibrosarcoma
- Synovial sarcoma - Cytokeratin+, EMA+, SS18-SSX fusion
- UPS (MFH) - Storiform pattern, marked pleomorphism
- Leiomyosarcoma - SMA+, desmin+, h-caldesmon+ (smooth muscle markers)
- Metastatic carcinoma - Cytokeratin+, epithelial markers, known primary
Evidence Base and Key Studies
Primary Fibrosarcoma of Bone: A Clinicopathologic Study of 130 Patients
- Classic series of 130 primary fibrosarcoma cases (Memorial Sloan-Kettering, 1918-1973); 89 medullary, 41 periosteal
- Mean age 38 years (range 4-83), near-equal sex distribution, femur the most common site
- Overall 5-year survival 34% (medullary 27%, periosteal 52%); 10-year survival 28%
- Periosteal and low-grade lesions fared substantially better than central high-grade tumors
- Distinguished fibrosarcoma from osteosarcoma, whose 5-year survival was then only ~17%
Primary Fibrosarcoma of Bone: Outcome After Primary Surgical Treatment
- 92 patients with primary fibrosarcoma of bone treated at Mayo Clinic (1910-1995); mean age 38 years
- Femur (28), tibia (21) and pelvis (14) the commonest sites; 66% were Enneking stage IIB
- Overall probability of survival was only 33.4% at 5 years after surgery
- Local recurrence in 15% of patients; metastases developed in 68% of stage I-II patients (median 9 months)
- Independent adverse prognostic factors: age over 40 years, axial location, and high grade (grade 3-4)
Post-Radiation Sarcomas: Clinical Outcome of 52 Patients
- 52 post-radiation sarcomas (45 bone, 7 soft tissue) treated at Rizzoli 1985-2011
- Risk of post-radiation sarcoma 0.06% at a mean latency of 15 years (range 3-50 years)
- Commonest histologies osteosarcoma, then MFH/UPS and fibrosarcoma; all were high grade
- Survival 51% at 2 years and 45% at 5 years; sarcoma type was the only significant predictor
- Wide surgical resection is the only treatment with curative potential as re-irradiation is constrained
Sarcomas Arising in Paget Disease of Bone: A Clinicopathologic Analysis of 70 Cases
- 70 sarcomas arising in Paget disease; predominance in older men (mean age 66) and the axial skeleton, especially pelvis
- Most tumors were osteosarcoma (88%); all were high grade
- 5-year survival just 10%, confirming a dismal prognosis for Paget sarcoma
- No significant correlation between number of involved bones or disease duration and malignant transformation
- Poor outcome was unrelated to site or stage at presentation
Outcome of Rare Primary Malignant Bone Sarcoma Treated With Multimodal Therapy (EURO-B.O.S.S.)
- Prospective European study of 113 patients aged 41-65 with high-grade spindle cell, pleomorphic or vascular bone sarcoma (88 UPS, 20 leiomyosarcoma, 3 fibrosarcoma, 2 angiosarcoma)
- Treated with an osteosarcoma-type regimen (doxorubicin, ifosfamide, cisplatin, with methotrexate for poor responders)
- 5-year overall survival 68.4% for localized disease; better with complete surgical remission and extremity location
- Outcomes were similar to age-matched high-grade osteosarcoma treated on the same protocol
- Substantial toxicity: grade III-IV haematologic toxicity in 81%