Zone 2 (No Man's Land) | 4-Strand Repair | Early Motion
- Zone 2 = 'No Man's Land' - both tendons in fibrous sheath
- A2 and A4 pulleys are critical (prevent bowstringing)
- 4-strand core suture minimum for early active motion
- Epitendinous suture adds 10-20% strength, improves gliding
- Early active motion reduces adhesions, better outcomes
- “FDP alone if lacerated distal to FDS insertion
- “Core suture 2mm from cut end = optimal strength
- “Early motion: controlled active flexion, passive extension
- “Rupture peak at 7-10 days (weakest point in healing)
Overview & Epidemiology
Flexor tendon injuries are common in hand trauma, typically in young working-age men cut by glass, knives and occupational sharp objects. Zone II is the most frequently injured zone and the most studied.
A digit that does not flex is a time-sensitive surgical problem. Getting the outcome right depends on understanding the zone system, the biomechanics of the repair and the principles of rehabilitation.
Pathophysiology & Anatomy
The two tendons. Flexor digitorum profundus (FDP) inserts on the base of the distal phalanx and flexes the DIP joint. Flexor digitorum superficialis (FDS) splits around FDP at Camper's chiasm and inserts on the middle phalanx, where it flexes the PIP joint.
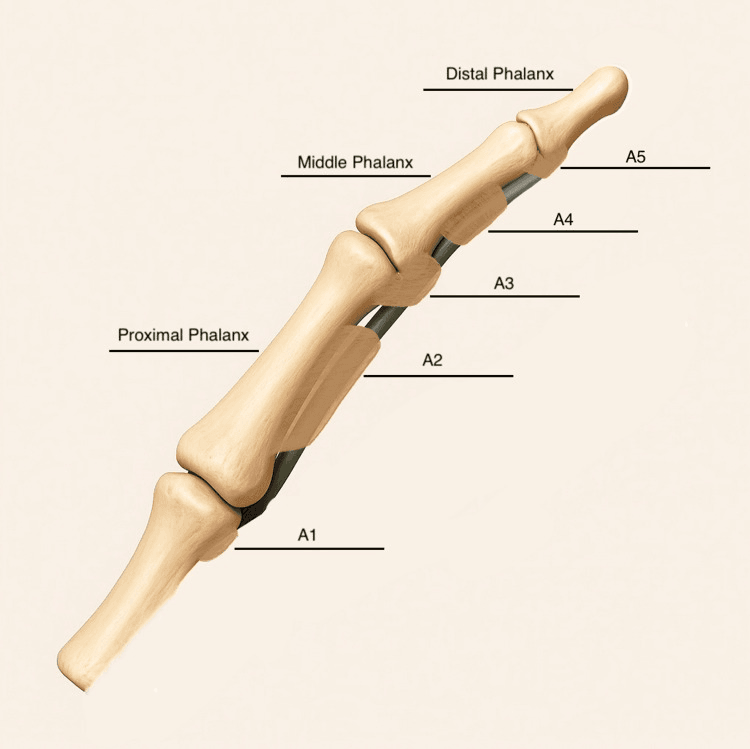
The pulleys. The sheath carries annular pulleys A1 to A5 and cruciate pulleys C1 to C3. A2, over the proximal phalanx, and A4, over the middle phalanx, are critical for mechanical advantage, A2 the most critical and A4 next. The even numbers are the pair to keep; the odd numbers can be sacrificed if necessary.
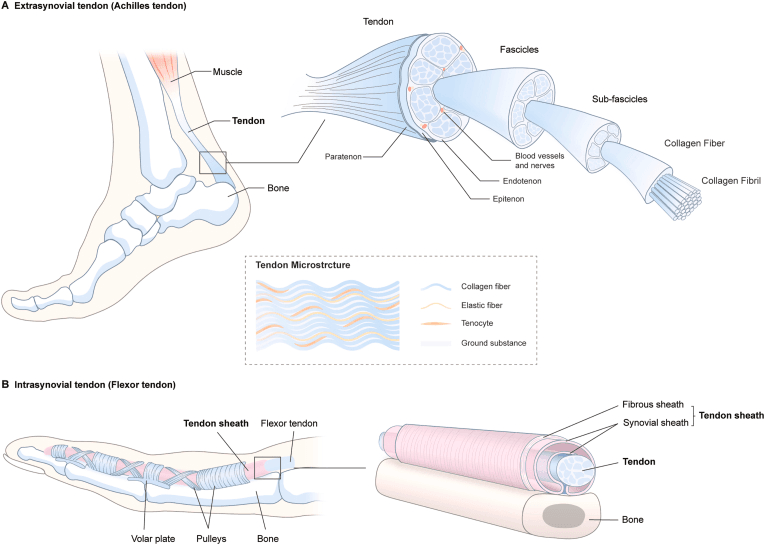
Healing and adhesions. Tendon heals by two pathways at once: intrinsic, mediated by tenocytes within the tendon, and extrinsic, from the sheath and surrounding tissue. The extrinsic pathway forms the adhesions that restrict gliding, and they are the central biological problem in zone II. Controlled tendon excursion biases healing toward the intrinsic pathway, which is the basis of early-motion rehabilitation.
The weak window. A repair is weakest at roughly 7-10 days, while the collagen remodels, and this is the period of peak rupture risk.
Zone Classification
The zones are numbered from the fingertip toward the forearm, and the position of the wound indicates the zone.
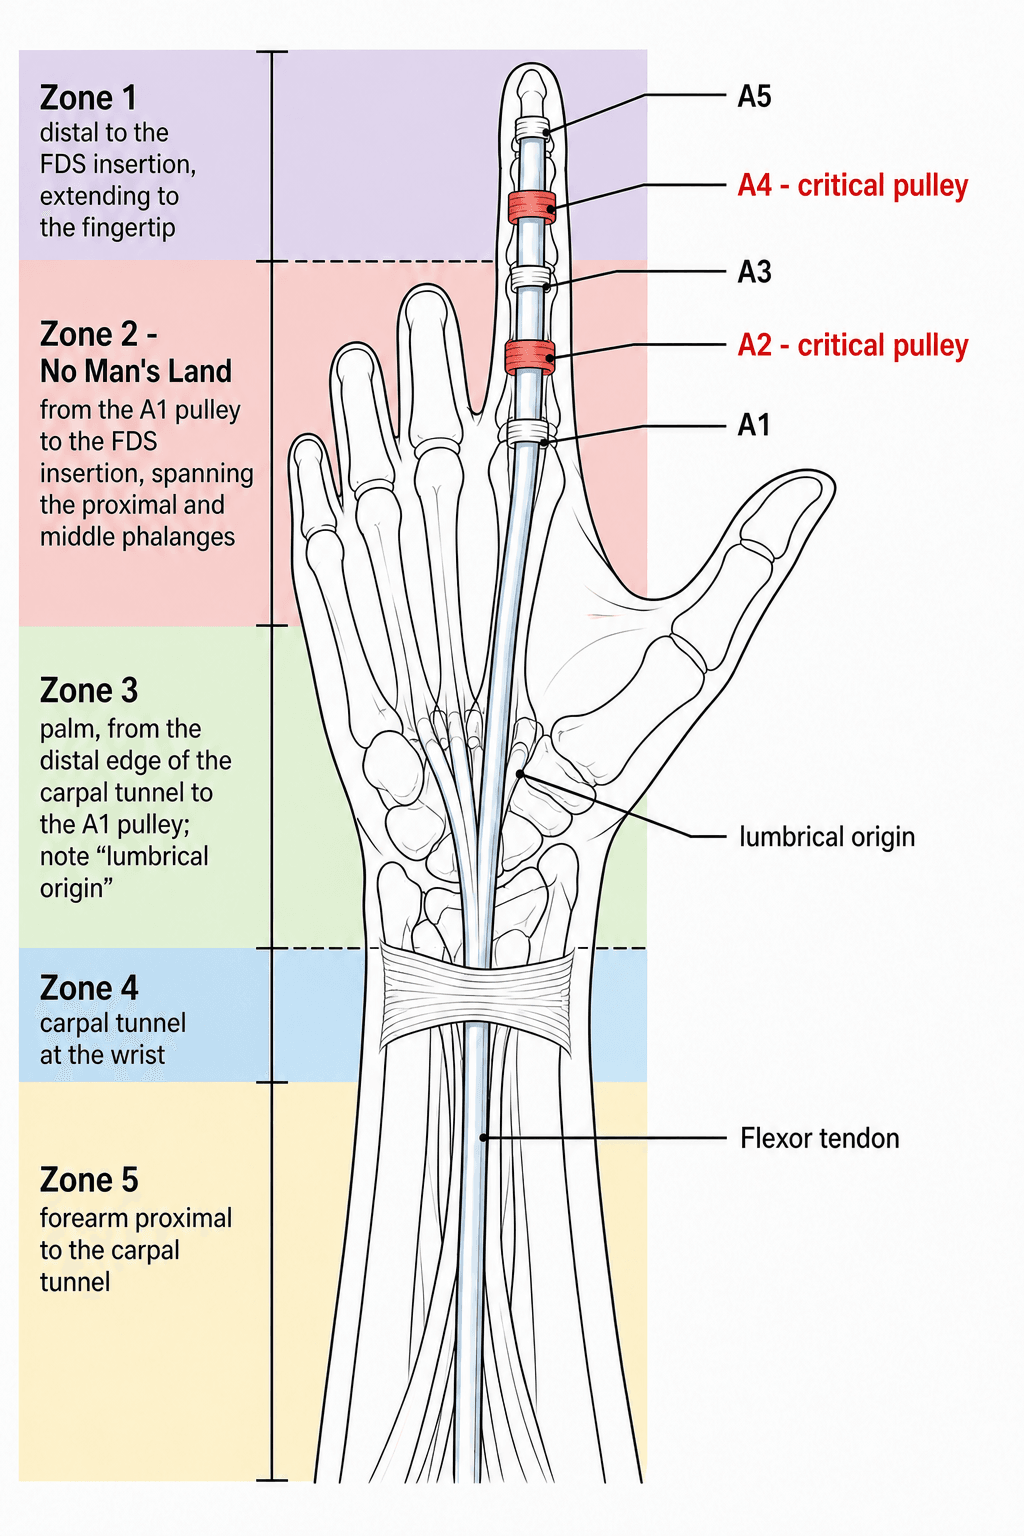
Zone 2, No Man's Land. From the A1 pulley to the FDS insertion, both FDP and FDS lie within the tight fibro-osseous sheath. Space is limited and the adhesion risk is high, so outcomes were historically poor; modern repair techniques and early motion have improved them.
Each of the other zones has its own hazard:
- Zone 1, distal to the FDS insertion and extending to the fingertip, holds FDP only. The classic injury is the jersey finger, an avulsion from bone, which may require a pull-out suture or anchor.
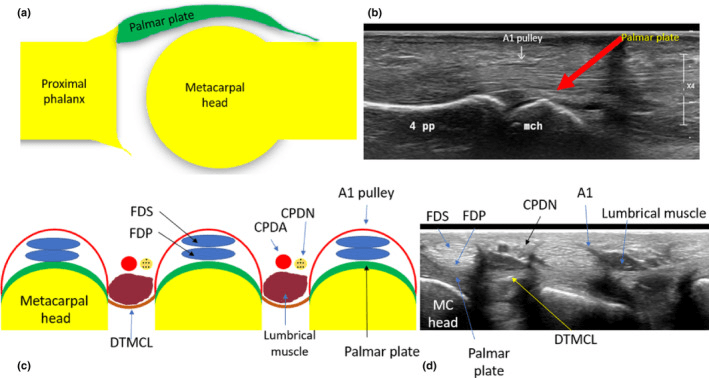
- Zone 3, the palm from the distal edge of the carpal tunnel to the A1 pulley, includes the lumbrical origin. The tendons lie relatively superficially with less adhesion risk, but the digital nerves and arteries may be injured with them; the digital neurovascular bundles lie adjacent in zones II and III.
- Zone 4, the carpal tunnel. The median nerve is at risk, and a carpal tunnel release may be needed to reach the tendons.
- Zone 5, the forearm proximal to the carpal tunnel. Repair is often of muscle rather than tendon, and multiple structures may be injured.
Clinical Presentation
Look first. The resting hand holds the fingers in a cascade of increasing flexion, and loss of that cascade suggests a laceration.
Test each tendon on its own. The two tendons act on different joints, so each is isolated in turn:
- FDP - hold the PIP extended and ask the patient to flex the DIP
- FDS - hold the other fingers extended, which blocks the FDP contribution, and ask the patient to flex the PIP
Explore when in doubt. If a tendon injury is suspected, the wound is explored in theatre under tourniquet.
Investigations
Flexor tendon laceration is largely a clinical and operative diagnosis, and imaging is adjunctive.
- Plain radiographs are mandatory after any sharp injury, to exclude retained glass or another foreign body, a fracture, or a bony avulsion fleck, which suggests an FDP avulsion (jersey finger)
- Ultrasound is useful for closed or doubtful injuries. It confirms tendon continuity and identifies the level of a retracted proximal stump, and it is operator-dependent
- MRI is reserved for complex, chronic or reconstructive planning: gap, sheath scarring, pulley integrity
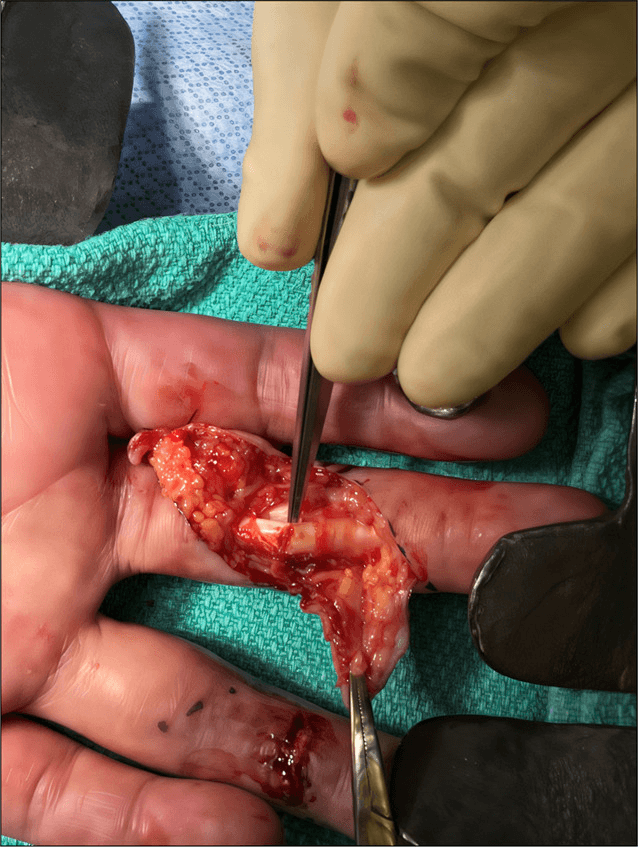
At operation. Intraoperative assessment remains the reference standard, and it answers what examination cannot:
- Complete or partial - a laceration of more than 60% of the width is functionally complete
- Level - the tendon injury may not lie under the skin wound, because the tendons may have retracted with the digit position at injury
- Associated injuries - digital nerves, vessels and bone
Differential Diagnosis & Mimics
A digit that will not flex is not always a tendon laceration. Telling the causes apart changes the operation, the timing and the consent.
- History / mechanism
- Sharp cut (glass, knife), open wound
- Examination clue
- No active flexion of relevant joint; loss of cascade
- Key discriminator
- Wound over flexor surface; tendon ends visible/retracted
- Action
- Surgical exploration and repair
- History / mechanism
- Sharp cut, weak/painful flexion
- Examination clue
- Flexion present but weak or triggering
- Key discriminator
- Greater than 60% width = functionally complete
- Action
- Repair if over 60%; otherwise trim/observe
- History / mechanism
- Forced extension of flexed DIP (rugby/jersey grab)
- Examination clue
- No active DIP flexion, often no skin wound
- Key discriminator
- Closed injury; Leddy-Packer type; possible bony fleck on X-ray
- Action
- Urgent reinsertion (type I/II earliest)
- History / mechanism
- Atraumatic, gradual catching/locking
- Examination clue
- Palpable A1 nodule, painful clicking
- Key discriminator
- No wound; intermittent locking not fixed loss
- Action
- Splint/steroid; A1 release if refractory
- History / mechanism
- Laceration proximal to muscle, or compression
- Examination clue
- Motor loss with sensory deficit in nerve territory
- Key discriminator
- Tendon intact on exploration; sensory map abnormal
- Action
- Nerve repair; treat cause
- History / mechanism
- Old injury, Dupuytren, prior trauma
- Examination clue
- Passive AND active motion both lost
- Key discriminator
- Tendon glides but joint will not move passively
- Action
- Address joint, not tendon
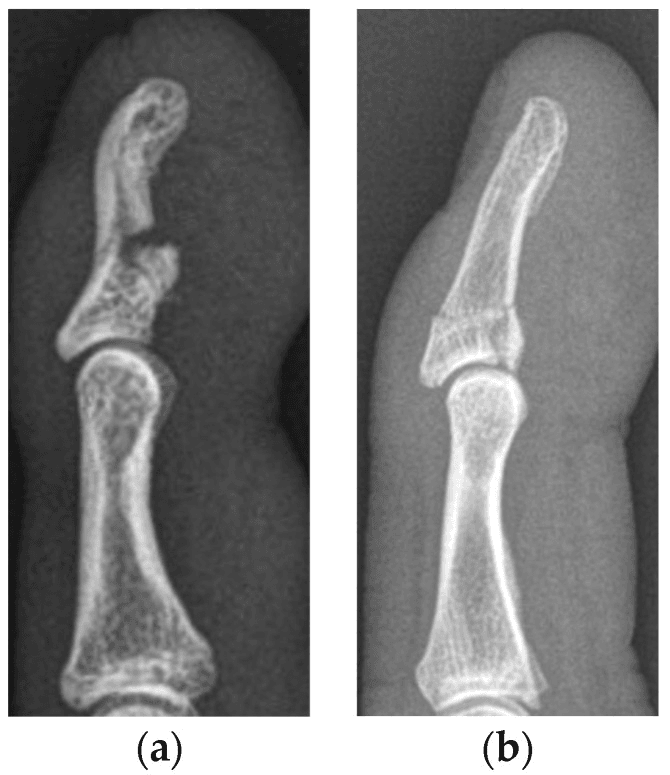
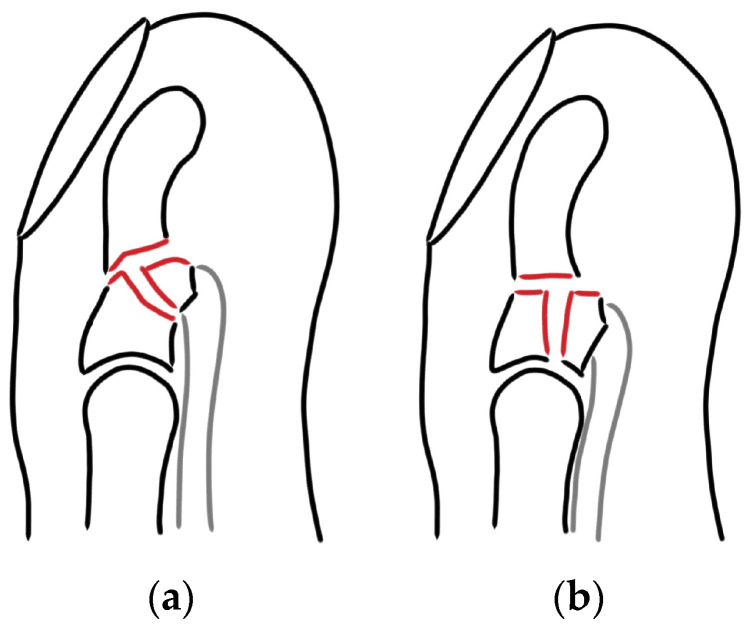
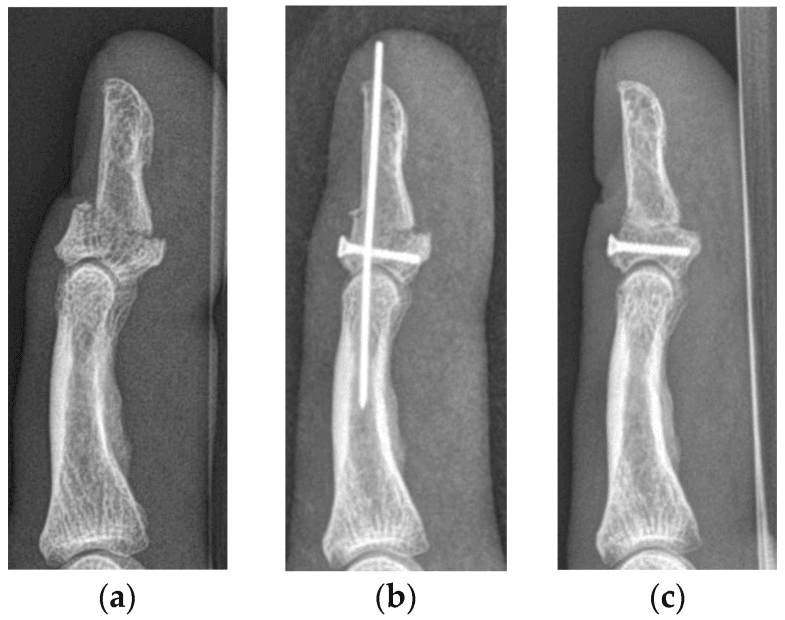
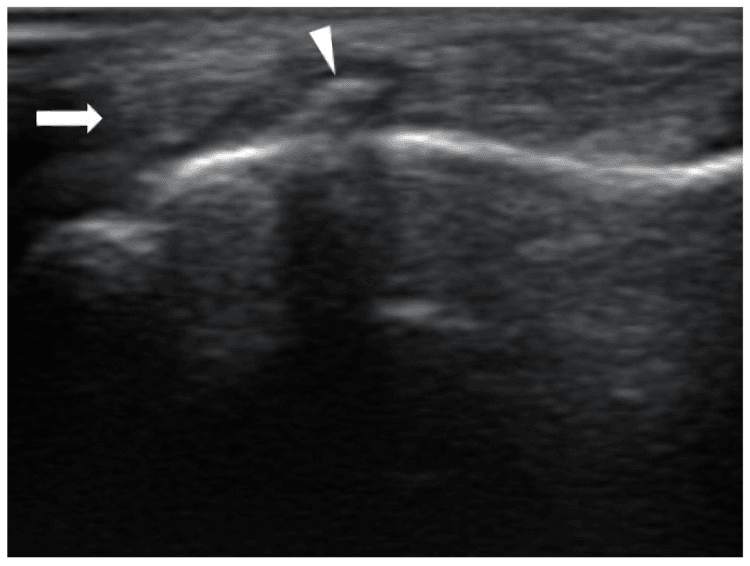
The bony avulsion. A fleck of bone on the radiograph changes the problem from an isolated tendon laceration to a tendon-bone injury. The Type Va and Vb jersey-finger fractures below show how.
Management
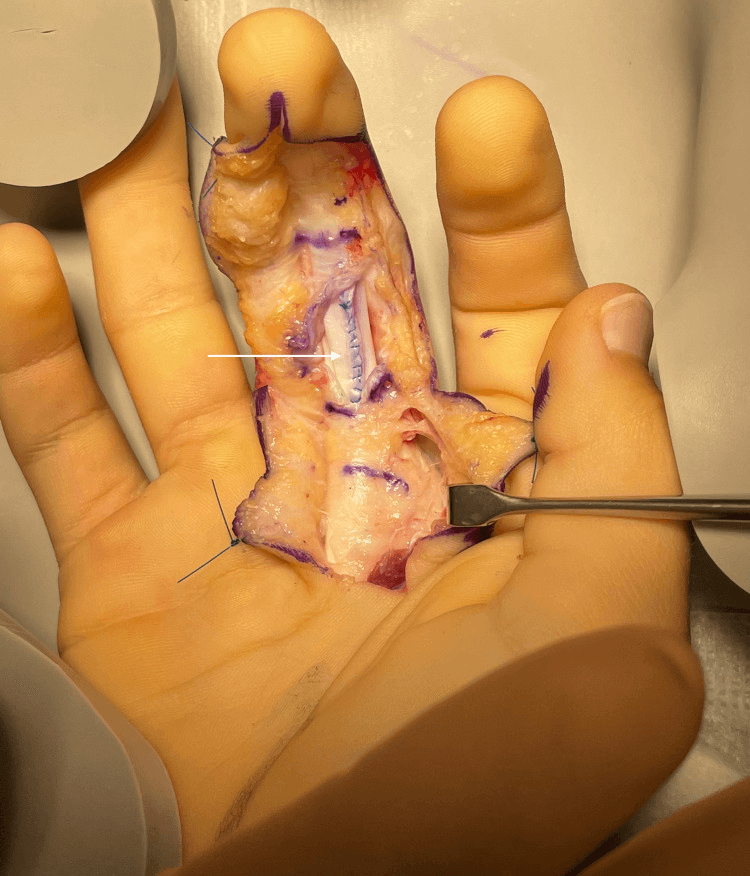
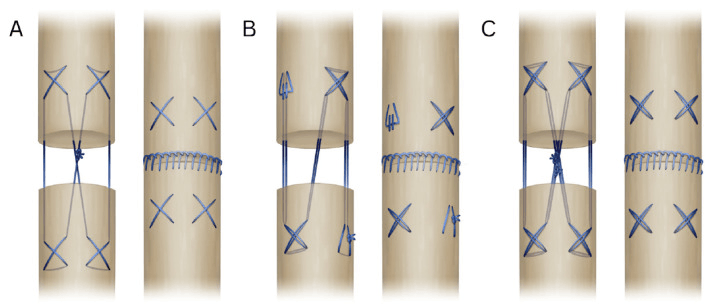
The core suture. A 4-strand core repair is the minimum for early active motion, and more strands make a stronger repair that allows earlier motion. A locking configuration adds strength. Common techniques are the modified Kessler, Strickland, Savage and cruciate repairs, in 3-0 or 4-0 braided non-absorbable suture; the choice of calibre is debated (see Controversies).
How strong is strong enough. In Thurman's cadaver model the ultimate tensile strength was 33.9N for a 2-strand, 43.0N for a 4-strand and 78.7N for a 6-strand repair. The threshold commonly quoted for early active motion is about 27N, and all of Bernstein's 4-strand constructs exceeded it.
Purchase and tension. The core suture is placed 2mm from the cut end for optimal strength. Tang asks for a core purchase no shorter than 0.7-1cm in each tendon end, and for the core to be well tensioned, slightly snug, to prevent a gap at the repair site.
The epitendinous suture. A running or interrupted peripheral suture of 5-0 or 6-0 adds 10-20% to repair strength, reduces gap formation and gives the repair a smooth surface to glide on. It is treated as an essential component of the modern repair, improving both strength and function, though how much of it is needed is debated (see Controversies).
In zone II. Repair both tendons if possible; whether to excise one slip of FDS when the sheath is crowded is covered under Controversies. Protect A2 and A4, which in Tang's practice may be judiciously vented to let the repair glide (the limits are under Pulley Reconstruction). Before closure, an intraoperative extension-flexion test, often under WALANT, confirms that the repair glides.
Complications
Adhesions are the most common problem. They limit gliding and may require tenolysis.
Rupture peaks in the weak window of healing described above, and requires re-repair.
Stiffness comes from adhesions or joint involvement and is addressed with therapy or tenolysis.
Bowstringing follows when the critical pulleys, A2 and A4, are not preserved or are over-vented. It reduces mechanical advantage and excursion, as the next section explains.
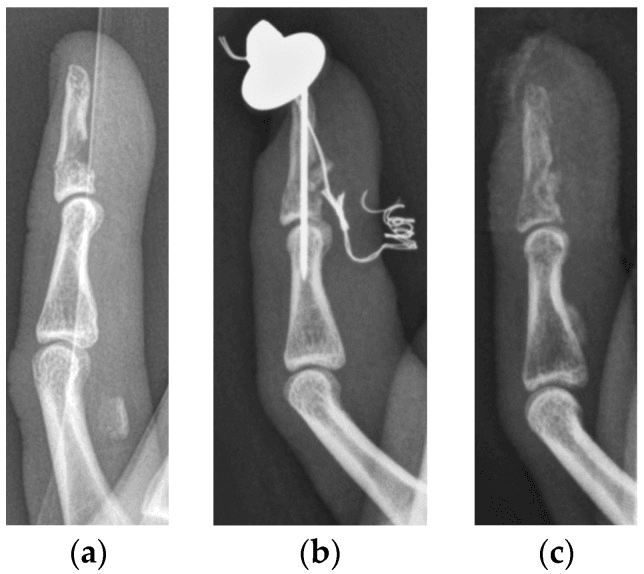
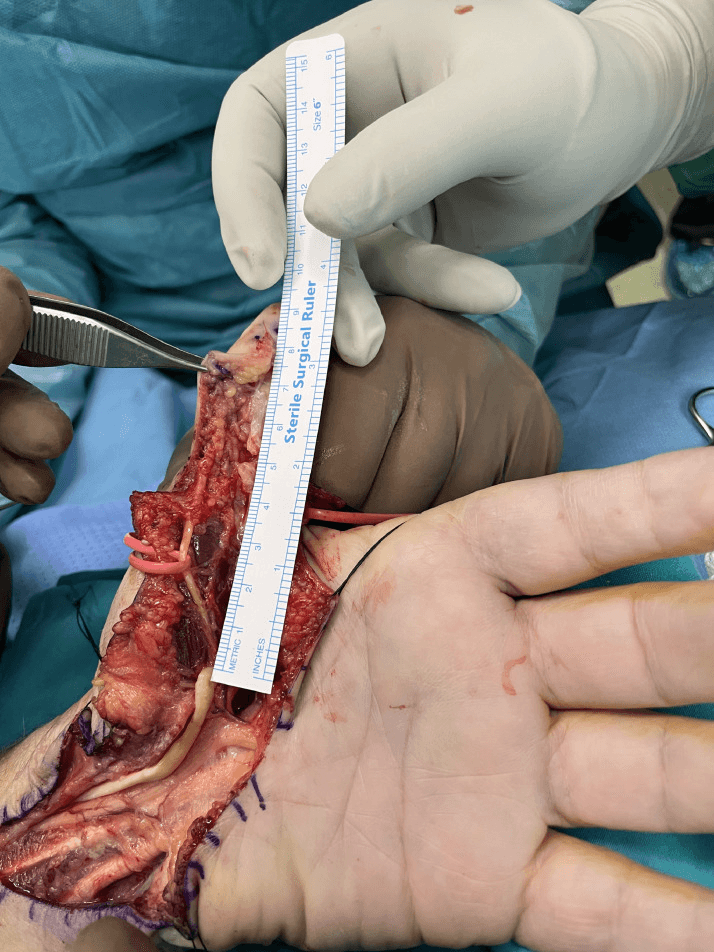
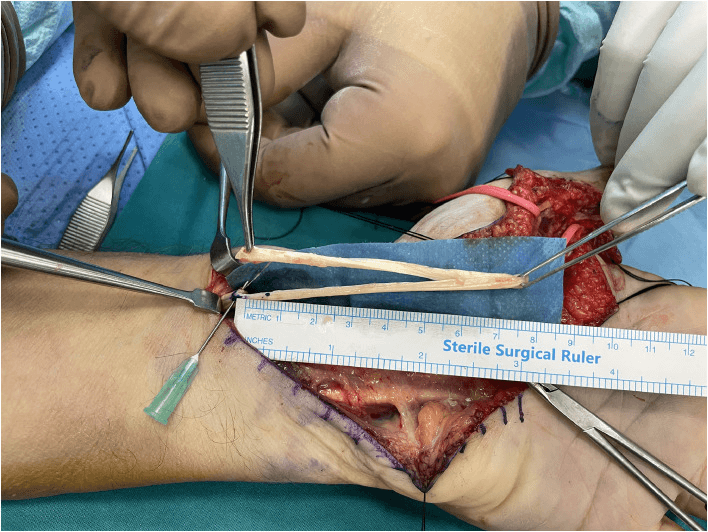
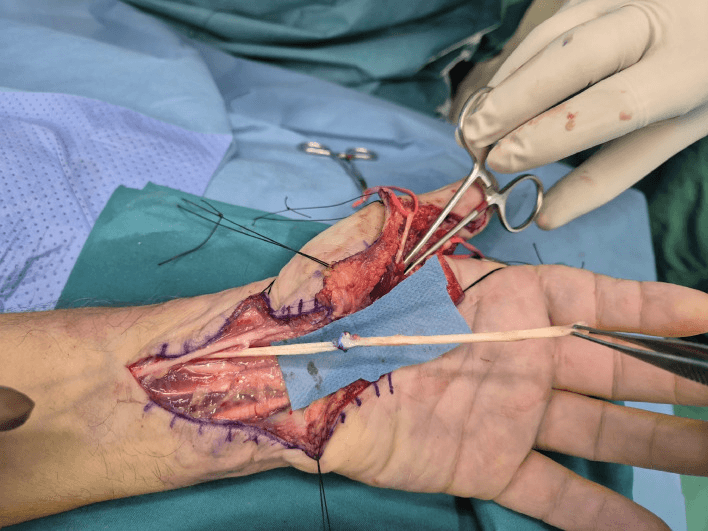
When direct repair is impossible, the defect has to be bridged. The sequence below shows one reconstruction option: a local sliding autograft for a chronic Zone 1 FPL defect.
Pulley Reconstruction & the Biomechanics of Bowstringing
Why bowstringing matters. The annular pulleys hold the flexor tendon against the phalanges and keep the line of pull close to the bone. This minimises the moment arm at each joint and conserves tendon excursion: a given amount of muscle shortening is spent flexing the joints rather than lifting the tendon off the skeleton. When a long pulley (A2 or A4) is lost, the tendon lifts away from the bone and takes the chord across the flexing joint instead of following its arc.
- Excursion is wasted on the bowstring path, so the same FDP contraction produces less distal flexion; the fingertip can no longer reach the palm, and the composite fist is lost
- The increased moment arm makes the proximal joint flex preferentially, producing an apparent flexion contracture and a weak, inefficient grip
- A visible, palpable bowstring lifting off the volar finger is the late clinical sign
Why A2 and A4. They matter most because they span the longest bony segments and resist the greatest bowstringing force.
Venting versus reconstruction. Tang shows that the system tolerates judicious venting: A2 may be partially incised over a length no greater than 1.5 to 2 cm, and A4 may be vented entirely, without observed bowstringing or functional loss. That is the safe ceiling for incising a pulley to expose or deliver a repair. A competent A2 and A4, preserved or reconstructed, are the practical minimum for normal mechanics.
When reconstruction is needed. Loss of both critical pulleys, or of a long segment of A2, is poorly tolerated and bowstrings. When trauma, infection or a failed repair has destroyed both, or a long segment of one, the pulley must be reconstructed to restore the tendon-to-bone relationship.
- Location
- Proximal phalanx
- Why it matters
- Longest pulley; largest bowstring force; conserves excursion
- Safe handling
- Partial vent up to 1.5 to 2 cm only
- If destroyed
- Reconstruct — loss poorly tolerated
- Location
- Middle phalanx
- Why it matters
- Holds the tendon over the PIP-to-DIP segment
- Safe handling
- May be vented entirely if needed for gliding
- If destroyed
- Reconstruct if both A2 and A4 are gone
- Location
- MCP / PIP / DIP volar plates
- Why it matters
- Minor mechanical contribution
- Safe handling
- Can be released or sacrificed
- If destroyed
- No reconstruction needed
Reconstruction techniques. Each recreates a smooth retinacular loop that holds the tendon, or in staged cases the Hunter rod, against the phalanx:
- Encircling free-graft loop - a strip of tendon graft (palmaris longus, a discarded slip of FDS, excised flexor tendon, or a toe extensor) is passed around the phalanx and sutured to itself. At the proximal phalanx the loop passes deep to the extensor mechanism; over the middle phalanx it can lie superficial to it
- Weave through the pulley rim (Weilby) - a graft woven through the surviving rim remnants of the original pulley, useful when a partial pulley remains
- Extensor-retinaculum graft (Lister) - a segment of dorsal extensor retinaculum, placed with its smooth synovial surface against the gliding tendon
In staged reconstruction. Pulley reconstruction is integral to stage 1 of a two-stage Hunter-rod reconstruction, where the pulleys are rebuilt around the silicone rod so the later tendon graft glides correctly. The graft and the staged technique themselves belong to flexor tendon reconstruction.
Rehabilitation
Why move early. Controlled early motion reduces adhesion formation and improves the final range of motion, with better results than immobilisation. It depends on the strong multi-strand repair described above.
A typical early active motion protocol:
- Dorsal blocking splint with the wrist flexed 20-30°, the MCPs at 50-70° and the IPs extended
- Active flexion and full passive extension, with exercises 4-6 times daily
- Synergistic exercises
- Progression to place-and-hold, then active motion
- 6 weeks protected, then progressive strengthening
Immobilisation. The historical protocol, 3-4 weeks of immobilisation before motion, brought a high adhesion rate, stiffness and poor outcomes, especially in Zone 2. It is now rarely indicated, but may be used in children, non-compliant patients or after a weak repair.
Measuring the Outcome: Strickland & Tang Criteria
Outcome after a flexor repair is graded by active interphalangeal motion, because the whole point of the repair is a finger that bends. Examiners expect a candidate who quotes "good or excellent" results to state the measurement behind them.
Total active motion (TAM) is the global metric: the sum of active flexion at the MCP, PIP and DIP joints, minus any extension deficit (fixed flexion) at those joints. It captures both how far the finger flexes and how far it fails to straighten.
The Strickland-Glogovac formula. Because FDS and FDP act across the PIP and DIP, a flexor repair is conventionally reported as a percentage of normal interphalangeal motion:
Percentage of normal = (active PIP flexion + active DIP flexion − PIP and DIP extension deficit) ÷ 175 × 100
The denominator, 175, is the assumed normal combined IP arc, roughly 100 degrees at the PIP plus 75 at the DIP. It is not a TAM target: TAM also counts the MCP.
- Original Strickland
- 85 to 100%
- Modified Strickland
- 75 to 100%
- Original Strickland
- 70 to 84%
- Modified Strickland
- 50 to 74%
- Original Strickland
- 50 to 69%
- Modified Strickland
- 25 to 49%
- Original Strickland
- under 50%
- Modified Strickland
- under 25%
Original or modified. The modified Strickland system uses the same formula with more lenient bands, so the same finger scores a grade higher than under the original. "Good or excellent" means little unless the paper, or the candidate, says which version is being used.
Tang criteria. The newer Tang grading, used in the zone II series in the Evidence Base, also sorts results into excellent, good, fair, poor and failure. It is built around the active flexion actually achieved and the residual extension loss, reflects modern strong-core, early-active-motion outcomes, and is the system behind the 52 of 60 fingers reported good or excellent.
Guidelines, Registries & Global Practice
Global epidemiology: Flexor tendon lacerations are common hand-trauma injuries, predominantly affecting young working-age men, most often from glass, knives and occupational sharp objects. Zone II is the most frequently injured and most studied zone. The dominant injury pattern reflects manual work and domestic glass injuries worldwide, so the burden is highest in working populations and in regions with high rates of interpersonal and occupational sharp trauma.
Side-by-side guidance (recommendations converge more than they differ):
- Emphasis
- Timing and specialist referral
- Practical position
- Primary repair ideally within days; refer to a hand unit; structured therapy-led rehabilitation
- Emphasis
- Repair strength and protected motion
- Practical position
- Multi-strand core repair supporting early controlled motion; hand-therapy partnership
- Emphasis
- Strong tensioned core + venting + EAM
- Practical position
- Well-tensioned 4-6 strand core, judicious A2/A4 venting, intraoperative gliding test, early active motion
- Emphasis
- WALANT and out-of-splint motion
- Practical position
- Increasing use of wide-awake repair with intraoperative active testing and freer early motion
Registry note: There is no dedicated international flexor-tendon registry equivalent to the arthroplasty registries (NJR, AJRR, AOANJRR, SHAR). Best evidence therefore comes from multicentre cohorts and meta-analyses, which consistently report rupture rates of roughly 4-12% and good/excellent outcomes around 70-90% with modern strong-core repair and early active motion.
High- vs limited-resource practice variation: In well-resourced settings, repair is performed under loupe/microscope magnification with hand-therapy-supervised early active motion and, increasingly, WALANT. In limited-resource or remote settings, delayed primary or staged repair, simpler 2-strand techniques and immobilisation-based rehabilitation are more common because of restricted theatre access and limited specialist hand therapy — a recognised driver of higher adhesion and stiffness rates rather than a difference in principle.
Controversies & Areas of Uncertainty
Flexor tendon surgery is one of the most opinion-driven areas in hand surgery, and examiners use these debates to separate safe candidates from outstanding ones.
How critical are A2 and A4? The classic teaching that they must never be touched has softened. Tang's judicious venting reports no bowstringing or functional loss and is now mainstream, yet the safe limit of venting before mechanical disadvantage appears is still debated.
Strand number, strong enough or too bulky. More strands increase strength and resist gapping, but extra core passes add bulk and gliding resistance and prolong surgery. In Thurman's cadaver model the increase in gliding resistance after repair was small and not significant. Many units now favour a well-tensioned 4- or 6-strand repair rather than chasing maximal strand counts.
Suture calibre. A larger 3-0 suture intuitively seems stronger, but cadaver data show it fails by pulling through the tendon; 4-0 may give a more reliable suture-tendon interface in average-sized tendons.
How much peripheral suture, and what kind. A formal circumferential epitendinous suture adds strength and smooths the repair, but tensioned strong-core series suggest that only sparse peripheral stitches are needed, which questions routine elaborate epitendinous work.
Should the FDS be repaired in zone II? Repairing both tendons restores independent PIP and DIP control but crowds the sheath and risks adhesions, so some surgeons excise one FDS slip to make room. The evidence does not clearly favour either approach.
Rehabilitation regime. True early active motion, place-and-hold, relative-motion-flexion orthoses and early passive motion all have advocates. The best protocol for a given repair strength and patient reliability is not settled.
Anaesthesia. WALANT permits intraoperative active testing and is cost-effective, but high-quality comparative outcome data against traditional anaesthesia remain limited.
MCQ Practice Points
Q: Why is Zone 2 called "No Man's Land"? A: Both FDP and FDS tendons are within the tight fibro-osseous sheath. Limited space leads to high adhesion risk and historically poor outcomes (now improved with modern techniques).
Q: Which pulleys are critical for flexor tendon function? A: A2 (proximal phalanx) and A4 (middle phalanx). These must be preserved or reconstructed to prevent bowstringing. A1, A3, A5 can be sacrificed if necessary.
Q: What is the minimum core suture for early active motion protocol? A: 4-strand at minimum, and the reason is gapping rather than raw strength. Quote this page's own cadaveric data rather than round numbers: Thurman measured ultimate tensile strength of 33.9 N for 2-strand, 43.0 N for 4-strand and 78.7 N for 6-strand, but the decisive result was gap formation after 1,000 cycles - 2.75 mm for the 2-strand repair against 0.30 mm and 0.31 mm for the 4- and 6-strand. A 2-strand repair is not so much weak as it stretches out. The clinical counterpart is Xu's meta-analysis, which found a higher rupture rate specifically in the active flexion-and-extension subgroup repaired with a 2-strand core suture and concluded that the 2-strand technique is not sufficient for that protocol. Note also that Bernstein found all four of his 4-strand constructs exceeded the ~27 N commonly quoted as the threshold for early active motion, so beyond four strands the limiting factor shifts from the core suture to the suture-tendon interface.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 30-year-old man cuts his right ring finger on broken glass. He cannot flex his DIP or PIP joints. How do you manage him?”
“A 35-year-old carpenter presents 6 hours after a knife injury to the volar aspect of his left index finger in Zone 2. He has weak but present DIP flexion and full PIP flexion. In theatre, you find the FDS is intact but the FDP has approximately 70% of its width lacerated with 30% still in continuity on the radial side. The A2 pulley is intact. He is reliable and motivated for therapy. How would you manage the FDP and what would you counsel him about rehabilitation?”
“A 28-year-old builder returns to clinic 3 weeks after Zone 2 FDP and FDS repair of his middle finger. He admits he returned to light work against advice and felt a pop 2 days ago. He now has no active DIP or PIP flexion. X-ray shows no bony injury. In theatre, you find both tendons have completely ruptured and the proximal ends have retracted into the palm with significant fraying and degeneration of the tissue at the previous repair site. The tendon ends are mushy and will not hold suture. What are your management options and what would you recommend?”
Zone Classification
- Zone 1: Distal to FDS (FDP only)
- Zone 2: No Man's Land (both in sheath)
- Zone 3: Palm (NV at risk)
- Zone 4: Carpal tunnel
- Zone 5: Forearm
Repair Principles
- 4-strand core suture minimum
- Suture 2mm from cut end
- Epitendinous suture adds 10-20%
- Preserve A2 and A4 pulleys
Rehabilitation
- Early active motion reduces adhesions
- Dorsal blocking splint
- Active flexion, passive extension
- 6 weeks protected motion
Complications
- Adhesions (most common)
- Rupture (peak 7-10 days)
- Stiffness
- Bowstringing
Evidence Base
Thurman, Trumble et al — 2/4/6-strand biomechanical comparison
- Cadaver zone II in situ model (12 hands), each specimen its own control
- Ultimate tensile strength: 2-strand 33.9N, 4-strand 43.0N, 6-strand 78.7N
- 2-strand gapped 2.75mm after 1000 cycles vs 0.30mm (4-strand) and 0.31mm (6-strand)
- Gliding resistance increase after repair was small and not significant
Bernstein, Netscher et al — suture caliber & looped configuration
- 72 cadaver FDP tendons, 4-strand modified Kessler, progressive cyclic loading
- All constructs exceeded the ~27N threshold for early active range of motion
- 3-0 suture failed by pullout in 63.5% (looped) and 38.9% (single-strand) of repairs
- 4-0 suture pulled out in only 11.1% (looped) and 0% (single-strand)
Tang — venting critical pulleys & modern repair principles
- Core suture purchase no shorter than 0.7-1cm in each tendon end, well tensioned
- A2 may be partially vented (incision under 1.5-2cm); A4 may be vented entirely
- Judicious venting did not cause loss of hand function or bowstringing
- Intraoperative extension-flexion test (often WALANT) confirms gliding before closure
Pan, Chen et al — strong tensioned core + sparse peripheral + EAM
- 60 zone II FDP repairs with tensioned 4- or 6-strand core and only 3-4 peripheral stitches
- Pulleys vented as needed; early active flexion started postoperatively
- No repairs ruptured during follow-up of 8-33 months
- 52/60 (87%) fingers achieved good or excellent function by Tang criteria
Xu, Huang et al — rehabilitation protocol meta-analysis
- Systematic review/meta-analysis: 7 studies, 569 zone II digits
- Early active motion gave greater total active motion than early passive motion
- Higher rupture risk when active flexion-extension was used with a 2-strand repair
- 2-strand technique judged insufficient for active flexion-extension protocols
Bamal et al — WALANT vs traditional anaesthesia for zone I/II repair
- Retrospective cohort, 86 fingers, zone I/II primary flexor repair
- Good/excellent 12-week ROM in 56% (WALANT) vs 31% (traditional) — not statistically significant
- Overall rupture rate 11.6%, tenolysis 3.5%, reoperation 9.3%
- Small sample and poor follow-up (41%) limit strength of conclusions