The repeating sequence of limb movements from one foot's initial contact to the next contact of the same foot
- Definition: One complete gait cycle runs from initial contact of one foot to the next contact of the same foot, divided into stance (60%) and swing (40%)
- Double vs single support: Double support occupies 20% total (10% at the start and 10% at the end of stance) and disappears at running speeds; single support equals the contralateral swing time
- Key kinetics: Vertical ground reaction force is an M-shaped double hump (first peak ~110% body weight at loading, valley ~80% at midstance, second peak ~110-120% at terminal stance)
- Clinical use: Phase-by-phase muscle and joint analysis localises pathology (Trendelenburg, antalgic, steppage, equinus) and guides surgical and rehabilitation planning
- “Quadriceps fire eccentrically at loading response (shock absorption); gastrocnemius-soleus fire concentrically at terminal stance (push-off)
- “Trendelenburg gait reflects weakness on the STANCE limb (gluteus medius), not the dropping side
- “Three ankle rockers (heel, ankle, forefoot) smooth centre-of-mass progression; losing them after ankle fusion raises walking energy cost
Gait Cycle Analysis
Overview
Definition. One gait cycle runs from the initial ground contact of one foot to the next ground contact of the same foot. [1] Normal walking alternates periods of single- and double-limb support, each limb passing through a repeating sequence of stance and swing that carries the body forward efficiently while keeping balance and minimising energy expenditure. [2]
Timing. Stance, from initial contact to toe-off, takes 60% of the cycle; swing, from toe-off to the next initial contact, takes 40%. Double support occupies 20%, as two periods of 10% at the beginning and end of stance. Single support takes 40%, the time the contralateral limb spends in swing.
Speed. The stance-to-swing ratio changes with walking speed: walking faster shortens stance time and lengthens swing time. [1,2] Double support disappears at running speeds.
Spatiotemporal norms. Reference values for normal adult walking:
- Cadence: 90-120 steps per minute
- Stride length, between successive contacts of the same foot: 1.2-1.5 m
- Step length, between contacts of opposite feet: 0.6-0.8 m
- Walking velocity: 1.2-1.4 m/s in the average adult
These parameters vary with age, gender, height and pathology. [3]
Why it matters. Gait analysis is fundamental to orthopaedic assessment. It identifies the specific abnormality that indicates the underlying pathology, guides surgery such as lengthening, osteotomy and fusion, measures the effect of an intervention objectively, and informs physiotherapy protocols and the prescription of assistive devices.
The Phases of the Gait Cycle
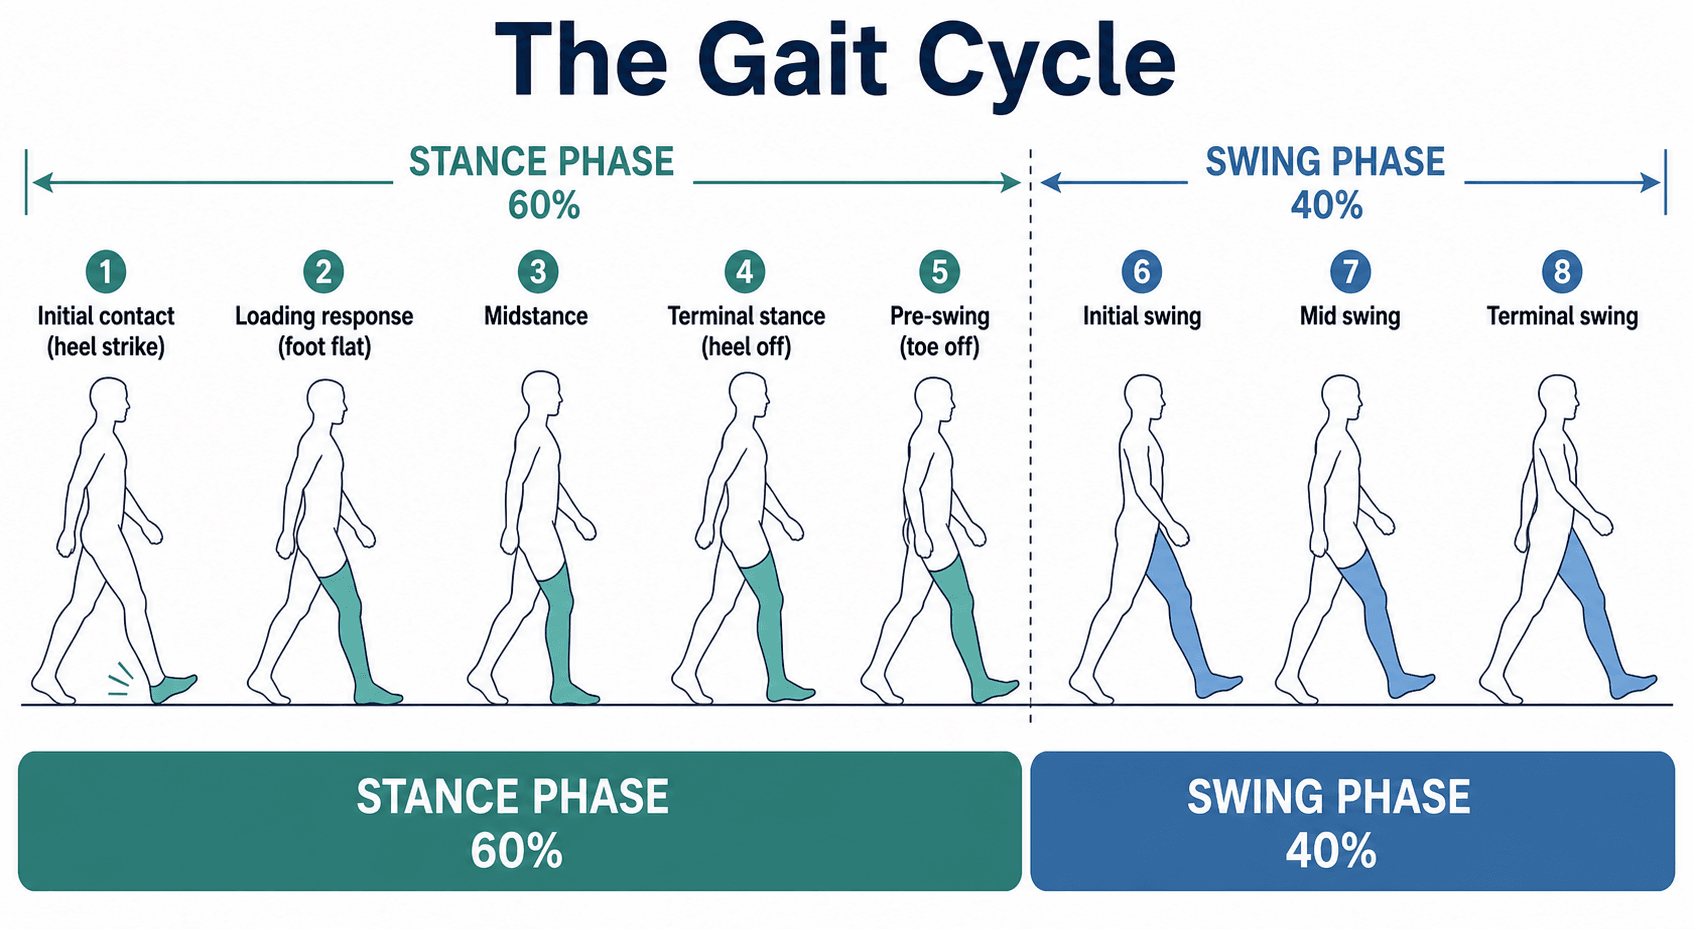
Stance has five phases and swing three. The percentages below are one common scheme; texts draw the boundaries slightly differently, and another scheme puts loading response at 2-12%, midstance at 12-31% and terminal stance at 31-50%, with double support at 0-12% and 50-60%.
Initial contact (0-2%). The first moment the foot touches the ground, historically termed "heel strike".
Loading response (0-10%). From initial contact to contralateral toe-off, this is the first period of double support. It is the phase of shock absorption and weight acceptance.
Midstance (10-30%). Single-limb support begins, and body weight passes over the supporting foot.
Terminal stance (30-50%). From heel rise to contralateral initial contact. The tibia advances over the foot, weight transfers to the forefoot, and this phase generates forward propulsion.
Pre-swing (50-60%). From contralateral initial contact to toe-off, the second period of double support, ending in the final push-off from the hallux. [1,6,7]
I Love My Two PillowsPhases of Stance Phase
Hook:Think of resting on pillows through the stance phase from heel to toe
Initial swing (60-73%). From toe-off until the feet are adjacent. This is the acceleration phase of swing, and the foot clears the ground by approximately 1 cm. [1,8]
Mid-swing (73-87%). From feet adjacent to tibia vertical. The foot maintains its clearance, and muscle activity is at its minimum: the most efficient part of gait.
Terminal swing (87-100%). From tibia vertical to the next initial contact: the deceleration phase, in which the limb prepares for contact. [1,8]
Joint Motion During Gait
Each lower-limb joint follows a characteristic, repeatable angle-versus-cycle curve. Motion is task-specific: the hip and ankle drive progression and power, while the knee provides two flexion waves, one for shock absorption in stance and one for toe clearance in swing. Deviations from these normative curves localise pathology to a joint, a plane and a phase.
The sagittal pattern. The table gives the hip, knee and ankle position through the eight phases.
- Hip
- 30° flexion
- Knee
- Near full extension (0-5° flexion)
- Ankle
- Neutral (0°)
- Hip
- 30° flexion maintained
- Knee
- Flexes to 15-20°
- Ankle
- Plantarflexes 10-15°, controlled by the dorsiflexors
- Hip
- Extends from 30° to 0°
- Knee
- Extends from 15-20° to 5°
- Ankle
- Dorsiflexes from 10° plantarflexion to 5° dorsiflexion
- Hip
- Extends to 10-20° hyperextension
- Knee
- Near full extension (0-5° flexion)
- Ankle
- Dorsiflexes to its maximum (10°) as the tibia advances over the foot
- Hip
- Neutral to slight flexion
- Knee
- Flexes rapidly to 40°
- Ankle
- Plantarflexes rapidly to 20° (passive)
- Hip
- Flexes rapidly to 20°
- Knee
- Flexes to its maximum (60°) for toe clearance
- Ankle
- Dorsiflexes from plantarflexion toward neutral
- Hip
- Continues flexing to 30°
- Knee
- Extends from 60° to 30° (passive pendular motion)
- Ankle
- Reaches neutral (0°)
- Hip
- Maintains 30° flexion
- Knee
- Extends to near full extension (0-5° flexion)
- Ankle
- Maintains neutral
Hip. Sagittal motion totals 40-50°, from maximum flexion of 30° at initial contact and terminal swing to maximum extension of 10-20° in terminal stance. Coronal motion is small, 5-7° in total, with slight abduction during single-limb support and a return to neutral during double support. In the transverse plane the hip rotates internally 5° in loading response and externally 5° in terminal stance, approximately 10° in all. The hip is the primary controller of limb advancement and body progression. [9]
Knee. The knee has the largest range of motion of any lower-limb joint during gait, 0-60°. [9,10]
Ankle. Each part of the ankle's arc has a job. Controlled plantarflexion prevents foot slap, dorsiflexion accommodates the forward progression of the tibia, plantarflexion generates propulsive power, and a neutral position enables toe clearance. [9,10]
Foot and subtalar joint. The foot is supinated at initial contact, a rigid structure for heel contact. It pronates from loading response to midstance, when it is pronated and flattened for shock absorption and adaptation, then resupinates in terminal stance into a rigid lever for push-off as the heel rises. This pronation-supination cycle is essential for shock absorption during loading, adaptation to uneven terrain and conversion to a rigid lever for propulsion. [11]
Muscle Activation Patterns
Tibialis anterior. It contracts concentrically from terminal swing to initial contact to bring the ankle to neutral. Its maximum activity is eccentric, from initial contact through loading response, controlling plantarflexion and preventing foot slap. The ankle dorsiflexors begin activating in pre-swing in preparation for swing and stay active throughout swing to maintain toe clearance. Weakness produces foot drop and a steppage gait; excessive activity is seen in spastic gait patterns. [6,12]
Quadriceps. The quadriceps begin firing during mid-swing and terminal swing to extend the knee for contact. Their maximum activity is eccentric, from initial contact to loading response, controlling knee flexion, and it is critical for shock absorption. Activity decreases through midstance as the knee extends. Weakness produces instability in loading response and may cause knee hyperextension or a flexed-knee gait as compensation. [12]
Hamstrings. They begin activity in mid-swing and reach maximum eccentric activity in terminal swing, decelerating knee extension and controlling hip flexion. They continue at initial contact, decelerating the forward swing of the leg and assisting hip extension in early stance, and their activity decreases from loading response to midstance. [12]
Gastrocnemius-soleus. The complex begins activity in midstance to control tibial advancement and increases progressively to a maximum concentric contraction for push-off in terminal stance, the forefoot rocker. Activity falls rapidly in pre-swing. It generates the majority of propulsive power, contributes to forward acceleration of the centre of mass, and is critical for normal walking speed and efficiency. [6,12]
Hip abductors. Gluteus medius and minimus activate in loading response to stabilise the pelvis, reach maximum activity during single-limb support in midstance, and decrease in terminal stance. They stabilise the pelvis in the coronal plane and prevent contralateral pelvic drop; weakness produces the characteristic Trendelenburg gait. [12,13]
Hip flexors. Iliopsoas and rectus femoris begin activating in pre-swing to initiate swing, and iliopsoas is the primary driver of swing-phase initiation. It contracts concentrically in initial swing to advance the limb, continues into mid-swing and decreases in terminal swing. Rectus femoris is active in initial swing for both hip flexion and the initiation of knee extension. Adductor longus is active in pre-swing for limb advancement, and the short head of biceps femoris assists hip flexion in initial swing. [12]
Hip extensors. Gluteus maximus begins activating in terminal swing for the coming stance and is active at initial contact to control hip flexion. The hip extensors continue through loading response and remain active in terminal stance.
Foot muscles. The intrinsic foot muscles are active in midstance for arch support and reach maximum activity in terminal stance to form the rigid lever. Tibialis posterior is active in terminal stance for supination and arch support.
Ground Reaction Forces
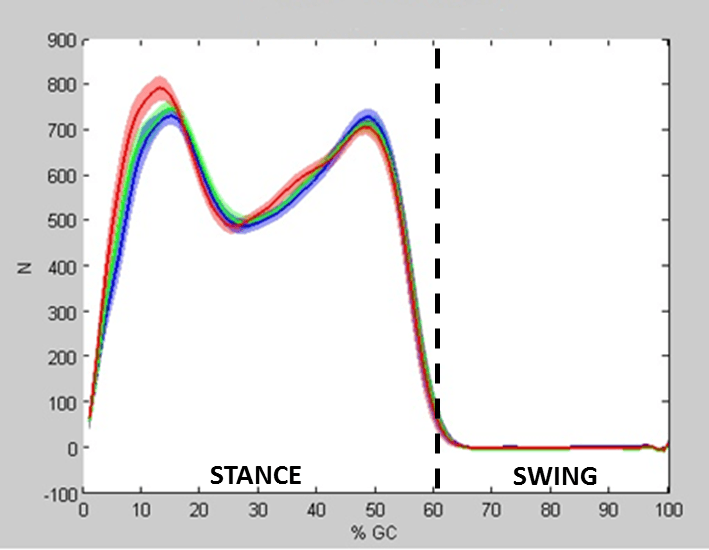
Vertical force. The vertical force begins to rise from zero at initial contact and climbs rapidly to a first peak of 110% body weight in loading response, the peak of weight acceptance and impact absorption. It falls to a valley of 80-90% in midstance as the body passes over the supporting foot in single-limb support, rises to a second peak of 120% in terminal stance with push-off and propulsion, and drops rapidly to zero in pre-swing. The shape of this double hump varies with walking speed and pathology. [7,14]
Fore-aft force. A posterior, braking component begins at initial contact and reaches its maximum of 15-20% body weight over loading response into midstance. The force turns from braking to propulsion in midstance, reaches its anterior, propulsive maximum of 20-25% in terminal stance, and decreases in pre-swing. Braking decelerates forward progression and propulsion accelerates the body forward; in normal gait the two are approximately equal, for a net horizontal acceleration of zero. [7,14]
Mediolateral force. Small, at 5% body weight, it is medially directed in loading response and laterally directed in terminal stance, and it maintains mediolateral stability. [7,14]
Centre of pressure. It starts at the lateral heel at initial contact, progresses forward along the lateral border of the foot through loading response and midstance, moves medially to the metatarsal heads in terminal stance, and terminates at the hallux in pre-swing. The path reflects the foot's rocker mechanism and weight-transfer pattern. [11,14]
Swing. The swinging limb has no ground contact and carries zero force while the contralateral limb is in single support. [1,8]
The Six Determinants of Gait
Saunders, Inman and Eberhart described six major determinants that minimise energy expenditure in normal gait by reducing the vertical and lateral displacement of the centre of mass. [15] In normal gait the centre of mass rises and falls approximately 5 cm.
- Pelvic rotation. The pelvis rotates approximately 4° forward on the swing side, effectively lengthening the limb at initial contact and terminal swing and reducing the amplitude of vertical displacement.
- Pelvic tilt. The pelvis drops approximately 5° on the swing side (contralateral hip adduction), lowering the peak of vertical displacement in single-limb support and flattening the sinusoidal curve of the centre of mass.
- Knee flexion in stance. Flexion of 15-20° in loading response lowers the body at what would otherwise be the highest point, reducing vertical displacement.
- Foot and ankle motion. The foot acts as a rocker in three phases (heel, ankle, forefoot), smoothing the forward progression of the centre of mass and preventing abrupt changes in velocity.
- Knee mechanism. The coordinated knee flexion-extension pattern through stance works with ankle motion to smooth progression and reduces the energy required for limb advancement.
- Lateral pelvic displacement. The pelvis shifts approximately 4-5 cm from side to side, keeping the centre of mass closer to the supporting limb and reducing the need for excessive hip abductor force.
Losing a determinant. Loss of any determinant, from a fused knee or an ankle arthrodesis for example, increases the energy cost of walking by demanding greater muscular effort and increasing vertical displacement. [15,16]
Pathological Gait Patterns
Pattern recognition is the highest-yield exam skill: match the visible deviation to the underlying lesion.
- Key Visible Feature
- Shortened stance on painful limb
- Phase Affected
- Stance
- Underlying Lesion / Cause
- Pain (arthritis, fracture, infection) in any lower-limb joint
- Key Visible Feature
- Contralateral pelvic drop / trunk lean over stance leg
- Phase Affected
- Single-limb stance
- Underlying Lesion / Cause
- Hip abductor weakness - gluteus medius, superior gluteal nerve, hip OA/DDH
- Key Visible Feature
- Exaggerated hip/knee flexion, foot slap
- Phase Affected
- Swing and initial contact
- Underlying Lesion / Cause
- Foot drop - common peroneal palsy, L5 radiculopathy, peripheral neuropathy
- Key Visible Feature
- Forefoot initial contact, no heel strike
- Phase Affected
- Stance
- Underlying Lesion / Cause
- Gastrocnemius-soleus contracture, spastic CP, idiopathic toe-walking
- Key Visible Feature
- Swing limb traces a lateral semicircle
- Phase Affected
- Swing
- Underlying Lesion / Cause
- Functional limb lengthening - stiff/fused knee or ankle, hip flexor weakness, spasticity
- Key Visible Feature
- Rises onto stance-side toes to clear the swing limb
- Phase Affected
- Swing
- Underlying Lesion / Cause
- Inadequate swing-limb clearance (long leg, knee/ankle stiffness, prosthesis)
- Key Visible Feature
- Stiff extended limb, circumduction, equinovarus foot
- Phase Affected
- Whole cycle
- Underlying Lesion / Cause
- Upper motor neurone lesion - stroke, TBI, hemiplegic CP
- Key Visible Feature
- Shuffling short steps, reduced arm swing, stooped posture
- Phase Affected
- Whole cycle
- Underlying Lesion / Cause
- Basal ganglia dysfunction - Parkinson disease, parkinsonism
- Key Visible Feature
- Wide base, irregular step length, instability
- Phase Affected
- Whole cycle
- Underlying Lesion / Cause
- Cerebellar disease or sensory (proprioceptive) ataxia
- Key Visible Feature
- Pelvic drop and trunk dip to short side each step
- Phase Affected
- Stance
- Underlying Lesion / Cause
- True or apparent limb-length discrepancy
Antalgic. Weight transfers rapidly to the opposite limb, the vertical ground reaction force on the affected side is decreased, and hip and knee motion may be decreased. Any painful lower-limb condition can produce it: arthritis of the hip, knee or ankle, fracture or stress fracture, muscle strain or tendinopathy. [17]
Trendelenburg. The weakness is on the stance limb: as the patient stands on the affected leg, the contralateral pelvis drops, and stance time on the affected side is decreased. Leaning the trunk toward the affected side is the compensated Trendelenburg. Beyond the causes in the table, gluteus medius paralysis, L5 radiculopathy (superior gluteal nerve) and nerve injury after hip surgery produce it. [13,17]
Steppage. The toe drags if compensation is inadequate. Anterior compartment syndrome and sciatic nerve injury are further causes. [17]
Equinus. The ankle is excessively plantarflexed throughout stance, stride length is shortened, and the knee may hyperextend in compensation. Achilles tendon shortening and residual or recurrent clubfoot are further causes, and the idiopathic toe walking in the table is seen in children. [17]
Vaulting. It is seen during the swing phase of the affected limb, with excessive plantarflexion of the stance limb. It compensates for a functional leg length discrepancy or an inability to flex the knee or dorsiflex the ankle on the swing side. [17]
Circumduction. The swing limb abducts and externally rotates at the hip, at increased energy expenditure. Limb length discrepancy also causes it, as does spasticity from stroke or cerebral palsy. [17]
Hemiplegic. Knee flexion during swing is also decreased. [17]
Parkinsonian. The posture is flexed at the trunk, hips and knees, the steps festinate (rapid and small), and the patient has difficulty initiating movement. Parkinsonism may be drug-induced or vascular. [17]
Clinical Gait Assessment
From the side. Take each phase in turn against the sagittal pattern above: heel strike, loading, the tibia advancing over the foot, heel rise, toe-off, and the swing-phase knee-flexion peak. Knee hyperextension points to quadriceps weakness or knee instability. [17,18]
From the front and behind. Five things to check:
- Pelvic stability during single-limb support
- Hip abduction-adduction
- Knee varus-valgus alignment
- Foot progression angle (internal or external rotation)
- Base width, normally 5-10 cm
Three-dimensional motion analysis. It is the gold standard for quantifying gait deviations in cerebral palsy, neuromuscular disorders and complex deformities, and is essential in assessing complex deformity. Multiple cameras track reflective markers to measure joint angles in three planes and calculate joint moments and powers. [4,5]
Force plates. They measure ground reaction forces in three directions, calculate the centre-of-pressure trajectory, determine temporal parameters and assess asymmetry between the limbs. [14]
Electromyography. EMG records the timing and amplitude of muscle activation and identifies abnormal firing patterns, and it guides treatment such as selective dorsal rhizotomy and botulinum toxin. [12]
Guidelines, Registries & Global Practice
Global Epidemiology and Clinical Drivers
- Gait disorders are common and rise steeply with age: a frequently cited US community study (Verghese and colleagues) found abnormal gait in roughly one-third of adults over 70, with neurological and multifactorial causes predominating.
- Cerebral palsy, the single largest indication for instrumented gait analysis, has a global prevalence of approximately 2 per 1000 live births, higher in preterm and low-birth-weight infants and in lower-resource perinatal settings.
- Reduced walking speed is an established marker of frailty and predicts falls, hospitalisation and mortality, making spatiotemporal gait a low-cost global health metric.
Guideline and Society Positions (Side by Side)
- Position on Gait Analysis
- Supports 3D instrumented gait analysis to inform single-event multilevel surgery and to evaluate outcomes in cerebral palsy
- Position on Gait Analysis
- Cerebral palsy guidance recommends specialist assessment, with instrumented gait analysis used in tertiary centres before complex multilevel surgery
- Position on Gait Analysis
- Routine use of motion-analysis laboratories for surgical planning and outcome measurement in CP and complex deformity
- Position on Gait Analysis
- Endorse 3D gait laboratories as the reference standard for quantifying gait deviation and guiding orthopaedic intervention
The common thread worldwide: observational analysis is universal and free; instrumented 3D analysis is reserved for complex (mainly neuromuscular) cases and for pre-/post-surgical assessment, with concentration in tertiary referral laboratories.
Standardisation and Outcome Measures
- There is no implant/arthroplasty-style registry for gait; instead, standardisation comes from shared marker models (Helen Hayes / Plug-in-Gait, derived from Kadaba's work) and validated summary scores - the Gait Deviation Index (GDI) and the Gait Profile Score (GPS) - which enable comparison across laboratories.
- Movement-analysis societies (e.g. ESMAC in Europe, GCMAS in North America) publish laboratory accreditation and good-practice standards to improve cross-centre comparability.
High- vs Limited-Resource Practice Variation
- High-resource settings: dedicated optoelectronic gait laboratories with force plates, dynamic EMG and, increasingly, markerless/wearable systems; routine pre-operative analysis for cerebral palsy multilevel surgery.
- Limited-resource settings: reliance on structured observational gait analysis (Edinburgh Visual Gait Score, Physician Rating Scale), smartphone video and timed walk tests (10-metre and 6-minute walk), which are validated, portable and inexpensive substitutes that capture most clinically actionable information.
Controversies and Areas of Uncertainty
Gait analysis is mature science, but several issues remain genuinely debated and are favourite "higher-order" viva topics.
- Validity of the six determinants of gait. The Saunders/Inman/Eberhart model remains the standard teaching framework, yet dynamic-walking and inverted-pendulum studies (e.g. Gard and colleagues) showed that pelvic rotation and pelvic list contribute little to flattening the centre-of-mass trajectory. The determinants are now best taught as a conceptual scaffold rather than a quantitatively exact energy model.
- Clinical impact of instrumented 3D gait analysis. It is the reference standard for quantifying deviations, but high-level evidence that it changes hard outcomes is limited. It demonstrably alters and often de-escalates surgical recommendations in cerebral palsy, yet routine 3D analysis before all multilevel surgery is not universally funded or adopted, and reliability depends on marker placement and modelling.
- Single global indices vs full curve interpretation. Summary scores such as the Gait Deviation Index and Gait Profile Score give reproducible severity tracking, but a single number can mask which joint or plane is abnormal; experts disagree on how far they should replace expert reading of kinematic curves.
- Terminology and normative ranges. "Heel strike" versus "initial contact", differing phase percentage boundaries between texts, and laboratory-specific normative bands mean reported joint angles and force values are approximate and method-dependent rather than fixed constants.
- Markerless and wearable gait analysis. Inertial-sensor and video/AI markerless systems are rapidly emerging as cheaper, clinic-friendly alternatives, but their agreement with gold-standard optoelectronic systems and their role in surgical decision-making are still being established.
High-Yield MCQ Topics
Temporal Parameters
- Stance phase = 60% of gait cycle
- Swing phase = 40% of gait cycle
- Double support = 20% total (10% at beginning and end of stance)
- Single support = 40% of cycle
- As walking speed increases, stance time decreases and swing time increases
Ground Reaction Forces
- First peak: 110% body weight (loading response)
- Valley: 80-90% body weight (midstance)
- Second peak: 120% body weight (terminal stance)
- Braking force maximum: 15-20% body weight
- Propulsive force maximum: 20-25% body weight
Joint Range of Motion
- Hip: 30 degrees flexion to 20 degrees extension (total 50 degrees)
- Knee: 0-60 degrees flexion (maximum at initial swing)
- Ankle: 10 degrees dorsiflexion to 20 degrees plantarflexion (total 30 degrees)
Muscle Activation
- Loading response: quadriceps eccentric (shock absorption)
- Terminal stance: gastrocnemius-soleus concentric (propulsion)
- Midstance: hip abductors maximum (pelvic stability)
- Terminal swing: hamstrings eccentric (knee deceleration)
Pathological Gait Recognition
- Trendelenburg = hip abductor weakness (gluteus medius)
- Steppage = foot drop (tibialis anterior weakness)
- Antalgic = shortened stance on painful side
- Equinus = toe walking (gastrocnemius contracture)
Joint Moments and Powers: the Kinetics of Gait
- Internal (net) joint moment. The ground reaction force acts at a distance (a moment arm) from each joint, creating an external moment that tends to collapse the limb; the muscles and passive structures generate an equal-and-opposite internal moment to control it. The net internal moment through the cycle is the kinetic signature of what the muscles are doing. Example: at loading the GRF passes behind the knee (external flexion moment → the quadriceps generate an internal EXTENSOR moment); at midstance the GRF passes in front of the knee (external extension moment → the knee is passively stable and quadriceps demand falls). The "support moment" - the sum of the hip, knee and ankle sagittal moments - stays net-extensor through stance to stop the limb collapsing, a key stability concept.
- Joint power = moment x joint angular velocity. Positive power = the muscle is generating energy (concentric, shortening) - a "burst"; negative power = the muscle is absorbing energy (eccentric, lengthening) - a "sink". This converts the qualitative "eccentric/concentric" description into a measurable quantity.
- The classic power profile (Winter). The ankle shows early absorption (controlled dorsiflexion in stance) then a large positive-work push-off burst ("A2") at terminal stance - the single biggest power generator in gait; the knee shows several smaller absorption/generation phases; the hip contributes a pull-off/flexion burst. This is exactly why calf weakness, ankle fusion or a below-knee amputation is so disabling - the dominant A2 power source is lost.
- Why it matters clinically. Moments and powers, not angles alone, reveal which muscle group is failing or over-working and where mechanical energy is lost - the basis of instrumented-gait surgical decisions such as tendon transfers (see the Dreher rectus-transfer trial).
Q: What is the difference between a joint moment and a joint power in gait? A: The internal joint moment is the net muscular effort opposing the external ground-reaction-force moment (e.g. an internal knee EXTENSOR moment at loading resists the GRF trying to flex the knee); the sum across hip/knee/ankle is the net-extensor support moment that keeps the limb from collapsing. Joint power = moment x angular velocity: positive = energy generation (concentric burst), negative = absorption (eccentric sink). The ankle A2 push-off burst is the largest power generator in gait, which is why losing it (calf weakness, ankle fusion, BKA) is so costly.
The Inverted Pendulum Model and Pendular Energy Exchange
The inverted-pendulum model is what the six determinants of gait were tested against, and the whole energy-conservation account of walking rests on it - so it is worth understanding directly.
- The model. During single-limb stance the body vaults over the relatively stiff stance leg like an inverted pendulum pivoting at the foot: the centre of mass rises to its highest point at midstance and falls during double support, tracing a smooth arc rather than a flat line.
- Energy exchange is the whole point. In a pendulum, potential energy (PE) and kinetic energy (KE) trade back and forth out of phase. At midstance the COM is highest and slowest - maximum PE, minimum KE; at double support it is lowest and fastest - minimum PE, maximum KE. Because they are out of phase, much of the energy is exchanged passively rather than supplied by muscle - normal walking recovers roughly 60-70% of the mechanical energy this way, which is why level walking is metabolically cheap.
- How it reframes Perry's determinants. The Saunders/Inman determinants were taught as flattening the COM path to save energy; the inverted-pendulum view shows that a smooth pendular arc (not a flat path) is what maximises PE-KE exchange, and modelling (Gard and colleagues) found pelvic rotation and pelvic list actually contribute little - so the determinants are best treated as a teaching scaffold, with the inverted pendulum the better mechanical account of walking economy.
- Clinical corollary. Anything that disrupts the pendulum - a stiff/fused joint that cannot vault smoothly, an antalgic gait that shortens stance, or loss of the ankle push-off that re-launches the COM into the next step - breaks the PE-KE exchange and raises the metabolic cost of walking (as the Waters energy-expenditure data quantify).
Q: What is the inverted pendulum model and why does it explain the low energy cost of walking? A: In stance the body vaults over the stiff stance limb like an inverted pendulum; potential and kinetic energy exchange out of phase (max PE/min KE at midstance, min PE/max KE at double support), so about 60-70% of the mechanical energy is recovered passively without muscular work. It reframes Perry's determinants (a smooth pendular arc, not a flattened COM path, maximises the exchange; pelvic rotation/list add little - Gard). Losing the smooth vault (fused joint, antalgic gait, absent ankle push-off) breaks the exchange and raises walking energy cost.
MCQ Practice Points
Q: What are the phases of the gait cycle and their relative durations?
A: Stance phase: 60% of cycle (heel strike to toe-off). Swing phase: 40% of cycle (toe-off to heel strike). Stance subdivided: initial contact (0-2%), loading response (2-12%), mid-stance (12-31%), terminal stance (31-50%), pre-swing (50-60%). Double limb support occurs at 0-12% and 50-60%.
Q: What are the six determinants of gait described by Saunders?
A: 1) Pelvic rotation (4° each direction), 2) Pelvic tilt (5° drop on swing side), 3) Knee flexion in stance (15-20°), 4) Foot mechanisms (ankle plantarflexion/dorsiflexion), 5) Knee mechanisms, 6) Lateral displacement of pelvis. These minimize vertical and lateral center of mass displacement, reducing energy expenditure.
Q: What muscle activity occurs during loading response phase of gait?
A: Tibialis anterior: Eccentric contraction controlling plantarflexion (foot slap prevention). Quadriceps: Eccentric contraction controlling knee flexion. Gluteus maximus/medius: Hip stabilization. This phase absorbs impact forces as body weight transfers onto the limb. Peak ground reaction force occurs here.
Q: What causes Trendelenburg gait?
A: Weakness of hip abductors (gluteus medius/minimus) on stance side causes contralateral pelvis to drop during single-limb support. Patient compensates with trunk lean toward affected side (compensated Trendelenburg). Causes: L5 radiculopathy, superior gluteal nerve injury, hip pathology, abductor mechanism failure post-THA.
Q: What is the center of mass displacement during normal gait?
A: Normal gait has approximately 5cm vertical displacement (sinusoidal pattern, lowest at double support, highest at mid-stance) and 4cm lateral displacement (side to side with each step). The determinants of gait minimize these excursions. Greater displacement = increased energy expenditure.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“An examiner asks you to describe the phases of the gait cycle and their relative durations. They then ask about the muscle activity patterns during these phases.”
“A 65-year-old patient presents with a noticeable limp. On observation, you note that the pelvis drops on the right side when standing on the left leg. The examiner asks you to explain this finding and its underlying causes.”
“The examiner presents a patient with bilateral ankle arthrodesis who complains of fatigue with walking. They ask you to explain why ankle fusion increases the energy cost of gait.”
Temporal Divisions
- Stance phase: 60% of cycle (initial contact to toe-off)
- Swing phase: 40% of cycle (toe-off to next initial contact)
- Double support: 20% total (10% early stance, 10% late stance)
- Single support: 40% of cycle (contralateral limb in swing)
Stance Phase Subdivisions
- Initial contact (0-2%): heel strike, knee extended
- Loading response (0-10%): foot flat, knee flexes 15 degrees, first double support
- Midstance (10-30%): single limb support, body over foot
- Terminal stance (30-50%): heel rise, maximum ankle dorsiflexion
- Pre-swing (50-60%): toe-off, rapid knee flexion, second double support
Swing Phase Subdivisions
- Initial swing (60-73%): acceleration, knee flexion to 60 degrees
- Mid-swing (73-87%): toe clearance, passive knee extension
- Terminal swing (87-100%): deceleration, knee extends, prepare for contact
Key Muscle Actions
- Tibialis anterior: eccentric loading response (prevent foot slap), active swing (toe clearance)
- Quadriceps: eccentric loading response (control knee flexion 15-20 degrees)
- Gastrocnemius-soleus: concentric terminal stance (push-off, 120% BW force)
- Gluteus medius: maximum midstance (pelvic stability, prevent Trendelenburg)
- Hamstrings: eccentric terminal swing (decelerate knee extension)
Ground Reaction Forces
- Vertical GRF: first peak 110% BW (loading), valley 80-90% BW (midstance), second peak 120% BW (push-off)
- Anterior-posterior: braking 15-20% BW, then propulsion 20-25% BW
- Mediolateral: small amplitude 5% BW for lateral stability
Joint ROM During Gait
- Hip: 30 degrees flexion to 20 degrees extension (total 50 degrees)
- Knee: 0 degrees to 60 degrees flexion (max at initial swing, 15-20 degrees at loading response)
- Ankle: 10 degrees dorsiflexion (terminal stance) to 20 degrees plantarflexion (pre-swing)
Perry's Six Gait Determinants
- 1. Pelvic rotation (4 degrees forward on swing side)
- 2. Pelvic tilt (5 degrees drop on swing side)
- 3. Knee flexion during stance (15-20 degrees at loading response)
- 4. Foot-ankle motion (three rockers: heel, ankle, forefoot)
- 5. Knee mechanism (coordinated flexion-extension)
- 6. Lateral pelvic displacement (4-5 cm side-to-side)
- Function: minimize vertical and lateral displacement of center of mass to conserve energy
Pathological Gait Patterns
- Trendelenburg: pelvic drop on unsupported side = hip abductor weakness (gluteus medius)
- Antalgic: shortened stance on painful limb = pain avoidance
- Steppage: excessive hip/knee flexion in swing = foot drop (tibialis anterior weakness)
- Equinus: toe walking, forefoot initial contact = gastrocnemius contracture
- Vaulting: rising on stance toes = inadequate swing limb clearance
- Circumduction: swing limb traces semicircle = limb length discrepancy or joint stiffness
Energy Expenditure
- Normal walking: 0.063 mL O2/kg/m
- Bilateral ankle fusion: 20-30% increase in metabolic cost
- Hemiplegic gait: 60% increase
- Loss of any gait determinant increases energy cost
- Rocker-bottom shoes can partially restore efficiency after ankle fusion
Evidence Base and Key Studies
The Major Determinants in Normal and Pathological Gait (Foundational Theory)
- Described six kinematic determinants that flatten the sinusoidal path of the body centre of mass and so reduce the energy cost of walking
- The six determinants: pelvic rotation, pelvic tilt (list), knee flexion in stance, foot-ankle interaction (rockers), knee-ankle interaction, and lateral pelvic displacement
- Argued that loss of any determinant (e.g. a fused joint) forces compensatory motion and raises metabolic demand
The Development of Mature Gait - Landmark EMG/Kinematic Series
- Combined cinematography, force-plate and EMG data to define normal and maturing gait in children
- Identified five maturity determinants and showed adult-pattern gait is essentially established by about age 7
- Documented the phasic timing of muscle activity (e.g. quadriceps at loading response, gastrocnemius-soleus at terminal stance) that underpins modern gait interpretation
Energy Generation and Absorption at the Ankle and Knee (Joint Power Analysis)
- Biomechanical analysis of 15 normal adults at slow, natural and fast cadences
- The ankle has two power phases: negative work (absorption) during weight acceptance then a dominant positive-work burst at push-off, identifying the plantarflexors as the prime movers of forward propulsion
- The dominant plantarflexor push-off burst falls as walking speed decreases; the knee shows four distinct power phases
Measurement of Lower Extremity Kinematics During Level Walking (3D Marker Model)
- Developed and validated an external marker set and Euler-angle algorithms (the basis of the Helen Hayes / Plug-in-Gait model) on a VICON system
- Gait analysis repeated on 40 normal young adults across three separate test days produced repeatable hip, knee, ankle and pelvis angle curves
- Quantified the effect of marker-placement and embedded-axis uncertainty on joint-angle error
Energy Expenditure of Normal and Pathologic Gait (Comprehensive Review)
- Synthesised oxygen-consumption data across neurological and orthopaedic conditions, using the rate of energy expenditure and energy cost per metre as the key metrics
- Pathological gait raises energy cost broadly in proportion to the level and severity of disability, with patients typically self-selecting a slower speed to keep the rate of expenditure near normal
- Hemiplegic, paraplegic and high-level amputation gaits carry the largest penalties; more proximal amputation and greater neurological involvement cost more
Comfortable and Maximum Walking Speed - Reference Values (Age 20-79)
- 230 healthy adults timed over a 7.62 m walkway, generating decade- and sex-specific reference speeds
- Comfortable speed ranged from ~127 cm/s (women in their 70s) to ~146 cm/s (men in their 40s); maximum speed up to ~253 cm/s in young men
- Walking speed correlated with age, height and lower-limb muscle strength and was highly reliable (coefficients greater than 0.9)
The Significance of the Trendelenburg Test (Standardisation Study)
- Examined 50 normal subjects and 103 patients with spine or hip disorders to standardise single-leg stance testing
- Defined the test as an assessment of hip abductor function and specified a standard performance method
- Catalogued the main false-positive (pain, poor cooperation, rib-iliac impingement) and false-negative (trunk/pelvic compensation) pitfalls
The Gait Deviation Index (GDI) - Comprehensive Index of Gait Pathology
- Derived a multivariate, single-number index of overall gait pathology from 15 independent kinematic gait features
- GDI is scaled so 100 represents the mean of typically developing children and every 10 points below 100 is one standard deviation of pathology
- Validated against the Gillette Gait Index and functional walking scales and shown to track severity across cerebral palsy topographical types
Distal Rectus Femoris Transfer in Multilevel Surgery - Randomized Trial
- 32 children with spastic diplegia indicated for distal rectus femoris transfer (DRFT) randomised to single-event multilevel surgery with or without DRFT, with 3D gait analysis at baseline and 1 year
- Peak knee flexion in swing was preserved in the DRFT group but fell in the non-DRFT group; benefit was confined to patients with a pre-operative knee-flexion deficit (stiff-knee gait)
- Around one third of DRFT patients did not benefit and roughly half of non-DRFT patients avoided an unnecessary procedure, so DRFT is not recommended as a prophylactic add-on for severe flexed-knee gait
References
- Perry J, Burnfield JM. Gait Analysis: Normal and Pathological Function. 2nd ed. Thorofare, NJ: SLACK Incorporated; 2010.
- Whittle MW. Gait Analysis: An Introduction. 4th ed. Edinburgh: Butterworth-Heinemann; 2007.
- Bohannon RW. Comfortable and maximum walking speed of adults aged 20-79 years: reference values and determinants. Age Ageing. 1997;26(1):15-19. doi:10.1093/ageing/26.1.15
- Baker R. Measuring Walking: A Handbook of Clinical Gait Analysis. London: Mac Keith Press; 2013.
- Gage JR, Schwartz MH, Koop SE, Novacheck TF. The Identification and Treatment of Gait Problems in Cerebral Palsy. 2nd ed. London: Mac Keith Press; 2009.
- Sutherland DH, Olshen R, Cooper L, Woo SL. The development of mature gait. J Bone Joint Surg Am. 1980;62(3):336-353.
- Winter DA. Biomechanics and Motor Control of Human Movement. 4th ed. Hoboken, NJ: John Wiley & Sons; 2009.
- Murray MP, Drought AB, Kory RC. Walking patterns of normal men. J Bone Joint Surg Am. 1964;46:335-360.
- Kadaba MP, Ramakrishnan HK, Wootten ME. Measurement of lower extremity kinematics during level walking. J Orthop Res. 1990;8(3):383-392. doi:10.1002/jor.1100080310
- Neumann DA. Kinesiology of the Musculoskeletal System: Foundations for Rehabilitation. 3rd ed. St Louis, MO: Elsevier; 2017.
- Leardini A, Benedetti MG, Berti L, et al. Rear-foot, mid-foot and fore-foot motion during the stance phase of gait. Gait Posture. 2007;25(3):453-462. doi:10.1016/j.gaitpost.2006.05.017
- Perry J. Gait Analysis: Normal and Pathological Function. Thorofare, NJ: SLACK Incorporated; 1992.
- Hardcastle P, Nade S. The significance of the Trendelenburg test. J Bone Joint Surg Br. 1985;67(5):741-746. doi:10.1302/0301-620X.67B5.4055873
- Whittle MW. Gait analysis in the assessment of soft tissue injuries. Defense Sci J. 1999;49(5):437-443. doi:10.14429/dsj.49.3852
- Saunders JB, Inman VT, Eberhart HD. The major determinants in normal and pathological gait. J Bone Joint Surg Am. 1953;35(3):543-558.
- Gard SA, Childress DS. The effect of pelvic list on the vertical displacement of the trunk during normal walking. Gait Posture. 1997;5(3):233-238. doi:10.1016/S0966-6362(96)01089-2
- Kirtley C. Clinical Gait Analysis: Theory and Practice. Edinburgh: Churchill Livingstone; 2006.
- Waters RL, Mulroy S. The energy expenditure of normal and pathologic gait. Gait Posture. 1999;9(3):207-231. doi:10.1016/S0966-6362(99)00009-0