Nucleus Pulposus | Annulus Fibrosus | Endplates | Nutrition | Degeneration
- Nucleus pulposus: 80% water, Type II collagen, gelatinous, resists compression
- Annulus fibrosus: 15-20 lamellae, Type I collagen at ±30°, resists tension and torsion
- Avascular after age 20 - nutrients diffuse through endplates (major limitation to healing)
- Disc height loss with degeneration → facet joint overload → osteoarthritis cascade
- Endplate injury disrupts nutrition → accelerates degeneration (Modic changes)
- “Viva opener: 'Draw the intervertebral disc showing annular fibre orientation'
- “Key biomechanical function: Compression resistance (nucleus) + tensile/torsional resistance (annulus)
- “Disc degeneration is biochemical before structural - proteoglycan loss → water loss → height loss
- “Pfirrmann grading (MRI T2): Grade I (white) → Grade V (black, collapsed)
Overview and Introduction
Gross Anatomy
The intervertebral disc has three components: a central nucleus pulposus, a peripheral annulus fibrosus, and a cartilaginous endplate above and below.
The nucleus pulposus. A gelatinous, hydrated core, 80% water at birth and down to 70% by age 60. Randomly oriented Type II collagen and aggrecan make up its matrix, and it resists compressive load through hydrostatic pressure. It sits slightly posterior to the anatomical centre, which matters for the pathomechanics of herniation.
The annulus fibrosus. 15-20 concentric lamellae of Type I collagen, the fibres set at ±30° from horizontal and alternating in direction from one layer to the next. The lamellae insert predominantly into the hyaline cartilaginous endplate. The change from the outer fibrous annulus to the inner, proteoglycan-rich region is gradual, so alternating fibre direction and gradual transition create tensile restraint without an abrupt nucleus-annulus boundary: the inner annulus blends into the nucleus with no clear boundary. The anterior annulus is thicker than the posterior, and the posterior is the more prone to tear.
Its nerve supply. The outer annulus contains pain fibres, from the recurrent meningeal nerve of Luschka.
The cartilaginous endplates. A thin layer of hyaline cartilage, 0.6-1.0 mm thick, covering the vertebral body endplate on each side of the disc. The endplate is the primary route for disc nutrition, by diffusion, and the weakest structural component of the disc, vulnerable to trauma. It combines chondrocyte-like cells with a distinct collagen architecture suited to diffusion and load transfer.
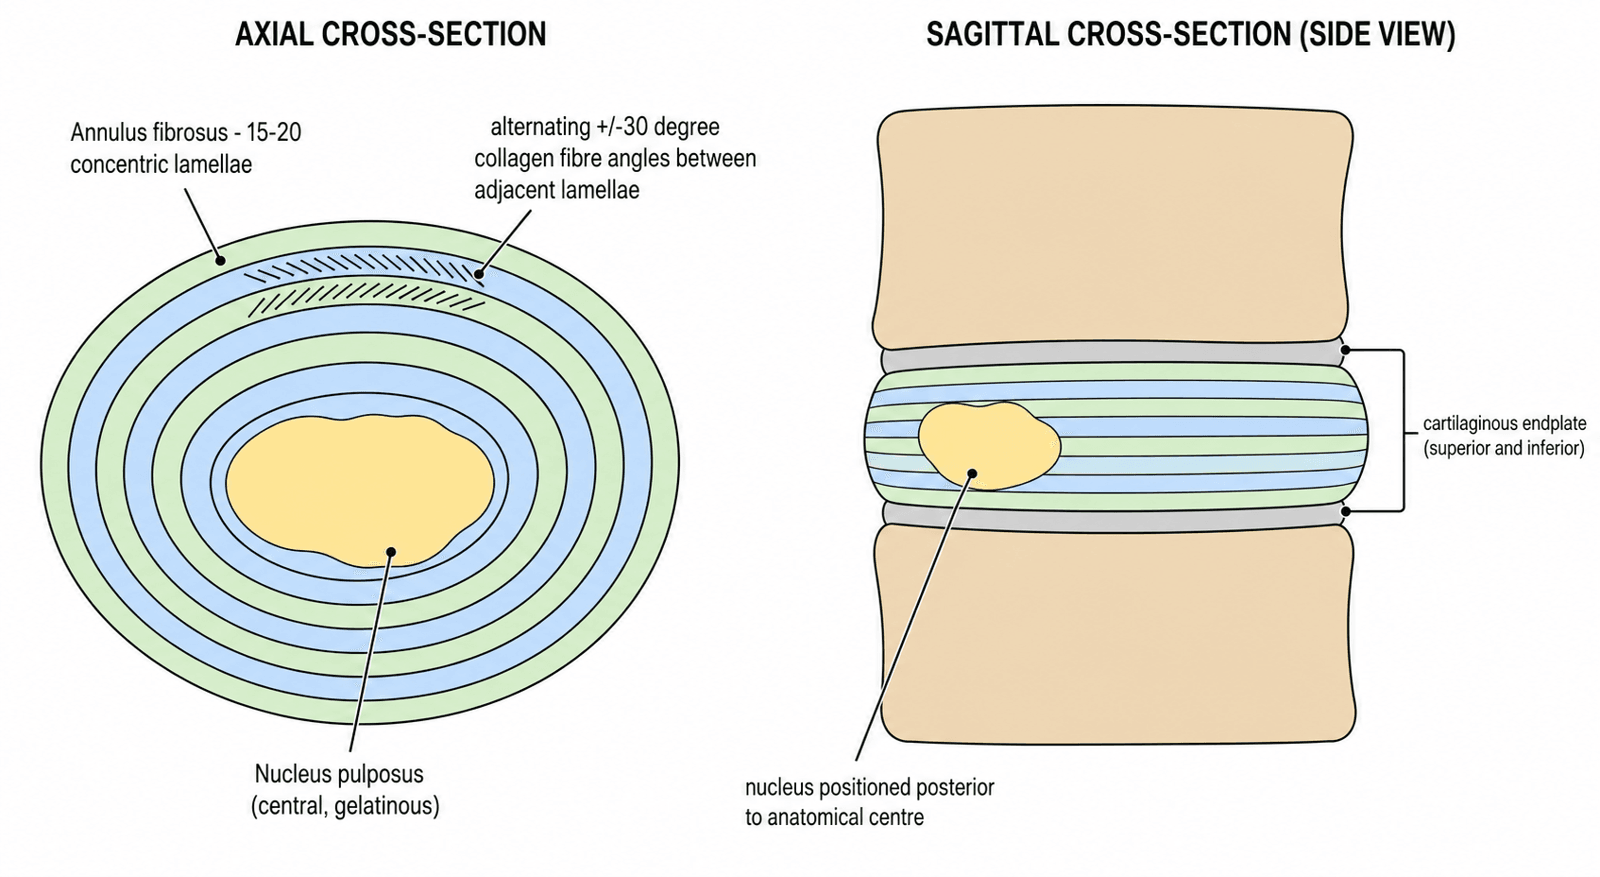
Why the fibres cross. The alternating ±30° layers of the annulus:
- Resist tensile loads in any direction
- Resist torsional (rotational) loads
- Confine the nucleus centrally under compression
- Prevent nuclear herniation, when intact
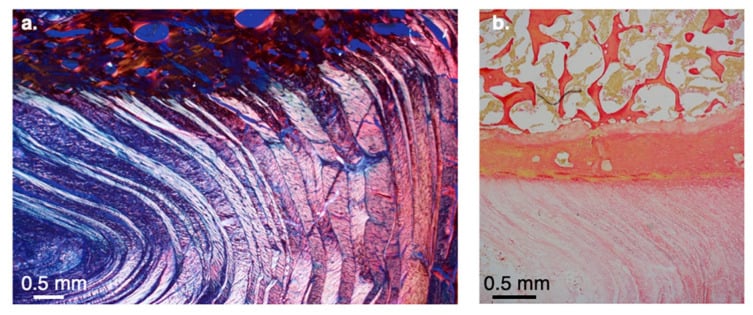
Concepts and Molecular Biology
Matrix and Cells
- Nucleus pulposus
- 70-80% (age-dependent)
- Annulus fibrosus
- 60-70%
- Nucleus pulposus
- 50-65% dry weight (mainly aggrecan)
- Annulus fibrosus
- 10-20% dry weight
- Nucleus pulposus
- 15-20% dry weight (Type II, random orientation)
- Annulus fibrosus
- 50-60% dry weight (Type I)
- Nucleus pulposus
- Notochordal cells (young), chondrocyte-like cells (adult)
- Annulus fibrosus
- Fibrochondrocytes
What each part of the matrix does. In the nucleus, aggrecan retains water and Type II collagen is the scaffold. In the annulus, Type I collagen gives tensile strength and elastin gives elasticity. The endplate's hyaline cartilage, collagen and proteoglycans allow nutrients to pass. The matrix undergoes significant changes with age and degeneration.
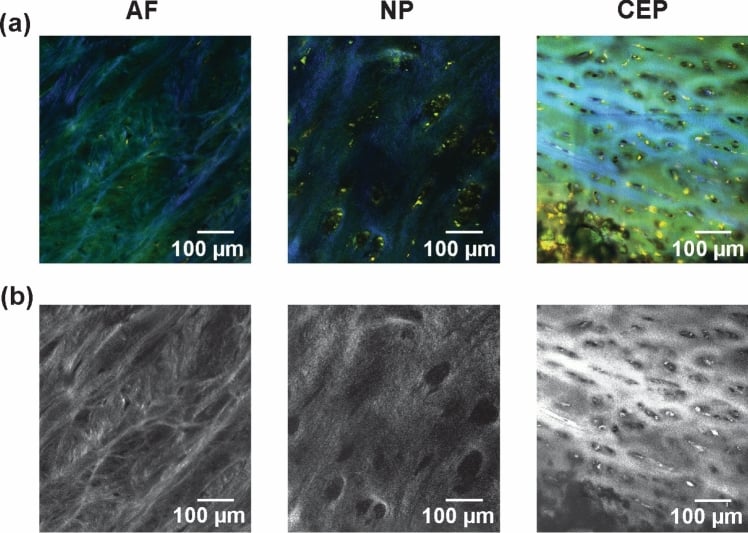
The cells. Cell density is very low, and the sparse cells rely entirely on diffusion for their oxygen and glucose.
Notochordal Cells: the Disc's Unique Cell Population and Why Their Loss Matters
The notochordal cell. The embryonic notochord persists as the nucleus pulposus, populated by large, vacuolated notochordal cells. They are highly anabolic, producing abundant aggrecan-rich matrix and maintaining the hydrated, gel-like nucleus.
Lost early in humans. In humans these cells are largely lost during the first decade of life, much earlier than in many animals, some of which keep them lifelong. Smaller, less productive chondrocyte-like cells replace them.
The regenerative angle. Notochordal cells and the factors they secrete are potent matrix producers. That makes them, and mesenchymal stem cells intended to behave like them, a major target of biological disc-regeneration research (the MSC-injection proof-of-concept work), though this remains investigational.
Q: Why does the human disc begin to degenerate so much earlier than other connective tissues? A: Once the notochordal cells have gone, the sparse, less-productive chondrocyte-like cells that remain sit in an avascular, hypoxic, low-pH niche with a failing endplate blood supply. They cannot keep pace with matrix (aggrecan) turnover, so breakdown begins in the second decade, earlier than in any other connective tissue.
Biomechanical Function
Load Distribution
A hydraulic system. The disc bears load hydraulically. Under compression the nucleus is subjected to hydrostatic pressure and tries to expand radially; the annulus resists that expansion as hoop stress in its fibres, and the load is distributed evenly across the vertebral endplate.
Flexion and extension. In flexion the anterior annulus is compressed, the posterior annulus is tensioned and the nucleus shifts posteriorly, which puts stress on the posterior annulus. Extension reverses all three: the posterior annulus is compressed, the anterior tensioned, and the nucleus shifts anteriorly.
Lateral bending and rotation. Both load the annular lamellae asymmetrically, and the crossed fibres resist torsion. In rotation the nucleus shows minimal response, but rotation is the most damaging motion because of the shear forces it places on the annulus.
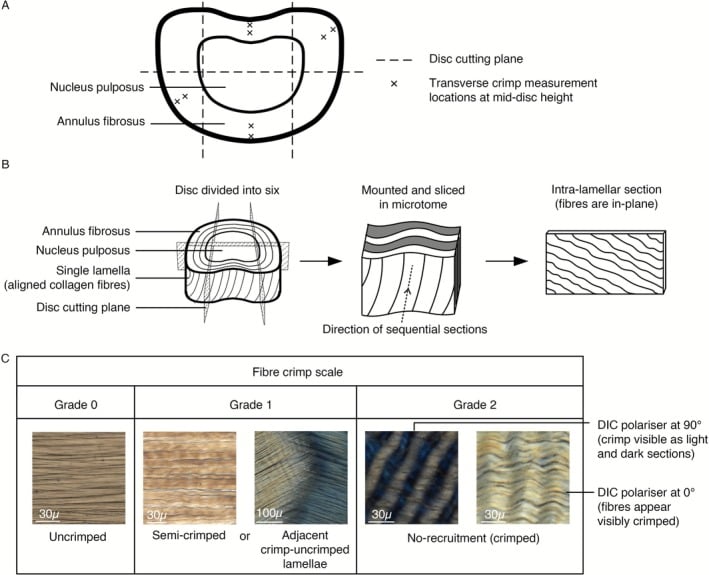
Fibre recruitment. Annular collagen bundles are wavy (crimped). Physiological loading recruits them sequentially rather than loading every lamella at once, and in bending the fibres straighten on the tensile side while remaining crimped elsewhere. That regional recruitment, with the alternating lamellae, is how the annulus resists complex bending and torsion without behaving as a homogeneous ring.
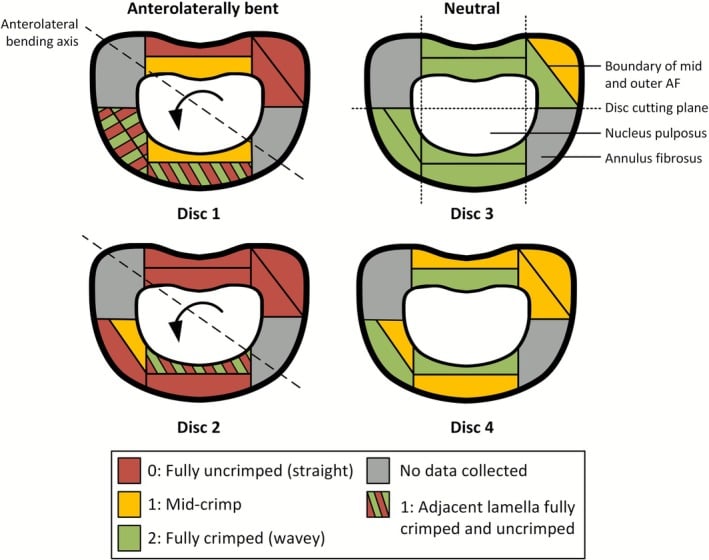
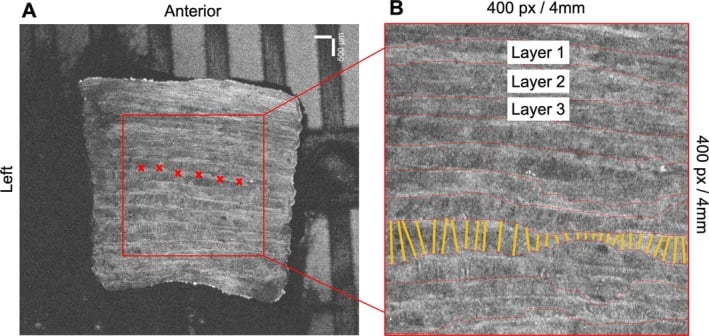
Anisotropy. The layered annulus is mechanically anisotropic: its shear stiffness depends on whether force is applied radially, across the layers, or circumferentially, along them.
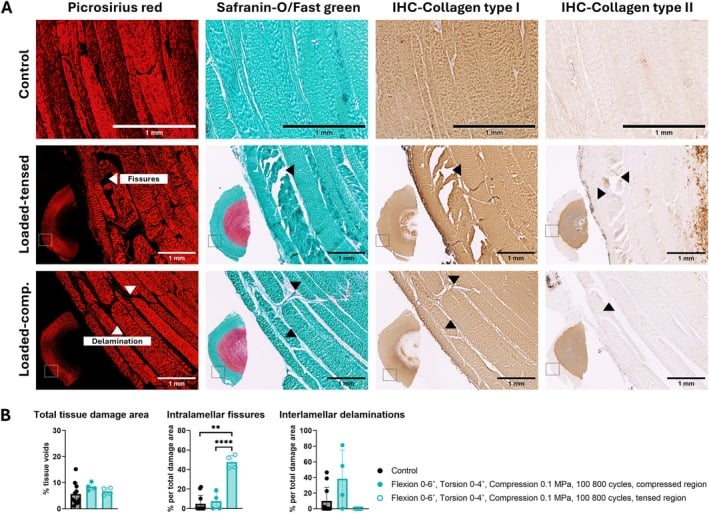
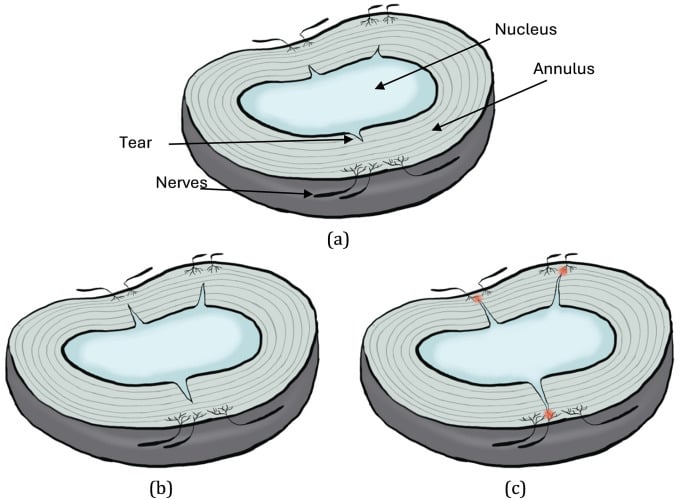
Combined loading. Repeated asymmetric flexion, torsion and compression disrupt the outer-annular lamellae, create intralamellar fissures and delamination, and alter collagen organisation. Combined loading fails the disc through tissue-specific mechanisms rather than simple compression alone.
Viscoelastic Properties
Time-dependent behaviour. The disc is viscoelastic. With age its water content falls, and its viscoelasticity falls with it.
- Creep: under constant load, disc height decreases over time as fluid is exuded
- Stress relaxation: under constant deformation, internal stress decreases over time
The diurnal cycle. Fluid is expressed during the day and reabsorbed overnight. The result is a diurnal stature change of roughly 15-20mm across all discs combined, each disc losing on the order of 1mm, with intradiscal pressure highest after a night of rest.
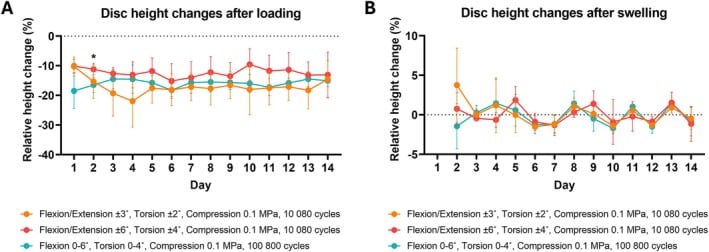
Recovery. Experimentally, height recovers only partially during unloaded free swelling, and more aggressive asymmetric cyclic loading progressively impairs recovery.
Why it matters clinically. This is why back pain is often worse in the morning, when the disc is fully hydrated and intradiscal pressure is at its maximum. It is also why prolonged standing or sitting causes symptoms, through creep deformation.
The Donnan Osmotic (Swelling) Pressure: How the Disc Resists Compression at a Molecular Level
Fixed negative charge. Aggrecan carries densely packed glycosaminoglycan chains (chondroitin and keratan sulphate), studded with negatively charged carboxyl and sulphate groups. The result is a high fixed-charge density trapped in the matrix.
The Donnan effect. These fixed anions draw in mobile cations, mainly sodium, raising the ion concentration inside the disc above that of its surroundings. Water follows osmotically and generates a swelling (imbibition) pressure that inflates the nucleus.
Load balance. At equilibrium the swelling pressure is balanced by the applied compressive load and the tension it places on the annular fibres. Under sustained load water is expressed (creep) until the rising charge concentration restores balance, and it is reimbibed at rest (the diurnal cycle). This osmotic mechanism, not the water alone, is how the nucleus generates and sustains its hydrostatic (intradiscal) pressure.
Why degeneration destroys it. Aggrecan loss lowers the fixed-charge density, so the disc can no longer hold water or generate swelling pressure. The nucleus depressurises and load shifts abnormally onto the annulus and facets, which is why degeneration is biochemical before it is structural. The molecular structure of aggrecan and GAGs is developed in the proteoglycans-collagen topic.
Nutrition and Metabolism
Avascular Nature
The largest avascular structure. The adult disc is the largest avascular structure in the human body. In childhood blood vessels penetrate the endplates, but they regress, and by age 20 diffusion is the only route of nutrition.
The longest diffusion pathway. Nutrients travel up to 8mm from the endplate to the central nucleus. The cells in the centre of the disc are the furthest from a blood supply of any in the body, and the most vulnerable to nutrient deprivation.
The avascular nature of the disc is the primary reason discs do not heal once injured. No blood supply means no inflammatory cells and no repair cascade; cell density is too low for adequate regenerative capacity; and the biochemical environment is hostile, with catabolic cytokines.
Bone, tendon and ligament are fundamentally different: their vascularity gives them robust healing capacity. This is why conservative treatment of the disc focuses on symptom management.
Nutrient Transport
Diffusion Pathway for Disc Nutrition
Nutrients (oxygen, glucose) in vertebral body capillaries adjacent to the endplate.
Nutrients diffuse through the porous cartilaginous endplate.
Nutrients diffuse through the disc matrix to reach the central nucleus cells.
Nucleus pulposus cells metabolise nutrients anaerobically, in a low-oxygen environment.
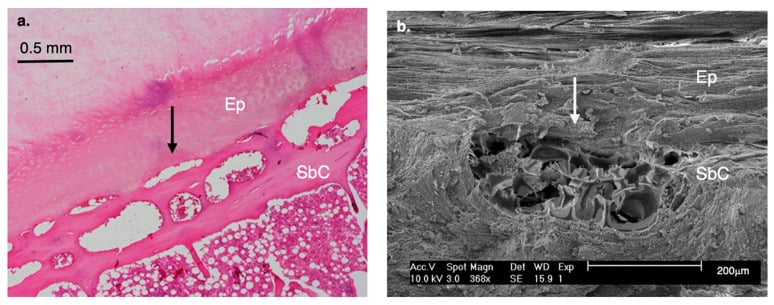
Factors affecting nutrition. Endplate injury or sclerosis disrupts an already tenuous supply and accelerates degeneration. The supply also depends on:
- Endplate permeability: sclerosis or calcification decreases diffusion, and cells die
- Disc height: thicker discs mean a longer diffusion pathway and poorer nutrition
- Loading: cyclic loading enhances diffusion by a pumping action; static loading impairs it
- Smoking: decreases endplate blood supply and accelerates degeneration
Disc Degeneration
Degeneration Cascade
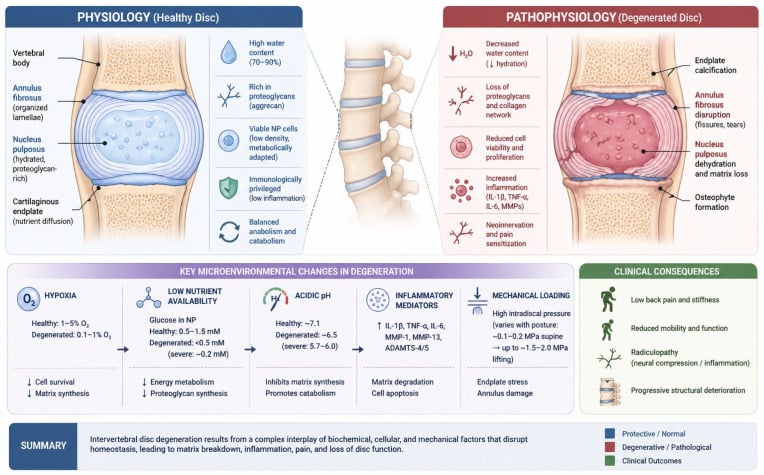
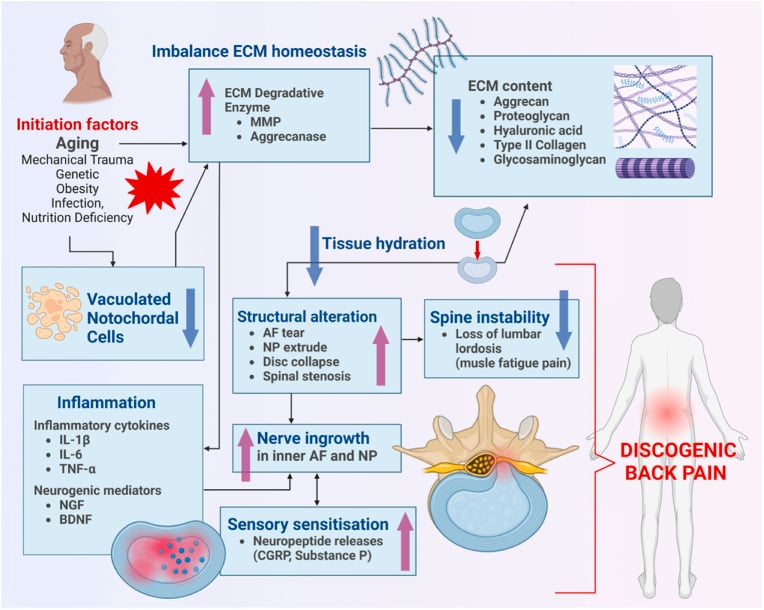
Disc degeneration follows a predictable biochemical → structural → biomechanical pathway. It couples matrix loss and fibrosis with endplate calcification, inflammatory signalling, cell loss, vascular and nerve ingrowth and falling nutrient availability.
Early Degeneration (Pfirrmann I-II)
Proteoglycan loss. Matrix metalloproteinases (MMPs) and ADAMTS degrade aggrecan. Losing it lowers osmotic pressure and the disc's capacity to bind water.
The cells. Nutrient deprivation increases apoptosis and cell density falls. The cells shift from anabolic to catabolic metabolism, and upregulated inflammatory cytokines (IL-1β, TNF-α) perpetuate the cycle.
The markers. Proteoglycan content falls, seen on MRI as decreased T2 signal. Collagen cross-linking increases, and pH falls as lactate accumulates from anaerobic metabolism.
In theory, early changes are reversible with improved nutrition.
PANDADisc Degeneration Cascade
Hook:Disc degeneration follows the PANDA pathway from biochemical to structural failure.
Pfirrmann Classification (MRI Grading)
Pfirrmann grades the disc on T2-weighted MRI by the structure of the nucleus, its signal and the disc height.
- Structure
- Homogeneous bright white
- Signal (T2)
- Hyperintense
- Disc Height
- Normal
- Interpretation
- Normal disc
- Structure
- Inhomogeneous with horizontal band
- Signal (T2)
- Hyperintense
- Disc Height
- Normal
- Interpretation
- Early degeneration
- Structure
- Inhomogeneous grey; nucleus-annulus distinction lost
- Signal (T2)
- Intermediate
- Disc Height
- Normal/decreased
- Interpretation
- Moderate degeneration
- Structure
- Inhomogeneous dark grey
- Signal (T2)
- Hypointense
- Disc Height
- Decreased
- Interpretation
- Advanced degeneration
- Structure
- Inhomogeneous black
- Signal (T2)
- Hypointense
- Disc Height
- Collapsed
- Interpretation
- Severe degeneration
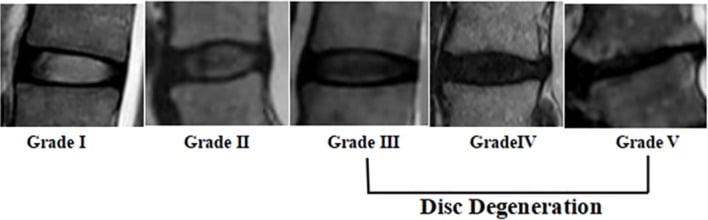
Modic Endplate Changes
Modic changes are endplate and adjacent bone marrow pathology associated with disc degeneration. They are read from the T1 and T2 signal:
- Type I (T1 low, T2 high): oedema and inflammation, acute or active degeneration
- Type II (T1 high, T2 high): fatty replacement, chronic degeneration
- Type III (T1 low, T2 low): sclerosis, end-stage degeneration
Modic Type I change is associated with discogenic back pain and may represent an inflammatory phenotype amenable to treatment.
Clinical Relevance and Applications
Differential Diagnosis of a Low-Signal ("Dark") Disc or Suspected Discogenic Pain
A degenerate disc on MRI is common and frequently asymptomatic. The exam-relevant skill is distinguishing benign age-related change from the pathology that mimics it.
- Key MRI / Clinical Feature
- Low T2 signal, mild height loss, no Modic or only Type II
- Distinguishing Point
- Very common, often asymptomatic; prevalence rises with age
- Action
- Reassure; treat symptoms, not the image
- Key MRI / Clinical Feature
- Modic Type I, high-intensity zone in posterior annulus, single-level concordant pain
- Distinguishing Point
- Inflammatory/active phenotype; pain reproduced by that level
- Action
- Targeted rehab; selected injection/fusion in refractory cases
- Key MRI / Clinical Feature
- T2-high disc and endplate, endplate destruction, paravertebral/epidural collection, contrast enhancement
- Distinguishing Point
- Pain at rest and night, raised CRP/ESR, fever; crosses the disc space
- Action
- Urgent - blood cultures, biopsy, antibiotics
- Key MRI / Clinical Feature
- Marrow replacement on T1 but disc space PRESERVED
- Distinguishing Point
- Tumour spares the avascular disc; infection destroys it
- Action
- Staging, biopsy, oncology referral
- Key MRI / Clinical Feature
- T1 low, T2 high endplate, NO disc destruction or collection
- Distinguishing Point
- Mimics early discitis; normal inflammatory markers
- Action
- Conservative; correlate with markers before treating as infection
Pyogenic infection crosses and destroys the disc space (the organism reaches the avascular disc via the endplate); metastatic and myeloma deposits spare the disc and replace vertebral marrow. "Marrow disease that respects the disc is tumour until proven otherwise; marrow disease that eats the disc is infection until proven otherwise."
Understanding Disc Biology Informs Clinical Practice
What surgery does to the disc. Discectomy removes the herniating nucleus but accelerates degeneration. Fusion eliminates the motion segment but increases stress at the adjacent level, and disc replacement aims to preserve motion, though its long-term outcomes are variable. Biologic therapies (stem cells, growth factors) target regeneration.
Prevention and modification. The measures within the patient's control are:
- Smoking cessation: nicotine impairs an already limited nutrition
- Weight management: reduces compressive load
- Avoiding repetitive flexion-rotation, the most damaging motion
- Core strengthening, for dynamic stabilisation
Guidelines, Registries & Global Practice
Global Epidemiology
- Low back pain is the leading cause of years lived with disability worldwide (Global Burden of Disease), and disc degeneration is its commonest structural correlate.
- Degenerative MRI findings are near-universal with age: disc signal loss and bulging are found in the majority of asymptomatic adults over 50-60 years.
- Heritability of disc degeneration is substantial (29-54% in twin data), with smoking, obesity, heavy repetitive loading, and vibration as modifiable contributors.
Side-by-Side Guidance on Degenerative Disc Disease / Low Back Pain
- Imaging stance
- Do NOT routinely image non-specific low back pain; image only if result changes management or red flags present
- Management emphasis
- Self-management, exercise, manual therapy; surgery reserved for radiculopathy/stenosis failing conservative care
- Imaging stance
- Avoid early imaging without red flags or progressive deficit
- Management emphasis
- First-line non-pharmacological care; injections and fusion in selected refractory discogenic cases
- Imaging stance
- Standardised MRI grading (Pfirrmann) and endplate (Modic) reporting for research and surgical planning
- Management emphasis
- Classification-led, evidence-graded surgical decision frameworks
- Imaging stance
- Reserve advanced imaging for surgical candidates
- Management emphasis
- Motion-preserving options (disc arthroplasty) vs fusion individualised to pathology
Registry and Resource-Setting Notes
- Spine device registries (e.g. national arthroplasty/spine registries, the international Spine Tango registry) track disc-replacement and fusion survival and adjacent-segment reoperation; medium-term data show broadly comparable outcomes for well-selected fusion versus disc arthroplasty.
- High-resource settings debate motion-preservation, biologics, and intradiscal therapies; limited-resource settings prioritise affordable conservative care and prioritising surgery for neurological compromise rather than axial discogenic pain.
- Across all settings, the consistent message is restraint with imaging and surgery for non-specific axial pain, reflecting the weak image-symptom correlation.
Controversies and Areas of Uncertainty
The biology of the disc is mature, but its clinical translation remains contested. These are the high-yield viva controversies.
Does degeneration cause pain? Disc degeneration on MRI is highly prevalent in asymptomatic people and rises with age, and the correlation between Pfirrmann grade and back pain is weak. Modic Type I and a posterior annular high-intensity zone are the features most linked to pain, but neither is specific. Treating images rather than patients is a recognised pitfall.
Degeneration or ageing? Whether disc degeneration is a distinct disease or simply accelerated normal ageing is unresolved. Boos et al showed an early, nutrition-driven histological continuum from the second decade, blurring the line between "normal ageing" and "pathology".
Biological regeneration. MSC and growth-factor injection (e.g. allogeneic MSC RCT, Noriega 2017) show proof-of-concept disc-quality and pain improvement. The benefit is confined to a responder subgroup, and no large definitive trial yet supports routine use. Re-injuring an avascular, hostile, low-pH niche to deliver cells remains a fundamental hurdle.
Fusion or motion preservation? Total disc replacement aims to avoid the adjacent-segment degeneration seen after fusion, but registry and trial evidence show comparable medium-term outcomes, and it has its own failure modes. Whether adjacent-segment change is caused by fusion or reflects the patient's underlying degenerative biology is debated.
MCQ Practice Points
Q: What is the predominant collagen type in the nucleus pulposus versus the annulus fibrosus?
A: Nucleus pulposus: Type II collagen (random orientation). Annulus fibrosus: Type I collagen (organized in ±30° alternating lamellae). This reflects their different biomechanical roles: nucleus resists compression, annulus resists tension and torsion.
Q: How does the adult intervertebral disc receive nutrition, and what is the significance?
A: Diffusion through cartilaginous endplates - the disc is avascular after age 20. This is the longest diffusion pathway in the body (up to 8mm). The avascular nature explains why discs cannot heal once injured and why endplate injury accelerates degeneration by disrupting the already tenuous nutrition supply.
Q: Describe the Pfirrmann Grade I and Grade V disc on MRI.
A: Grade I: Bright white (hyperintense) homogeneous nucleus on T2, normal disc height - represents a normal disc. Grade V: Black (hypointense) heterogeneous signal on T2, collapsed disc height - represents severe degeneration. The classification progresses from I to V based on decreasing T2 signal (water content) and disc height.
Q: What is a Modic Type I change and its clinical significance?
A: Modic Type I: T1 low signal, T2 high signal - represents edema and inflammation in the vertebral endplate and adjacent bone marrow. This indicates active/acute degeneration and correlates with discogenic back pain. It may represent an inflammatory phenotype amenable to targeted treatment.
Q: Why is the annular fiber orientation at ±30° biomechanically important?
A: The alternating ±30° crossed-fiber arrangement allows the annulus to resist loads in multiple directions: tensile forces in any direction, torsional (rotational) forces, and radial expansion of the nucleus under compression. This creates hoop stress that confines the nucleus and distributes load evenly.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“The examiner shows you a sagittal MRI of the lumbar spine and asks: 'Describe the structure and biomechanical function of the intervertebral disc.'”
“The examiner shows you sequential MRI scans showing progressive disc degeneration and asks: 'Describe the pathophysiology of disc degeneration and the Pfirrmann classification.'”
“A 45-year-old presents with chronic axial low back pain. The MRI shows a single dark (Pfirrmann IV) disc at L5/S1 with Modic Type I endplate change. The examiner asks: 'How confident are you that this disc is the source of pain, and what does disc biology tell us about treatment options?'”
Key Structures
- Nucleus pulposus: 80% water, Type II collagen, aggrecan, resists compression
- Annulus fibrosus: 15-20 lamellae, Type I collagen at ±30°, resists tension/torsion
- Cartilaginous endplates: 0.6-1.0mm thick, nutrition pathway
- Avascular after age 20 - largest avascular structure in body
Biomechanical Functions
- Nucleus: Hydrostatic compression resistance
- Annulus: Tensile and torsional resistance via hoop stress
- Crossed fibers (±30°): Resist multi-directional loads
- Viscoelastic: creep, stress relaxation, and diurnal stature loss of roughly 1-2 cm summed across ALL spinal discs - not per disc
Nutrition Pathway
- Diffusion only route (no blood supply)
- Pathway: Vertebral capillaries → Endplate → Disc matrix (up to 8mm)
- Endplate injury/sclerosis → disrupts nutrition → accelerates degeneration
- Smoking decreases endplate blood supply
Degeneration Cascade
- Biochemical: Proteoglycan loss → water loss
- Structural: Nucleus fibrosis, height loss, annular tears
- Biomechanical: Instability → facet overload → OA
- Structural change does not reverse spontaneously (biological repair remains experimental)
Pfirrmann Classification
- Grade I: Bright white homogeneous (normal)
- Grade II: Inhomogeneous with band (early degeneration)
- Grade III: Gray inhomogeneous (moderate)
- Grade IV: Dark gray, decreased height (advanced)
- Grade V: Black, collapsed (severe)
Modic Changes
- Type I: T1 low, T2 high = edema/inflammation (active, painful)
- Type II: T1 high, T2 high = fatty replacement (chronic stable)
- Type III: T1 low, T2 low = sclerosis (end-stage)
Evidence Base
Degeneration of the Intervertebral Disc (Urban & Roberts review)
- Adult disc is the largest avascular structure - nutrition is by diffusion through the endplate only
- Cells in the disc centre lie up to 8mm from the nearest blood supply, with the lowest oxygen and glucose concentrations of any tissue
- Disc shows degenerative and ageing change earlier than any other connective tissue in the body
- Falling nutrient supply and rising lactate (low pH) drive cell death and a shift to a catabolic matrix-degrading phenotype
- Disc degeneration is associated with low back pain but the relationship is inconsistent
Pfirrmann MRI Classification of Lumbar Disc Degeneration
- Five-grade T2-weighted MRI system (I-V) based on nucleus structure, signal, and disc height; tested on 300 discs in 60 patients
- Grade I: bright homogeneous nucleus, normal height (normal disc)
- Grade V: black heterogeneous signal with collapsed disc space (severe degeneration)
- Intra-observer agreement kappa 0.84-0.90; inter-observer agreement kappa 0.69-0.81 (substantial to excellent)
- Complete agreement in 83.8% of discs; a two-grade discrepancy in only 1.3%
Modic Vertebral Endplate Marrow Changes
- Reviewed 474 consecutive lumbar MRI studies and defined endplate marrow change types
- Type I (T1 low, T2 high) in 4%: fissured endplates with vascularised fibrous tissue (active)
- Type II (T1 high, T2 high) in 16%: yellow marrow (fatty) replacement (chronic stable)
- Type I converted to Type II over 14 months to 3 years in 5 of 6 followed patients; Type II remained stable
- All cases had degenerative disc disease at the involved level
Histologic Classification of Age-Related Disc Change (2002 Volvo Award)
- Histologic study of 180 sagittal lumbar motion-segment slices from 44 individuals (fetal to 88 years)
- Tissue breakdown begins in the nucleus pulposus in the second decade of life
- Diminished blood supply to the endplate in the first half of the second decade appears to initiate disc breakdown
- Ageing and degeneration form a histological continuum rather than discrete processes
- Macroscopic grading scattered widely against histology, favouring a histology-based reference standard
Genetic vs Environmental Influences on Disc Degeneration (Twin Study)
- Classic twin study of 152 monozygotic and 148 dizygotic male twin pairs (Finnish Twin Cohort)
- Heritability of disc degeneration phenotypes ranged 29-54% depending on phenotype and level
- Signal loss, height narrowing, and bulging shared a common genetic pathway
- Genetic and environmental influences differed substantially between upper and lower lumbar levels
- Genetics and environment were of broadly similar overall importance
Allogeneic MSC Intradiscal Injection for Degenerative Disc Disease (RCT)
- Phase II randomised controlled trial: 24 patients, intradiscal allogeneic bone-marrow MSC versus sham paravertebral anaesthetic
- Feasibility and safety confirmed at 1 year
- Pain and disability improved rapidly in the MSC group, but benefit was restricted to a ~40% responder subgroup
- Pfirrmann grade improved in MSC-treated discs and worsened in controls
- Allogeneic cells offer a logistically simpler off-the-shelf alternative to autologous MSC