Rare Benign Fat-Containing Bone Tumor | Classic Central Calcification | Calcaneus Most Common Site
- Calcaneus is the most common single site - 32% of pooled cases in the Campbell series
- Central calcification on X-ray is pathognomonic - radiolucent lesion with dense central nidus
- MRI shows fat signal on all sequences - diagnostic feature distinguishing from other lucent lesions
- Benign - no meaningful malignant potential in practice, and an excellent prognosis with simple curettage
- Milgram staging based on degree of fat necrosis and calcification, not biological behavior
- “Examiners love the central calcification pattern - it's pathognomonic for intraosseous lipoma
- “Fat signal on MRI (high T1, low T2 with fat suppression) clinches the diagnosis
- “Distinguish from bone infarct - infarcts have serpentine peripheral calcification, lipomas have central calcification
- “Simple curettage is curative - no wide margins needed as this is completely benign
Overview and Epidemiology
Intraosseous lipoma is a rare benign tumour of mature adipose tissue within the medullary cavity of bone, accounting for under 0.1% of all bone tumours. It is worth knowing well because the imaging is characteristic: central calcification on the radiograph and fat signal on MRI allow a confident diagnosis without biopsy in most cases.
Who. A middle-aged adult, typically 40-60 years, with no sex predilection. Under 5% of cases are children. The lesion is usually solitary, and multiple lipomas are exceptionally rare.
Where. About a third arise in the calcaneus, the commonest single site, and the proximal femur comes next.
- Calcaneus, 32% of the pooled Campbell series. Usually asymptomatic, found incidentally or with heel pain.
- Proximal femur, 20%, in the intertrochanteric region, where a large lesion carries a risk of pathological fracture.
- Proximal tibia, 5%, metaphyseal and usually asymptomatic.
- Other sites, 15%: fibula, ribs, skull and ilium, all rare; fibula, ribs and skull under 5% each.
- Never in the spine, unlike soft-tissue lipomas.
Why the calcaneus. The predilection is unexplained. It may relate to the high proportion of fatty marrow in the calcaneus, to repetitive microtrauma from weight-bearing, or to a vascular anatomy that predisposes to focal ischaemia. Whatever the mechanism, the calcaneus is the first site to consider when you see an intraosseous lipoma.
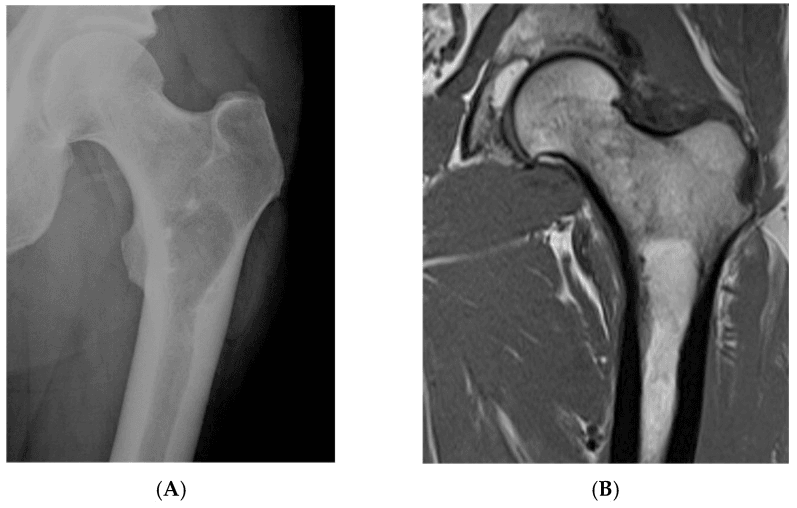
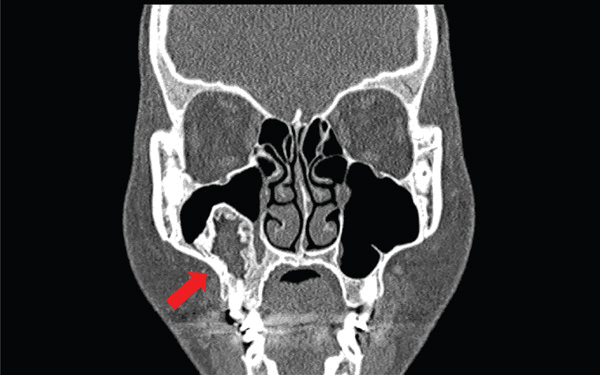
Pathophysiology and Mechanisms
Origin. The origin is unknown. The most accepted theory is metaplasia: bone marrow mesenchymal cells transform into adipocytes in response to trauma or microtrauma, ischaemia or infarction, or an unknown stimulus. The alternative, a congenital nidus of ectopic fat cells that slowly expands, is less favoured because most cases present in adulthood rather than childhood.
Why the calcification is central. Fat at the centre of the lesion is furthest from its blood supply, and it necroses there, whether from ischaemia or because the lesion outgrows its supply. The necrotic fat undergoes dystrophic calcification, which spreads from the centre outward as the lesion involutes. A bone infarct is the opposite: its calcification is peripheral and serpentine, delineating the margin of the dead segment like a geographic map.
Pathology
Gross appearance. Yellow, greasy, soft tissue indistinguishable from normal adipose tissue, sometimes with areas of white chalky calcification where fat has necrosed. Lesions are typically 2-5 cm across, rarely larger.
Microscopy. Histologically the lesion is indistinguishable from a soft-tissue lipoma: both are mature adipose tissue. What identifies it is the intramedullary location and the central calcification pattern.
- Mature adipocytes: large cells with a single lipid vacuole displacing the nucleus to the periphery, with minimal atypia
- Fat necrosis (stages 2-3): ghost cells and loss of cell membranes
- Dystrophic calcification: calcium deposited in the necrotic fat
- Reactive bone: woven bone at the periphery in some cases
The histological differential. Normal marrow fat is excluded because the lipoma is an expansile mass, not simply fatty marrow. Liposarcoma contains lipoblasts, cells with scalloped hyperchromatic nuclei, which are not present in a benign lipoma. A bone infarct shows geographic necrosis of bone and marrow with calcification at the periphery.
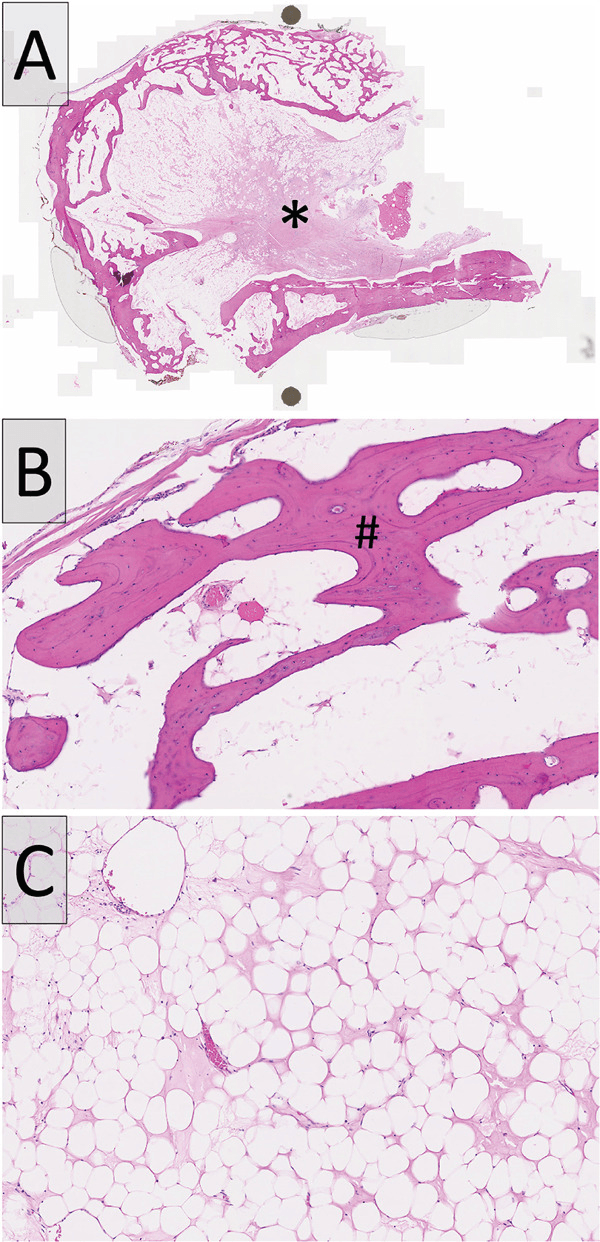
Classification and Staging
Milgram's histological classification (1988) is the gold standard. It describes the natural involution of the lesion from viable fat through necrosis to calcification, and does not indicate biological behaviour or malignant potential: all three stages are equally benign.
- Histology
- Mature adipose tissue: viable fat cells with intact cell membranes and normal nuclei
- Radiographic Appearance
- Purely radiolucent, no calcification
- Clinical Significance
- Early lesion, purely fatty
- Histology
- Viable fat at the periphery, central fat necrosis with dystrophic calcification
- Radiographic Appearance
- Radiolucent with central calcification - the pathognomonic appearance
- Clinical Significance
- The classic lesion
- Histology
- Extensive calcification, minimal residual fat, cyst formation, reactive bone
- Radiographic Appearance
- Heavily calcified, may mimic bone infarct or enchondroma
- Clinical Significance
- Advanced involution, difficult to diagnose
How common each stage is. No reliable proportion exists. Milgram described the three stages but did not publish their relative frequencies, and the two surgical series cited on this page disagree sharply.
- Stage 1: 10 of 29 (34%) in Radl, 9 of 14 (64%) in Aycan
- Stage 2: 14 of 29 (48%) and 4 of 14 (29%), not a clear majority
- Stage 3: the least frequent in both, 3 of 29 (10%) and 1 of 14 (7%)
Both are operated cohorts, so they over-represent symptomatic lesions and cannot give a population distribution. Stage 2 is called the classic appearance, and it is the one an examiner will show, but its prominence reflects how recognisable it is rather than a measured predominance.
Why stages 1 and 3 are harder. A stage 1 lesion has no calcification to see. A stage 3 lesion is the hardest of all, because heavy calcification loses the fat signal that otherwise makes the diagnosis straightforward.
Clinical Presentation
Symptoms. Between 50 and 70% are asymptomatic, found on imaging done for other reasons. The other 30-50% have a dull, aching, activity-related pain, lasting months to years; its mechanism is unclear, and may be microfracture or pressure. There are never systemic symptoms such as fever, weight loss or malaise. Pathological fracture is rare (under 5%) but possible when a large lesion has thinned the cortex.
Natural history. The lesion stays the same size, without the progressive enlargement of a malignant lesion. It involutes slowly, and may calcify and become more apparent over years.
Examination. There is usually little to find. The lesion is intramedullary, so there is no visible swelling or external mass, and no erythema, warmth or overlying soft-tissue abnormality. There may be mild focal tenderness over the lesion. Neurovascular examination is normal and the adjacent joints move fully. A painful calcaneal lesion may produce an antalgic gait. Weight-bearing is tolerated unless there is a fracture or severe pain, and there is no deformity unless a pathological fracture has occurred.
Imaging and Diagnosis
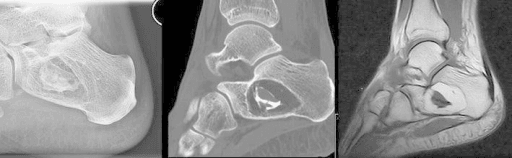
The radiograph. A well-defined, trabeculated radiolucency, geographic with a narrow zone of transition (Lodwick type IA or IB). It sits in the metaphysis or diaphysis of a long bone, or in the body of the calcaneus, where it occupies the neutral triangle: the naturally trabecula-poor area that is also the commonest site of a simple bone cyst.
The central calcification. A dense, round or oval nidus sitting centrally within the lucency, the dystrophic calcification of necrotic fat described above, and the feature that separates the lesion from a bone infarct. It is not universal: in Campbell's pooled series it was present in 62% of os calcis lesions and 30% of lesions elsewhere.
The cortex. Intact or mildly thinned but never destroyed, often with a sclerotic rim at the margin. An intraosseous lipoma has no reason to provoke the periosteum, so any periosteal reaction should be attributed to a pathological fracture rather than accepted as part of the lesion.
No soft-tissue component. The lesion is purely intramedullary. A fatty lesion with a soft-tissue mass is not this diagnosis, and the finding should redirect you toward a liposarcoma or another aggressive process rather than being explained away.
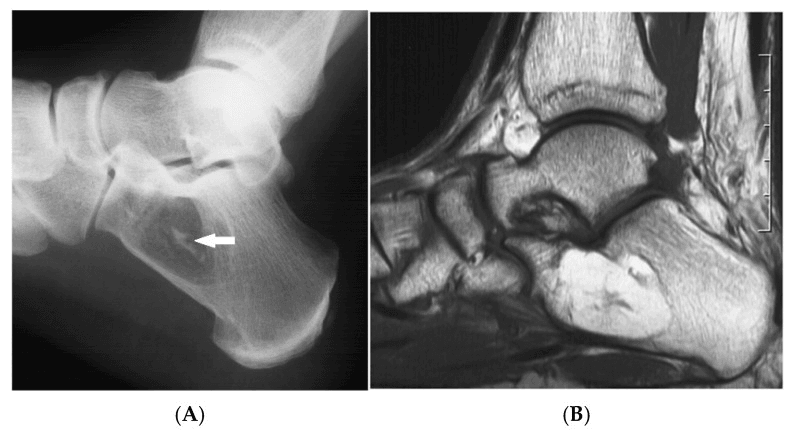
MRI, the gold standard. The lesion matches subcutaneous fat on every sequence.
- T1: high signal
- T2: intermediate to high signal
- STIR or fat saturation: the signal suppresses completely
- Gadolinium: no enhancement, because fat does not enhance
- Central calcification: a low-signal nidus on all sequences
The margins are well defined, with a smooth interface against normal marrow. There is no soft-tissue extension beyond the cortex, and the surrounding marrow shows no oedema unless there has been a fracture.
The key to MRI diagnosis is demonstrating that the high T1 signal SUPPRESSES with fat saturation sequences (STIR or fat-sat T2). This proves the lesion contains fat, distinguishing it from other T1 hyperintense lesions like haemorrhage or proteinaceous cyst fluid.
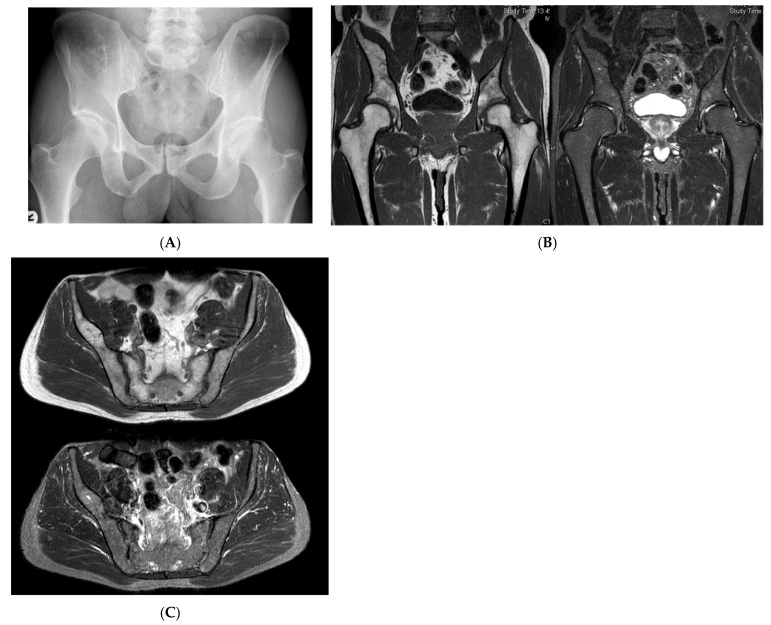
CT. Rarely needed. It shows fat density (-40 to -120 HU), delineates the central calcification and assesses cortical integrity, which makes it useful for surgical planning when curettage is planned.
Differential diagnosis. The lesions to distinguish from an intraosseous lipoma:
- Key Distinguishing Feature
- Peripheral serpentine calcification
- Imaging Clue
- Geographic map pattern at periphery, NOT central
- Key Distinguishing Feature
- No central calcification, younger age
- Imaging Clue
- Fallen fragment sign, fluid signal on MRI, no fat signal
- Key Distinguishing Feature
- Expansile, fluid-fluid levels
- Imaging Clue
- Blow-out appearance, haemorrhagic fluid on MRI
- Key Distinguishing Feature
- Chondroid matrix calcification
- Imaging Clue
- Rings and arcs calcification, no fat signal
- Key Distinguishing Feature
- Ground-glass matrix, no fat signal
- Imaging Clue
- Expansile, no central calcification pattern
- Key Distinguishing Feature
- Younger age, painful
- Imaging Clue
- Rare in the calcaneus
When to biopsy. Rarely. Classic imaging allows a confident diagnosis without it: a radiolucent lesion with central calcification, fat signal on MRI that suppresses with fat saturation, a typical site such as the calcaneus or proximal femur, and a middle-aged patient.
These suggest an alternative diagnosis:
- Rapid growth or increasing size (consider malignancy)
- A soft-tissue mass extending beyond bone
- Systemic symptoms such as fever or weight loss (consider infection or malignancy)
- A pathological fracture through an aggressive-appearing lesion (reassess the diagnosis)
Consider biopsy when there is no fat signal on MRI, when aggressive features such as cortical destruction or a soft-tissue mass are present, with rapid growth or change in appearance, or when symptoms are out of proportion to the imaging. If a lesion shows rapid growth, cortical destruction or a soft-tissue component, abandon the assumption of a benign lipoma and refer for bone-tumour assessment and biopsy.
Management and Treatment
The principle. Most intraosseous lipomas can be observed. Treatment is guided by symptoms and fracture risk, not by Milgram stage: an asymptomatic lesion is observed, and a symptomatic or structurally threatened one is curetted and grafted. Site shapes the threshold. A calcaneal or proximal tibial lesion is observed unless symptomatic, a proximal femoral lesion with cortical thinning is considered for prophylactic curettage, and lesions elsewhere are managed case by case.
Observation. Observation is appropriate when:
- The lesion is asymptomatic and discovered incidentally
- The imaging is classic, leaving no diagnostic uncertainty
- It is small, with no risk of pathological fracture
- The patient prefers to avoid surgery
Repeat the radiograph at 6 months to confirm stability and again at 1 year; if it is still stable, discharge. Explain that the lesion is benign and ask the patient to return if new pain or symptoms develop. Most lesions never become symptomatic, and mild pain from a small lesion with an intact cortex and no fracture risk is managed conservatively with analgesia and activity modification.
Surgery. Curettage is indicated for:
- Persistent pain unresponsive to conservative measures
- Pathological fracture or imminent fracture risk
- A large lesion with cortical thinning (prophylactic treatment)
- Diagnostic uncertainty (biopsy and curettage)
Technique. Curettage proceeds in four steps.
- Approach: direct, through a small cortical window made with a curette or drill, preserving the structural integrity of the bone and avoiding neurovascular structures
- Curettage: remove all fatty tissue and calcification, curette the walls to ensure complete excision, and send the specimen for histology to confirm the diagnosis
- Grafting: fill a large defect with iliac crest autograft for structural defects, cancellous allograft chips for small defects, or a calcium phosphate or sulfate substitute
- Closure: irrigate and close the soft tissues in layers; a drain is usually not needed for small defects
Completeness. Recurrence occurs when curettage is incomplete, so curette every wall thoroughly. Wide margins are not needed for a benign lesion, and nor are adjuvants such as phenol or burr (see Controversies).
- Surgical Approach
- Lateral approach below peroneal tendons
- Graft Needed?
- Usually yes - to restore structural integrity
- Special Considerations
- Protect sural nerve; avoid plantar medial neurovascular bundle
- Surgical Approach
- Lateral approach to intertrochanteric region
- Graft Needed?
- Yes - autograft preferred for structural support
- Special Considerations
- Risk of subtrochanteric fracture if large defect; may need prophylactic fixation
- Surgical Approach
- Anteromedial or anterolateral approach
- Graft Needed?
- Depends on size - small defects can heal without graft
- Special Considerations
- Avoid popliteal vessels posteriorly
Prophylactic fixation. Consider internal fixation when:
- The lesion is large, greater than 50% of the bone diameter
- Cortical thinning is significant after curettage
- The bone is weight-bearing (proximal femur, tibia)
- The location carries a high fracture risk (femoral neck, subtrochanteric)
The options, depending on location, are an intramedullary nail, a plate and screws, or percutaneous screws.
Complications
- Incidence
- Under 5%
- Prevention
- Complete curettage of all walls
- Management
- Re-curettage if symptomatic recurrence
- Incidence
- Rare (under 3%)
- Prevention
- Prophylactic fixation if large lesion with cortical thinning
- Management
- ORIF with bone graft
- Incidence
- 2-3%
- Prevention
- Standard sterile technique, prophylactic antibiotics
- Management
- Antibiotics, irrigation and debridement if deep infection
- Incidence
- Under 2%
- Prevention
- Careful approach avoiding neurovascular structures; the sural nerve is at risk in the calcaneus
- Management
- Observation for neuropraxia, exploration if transection suspected
Liposclerosing Myxofibrous Tumour (LSMFT): the Key Intertrochanteric Mimic
Liposclerosing myxofibrous tumour is the key differential at the intertrochanteric femur. That matters because the proximal femur is the second most common site of intraosseous lipoma, and the two lesions behave differently.
A different, mixed lesion. LSMFT is a benign fibro-osseous lesion with a mixed histology: variable proportions of lipoma, fibrous tissue, myxoid change, fat necrosis, cyst formation, ischaemic ossification and ground-glass, fibrous-dysplasia-like bone, rather than the pure mature fat of an intraosseous lipoma. It is characteristically located in the intertrochanteric region of the proximal femur, in the great majority of cases.
The MRI discriminator. Because of its mixed matrix, LSMFT usually does not follow fat signal uniformly. It shows heterogeneous T1 and T2 signal, often with a fibrous-dysplasia-like or myxoid appearance and sometimes a sclerotic rim, so the reassuring high T1 that fully suppresses with fat saturation is typically absent.
The risk of change. A true intraosseous lipoma has essentially zero malignant potential. LSMFT has a described, though contested and probably referral-biased, risk of malignant transformation to malignant fibrous histiocytoma or osteosarcoma. A symptomatic, enlarging or aggressive-appearing intertrochanteric LSMFT is therefore treated with a lower threshold for biopsy and closer surveillance than a classic intraosseous lipoma.
Why it is examined. It is the classic intertrochanteric fibro-osseous lesion that overlaps radiologically with intraosseous lipoma and fibrous dysplasia. The point being tested is that a heterogeneous, not purely fatty, intertrochanteric lesion is not automatically a benign lipoma to be ignored.
Parosteal (Juxtacortical) Lipoma: the Surface Bone Lipoma
A fatty mass on the bone surface. Parosteal (juxtacortical) lipoma is a benign lipoma arising on the outer surface of the cortex or periosteum, most often around the radius, femur, humerus and pelvis. Like the intraosseous type it has fat signal on CT and MRI, but it is juxtacortical, not intramedullary. It frequently provokes a reactive bony excrescence, cortical hyperostosis or an osteochondroma-like spur at its base, a useful radiographic clue.
The clinical catch: nerve compression. Its surface position means it can compress an adjacent peripheral nerve, a functional consequence the intramedullary lipoma never causes. The classic and most examined example is a parosteal lipoma of the proximal radius compressing the posterior interosseous nerve, producing a PIN palsy or radial-tunnel-type presentation; similar compressive syndromes occur elsewhere.
Diagnosis and treatment. MRI shows a fat-signal mass abutting the cortex with the reactive bony change, confirming the diagnosis without biopsy in typical cases. Because the lesion is benign, marginal excision is curative. It is indicated when the lipoma is symptomatic or compressing a nerve, with neurolysis of the involved nerve, and asymptomatic incidental lesions can be observed.
Postoperative Care
Post-Curettage Rehabilitation Protocol
Wound care and dressing changes. Weight-bearing status depends on site: calcaneus - partial weight-bearing in boot; proximal femur - protected weight-bearing with crutches.
Suture removal at 2 weeks. Progressive weight-bearing as tolerated. X-ray at 6 weeks to assess graft incorporation.
Full weight-bearing for most patients. Transition to normal footwear (calcaneus). Resume light activities.
Return to full activity including sports. Final X-ray to confirm healing and no recurrence. Discharge if stable.
Radiographs are taken at 6 weeks and 3 months after curettage. Annual follow-up is not required once the lesion is confirmed as a benign lipoma.
Outcomes and Prognosis
After curettage. Curettage with or without bone graft is curative in over 95% of cases, and 95% of patients have complete pain relief. Grafted defects heal within 6-12 weeks, and patients return to full activity by 3-6 months.
Long-term prognosis. Excellent. The lesion does not grow, does not metastasise, does not affect other organs and does not cause death. It may calcify and involute over time, from stage 2 to stage 3. For practical purposes it has no meaningful malignant potential, and patients can be reassured on that point; the presumed cases of malignant transformation are discussed under Controversies.
Guidelines, Registries & Global Practice
Global Epidemiology
Intraosseous lipoma is reported worldwide with a consistent profile: peak presentation in middle age (mean ~43-48 years across pooled series), near-equal sex distribution, and a lower-limb predominance (~71% of cases), with the os calcis the single most common site. It is genuinely uncommon (classically quoted at under 0.1% of primary bone tumours) but is widely regarded as underdiagnosed because involuted (Milgram III) lesions are mistaken for cysts or bone infarcts. There is no dedicated tumour registry for this benign entity; epidemiology derives from radiology and orthopaedic-oncology case series rather than national arthroplasty/implant registries.
Guideline Framework (Side-by-Side)
- Relevant guidance
- Listed as a benign adipocytic bone tumour; diagnosis rests on identifying mature fat
- Practical implication
- Histology not required when imaging is unequivocal
- Relevant guidance
- Any indeterminate or aggressive-appearing bone lesion should be referred to a bone-tumour unit before biopsy
- Practical implication
- Refer only atypical cases; classic lipomas need no referral
- Relevant guidance
- "Diagnostic uncertainty or aggressive features" trigger sarcoma-unit referral
- Practical implication
- A confidently diagnosed fatty lesion is managed locally
- Relevant guidance
- Latent benign bone lesions (Enneking stage 1) may be observed
- Practical implication
- Curettage reserved for symptoms or fracture risk
No major society mandates routine biopsy or specialist referral for a radiologically classic intraosseous lipoma.
- MRI readily available to confirm fat signal and assign Milgram stage
- CT reserved for surgical planning (cortical integrity, fracture risk)
- Histological confirmation easily obtained when a lesion is curetted
- Plain radiograph (central calcification in a lucent calcaneal lesion) often sufficient for a confident working diagnosis
- Where MRI is unavailable, typical radiographic features plus stability on follow-up support observation
- Curettage with locally available graft or substitute is curative when surgery is needed
Across the major orthopaedic exit examinations and board certifications, be ready to describe the characteristic imaging features (central calcification on radiograph, fat signal on MRI that suppresses with fat saturation), the Milgram classification (Stages 1-3 reflecting involution, not malignancy), and to justify observation for asymptomatic lesions versus curettage and grafting for symptomatic or fracture-prone disease.
Controversies and Areas of Uncertainty
True neoplasm or involutional process? Campbell and colleagues questioned whether intraosseous lipoma is a genuine benign tumour of fat or the end-result of involution of pre-existing lesions and biomechanical stress, pointing to the constant os calcis location at the critical angle. The histogenesis remains unsettled.
Does malignant transformation exist? Milgram reported four cases of presumed malignant transformation (liposarcoma or malignant fibrous histiocytoma) within bone lipomas. These are exceptionally rare and contested. For practical purposes the lesion is treated as having no meaningful malignant potential, but rapid bone destruction in a previously lucent lesion warrants reassessment.
Observe or operate? There are no randomised data comparing observation with curettage. Practice is guided by symptoms and fracture risk, as set out under Management.
Adjuvants. Phenolisation and extended (burr or argon) curettage are sometimes used by analogy with other bone lesions. The Radl cohort found no added benefit from phenol, consistent with the benign biology, and aggressive adjuvants are not justified.
MCQ Practice Points
Q: What is the most common site for intraosseous lipoma? A: Calcaneus is the most common single site - 32% of pooled cases in the Campbell series, which pooled 145 lesions. The older quoted figure of 60% is not supported by the largest dataset; quote a third.
Q: What is the pathognomonic radiographic finding of intraosseous lipoma? A: Central calcification within a radiolucent lesion. This dense central nidus of calcification distinguishes intraosseous lipoma from simple bone cyst and other lucent lesions.
Q: What MRI finding confirms the diagnosis of intraosseous lipoma? A: High T1 signal that suppresses with fat saturation sequences. This proves fat content and allows confident diagnosis without biopsy.
Q: What does the Milgram classification of intraosseous lipoma indicate? A: The Milgram classification (Stages 1-3) reflects the histological evolution from viable fat to necrosis and calcification. It does NOT indicate biological behavior or prognosis - all stages are equally benign.
Q: What are the indications for surgical treatment of intraosseous lipoma? A: Surgery indicated for: persistent pain unresponsive to conservative treatment, pathological fracture or imminent fracture risk (large lesion with cortical thinning), or diagnostic uncertainty. Asymptomatic lesions can be observed.
Q: What is the malignant potential of intraosseous lipoma? A: Zero for practical purposes. Intraosseous lipoma is benign; the four presumed cases of malignant transformation Milgram reported are exceptionally rare and contested. Prognosis is excellent.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 52-year-old woman presents after ankle sprain. X-ray shows a well-defined radiolucent lesion in the calcaneus with a central dense calcification. She has no heel pain. What is your diagnosis and management?”
“A 58-year-old man presents with 6 months of hip pain. Imaging shows a 5cm radiolucent lesion in the intertrochanteric region of the proximal femur with central calcification and significant cortical thinning. MRI confirms fat signal. How do you manage this?”
“A 45-year-old presents with a radiolucent lesion in the calcaneus. Your colleague suggests this is a simple bone cyst. The X-ray shows some central density. How do you differentiate between intraosseous lipoma and simple bone cyst? What additional imaging would you order?”
Key Facts
- Rare benign tumor - under 0.1% of all bone tumors
- Calcaneus most common single site (about a third of pooled cases), proximal femur next
- Age 40-60 years, equal gender distribution
- Completely benign - no malignant potential
Pathognomonic Imaging
- Central calcification on X-ray - dense nidus within radiolucent lesion
- Fat signal on MRI - high T1, suppresses with fat saturation
- Distinguish from bone infarct - infarct has peripheral serpentine calcification
- MRI diagnostic - biopsy rarely needed if imaging classic
Milgram Classification
- Stage 1: Viable fat only - no calcification visible
- Stage 2: Fat necrosis with central calcification - the classic appearance
- Stage 3: Extensive calcification with cyst formation
- Staging reflects involution, NOT biological behavior - all benign
Clinical Presentation
- Asymptomatic (50-70%) - incidental finding
- Pain (30-50%) - dull, aching, activity-related
- Pathological fracture rare (under 5%) with large lesions
- No systemic symptoms
Management
- Asymptomatic: Observation with 6-month X-ray to confirm stability
- Symptomatic or fracture risk: Curettage with bone graft
- Prophylactic fixation if large lesion with cortical thinning
- Recurrence rare (under 5%) with complete curettage
Exam Pearls
- Central calcification = pathognomonic (vs peripheral in bone infarct)
- Fat on MRI confirms diagnosis - high T1, suppresses with fat-sat
- Calcaneus is #1 site - always think lipoma for lucent calcaneal lesion with central calcification
- Simple curettage curative - no wide margins needed (benign)
Evidence Base and Key Studies
Intraosseous Lipomas: A Clinicopathologic Study of 66 Cases (Original Milgram Classification)
- Landmark paper analysing 66 cases (61 histologically confirmed solitary lesions) that defined the still-used three-stage classification
- Stage I solid viable lipocytes; Stage II transitional fat necrosis with focal calcification plus viable fat; Stage III late involution with cyst formation, calcification and reactive bone
- The lesion undergoes spontaneous involution, so surgical excision may not be necessary in many cases
- Concluded intraosseous lipoma is not as rare as previously thought but is frequently underdiagnosed and confused with cysts and bone infarction
Intraosseous Lipoma: Report of 35 New Cases and a Review of the Literature
- 35 new cases plus meta-analysis of 110 further cases from the English-language literature (145 total)
- Mean age 43 years with near-equal sex distribution; 71% occur in the lower limb and 32% in the os calcis
- Central calcification far commoner in os calcis lesions (62%) than other sites (30%); marginal sclerosis 61% in os calcis vs 38% elsewhere
- Fat necrosis and cyst formation seen on MRI in 67% of cases - the radiological correlate of Milgram involution
Radiologic-Pathologic Correlation of Intraosseous Lipomas
- Correlated imaging appearances with histology across the three Milgram stages
- Stage 1 = uniform fat signal; Stage 2 = fat with central fat necrosis and calcification; Stage 3 = cystic degeneration, calcification and reactive bone
- MRI fat signal (matching subcutaneous fat, suppressing on fat-saturated sequences) is the key diagnostic feature
- Calcification and cystic change increase with stage, explaining why involuted lesions mimic bone infarct
Intraosseous Lipoma: Retrospective Analysis of 29 Patients (Surgical Outcomes)
- 29 patients (mean age 48 years) treated 1985-2002; Milgram stages I=10, II=14, III=3
- All treated by curettage; phenolisation added in 11 cases showed no added benefit
- No clinical or radiological recurrence at mean follow-up of 32 months (range 6-208)
- Asymptomatic lesions without impending fracture can be managed conservatively
Surgical Treatment of Confirmed Intraosseous Lipoma of the Calcaneus: A Case Series
- 14 patients with symptomatic calcaneal intraosseous lipoma treated by curettage (Milgram I=9, II=4, III=1)
- Mean VAS pain improved from 5.29 preoperatively to 1.14 at final follow-up (p less than 0.01)
- Mean Maryland foot score 97.7 and AOFAS ankle-hindfoot score 97.9 at final review
- No recurrence over a median follow-up of 84 months
From the Archives of the AFIP: Benign Musculoskeletal Lipomatous Lesions
- Authoritative AFIP pictorial review classifying benign lipomatous lesions of soft tissue, bone, joint and tendon sheath
- States intraosseous lipoma has a pathognomonic CT/MR appearance with fat in the marrow space
- Highlights liposclerosing myxofibrous tumour (intertrochanteric femur) as a key mimic and differential
- Reinforces that fat identification on cross-sectional imaging is diagnostic for the lipomatous family