Subscapularis Attachment | Posterior Dislocation Association | Medial Displacement
- Subscapularis attachment: The only rotator cuff tendon on the lesser tuberosity
- Medial displacement: Deforming force pulls fragment medially
- Posterior dislocation: Always rule out associated posterior dislocation (seizures/electrocution)
- Axillary view essential: Shows lesser tuberosity profile anteriorly
- Biceps tendon: Medial to GT, lateral to LT (in groove) - at risk during fixation
- “Modified Axillary view helps visualize lesser tuberosity profile
- “Chronic malunion can cause mechanical block to internal rotation
- “Open reduction requires deltopectoral approach
- “Hardware must avoid the bicipital groove
Overview
Lesser tuberosity fractures are rare as isolated injuries but significant because of their association with posterior shoulder dislocation and their effect on subscapularis function. The lesser tuberosity sits on the anterior aspect of the proximal humerus and is the insertion of the subscapularis tendon.
How often. The epidemiological study cited on this page (Court-Brown, 1,027 proximal humeral fractures) does not report a percentage for the isolated injury, so "uncommon" is the honest description. The fracture is frequently associated with posterior dislocation, though no series cited here quantifies how often, and it is often missed at first presentation.
Mechanism. A posterior glenohumeral dislocation avulses the tuberosity, and seizures and electric shock, common causes of that dislocation, do so through violent muscle contraction. Forced external rotation of the adducted arm is the other acute mechanism. A direct blow to the anterior shoulder is a rare cause.
Anatomy and Pathophysiology
The bone. The lesser tuberosity is an anterior projection of the proximal humerus, distal to the anatomical neck and smaller than the greater tuberosity. It forms the medial border of the bicipital groove, and knowing its normal outline is what lets you see a subtle displacement.
- Lateral: the bicipital groove, carrying the long head of biceps
- Lateral to the groove: the greater tuberosity
- Medial: the articular surface
Subscapularis. The only rotator cuff tendon on the lesser tuberosity, it inserts broadly onto it. It is the primary internal rotator of the shoulder and an anterior stabiliser of the glenohumeral joint, and after a fracture it is the deforming force, pulling the fragment medially.
The long head of biceps. It runs in the groove immediately lateral to the lesser tuberosity, retained by the transverse humeral ligament, which bridges the lesser to the greater tuberosity. Its proximity determines the surgical risk zones: it can be incarcerated in the fracture and is at risk during screw placement, which the biceps section below takes up.
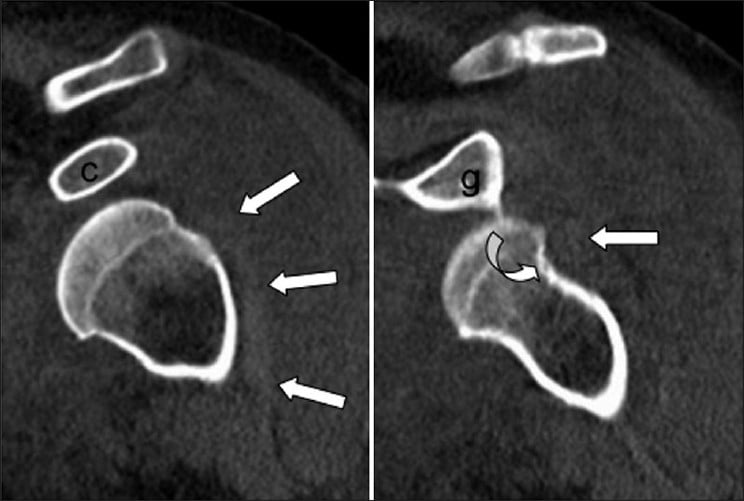
Pathomechanics. The avulsion comes from a violent subscapularis contraction, as in a seizure, with the muscle resisting the forces of posterior dislocation. Displacement is typically medial, from the muscle pull. A medially displaced fragment can create a mechanical block against the glenoid rim, and if it heals in malposition it limits internal rotation.
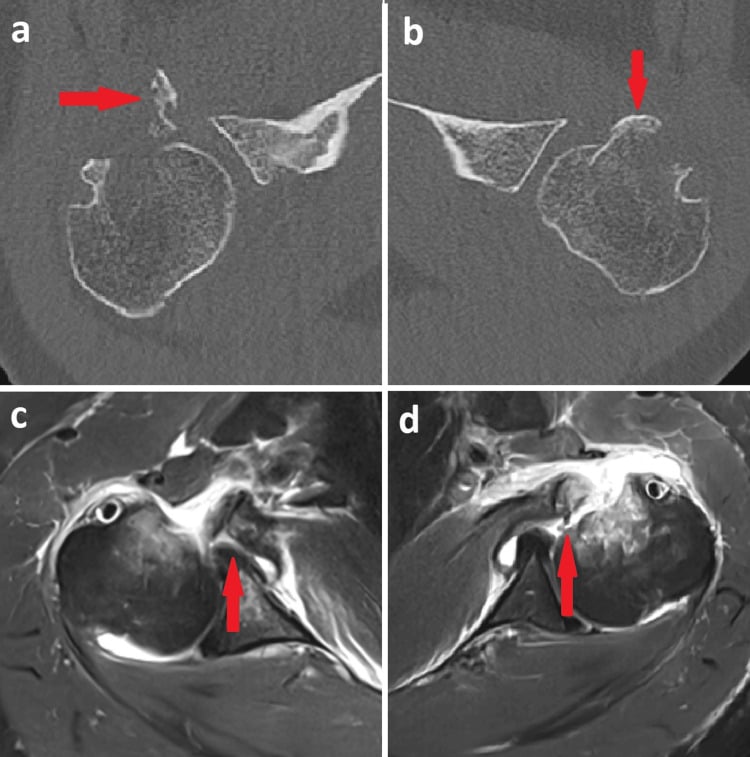
Classification
There is no widely used alphanumeric classification for isolated lesser tuberosity fractures equivalent to Neer's for the greater tuberosity. They are generally described by fragment size and displacement, less than or greater than 5 mm, and a descriptive grading on those lines aids surgical planning:
- Description
- Minimally displaced (less than 5 mm), small avulsion
- Description
- Displaced (greater than 5 mm), large fragment involving the articular surface
- Description
- Comminuted, with poor bone stock
- Description
- Associated with posterior dislocation
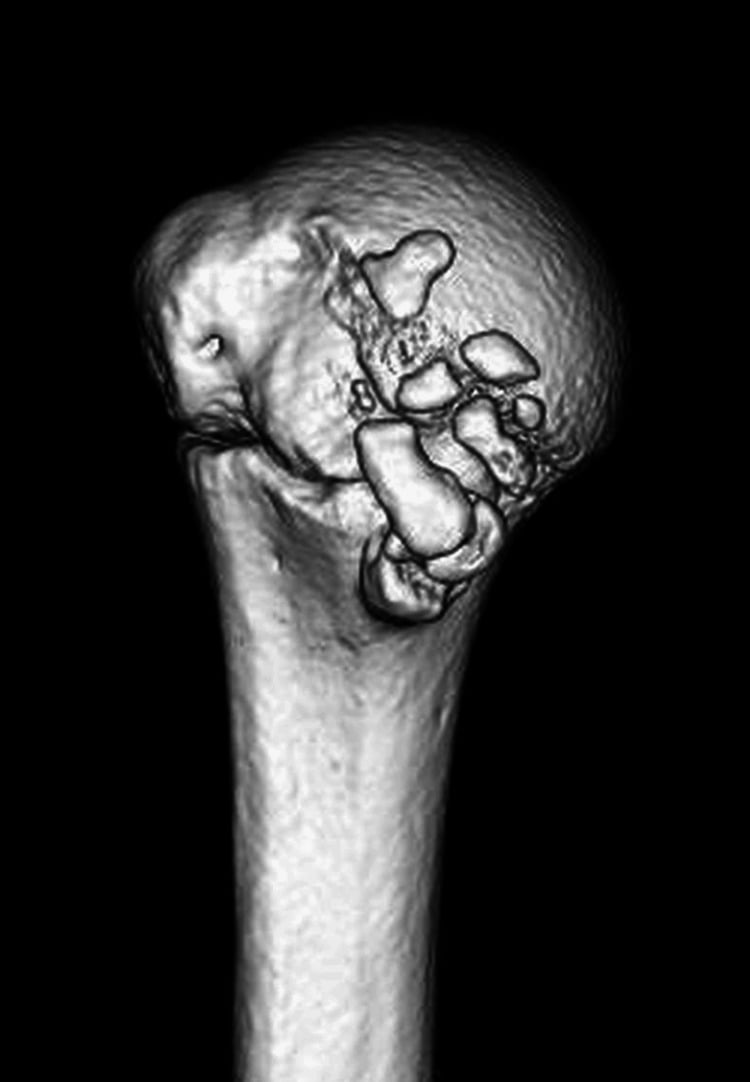
Ogawa is specific to the lesser tuberosity and is useful for choosing the implant. Type I is an avulsion: small fragments, usually isolated. Type II is a fracture: large fragments that often extend into the head or neck. The size of the fragment determines the fixation, anchor or screw.
Robinson classifies the overall proximal humerus injury and incorporates the lesser tuberosity as one of its parts. An isolated lesser tuberosity fracture is a 2-part injury; the 4-part fracture comprises greater tuberosity, lesser tuberosity, shaft and head; and the fracture-dislocation pattern is the one associated with posterior dislocation.
Clinical Assessment
History. The mechanism is a strong predictor of this fracture pattern, and a history of seizure must be asked for. The answers that matter:
- Seizure or electric shock
- Trauma with the arm in adduction and internal rotation
- A "pop" or a sensation of instability
The patient reports anterior shoulder pain, weakness of internal rotation and pain with overhead activity.
Examination. Physical examination must confirm that the joint is reduced first. Look for anterior swelling and bruising, and for posterior prominence with flattening of the anterior shoulder if the joint is dislocated. External rotation is limited by a painful stretch of the subscapularis, internal rotation by weakness or a block, and locked internal rotation suggests posterior dislocation.
Subscapularis tests. Avulsion of the insertion costs internal rotation strength, and these tests find it:
- Lift-off test - positive when the patient cannot lift the hand off the back
- Belly press test - positive when the wrist flexes or the elbow drops
- Bear hug test - sensitive for the upper subscapularis
Any lesser tuberosity fracture should raise high suspicion of a posterior shoulder dislocation until proven otherwise. Check the axillary view carefully.
LIGHTPosterior Dislocation Signs
Hook:Look for the LIGHT to diagnose the associated posterior dislocation.
Investigations
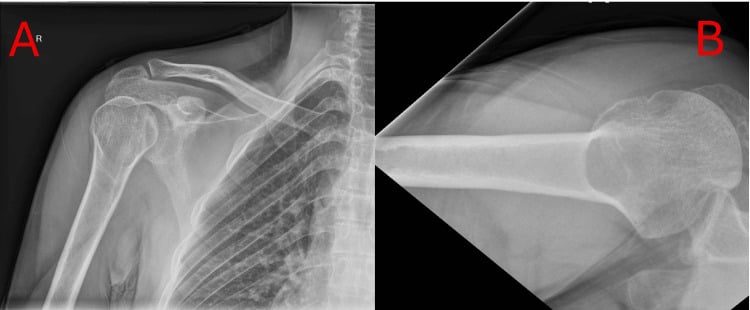
Radiographs. A standard series is usually sufficient for initial screening, provided it includes the axillary view:
- True AP (Grashey) - the fragment is often superimposed on the head as a double density, or seen medially
- Scapular Y - helps rule out dislocation
- Axillary - essential: it profiles the lesser tuberosity anteriorly and confirms glenohumeral reduction
The AP trap. An isolated fracture is easily missed on the standard AP because the fragment overlaps the humeral head; the axillary view is diagnostic. When the examination suggests a subscapularis injury and the frontal film is inconspicuous, an axillary view and CT are required.
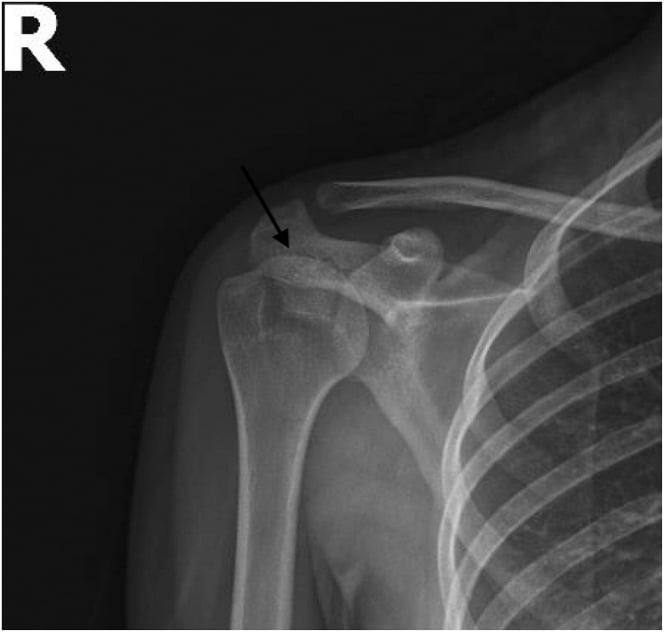
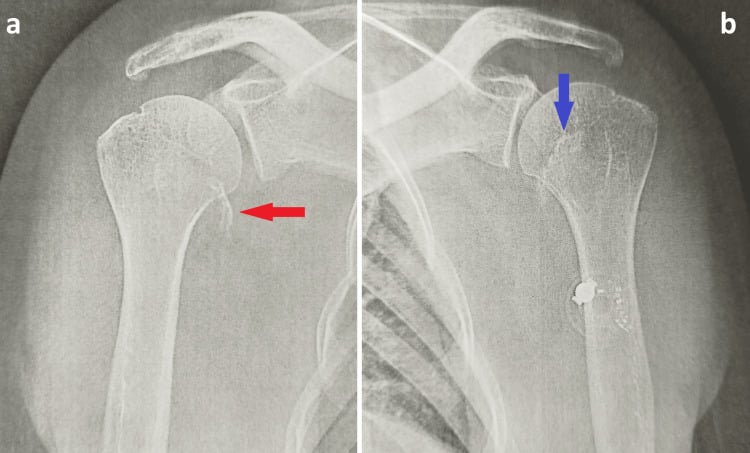
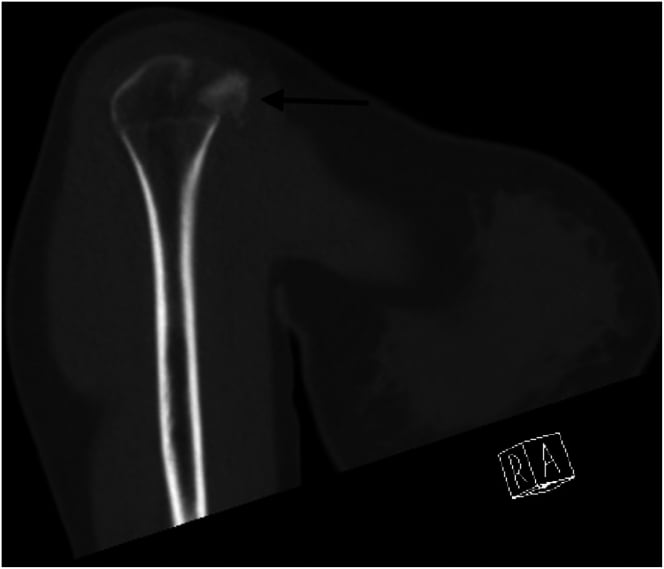
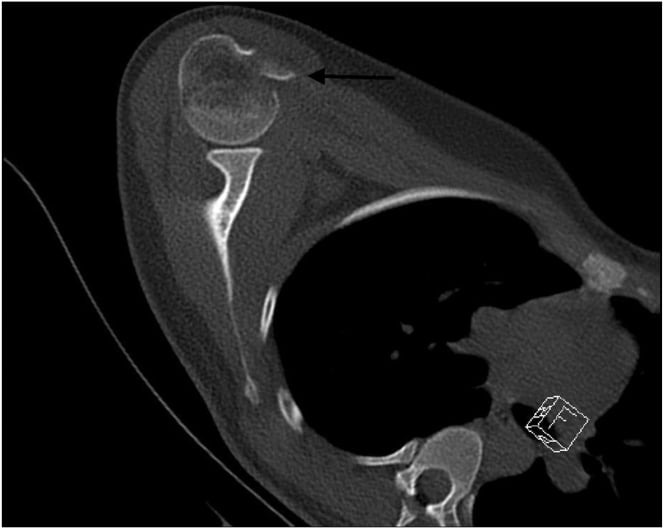
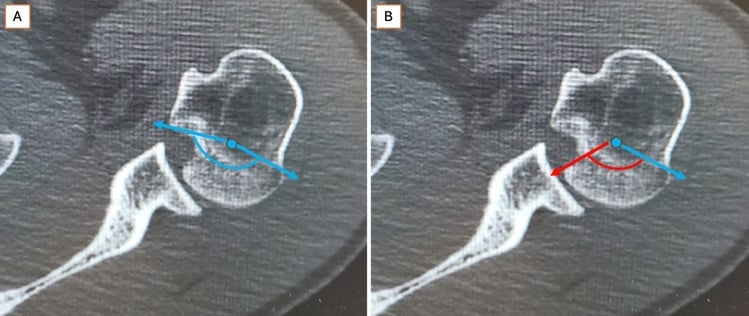
CT is the gold standard for lesser tuberosity assessment. It confirms a diagnosis that is often missed on radiographs, gives the exact displacement and the fragment size, shows comminution and involvement of the bicipital groove, and reveals a reverse Hill-Sachs lesion if the joint has dislocated. It is also the planning study for the choice between screw and anchor.
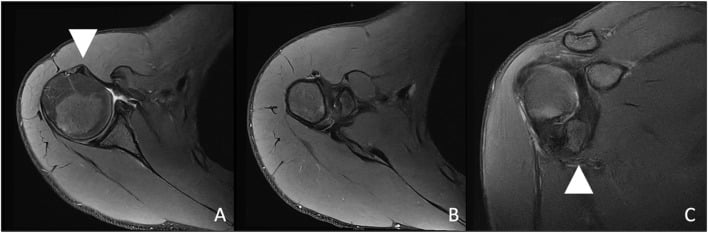
MRI is reserved for the soft tissues. It distinguishes a subscapularis tear from an avulsion, defines the extent of the soft-tissue injury and whether the tendon is repairable, and shows biceps and labral pathology. It is also the investigation for chronic pain.
Differential Diagnosis
The single most useful discriminator on imaging is the position of the fragment relative to the bicipital groove: a lesser tuberosity fragment sits medial to the groove, a greater tuberosity fragment lateral to it.
- Key Distinguishing Feature
- Bony fragment medial to bicipital groove; avulsion mechanism
- Best Test
- Axillary radiograph and CT
- Key Distinguishing Feature
- Tendon retraction without a bony fragment; older or overhead athlete
- Best Test
- MRI; lift-off and belly-press
- Key Distinguishing Feature
- Locked internal rotation, empty glenoid, reverse Hill-Sachs
- Best Test
- Axillary view and CT
- Key Distinguishing Feature
- Fragment lateral to groove; arm in external rotation
- Best Test
- AP and axillary radiograph
- Key Distinguishing Feature
- Pain over groove, no bony fragment; positive Speed/Yergason
- Best Test
- MRI or ultrasound
- Key Distinguishing Feature
- Global passive restriction, no trauma or fragment
- Best Test
- Clinical; normal radiograph
Management Algorithm
The threshold. Displacement greater than 5 mm is the widely cited operative threshold. It is expert consensus extrapolated from small series, not a validated cut-off: some advocate fixation at 3 mm in overhead athletes, and others tolerate larger displacement in low-demand patients.
- Displacement
- Less than 5mm
- Symptoms
- Minimal weakness
- Treatment
- Non-operative (sling)
- Displacement
- Greater than 5mm
- Symptoms
- Weakness / Block
- Treatment
- Surgical fixation
- Displacement
- Variable
- Symptoms
- Locked shoulder
- Treatment
- Reduce dislocation, then reassess
- Displacement
- Healed medial
- Symptoms
- Internal rotation block
- Treatment
- Excision or Osteotomy
Non-operative treatment suits displacement of less than 5 mm, the minimally displaced fracture, a fragment that does not block motion and the low-demand patient. If the fracture is stable, motion begins early to prevent stiffness, and close radiographic follow-up is required to ensure it does not displace late.
- Sling immobilisation for 4-6 weeks
- Passive external rotation restricted, usually to neutral, to protect the subscapularis
- Active internal rotation avoided for 6 weeks
- Elbow, wrist and hand motion immediately
- Progressive strengthening after 6-8 weeks
Operative indications. Surgery is indicated for:
- Displacement greater than 5 mm
- Mechanical block to rotation
- Intra-articular extension
- Open reduction of an associated posterior dislocation
- Biceps tendon incarceration
- Chronic weakness from symptomatic subscapularis insufficiency
- Unresolving pain in an active patient
The operation depends on fragment size and bone quality. A large fragment is fixed with screws; a small or comminuted one is repaired with suture anchors, the preferred option, or excised if it causes a block. Arthroplasty is for the head that is destroyed or carries a large reverse Hill-Sachs lesion.
Surgical Technique
Approach. The deltopectoral approach is the standard route to the lesser tuberosity, and adequate exposure is critical for anatomical reduction.
- Beach-chair position
- Incision from the coracoid to the axillary fold
- Develop the plane between pectoralis major (medial) and deltoid (lateral), retracting the cephalic vein laterally with the deltoid
- Expose the clavipectoral fascia and identify the conjoined tendon
Screws for the large fragment. Identify the fragment and the biceps tendon, which lies in the groove lateral to the lesser tuberosity. Reduce the fragment anatomically, hold it with a provisional K-wire and fix it with one or two 4.0 mm cannulated screws; a washer can be used to prevent pull-through. Screws provide rigid columnar support, and the danger is penetrating the articular surface or the bicipital groove.
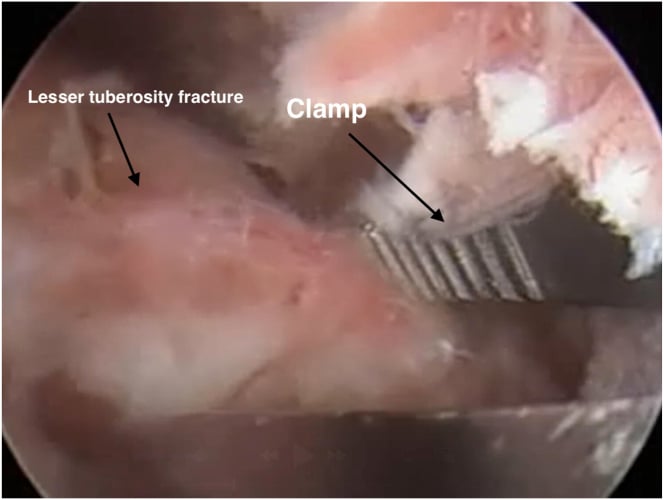
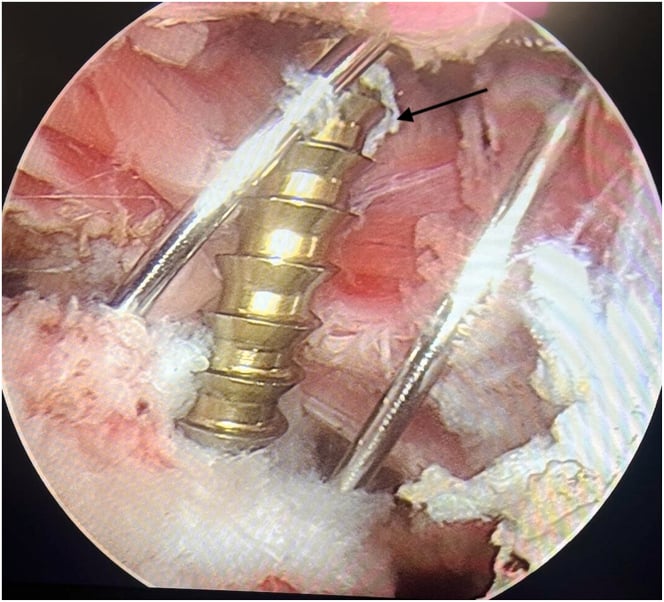
Suture anchors for the small or comminuted fragment. When the fragment is too small for screws or is comminuted, place anchors in the fracture bed (the humeral footprint), pass the sutures through the interface between the subscapularis tendon and the fragment, and tie them as a suture bridge or a simple mattress. The construct is biomechanically strong, avoids hardware prominence and is ideal for osteoporotic bone. In osteopenic bone, whether the tendon remains attached to the fragment determines whether the fixation should capture bone, tendon or both. Chronic cases require release sufficient to regain reduction without over-tensioning the subscapularis.
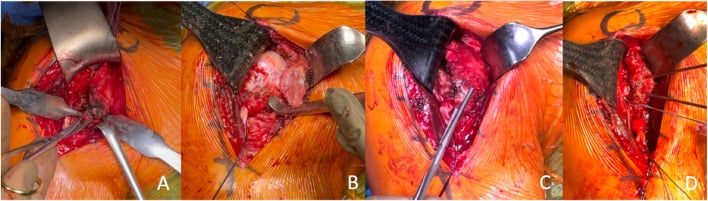
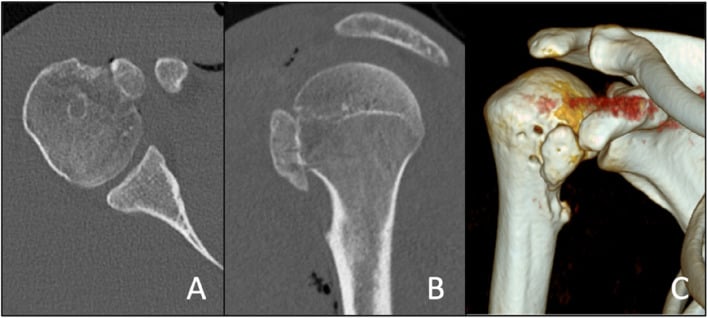
Excision. Indicated for a chronic malunion causing a block, a small piece blocking reduction, or late presentation (greater than 6 months). Excise the bony fragment, repair the subscapularis tendon to bone with transosseous sutures or anchors, and ensure a smooth arc of motion. Excision prevents future impingement.
The McLaughlin Procedure (Lesser Tuberosity Transfer)
For a locked posterior dislocation with an engaging anteromedial reverse Hill-Sachs defect, the McLaughlin procedure fills the defect.
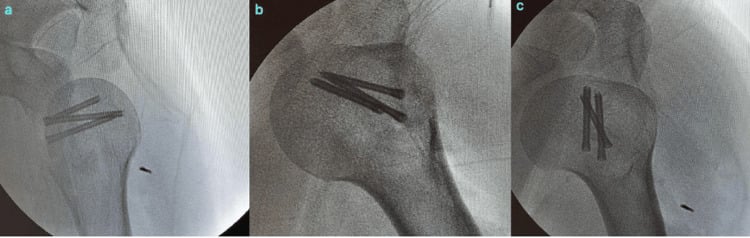
Two versions. McLaughlin's original operation (1952) transfers the subscapularis tendon into the reverse Hill-Sachs defect, so soft tissue fills and blocks the engaging notch. Neer's modification transfers the lesser tuberosity together with its attached subscapularis, a bone block that fills the notch more durably and heals bone to bone.
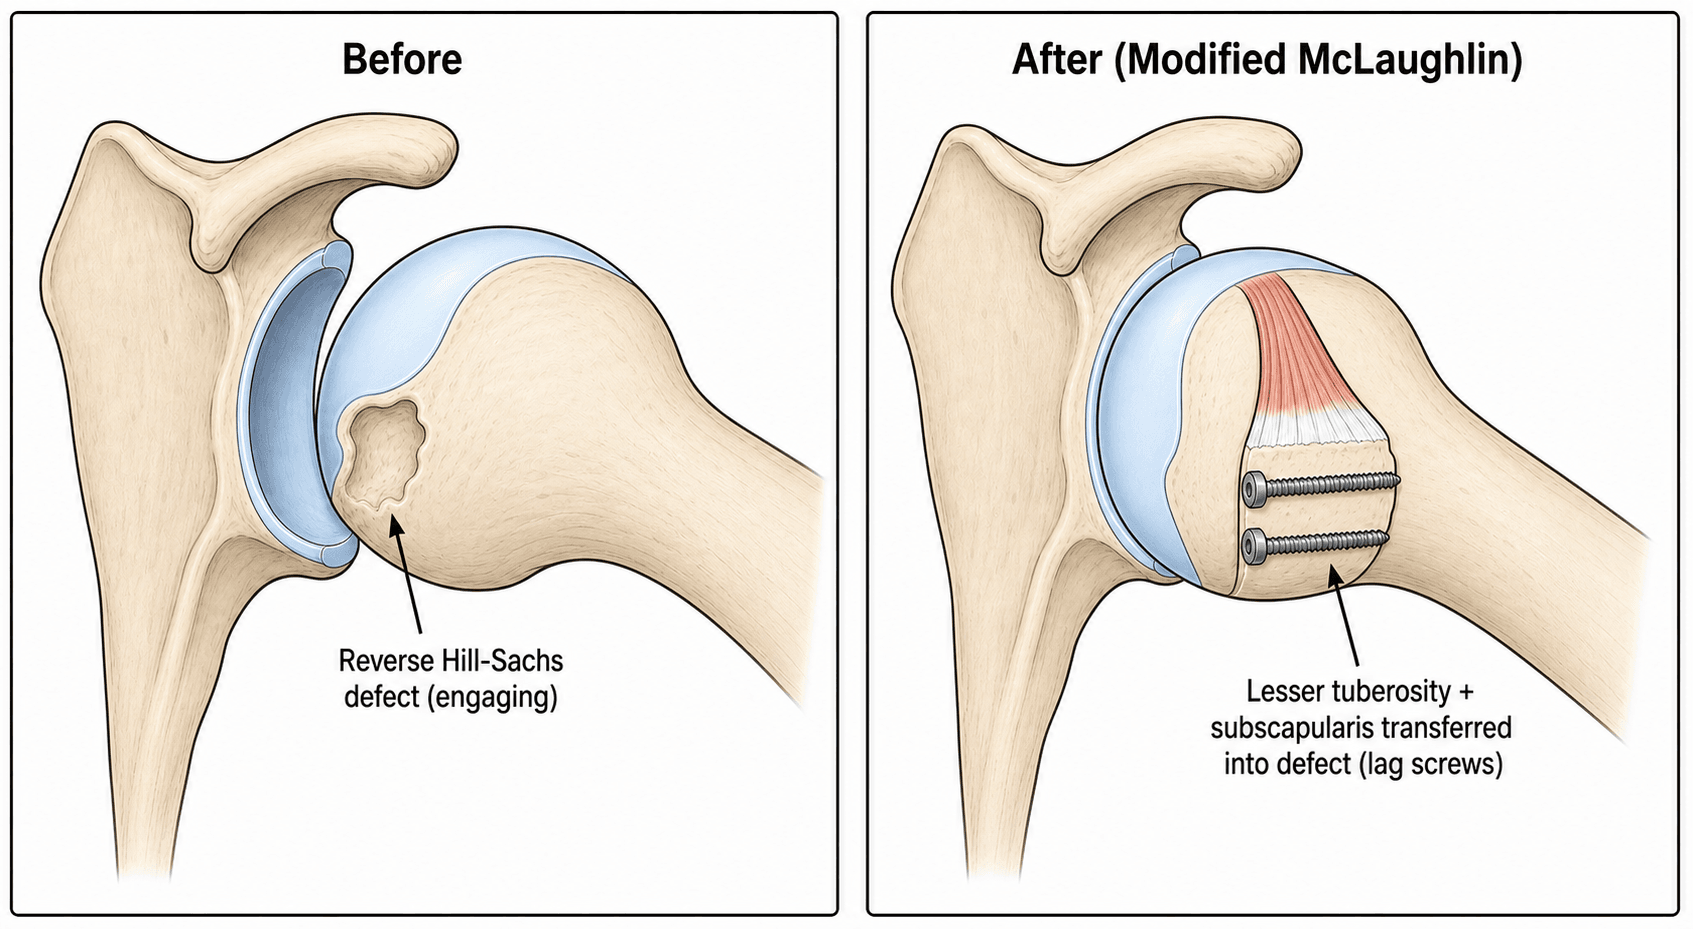
The modified technique. Through a deltopectoral approach, reduce the dislocation, osteotomise or elevate the lesser tuberosity with the subscapularis, transpose it into the defect and fix it with lag screws and sutures, with or without bone graft. Xiong used a partial lesser tuberosity plus artificial bone, secured with two lag screws and Ethibond.
Where it sits. Defect size drives the choice; the broader reverse Hill-Sachs decision is developed in the reverse Hill-Sachs lesions topic.
- Strategy
- Closed reduction +/- disimpaction; often stable
- Strategy
- McLaughlin / modified McLaughlin (lesser tuberosity transfer)
- Strategy
- Rotational osteotomy, osteoarticular allograft, or arthroplasty
How firm the cut-offs are. Treat them as convention rather than evidence. They are derived from small cohorts and vary between authors, and the only series cited on this page (Xiong, n=5) treated defects of 30-40% and tested no threshold at all. For that moderate defect the outcome was good: the Constant-Murley score improved from 46.0 to 85.8 with no recurrent instability.
The Long Head of Biceps in Lesser Tuberosity Fractures
Lying in the groove beside the fragment, the long head of biceps (LHB) is threatened by a lesser tuberosity fracture in three distinct ways. Always identify it: it is both the orientation landmark and the structure most at risk.
- Mechanism
- The LHB or a fragment becomes trapped in the fracture, blocking reduction
- Management
- Identify and FREE the tendon from the fracture before reducing; the block will not reduce until it is extracted
- Mechanism
- Loss of the medial groove wall / transverse ligament lets the LHB sublux medially out of the groove
- Management
- If the tendon is unstable, tenotomy or tenodesis rather than leaving it to subluxate and cause pain
- Mechanism
- Screws or anchors placed too laterally enter the groove and abrade or transfix the tendon
- Management
- Keep ALL hardware medial to / out of the bicipital groove; orient off the LHB as a landmark
The decision. When the LHB is damaged, unstable or an obvious pain generator at the time of lesser tuberosity fixation, deal with it definitively rather than ignoring it. Tenodesis suits the younger, higher-demand patient, because it preserves contour and avoids cramping; tenotomy suits the older, lower-demand patient. General LHB pathology, SLAP lesions and tenodesis technique are developed in the proximal biceps ruptures topic.
Complications
Subscapularis deficiency. Failure of healing, or non-union, leaves weak internal rotation and anterior instability, with positive lift-off and belly-press tests. It is the most common reason for revision if non-operative treatment fails.
Biceps pathology. Callus or hardware beside the tendon can cause tenosynovitis or rupture.
Recurrent posterior instability. If the lesser tuberosity fails to heal, the humeral head may subluxate posteriorly.
Malunion. A fragment that heals medially can block internal rotation, and is treated by excision or osteotomy. A prominent anterior malunion can also block internal rotation or impinge on the coracoid, and requires excision.
Postoperative Care
- Sling immobilisation
- No active internal rotation
- Passive external rotation limited, usually to 0 degrees (neutral)
- Elbow, wrist and hand motion
- Pendulum exercises started early
- Wean from the sling
- Progressive passive range of motion
- Gentle active-assisted motion, grade 1-2
- Avoid forceful external rotation, which puts tension on the subscapularis repair
- Active-assisted forward elevation
- Active range of motion allowed
- Isometrics progressing to isotonics
- Internal rotation strengthening begins
- Scapular stabilisation
- Hydrotherapy can be useful
- Return to sport and heavy labour
- Goal of full range of motion
- Maintenance of cuff strength
- Contact sport only when strength is 90% of the contralateral side
Outcomes
Union. Union rates are high, with generally excellent healing potential from the cancellous bed. Non-union is rare but symptomatic.
Function. The cited evidence is small but uniformly favourable: Ogawa reported all ten patients excellent or satisfactory (five of them operated), and Garrigues reported a mean ASES of 97 and WOSI of 94 in six adolescents. No series here is large enough to support a percentage.
Subscapularis strength often recovers to near normal, but some residual weakness on lift-off is common even with a successful repair.
The missed diagnosis leads to chronic pain and weakness. A chronic posterior dislocation missed for more than 3 weeks has a poor prognosis and often requires arthroplasty.
Guidelines, Registries & Global Practice
Global Epidemiology
- Isolated lesser tuberosity fracture is rare - a small minority of proximal humeral fractures. Do not attach a percentage to the Court-Brown series: as its card on this page notes, that paper never counts lesser tuberosity fractures, so no verified frequency exists.
- Two distinct populations: adolescent males with an apophyseal avulsion during sport (abduction-extension mechanism), and adults sustaining avulsion during a posterior dislocation from seizure, electric shock, or trauma.
- Posterior glenohumeral dislocation itself accounts for only 2-4% of all shoulder dislocations and is missed at first presentation in roughly half of cases.
Side-by-Side Guidance
- Region
- Global
- Emphasis
- Anatomical reduction of the subscapularis footprint; screw or suture-anchor fixation; protect the long head of biceps
- Region
- US
- Emphasis
- Most proximal humeral fractures non-operative; shared decision-making and early supervised motion
- Region
- UK
- Emphasis
- Senior review of fracture-dislocations; CT for surgical planning; urgent reduction of locked dislocations
- Region
- Europe
- Emphasis
- Recognise posterior dislocation early; reverse Hill-Sachs size drives reconstruction strategy
No society publishes a lesser-tuberosity-specific guideline; recommendations are extrapolated from proximal humerus and posterior instability guidance. The widely cited 5 mm displacement threshold is expert-consensus, not guideline-mandated.
Registry Note
- Proximal humerus registries (e.g. national arthroplasty registries) capture this injury only when it progresses to arthroplasty for a chronic locked fracture-dislocation; isolated tuberosity fixation is not separately tracked, so the evidence base remains case series rather than registry data.
High- vs Limited-Resource Practice
- Well-resourced settings: Cross-sectional CT for fragment sizing, MRI for tendon integrity, arthroscopic-assisted or open anchor repair.
- Limited-resource settings: Diagnosis rests on a good axillary radiograph and clinical subscapularis testing; transosseous suture repair through drill holes substitutes for anchors, with comparable healing in cancellous bone.
- Universal priority: Early reduction of any associated locked posterior dislocation — delay beyond 3 weeks markedly worsens the outcome regardless of setting.
Controversies and Areas of Uncertainty
The displacement threshold and the reverse Hill-Sachs cut-offs are discussed where they are used, under Management and the McLaughlin procedure.
Screw or suture anchor. No comparative trial exists. Large bony fragments favour lag screws; small, comminuted or apophyseal fragments favour an anchor lasso. The choice remains surgeon preference guided by fragment size and bone quality.
The role of arthroscopy. Arthroscopic-assisted repair is increasingly described, but the evidence is limited to case series. Open deltopectoral fixation remains the reference standard, especially when a posterior dislocation must also be addressed.
MCQ Practice
Self-Assessment Questions
Q: Which muscle attaches to the lesser tuberosity of the humerus?
- A) Supraspinatus
- B) Infraspinatus
- C) Teres Minor
- D) Subscapularis
- E) Pectoralis Major
A: D - The subscapularis is the only rotator cuff muscle that attaches to the lesser tuberosity. Supraspinatus, Infraspinatus, and Teres Minor attach to the Greater Tuberosity. Pectoralis Major attaches to the lateral lip of the bicipital groove.
Q: An isolated lesser tuberosity fracture following a seizure should raise highest suspicion for:
- A) Anterior dislocation
- B) Posterior dislocation
- C) Axillary nerve injury
- D) Biceps rupture
- E) Rotator cuff tear
A: B - Seizures cause violent muscle contractions leading to posterior dislocation. The lesser tuberosity fracture is often an avulsion injury associated with this mechanism.
Q: What is the most sensitive radiographic view for diagnosing a lesser tuberosity fracture profile?
- A) AP Internal Rotation
- B) AP External Rotation
- C) Scapular Y
- D) Axillary Lateral
- E) Outlet View
A: D - The Axillary Lateral view projects the lesser tuberosity anteriorly, allowing assessment of its profile and displacement. It is also diagnostic for posterior dislocation.
Q: What is the generally accepted displacement threshold for surgical fixation of lesser tuberosity fractures in active patients?
- A) 1mm
- B) 3mm
- C) 5mm
- D) 10mm
- E) Any displacement requires surgery
A: C - 5mm is the commonly cited threshold (Ogawa et al.) where surgical fixation is recommended to restore subscapularis function and prevent mechanical block.
Q: Which surgical approach is most appropriate for open reduction internal fixation of a lesser tuberosity fracture?
- A) Deltoid Splitting
- B) Deltopectoral
- C) Posterior
- D) Mackenzie
- E) Trans-acromial
A: B - The Deltopectoral approach utilizes the interval between the deltoid and pectoralis major to provide direct anterior access to the lesser tuberosity and subscapularis.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 40-year-old male presents with shoulder pain after a seizure. X-rays show a lesser tuberosity fracture. What is your immediate concern and how do you investigate it?”
“What are the surgical indications for a lesser tuberosity fracture?”
“Describe the Deltopectoral Approach for fixing a lesser tuberosity fracture.”
Key Facts
- Attachment: Subscapularis
- Threshold: 5mm displacement
- Assoc: Posterior Dislocation (Seizures)
- Nerve at risk: Axillary (inf), Musculocutaneous (medial retraction)
- Structure at risk: Biceps Tendon (lateral)
Surgical Steps
- Deltopectoral Approach
- Identify LHB and LT
- Reduce fragment (medial to lateral)
- Screw fixation (large) or Suture Anchor (small)
- Protect Biceps
Common Pitfalls
- Missing posterior dislocation
- Missing associated reverse Hill-Sachs
- Hardware in bicipital groove
- Failure to recognize subscapularis weakness
Examiner Favorites
- What muscle attaches here?
- Mechanism of injury?
- How do you test clinical function? (Lift-off)
- Surgical approach anatomy?
Evidence Base
Key Studies
Ogawa & Takahashi - Long-Term Outcome of Isolated Lesser Tuberosity Fractures
- Series of 10 isolated lesser tuberosity fractures (6 acute, 4 chronic), mean age 30 years
- ORIF most often recommended for displaced acute injuries; all 3 operated acute cases excellent/satisfactory
- In chronic cases conservative (muscle strengthening) is first line, with ORIF reserved for failures
Garrigues et al. - Subscapularis Avulsion of the Lesser Tuberosity in Adolescents
- 6 skeletally immature patients plus pooled literature review; mean follow-up over 4 years
- Prototype: 13-year-old male, abduction-extension sporting injury, positive belly-press and lift-off
- Suture-anchor lasso technique gave predictably good results (mean ASES 97, WOSI 94)
Levine et al. - Avulsion Fractures of the Lesser Tuberosity in Adolescents
- Case report plus literature review of lesser tuberosity apophyseal avulsion in adolescents
- Often present late as chronic shoulder pain after a missed acute diagnosis
- ORIF of the displaced apophyseal fragment restored full motion and strength at 4 months
Gerber & Krushell - Isolated Rupture of the Subscapularis Tendon
- 16 men with isolated subscapularis rupture from forced hyperextension or external rotation of the adducted arm
- Loss of internal-rotation strength and increased passive external rotation without instability
- Introduced and validated the lift-off test for clinically relevant subscapularis lesions
Xiong et al. - Modified McLaughlin for Locked Chronic Posterior Dislocation
- 5 locked chronic posterior dislocations with reverse Hill-Sachs defects of 30-40% of the head
- Lesser tuberosity plus artificial bone transferred into the defect, fixed with two lag screws and sutures
- Constant-Murley score improved from 46.0 to 85.8 with no recurrent instability at mean 19.8 months
Court-Brown et al. - Epidemiology of Proximal Humeral Fractures
- Prospective 5-year study of 1,027 proximal humeral fractures
- Unimodal age distribution peaking in women aged 80-89 years
- AO classification more comprehensive than Neer; isolated tuberosity patterns are uncommon