Motion Preservation Alternative to Fusion | Strict Patient Selection | Anterior Approach
- Primary indication = single or two-level DDD (L4-S1) with discogenic pain, failed conservative care
- Contraindications: Facet arthropathy, spondylolisthesis, previous surgery at level, osteoporosis, stenosis
- Motion preservation theoretically reduces adjacent segment disease (ASD) compared to fusion
- Anterior retroperitoneal approach (ALIF) required - major vascular structures at risk
- Patient selection critical - strict criteria essential for good outcomes
- “Ideal candidate: young (under 60), single-level L4-5 or L5-S1, no facet disease, good bone quality
- “Cannot perform if previous posterior surgery at same level (scar tissue)
- “Vascular injury (iliac vessels) is main intraoperative risk
- “Retrograde ejaculation risk from hypogastric plexus injury at L5-S1
- “Non-inferior to fusion in FDA IDE trials (Charite, ProDisc-L)
Overview and Rationale
Lumbar total disc replacement (TDR) is a motion-preserving alternative to spinal fusion for degenerative disc disease (DDD). The aim is to relieve discogenic axial low back pain while keeping segmental motion at the affected level, theoretically reducing the adjacent segment disease (ASD) that commonly follows fusion.
History. The concept dates to the 1960s and Fernström's stainless steel ball-and-socket designs. Modern TDR evolved in the 1980s and 1990s with better biomechanical understanding and materials science. The Charité artificial disc (SB Charité III, DePuy Spine) was the first FDA-approved device, in 2004, followed by ProDisc-L (Synthes) in 2006; several other designs hold European CE marking but not FDA approval.
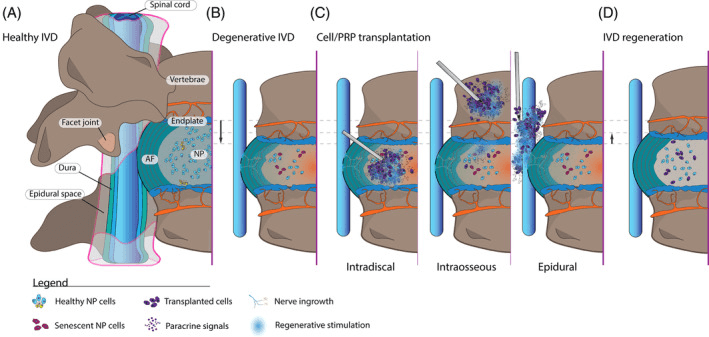
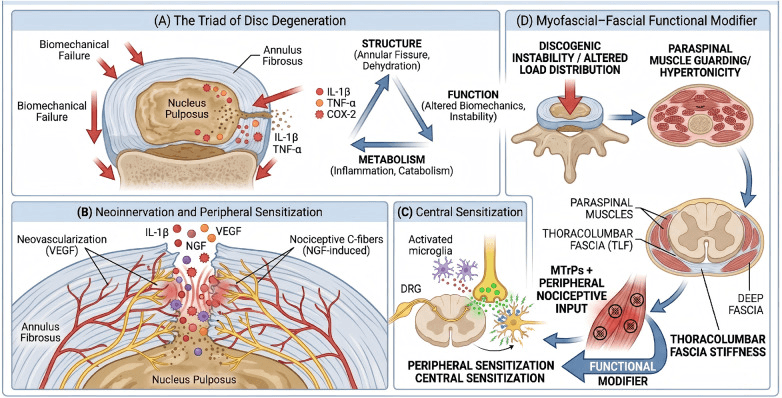
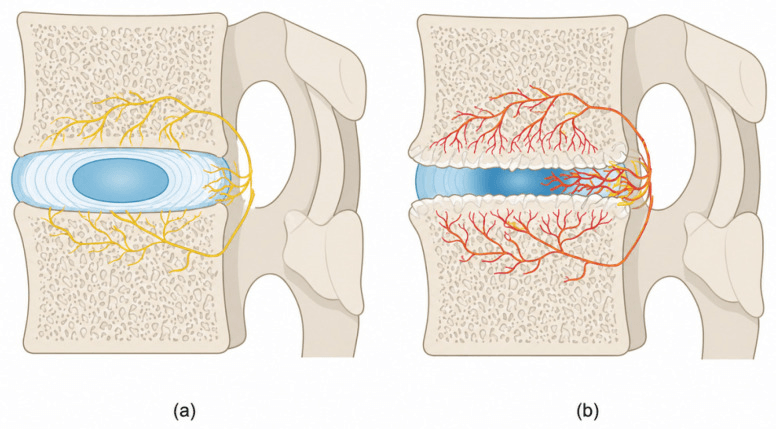
The degenerate disc as a pain generator. A healthy disc maintains an organised annulus, a hydrated nucleus and intact endplate exchange; degeneration brings matrix loss, annular disorganisation and impaired nutrient transport. Annular and endplate disruption combine with inflammatory signalling, neovascularisation and nociceptive ingrowth, which explains why a morphologically abnormal disc can become a pain generator.
The case against fusion. Adjacent segment disease is well documented after fusion: radiographic change develops in 8-30% of patients at 10 years, and clinical ASD requiring reoperation in 2-4% per year. The proposed mechanisms:
- Increased intradiscal pressure at the adjacent levels, up to 45%
- Altered kinematics, with hypermobility compensating
- Facet joint overload from loss of normal load sharing
- Accelerated disc degeneration from abnormal stress concentration
What TDR is meant to do. It aims to maintain physiological motion, 5-15° of flexion-extension per level, preserve the normal distribution of intradiscal pressure and reduce stress transfer to the adjacent segments. Whether it truly prevents ASD compared with fusion remains controversial; the benefit is still theoretical, and data beyond 10 years are still accumulating.
What the trials show. Multiple Level I randomised trials have compared TDR with fusion, and the FDA Investigational Device Exemption (IDE) trials for Charité and ProDisc-L established it as a viable alternative for highly selected patients. Across them:
- Clinical outcomes were non-inferior at 2, 5 and 10 years
- Pain relief and functional improvement were equivalent
- Motion was preserved at the index level, averaging 7-10°
- Overall complication rates were similar, but the complication profiles differed
- Adjacent-level reoperation was not significantly lower (1.9% vs 4.0%, p = 0.68); only the radiographic degeneration score differed
Implant Designs and Biomechanics
The designs divide by their bearing: a free polyethylene core, a fixed polyethylene inlay, or metal on metal.
SB Charité III (DePuy Spine)
Design. A three-component mobile-bearing device: an unconstrained ultra-high molecular weight polyethylene (UHMWPE) core between two cobalt-chromium-molybdenum (CoCrMo) endplates.
Biomechanics. Unconstrained motion allows translation and rotation, and the low constraint may reduce stress at the bone-implant interface. The self-centring core is intended to maintain the centre of rotation, but improper positioning brings the potential for core dislocation. Reduced constraint minimises implant-bone stress at the price of a technique that must be precise.
In practice. Strict midline placement is required to prevent core subluxation, and restoring sagittal alignment is more challenging than with fixed-bearing designs. Its FDA IDE trial showed non-inferiority to BAK-cage anterior interbody fusion; the circumferential-fusion comparator belongs to the ProDisc-L trial.
Outcomes. Patient satisfaction at 2 years in the FDA trial was 73.7% against 53.1% for fusion, a satisfaction figure and not the composite success endpoint. Motion averaged 6.0° at 5 years against 1.0° after fusion (Guyer). Heterotopic ossification is reported across a wide range in the literature, clinically significant far less often, and at 17 years 60% of Charité discs had spontaneously ankylosed (Putzier).
- Mobile-Bearing (Charité)
- 3 (endplates + core)
- Fixed-Bearing (ProDisc-L)
- 2 (integrated inlay)
- Metal-on-Metal (Maverick)
- 2 (metal-on-metal)
- Mobile-Bearing (Charité)
- Unconstrained
- Fixed-Bearing (ProDisc-L)
- Semi-constrained
- Metal-on-Metal (Maverick)
- Semi-constrained
- Mobile-Bearing (Charité)
- Variable (core migrates)
- Fixed-Bearing (ProDisc-L)
- Fixed posterior
- Metal-on-Metal (Maverick)
- Fixed central
- Mobile-Bearing (Charité)
- Limited
- Fixed-Bearing (ProDisc-L)
- Excellent (angled endplates)
- Metal-on-Metal (Maverick)
- Good
- Mobile-Bearing (Charité)
- High (positioning critical)
- Fixed-Bearing (ProDisc-L)
- Moderate
- Metal-on-Metal (Maverick)
- Moderate
- Mobile-Bearing (Charité)
- UHMWPE wear debris
- Fixed-Bearing (ProDisc-L)
- UHMWPE wear debris
- Metal-on-Metal (Maverick)
- Metallosis
- Mobile-Bearing (Charité)
- Approved 2004
- Fixed-Bearing (ProDisc-L)
- Approved 2006
- Metal-on-Metal (Maverick)
- Humanitarian device only
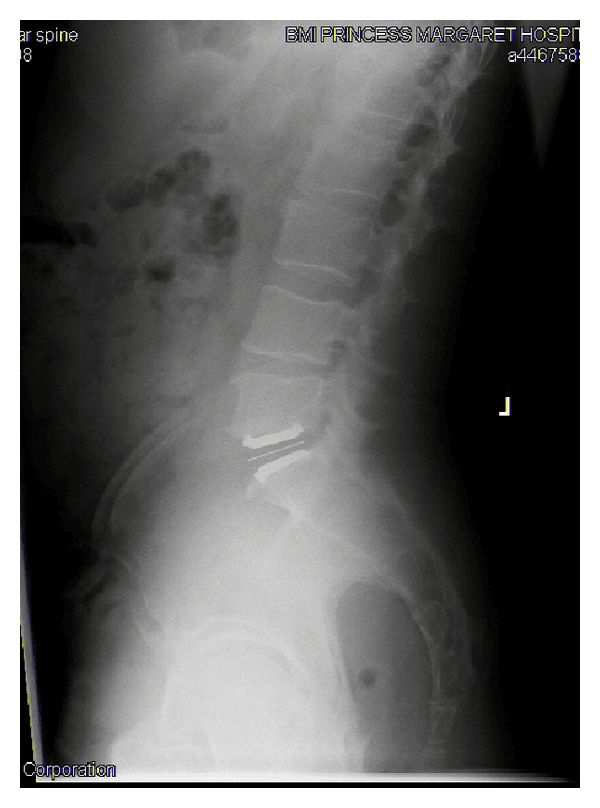
Patient Selection and Indications
Patient selection is the single most important determinant of TDR success. Expanding indications beyond strict criteria leads to poor outcomes and high complication rates. When in doubt, fusion is the safer option.
The approved indication. Symptomatic degenerative disc disease at L4-5 or L5-S1. Charité and ProDisc-L were approved for a single level, and ProDisc-L was later approved for two.
The criteria. The patient who qualifies has:
- Failed a minimum of 6 months of non-operative management, including physiotherapy, medication and injections
- Discogenic pain, shown by concordant pain provocation on discography or a high-intensity zone (HIZ) on T2-weighted MRI
- Maintained disc height of at least 4mm (some implants require at least 5mm)
- An age typically of 18-60 years, the upper limit varying by study and surgeon preference
- No facet arthropathy: less than Grade 2 facet degeneration on imaging
- No posterior element disease: an intact pars and no spondylolisthesis
- Skeletal maturity, with closed physes confirmed
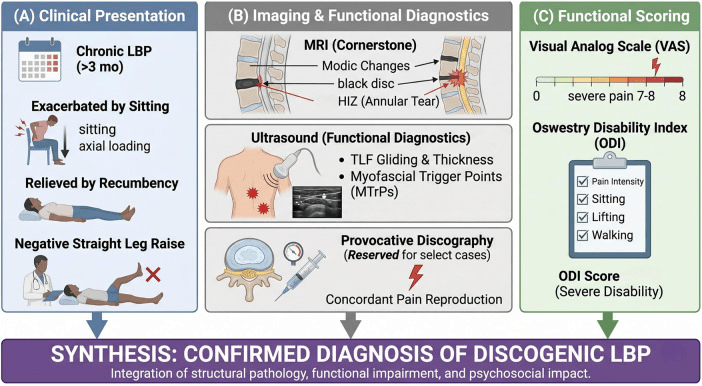
Absolute contraindications. Each of these excludes the patient from TDR:
- Facet joint arthropathy, moderate to severe (Fujiwara Grade 2 or higher). TDR does not address facetogenic pain.
- Spondylolisthesis. Motion preservation is inappropriate with baseline instability. Isthmic spondylolisthesis at any grade excludes TDR; for degenerative slips the threshold quoted ranges from any grade to greater than Grade I.
- Spinal stenosis: central canal stenosis requiring decompression, lateral recess or foraminal stenosis. TDR does not decompress.
- Previous surgery at the target level: discectomy, laminectomy or fusion. Scar tissue and altered anatomy preclude safe placement.
- Osteoporosis or severe osteopenia: a T-score below −1.5 on DEXA, or bone too poor for implant fixation, with a high risk of endplate subsidence and implant migration.
- Active infection: discitis, osteomyelitis or systemic infection, which contraindicate a metal implant.
- Severe disc collapse, with less than 4mm of disc height remaining: too little space for the implant, and altered biomechanics.
- Documented allergy to cobalt, chromium, molybdenum or titanium.
Relative contraindications. These raise the risk and call for an individual decision:
- Obesity, BMI over 35 kg/m², for approach difficulty and increased mechanical loading; morbid obesity, BMI over 40, brings vascular access challenges
- Active smoking, which impairs wound healing and may affect outcomes
- More than two levels of symptomatic DDD, which is not FDA approved
- Age over 60, leaving limited life expectancy for the benefit of motion preservation
- Workers' compensation, with worse outcomes in some studies, and ongoing injury litigation, associated with poor outcomes
- Psychological factors: untreated depression, chronic pain syndrome
- Pregnancy, current or planned within 2 years
FOSSILSTDR Contraindications
Hook:FOSSILS = Ancient, outdated patients for disc arthroplasty - these patients need fusion instead!
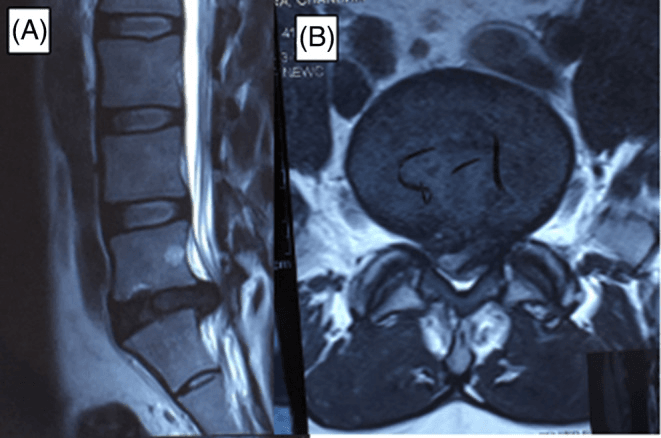
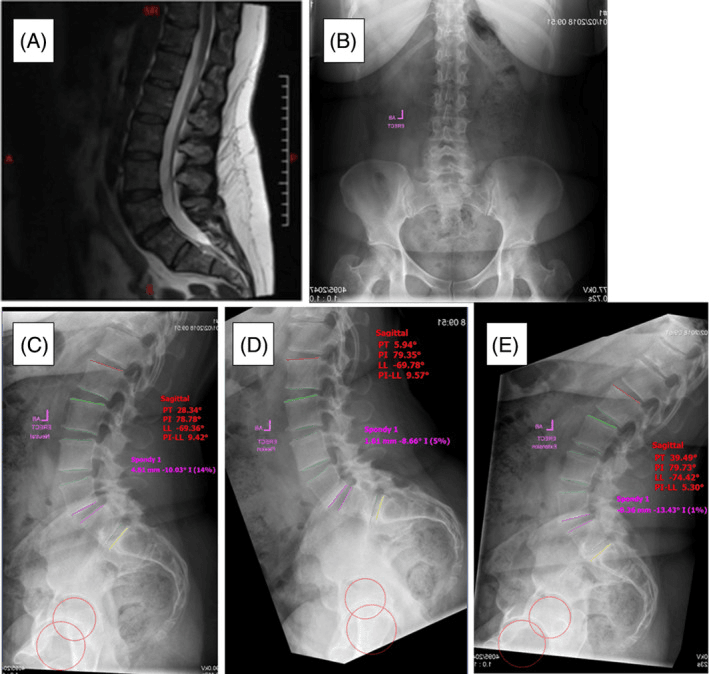
The ideal candidate. Beyond the criteria, the ideal candidate is aged 30-50, with single-level disease, pain confirmed by provocative discography and facets of Grade 0-1, and also has:
- Normal sagittal alignment
- Normal bone density, a T-score above −1.0
- No smoking, and a BMI under 30
- No previous lumbar surgery
- Psychological health and realistic expectations
- No involvement in litigation or workers' compensation
Few patients meet every ideal criterion, and clinical judgement decides which deviations are acceptable.
Differential Diagnosis of the Pain Generator
Before offering TDR you must be confident the pain is discogenic and isolated. The commonest reason for TDR failure is an unrecognised or mislabelled pain generator, and the table triages the patient presenting with chronic low back pain.
- Typical Features
- Central axial pain, worse with sitting/flexion, midline
- Key Imaging / Test
- Pfirrmann grade III-IV, HIZ on T2 MRI, concordant provocative discography
- Implication for TDR
- The ONLY indication — proceed if isolated
- Typical Features
- Pain with extension/rotation, paraspinal tenderness, worse standing
- Key Imaging / Test
- Facet hypertrophy on CT/MRI; relief with medial branch block
- Implication for TDR
- Absolute contraindication — TDR does not treat it
- Typical Features
- Mechanical pain, may have radicular features, start-up pain
- Key Imaging / Test
- Greater than 3mm translation or over 10° angulation on flexion-extension films
- Implication for TDR
- Contraindication — needs fusion
- Typical Features
- Neurogenic claudication, leg over back pain, relief with flexion
- Key Imaging / Test
- Central or lateral recess narrowing on MRI
- Implication for TDR
- Contraindication — needs decompression
- Typical Features
- Pain below L5, over the SIJ/buttock, FABER positive
- Key Imaging / Test
- SIJ provocation tests; diagnostic SIJ injection
- Implication for TDR
- Not addressed by TDR — exclude first
- Typical Features
- Non-anatomical pain, Waddell signs, yellow flags
- Key Imaging / Test
- Distress/risk screening; widespread pain
- Implication for TDR
- Predicts poor outcome — relative contraindication
Phenotypes. Vertebrogenic, annulogenic and mixed phenotypes have different anatomical pain generators. Separating them prevents selection of disc arthroplasty for pain dominated by endplate or neural pathology.
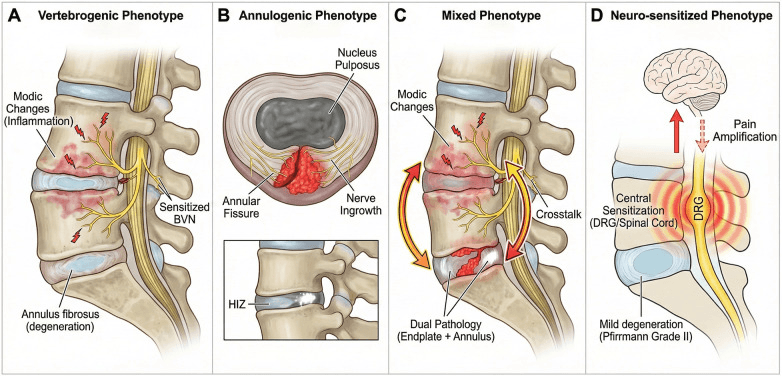
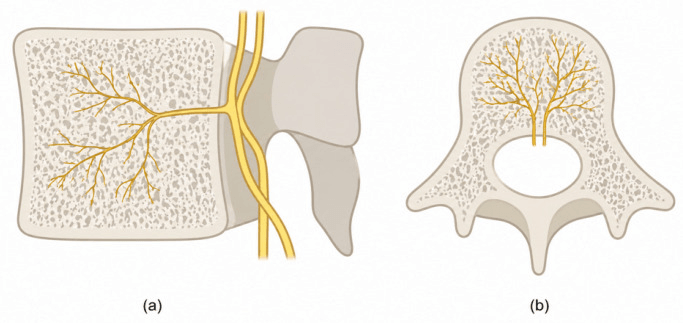
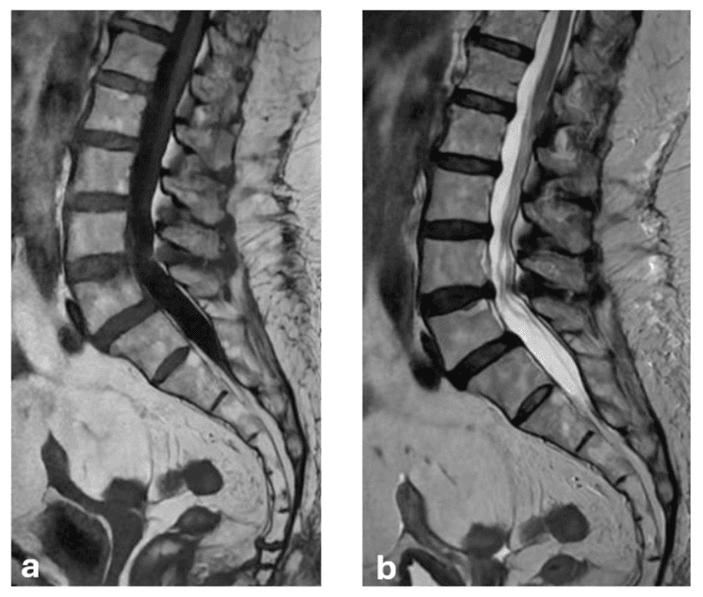
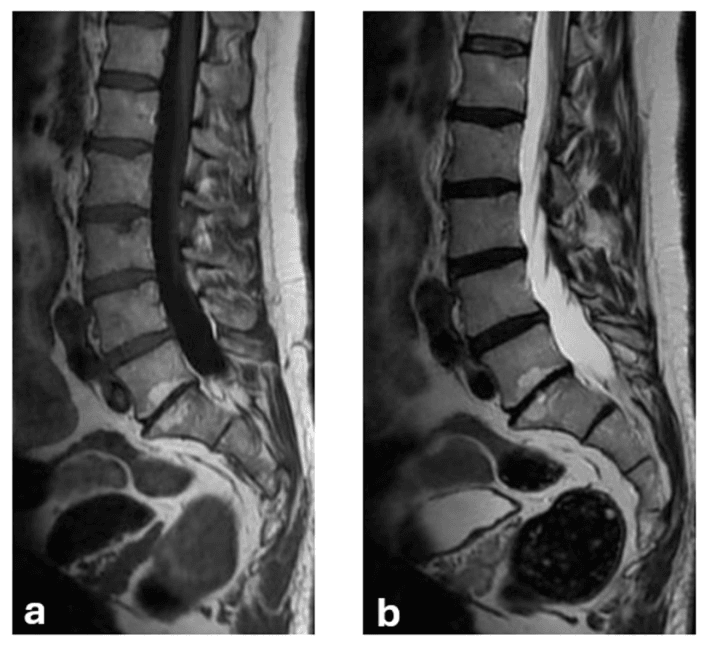
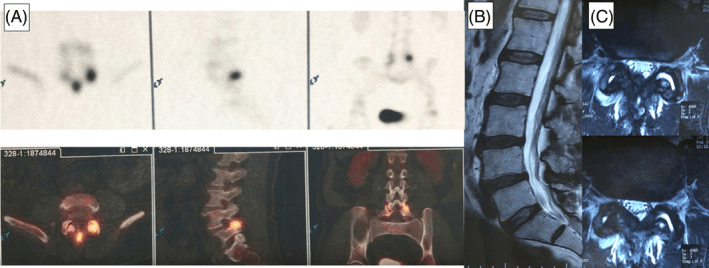
Vertebrogenic pain. The basivertebral nerve enters the posterior vertebral body and branches through the endplate region, an anatomical basis for vertebrogenic pain that can mimic discogenic pain. On MRI, Modic endplate change may indicate a vertebrogenic generator:
- Type 1: low signal on T1 and high signal on T2, reflecting active inflammatory endplate change that must be interpreted alongside the clinical pain phenotype
- Type 2: hyperintense on both T1 and T2, indicating fatty marrow replacement and a possible vertebrogenic rather than purely discogenic pain generator
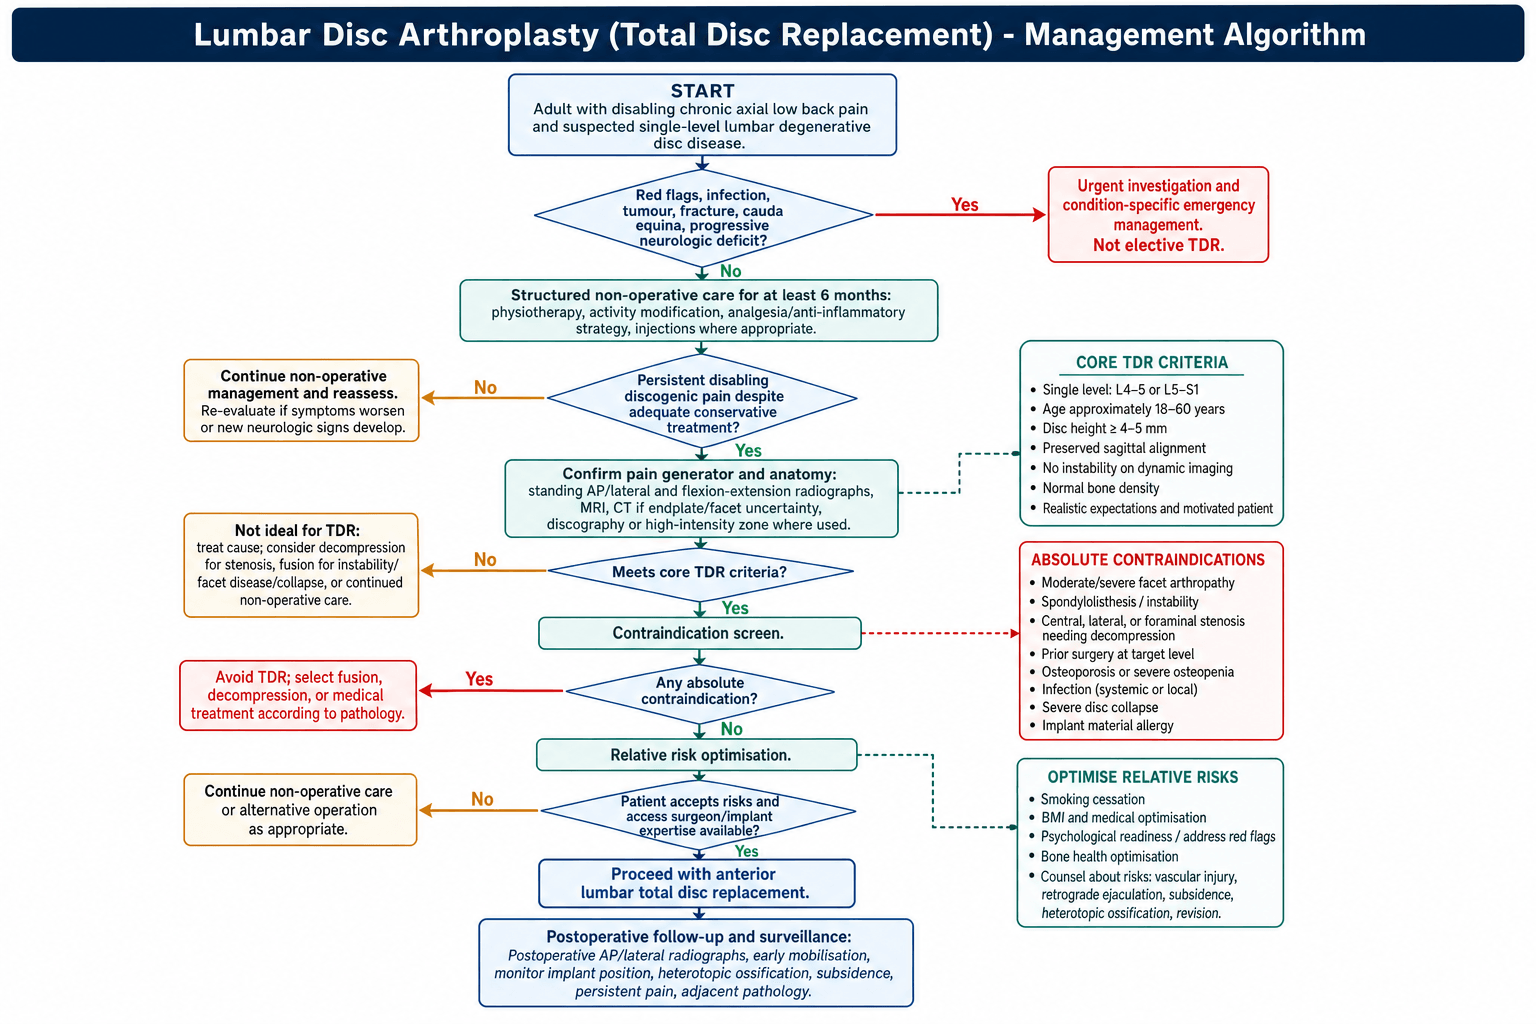
Decision Algorithm
Surgical Technique
Vascular surgery standby. Many surgeons recommend having a vascular surgeon available or performing the approach, particularly for L4-5, where left common iliac vein mobilisation is required. Have vascular instruments and blood products available.
Standing lateral radiograph. Measures the disc height at the target level (at least 4-5mm is required), the sagittal alignment (lordosis and pelvic parameters) and the implant size needed in the AP and lateral dimensions, and identifies transitional anatomy such as sacralisation or lumbarisation.
MRI. Confirms the disc degeneration (Pfirrmann grade) and identifies a high-intensity zone if present. It rules out facet arthropathy (Grade 2 or higher excludes the patient) and central, lateral or foraminal stenosis, and assesses adjacent-level disease.
CT, if needed. Evaluates the facet joints and endplate integrity better, identifies vascular calcification and rules out posterior element pathology.
Flexion-extension radiographs. Rule out instability, more than 3mm of translation or more than 10° of angulation, and assess motion at the target level. A level that has already fused spontaneously is not an indication for TDR.
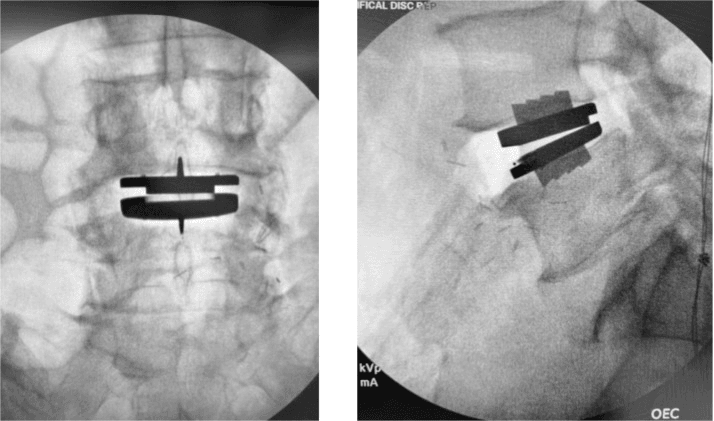
Sizing. Most systems use trial implants with fluoroscopic verification:
- Anteroposterior, typically 38-50mm, avoiding anterior cortical overhang
- Mediolateral, typically 30-42mm, staying within the lateral borders
- Height matched to the native disc or restored slightly, avoiding over-distraction
- Lordotic angle: ProDisc-L offers 6° or 11° for sagittal balance
Positioning.
- Supine on a radiolucent table
- Slight Trendelenburg (15-20°) to move the bowel contents cephalad
- Arms tucked or on arm boards, not extended over the head
- Minimal hip flexion, to reduce tension on the femoral vessels
- C-arm tested for a true lateral view before draping
Complications
Intraoperative
Vascular injury (1-3%). The most feared complication of the anterior approach. The iliac vessels are at highest risk, the vein more than the artery, and the left common iliac vein is particularly vulnerable at L4-5. Prevention is gentle retraction, good lighting and an available vascular surgeon; an injury needs immediate vascular surgery consultation, direct repair and possibly blood transfusion.
Visceral injury. Bowel perforation is rare if the peritoneum stays intact, and is recognised and repaired primarily. The ureter is identified, protected and retracted with the peritoneum. Bladder injury is rare, and more common with low transverse incisions.
Neurological injury. Nerve root injury is rare, a risk of posterior rather than anterior approaches. Sympathetic plexus injury causes retrograde ejaculation (below).
Malposition. Recognised on intraoperative fluoroscopy, and corrected by removing and repositioning the implant if it is significant. Checking with trial implants before the final one makes this easier.
Early (First 6 Weeks)
Retrograde ejaculation. Occurs in 1-5% at L5-S1 and in less than 1% at L4-5, higher with inexperienced surgeons or excessive dissection. Stretch or thermal injury to the hypogastric plexus leaves orgasm intact but ejaculation dry. It is usually permanent, so counsel the patient before surgery and refer to urology for fertility concerns; prevention is the careful handling of the plexus described in the approach.
Wound complications. Infection occurs in 1-2%, and prophylactic antibiotics are standard. Haematoma is rare because the retroperitoneal approach leaves less dead space, and dehiscence is rare with proper fascial closure.
Ileus. Occurs in 5-10%, from bowel manipulation during retraction. Management is conservative (nil by mouth, with a nasogastric tube if needed), and it usually resolves within 3-5 days.
Early subsidence. Subsidence in the first 6 weeks suggests osteoporosis or endplate violation. Serial radiographs monitor it, and more than 3mm is concerning. Asymptomatic subsidence is usually observed; progressive or symptomatic subsidence is treated by fusion.
Late (After 6 Weeks)
Heterotopic ossification (HO). Reported in 5-60% depending on the grading system, and clinically significant in 5-15%. It is ectopic bone formation, lying only in the surrounding soft tissue at Grade I and within or across the disc space at higher grades, and it is graded by McAfee (Grade 0-IV, below) or Brooker (Grade 1-4). Severe HO (Grade 3-4) may limit motion; Grade 1-2 is usually asymptomatic. Prevention is a postoperative NSAID (indomethacin 75mg daily for 6 weeks), with low-dose radiation controversial; established HO is observed if asymptomatic, and excision is rarely indicated.
Why HO grading matters. HO is the specific way a motion-preserving disc loses its motion and starts to behave like a fusion, the process behind the Putzier auto-fusion. Grading tells you whether the prosthesis is still moving. General HO biology and prophylaxis are covered in the heterotopic ossification topic; the McAfee scale, adapted from Ryu's cervical grading, is the disc-arthroplasty-specific grade, set by where the HO lies and what it does to prosthesis motion:
- Grade 0: no heterotopic ossification
- Grade I: HO present, but only in the surrounding soft tissue and not within the disc space
- Grade II: HO within the disc space, but not bridging it and not limiting prosthesis motion
- Grade III: HO bridging the disc space, with some motion still preserved on flexion-extension (a restricted range)
- Grade IV: bony ankylosis with no motion; the prosthesis has spontaneously fused
Grades 0-II preserve useful motion, and Grades III-IV, the "clinically significant" HO, progressively abolish it. High-grade HO negates the motion-preservation rationale, which is why postoperative NSAID prophylaxis is used and why long-term auto-fusion undermines the case for TDR.
Facet degeneration. Facet arthropathy may progress despite motion preservation. That suggests poor patient selection, with facet disease unrecognised before surgery, and symptomatic progression may require fusion.
Wear and loosening. Polyethylene wear is a long-term concern, beyond 10 years, and osteolysis from wear debris is rare but reported. Progressive endplate failure causes late subsidence, with osteoporosis a risk factor. Migration is very rare with modern designs, which use keel and teeth fixation.
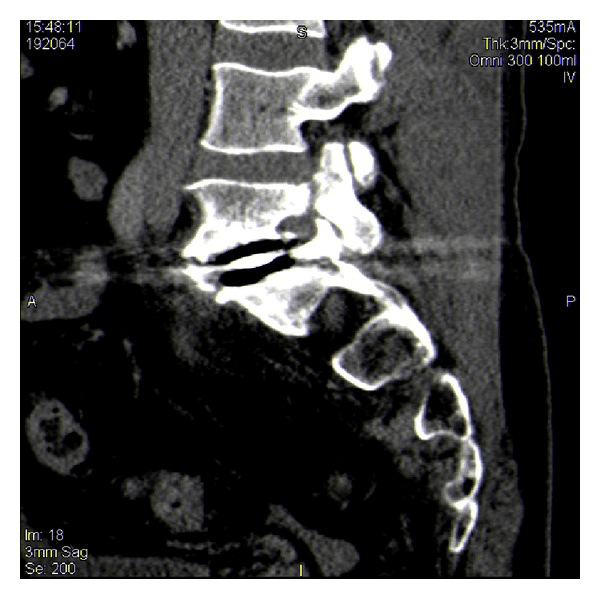
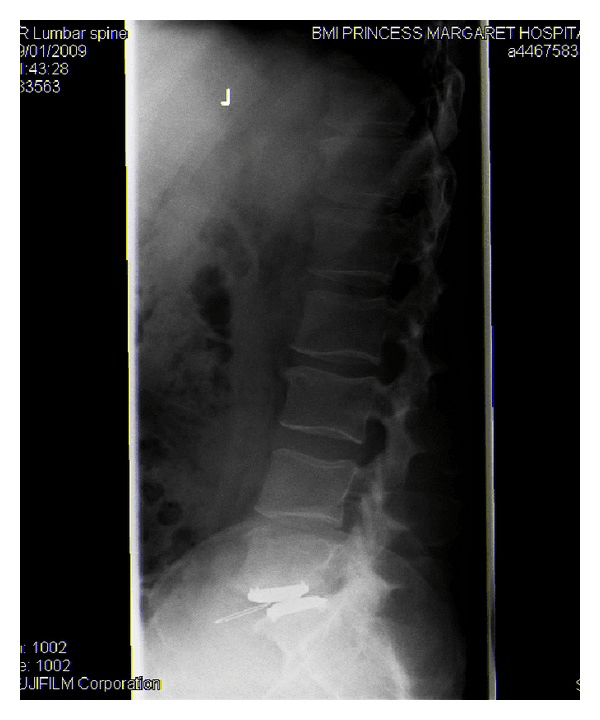
Core dislocation (Charité). Subluxation or dislocation of the mobile core occurs in 1-3%, related to malposition at surgery (non-midline placement). It may cause recurrent pain or a clicking sensation, and lateral radiographs show the core position.
Adjacent segment disease. Despite the theoretical benefit, ASD still occurs after TDR, at a lower rate than after fusion in some studies. Radiographic ASD is seen in 10-20% at 5 years, and symptomatic ASD requiring surgery in 2-4% per year, similar to fusion.
Persistent or recurrent pain. Occurs in 10-30%, similar to fusion. The causes are facetogenic pain missed at selection, persistent discogenic pain and psychosocial factors. Work-up rules out implant-related problems (subsidence, malposition, HO), and management is conservative, with fusion if the TDR has clearly failed.
Revision
When to revise. Revision is indicated for:
- Implant malposition causing symptoms
- Progressive subsidence with instability
- Infection
- Intractable pain despite appropriate patient selection
The options.
- Anterior revision TDR, removing and replacing the implant; technically demanding
- Anterior implant removal and fusion, converting to an ALIF with cage and screws
- Circumferential fusion, adding posterior instrumentation; the most common
Why revision is hard. The surgeon meets severe scar from the previous anterior approach, vascular adhesions to the vertebral bodies, and keel and teeth fixation that makes removal difficult. The complication rate is higher than for primary surgery, with 5-10% major complications. Revision to fusion gives 60-80% pain relief; data for revision TDR are limited and its outcomes less predictable.
Postoperative Rehabilitation and Return to Activity
0-6 weeks. The anterior approach spares the posterior musculature and causes less soft tissue trauma than posterior approaches, so patients mobilise on day 1 and typically go home within 1-3 days. With no arthrodesis to protect, rigid bracing is not required and a soft lumbar support is optional. The priority is early walking, avoiding heavy lifting, repetitive bending and end-range extension while the annulus and approach heal.
6-12 weeks. Progressive core and lumbar-stabilisation physiotherapy, with a graded increase in activity. Light or sedentary work often resumes by 2-6 weeks and manual work by around 3 months, guided by symptoms and radiographic stability (checking for subsidence or migration).
Sport. Low-impact activity (walking, cycling, swimming) is encouraged early. Higher-impact loading and contact sport are deferred to around 3-6 months, once motion and stability are confirmed.
How it differs from fusion. With no fusion mass to protect, rehabilitation is generally faster and less restrictive than after lumbar fusion, and motion is actively encouraged. The device relies on bony on-growth to the endplates, however, and early endplate loading before that fixation matures risks subsidence, so heavy loading is still staged.
Guidelines, Registries & Global Practice
Global Epidemiology and Utilisation
- Chronic low back pain is the leading cause of years lived with disability worldwide; isolated single-level discogenic pain in a young patient is the narrow niche TDR targets.
- TDR represents a small minority of lumbar surgery globally. Uptake peaked in the late 2000s after the FDA approvals and has since declined in most high-income systems as fusion techniques matured and long-term motion-preservation data disappointed.
- Highest sustained use is in parts of continental Europe (where multiple devices hold CE marking); use is comparatively low in the UK, North America, and most of Asia.
Side-by-Side Guideline Positions
- Position
- Charité (2004) and ProDisc-L (2006) approved for 1-level DDD L4-S1; ProDisc-L later 2-level
- Practical Effect
- Available but with strict labelled indications
- Position
- Procedure may be used with normal arrangements for consent/audit, but evidence on long-term efficacy is limited; not routinely funded
- Practical Effect
- Rarely performed in the NHS; case-by-case
- Position
- Coverage recommendation supports TDR for carefully selected 1-level discogenic DDD that has failed conservative care
- Practical Effect
- Used to justify insurer coverage in the US
- Position
- Recognised as an option in selected patients; emphasis on strict selection and surgeon experience
- Practical Effect
- Continued use in specialist European centres
- Position
- At best equivalent to fusion short-term; advantages not clinically meaningful; long-term harm uncertain
- Practical Effect
- Underpins cautious / restrictive funding
All major bodies converge on one point: patient selection and surgeon experience are decisive, and TDR is never a substitute for fusion when instability, facet disease, stenosis, or deformity is present.
Registry Evidence
- Unlike hip and knee arthroplasty, lumbar TDR has no large dedicated international implant registry; long-term survivorship data therefore rest on the IDE trial cohorts and single-centre series (e.g. the 17-year Charité data above).
- The Swedish Spine Register (Swespine) and similar national spine registries capture some TDR cases and consistently show good short- to mid-term patient-reported outcomes but high heterogeneity, reinforcing the selection-dependent nature of results.
- The absence of arthroplasty-grade registry surveillance is itself a recognised gap and a reason for ongoing caution.
High- vs Limited-Resource Practice Variation
- Well-resourced specialist centres: access to an approach (vascular/access) surgeon, intraoperative fluoroscopy, a range of implant sizes/lordotic angles, and MRI/CT selection workup — the setting in which TDR outcomes are best.
- Limited-resource settings: device cost, lack of an access surgeon, and limited revision capacity make TDR impractical; instrumented fusion (TLIF/PLIF/ALIF) is the pragmatic and far more commonly available motion-segment treatment.
- Globally, fusion remains the default for surgical discogenic pain; TDR is reserved for the rare ideal candidate where the infrastructure to do it safely exists.
Antibiotic Prophylaxis (Implant Surgery — Global Principle)
- Single-dose IV cephalosporin (e.g. cefazolin) at induction; substitute a glycopeptide where MRSA colonisation or beta-lactam allergy applies — consistent with WHO and major national surgical-site-infection prevention guidance.
- Reported surgical-site infection rates are under 2% with appropriate prophylaxis; deep implant infection is managed along arthroplasty/prosthetic-infection lines.
Controversies and Areas of Uncertainty
Does TDR actually prevent ASD? This is the central selling point. The 5-year ProDisc-L trial data show that radiographic adjacent-level degeneration is genuinely lower with TDR, yet adjacent-level reoperation rates are statistically similar to fusion. The radiographic benefit has not yet translated into a hard clinical endpoint: plausible, and not proven.
Auto-fusion of the prosthesis. If a motion-preserving device fuses itself, the rationale collapses, and long-term Charité data show 60% spontaneous ankylosis at 17 years, with heterotopic ossification the driver. Whether modern fixed-bearing designs behave better over 15-20 years is unknown.
Is the clinical advantage real? The Cochrane review found ODI and VAS differences favouring TDR that are statistically significant but below the threshold for clinical relevance, on low-quality, industry-sponsored evidence. NICE and several payers therefore do not endorse routine TDR.
The revision burden. Revising a TDR means a repeat anterior approach through scarred retroperitoneum and vascular adhesions, with a higher major-complication rate than primary surgery. Many surgeons argue this future morbidity outweighs an unproven ASD benefit, and favour primary fusion in borderline cases.
Discography as a selection tool. Provocative discography is used to confirm a discogenic source, but it is invasive and operator-dependent, has false positives, and may itself accelerate disc degeneration. Reliance on it for TDR selection is contested, and many centres prefer MRI HIZ or Modic changes plus clinical correlation.
Where TDR sits today. Use has declined globally as minimally invasive and lateral fusion techniques matured and long-term concerns about TDR emerged. It survives as a niche option for the rare, strictly selected young patient with single-level discogenic pain, not as a mainstream alternative to fusion.
MCQ Practice Points
Q: Which of the following is an absolute contraindication to lumbar total disc replacement?
A) Age 55 years B) BMI 32 C) Fujiwara Grade 2 facet arthropathy D) Two-level disease (L4-5 and L5-S1) E) Non-union of previous wrist fracture
Answer: C) Fujiwara Grade 2 facet arthropathy
Explanation: Moderate to severe facet arthropathy (Grade 2 or higher) is an absolute contraindication to TDR because the facet joints are a pain generator that TDR does not address. Patients with facet disease have consistently poor outcomes with TDR. Age 55 is acceptable (under 60 preferred). BMI 32 is a relative contraindication but not absolute. Two-level disease is FDA-approved for some devices (ProDisc-L). Previous wrist fracture is irrelevant unless it indicates systemic bone disease.
Q: During anterior approach to L4-5 for disc replacement, which structure must typically be mobilized to access the disc space?
A) Right common iliac artery B) Left common iliac vein C) Inferior vena cava D) Abdominal aorta E) Middle sacral artery
Answer: B) Left common iliac vein
Explanation: The left common iliac vein crosses anterior to the L4-5 disc space and must be mobilized cranially (superiorly) to access L4-5. This makes L4-5 approach more challenging and higher vascular risk than L5-S1, where access is between the bifurcation of the great vessels. The middle sacral artery is ligated at L5-S1, not L4-5. The IVC and aorta are more proximal (cephalad) and typically do not require mobilization.
Q: A 40-year-old male underwent L5-S1 disc replacement and reports inability to ejaculate 6 weeks postoperatively. What is the most likely cause?
A) Spinal cord injury B) Cauda equina syndrome C) Hypogastric plexus injury D) Pudendal nerve injury E) Psychological reaction to surgery
Answer: C) Hypogastric plexus injury
Explanation: Retrograde ejaculation from hypogastric (sympathetic) plexus injury occurs in 1-5% of L5-S1 TDR cases. The hypogastric plexus runs over the L5-S1 disc space anteriorly and can be stretched or injured during vessel mobilization. The patient has normal orgasm but dry ejaculation (semen goes into bladder instead of urethra). This is usually permanent. Spinal cord ends at L1-2 (not injured at L5-S1). Cauda equina would cause bowel/bladder/saddle numbness. Pudendal nerve injury would affect sensation and erection, not just ejaculation.
Q: What is the primary biomechanical difference between Charité and ProDisc-L lumbar disc replacements?
A) Charité is cemented; ProDisc-L is uncemented B) Charité has mobile polyethylene core; ProDisc-L has fixed core C) Charité is metal-on-metal; ProDisc-L is metal-on-polyethylene D) Charité requires posterior instrumentation; ProDisc-L does not E) Charité is placed posteriorly; ProDisc-L is placed anteriorly
Answer: B) Charité has mobile polyethylene core; ProDisc-L has fixed core
Explanation: The Charité is a mobile-bearing design with a free-floating polyethylene core between two metal endplates (unconstrained). The ProDisc-L is a fixed-bearing design with the polyethylene inlay fixed to the inferior endplate and articulating with the superior endplate (semi-constrained, ball-and-socket). Both are uncemented (rely on teeth/keel fixation). Both are metal-on-polyethylene (not metal-on-metal). Both are placed via anterior approach. Neither requires posterior instrumentation.
Q: What is the theoretical advantage of TDR over fusion regarding adjacent segment disease?
A) TDR decompresses adjacent neural elements B) TDR maintains motion, reducing stress transfer to adjacent levels C) TDR strengthens adjacent disc collagen D) TDR prevents facet degeneration at adjacent levels E) TDR increases disc height at adjacent levels
Answer: B) TDR maintains motion, reducing stress transfer to adjacent levels
Explanation: The biomechanical rationale for TDR is that fusion eliminates motion at the index level, transferring increased stress (intradiscal pressure up to 45% higher, altered kinematics) to adjacent segments, potentially accelerating degeneration. TDR preserves motion (5-15° per level), maintaining more physiologic load distribution and theoretically reducing adjacent segment stress. However, this benefit remains theoretical - while some studies show lower radiographic ASD rates with TDR, symptomatic ASD requiring surgery is similar between TDR and fusion in most long-term studies. TDR does not directly decompress, strengthen, or increase height at adjacent levels.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 42-year-old accountant presents with 18 months of chronic low back pain. MRI shows L5-S1 disc degeneration with high-intensity zone (HIZ) and maintained disc height. No facet arthropathy. Failed 8 months of physiotherapy and epidural injections. He asks about disc replacement after researching online. How do you counsel him?”
“A 38-year-old woman with chronic low back pain is referred by her GP requesting disc replacement at L4-5. Her MRI shows disc degeneration at L4-5 with Grade 2 facet arthropathy (moderate facet joint degeneration). She had a microdiscectomy at L4-5 three years ago. How do you manage?”
“You are performing an L4-5 disc replacement and mobilizing the left common iliac vein when you notice pulsatile bleeding from the vein. The access surgeon is not in the room but is in the hospital. How do you manage?”
“A 48-year-old woman had L5-S1 ProDisc-L performed 3 years ago at an outside institution. She initially did well for 12 months but now has recurrent severe low back pain. Imaging shows the implant is well-positioned with no subsidence, but there is progressive Grade 3 facet arthropathy at L5-S1 and Grade 2 at L4-5. She has failed injections and medications. She asks what can be done. How do you manage?”
Indications (Must Meet ALL)
- Single or two-level DDD at L4-5 or L5-S1 (FDA approved)
- Discogenic pain confirmed (provocative discography or HIZ on MRI)
- Failed conservative treatment minimum 6 months
- Age typically under 60 years (young patient, long benefit)
- Maintained disc height (at least 4-5mm for implant placement)
- NO facet arthropathy (Grade 0-1 only, Grade 2+ excludes)
- NO spondylolisthesis, stenosis, or previous surgery at level
Contraindications (FOSSILS)
- Facet arthropathy (major pain generator not addressed)
- Osteoporosis (T-score less than negative 1.5, subsidence risk)
- Spondylolisthesis (greater than Grade I, instability)
- Stenosis (spinal, needs decompression not motion)
- Infection (active or previous at target level)
- Levels more than 2 (multi-level disease not approved)
- Surgery previous at level (scar tissue, altered anatomy)
Implant Designs
- Mobile-bearing (Charité): 3-piece, unconstrained, free poly core
- Fixed-bearing (ProDisc-L): 2-piece, semi-constrained, ball-and-socket
- Metal-on-metal (Maverick): No polyethylene, metallosis concerns
- All use teeth/keel fixation (no cement), anterior approach only
Surgical Approach
- Anterior midline incision (infraumbilical for L5-S1, extended L4-5)
- Clear peritoneum laterally (retroperitoneal dissection)
- Control vessels: L5-S1 between bifurcation; L4-5 mobilize left iliac vein
- Expose disc space (ligate middle sacral vessels at L5-S1)
- Sympathetic plexus preserve (hypogastric, retrograde ejaculation risk)
- Secure implant (midline positioning critical, especially Charité)
Complications
- Vascular injury 1-3% (iliac vessels, higher at L4-5)
- Retrograde ejaculation 1-5% at L5-S1 (hypogastric plexus injury)
- Heterotopic ossification 5-15% clinically significant (may limit motion)
- Subsidence (early: osteoporosis; late: endplate failure)
- Implant malposition (check intraop fluoro, reposition if needed)
- Revision difficult (scar, vascular adhesions, implant removal challenging)
Evidence and Outcomes
- FDA IDE trials: Non-inferior to fusion at 2, 5, 10 years
- Motion preservation: 5-15° per level (average 7-10° long-term)
- Adjacent segment surgery: Lower rate than fusion (2-4% vs 4-8% at 5yr)
- Overall success: 70-80% in selected patients (patient selection critical)
- Reoperation rate: 5-8% at 5 years (lower than fusion 8-12%)
Exam Pearls
- Ideal candidate: Young (under 60), single-level L4-5/L5-S1, no facet disease
- Never offer TDR if facet arthropathy (absolute contraindication)
- L4-5 approach harder than L5-S1 (left iliac vein mobilization)
- Counsel males about retrograde ejaculation risk before L5-S1 TDR
- Non-inferior to fusion but different complication profile
- Strict patient selection = key to success (expanding criteria = poor outcomes)
Outcomes and Evidence Base
FDA Investigational Device Exemption Trials
Charité IDE Trial — 2-Year Clinical Results (Blumenthal et al.)
- 304 patients at 14 US centres, randomized 2:1: Charité TDR (n=205) vs anterior lumbar interbody fusion with BAK cage + iliac crest autograft (n=99)
- Single-level DDD L4-S1 unresponsive to non-operative care
- Clinical outcomes (VAS, ODI, SF-36) at least equivalent to ALIF; TDR recovered faster with lower disability scores at most intervals
- Patient satisfaction at 24 months: 73.7% (TDR) vs 53.1% (fusion), p=0.0011
- Reoperation rate lower with TDR: 5.4% vs 9.1%; hospital stay 1 day shorter
- Complication rate similar between groups
Charité IDE Trial — 5-Year Follow-Up (Guyer et al.)
- Five-year data: 90 Charité and 43 BAK fusion patients (133 randomized completers)
- Overall success 57.8% (Charité) vs 51.2% (BAK) — non-inferiority maintained vs the 2-year result
- No statistically significant difference in ODI, VAS, or SF-36 between groups
- Index-level ROM preserved: 6.0° (Charité) vs 1.0° (fusion)
- Additional index-level surgery: 7.7% (Charité) vs 16.3% (fusion)
- Lower long-term disability (8.0% vs 20.9%) and higher full-time employment with TDR
ProDisc-L IDE Trial — 2-Year Results (Zigler et al.)
- 286 patients treated on protocol, randomized 2:1: ProDisc-L vs circumferential (360°) fusion for 1-level DDD (L3-S1)
- 0% major device-related complications (safety endpoint)
- ODI improvement (at least 15%) in 77.2% (TDR) vs 64.8% (fusion)
- Neurological success superior with TDR: 91.2% vs 81.4% (p=0.0341)
- VAS pain and patient satisfaction significantly favoured TDR at 24 months
- Radiographic ROM maintained within normal range in 93.7%, averaging 7.7°
ProDisc-L 5-Year Adjacent-Level Degeneration (Zigler, Glenn, Delamarter)
- 5-year radiographs: 123 ProDisc-L TDR vs 43 circumferential fusion patients (single-level DDD)
- Adjacent-level degeneration: 9.2% (TDR) vs 28.6% (fusion), p=0.004
- In patients without baseline adjacent disease: new ALD 6.7% (TDR) vs 23.8% (fusion), p=0.008 — fusion patients 3x more likely to develop ALD
- Adjacent-level surgery: 1.9% (TDR) vs 4.0% (fusion), not statistically significant (p=0.68)
- Index-level ROM maintained: 7.3° preop to 6.0° at 5 years
ProDisc-L IDE — 5-Year Clinical Results (Zigler & Delamarter)
- 236 patients (161 TDR : 75 fusion), 81.8% follow-up at 5 years
- Composite study success: TDR non-inferior to fusion (12.5% margin, p=0.0099)
- Both groups maintained significant ODI improvement vs baseline (p less than 0.0001); VAS pain down ~48% in both
- Index-level secondary surgery: 8% (TDR) vs 12% (fusion)
- No TDR developed spontaneous fusion; segmental ROM stayed within normal range
- Would have surgery again: 82.5% (TDR) vs 68.0% (fusion)
Total Disc Replacement for Chronic Discogenic LBP — Cochrane Review (Jacobs et al.)
- 7 RCTs (24-month follow-up) included; significant risk of bias from industry sponsorship and absence of blinding
- Six trials compared TDR with fusion: ODI improved 4.3 points more with TDR (5 studies; 95% CI 1.85-6.68)
- Back-pain VAS improved 5.2 mm more with TDR (2 studies; 95% CI 0.2-10.3)
- Both differences, though statistically significant, fell BELOW the predefined threshold for clinical relevance
- Prevention of adjacent-level disease and facet degeneration was not adequately assessed
- Evidence graded LOW quality (GRADE)
Long-Term Outcomes (Beyond 10 Years)
Charité TDR — 17-Year Outcomes (Putzier et al.)
- 53 patients (63 Charité TDRs, types I-III) followed a mean of 17 years — the longest published lumbar TDR series
- Spontaneous ankylosis (auto-fusion) of the prosthesis occurred in 60%
- Reoperation required in 11%
- No adjacent-segment degeneration was seen in the 17% of implants that remained mobile, but these patients were significantly LESS satisfied than the auto-fused group
- No significant clinical difference between the three prosthesis generations
The Putzier series highlights that the long-term behaviour of a mobile-bearing prosthesis may converge on that of a fusion (auto-ankylosis), questioning whether the theoretical adjacent-segment benefit is realised in practice. Contemporary fixed-bearing devices (ProDisc-L) maintain measurable motion at 5 years, but comparable independent 15-20 year data remain scarce.
Comparison to Fusion Outcomes
- TDR (Average)
- 4-5 cm improvement
- Fusion (Average)
- 3-4 cm improvement
- Clinical Significance
- Similar magnitude
- TDR (Average)
- 20-25 point improvement
- Fusion (Average)
- 18-22 point improvement
- Clinical Significance
- Similar magnitude
- TDR (Average)
- 6-10° maintained
- Fusion (Average)
- 0-2° (fused)
- Clinical Significance
- TDR preserves motion
- TDR (Average)
- 2-4%
- Fusion (Average)
- 4-8%
- Clinical Significance
- Lower with TDR
- TDR (Average)
- 5-8%
- Fusion (Average)
- 8-12%
- Clinical Significance
- Lower with TDR
- TDR (Average)
- 5-15% clinically significant
- Fusion (Average)
- N/A
- Clinical Significance
- TDR-specific complication
- TDR (Average)
- 1-5% (L5-S1)
- Fusion (Average)
- Rare with posterior
- Clinical Significance
- TDR higher (anterior approach)
Predictors of Success
Positive Predictors:
- Age under 50 years
- Single-level disease
- Normal BMI (less than 30)
- No facet arthropathy
- No previous surgery
- Non-smoker
- No litigation/workers' compensation
- Realistic expectations
Negative Predictors:
- Multi-level disease
- Facet arthropathy (even mild)
- BMI over 35
- Active smoking
- Previous surgery at level
- Compensation/litigation
- Psychological comorbidities