SINS Classification | NOMS Framework | Bilsky Grading | Surgical Management
- SINS score determines mechanical stability (0-6 stable, 7-12 consult, 13-18 unstable)
- Bilsky grading assesses epidural cord compression (0-3, 1c or higher needs evaluation)
- NOMS framework integrates Neurologic, Oncologic, Mechanical, Systemic factors
- Radioresistant tumors: RCC, thyroid, melanoma require SBRT not conventional RT
- Separation surgery enables post-op SBRT for high-grade epidural disease
- “SINS 13 or higher = unstable spine requiring surgical stabilization
- “Bilsky 1c or higher in radioresistant tumor = surgical evaluation
- “MESCC is oncological emergency - steroids immediately, surgery within 24-48h
- “Ambulatory status at presentation predicts neurological outcome
Overview and Epidemiology
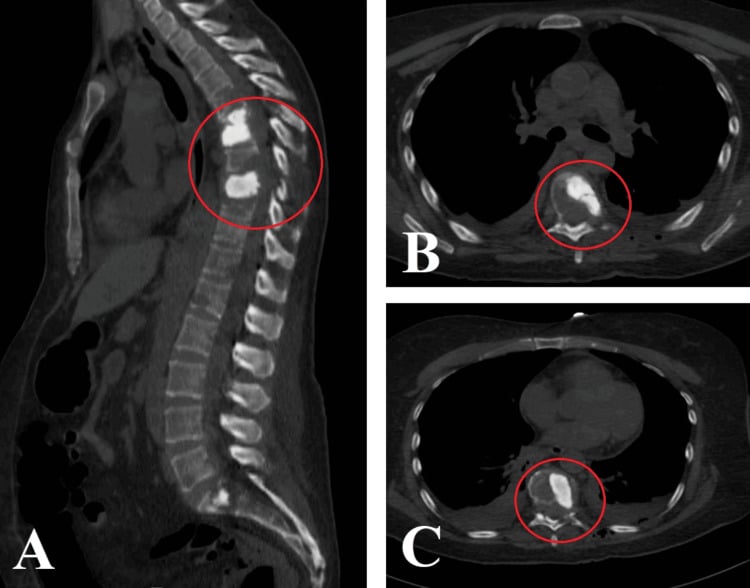
Metastatic disease is the most common neoplasm of the spine, 90% of all spinal tumours, and it costs the patient through pain, neurological dysfunction and mechanical instability. Between 10 and 30% of cancer patients develop spinal metastases, and the spine is the most common site of skeletal metastasis.
Who sends them. Breast, prostate, lung, thyroid and kidney primaries account for 80% of cases; the card carries what matters about each.
BPLTKBPLTK Primary Tumours
Hook:BPLTK account for 80% of all spine metastases
Where. The distribution follows red marrow, which is why the thoracic spine carries most of the disease. Each region brings its own problems:
- Frequency
- 70%
- Unique Considerations
- Kyphotic deformity, rib involvement
- Frequency
- 20%
- Unique Considerations
- Cauda equina, psoas involvement
- Frequency
- 10%
- Unique Considerations
- High morbidity, vertebral artery
- Frequency
- Rare
- Unique Considerations
- Pelvic organs, sacral nerve roots
Within the vertebra. The vertebral body, the anterior column, is involved in 85% of lesions, the pedicles in 60% and the posterior elements in 40%. Isolated posterior element disease is under 5%.
The valveless paravertebral venous plexus allows direct retrograde tumour spread from pelvic and abdominal organs to the spine, bypassing the pulmonary filter. This explains the high frequency of spine metastases from prostate, breast and lung primaries.
Pathophysiology
The metastatic cascade. Reaching the spine takes six steps:
- Local invasion - the primary tumour invades local vasculature
- Intravasation - tumour cells enter the circulation
- Survival - evading immune surveillance in the bloodstream
- Extravasation - exit at distant sites, where Batson's plexus plays its part
- Colonisation - a micrometastasis is established in the marrow
- Angiogenesis - a blood supply develops for growth
Osteolytic metastases, the most common type, destroy bone through osteoclast activation: the tumour secretes PTHrP, IL-6 and IL-11. They appear as punched-out lesions with cortical destruction, cause rapid structural compromise, and the fracture risk is high once over 50% of the vertebral body is involved.
Osteoblastic (sclerotic) metastases lay down abnormal bone under TGF-beta, BMPs and endothelin-1, giving dense sclerotic lesions, the "ivory vertebra". Prostate cancer is 95% blastic and some breast cancers are too. Blastic lesions are relatively more stable, but a dense vertebra is still biomechanically abnormal.
Mixed lytic and blastic metastases show both destruction and formation, a variable tumour-bone interaction with heterogeneous density. Half of breast cancer metastases are mixed, and lung is another source. For stability they are treated as lytic.
By primary. Lesion type, vascularity, radiosensitivity and prognosis all travel with the histology:
- Lesion Type
- Mixed/Lytic
- Vascularity
- Moderate
- Radiosensitivity
- Moderate
- Median Survival
- 24-36 months
- Lesion Type
- Blastic
- Vascularity
- Low
- Radiosensitivity
- Moderate
- Median Survival
- 24-36 months
- Lesion Type
- Lytic
- Vascularity
- Moderate
- Radiosensitivity
- Radiosensitive
- Median Survival
- 6-12 months
- Lesion Type
- Lytic
- Vascularity
- High
- Radiosensitivity
- Radioresistant
- Median Survival
- 12-24 months
- Lesion Type
- Lytic
- Vascularity
- High
- Radiosensitivity
- Radioresistant
- Median Survival
- 24-48 months
- Lesion Type
- Lytic
- Vascularity
- Low
- Radiosensitivity
- Radiosensitive
- Median Survival
- 24-36 months
- Lesion Type
- Lytic
- Vascularity
- Moderate
- Radiosensitivity
- Radioresistant
- Median Survival
- 6-12 months
RCC and thyroid metastases are highly vascular. Preoperative embolisation is essential to reduce intraoperative blood loss. Consider embolising 24-48 hours before surgery when operatively managing these tumours.
Classification Systems
SINS - Spinal Instability Neoplastic Score
SINS answers one question: is this spine mechanically stable? Six components are scored and summed to a maximum of 18 points.
- Score
- Description
- Score
- 3
- Description
- Highest instability risk
- Score
- 2
- Description
- Moderate risk
- Score
- 1
- Description
- Lower risk (rib cage support)
- Score
- 0
- Description
- Minimal risk
- Score
- Description
- Score
- 3
- Description
- Suggests structural compromise
- Score
- 1
- Description
- Less concerning
- Score
- 0
- Description
- Favourable
- Score
- Description
- Score
- 2
- Description
- Highest fracture risk
- Score
- 1
- Description
- Intermediate
- Score
- 0
- Description
- More stable
- Score
- Description
- Score
- 4
- Description
- Critical instability
- Score
- 2
- Description
- Significant
- Score
- 0
- Description
- Favourable
- Score
- Description
- Score
- 3
- Description
- Severe compromise
- Score
- 2
- Description
- Moderate
- Score
- 1
- Description
- At risk
- Score
- 0
- Description
- Intact
- Score
- Description
- Score
- 3
- Description
- Highest instability
- Score
- 1
- Description
- Moderate
- Score
- 0
- Description
- Stable
Reading the total. The score sorts the spine into three bands, and the band tells you who needs to be in the room:
- 0-6, stable: no surgical consultation required; radiation alone if oncologically indicated
- 7-12, potentially unstable: surgical consultation recommended, and clinical judgement decides whether to stabilise
- 13-18, unstable: surgical stabilisation required
Bilsky Epidural Compression Scale
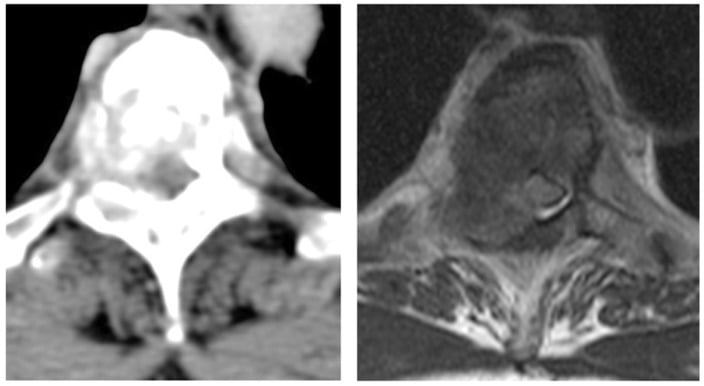
The epidural spinal cord compression (ESCC) scale grades what the epidural tumour is doing to the thecal sac and cord on the axial image, from bone-only disease to circumferential compression with no CSF left. What grade 1c means depends on histology: in a radiosensitive tumour it may be observed or treated with radiation alone, and the radioresistant case is the alert below.
- Description
- Bone-only disease
- Management
- Radiation if indicated
- Description
- Epidural impingement, no thecal deformation
- Management
- Radiation alone
- Description
- Thecal sac deformed, no cord contact
- Management
- Radiation alone
- Description
- Cord contact without compression
- Management
- Surgical evaluation
- Description
- Cord compression, CSF visible
- Management
- Surgical decompression
- Description
- Cord compression, no CSF (circumferential)
- Management
- Urgent surgery
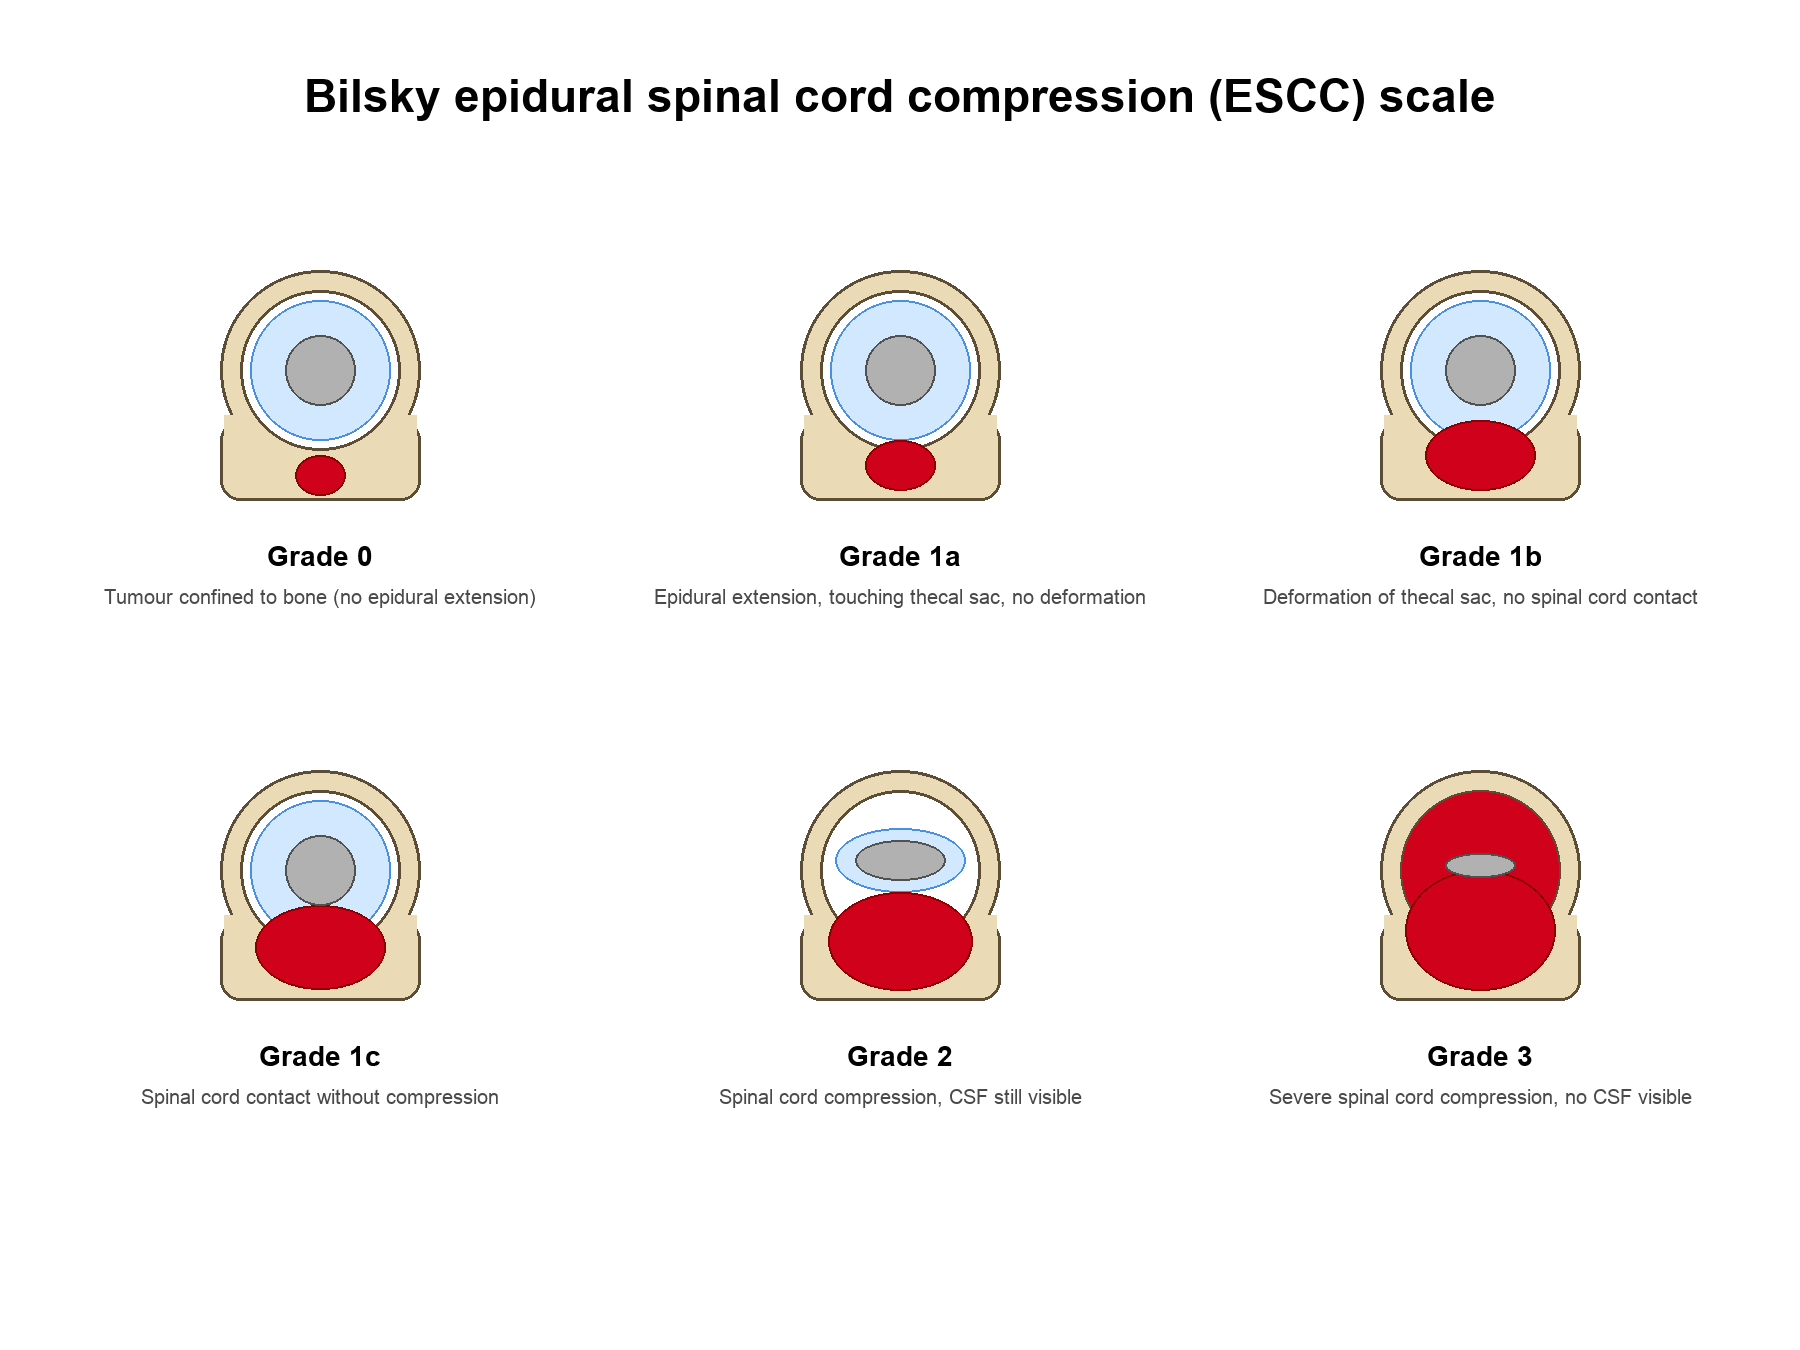
Bilsky 1c is the critical decision point. In radioresistant tumours (RCC, thyroid, melanoma), Bilsky 1c or higher requires surgical evaluation for separation surgery to enable safe delivery of SBRT.
NOMS Decision Framework
NOMS puts the four questions that decide treatment into one frame: Neurologic, Oncologic, Mechanical and Systemic. Each component independently influences the decision, and the answer comes from integrating all four rather than from any one of them.
What the tumour is doing to the cord. The Bilsky grade sets the stakes: grades 0-1b mean no significant neural compromise, while 1c-3 is progressive compression requiring intervention. Function is recorded alongside it as the Frankel/ASIA grade (A-E), ambulatory status and bladder and bowel function. Ambulatory status at presentation is the strongest predictor of outcome.
Time. The clock runs against the cord:
- Rapid progression under 48 hours = urgent decompression
- Motor deficit under 48 hours = best surgical outcomes
- Complete paralysis over 24-48 hours = poor recovery
Clinical Presentation
Pain. Four patterns, each pointing somewhere different:
- Mechanical pain, worse with movement, suggests instability (SINS +3)
- Biological pain is night pain, constant and progressive, from tumour burden
- Radicular pain in a dermatomal distribution points to nerve root compression
- Myelopathic symptoms: gait difficulty and coordination problems
Red flags for metastatic disease. Any of these in a patient with back pain should raise the question:
- Age over 50 with new back pain
- Known cancer history, even remote
- Unexplained weight loss, over 10% in 6 months
- Night pain unrelieved by position
- Progressive neurological symptoms
- Pain unresponsive to conservative treatment
Neurological examination is essential:
- Motor: myotomal testing, with the Frankel/ASIA grade recorded
- Sensory: dermatomal assessment and a sensory level
- Reflexes: hyperreflexia (upper motor neurone) versus hyporeflexia (lower motor neurone)
- Long tract signs: Hoffman's, Babinski, clonus
- Gait: ambulatory status
The spine itself is examined for tenderness over the involved levels, a palpable step-off or deformity, and paraspinal muscle spasm.
MESCC. Metastatic epidural spinal cord compression develops in 5-10% of cancer patients. Neurological deterioration can be rapid, over hours to days, and time to treatment is what determines the neurological outcome.
MESCC is an oncological emergency. Patients ambulatory at presentation have a 75-90% chance of remaining ambulatory with treatment. Non-ambulatory patients have only a 10-30% chance of regaining ambulation. Start steroids immediately, expedite imaging and surgical consultation.
Investigations
Laboratory studies. The essential tests:
- CBC, CMP, LFTs (baseline, nutritional status)
- Calcium (hypercalcaemia is common in bone metastases)
- Tumour markers (PSA, CEA, CA 19-9, AFP)
- SPEP/UPEP (exclude myeloma)
- HIV (if unknown primary)
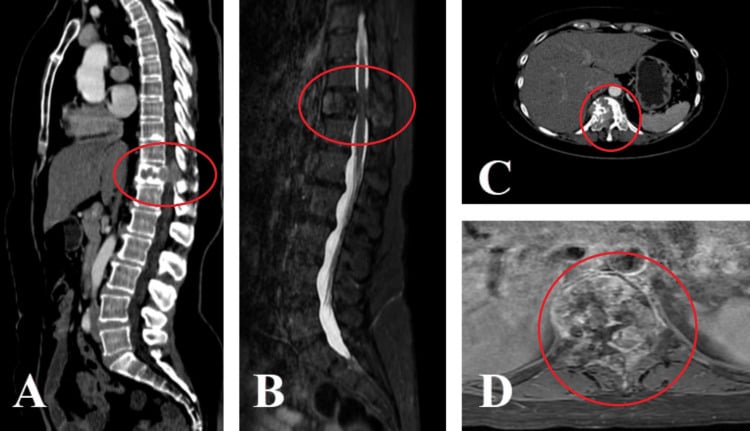
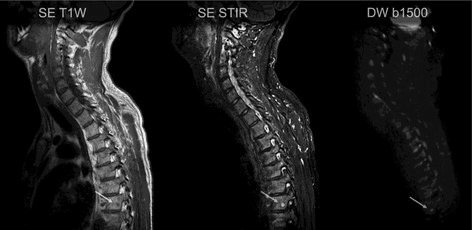
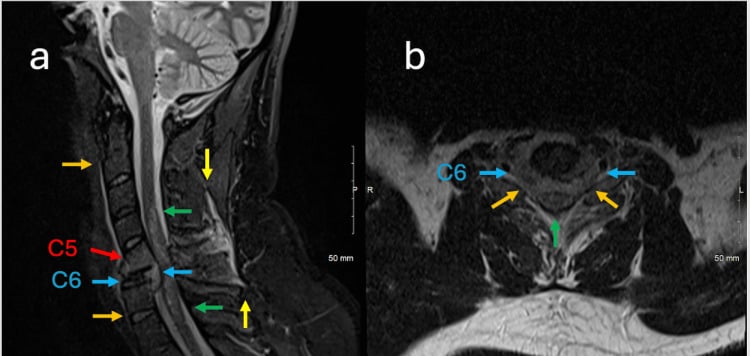
MRI is the gold standard, with a sensitivity of 98.5% and specificity of 98.9% for osseous metastases. The sequences are T1, T2, STIR and post-gadolinium, and the findings that make the diagnosis are:
- T1 hypointense (marrow replacement)
- T2 hyperintense (tumour/oedema)
- Gadolinium enhancement
- Epidural extension (Bilsky grading)
CT assesses the bone architecture and shows cortical destruction, guides the biopsy, and is the surgical planning study for pedicle trajectory.
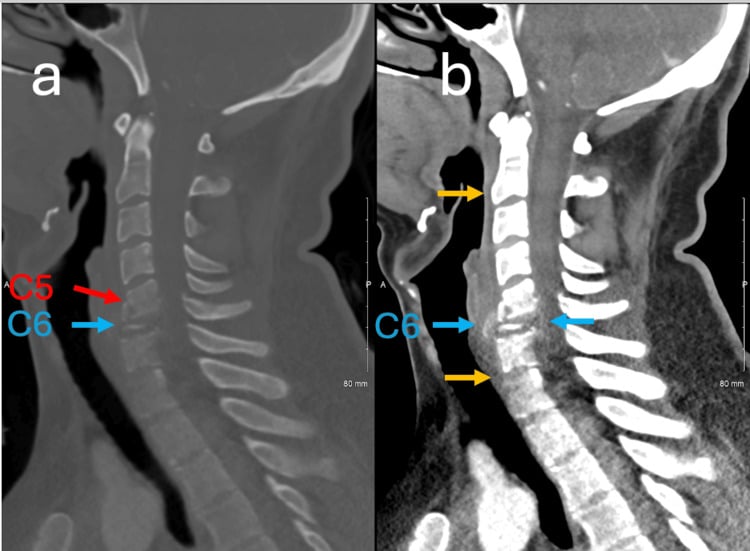
Plain radiographs have limited sensitivity, because 30-50% of the bone must be lost before a lesion shows. They still assess alignment, and standing views give the sagittal balance.
Nuclear medicine. Bone scan is sensitive but non-specific; PET-CT stages the disease and measures treatment response; SPECT improves localisation.
Biopsy is indicated when the tissue diagnosis is in doubt:
- Unknown primary
- Solitary lesion (exclude a primary tumour)
- Atypical imaging features
- No other accessible biopsy site
In a patient with no known primary or a solitary lesion, obtain a tissue diagnosis (CT-guided or open) before instrumented surgery or radiotherapy. Operating on or irradiating an undiagnosed lesion can compromise a primary bone tumour (e.g. plasmacytoma, lymphoma, chordoma) that would have a different, potentially curative treatment plan.
Differential diagnosis. A destructive or marrow-replacing vertebral lesion is not always a carcinoma metastasis. The key differentials and their discriminating features:
- Typical clue
- Known primary, age over 50, multiple levels
- Discriminating feature
- Multiplicity; pedicle ('winking owl') destruction; T1 marrow replacement
- Typical clue
- Diffuse lytic 'punched-out' lesions, anaemia, renal impairment
- Discriminating feature
- SPEP/UPEP and serum free light chains positive; bone scan often COLD
- Typical clue
- Bulky soft-tissue mass, relatively preserved bone outline
- Discriminating feature
- Encasing 'wrap-around' epidural mass; markedly radiosensitive/chemosensitive
- Typical clue
- Elderly, no destruction, fluid sign / preserved posterior cortex
- Discriminating feature
- Retropulsion without soft tissue mass; benign marrow on chemical-shift MRI
- Typical clue
- Fever, raised CRP, endplate and disc destruction
- Discriminating feature
- DISC involvement (spared by most tumours); paraspinal/psoas abscess in TB
- Typical clue
- Solitary, younger patient, characteristic location (sacrum/clivus for chordoma)
- Discriminating feature
- Biopsy mandatory before any intervention; en bloc resection may be curative
Metastases characteristically spare the intervertebral disc and may destroy a single pedicle (the 'winking owl' sign on AP radiograph), whereas infection crosses the disc space and destroys adjacent endplates. Myeloma is the classic lesion that is lytic on radiograph yet cold (negative) on technetium bone scan because it lacks osteoblastic reaction.
Management
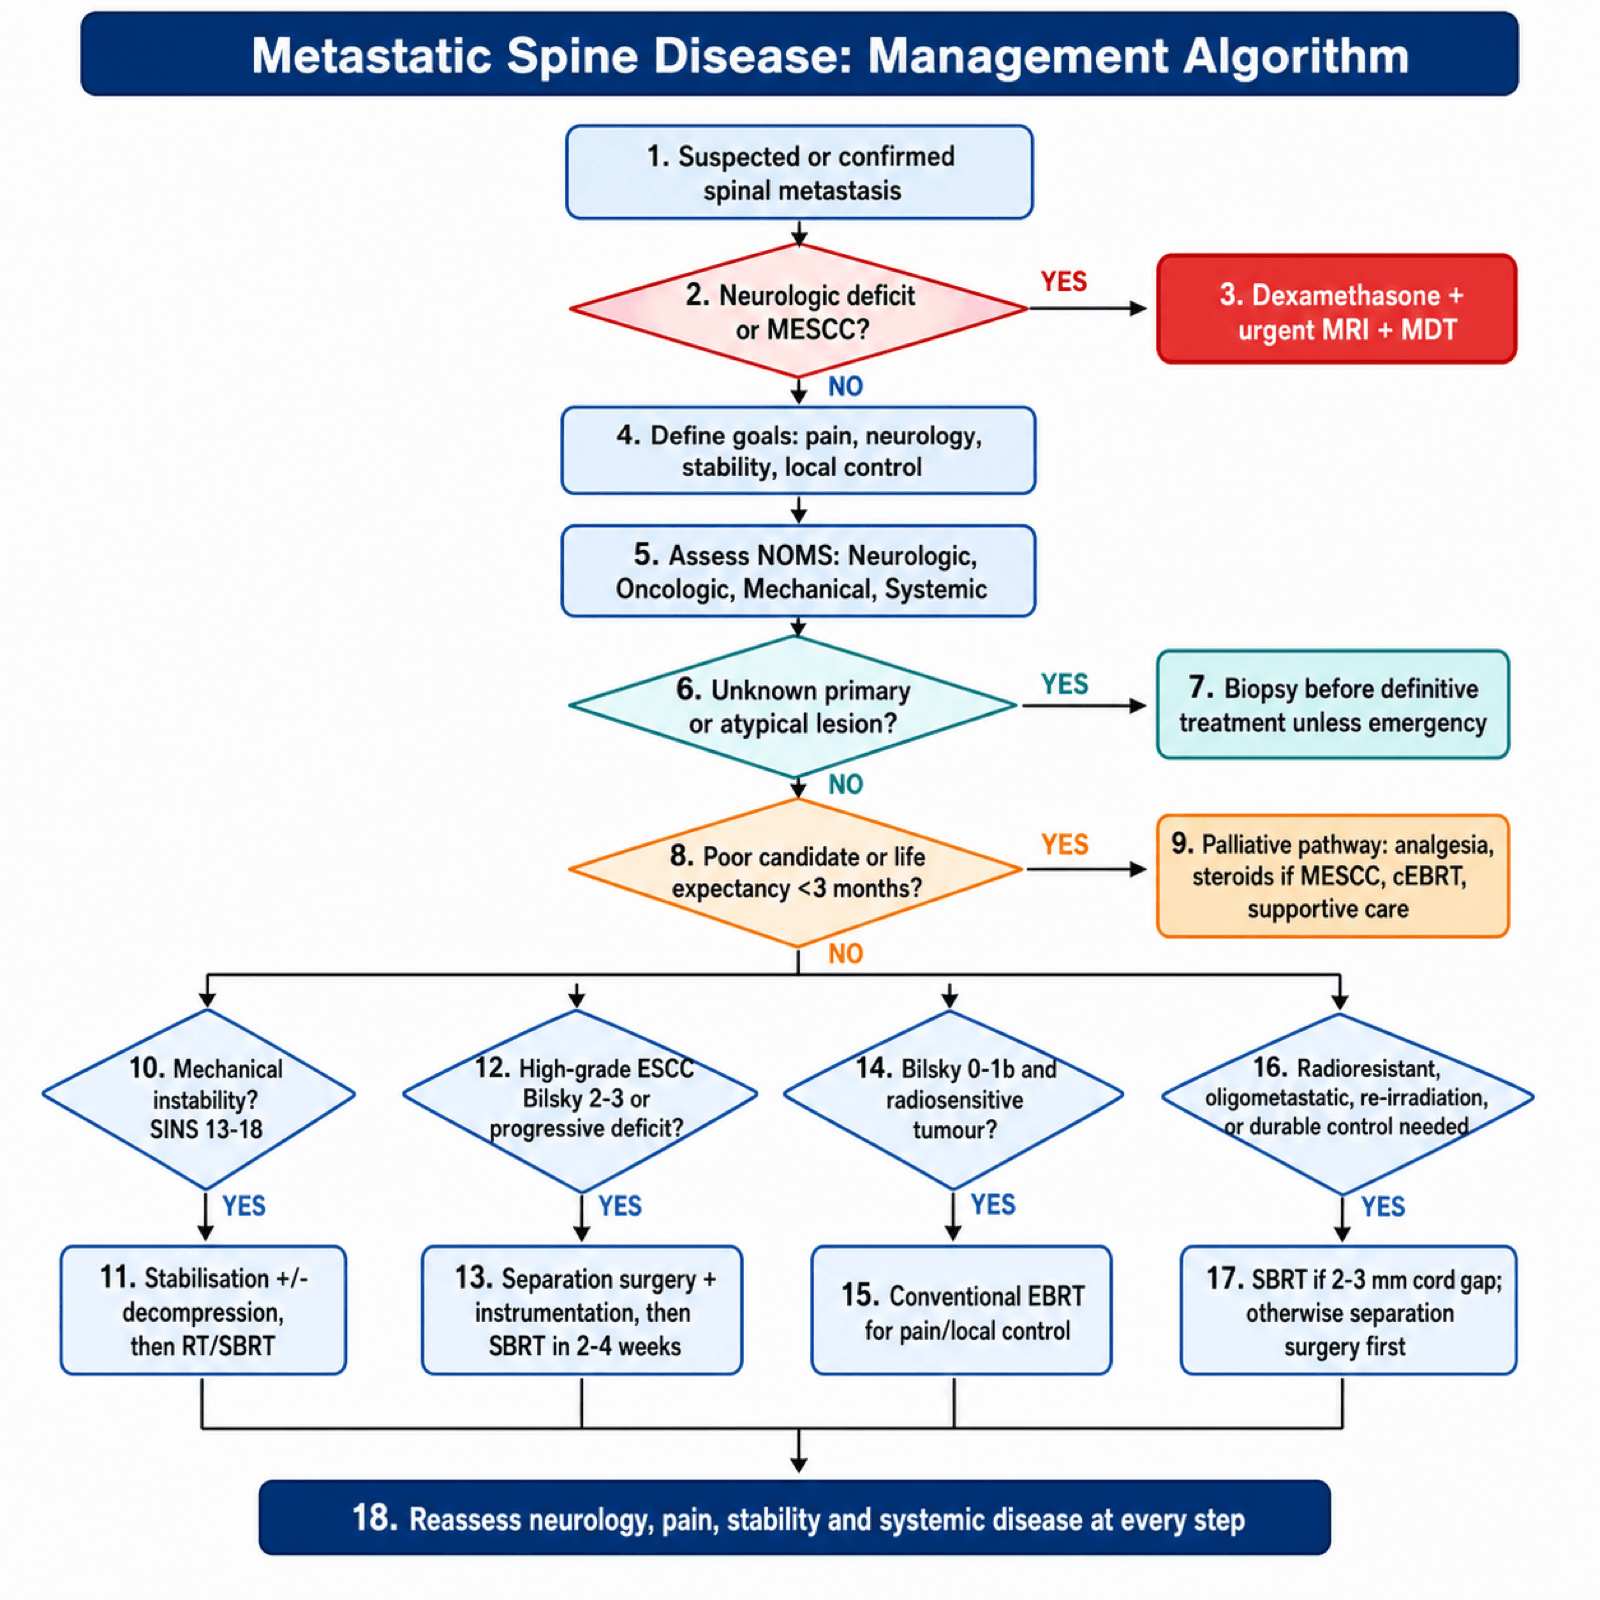
Corticosteroids
Dexamethasone for MESCC is started immediately at presentation:
- Indication
- Initial presentation
- Indication
- Maintenance until definitive Rx (NICE-recommended regimen)
- Indication
- Historical/selected rapid progression - largely abandoned due to higher toxicity without clear benefit
It works by reducing vasogenic oedema, with a possible tumoricidal effect on lymphoma. Co-prescribe gastric protection, monitor glucose, and taper once definitive treatment is established.
Bone-Modifying Agents
Every patient with solid-tumour bone metastases (and myeloma) should be considered for a bone-modifying agent to reduce skeletal-related events (SREs: pathological fracture, cord compression, need for radiotherapy or surgery to bone, and hypercalcaemia). Both classes require a dental review before starting and calcium plus vitamin D supplementation.
- Bisphosphonates (zoledronic acid) inhibit osteoclast-mediated resorption and reduce SREs across solid tumours and myeloma; they are renally cleared, so avoid or dose-reduce in renal impairment
- Denosumab, a monoclonal RANKL inhibitor given subcutaneously, is at least as effective as zoledronic acid for SRE reduction
Know the three complications examiners probe: osteonecrosis of the jaw (ONJ) - hence a dental check and good oral hygiene before starting; atypical (subtrochanteric) femoral fractures with prolonged use - ask about prodromal thigh pain; and hypocalcaemia - always replete calcium and vitamin D first. Denosumab is preferred in renal impairment (not renally cleared) but its effect is reversible, so abrupt cessation causes a rebound of bone turnover and a risk of multiple vertebral fractures - transition to a bisphosphonate if stopping.
Non-Operative Management
Non-operative management is the path when the mechanical and neurological axes are quiet, or when the systemic axis rules surgery out:
- SINS 0-6 (stable)
- Bilsky 0-1b with a radiosensitive tumour
- Poor surgical candidate or short life expectancy, by the systemic criteria above
External beam radiation (cEBRT) is effective for radiosensitive tumours and for pain palliation. Three regimens:
- 30 Gy in 10 fractions (standard)
- 20 Gy in 5 fractions (hypofractionated)
- 8 Gy single fraction (palliation)
What it achieves. Pain relief in 70-80%, motor improvement in 40-60%, and local control of 60-70% in radiosensitive tumours. Its limits are the dose constraint near the spinal cord and the radioresistant histologies, where 30-40% have failed locally at 1 year.
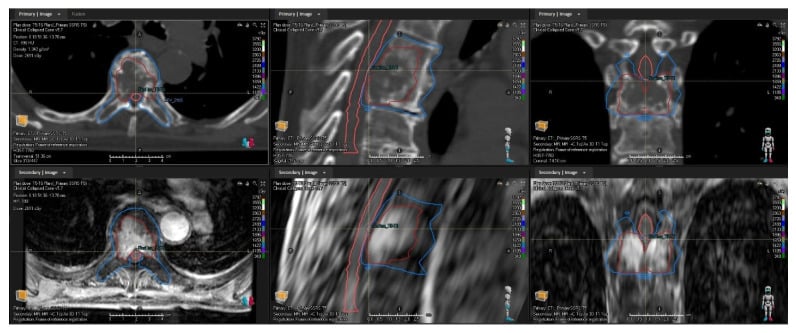
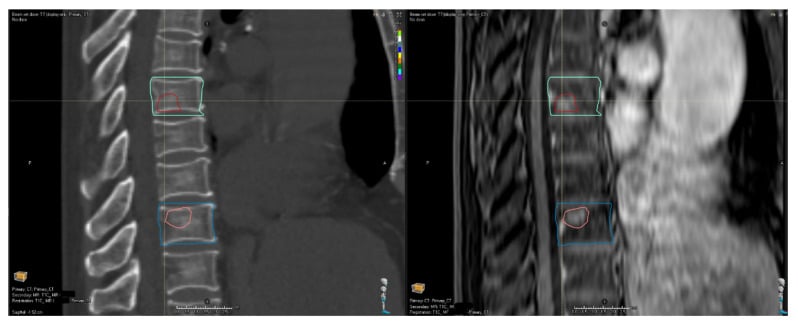
Two landmark RCTs frame the radiotherapy discussion. SCORAD (Hoskin, JAMA 2019) showed single 8 Gy is a reasonable convenient option versus 20 Gy in 5 fractions for MSCC (ambulatory benefit broadly similar; high early mortality). NRG/RTOG 0631 (Ryu, JAMA Oncol 2023) found that spine SRS did NOT improve patient-reported pain at 3 months over single-fraction 8 Gy cEBRT (41% vs 60%). The take-home: for simple pain palliation in radiosensitive disease, conventional EBRT suffices; reserve SRS/SBRT for radioresistant histology, oligometastatic disease, re-irradiation, or postoperative durable local control.
Surgical Management
Indications. Surgery is offered when one of six things is true:
- Mechanical instability (SINS 13-18)
- High-grade ESCC (Bilsky 2-3) with deficit
- Radioresistant tumour with Bilsky 1c or higher
- Progressive deficit despite radiation
- Pathological fracture with canal compromise
- Tissue diagnosis needed
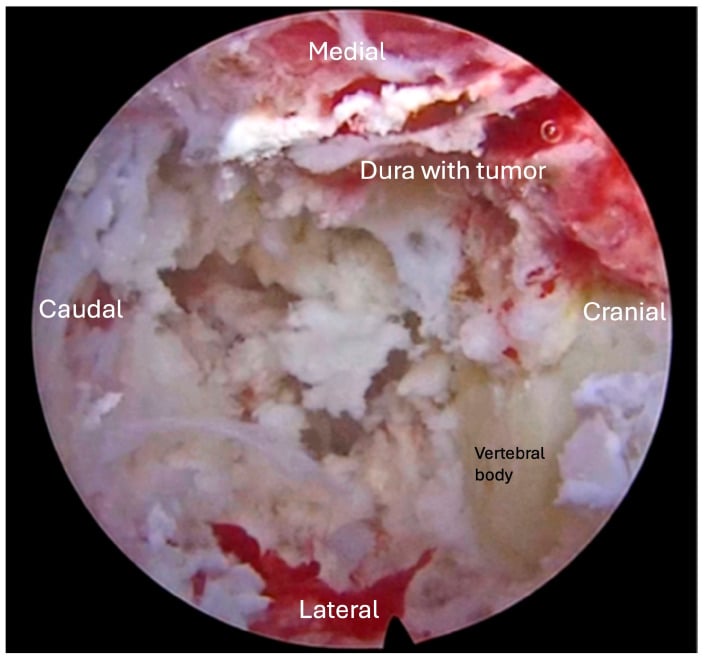
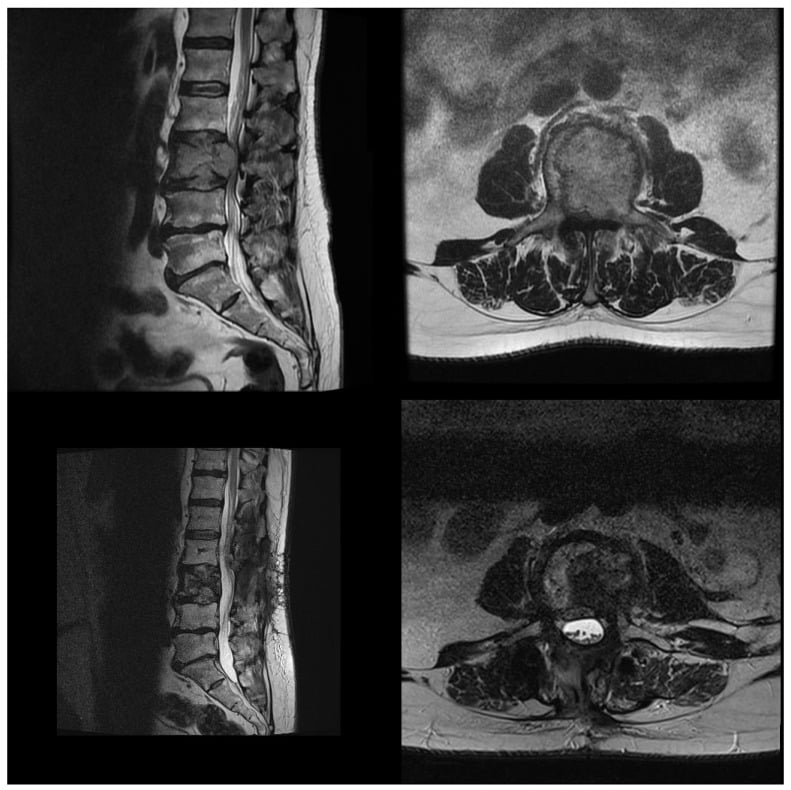
Separation surgery. The purpose is to create the 2-3mm gap around the cord that makes high-dose SBRT or SRS safe, not to remove the tumour: a posterior approach with instrumentation and circumferential decompression, not gross total or en bloc resection. Postoperative SBRT typically follows within 2-4 weeks. In the Laufer series 1-year local control was about 84% overall, rising to about 96% with high-dose hypofractionated SRS (24-30 Gy in 3 fractions).
Separation surgery (palliative decompression plus SBRT) is the default for most epidural metastases, but a small group warrants aggressive en bloc (total) spondylectomy with wide or marginal margins - the oncological resection more usually reserved for primary tumours. Consider it for the fit patient (good ECOG, long predicted survival, Tomita 2-3) with a solitary spinal metastasis, a controlled or absent primary, and no visceral metastases, especially from a biologically favourable, often radioresistant primary (renal cell, thyroid, or a solitary breast metastasis) where durable local control may change the disease course. The benefit (lower local recurrence, a possible survival advantage) is weighed against the high morbidity and major blood loss of total spondylectomy, so it remains the exception, justified only when prognosis is genuinely long. This is the answer to "what if she had a solitary metastasis with no visceral disease?" - shift from palliation toward oncological resection.
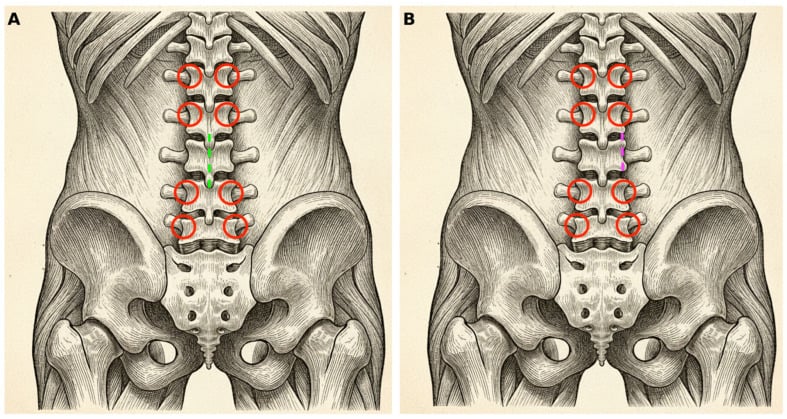
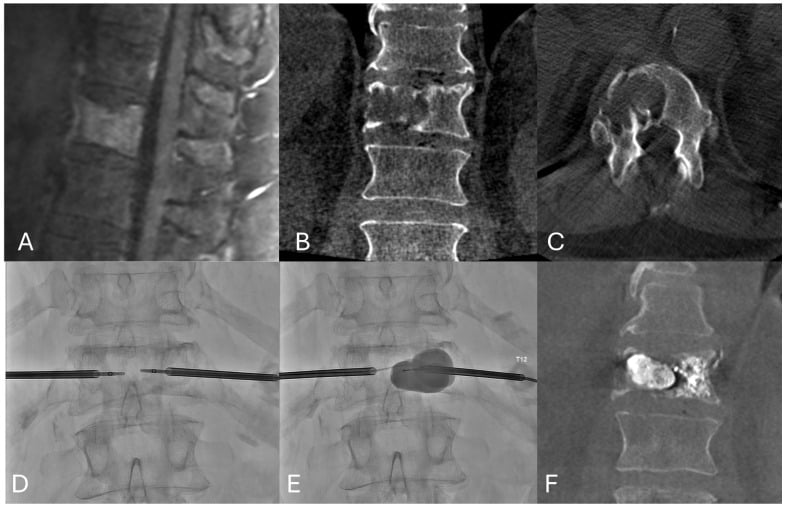
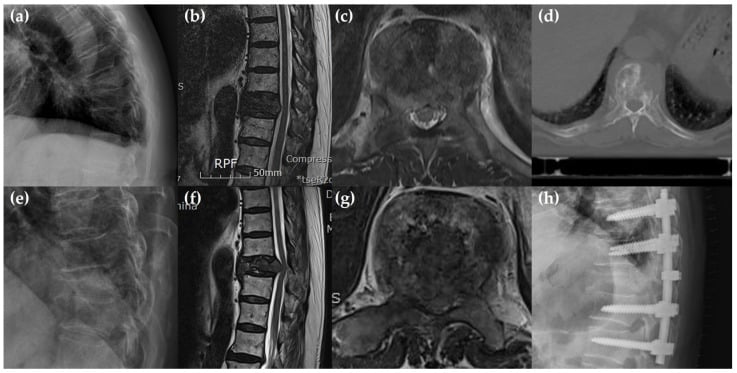
Approach. Posterior is the most common: extensile, and it takes pedicle screws. Anterior gives corpectomy and cervical plating. Minimally invasive options are percutaneous screws and vertebroplasty.
Instrumentation. Fix a minimum of 2 levels above and below the lesion, use cement augmentation in poor bone, and support the anterior column with an expandable cage.
Complications
Surgical complications run from the general to the spine-specific:
- Wound infection: 5-10%
- DVT/PE: 5-15%
- Medical complications: 10-20%
- 30-day mortality: 5-10%
- Hardware failure: 5-10%
- Adjacent level fracture: 5-15%
- Neurological deterioration: 2-5%
- CSF leak: 2-5%
Wounds are the particular problem after prior radiation, where the risk is higher and plastic surgery may be needed for closure.
Radiation. Acute effects are dermatitis, oesophagitis in the thoracic spine, nausea and fatigue. The late effects are radiation myelopathy, rare with modern techniques, and vertebral compression fracture in 10-15% after SBRT.
Local recurrence at 1 year is the number that separates the treatments:
- cEBRT alone (radioresistant): 30-40%
- SBRT: 5-15%
- Separation surgery + SBRT: about 16% overall, about 4% with high-dose hypofractionated SRS (the Laufer series)
Guidelines, Registries & Global Practice
Global Epidemiology
Spine is the most common site of skeletal metastasis worldwide, and the spine is involved in the majority of patients with bone metastases at autopsy. Roughly 10-30% of cancer patients develop clinically relevant spinal metastases during their disease, and around 5-10% develop metastatic epidural spinal cord compression (MESCC). As cancer survival improves globally with modern systemic therapy, the population living with spinal metastases is growing, increasing demand for spine oncology services. Across high-income health systems the dominant primaries are consistent: in the SCORAD cohort (UK and Australia) prostate (44%), lung (19%) and breast (12%) accounted for most MSCC, mirroring the BPLTK pattern (Hoskin, JAMA 2019, PMID 31794625).
Side-by-Side Guidance
- Core recommendation
- Treat suspected MSCC as an emergency; whole-spine MRI within 24h, dexamethasone 16 mg/day, definitive treatment within 24h of diagnosis; surgery for suitable patients then radiotherapy
- Evidence basis
- Underpinned by Patchell RCT (Level I)
- Core recommendation
- Integrate Neurologic (Bilsky), Oncologic (radiosensitivity), Mechanical (SINS), Systemic status to choose RT, SRS or separation surgery + SRS
- Evidence basis
- Expert synthesis (Barzilai, JCO 2017)
- Core recommendation
- Use SINS to trigger surgical consultation (score 7 or higher) and the Bilsky ESCC scale to grade compression
- Evidence basis
- Consensus + reliability data (Fisher 2010; Fourney 2011)
- Core recommendation
- Single-fraction 8 Gy cEBRT for simple pain palliation/short prognosis; reserve SBRT/SRS for radioresistant histology, oligometastases, re-irradiation or postoperative durable control
- Evidence basis
- SCORAD and RTOG 0631 (Level I)
- Core recommendation
- Zoledronic acid or denosumab to reduce skeletal-related events in solid-tumour bone metastases and myeloma, with dental review and calcium/vitamin D
- Evidence basis
- RCT evidence
Registry and Trial Evidence
There is no single dominant international spinal-metastasis registry equivalent to arthroplasty registries; the evidence base rests on landmark RCTs (Patchell 2005, SCORAD 2019, RTOG 0631 2023) plus large institutional cohorts (e.g. the Laufer separation-surgery series) and prospective prognostic-score validation (Tokuhashi, Tomita). The Global Spine Tumour Study Group and AO Spine Knowledge Forum Tumour have driven prospective multinational data collection on surgical outcomes, quality of life and prognostic modelling, increasingly favouring patient-reported outcomes over survival alone.
Practice Variation
Real-world practice varies with access to technology and multidisciplinary infrastructure. SBRT/SRS and separation surgery are concentrated in tertiary centres with image-guided radiotherapy and spinal navigation; in lower-resource settings conventional EBRT and posterior decompression-stabilisation remain the mainstay. Timeliness also varies: NICE-style emergency pathways with 24-hour MRI access are not universally available, and delayed diagnosis remains a major determinant of poorer ambulatory outcome globally.
MCQ Practice Points
Q: What is the SINS (Spinal Instability Neoplastic Score) threshold for surgical stabilization? A: SINS 7-12 is indeterminate (requires surgical consultation); SINS greater than 12 indicates instability requiring surgical stabilization. SINS assesses location, pain, lesion type, alignment, vertebral body collapse, and posterolateral element involvement.
Q: What are the components of the NOMS framework for metastatic spine treatment decisions? A: N = Neurologic status, O = Oncologic (tumor radiosensitivity and systemic disease burden), M = Mechanical instability (SINS), S = Systemic disease and medical comorbidities. This framework guides the choice between surgery, radiation, or conservative management.
Q: What is the Tomita scoring system used for? A: Predicting survival and guiding surgical extent in metastatic spine disease. Scores 2-3 favor wide/marginal excision, 4-5 favor marginal/intralesional surgery, 6-7 favor palliative surgery, and 8-10 suggest non-operative care. Factors include primary tumor type, visceral metastases, and bone metastases number.
Q: What is separation surgery in metastatic spine disease? A: Decompression and stabilization to create a 2-3mm gap between tumor and spinal cord, allowing safe delivery of high-dose stereotactic body radiotherapy (SBRT). It is not an oncologic resection but enables effective radiation while protecting neural structures.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 58-year-old man with metastatic prostate cancer has T8 vertebral body lesion with 30% collapse, no epidural extension, 4 weeks of mechanical back pain. No neurological symptoms.”
“The same patient returns 3 months later with 2 days of progressive leg weakness. Examination: 3/5 bilateral LE power, hyperreflexia, upgoing plantars. MRI shows T8 with Bilsky grade 2.”
“A 62-year-old woman with metastatic RCC has L2 lytic lesion, 60% collapse, kyphotic deformity, Bilsky 1c. Intact neurology. Calculate SINS and outline management.”
“A 75-year-old with ECOG 3, multiple visceral metastases from lung cancer, life expectancy 6-8 weeks. Severe mechanical back pain from L3 pathological fracture. SINS 10, Bilsky 0.”
SINS Score Components
- Location: Junctional=3, Mobile=2, Semi-rigid=1, Rigid=0
- Pain: Mechanical=3, Non-mechanical=1, None=0
- Bone: Lytic=2, Mixed=1, Blastic=0
- Alignment: Subluxation=4, Deformity=2, Normal=0
- VB Collapse: Over 50%=3, Under 50%=2, Over 50% involved=1, None=0
- Posterolateral: Bilateral=3, Unilateral=1, None=0
- INTERPRETATION: 0-6 stable, 7-12 consult, 13-18 unstable
Bilsky Grading
- Grade 0: Bone only
- Grade 1a: Epidural impingement
- Grade 1b: Thecal deformation, no cord contact
- Grade 1c: Cord contact (KEY THRESHOLD)
- Grade 2: Cord compression, CSF visible
- Grade 3: Circumferential compression, no CSF
- 1c or higher in radioresistant tumor = surgery
NOMS Framework
- N = Neurologic: Bilsky grade, deficit, ambulatory status
- O = Oncologic: Radiosensitivity determines RT approach
- M = Mechanical: SINS score guides stabilization
- S = Systemic: ECOG, life expectancy
- Radiosensitive: Lymphoma, myeloma, SCLC
- Radioresistant: RCC, thyroid, melanoma, sarcoma
Surgical Indications
- SINS 13-18 (unstable) - even without neurology
- Bilsky 2-3 with neurological deficit
- Bilsky 1c or higher in radioresistant tumor
- Progressive deficit despite radiation
- Pathological fracture with instability
Key Numbers
- Dexamethasone: 10mg bolus then 4mg q6h
- SBRT/SRS: 24 Gy single or 24-30 Gy/3# or 30-35 Gy/5#
- Pedicle screws: Minimum 2 levels above/below
- Patchell (Lancet 2005): Surgery+RT 84% ambulatory vs RT 57%
- RTOG 0631 (JAMA Oncol 2023): cEBRT 60.5% vs SRS 41.3% pain response - SRS not superior for pain
- Separation surgery + high-dose SRS: ~96% 1-year local control
Examiner Favorites
- Calculate SINS explicitly in viva
- MESCC = emergency - steroids first
- RCC and thyroid need embolization
- Separation surgery = decompression for SBRT
- Match treatment to life expectancy
Evidence Base
Patchell Trial - Direct Decompressive Surgery + RT vs RT Alone
- Multicentre RCT, 101 patients with MESCC (single compressive site); both arms received 30 Gy in 10 fractions
- Ambulatory after treatment: surgery + RT 84% (42/50) vs RT alone 57% (29/51); OR 6.2 (95% CI 2.0-19.8), p=0.001
- Retained ambulation longer: median 122 vs 13 days (p=0.003)
- Of those non-ambulatory at entry, 62% regained walking with surgery vs 19% with RT (p=0.01); reduced steroid and opioid need
- Excluded radiosensitive tumours (lymphoma, myeloma, germ cell) and total paraplegia over 48h
NRG/RTOG 0631 - Spine SRS vs Conventional EBRT for Pain
- Phase 3 RCT, 339 analysed; 1-3 vertebral metastases randomised 2:1 to SRS (single 16-18 Gy) vs cEBRT (single 8 Gy)
- Primary endpoint (patient-reported pain response at 3 months) FAVOURED cEBRT: 41.3% SRS vs 60.5% cEBRT (difference -19 points, 95% CI -32.9 to -5.5; 2-sided p=0.01)
- Superiority of SRS for pain was NOT demonstrated; no difference in acute/late toxicity
- Vertebral compression fracture at 24 months: 19.5% SRS vs 21.6% cEBRT (p=0.59); no spinal cord complications at 2 years
SINS - Development and Expert Consensus (Spine Oncology Study Group)
- Systematic review plus modified Delphi consensus from the Spine Oncology Study Group
- Six weighted components: location, pain, bone lesion quality, alignment, vertebral body collapse, posterolateral involvement (0-18)
- Categories: 0-6 stable, 7-12 potentially unstable, 13-18 unstable
- Designed to flag when patients warrant surgical consultation, not to mandate surgery
SINS - Reliability and Validity
- 30 spinal tumour cases scored twice by Spine Oncology Study Group members
- Total-score reliability near-perfect: ICC 0.846 (inter-observer) and 0.886 (intra-observer)
- Predictive validity vs consensus gold standard: kappa 0.712
- Sensitivity 95.7% and specificity 79.5% for detecting potentially unstable or unstable lesions
ESCC (Bilsky) Scale - Reliability Analysis
- Established the 6-point MRI-based epidural spinal cord compression scale (0, 1a, 1b, 1c, 2, 3) because the literature had no agreed definition of 'high-grade' compression despite using it as a surgical indication
- Seven Spine Oncology Study Group surgeons rated 25 cervical or thoracic tumours on three occasions at 2-week intervals
- Inter- and intrarater reliability ranged from GOOD TO EXCELLENT when graded on T2-WEIGHTED AXIAL images
- T2-weighted images were SUPERIOR to T1-weighted images both with and without gadolinium for assessing the degree of compression
Separation Surgery + Postoperative Stereotactic Radiosurgery
- Retrospective series of 186 patients with high-grade ESCC treated by decompression, instrumentation and postoperative SRS
- Overall cumulative local progression 16.4% at 1 year (i.e. ~84% local control)
- High-dose hypofractionated SRS (24-30 Gy in 3 fractions) gave 1-year local progression of only 4.1% vs 22.6% for low-dose hypofractionated SRS
- Local control was independent of tumour radiosensitivity, ESCC grade and extent of decompression
SCORAD - Single vs Multifraction RT for Spinal Cord Compression
- Noninferiority RCT in 42 UK and 5 Australian centres; 686 patients with MSCC and life expectancy over 8 weeks
- Single 8 Gy vs 20 Gy in 5 fractions; ambulatory grade 1-2 at week 8: 69.3% vs 72.7% (difference -3.5%)
- Noninferiority of single fraction at 8 weeks was NOT formally met (p=0.06) but the CI overlapped the margin; noninferiority was met at weeks 1, 4 and 12
- No survival difference (12-week survival 50% vs 55%); roughly half the cohort died before the 8-week assessment
NOMS Decision Framework
- Integrative framework synthesising evidence across Neurologic, Oncologic, Mechanical and Systemic domains
- Incorporates spinal SRS, allowing ablative dose delivery and a shift toward less aggressive, often minimally invasive surgery
- Couples Bilsky ESCC grade with tumour radiosensitivity to choose RT alone, SRS or separation surgery + SRS
- Emphasises multidisciplinary decision-making rather than a fixed algorithm
Tomita Prognostic Score and Surgical Strategy
- Prognostic score (2-10) from three factors: grade of malignancy, visceral metastases, and number of bone metastases
- Score 2-3 wide/marginal excision; 4-5 marginal/intralesional; 6-7 palliative surgery; 8-10 supportive care
- Mean survival: 38.2 months after wide/marginal excision vs 5.3 months with terminal care in the original cohort
- Lower Tomita score indicates a better prognosis (opposite direction to Tokuhashi)
Revised Tokuhashi Prognostic Score
- Six parameters, each 0-5, total 0-15 (general condition, extraspinal mets, vertebrae involved, visceral mets, primary site, neurology)
- Score 0-8 predicts under 6 months (conservative/palliative); 12-15 predicts 1 year or more (excision justified)
- Prospective consistency between predicted and actual survival 86.4% (n=118)
- Higher Tokuhashi score indicates a better prognosis (opposite direction to Tomita)
References
- Fisher CG, DiPaola CP, Ryken TC, et al. A novel classification system for spinal instability in neoplastic disease: an evidence-based approach and expert consensus from the Spine Oncology Study Group. Spine (Phila Pa 1976). 2010;35(22):E1221-9. PMID 20562730. doi:10.1097/BRS.0b013e3181e16ae2
- Fourney DR, Frangou EM, Ryken TC, et al. Spinal instability neoplastic score: an analysis of reliability and validity from the Spine Oncology Study Group. J Clin Oncol. 2011;29(22):3072-7. PMID 21709187. doi:10.1200/JCO.2010.34.3897
- Bilsky MH, Laufer I, Fourney DR, et al. Reliability analysis of the epidural spinal cord compression scale. J Neurosurg Spine. 2010;13(3):324-8. PMID 20809724. doi:10.3171/2010.3.SPINE09459
- Patchell RA, Tibbs PA, Regine WF, et al. Direct decompressive surgical resection in the treatment of spinal cord compression caused by metastatic cancer: a randomised trial. Lancet. 2005;366(9486):643-8. PMID 16112300. doi:10.1016/S0140-6736(05)66954-1
- Laufer I, Iorgulescu JB, Chapman T, et al. Local disease control for spinal metastases following "separation surgery" and adjuvant hypofractionated or high-dose single-fraction stereotactic radiosurgery. J Neurosurg Spine. 2013;18(3):207-14. PMID 23339593. doi:10.3171/2012.11.SPINE12111
- Ryu S, Deshmukh S, Timmerman RD, et al. Stereotactic radiosurgery vs conventional radiotherapy for localized vertebral metastases of the spine: phase 3 results of NRG Oncology/RTOG 0631 randomized clinical trial. JAMA Oncol. 2023;9(6):800-7. PMID 37079324. doi:10.1001/jamaoncol.2023.0356
- Hoskin PJ, Hopkins K, Misra V, et al. Effect of single-fraction vs multifraction radiotherapy on ambulatory status among patients with spinal canal compression from metastatic cancer: the SCORAD randomized clinical trial. JAMA. 2019;322(21):2084-94. PMID 31794625. doi:10.1001/jama.2019.17913
- Barzilai O, Laufer I, Yamada Y, et al. Integrating evidence-based medicine for treatment of spinal metastases into a decision framework: neurologic, oncologic, mechanical stability, and systemic disease. J Clin Oncol. 2017;35(21):2419-27. PMID 28640703. doi:10.1200/JCO.2017.72.7362
- Tomita K, Kawahara N, Kobayashi T, et al. Surgical strategy for spinal metastases. Spine (Phila Pa 1976). 2001;26(3):298-306. PMID 11224867. doi:10.1097/00007632-200102010-00016
- Tokuhashi Y, Matsuzaki H, Oda H, et al. A revised scoring system for preoperative evaluation of metastatic spine tumor prognosis. Spine (Phila Pa 1976). 2005;30(19):2186-91. PMID 16205345. doi:10.1097/01.brs.0000180401.06919.a5