Opioid-Sparing | Multiple Drug Classes | Superior Outcomes
- Synergistic effect of multiple analgesics acting at different pain pathways
- Opioid-sparing reduces side effects: PONV, ileus, respiratory depression, sedation
- Preemptive analgesia given before incision reduces central sensitisation
- Regional anaesthesia is cornerstone for major orthopaedic procedures
- Acetaminophen and NSAIDs are foundation - scheduled, not PRN dosing
- “Multimodal means targeting multiple pain pathways, not just multiple drugs
- “WHO ladder is outdated - modern approach uses concurrent non-opioid agents
- “Gabapentinoids effective for neuropathic pain but sedation limits use
- “IV acetaminophen no better than oral - save money, use oral when possible
Overview
Definition. Multimodal analgesia, also called balanced analgesia, is the concurrent use of several analgesic agents with different mechanisms of action, so that different points on the pain pathway are targeted at once. The aim is better pain relief with fewer side effects than any single agent gives, and in particular less opioid consumption and fewer opioid-related adverse events.
How we got here. The WHO analgesic ladder of the 1980s escalated step-wise from non-opioids to strong opioids. The 1990s brought recognition of opioid side effects and the multimodal concept; the 2000s brought ERAS (Enhanced Recovery After Surgery) protocols that built multimodal analgesia in; the opioid crisis of the 2010s drove the emphasis on opioid-sparing techniques; and the 2020s have brought standardised multimodal protocols, the expansion of regional anaesthesia and personalised pain medicine.
The traditional WHO analgesic ladder suggests sequential escalation (paracetamol, then weak opioid, then strong opioid). Modern multimodal analgesia uses concurrent administration of multiple non-opioid agents, reserving opioids for breakthrough pain only.
Why it works. Drugs acting at different sites produce an additive or synergistic effect, greater than the sum of their individual effects, and because each contributes, each can be given at a lower dose, which minimises its dose-dependent toxicity. Together they cover the nociceptive, inflammatory and neuropathic components of pain, and given preemptively they reduce the wind-up of central sensitisation.
What opioid-sparing buys. A 30-50 percent reduction in opioid consumption is achievable, and with it fall the opioid side effects: PONV (a 40 percent reduction), sedation, respiratory depression, ileus and addiction risk. Bowel function returns faster, patients mobilise earlier and hospital stay is shorter.
How it is run. Non-opioids are given scheduled, around the clock, rather than PRN, because regular dosing is more effective. Doses are weight-based and adjusted for renal and hepatic function, pain is scored frequently and the regimen adjusted, and the plan runs on past the acute phase: transition to oral agents, opioid weaning and continued physiotherapy.
Pathophysiology
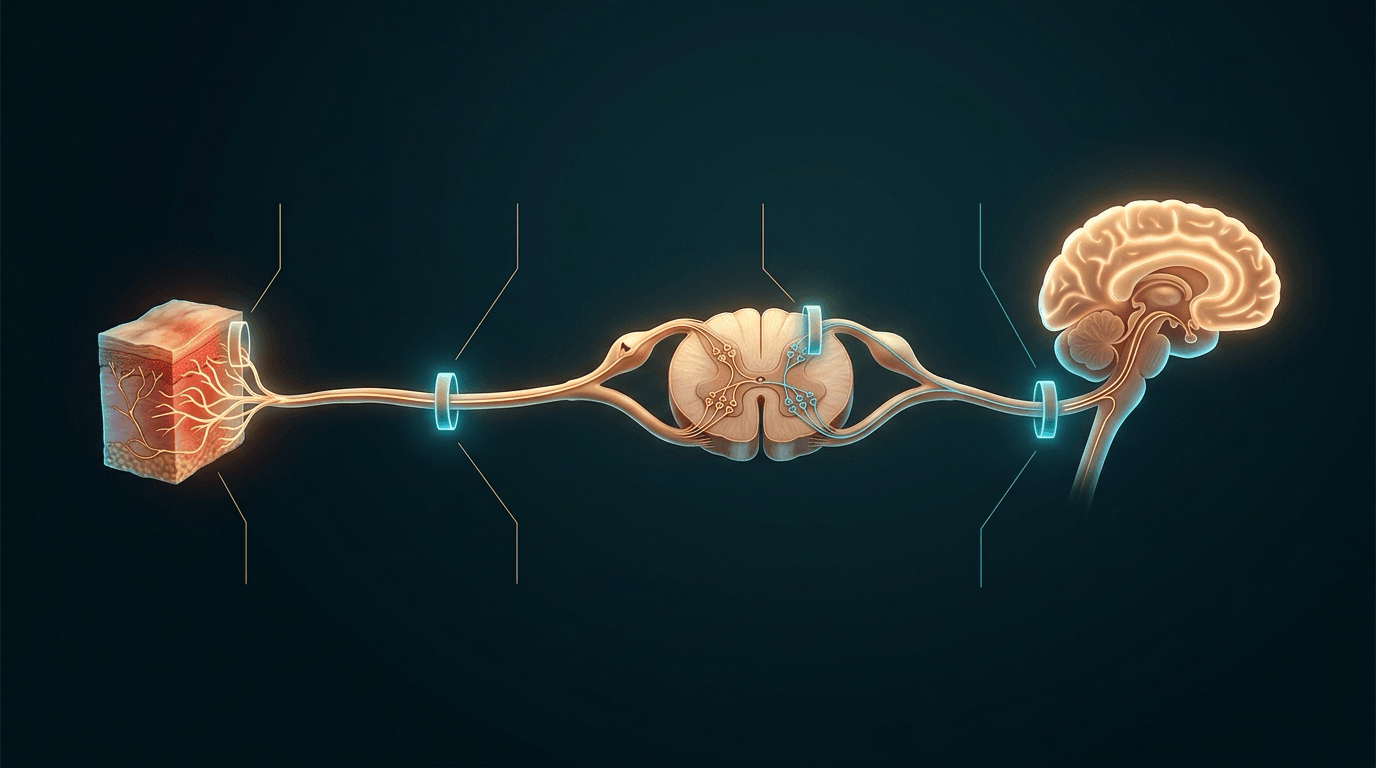
The pain pathway. Pain reaches consciousness in four steps, and each step is a target:
- Transduction (peripheral) - a noxious stimulus is converted to an electrical signal at nociceptors
- Transmission (peripheral and spinal) - the signal is conducted along A-delta and C fibres to the dorsal horn
- Modulation (spinal) - the signal is amplified or suppressed at dorsal horn synapses
- Perception (supraspinal) - conscious awareness of pain in the thalamus and cortex
Peripheral targets. Transduction and transmission are where NSAIDs act, reducing prostaglandin synthesis and so nociceptor sensitisation; where local anaesthetics block sodium channels and stop the action potential propagating; where opioids reduce nociceptor excitability through peripheral mu receptors; and where corticosteroids reduce the release of inflammatory mediators.
Central targets. Modulation and perception are where paracetamol acts, through central COX inhibition and serotonergic pathways; where gabapentinoids reduce excitatory neurotransmitter release in the dorsal horn; where ketamine's NMDA antagonism prevents central sensitisation; where opioids activate spinal and supraspinal mu receptors; and where alpha-2 agonists enhance the descending inhibitory pathways.
Central sensitisation (wind-up). Repeated C-fibre stimulation progressively amplifies the responses of dorsal horn neurons: glutamate activates NMDA receptors and excitability rises. The result is hyperalgesia, increased pain to noxious stimuli, and allodynia, pain from non-noxious stimuli, and it persists beyond tissue healing, contributing to chronic pain.
Preventing it. The strategies are preemptive analgesia, meaning analgesics given before the surgical incision; NMDA antagonism with low-dose ketamine during surgery; gabapentinoids, which reduce glutamate release; and adequate regional anaesthesia, because complete afferent blockade prevents sensitisation.
Preemptive means given before incision. Preventive means given before incision and continued postoperatively. Evidence suggests preventive (extended duration) is more effective than a single preoperative dose: the point is to prevent central sensitisation throughout the entire nociceptive period.
Chronic (persistent) postsurgical pain (CPSP) is the downstream consequence of the sensitisation described above. It is pain persisting beyond the expected healing period, conventionally more than 3 months after surgery, not explained by another cause, and often carrying a neuropathic component. It is common: after total knee arthroplasty roughly 10-20 percent of patients report persistent pain.
The predictable risk factors are severe, poorly controlled acute postoperative pain; pre-operative pain and pre-operative opioid use; psychological factors (catastrophising, anxiety, depression); nerve injury during surgery; and female sex or younger age in some series.
The strongest preventive levers are excellent acute pain control and regional anaesthesia that blunt central sensitisation, plus addressing psychological risk; low-dose ketamine may reduce it in high-risk or high-pain surgery. Note the negative: gabapentinoids do not prevent CPSP (the large meta-analysis found no effect), so do not justify them on this basis. The transitional pain service identifies high-risk patients pre-operatively and follows them across the acute-to-chronic transition, optimising non-opioid analgesia and opioid weaning rather than escalating opioids.
Drug Classes and Mechanisms
Paracetamol (Acetaminophen)
Mechanism. Paracetamol inhibits COX centrally, reducing prostaglandin synthesis in the CNS, and activates serotonergic pathways that enhance descending pain inhibition. Indirect activation of CB1 receptors through the cannabinoid system, and nitric-oxide-mediated signalling, are possible further contributions.
Dosing. The adult dose is 1g PO or IV every 6 hours, to a maximum of 4g per day. In the elderly or those under 50kg it is 500-750mg every 6 hours, and in hepatic impairment the dose is reduced or the interval extended.
Evidence. A single 1g dose has an NNT of 4-5 for 50 percent pain relief, and paracetamol reduces morphine consumption by 20-30 percent. Combined with an NSAID the effect is additive and superior to either drug alone.
IV paracetamol costs 10-20 times more than oral with no proven superiority in analgesia when the oral route is available. Reserve IV for patients who are NBM, have GI dysfunction, or require immediate effect, and switch to oral as soon as feasible.
Contraindications and cautions. Severe hepatic impairment (Child-Pugh C) is a contraindication. In chronic alcohol use the maximum daily dose falls to 2-3g, and glutathione depletion states, such as malnutrition, HIV and chronic illness, are the other cautions.
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)
Mechanism. NSAIDs inhibit the COX enzymes and so prostaglandin synthesis. COX-1 is constitutive and serves gastric protection, platelet function and renal blood flow; COX-2 is inducible and drives inflammation, pain and fever. The effect is both peripheral and central, reducing inflammatory sensitisation.
- COX Selectivity
- Non-selective
- Dosing
- 400mg every 6-8 hours (max 2.4g/day)
- Key Advantage
- Short half-life, rapid onset, low cost
- COX Selectivity
- Preferential COX-2
- Dosing
- 50mg every 8 hours or 75mg every 12 hours
- Key Advantage
- Potent analgesia, good toleration
- COX Selectivity
- Selective COX-2
- Dosing
- 200mg twice daily or 400mg preop
- Key Advantage
- Reduced GI bleeding risk, no platelet effect
- COX Selectivity
- Highly selective COX-2
- Dosing
- 90-120mg daily
- Key Advantage
- Once-daily dosing, potent
- COX Selectivity
- Non-selective (IV)
- Dosing
- 10-30mg every 6 hours (max 5 days)
- Key Advantage
- IV/IM option for NBM patients
Evidence. NSAIDs reduce morphine consumption by 30-40 percent, and the combination with paracetamol is synergistic. COX-2 selective and non-selective agents give similar analgesia; the selective agents cause less GI bleeding but carry increased cardiovascular risk at high doses.
Contraindications. The list mixes absolute and relative:
- Active peptic ulcer disease - absolute contraindication for non-selective NSAIDs
- Severe renal impairment (eGFR less than 30 mL/min) - avoid or use cautiously
- History of GI bleeding - use a COX-2 selective agent with a PPI
- Cardiovascular disease - avoid high-dose COX-2 inhibitors
- Bleeding risk - non-selective NSAIDs impair platelet function; avoid perioperatively if this is a concern
- Third trimester pregnancy - risk of premature closure of the ductus arteriosus
- Aspirin-sensitive asthma - cross-reactivity possible
The concern is that NSAIDs may impair fracture healing and spinal fusion. Animal studies show delayed healing; human studies are conflicting, and short-term use (less than 2 weeks) appears safe. The current consensus is to avoid NSAIDs in high-risk fractures (scaphoid, femoral neck stress fracture) and spinal fusions, and that they are safe for short-term use in routine arthroplasty and stable fractures.
Gabapentinoids
The drugs. Gabapentin requires dose escalation and three-times-daily dosing. Pregabalin has higher bioavailability, twice-daily dosing and a faster onset.
Mechanism. Both bind the alpha-2-delta subunit of voltage-gated calcium channels in the dorsal horn, reducing calcium influx into presynaptic terminals and so the release of excitatory neurotransmitters, glutamate and substance P, which prevents central sensitisation.
Dosing. Gabapentin is given as a single 600-1200mg dose 1-2 hours before surgery, then 300mg three times daily postoperatively, titrated to 300-600mg three times daily. Pregabalin is 150-300mg 1-2 hours before surgery, then 75mg twice daily, titrated to 150mg twice daily. Both are renally cleared, and the dose is reduced if CrCl is less than 60 mL/min.
Evidence, and the retreat from routine use. A meta-analysis of 281 RCTs and 24,682 patients found the reduction in pain intensity below the minimally important difference at every timepoint, no effect on chronic postsurgical pain, and more dizziness and visual disturbance. Routine perioperative use is therefore no longer supported by high-quality evidence, and the historical "25-30 percent opioid-sparing" claim has not held up in pooled data. Reserve gabapentinoids for a genuine neuropathic component (nerve injury, amputation, some spine surgery), decided case by case.
Side effects. Sedation is the dose-limiting one:
- Sedation (20-30 percent) - dose-limiting, avoid in the elderly
- Dizziness (15-20 percent)
- Visual disturbances (blurred vision)
- Peripheral oedema
- Cognitive impairment (especially the elderly or cognitively impaired)
Best for a neuropathic pain component (spine surgery, limb amputation, nerve injury). Avoid in elderly patients, pre-existing cognitive impairment, and patients requiring high alertness postoperatively. Where sedation is a concern, use lower doses (gabapentin 300mg twice daily) or omit.
Cautions. Combined with opioids, gabapentinoids cause synergistic respiratory depression, the key safety signal, especially in the elderly or those with sleep-disordered breathing. They may worsen the muscle weakness of myasthenia gravis.
Ketamine
Mechanism. Ketamine is an NMDA receptor antagonist: it prevents glutamate-mediated excitation and so central sensitisation and wind-up. It also interacts with opioid receptors, which may reverse opioid-induced hyperalgesia, and it modulates cytokine release, an anti-inflammatory effect.
Low-dose (sub-anaesthetic) dosing. The protocols are:
- Intraoperative infusion: 0.1-0.5 mg/kg/hr (typically 0.2 mg/kg/hr)
- Bolus: 0.1-0.25 mg/kg IV at induction
- Postoperative infusion: 0.05-0.2 mg/kg/hr for 24-48 hours
Evidence. Ketamine reduces morphine consumption by 15-30 percent, and is most effective in opioid-tolerant patients and in procedures with high pain intensity. There is a possible benefit in preventing chronic postsurgical pain.
Side effects. The psychomimetic effects, dysphoria, hallucinations and nightmares, are dose-dependent. Nausea is less common than with opioids; hypertension and tachycardia reflect its sympathomimetic action; and respiratory depression is minimal at low doses.
Contraindications. Ketamine is avoided in:
- Psychotic disorders - may precipitate psychosis
- Uncontrolled hypertension - sympathomimetic effects
- Raised intracranial pressure - increases cerebral blood flow and ICP
- Ischaemic heart disease - caution, because myocardial oxygen demand rises
Psychomimetic effects occur at doses greater than 1 mg/kg; analgesia occurs at much lower doses. Always use low-dose protocols for postoperative analgesia, and consider a benzodiazepine (midazolam 1-2mg) if emergence phenomena occur.
Local Anaesthetics
Mechanism. Local anaesthetics block sodium channels, preventing the generation and propagation of action potentials, a reversible block of nerve conduction. The blockade is differential: smaller fibres, carrying pain and autonomic traffic, are blocked before motor fibres.
- Onset
- Fast (5-10 min)
- Duration
- Short (60-120 min)
- Maximum Dose
- 4.5 mg/kg plain, 7 mg/kg with adrenaline
- Onset
- Slow (15-20 min)
- Duration
- Long (4-8 hours)
- Maximum Dose
- 2 mg/kg plain, 3 mg/kg with adrenaline
- Onset
- Moderate (10-15 min)
- Duration
- Long (4-8 hours)
- Maximum Dose
- 3 mg/kg
- Onset
- Slow (15-20 min)
- Duration
- Long (4-8 hours)
- Maximum Dose
- 2.5 mg/kg
Applications. Local anaesthetics reach the multimodal regimen as peripheral nerve blocks (femoral, sciatic, interscalene, adductor canal, TAP block), neuraxial techniques (spinal and epidural analgesia), local infiltration (wound infiltration, intra-articular injection) and continuous catheters (peripheral nerve catheters, wound catheters). Allergy and local infection at the injection site are the contraindications.
Toxicity. CNS toxicity presents as tinnitus, a metallic taste, perioral numbness and seizures; cardiovascular toxicity as arrhythmias and cardiac arrest, and bupivacaine is the most cardiotoxic of the agents.
Prevent it by aspirating before injection, dosing incrementally and staying below the maximum dose. Recognise it early: CNS symptoms (tinnitus, seizures) precede cardiovascular collapse. Treat by stopping the injection, calling for help, managing the airway and seizures, and giving Intralipid 20 percent 1.5 mL/kg as a bolus (repeated if needed) followed by an infusion; start CPR if arrest occurs.
Regional Anaesthesia Integration
Why regional. Regional anaesthesia is the gold standard for major procedures: peripheral nerve blocks (femoral, sciatic, interscalene) or neuraxial techniques (epidural, spinal) provide superior analgesia to systemic opioids. Whether a single shot or a continuous catheter is used depends on the surgery and the expected duration of pain.
Peripheral Nerve Blocks
Femoral block. Indicated for TKA, femoral shaft fracture and anterior thigh procedures, it gives excellent quadriceps analgesia at the price of quadriceps weakness and fall risk. The motor-sparing alternative is the adductor canal block.
Adductor canal block. Indicated for TKA and ACL reconstruction, it preserves quadriceps strength, so fall risk is lower, and covers the medial knee and distal femur. Its analgesia is non-inferior to the femoral block for TKA, and it is now the preferred block for total knee arthroplasty.
Sciatic block. Indicated for ankle and foot surgery, the posterior pain of TKA and below-knee amputation, by the popliteal (distal), subgluteal or anterior approach. It covers the posterior knee and the entire lower leg and foot, lasts 12-24 hours as a single shot and 48-72 hours with a catheter, and is essential for complete analgesia in lower limb procedures.
Interscalene block. The block for shoulder surgery, arthroplasty and rotator cuff repair, covering the shoulder and proximal humerus. Its complications are phrenic nerve palsy, which occurs in 100 percent, and Horner syndrome.
Supraclavicular block. The block for elbow, forearm and hand surgery, where the brachial plexus anatomy is compact. The risk is pneumothorax, less than 1 percent with ultrasound.
Neuraxial Analgesia
Epidural indications. Epidural analgesia is indicated for:
- Major spine surgery (multi-level fusion)
- Lower limb surgery with expected severe pain (revision arthroplasty)
- Bilateral lower limb procedures
Technique. The catheter is placed thoracic (T8-L1) or lumbar (L2-L4) depending on the surgical level, and runs bupivacaine 0.125-0.25 percent plus fentanyl 2-4 mcg/mL at 4-10 mL/hr for 48-72 hours postoperatively.
The trade. In its favour: analgesia superior to systemic opioids, bilateral coverage, a 60-80 percent reduction in opioid use, and easier mobilisation and physiotherapy. Against it: hypotension from sympathetic blockade, managed with fluids and vasopressors; motor blockade that delays mobilisation if the concentration is too high; urinary retention, so a catheter is required; and the rare complications of epidural haematoma (1 in 10,000), abscess and permanent neurological injury.
The high-risk scenarios are traumatic placement, anticoagulation (therapeutic or prophylactic), coagulopathy and spinal abnormalities. Stop LMWH 12 hours before a neuraxial procedure and restart it 6-8 hours after catheter removal; check motor and sensory function every 2-4 hours, and remove the catheter before restarting therapeutic anticoagulation.
Alpha-2 agonists (clonidine, dexmedetomidine) act on the descending inhibitory alpha-2 pathways. Given systemically, as a dexmedetomidine infusion, they are opioid-sparing and antiemetic but cause bradycardia, hypotension and sedation.
As perineural adjuvants they prolong single-shot blocks: perineural dexamethasone and perineural dexmedetomidine each meaningfully extend block and analgesia duration, often by several hours, directly reducing the rebound-pain gap. IV dexamethasone also prolongs blocks and is the safer route where perineural use is off-label. Buprenorphine and adrenaline are the other recognised additives, adrenaline both prolonging the block and serving as an intravascular marker.
The strategic point is that there are two ways to defeat single-shot rebound: a continuous catheter, the gold standard for prolonged severe pain, or a prolonging adjuvant plus scheduled oral analgesia started pre-emptively, before the block regresses. Never wait for the patient to wake in agony.
Procedure-Specific Protocols
The arthroplasty protocols. Both share one skeleton: oral non-opioids before surgery, a spinal or a peripheral block plus local infiltration and IV dexamethasone during it, then scheduled non-opioids with PRN oxycodone afterwards. They differ in intensity, because THA is generally less painful than TKA.
- Total Knee Arthroplasty (TKA)
- Gabapentin 600mg, paracetamol 1g and celecoxib 400mg, all given 1-2 hours before surgery
- Total Hip Arthroplasty (THA)
- Gabapentin 600mg, paracetamol 1g and celecoxib 200mg
- Total Knee Arthroplasty (TKA)
- Spinal anaesthesia with intrathecal morphine 100-200 mcg OR adductor canal block; local infiltration analgesia (LIA) with 100 mL ropivacaine 0.2 percent periarticular injection; dexamethasone 8mg IV
- Total Hip Arthroplasty (THA)
- Spinal anaesthesia with intrathecal morphine 100 mcg OR lumbar plexus block or fascia iliaca block; local infiltration around the acetabulum and femoral canal; dexamethasone 4-8mg IV
- Total Knee Arthroplasty (TKA)
- Paracetamol 1g every 6 hours; celecoxib 200mg twice daily (or ibuprofen 400mg three times daily); gabapentin 300mg three times daily; oxycodone 5-10mg PO every 4 hours PRN (goal less than 30mg per 24 hours); early mobilisation day 0-1
- Total Hip Arthroplasty (THA)
- Paracetamol 1g every 6 hours; ibuprofen 400mg every 8 hours; oxycodone 5mg PO every 6 hours PRN (goal less than 20mg per 24 hours); mobilisation day 0
- Total Knee Arthroplasty (TKA)
- Pain scores 3-4 out of 10 at rest, 5-6 with physiotherapy; opioid consumption 20-40 mg oral morphine equivalents in the first 24 hours; mobilisation day 0-1; discharge day 1-2
- Total Hip Arthroplasty (THA)
- Pain scores 2-3 out of 10; minimal opioid requirement (10-20 mg oral morphine equivalents); mobilisation day 0; discharge day 1
A note on the gabapentin. It appears in both protocols as the historical preemptive agent. On the pooled evidence set out under Gabapentinoids, routine use is no longer supported, so it is reserved for a genuine neuropathic component rather than given to every arthroplasty patient.
Differential of the Patient With Uncontrolled Postoperative Pain
Severe pain despite a multimodal regimen is itself a clinical problem with a differential. Do not simply escalate opioids: work through the causes, because several require a specific intervention rather than more analgesia.
- Clues / How to Recognise
- Sudden severe pain as a single-shot block regresses (often 12-24h); dermatomal return of sensation
- Specific Action
- Anticipate with scheduled non-opioids and oral opioid before regression; consider catheter or repeat block
- Clues / How to Recognise
- Pain out of proportion, pain on passive stretch, increasing analgesic demand, tense compartment
- Specific Action
- Surgical emergency - remove dressings, do NOT mask with dense block, urgent compartment pressures and fasciotomy
- Clues / How to Recognise
- New, escalating or localised pain different in character; systemic signs; abnormal wound or imaging
- Specific Action
- Clinical review and imaging; treat the cause rather than uptitrating analgesia
- Clues / How to Recognise
- Known chronic opioid use; diffuse worsening pain despite rising opioid doses
- Specific Action
- Add ketamine, optimise non-opioid and regional components, involve acute pain service
- Clues / How to Recognise
- Burning, shooting, allodynia in a nerve distribution; nerve handled or stretched intra-operatively
- Specific Action
- Trial a gabapentinoid in selected cases, consider lidocaine, escalate to chronic pain team if persistent
- Clues / How to Recognise
- PRN-only prescribing, missed scheduled paracetamol/NSAID, no regional plan
- Specific Action
- Convert to scheduled non-opioids, add regional/LIA, reassess with a validated pain score
- Clues / How to Recognise
- High distress, disproportionate behavioural response, unrealistic pain expectation
- Specific Action
- Reassurance, education, realistic goal-setting; psychological input if persistent
Guidelines, Registries & Global Practice
Global Burden and Why It Matters
Inadequately controlled acute postoperative pain remains common worldwide and is consistently associated with delayed mobilisation, higher complication rates, prolonged stay and an increased risk of persistent postsurgical pain. Major joint arthroplasty volumes are rising globally with ageing populations, so the perioperative analgesic strategy is a high-frequency, high-impact clinical decision in every health system. The shared global driver of the last decade has been opioid stewardship: reducing both inpatient and post-discharge opioid exposure while maintaining function-enabling analgesia. Multimodal, opioid-sparing analgesia embedded within enhanced-recovery pathways is the converged international answer.
Major Guidance, Side by Side
Recommendations from the leading bodies are broadly concordant - paracetamol plus an NSAID/COX-2 backbone, regional or local-infiltration techniques, and opioids reserved as rescue. The main areas of genuine divergence are the role of gabapentinoids and the choice between intrathecal morphine and peripheral techniques.
- Core Recommendation
- For TKA: scheduled paracetamol + NSAID/COX-2, single-shot adductor canal block + periarticular LIA, single IV dexamethasone; opioids as rescue
- Notable Position / Evidence Level
- Procedure-specific systematic-review methodology (Level I synthesis); intrathecal morphine only when block and LIA impossible
- Core Recommendation
- Opioid-sparing multimodal analgesia as one integral element of a wider enhanced-recovery pathway with education and early mobilisation
- Notable Position / Evidence Level
- Multidisciplinary consensus across 17 topics; no single surgical technique independently expedites discharge
- Core Recommendation
- Multimodal regimens to minimise opioid use; preoperative counselling and limits on post-discharge opioid quantity
- Notable Position / Evidence Level
- Strong emphasis on reducing the opioid prescription that seeds long-term use
- Core Recommendation
- Perioperative multimodal analgesia and joint-replacement enhanced recovery; cautions on routine gabapentinoid use and on opioid initiation
- Notable Position / Evidence Level
- UK gabapentinoids reclassified as controlled drugs, reflecting misuse and respiratory-depression concern
- Core Recommendation
- Multimodal analgesia first-line; validated pain assessment (NRS/VAS); realistic expectation-setting and opioid minimisation
- Notable Position / Evidence Level
- Comprehensive graded evidence document used internationally as an acute-pain reference
Convergent Points of International Consensus
- Paracetamol + NSAID/COX-2 is the non-opioid backbone - scheduled, not PRN, unless contraindicated (Ong meta-analysis supports the combination).
- Regional and local-infiltration techniques are central for major joint and limb surgery (adductor canal block + LIA for TKA per PROSPECT).
- Opioids are rescue analgesics, with deliberate limits on post-discharge quantity to reduce persistent use.
- A single intra-operative dose of dexamethasone improves analgesia and reduces PONV and is now widely recommended for arthroplasty.
Genuine Areas of Practice Variation
- Gabapentinoids: historically routine, now discouraged for unselected patients after large meta-analytic data (Verret) showed sub-threshold benefit and real harms; several systems have reclassified them as controlled drugs. Reserve for a clear neuropathic component.
- Intrathecal morphine vs peripheral block/LIA: some centres still use low-dose intrathecal morphine for arthroplasty; PROSPECT positions it as a fall-back when block and LIA are not feasible, partly because of pruritus, urinary retention and delayed respiratory depression.
- Resource setting: in limited-resource environments where ultrasound and catheter services are scarce, reliance shifts toward scheduled oral non-opioids, surgeon-delivered LIA and judicious opioids; ultrasound-guided regional services and acute pain teams are concentrated in higher-resource centres.
Registry and System-Level Evidence
Although multimodal analgesia is not itself tracked by joint registries, the major arthroplasty registries (NJR for England and Wales, AJRR in the USA, AOANJRR in Australia, the Swedish and Norwegian registries, and the New Zealand Joint Registry) document the rise of same-day and short-stay arthroplasty that opioid-sparing multimodal pathways have enabled. Real-time prescription-monitoring systems in several jurisdictions now track perioperative and post-discharge opioid prescribing, reflecting the global shift toward measurable opioid stewardship.
Relevance Across Examinations
Multimodal analgesia is high-yield for every major orthopaedic board. Examiners reliably probe: the rationale for opioid-sparing, the non-opioid backbone, procedure-specific regional choices (adductor canal block vs femoral block, interscalene for shoulder), the NSAID-and-bone-healing controversy, the modern retreat from routine gabapentinoids, and recognition of the patient whose pain signals a complication rather than under-dosing.
MCQ Practice Points
Q: What is the primary mechanism of analgesia achieved by preoperative paracetamol administration?
A: Central COX-2 inhibition in the spinal cord and descending serotonergic pathways. Paracetamol is NOT peripherally anti-inflammatory but provides central analgesia by inhibiting prostaglandin synthesis in the CNS. Maximum dose 4g/day (reduce to 3g/day if liver disease or weight under 50kg). Can be given IV or oral with equal efficacy.
Q: Which injectable COX-2 selective NSAID is used perioperatively and what are its key contraindications?
A: Parecoxib 40mg IV (the prodrug of valdecoxib) is a parenteral COX-2 selective inhibitor useful when the oral route is unavailable. Key contraindications: sulfonamide allergy, established cardiovascular disease (raised MI and stroke risk - the reason rofecoxib was withdrawn), renal impairment (GFR under 60), active GI ulceration, and aspirin-sensitive asthma. Use caution with anticoagulation. The bone-healing concern remains low-quality and largely animal-derived; short-term use (under 14 days) appears acceptable in most cases.
Q: What is the opioid-sparing effect of a well-designed multimodal analgesia protocol?
A: 30-50% reduction in opioid consumption. A typical ERAS multimodal protocol includes: preoperative paracetamol 1g + gabapentin 300mg, intraoperative local infiltration analgesia (LIA), postoperative regular paracetamol + NSAID + low-dose opioid PRN. The synergistic effect of targeting multiple pain pathways reduces opioid requirements and associated complications (nausea, constipation, respiratory depression).
Q: What is the mechanism of gabapentin in multimodal analgesia and what is the optimal dosing strategy?
A: Gabapentin inhibits alpha-2-delta voltage-gated calcium channels, reducing central sensitization and hyperalgesia. For perioperative use: single preoperative dose of 300-600mg given 1-2 hours before surgery. Reduces acute postoperative pain scores and opioid requirements by approximately 30%. Avoid high doses (over 600mg) due to sedation, especially in elderly. Contraindicated in renal impairment.
Q: What are the key components of local infiltration analgesia (LIA) used in total knee arthroplasty?
A: Typical LIA cocktail contains ropivacaine 200mg (or bupivacaine 100mg) + ketorolac 30mg + adrenaline 0.3mg in saline 100-150mL. Injected into the posterior capsule, collateral ligaments, quadriceps, and subcutaneous tissues before closure. Provides 12-24 hours analgesia. Adductor canal block provides additional analgesia while preserving quadriceps strength for early mobilization (preferred over femoral nerve block).
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are planning anesthesia for a 68-year-old woman undergoing primary total knee arthroplasty. She has well-controlled hypertension and takes aspirin for cardiovascular prophylaxis. Describe your multimodal analgesia plan.”
“A 45-year-old man with chronic low back pain on long-term opioids (oxycodone 40mg twice daily) requires lumbar spinal fusion L4-S1. How would you manage his perioperative analgesia?”
“The orthopaedic surgeon asks you not to use NSAIDs in a patient undergoing open reduction and internal fixation of a scaphoid nonunion as he is concerned about fracture healing. What is your response?”
Definition and Principles
- Multimodal equals concurrent use of multiple analgesics with different mechanisms targeting different pain pathways
- Goal: superior analgesia with reduced opioid consumption and fewer side effects
- Synergy - additive or synergistic effect greater than sum of individual agents
- Opioid-sparing achieves 30-50 percent reduction in opioid use with improved outcomes
Core Drug Classes (Foundation)
- Acetaminophen 1g every 6 hours - central COX inhibition, foundation of all protocols
- NSAIDs - celecoxib 200mg twice daily or ibuprofen 400mg three times daily
- Gabapentinoids - gabapentin 300-600mg three times daily or pregabalin 75-150mg twice daily
- Regional anesthesia - peripheral nerve blocks or neuraxial (gold standard)
- Opioids - rescue therapy only, NOT primary analgesic
Preemptive Analgesia
- Give BEFORE surgical incision to prevent central sensitization (wind-up)
- Gabapentin 600-1200mg given 1-2 hours preoperatively
- Acetaminophen 1g and celecoxib 200-400mg preoperatively
- Mechanism - prevents NMDA receptor activation and dorsal horn sensitization
Regional Anesthesia Options
- TKA - adductor canal block (motor-sparing) or spinal plus intrathecal morphine
- THA - spinal plus intrathecal morphine or fascia iliaca block
- Shoulder - interscalene block (gold standard, but 100 percent phrenic palsy)
- Spine fusion - ketamine infusion plus local infiltration
- Single-shot vs catheter - single shot lasts 12-24h, catheter for 48-72h
Adjuvant Agents
- Ketamine 0.1-0.5 mg/kg/hr intraoperatively - NMDA antagonist
- Dexamethasone 4-8mg IV - anti-inflammatory, antiemetic
- Local infiltration - surgeon performs periarticular injection
- Lidocaine infusion - emerging evidence for 1 mg/kg/hr for 24h
Opioid-Sparing Benefits
- PONV reduced by 40 percent
- Ileus - faster return of bowel function (6-12 hours earlier)
- Sedation reduced by 30 percent
- Respiratory depression reduced by 50 percent
- Length of stay reduced by 0.5-1 day
NSAID Controversy
- Animal studies - NSAIDs delay fracture healing (high doses, prolonged use)
- Human studies - conflicting, short-term use (less than 2 weeks) appears safe
- Avoid in - scaphoid fractures, femoral neck stress fractures, spinal fusions
- Safe in - arthroplasty, routine stable fractures (5-7 days duration)
Special Populations
- Elderly - reduce doses by 25-50 percent, avoid gabapentinoids
- Opioid-tolerant - continue baseline opioid, add ketamine, expect 50-100 percent higher needs
- Renal impairment - avoid NSAIDs if eGFR less than 30, reduce gabapentin dose
- Chronic pain - high-dose gabapentinoids, ketamine, early pain team involvement
TKA Protocol (Example)
- Preop - gabapentin 600mg, acetaminophen 1g, celecoxib 400mg
- Intraop - adductor canal block plus LIA plus dexamethasone 8mg IV
- Postop - acetaminophen 1g every 6 hours plus celecoxib 200mg twice daily
- Breakthrough - oxycodone 5-10mg every 4 hours PRN (goal less than 30mg in 24 hours)
High-Yield Numbers
- Opioid reduction - 30-50 percent achievable with multimodal approach
- PONV reduction - 40 percent compared to opioid-based analgesia
- Acetaminophen max dose - 4g per day (reduce to 2-3g in liver disease)
- Gabapentin preoperative - 600-1200mg
- Ketamine low dose - 0.1-0.5 mg/kg/hr
- Intrathecal morphine - 100-200 mcg for lower limb surgery
Evidence Base
Kehlet & Dahl: The Concept of Balanced (Multimodal) Analgesia
- Defining paper that introduced the concept of balanced (multimodal) analgesia into clinical practice
- Proposed combining analgesics with different mechanisms (local anaesthetics, NSAIDs, opioids, alpha-2 agonists) to obtain additive or synergistic relief
- Argued that combination therapy allows lower doses of each agent and therefore fewer dose-dependent side effects
- Set the rationale for opioid-sparing perioperative regimens that underpins modern ERAS pathways
PROSPECT Recommendations for Pain Management After TKA
- Analysed 151 systematic reviews and 106 RCTs that met PROSPECT inclusion criteria
- Recommends basal paracetamol plus an NSAID or COX-2-specific inhibitor as the foundation
- Recommends a single-shot adductor canal block plus periarticular local infiltration analgesia together with a single intra-operative dose of IV dexamethasone
- Intrathecal morphine 100 mcg considered only when both adductor canal block and LIA are impossible; opioids reserved as rescue analgesics
Paracetamol Combined With an NSAID Improves Analgesia
- Systematic review of 21 RCTs enrolling 1909 patients across acute pain models
- The paracetamol plus NSAID combination was superior to paracetamol alone in 85 percent of relevant studies and superior to NSAID alone in 64 percent
- Pain intensity and rescue analgesic use were reduced by roughly 35 percent versus paracetamol alone
- Supports paracetamol plus NSAID as the routine non-opioid backbone of multimodal regimens
Perioperative Gabapentinoids: Limited Clinical Benefit
- Very large meta-analysis of 281 RCTs with 24,682 participants
- Reduction in pain intensity was below the minimally important difference at every timepoint (for example 7 of 100 points lower at 24 hours)
- No effect on subacute or chronic postsurgical pain prevention
- Gabapentinoids increased dizziness and visual disturbance, with only a small reduction in PONV
Perioperative IV Ketamine for Acute Postoperative Pain (Cochrane)
- Cochrane review of 130 RCTs with 8341 participants
- Reduced 24-hour opioid consumption by about 8 mg morphine equivalents (roughly 19 percent) and 48-hour consumption by about 13 mg
- Reduced pain at rest and on movement and prolonged time to first analgesic request by around 54 minutes
- Reduced PONV and reduced the area of postoperative hyperalgesia, with no clinically important excess of CNS adverse events at sub-anaesthetic doses
Local Infiltration Analgesia (LIA): The Originating Series
- Described the LIA technique (ropivacaine, ketorolac and adrenaline infiltrated systematically around the surgical field) in 325 hip and knee arthroplasty patients
- Two-thirds of patients required no morphine for postoperative pain control
- Most patients mobilised with assistance 5-6 hours after surgery and achieved independent mobility within 13-22 hours
- 71 percent were discharged directly home after a single overnight stay
Adductor Canal vs Femoral Nerve Block for TKA
- Meta-analysis comparing adductor canal block with femoral nerve block for TKA
- Adductor canal block provides comparable (non-inferior) analgesia
- Quadriceps strength is better preserved with the adductor canal block, supporting safer early mobilisation
- No clinically important difference in pain scores or opioid consumption between the two blocks
NSAIDs and Bone Healing: The Evidence Is Weak
- Clinical studies reporting that NSAIDs impair bone healing had significantly lower methodological (Coleman) scores than studies finding them safe
- Reviews recommending NSAID avoidance cited far fewer clinical studies than reviews concluding NSAIDs were safe
- No consensus exists on NSAID safety after orthopaedic procedures; the strongest concern derives from animal data
- Withholding NSAIDs has no proven benefit and may increase opioid requirements
ERAS Society Consensus for Hip and Knee Replacement
- Multidisciplinary consensus across 17 perioperative topic areas for hip and knee replacement
- Best practice combines preoperative education, optimised anaesthetic and transfusion strategy, an opioid-sparing multimodal analgesic approach and early mobilisation
- Insufficient evidence that any single surgical technique independently expedites discharge
- Frames multimodal opioid-sparing analgesia as an integral component of enhanced recovery, not a stand-alone intervention